AMYVID images should be interpreted only by readers who successfully complete the training program provided by the manufacturer.
Perform image interpretation independently of the patient's clinical features, relying on the recognition of unique image features.
Interpret AMYVID images based upon the distribution of signal intensity within the cerebral cortex by comparing the signal intensity in the cortical gray matter and the adjacent white matter. The signal intensity in the cerebellum does not contribute to the scan interpretation. For example, a positive scan may show retained cerebellar gray-white contrast even when the cortical gray-white contrast is lost.
Some scans may be difficult to interpret due to image noise, atrophy with a thinned cortical ribbon, or image blur. For cases where there is uncertainty as to the location of cortical signal, use co-registered anatomical imaging to improve localization of signal [see Warnings and Precautions (5.1)].
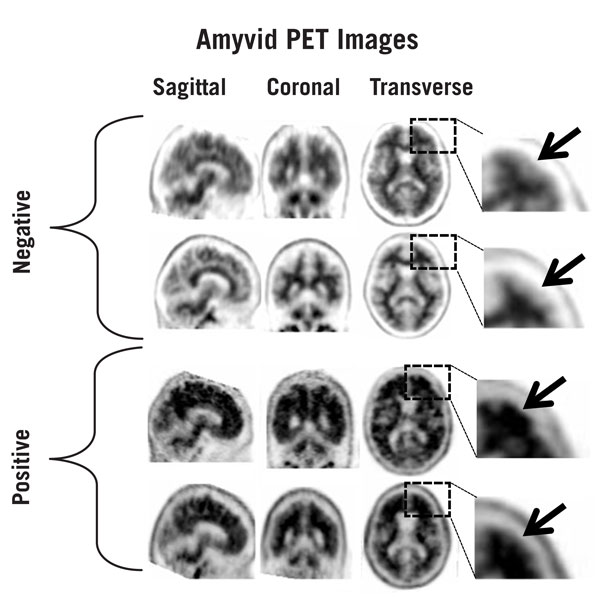
Negative scans show more signal in white matter than in adjacent cortical gray matter, creating clear gray-white contrast.
A negative scan indicates sparse to no amyloid beta neuritic plaques. In patients being evaluated for AD and other causes of cognitive decline who have not been treated with amyloid beta-directed therapy, a negative scan is inconsistent with a neuropathological diagnosis of AD at the time of image acquisition and reduces the likelihood that a patient's cognitive impairment is due to AD. A negative scan result does not preclude the accumulation of amyloid beta in the brain in the future.
Positive scans show cortical areas with reduction or loss of the normally distinct gray-white contrast. These scans will have one or more areas with increased cortical gray matter signal which results in reduced (or absent) gray-white contrast. Specifically, a positive scan will have either:
- a)
Two or more brain areas (each larger than a single cortical gyrus) in which there is reduced or absent gray-white contrast. This is the most common appearance of a positive scan.
or - b)
One or more areas in which cortical gray matter signal is intense and clearly exceeds the signal in adjacent white matter.
A positive scan establishes the presence of moderate to frequent amyloid beta neuritic plaques. Neuropathological examination has shown that moderate to frequent amyloid beta neuritic plaques are present in patients with AD, but may also be present in patients with other types of neurologic conditions as well as older people with normal cognition.
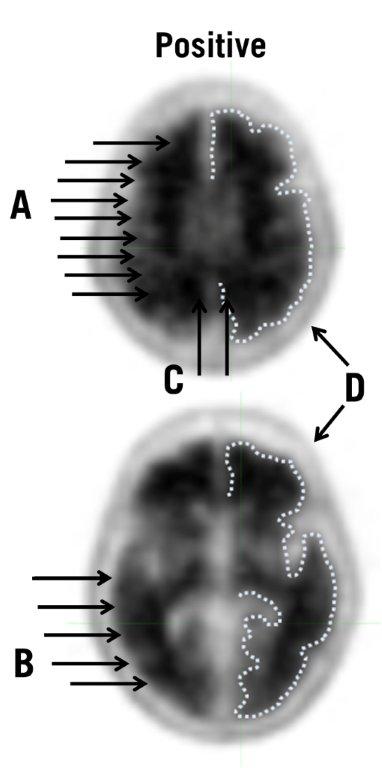
Figures 1, 2, and 3 provide examples of negative and positive scans.

Figure 1 (Amyvid Pet Image 1)
Figure 1: Examples of AMYVID negative scans (top two rows) and positive scans (bottom two rows). Left to right panels show sagittal, coronal, and transverse PET image slices. Final panel to right shows an enlarged picture of the brain area under the box. The top two arrows are pointing to normal preserved gray-white contrast with cortical signal intensity less than the adjacent white matter. The bottom two arrows indicate areas of decreased gray-white contrast with increased cortical signal intensity that is comparable to the intensity in the adjacent white matter.
 Figure 2 (Amyvid Pet Image 2) | Figure 2: Typical Negative Scan. The upper (top) and lower (bottom) transverse slices both show good gray-white matter contrast. The dotted lines illustrate the edge of the cortical gray matter (outer line) and the gray-white border (inner line) and highlight the contrast between less intense signal in the gray matter and more intense signal in the white matter. The arrows illustrate the following points:
A. White matter tracts can be delineated from the frontal lobe to parietal lobe.
B. White matter tracts are clearly identified throughout the occipital / temporal area.
C. Scalloped appearance is seen with “fingers” of white matter in the frontal cortex.
D. Low levels of signal in scalp or skull are distinguished from gray matter signal by the shape and position.
|
 Figure 3 (Amyvid Pet Image 3) | Figure 3: Typical Positive Scan: The upper (top) and lower (bottom) transverse slices show loss of gray-white matter contrast in multiple brain regions. The dotted lines illustrate the edge of the cortical gray matter. Compared to the images from the negative case in Figure 2, the gray matter signal is similar to white matter signal and the gray-white matter border is more difficult to discern. The arrows show the following points:
A. White matter tracts are difficult to fully identify as they travel from frontal to parietal lobe.
B. Borders of white matter tracts in occipital / temporal area are lost in places.
C. Gray matter in medial parietal cortex (precuneus) has increased signal.
D. Low levels of signal in scalp or skull are distinguished from gray matter signal by the shape and position.
|
Quantitative Analysis
Quantification of amyloid beta neuritic plaque levels (e.g., Centiloid scale or standardized uptake value ratio (SUVR)) can be used in conjunction with visual assessment and performed with FDA-authorized software indicated for quantification of brain amyloid beta PET scans. Refer to the drug manufacturer's training materials for qualitative and quantitative assessment and software manufacturers' documentation for software operation.
Risk Summary
There are no available data on AMYVID use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal reproduction studies have not been conducted with florbetapir F 18 to evaluate its effect on female reproduction and embryo-fetal development.
All radiopharmaceuticals, including AMYVID, have the potential to cause fetal harm depending on the stage of fetal development and the magnitude of the radiation dose. If considering AMYVID administration to a pregnant woman, inform the patient about the potential for adverse pregnancy outcomes based on the radiation dose from the drug and the gestational timing of exposure.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Risk Summary
There are no data on the presence of florbetapir F 18 in human milk, the effects on the breastfed infant, or effects on milk production. Lactation studies have not been conducted in animals. Exposure of AMYVID to a breastfed infant can be minimized by temporary discontinuation of breastfeeding (see Clinical Considerations). The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for AMYVID and any potential adverse effects on the breastfed child from AMYVID or from the underlying maternal condition.
Clinical Considerations
To decrease radiation exposure to the breastfed infant, advise a lactating woman to pump and discard breast milk for 24 hours (>10 half-lives of radioactive decay for the F 18 isotope) following administration of AMYVID.
Drug Interaction Studies
Clinical
In patients with probable AD, mean cortical SUVR did not differ between patients taking or not taking donepezil, galantamine, or memantine.
In vitro
Effect of acetylcholinesterase inhibitors: donepezil, galantamine, and tacrine did not alter florbetapir F 18 binding to its target.
Effect of amyloid beta-directed therapy: donanemab and lecanemab did not alter florbetapir F 18 binding to its target.
Mutagenesis
In an in vitro bacterial reverse mutation assay (Ames test), increases in the number of revertant colonies were observed in 2 of the 5 strains exposed to 19F-AV-45, the non-radioactive form of florbetapir F 18. In a chromosomal aberration in vitro study with cultured human peripheral lymphocytes, 19F-AV-45 did not increase the percentage of cells with structural aberrations with 3-hour exposure with or without activation; however, 22-hour exposure produced a statistically significant increase in structural aberrations at all tested concentrations. Potential in vivo genotoxicity of 19F-AV-45 was evaluated in a rat micronucleus study. In this assay, 19F-AV-45 did not increase the number of micronucleated polychromatic erythrocytes at the highest achievable dose level, 372 mcg/kg/day, when given twice daily for 3 consecutive days.
How Supplied
AMYVID (florbetapir F 18 injection) is a clear, colorless solution supplied in a shielded multiple-dose vial available as:
| Concentration @ EOS | Volume | Vial Size | NDC |
500 MBq/mL to 1,900 MBq/mL
(13.5 mCi/mL to 51 mCi/mL)
| 10 mL to 50 mL
| 50 mL
| 0002-1200-50
|
500 MBq/mL to 1,900 MBq/mL
(13.5 mCi/mL to 51 mCi/mL)
| 10 mL to 100 mL
| 100 mL
| 0002-1200-48
|
Storage and Handling
Store AMYVID in the original container with radiation shielding at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
AMYVID does not contain a preservative.
Do not use after the expiration date and time provided on the container label.
AMYVID multiple-dose vial expires 10 hours after EOS.
Dispose of unused product in accordance with all federal, state, and local laws and institutional requirements.
This preparation is for use by persons under license by the Nuclear Regulatory Commission or the relevant regulatory authority of an Agreement State.
Radiation Risk
Advise patients of the radiation risk of AMYVID. Instruct patients to drink water to ensure adequate hydration prior to administration of AMYVID and to continue drinking and voiding frequently following administration to reduce radiation exposure [see Warnings and Precautions (5.2)].
Pregnancy
Inform pregnant women of the potential risks of fetal exposure to radiation doses with AMYVID [see Use in Specific Populations (8.1)].
Lactation
Advise a lactating woman to temporarily discontinue breastfeeding and to pump and discard breast milk for 24 hours (>10 half-lives of radioactive decay for the F 18 isotope) after AMYVID administration to minimize radiation exposure to the breastfed infant [see Use in Specific Populations (8.2)].
Marketed by
Lilly USA, LLC
Indianapolis, IN 46285
USA
Copyright © 2012, 2025, Eli Lilly and Company. All rights reserved.
AMV-0005-USPI-20250709