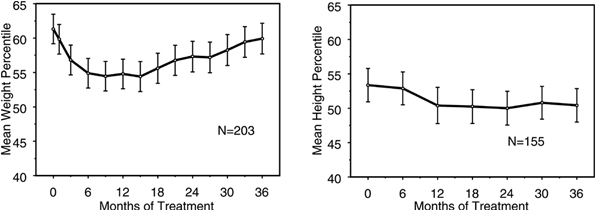
CYP2D6 poor metabolizers and other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) treated with STRATTERA for at least two years gained weight and height. However, in:
- CYP2D6 poor metabolizers the mean weight gain was 2.4 kg less than predicted and the mean height gain was 1.1 cm less than predicted
- Other CYP2D6 metabolizer types the mean weight gain was 0.2 kg less than predicted and the mean height gain was 0.4 cm less than predicted.
In the long-term open-label studies, the growth pattern was generally similar regardless of pubertal status at the time of
STRATTERA treatment initiation.
Weight and Height in Short-Term, Placebo-Controlled Studies in Pediatric Patients
In short-term, placebo-controlled studies (up to 9 weeks), STRATTERA-treated patients lost an average of 0.4 kg in weight and gained an average of 0.9 cm in height, compared to a gain of 1.5 kg in weight and 1.1 cm in height in the placebo-treated patients.
In a fixed-dose controlled trial, 1.3%, 7.1%, 19.3%, and 29.1% of patients in the placebo, 0.5, 1.2, and 1.8 mg/kg/day STRATTERA groups, respectively, lost at least 3.5% of their body weight.
Adverse Reactions in the Clinical Trials of Pediatric Patients 6 Years of Age and Older with ADHD
Discontinuation of Treatment Due to Adverse Reactions in the Clinical Studies of Pediatric Patients 6 Years of Age and Older:
In the acute placebo-controlled studies of pediatric patients 6 years of age and older with ADHD, 3% (48/1,613) of STRATTERA-treated pediatric patients and 1.4% (13/945) of placebo-treated pediatric patients discontinued due to an adverse reaction. Among STRATTERA-treated patients, irritability (0.3%, N=5); somnolence (0.3%, N=5); aggression (0.2%, N=4); nausea (0.2%, N=4); vomiting (0.2%, N=4); abdominal pain (0.2%, N=4); constipation (0.1%, N=2); fatigue (0.1%, N=2); feeling abnormal (0.1%, N=2); and headache (0.1%, N=2) were the reasons for discontinuation reported by more than one patient.
For all studies, (including open-label and long-term studies), 6% of STRATTERA-treated pediatric patients who were other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) and 11% of those who were CYP2D6 poor metabolizers discontinued due to an adverse reaction.
Common Adverse Reactions in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: Common adverse reactions (incidence of 2% or greater in STRATTERA-treated patients and with a higher incidence in STRATTERA-treated patients compared to placebo-treated patients) in pediatric patients 6 years of age and older with ADHD are listed in Table 2. The most commonly observed adverse reactions in STRATTERA-treated patients (incidence of ≥5% and ≥ twice the incidence in placebo-treated patients), for either twice daily or once daily dosing were: nausea, vomiting, fatigue, decreased appetite, abdominal pain, and somnolence (see
Tables 2 and 3).
Table 2: Common Adverse Reactionsa in Acute Studies (up to 18 weeks) in Pediatric Patients 6 Years and Older with ADHD
|
|
|
| Adverse Reaction | STRATTERA
(N=1,597) | Placebo
(N=934) |
| Headache
| 19%
| 15%
|
| Abdominal painb | 18%
| 10%
|
| Decreased appetite
| 16%
| 4%
|
| Somnolencec | 11%
| 4%
|
| Vomiting
| 11%
| 6%
|
| Nausea
| 10%
| 5%
|
| Fatigue
| 8%
| 3%
|
| Irritability
| 6%
| 3%
|
| Dizziness
| 5%
| 2%
|
| Decreased weight
| 3%
| 0%
|
| Anorexia
| 3%
| 1%
|
| Rash
| 2%
| 1%
|
Adverse reaction in the STRATTERA-treated patients who received twice daily, and once daily dosing are shown in Table 3 (adverse reactions based on statistically significant Breslow-Day tests).
Table 3: Common Adverse Reactions in Acute Studies (up to 18 weeks) in Pediatric Patients 6 Years and Older with ADHD
|
|
|
| Adverse Reaction | ADHD Studies with Twice Daily Dosing | ADHD Studies with Once Daily Dosing |
STRATTERA
(N=715) | Placebo
(N=434) | STRATTERA
(N=882) | Placebo
(N=500) |
| Abdominal paina | 17%
| 13%
| 18%
| 7%
|
| Vomiting
| 11%
| 8%
| 11%
| 4%
|
| Nausea
| 7%
| 6%
| 13%
| 4%
|
| Fatigue
| 6%
| 4%
| 9%
| 2%
|
| Mood swingsb | 2%
| 0%
| 1%
| 1%
|
| Constipationc | 2%
| 1%
| 1%
| 0%
|
Common Adverse Reactions by CYP2D6 Metabolizer Status in the Clinical Studies of Pediatric Patients 6 Years of Age and Older:
Table 4 displays adverse reactions that occurred in at least 2% of STRATTERA-treated pediatric patients who were CYP2D6 poor metabolizers and were statistically significantly more frequent in CYP2D6 poor metabolizers compared with other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate).
Table 4: Common Adverse Reactionsa in STRATTERA-treated Pediatric Patients 6 Years and Older with ADHD by CYP2D6 Metabolizer Types
|
|
| Adverse Reaction | STRATTERA
CYP2D6 Poor Metabolizers (N=355) | STRATTERA
Other CYP2D6 Metabolizer Types (N=5,019) |
| Insomnia
| 11%
| 6%
|
| Decreased weight
| 7%
| 4%
|
| Constipation
| 7%
| 4%
|
| Depressionb | 7%
| 4%
|
| Tremor
| 5%
| 1%
|
| Excoriation
| 4%
| 2%
|
| Sedation
| 4%
| 2%
|
| Middle insomnia
| 3%
| 1%
|
| Conjunctivitis
| 3%
| 1%
|
| Syncope
| 3%
| 1%
|
| Early morning awakening
| 2%
| 1%
|
| Mydriasis
| 2%
| 1%
|
Less Common Adverse Reactions in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: The following reactions did not meet this criterion but were reported by more STRATTERA-treated patients than placebo-treated patients and are possibly related to STRATTERA treatment: blood pressure increased, early morning awakening (terminal insomnia), flushing, mydriasis, sinus tachycardia, asthenia, palpitations, mood swings, constipation, and dyspepsia.
The following reactions were reported by at least 2% of patients treated with STRATTERA, and equal to or less than placebo: pharyngolaryngeal pain, insomnia (insomnia includes the terms, insomnia, initial insomnia, middle insomnia). The following reaction did not meet this criterion but shows a statistically significant dose relationship: pruritus.
Seizures in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: STRATTERA has not been systematically evaluated in pediatric patients with seizure disorder as these patients were excluded from STRATTERA studies. In the clinical development program, seizures were reported in 0.2% (12/5,073) of STRATTERA-treated pediatric patients whose average age was 10 years old (range 6 to 16 years of age). In these clinical trials, the seizure incidence among CYP2D6 poor metabolizers was 0.3% (1/293) compared to 0.2% (11/4,741) for other CYP2D6 metabolizer types.
Heart Rate and Blood Pressure Increases in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: Additional data from ADHD clinical trials (controlled and uncontrolled) has shown that approximately 5 to 10% of pediatric patients experienced potentially clinically important changes in heart rate (≥20 beats per minute) or blood pressure (≥15 to 20 mm Hg) [see Contraindications (4) and Warnings and Precautions (5.4)].
Adverse Reactions in the Clinical Trials of Adults with ADHD
Discontinuation of Treatment Due to Adverse Reactions in the Clinical Studies of Adults: In the acute adult placebo-controlled trials, 11.3% (61/541) STRATTERA-treated patients and 3% (12/405) placebo-treated patients discontinued for adverse reactions. Among STRATTERA-treated patients, insomnia (0.9%, N=5); nausea (0.9%, N=5); chest pain (0.6%, N=3); fatigue (0.6%, N=3); anxiety (0.4%, N=2); erectile dysfunction (0.4%, N=2); mood swings (0.4%, N=2); nervousness (0.4%, N=2); palpitations (0.4%, N=2); and urinary retention (0.4%, N=2) were the reasons for discontinuation reported by more than 1 patient.
Common Adverse Reactions in the Clinical Studies of Adults: Commonly observed adverse reactions associated with the use of STRATTERA (incidence of 2% or greater) and not observed at an equivalent incidence among placebo-treated patients (STRATTERA incidence greater than placebo) are listed in Table 5. The most commonly observed adverse reactions in patients treated with STRATTERA (incidence of 5% or greater and at least twice the incidence in placebo patients) were: constipation, dry mouth, nausea, decreased appetite, dizziness, erectile dysfunction, and urinary hesitation (see
Table 5).
Table 5: Common Adverse Reactionsa Associated in Acute Studies (up to 25 weeks) of Adult Patients with ADHD
|
|
|
|
|
|
|
| Adverse Reaction | STRATTERA (N=1,697) | Placebo (N=1,560) |
| Nausea
| 26%
| 6%
|
| Dry mouth
| 20%
| 5%
|
| Decreased appetite
| 16%
| 3%
|
| Insomniab | 15%
| 8%
|
| Fatigue
| 10%
| 6%
|
| Erectile dysfunctionc | 8%
| 1%
|
| Constipation
| 8%
| 3%
|
| Dizziness
| 8%
| 3%
|
| Somnolenced | 8%
| 5%
|
| Abdominal paine | 7%
| 4%
|
| Urinary hesitationf | 6%
| 1%
|
| Irritability
| 5%
| 3%
|
| Ejaculation delayedc and/or ejaculation disorderc | 4%
| 1%
|
| Hyperhidrosis
| 4%
| 1%
|
| Dyspepsia
| 4%
| 2%
|
| Vomiting
| 4%
| 2%
|
| Abnormal dreams
| 4%
| 3%
|
| Chills
| 3%
| 0%
|
| Paraesthesia
| 3%
| 0%
|
| Hot flush
| 3%
| 0%
|
| Palpitations
| 3%
| 1%
|
| Libido decreased
| 3%
| 1%
|
| Sleep disorder
| 3%
| 1%
|
| Dysmenorrheag | 3%
| 2%
|
| Dysuria
| 2%
| 0%
|
| Thirst
| 2%
| 1%
|
| Weight decreased
| 2%
| 1%
|
| Feeling jittery
| 2%
| 1%
|
Common Adverse Reactions by CYP2D6 Metabolizer Status in the Clinical Studies of Adults:
Table 6 displays adverse reactions that occurred in at least 2% of STRATTERA-treated adult patients who were CYP2D6 poor metabolizers and were statistically significantly more frequent compared to other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate).
Table 6: Common Adverse Reactionsa in STRATTERA-treated Adult Patients with ADHD by CYP2D6 Metabolizer Types
|
| Adverse Reaction | STRATTERA
CYP2D6 Poor Metabolizers (N=203) | STRATTERA
Other CYP2D6 Metabolizer Types (N=3,599) |
| Dry mouth
| 35%
| 17%
|
| Decreased appetite
| 23%
| 15%
|
| Erectile dysfunction
| 21%
| 9%
|
| Insomnia
| 19%
| 11%
|
| Hyperhidrosis
| 15%
| 7%
|
| Constipation
| 11%
| 7%
|
| Sleep disorder
| 7%
| 3%
|
| Urinary retention
| 6%
| 1%
|
| Ejaculation disorder
| 6%
| 2%
|
| Tremor
| 5%
| 1%
|
| Feeling jittery
| 5%
| 2%
|
| Middle insomnia
| 5%
| 3%
|
| Blurred vision
| 4%
| 1%
|
| Terminal insomnia
| 3%
| 1%
|
| Peripheral coldness
| 3%
| 1%
|
Less Common Adverse Reactions in the Clinical Studies of Adults: The following reactions did not meet this criterion but were reported by more STRATTERA-treated patients than placebo-treated patients and are possibly related to STRATTERA treatment: peripheral coldness, tachycardia, prostatitis, testicular pain, orgasm abnormal, flatulence, asthenia, feeling cold, muscle spasm, dysgeusia, agitation, restlessness, micturition urgency, pollakiuria, pruritus, urticaria, flushing, tremor, menstruation irregular, rash, and urinary retention.
Seizures in the Clinical Studies of Adults: STRATTERA has not been systematically evaluated in adult patients with a seizure disorder as these patients were excluded from clinical studies during the product's premarket testing. In the clinical development program, seizures were reported on 0.1% (1/748) of adult patients. In these clinical trials, no CYP2D6 poor metabolizers (0/43) reported seizures compared to 0.1% (1/705) for other CYP2D6 metabolizer types.
Heart Rate and Blood Pressure Increases in the Clinical Studies of Adults:
Table 7 displays the proportion of STRATTERA-treated and placebo-treated patients who had an increase in diastolic blood pressure (DBP) ≥15 mm Hg, systolic blood pressure (SBP) ≥20 mm Hg, or heart rate ≥ 20 bpm in short-term, placebo-controlled clinical studies in pediatric and adult patients with ADHD [see Warnings and Precautions (5.4)].
Table 7: Proportion of ADHD Patients With an Increase of ≥ 15 mm Hg in DBP, ≥20 mm Hg in SBP, or ≥ 20 bpm in Heart Ratea |
|
| Pediatric Acute ADHD Studies | Adult Acute ADHD Studies |
| Maximumb | Endpoint | Maximumb | Endpoint |
| STRATTERA | Placebo | STRATTERA | Placebo | STRATTERA | Placebo | STRATTERA | Placebo |
| DBP (≥15 mm Hg)
| 22%
| 14%
| 9%
| 5%
| 13%
| 9%
| 5%
| 4%
|
| SBP (≥20 mm Hg)
| 13%
| 9%
| 5%
| 3%
| 12%
| 8%
| 4%
| 3%
|
| HR (≥20 bpm)
| 23%
| 12%
| 12%
| 4%
| 22%
| 8%
| 10%
| 2%
|
Additional data from ADHD clinical trials (controlled and uncontrolled) showed that approximately 5 to 10% of adult patients had potentially clinically important changes in heart rate (≥20 beats per minute) or blood pressure (≥15 to 20 mm Hg) [see Contraindications (4) and Warnings and Precautions (5.4)].
Male and Female Sexual Dysfunction in the Clinical Studies of Adults: STRATTERA impaired sexual function in some patients. Estimates of the incidence of untoward sexual experience and performance in these studies are likely to underestimate their actual incidence because patients and health care providers may be reluctant to discuss them. Table 5 displays the incidence of sexual adverse reactions (reported by at least 2% of STRATTERA-treated adult patients in the placebo-controlled studies of adults with ADHD (i.e., erectile dysfunction, dysmenorrhea, and ejaculation delayed and/or ejaculation disorder).
There are no adequate and well-controlled studies examining sexual dysfunction with STRATTERA treatment. While it is difficult to know the precise risk of sexual dysfunction associated with the use of STRATTERA, health care providers should routinely inquire about sexual dysfunction.
Pregnancy Exposure Registry
There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD drugs, including STRATTERA, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388 or visiting https://womensmentalhealth.org/adhd-medications/.
Risk Summary
Available published studies with STRATTERA use in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
Some animal reproduction studies of atomoxetine had adverse developmental outcomes. One of 3 studies in pregnant rabbits dosed during organogenesis resulted in decreased live fetuses and an increase in early resorptions, as well as slight increases in the incidences of atypical origin of carotid artery and absent subclavian artery. These effects were observed at plasma levels (AUC) 3 times and 0.4 times the human plasma levels in other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) and poor metabolizers receiving the maximum recommended human dose (MRHD), respectively. In rats dosed prior to mating and during organogenesis a decrease in fetal weight (female only) and an increase in the incidence of incomplete ossification of the vertebral arch in fetuses were observed at a dose approximately 5 times the MRHD on a mg/m2 basis. In one of 2 studies in which rats were dosed prior to mating through the periods of organogenesis and lactation, decreased pup weight and decreased pup survival were observed at doses corresponding to 5-6 times the MRHD on a mg/m2 basis. No adverse fetal effects were seen in pregnant rats dosed during the organogenesis period (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data
Animal Data: Pregnant rabbits were treated with up to 100 mg/kg/day of atomoxetine by gavage throughout the period of organogenesis. At this dose, in 1 of 3 studies, a decrease in live fetuses and an increase in early resorptions was observed. Slight increases in the incidences of atypical origin of carotid artery and absent subclavian artery were observed. These findings were observed at doses that caused slight maternal toxicity. The no-effect dose for these findings was 30 mg/kg/day. The 100 mg/kg dose is approximately 23 times the MRHD on a mg/m2 basis; plasma levels (AUC) of atomoxetine at this dose in rabbits are estimated to be 3.3 times (other CYP2D6 metabolizer types) or 0.4 times (CYP2D6 poor metabolizers) those in humans receiving the MRHD.
Rats were treated with up to approximately 50 mg/kg/day of atomoxetine (approximately 6 times the MRHD on a mg/m2 basis) in the diet from 2 weeks (females) or 10 weeks (males) prior to mating through the periods of organogenesis and lactation. In 1 of 2 studies, decreases in pup weight and pup survival were observed. The decreased pup survival was also seen at 25 mg/kg (but not at 13 mg/kg). In a study in which rats were treated with atomoxetine in the diet from 2 weeks (females) or 10 weeks (males) prior to mating throughout the period of organogenesis, a decrease in fetal weight (female only) and an increase in the incidence of incomplete ossification of the vertebral arch in fetuses were observed at 40 mg/kg/day (approximately 5 times the MRHD on a mg/m2 basis) but not at 20 mg/kg/day.
No adverse fetal effects were seen when pregnant rats were treated with up to 150 mg/kg/day (approximately 17 times the MRHD on a mg/m2 basis) by gavage throughout the period of organogenesis.
Risk Summary
There are no data on the presence of atomoxetine or its metabolite in human milk, the effects on the breastfed child, or the effects on milk production. Atomoxetine is present in animal milk. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for STRATTERA and any potential adverse effects on the breastfed child from STRATTERA or from the underlying maternal condition.
Juvenile Toxicity Animal Data
A study was conducted in young rats to evaluate the effects of atomoxetine on growth and neurobehavioral and sexual development. Rats were treated with 1, 10, or 50 mg/kg/day (approximately 0.2, 2, and 8 times, respectively, the maximum human dose on a mg/m2 basis) of atomoxetine given by gavage from the early postnatal period (Day 10 of age) through adulthood. Slight delays in onset of vaginal patency (all doses) and preputial separation (10 and 50 mg/kg), slight decreases in epididymal weight and sperm number (10 and 50 mg/kg), and a slight decrease in corpora lutea (50 mg/kg) were seen, but there were no effects on fertility or reproductive performance. A slight delay in onset of incisor eruption was seen at 50 mg/kg. A slight increase in motor activity was seen on Day 15 (males at 10 and 50 mg/kg and females at 50 mg/kg) and on Day 30 (females at 50 mg/kg) but not on Day 60 of age. There were no effects on learning and memory tests. The significance of these findings to humans is unknown.
Cardiac Electrophysiology
The effect of STRATTERA on QTc interval prolongation was evaluated in a randomized, double-blinded, positive-(moxifloxacin 400 mg) and placebo-controlled, cross-over study in healthy male CYP2D6 poor metabolizers. A total of 120 healthy subjects were administered STRATTERA (20 mg and 60 mg) twice daily for 7 days. No large changes in QTc interval (i.e., increases >60 msec from baseline, absolute QTc >480 msec) were observed in the study. However, small changes in QTc interval cannot be excluded from this study, because the study failed to demonstrate assay sensitivity. There was a slight increase in QTc interval with increased atomoxetine concentration.
Pharmacodynamic Drug Interaction Studies
- Consumption of ethanol with STRATTERA did not change the intoxicating effects of ethanol.
- Concomitant use of STRATTERA with methylphenidate did not increase cardiovascular effects beyond those seen with methylphenidate alone.
- Albuterol 600 mcg given intravenously over 2 hours (albuterol is not approved for intravenous use) induced heart rate and blood pressure increases; these effects were potentiated when co-administered with STRATTERA (60 mg twice daily for 5 days), particularly initially [see Drug Interactions (7)].
Specific Populations
Hepatic Impairment: Atomoxetine exposure (AUC) was increased in subjects with moderate (Child-Pugh Class B) (2‑fold increase) and severe (Child-Pugh Class C) (4‑fold increase) hepatic impairment compared to subjects with normal hepatic function in other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) [see Dosage and Administration (2.4) and Use in Specific Populations (8.6)].
Renal Impairment: Patients with severe renal impairment (end stage renal disease requiring hemodialysis) had higher systemic atomoxetine exposure (about a 65% increase) than patients with normal renal function (CrCl ≥ 90 ml/minute) in other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate), but there was no difference when exposure was corrected for mg/kg dose. Thus, the differences in exposure were not clinically significant.
Pediatric Patients: The pharmacokinetics of atomoxetine were evaluated in more than 400 pediatric patients in clinical studies, primarily using population pharmacokinetic modeling. Single-dose and steady-state individual pharmacokinetic data were also obtained in pediatric patients and adults. When STRATTERA doses were normalized to a mg/kg basis, similar half- life, Cmax, and AUC values were observed in pediatric patients and adults. Clearance and volume of distribution after adjustment for body weight were also similar.
Sex: Sex did not influence atomoxetine disposition.
Ethnic Origin: Ethnic origin did not influence atomoxetine disposition.
Drug Interaction Studies
Clinical Studies:
Strong CYP2D6 Inhibitors: Concomitant use of STRATTERA (20 mg BID for 5 days) with paroxetine (20 mg QD for 17 days), a known inhibitor of CYP2D6, in subjects who were not CYP2D6 poor metabolizers resulted in a 6.5-fold higher plasma exposure (AUC) to atomoxetine at steady state.
Concomitant use of STRATTERA (at sequential dosing of 10, 45, and 75 mg BID for up to 5 days of each dosage) with fluoxetine (20 mg QD for 36 days) a known inhibitor of CYP2D6, in subjects who were not CYP2D6 poor metabolizers resulted in 6- to 8-fold increases of plasma atomoxetine exposure (AUC) at steady state compared to taking STRATTERA alone.
After concomitant use of STRATTERA with paroxetine or fluoxetine, the Css, max of atomoxetine was about 3-to 4-fold greater than the use of STRATTERA alone [see Drug Interactions (7)].
CYP3A Substrates: Concomitant use of STRATTERA (60 mg twice daily for 12 days) with midazolam (CYP3A substrate) (single dose of 5 mg), resulted in 15% increase in the midazolam AUC. This pharmacokinetic change is not clinically significant.
CYP2D6 Substrates: Concomitant use of STRATTERA (40 or 60 mg twice daily for 13 days) with desipramine, (CYP2D6 substrate) (single dose of 50 mg), did not alter the desipramine pharmacokinetics.
Drugs that Affect Gastric pH: Drugs that elevate gastric pH had no effect on atomoxetine bioavailability.
In Vitro Studies:
Drugs Highly Bound to Plasma Protein: In vitro drug-displacement studies were conducted with atomoxetine and other drugs highly bound to plasma protein at therapeutic atomoxetine concentrations. Atomoxetine did not affect the binding of warfarin, acetylsalicylic acid, phenytoin, or diazepam to human albumin. Similarly, warfarin, acetylsalicylic acid, phenytoin, or diazepam did not affect the binding of atomoxetine to human albumin.
CYP Inhibition/induction: Atomoxetine did not cause clinically important inhibition or induction of cytochrome P450 enzymes (including CYP1A2, CYP3A, CYP2D6, and CYP2C9).
Carcinogenesis — Atomoxetine HCl was not carcinogenic in rats and mice when given in the diet for 2 years at time-weighted average doses up to 47 and 458 mg/kg/day, respectively. The highest dose used in rats is approximately 8 and 5 times the maximum recommended human dose (MRHD) in children and adults, respectively, on a mg/m2 basis.
Plasma levels (AUC) of atomoxetine at this dose in rats are estimated to be 1.8 times (other CYP2D6 metabolizer types) or 0.2 times (CYP2D6 poor metabolizers) those in humans receiving the maximum human dose. The highest dose used in mice is approximately 39 and 26 times the MRHD in children and adults, respectively, on a mg/m2 basis.
Mutagenesis — Atomoxetine HCl was negative in a battery of genotoxicity studies that included a reverse point mutation assay (Ames Test), an in vitro mouse lymphoma assay, a chromosomal aberration test in Chinese hamster ovary cells, an unscheduled DNA synthesis test in rat hepatocytes, and an in vivo micronucleus test in mice. However, there was a slight increase in the percentage of Chinese hamster ovary cells with diplochromosomes, suggesting endoreduplication (numerical aberration).
The metabolite N-desmethylatomoxetine HCl was negative in the Ames Test, mouse lymphoma assay, and unscheduled DNA synthesis test.
Impairment of Fertility — Atomoxetine HCl did not impair fertility in rats when given in the diet at doses of up to 57 mg/kg/day, which is approximately 6 times the MRHD on a mg/m2 basis.
Acute Studies in Pediatric Patients 6 Years of Age and Older with ADHD:
The effectiveness of STRATTERA in the treatment of ADHD was established in four randomized, double-blind, placebo-controlled studies of pediatric patients 6 to 18 years of age (Studies 1, 2, 3, and 4). In these studies, approximately one-third of the patients met DSM-IV criteria for inattentive subtype and two-thirds met criteria for both inattentive and hyperactive/impulsive subtypes.
In these studies, signs and symptoms of ADHD were evaluated with the investigator administered and scored ADHD Rating Scale-IV-Parent Version (ADHDRS) total score including hyperactive/impulsive and inattentive subscales by comparing the mean change from baseline to endpoint in the STRATTERA and placebo groups using an intent-to-treat (ITT) analysis (the primary endpoint). Each item on the ADHDRS maps directly to one symptom criterion for ADHD in the DSM-IV.
In Study 1, an 8-week randomized, double-blind, placebo-controlled, dose-response, acute treatment study, pediatric patients 8 to 18 years of age (N=297) received either a fixed dosage of STRATTERA (0.25, 0.6, or 0.9 mg/kg twice daily (in the early morning and late afternoon/early evening) or placebo. Improvements in ADHD symptoms were statistically significantly superior in patients treated with either of the two higher STRATTERA dosages compared with patients treated with placebo as measured on the ADHDRS scale. The 0.9 mg/kg twice daily STRATTERA dosage did not provide any additional benefit over that observed with the 0.6 mg/kg twice daily STRATTERA dosage. The 0.25 mg/kg twice daily STRATTERA dosage group was not superior to the placebo group.
In Study 2, a 6-week randomized, double-blind, placebo-controlled, acute treatment study, pediatric patients 6 to 16 years of age (N=171) received either STRATTERA or placebo. STRATTERA was administered as a once daily dose in the early morning and titrated on a weight-adjusted basis according to clinical response, up to a maximum dosage of 1.5 mg/kg once daily. The mean final dosage of STRATTERA was approximately 1.3 mg/kg once daily. ADHD symptoms were statistically significantly improved in the STRATTERA group compared to the placebo group, as measured on the ADHDRS scale. Study 2 showed that STRATTERA was effective when administered once daily in the morning.
In two identically designed, 9-week, acute, double-blind, placebo-controlled studies, pediatric patients 7 to 13 years of age (Study 3, N=147; Study 4, N=144) were randomized to receive STRATTERA, methylphenidate, or placebo. In Studies 3 and 4, STRATTERA was administered twice daily (in the early morning and late afternoon, after school) and titrated on a weight-adjusted basis according to clinical response up to the maximum recommended STRATTERA dosage of 1 mg/kg twice daily. The mean final dosage of STRATTERA in Studies 3 and 4 was approximately 0.8 mg/kg twice daily. In Studies 3 and 4, ADHD symptoms statistically significantly improved more in the STRATTERA group than the placebo group, as measured on the ADHDRS scale.
Examination of population subsets based on sex and age (<12 and 12 to 17 years of age) in these studies did not reveal any differences in response. There were not sufficient numbers of patients in racial or ethnic groups to determine if there were differences in responses in these subgroups.
Maintenance Study in Pediatric Patients 6 Years of Age and Older with ADHD
The effectiveness of STRATTERA in the maintenance treatment of ADHD in pediatric patients 6 years of age and older was established in an outpatient randomized withdrawal study of pediatric patients 6-15 years of age (Study 5). In this study, patients who met DSM-IV criteria for ADHD, and showed continuous response for about 4 weeks during an initial 10-week open-label treatment phase with STRATTERA (1.2 to 1.8 mg/kg/day) were randomized to continue of their current STRATTERA dosage (N=292) or to placebo (N=124) under double-blind treatment for observation of relapse (first double-blind phase). Response during the open-label phase was defined as CGI-ADHD-S score ≤2 and a reduction of at least 25% from baseline in ADHDRS-IV-Parent: Investigator total score.
Patients who were assigned to STRATTERA during the first double-blind phase who showed continuous response for approximately 8 months during the first double-blind treatment phase were again randomized to continue their current STRATTERA dosage (N=81) or placebo (N=82) under double-blind treatment for observation of relapse (second double-blind phase). Relapse during each of the double-blind phases was defined as CGI-ADHD-S score increases of at least 2 from the end of open-label phase and ADHDRS-IV-Parent: Investigator total score returns to ≥90% of study entry score for 2 consecutive visits.
In both double-blind phases, patients who received STRATTERA treatment experienced significantly longer times to relapse than those who received placebo.
Tics in Patients with ADHD and Tourette's Disorder or Chronic Motor Tic Disorder
In a randomized, double-blind, placebo-controlled 18-week trial in 148 pediatric patients 7 to 17 years old with a DSM-IV diagnosis of ADHD and concurrent Tourette syndrome or chronic motor tic disorder, STRATTERA affect on tic severity was assessed. Patients in the STRATTERA group received a flexible dosage range of 0.5 to 1.5 mg/kg/day (mean dose of 1.3 mg/kg/day). In this study, 80% (n=116) of patients had Tourette's Disorder and 20% (n=29) of patients had chronic motor tic disorder. A non-inferiority analysis revealed that STRATTERA did not worsen tics in these patients as determined by the Yale Global Tic Severity Scale Total Score (YGTSS). Out of 148 patients who entered the acute treatment phase, 103 (70%) patients discontinued the study. The primary reason for discontinuation in both the STRATTERA group (50% (38/76) and placebo group (63% (45/72) was identified lack of ADHD efficacy with most of the patients discontinuing at Week 12. There have been postmarketing reports of tics in STRATTERA-treated patients [see Adverse Reactions (6.2)].
Anxiety in Pediatric Patients with ADHD and Anxiety Disorders
Two post-marketing, double-blind, placebo-controlled trials demonstrated that treating patients with ADHD and comorbid anxiety disorders with STRATTERA does not worsen their anxiety.
In a 12-week double-blind, placebo-controlled trial, 176 pediatric patients 8-17 years of age, who met DSM-IV criteria for ADHD and at least one of the anxiety disorders of separation anxiety disorder, generalized anxiety disorder or social phobia were randomized to receive STRATTERA or placebo. In the STRATTERA group, following a 2-week double-blind placebo lead-in, STRATTERA was initiated at 0.8 mg/kg/day with increase to a target dose of 1.2 mg/kg/day (median dose 1.3 mg/kg/day +/- 0.29 mg/kg/day). STRATTERA did not worsen anxiety in these patients as determined by the Pediatric Anxiety Rating Scale (PARS). Of the 158 patients who completed the double-blind placebo lead-in, 26 (16%) patients discontinued the study.
In a separate 16-week, double-blind, placebo-controlled trial, 442 patients aged 18-65, who met DSM-IV criteria for adult ADHD and social anxiety disorder (23% of whom also had Generalized Anxiety Disorder) were randomized to receive STRATTERA or placebo. In the STRATTERA group, following a 2-week double-blind placebo lead-in, STRATTERA was initiated at 40 mg/day to a maximum dosage of 100 mg/day (mean daily dose 83 mg/day +/- 19.5 mg/day). STRATTERA did not worsen anxiety in these patients as determined by the Liebowitz Social Anxiety Scale (LSAS). Of the 413 patients who completed the double-blind placebo lead-in, 36% (n=149) patients discontinued the study. There have been postmarketing reports of anxiety [see Adverse Reactions (6.2)].
Suicide Risk
Patients, their families, and their caregivers should be alerted about the need to monitor patients daily for the emergence of anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, mania, other unusual changes in behavior, depression, and suicidal ideation, especially early during STRATTERA treatment and when the dosage is adjusted. Such symptoms should be reported to the patient's health care provider immediately [see Warnings and Precautions (5.1)].
Severe Liver Injury
Patients initiating STRATTERA should be cautioned that severe liver injury may develop. Patients should be instructed to contact their healthcare provider immediately should they develop pruritus, dark urine, jaundice, right upper quadrant tenderness, or unexplained “flu-like” symptoms [see Warnings and Precautions (5.2)].
Serious Cardiovascular Reactions
Patients who develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease during STRATTERA treatment should stop STRATTERA and contact a health care provider [see Warnings and Precautions (5.3)].
Increased Blood Pressure or Heart Rate
STRATTERA can increase blood pressure and heart rate [see Warnings and Precautions (5.4)].
Emergence of New Psychotic or Manic Symptoms and Activation of Mania
Instruct patients and their caregivers to look for signs of activation of mania/hypomania and psychosis [see Warnings and Precautions (5.5)].
Aggression or Hostility
Instruct patients and their caregivers to contact their healthcare provider as soon as possible should they notice an increase in aggression or hostility [see Warnings and Precautions (5.7)].
Priapism
The parents or guardians of pediatric patients taking STRATTERA and adult patients taking STRATTERA should be instructed that priapism requires prompt medical attention [see Warnings and Precautions (5.10)].
Ocular Irritant
STRATTERA is an ocular irritant. STRATTERA capsules are not intended to be opened. In the event of capsule content coming in contact with the eye, the affected eye should be flushed immediately with water, and medical advice obtained. Hands and any potentially contaminated surfaces should be washed as soon as possible.
Drug-Drug Interactions
Patients should be instructed to consult a healthcare provider if they are taking or plan to take any prescription or over-the-counter drugs, dietary supplements, or herbal remedies [see Drug Interactions (7)].
Sexual Dysfunction
Advise patients that STRATTERA may impair sexual function. Advise patients if they experience sexual dysfunction, they should contact their health care provider [see Adverse Reactions (6.1)].
Pregnancy Registry
Advise patients that there is a pregnancy registry that monitors pregnancy outcomes in women exposed to atomoxetine during pregnancy [see Use in Specific Populations (8.1)].
Food
Patients may take STRATTERA with or without food.
Missed Dose
If patients miss a dose, they should be instructed to take it as soon as possible but should not take more than the prescribed total daily amount of STRATTERA in any 24-hour period.
Somnolence
The incidence of somnolence was higher in STRATTERA-treated patients than placebo-treated patients [see Adverse Reactions (6.1)]. Patients should be instructed to use caution when driving a car or operating hazardous machinery until they are reasonably certain that their performance is not affected by STRATTERA.
Marketed by: Lilly USA, LLC, Indianapolis, IN 46285, USA
Copyright © 2002, 2026, Eli Lilly and Company. All rights reserved.
STR-0006-USPI-20260629