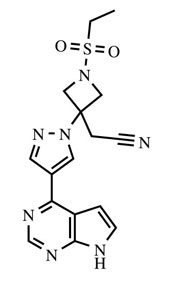
Other
SERIOUS INFECTIONS
Patients treated with OLUMIANT are at risk for developing serious infections that may lead to hospitalization or death [see Warnings and Precautions (5.1) and Adverse Reactions (6.1)]. Most patients with rheumatoid arthritis who developed these infections were taking concomitant immunosuppressants such as methotrexate or corticosteroids.
If a serious infection develops, interrupt OLUMIANT until the infection is controlled.
Reported infections include:
- Active tuberculosis, which may present with pulmonary or extrapulmonary disease. OLUMIANT should not be given to patients with active tuberculosis. Patients, except those with COVID-19, should be tested for latent tuberculosis before initiating OLUMIANT and during therapy. If positive, start treatment for latent infection prior to OLUMIANT use.
- Invasive fungal infections, including candidiasis and pneumocystosis. Patients with invasive fungal infections may present with disseminated, rather than localized, disease.
- Bacterial, viral, and other infections due to opportunistic pathogens.
- Avoid use of OLUMIANT in patients with active, serious or opportunistic infection, including localized infections. If a patient develops a serious infection hold treatment with OLUMIANT until the infection is controlled [see Warnings and Precautions (5.1)].
- Dosage modifications for patients with moderately to severely active rheumatoid arthritis or severe alopecia areata and cytopenias or anemia are described in Table 1.
- Monitor patients for signs and symptoms of new infections during treatment with OLUMIANT. The risks and benefits of treatment with OLUMIANT in COVID-19 patients with other concurrent infections should be considered [see Warnings and Precautions (5.1)].
- Dosage modifications for patients with COVID-19 and cytopenias are described in Table 2.
- OLUMIANT is not recommended for use in patients with severe (Child-Pugh C) hepatic impairment.
- No dose adjustment of OLUMIANT is necessary in patients with mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment.
- Interrupt OLUMIANT, if increases in ALT or AST are observed and drug-induced liver injury (DILI) is suspected, until the diagnosis of DILI is excluded [see Warnings and Precautions (5.9)].
- Dosage modifications for patients with COVID-19 and renal impairment are described in Table 4.
- It is not known if dosage adjustment is needed in patients with COVID-19 and severe (Child-Pugh C) hepatic impairment. OLUMIANT should only be used in patients with COVID-19 and severe hepatic impairment if the potential benefit outweighs the potential risk.
- No dose adjustment of OLUMIANT is necessary in patients with mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment.
- Interrupt OLUMIANT, if increases in ALT or AST are observed and DILI is suspected, until the diagnosis of DILI is excluded [see Warnings and Precautions (5.9)].
- OLUMIANT is not recommended for use in patients with severe (Child-Pugh C) hepatic impairment.
- No dose adjustment of OLUMIANT is necessary in patients with mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment.
- Interrupt OLUMIANT, if increases in ALT or AST are observed and DILI is suspected, until the diagnosis of DILI is excluded [see Warnings and Precautions (5.9)].
- Oral administration of dispersed tablets in water: For patients who are unable to swallow whole tablets, 1-mg, 2-mg, or 4-mg baricitinib tablet(s), or any combination of tablets necessary to achieve the desired dose up to 4-mg may be placed in a container with approximately 10 mL (5 mL minimum) of room temperature water, dispersed by gently swirling the tablet(s) and immediately taken orally. The container should be rinsed with an additional 10 mL (5 mL minimum) of room temperature water and the entire contents swallowed by the patient (Table 7).
- Administration via G tube: For patients with a G tube, 1-mg, 2-mg, or 4-mg baricitinib tablet(s), or any combination of tablets necessary to achieve the desired dose up to 4-mg may be placed in a container with approximately 15 mL (10 mL minimum) of room temperature water and dispersed with gentle swirling. Ensure the tablet(s) are sufficiently dispersed to allow free passage through the tip of the syringe. Withdraw entire contents from the container into an appropriate syringe and immediately administer through the gastric feeding tube. Rinse container with approximately 15 mL (10 mL minimum) of room temperature water, withdraw the contents into the syringe, and administer through the tube (Table 7).
- Administration via NG or OG tube: For patients with a NG or OG tube, 1-mg, 2-mg, or 4-mg baricitinib tablet(s), or a combination of tablets necessary to achieve the desired dose up to 4-mg may be placed into a container with approximately 30 mL of room temperature water and dispersed with gentle swirling. Ensure the tablet(s) are sufficiently dispersed to allow free passage through the tip of the syringe. Withdraw the entire contents from the container into an appropriate syringe and immediately administer through the enteral feeding tube. To avoid clogging of small diameter tubes (smaller than 12 Fr), the syringe can be held horizontally and shaken during administration. Rinse container with a sufficient amount (minimum of 15 mL) of room temperature water, withdraw the contents into the syringe, and administer through the tube (Table 7).
- During the 16-week treatment period, ALT elevations ≥3 times the ULN occurred in 1.0% of subjects treated with placebo, 1.7% of subjects treated with OLUMIANT 2 mg, and 1.4% of subjects treated with baricitinib 4 mg.
- During the 16-week treatment period, AST elevations ≥ 3 times the ULN occurred in 0.8% of subjects treated with placebo, 1.3% of subjects treated with OLUMIANT 2 mg, and 0.8% of subjects treated with baricitinib 4 mg.
- In a phase 3 study of DMARD naive subjects, during the 24-week treatment period, ALT and AST elevations ≥3 times the ULN occurred in 1.9% and 0% of subjects treated with methotrexate monotherapy, 1.9% and 1.3% of subjects treated with baricitinib 4 mg monotherapy, and 4.7% and 1.9% of subjects treated with baricitinib 4 mg plus methotrexate.
- Mean LDL cholesterol increased by 8 mg/dL in subjects treated with OLUMIANT 2 mg and by 14 mg/dL in subjects treated with baricitinib 4 mg.
- Mean HDL cholesterol increased by 7 mg/dL in subjects treated with OLUMIANT 2 mg and by 9 mg/dL in subjects treated with baricitinib 4 mg.
- The mean LDL/HDL ratio remained stable.
- Mean triglycerides increased by 7 mg/dL in subjects treated with OLUMIANT 2 mg and by 15 mg/dL in subjects treated with baricitinib 4 mg.
- Baricitinib 4 mg once daily (orally) for up to 14 days or until hospital discharge, whichever came first
- Remdesivir 200 mg on Day 1 and 100 mg once daily (via intravenous infusion) on subsequent days for a total treatment duration of 10 days or until hospital discharge
- Not hospitalized, no limitations on activities [OS 1];
- Not hospitalized, limitation on activities and/or requiring home oxygen [OS 2];
- Hospitalized, not requiring supplemental oxygen - no longer requires ongoing medical care [OS 3];
- Hospitalized, not requiring supplemental oxygen - requiring ongoing medical care (COVID-19 related or otherwise) [OS 4];
- Hospitalized, requiring supplemental oxygen [OS 5];
- Hospitalized, on non-invasive ventilation or high-flow oxygen devices [OS 6];
- Hospitalized, on invasive mechanical ventilation or ECMO [OS 7]; and
- Death [OS 8]
- corticosteroids (79% of subjects, mostly dexamethasone)
- remdesivir (19% of subjects)
The risks and benefits of treatment with OLUMIANT should be carefully considered prior to initiating therapy in patients with chronic or recurrent infection.
Patients should be closely monitored for the development of signs and symptoms of infection during and after treatment with OLUMIANT including the possible development of tuberculosis in patients who tested negative for latent tuberculosis infection prior to initiating therapy [see Warnings and Precautions (5.1)].
MORTALITY
In a large, randomized, postmarketing safety study in rheumatoid arthritis (RA) patients 50 years of age and older with at least one cardiovascular risk factor comparing another Janus kinase (JAK) inhibitor to tumor necrosis factor (TNF) blockers, a higher rate of all-cause mortality, including sudden cardiovascular death, was observed with the JAK inhibitor [see Warnings and Precautions (5.2)].
MALIGNANCIES
Lymphoma and other malignancies have been observed in patients treated with OLUMIANT. In RA patients treated with another JAK inhibitor, a higher rate of malignancies (excluding non-melanoma skin cancer (NMSC)) was observed when compared with TNF blockers. Patients who are current or past smokers are at additional increased risk [see Warnings and Precautions (5.3)].
MAJOR ADVERSE CARDIOVASCULAR EVENTS
MACE (defined as cardiovascular death, myocardial infarction, and stroke) may occur in patients treated with OLUMIANT. In RA patients 50 years of age and older with at least one cardiovascular risk factor treated with another JAK inhibitor, a higher rate of MACE was observed when compared with TNF blockers. Patients who are current or past smokers are at additional increased risk. Discontinue OLUMIANT in patients that have experienced a myocardial infarction or stroke [see Warnings and Precautions (5.4)].
THROMBOSIS
Thrombosis, including deep venous thrombosis and pulmonary embolism, has been observed at an increased incidence in patients treated with OLUMIANT compared to placebo. In addition, there were cases of arterial thrombosis. Many of these adverse events were serious and some resulted in death. In two studies of patients with RA with an increased risk of venous thrombosis, a higher rate of venous thrombosis was observed in patients treated with OLUMIANT compared to patients treated with TNF blockers. In RA patients 50 years of age and older with at least one cardiovascular risk factor treated with another JAK inhibitor, a higher rate of thrombosis was observed when compared with TNF blockers. Avoid OLUMIANT in patients at risk. Patients with symptoms of thrombosis should discontinue OLUMIANT and be promptly evaluated. [see Warnings and Precautions (5.5)].
Moderately to Severely Active Rheumatoid Arthritis and Severe Alopecia Areata
| Laboratory Analyte | Laboratory Analyte Value | Recommendation |
| Absolute Lymphocyte Count (ALC) | ≥500 cells/μL | Maintain dosage |
| <500 cells/μL | Interrupt OLUMIANT until ALC ≥500 cells/μL | |
| Absolute Neutrophil Count (ANC) | ≥1000 cells/μL | Maintain dosage |
| <1000 cells/μL | Interrupt OLUMIANT until ANC ≥1000 cells/μL | |
| Hemoglobin | ≥8 g/dL | Maintain dosage |
| <8 g/dL | Interrupt OLUMIANT until hemoglobin ≥8 g/dL |
COVID-19
| Laboratory Analyte | Laboratory Analyte Value | Recommendation |
| Absolute Lymphocyte Count (ALC) | ≥200 cells/μL | Maintain dosage |
| <200 cells/μL | Interrupt OLUMIANT until ALC ≥200 cells/μL | |
| Absolute Neutrophil Count (ANC) | ≥500 cells/μL | Maintain dosage |
| <500 cells/μL | Interrupt OLUMIANT until ANC ≥500 cells/μL |
Moderately to Severely Active Rheumatoid Arthritis
Renal Impairment
Dosage modifications for patients with rheumatoid arthritis and renal impairment are described in Table 3.
| Renal Impairment Stage | Estimated Glomerular Filtration Rate (eGFR) | Recommendation |
| Mild | 60 - <90 mL/minute/1.73 m2 | 2 mg once daily |
| Moderate | 30 - <60 mL/min/1.73 m2 | 1 mg once daily |
| Severe | <30 mL/minute/1.73 m2 | Not recommended |
Hepatic Impairment
COVID-19
Renal Impairment
| Renal Impairment Stage | Estimated Glomerular Filtration Rate (eGFR) | Recommendation |
| Mild | 60 - <90 mL/min/1.73 m2 | 4 mg once daily |
| Moderate | 30 - <60 mL/min/1.73 m2 | 2 mg once daily |
| Severe | 15 - <30 mL/min/1.73 m2 | 1 mg once daily |
| End Stage Renal Disease, Patients on Dialysis, or Acute Kidney Injury | <15 mL/min/1.73 m2 | Not recommended |
Hepatic Impairment
Severe Alopecia Areata
Renal Impairment
Dosage modifications for patients with severe alopecia areata and renal impairment are described in Table 5.
| Renal Impairment Stage | Estimated Glomerular Filtration Rate (eGFR) | Recommendation | |
| If the recommended dosage is 2 mg once daily | If the recommended dosage is 4 mg once daily | ||
| Mild | 60 – <90 mL/minute/1.73 m2 | Maintain dosage | |
| Moderate | 30 – <60 mL/min/1.73 m2 | Reduce to 1 mg once daily | Reduce to 2 mg once daily |
| Severe | <30 mL/minute/1.73 m2 | Not recommended | |
Hepatic Impairment
Moderately to Severely Active Rheumatoid Arthritis, COVID-19 or Severe Alopecia Areata
The recommended dosage of OLUMIANT in patients taking strong Organic Anion Transporter 3 (OAT3) inhibitors, such as probenecid, are shown in Table 6[see Drug Interactions (7.1) and Clinical Pharmacology (12.3)].
| Concomitant Medication | Recommendation |
Strong OAT3 inhibitors (e.g., probenecid) | If the recommended dosage is 4 mg once daily, reduce dosage to 2 mg once daily. |
| If the recommended dosage is 2 mg once daily, reduce dosage to 1 mg once daily. | |
| If the recommended dosage is 1 mg once daily, consider discontinuing probenecid. |
Preparation Instructions for Alternative Administration:
| Administration via | Dispersion Volume | Container Rinse Volume |
| Oral dispersion | 10 mL | 10 mL |
| G tube | 15 mL | 15 mL |
| NG tube or OG tube | 30 mL | 15 mL |
Tuberculosis
Evaluate patients for active infection prior to administration of OLUMIANT. OLUMIANT should not be given to patients with active TB.
Test patients with rheumatoid arthritis or alopecia areata for latent tuberculosis. Patients with rheumatoid arthritis or alopecia areata and latent tuberculosis (TB) should be treated with standard antimycobacterial therapy before initiating OLUMIANT. Consider anti-TB therapy prior to initiation of OLUMIANT in patients with a history of latent or active TB in whom an adequate course of treatment cannot be confirmed, and for patients with a negative test for latent TB but who have risk factors for TB infection. Consultation with a physician with expertise in the treatment of TB is recommended to aid in the decision about whether initiating anti-TB therapy is appropriate for an individual patient.
During OLUMIANT use, monitor patients for the development of signs and symptoms of TB, including patients who tested negative for latent TB infection prior to initiating therapy.
Viral Reactivation
Viral reactivation, including cases of herpes virus reactivation (e.g., herpes zoster), were reported in clinical studies with OLUMIANT. If a patient develops herpes zoster, interrupt OLUMIANT treatment until the episode resolves.
The impact of OLUMIANT on chronic viral hepatitis reactivation is unknown. Patients with evidence of active hepatitis B or C infection were excluded from clinical trials. In clinical trials in patients with rheumatoid arthritis or alopecia areata, patients who were positive for hepatitis C antibody but negative for hepatitis C virus RNA were permitted to enroll. Patients with positive hepatitis B surface antibody and hepatitis B core antibody, without hepatitis B surface antigen, were permitted to enroll; such patients should be monitored for expression of hepatitis B virus (HBV) DNA. Should HBV DNA be detected, consult with a hepatologist. Perform screening for viral hepatitis in accordance with clinical guidelines before starting therapy with OLUMIANT.
Non-melanoma skin cancers
Non-melanoma skin cancers (NMSCs) have been reported in patients treated with OLUMIANT. Periodic skin examination is recommended for patients who are at increased risk for skin cancer.
Neutropenia – Treatment with OLUMIANT was associated with an increased incidence of neutropenia (ANC less than 1000 cells/mm3) compared to placebo.
In patients with rheumatoid arthritis or alopecia areata, avoid initiation or interrupt OLUMIANT treatment in patients with an ANC less than 1000 cells/mm3.
In patients with COVID-19, there is limited information regarding use of OLUMIANT in patients with ANC less than 1000 cells/mm3. Avoid initiation or interrupt OLUMIANT treatment in patients with COVID-19 and an ANC less than 500 cells/mm3.
Evaluate at baseline and thereafter according to routine patient management. Adjust dosing based on ANC [see Dosage and Administration (2.1, 2.5) and Adverse Reactions (6.1)].
Lymphopenia – ALC less than 500 cells/mm3 were reported in OLUMIANT clinical trials. Lymphocyte counts less than the lower limit of normal were associated with infection in patients treated with OLUMIANT, but not placebo.
In patients with rheumatoid arthritis or alopecia areata, avoid initiation or interrupt OLUMIANT treatment in patients with an ALC less than 500 cells/mm3.
In patients with COVID-19, there is limited information regarding use of OLUMIANT in patients with ALC less than 200 cells/mm3. Avoid initiation or interrupt OLUMIANT treatment in patients with COVID-19 and an ALC less than 200 cells/mm3.
Evaluate at baseline and thereafter according to routine patient management. Adjust dosing based on ALC [see Dosage and Administration (2.1, 2.5)].
Anemia – Decreases in hemoglobin levels to less than 8 g/dL were reported in OLUMIANT clinical trials. In patients with rheumatoid arthritis or alopecia areata, avoid initiation or interrupt OLUMIANT treatment in patients with hemoglobin less than 8 g/dL. Evaluate at baseline and thereafter according to routine patient management. Adjust dosing based on hemoglobin levels [see Dosage and Administration (2.1, 2.5)].
In patients with COVID-19, there is limited information regarding use of OLUMIANT in patients with hemoglobin less than 8 g/dL.
Liver Enzyme Elevations – Treatment with OLUMIANT was associated with increased incidence of liver enzyme elevation compared to placebo. Increases of ALT ≥5 times the upper limit of normal (ULN) and increases of AST ≥10 times the ULN were observed in patients in OLUMIANT clinical trials. Evaluate at baseline and thereafter according to routine patient management. Prompt investigation of the cause of liver enzyme elevation is recommended to identify potential cases of drug-induced liver injury. If increases in ALT or AST are observed and drug-induced liver injury is suspected, interrupt OLUMIANT until this diagnosis is excluded [see Adverse Reactions (6.1)].
Lipid Elevations – Treatment with OLUMIANT was associated with increases in lipid parameters, including total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol. Assessment of lipid parameters should be performed approximately 12 weeks following OLUMIANT initiation in patients with rheumatoid arthritis or alopecia areata [see Adverse Reactions (6.1)]. Manage patients according to clinical guidelines for the management of hyperlipidemia.
Moderately to Severely Active Rheumatoid Arthritis
The safety of OLUMIANT was evaluated in six randomized double-blind placebo-controlled studies (three Phase 2, three Phase 3) and a long-term extension study in subjects with moderately to severely active RA. Subjects were randomized to placebo (1070 subjects), OLUMIANT 2 mg (479 subjects), or baricitinib 4 mg (997 subjects).
Subjects could be switched to baricitinib 4 mg from placebo or OLUMIANT 2 mg from as early as Week 12 depending on the study design. All subjects initially randomized to placebo were switched to baricitinib 4 mg by Week 24.
During the 16-week treatment period, adverse events leading to discontinuation of treatment were reported by 35 subjects (11.4 per 100 patient-years) treated with placebo, 17 subjects (12.1 per 100 patient-years) with OLUMIANT 2 mg, and 40 subjects (13.4 per 100 patient-years) treated with baricitinib 4 mg.
During 0 to 52-week exposure, adverse events leading to discontinuation of treatment were reported by 31 subjects (9.2 per 100 patient-years) with OLUMIANT 2 mg, and 92 subjects (10.2 per 100 patient-years) treated with baricitinib 4 mg.
Overall Infections – During the 16-week treatment period, infections were reported by 253 subjects (82.1 per 100 patient-years) treated with placebo, 139 subjects (99.1 per 100 patient-years) treated with OLUMIANT 2 mg, and 298 subjects (100.1 per 100 patient-years) treated with baricitinib 4 mg.
During 0 to 52-week exposure, infections were reported by 200 subjects (59.6 per 100 patients-years) treated with OLUMIANT 2 mg, and 500 subjects (55.3 per 100 patient-years) treated with baricitinib 4 mg.
In the 0 to 52-week exposure population, the most commonly reported infections with OLUMIANT were viral upper respiratory tract infection, upper respiratory tract infection, urinary tract infection, and bronchitis.
Serious Infections – During the 16-week treatment period, serious infections were reported in 13 subjects (4.2 per 100 patient-years) treated with placebo, 5 subjects (3.6 per 100 patient-years) treated with OLUMIANT 2 mg, and 11 subjects (3.7 per 100 patient-years) treated with baricitinib 4 mg.
During 0 to 52-week exposure, serious infections were reported in 14 subjects (4.2 per 100 patient-years) treated with OLUMIANT 2 mg and 32 subjects (3.5 per 100 patient-years) treated with baricitinib 4 mg.
In the 0 to 52-week exposure population, the most commonly reported serious infections with OLUMIANT were pneumonia, herpes zoster, and urinary tract infection [see Warnings and Precautions (5.1)].
Tuberculosis – During the 16-week treatment period, no events of tuberculosis were reported.
During 0 to 52-week exposure, events of tuberculosis were reported in 0 subjects treated with OLUMIANT 2 mg and 1 subject (0.1 per 100 patient-years) treated with baricitinib 4 mg [see Warnings and Precautions (5.1)].
Cases of disseminated tuberculosis were also reported.
Opportunistic Infections (excluding tuberculosis) – During the 16-week treatment period, opportunistic infections were reported in 2 subjects (0.6 per 100 patient-years) treated with placebo, 0 subjects treated with OLUMIANT 2 mg and 2 subjects (0.7 per 100 patient-years) treated with baricitinib 4 mg. During 0 to 52-week exposure, opportunistic infections were reported in 1 subject (0.3 per 100 patient-years) treated with OLUMIANT 2 mg and 5 subjects (0.6 per 100 patient-years) treated with baricitinib 4 mg [see Warnings and Precautions (5.1)].
Malignancies
During the 16-week treatment period, malignancies excluding non-melanoma skin cancers (NMSC) were reported in 0 subjects treated with placebo, 1 subject (0.7 per 100 patient-years) treated with OLUMIANT 2 mg, and 1 subject (0.3 per 100 patient-years) treated with baricitinib 4 mg.
During the 0 to 52-week treatment period, malignancies excluding NMSC were reported in 2 subjects (0.6 per 100 patient-years) treated with OLUMIANT 2 mg and 6 subjects (0.7 per 100 patient-years) treated with baricitinib 4 mg [see Warnings and Precautions (5.3)].
Thrombosis
Venous Thrombosis – During the 16-week treatment period, venous thromboses (deep vein thrombosis or pulmonary embolism) were reported in 0 subjects treated with placebo, 0 subjects treated with OLUMIANT 2 mg, and 5 subjects (1.7 per 100 patient-years) treated with baricitinib 4 mg. During the 0 to 52-week treatment period, venous thromboses were reported in 2 subjects (0.6 per 100 patient-years) treated with OLUMIANT 2 mg and 7 subjects (0.8 per 100 patient-years) treated with baricitinib 4 mg.
Arterial Thrombosis – During the 16-week treatment period, arterial thromboses were reported in 1 subject treated with placebo (0.3 per 100 patient-years), 2 subjects (1.4 per 100 patient-years) treated with OLUMIANT 2 mg, and 2 subjects (0.7 per 100 patient-years) treated with baricitinib 4 mg. During the 0 to 52-week treatment period, arterial thromboses were reported in 3 subjects (0.9 per 100 patient-years) treated with OLUMIANT 2 mg and 3 subjects (0.3 per 100 patient-years) treated with baricitinib 4 mg.
Laboratory Abnormalities
Neutropenia – During the 16-week treatment period, neutrophil counts below 1000 cells/mm3 occurred in 0% of subjects treated with placebo, 0.6% of subjects treated with OLUMIANT 2 mg, and 0.3% of subjects treated with baricitinib 4 mg. There were no neutrophil counts below 500 cells/mm3 observed in any treatment group [see Warnings and Precautions (5.1, 5.9)].
Platelet Elevations – During the 16-week treatment period, increases in platelet counts above 600,000 cells/mm3 occurred in 1.1% of subjects treated with placebo, 1.1% of subjects treated with OLUMIANT 2 mg, and 2.0% of subjects treated with baricitinib 4 mg. Mean platelet count increased by 3000 cells/mm3 at 16 weeks in subjects treated with placebo, by 15,000 cells/mm3 at 16 weeks in subjects treated with OLUMIANT 2 mg and by 23,000 cells/mm3 in subjects treated with baricitinib 4 mg.
Liver Enzyme Elevations – Events of increases in liver enzymes ≥3 times the ULN were observed in subjects treated with OLUMIANT [see Warnings and Precautions (5.9)].
Lipid Elevations – In controlled clinical trials, OLUMIANT treatment was associated with dose-related increases in lipid parameters including total cholesterol, triglycerides, LDL cholesterol, and HDL cholesterol. Elevations were observed at 12 weeks and remained stable thereafter. During the 12-week treatment period, changes in lipid parameters are summarized below:
[See Warnings and Precautions (5.9)].
Creatine Phosphokinase (CPK) – OLUMIANT treatment was associated with increases in CPK within one week of starting OLUMIANT and plateauing after 8 to 12 weeks. At 16 weeks, the mean change in CPK for OLUMIANT 2 mg and baricitinib 4 mg was 37 IU/L and 52 IU/L, respectively.
Creatinine – In controlled clinical trials, dose-related increases in serum creatinine were observed with OLUMIANT treatment. At 52 weeks, the mean increase in serum creatinine was less than 0.1 mg/dL with baricitinib 4 mg. The clinical significance of the observed serum creatinine increases is unknown.
Other Adverse Reactions
Other adverse reactions are summarized in Table 8.
a Includes acute sinusitis, acute tonsillitis, chronic tonsillitis, epiglottitis, laryngitis, nasopharyngitis, oropharyngeal pain, pharyngitis, pharyngotonsillitis, rhinitis, sinobronchitis, sinusitis, tonsillitis, tracheitis, and upper respiratory tract infection. | |||
b Includes eczema herpeticum, genital herpes, herpes simplex, ophthalmic herpes simplex, and oral herpes. | |||
| Events | Weeks 0-16 | ||
| Placebo | OLUMIANT 2 mg | OLUMIANT 4 mg | |
| n=1070 (%) | n=479 (%) | n=997 (%) | |
| Upper respiratory tract infectionsa | 11.7 | 16.3 | 14.7 |
| Nausea | 1.6 | 2.7 | 2.8 |
| Herpes simplexb | 0.7 | 0.8 | 1.8 |
| Herpes zoster | 0.4 | 1.0 | 1.4 |
Additional adverse drug reactions occurring in fewer than 1% of subjects: acne.
COVID-19
The safety of OLUMIANT was evaluated in two randomized, double-blind, placebo-controlled clinical trials of hospitalized adults with COVID-19 for up to 29 days, in which 1307 subjects received at least one dose of OLUMIANT 4 mg once daily, and 1310 subjects received placebo, for up to 14 days or until hospital discharge, whichever occurred first. In these studies, prophylaxis for venous thromboembolic event (VTEs) was recommended or required for all subjects unless a major contraindication was noted.
Overall, the safety profile observed in subjects with COVID-19 treated with OLUMIANT was consistent with the safety profile in subjects with rheumatoid arthritis.
Overall Infections – During the first 29 days of the randomized clinical trials, infections were reported in 194 subjects (14.8%) treated with OLUMIANT 4 mg and by 219 subjects (16.7%) treated with placebo. The most commonly reported infection with OLUMIANT was pneumonia (3.1%).
Serious Infections – During the first 29 days of the randomized clinical trials, serious infections were reported in 98 subjects (7.5%) treated with OLUMIANT 4 mg and 120 subjects (9.2%) treated with placebo. The most commonly reported serious infections with OLUMIANT were COVID-19 pneumonia (2.1%) and septic shock (2.1%).
Opportunistic Infections – During the first 29 days of the randomized clinical trials, opportunistic infections were reported in 12 subjects (0.9%) treated with OLUMIANT 4 mg and 14 subjects (1.1%) treated with placebo. Tuberculosis was reported in 1 subject (0.1%) treated with OLUMIANT 4 mg and 0 subjects treated with placebo.
Venous Thrombosis Events – During the first 29 days of the randomized clinical trials, pulmonary embolism was reported in 20 subjects (1.5%) treated with OLUMIANT 4 mg and 11 subjects (0.8%) treated with placebo. Deep vein thrombosis was reported in 20 subjects (1.5%) treated with OLUMIANT 4 mg and 18 subjects (1.4%) treated with placebo.
Adverse drug reactions in greater than or equal to 1% of subjects in trials for COVID-19 are summarized in Table 9.
a As assessed by measured values within the clinical trial database. Frequencies are based on shifts from pre-treatment to post-treatment (with number at risk as the denominator), except for ALT and AST for which frequencies are based on observed elevation during treatment. | ||
b Creatine phosphokinase frequencies presented in the table were available for a single trial (COVID II) in subjects with COVID-19 and do not represent integrated data. | ||
| Placebo N = 1310 n (%) | OLUMIANT 4 mg N = 1307 n (%) | |
| ALT ≥3 x ULNa | 201(16.0) | 230 (18.1) |
| AST ≥3 x ULNa | 117 (9.4) | 149 (11.8) |
| Thrombocytosis >600,000 cells/mm3a | 34 (4.6) | 59 (7.9) |
| Creatine phosphokinase (CPK) >5 x ULNa, b | 38 (4.7) | 36 (4.5) |
| Neutropenia <1000 cells/mm3a | 22 (1.8) | 26 (2.2) |
| Deep vein thrombosis | 18 (1.4) | 20 (1.5) |
| Pulmonary embolism | 11 (0.8) | 20 (1.5) |
| Urinary tract infection | 13 (1.0) | 19 (1.5) |
Severe Alopecia Areata
Adults with Severe Alopecia Areata
The safety of OLUMIANT was evaluated in two placebo-controlled trials in adults with severe alopecia areata [see Clinical Studies (14)]. Subjects were randomized to placebo (371 subjects), OLUMIANT 2 mg (365 subjects), or OLUMIANT 4 mg (540 subjects). Of these, a total of 845 subjects were treated with OLUMIANT for at least 1 year.
Table 10 summarizes adverse reactions that occurred at a frequency of at least 1% in subjects treated with OLUMIANT 2 mg once daily or OLUMIANT 4 mg once daily and more frequently than in subjects receiving placebo during the 36-week placebo-controlled period of the severe alopecia areata clinical trials.
a %-study size adjusted percentages. | |||
b URTI includes: acute sinusitis, influenza, laryngitis, nasopharyngitis, oropharyngeal pain, pharyngitis, pharyngotonsillitis, rhinitis, sinusitis, tonsillitis, upper respiratory tract infection, viral upper respiratory tract infection, viral sinusitis, viral pharyngitis, respiratory tract infection viral, rhinovirus infection and adenoiditis | |||
c Acne includes: acne and dermatitis acneiform. | |||
d Hyperlipidemia includes: hyperlipidemia, hypercholesterolemia, hypertriglyceridemia, dyslipidemia, lipids increased, low density lipoprotein increased, blood cholesterol increased, and blood triglycerides increased. | |||
e UTI includes: cystitis, urinary tract infection, white blood cells urine positive, urinary tract infection bacterial, and pyelonephritis. | |||
f Liver enzyme elevations includes: transaminases increased, aspartate aminotransferase increased, alanine aminotransferase increased, hepatic enzyme increased, gamma-glutamyl transferase increased, and hepatic function abnormal. | |||
g Folliculitis was most commonly localized in the scalp region associated with hair regrowth | |||
h LRTI includes: bronchitis, bronchiolitis, lower respiratory tract infection, pneumonia, COVID-19 pneumonia, and respiratory tract infection. | |||
i Genital Candida infections includes: vulvovaginal candidiasis, vulvovaginal mycotic infection, and genital infection fungal. | |||
j Neutropenia includes: neutropenia and neutrophil count decreased. | |||
k Abdominal pain includes: abdominal pain, abdominal pain lower, abdominal pain upper, and abdominal discomfort. | |||
| Adverse Reaction | Weeks 0-36 | ||
| Placebo | OLUMIANT 2 mg | OLUMIANT 4 mg | |
| N=371 (%)a | N=365 (%)a | N=540 (%)a | |
| Upper respiratory tract infectionsb (URTI) | 19.9 | 18.4 | 21.3 |
| Headache | 5.4 | 5.5 | 6.6 |
| Acnec | 2.2 | 5.8 | 5.9 |
| Hyperlipidemiad | 3.0 | 3.6 | 5.9 |
| Blood creatine phosphokinase increased | 1.3 | 0.8 | 4.3 |
| Urinary tract infections (UTI)e | 2.2 | 3.8 | 3.7 |
| Liver enzyme elevationsf | 2.4 | 1.1 | 3.0 |
| Folliculitisg | 0.8 | 1.4 | 2.2 |
| Fatigue | 1.1 | 0.8 | 2.2 |
| Lower respiratory tract infections (LRTI)h | 0.8 | 2.2 | 2.0 |
| Nausea | 1.6 | 2.7 | 2.0 |
| Genital Candida infectionsi | 0.3 | 2.2 | 1.3 |
| Anemia | 0.3 | 0.3 | 1.3 |
| Neutropeniaj | 0.8 | 0.3 | 1.3 |
| Abdominal paink | 2.2 | 3.8 | 0.9 |
| Herpes zoster | 0.5 | 1.4 | 0.9 |
| Weight increased | 0.3 | 1.6 | 0.9 |
In subjects treated with any dose of baricitinib, adverse reactions that occurred in fewer than 1% of subjects include arterial thrombosis, B cell lymphoma, lymphopenia, and fungal skin infections.
Additional adverse reactions observed after Week 52: venous thromboembolic events (VTE), including deep venous thrombosis (DVT) and pulmonary embolism (PE), and malignancy including non-melanoma skin cancer.
Overall, the adverse reactions observed in subjects with severe alopecia areata treated with OLUMIANT were consistent with the adverse reactions in subjects with moderately to severely active rheumatoid arthritis.
Pediatric Subjects 12 Years of Age and Older with Severe Alopecia Areata
The safety of OLUMIANT was evaluated in pediatric subjects 12 years of age and older who weigh at least 30 kg with severe alopecia areata in a randomized, double-blind, placebo-controlled clinical trial [see Clinical Studies (14)]. Subjects were randomized to placebo (88 subjects), OLUMIANT 2 mg (83 subjects), or OLUMIANT 4 mg (85 subjects). Overall, the safety profile observed in pediatric subjects 12 years of age and older with severe alopecia areata treated with OLUMIANT is consistent with the safety profile in adults with severe alopecia areata.
In the open-label extension period of this trial, 316 pediatric subjects 12 years of age and older were treated with OLUMIANT 2 mg or 4 mg for at least 1 year and the safety profile remained consistent with that observed in adults with severe AA [see Use in Specific Populations (8.4)].
Pregnancy Exposure Registry
There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to OLUMIANT during pregnancy. Healthcare providers may encourage pregnant women exposed to OLUMIANT to enroll in the OLUMIANT pregnancy registry by calling 1-800-284-1695 or by visiting https://pregnancyregistry.lilly.com.
Risk Summary
Based on the findings from animal reproduction studies, OLUMIANT may cause fetal harm during pregnancy. Available data from clinical trials and postmarketing case reports with OLUMIANT exposure in pregnancy are insufficient to inform a drug-associated risk for major birth defects, miscarriage, or other adverse maternal or fetal outcomes. There are no human data on chronic baricitinib exposure throughout pregnancy. There are risks to the mother and the fetus associated with rheumatoid arthritis in pregnancy (see Clinical Considerations). Consider the risks and benefits with chronic use of OLUMIANT during pregnancy.
In animal embryo-fetal development studies, oral baricitinib administration to pregnant rats and rabbits at exposures equal to and greater than approximately 11 and 46 times the maximum recommended human dose (MRHD) of 4 mg/day, respectively, resulted in reduced fetal body weights, increased embryolethality (rabbits only), and dose-related increases in skeletal malformations. No developmental toxicity was observed in pregnant rats and rabbits treated with oral baricitinib during organogenesis at approximately 2 and 7 times the exposure at the MRHD, respectively. In a pre- and post-natal development study in pregnant female rats, oral baricitinib administration at exposures approximately 24 times the MRHD resulted in reduction in pup viability (increased incidence of stillborn pups and early neonatal deaths), decreased fetal birth weight, reduced fetal body weight gain, decreased cytotoxic T cells on post-natal day (PND) 35 with evidence of recovery by PND 65, and developmental delays that might be attributable to decreased body weight gain. No developmental toxicity was observed at an exposure approximately 5 times the exposure at the MRHD (see Data).
The background risks of major birth defects and miscarriage for the indicated population(s) are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with rheumatoid arthritis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth.
Data
Animal Data
In an embryofetal development study in pregnant rats, dosed orally during the period of organogenesis from gestation days 6 to 17, baricitinib was teratogenic (skeletal malformations that consisted of bent limb bones and rib anomalies) at exposures equal to or greater than approximately 11 times the MRHD (on an AUC basis at maternal oral doses of 10 mg/kg/day and higher). No developmental toxicity was observed in rats at an exposure approximately 2 times the MRHD (on an AUC basis at a maternal oral dose of 2 mg/kg/day).
In an embryofetal development study in pregnant rabbits, dosed orally during the period of organogenesis from gestation days 7 to 20, embryolethality, decreased fetal body weights, and skeletal malformations (rib anomalies) were observed in the presence of maternal toxicity at an exposure approximately 46 times the MRHD (on an AUC basis at a maternal oral dose of 30 mg/kg/day). Embryolethality consisted of increased post-implantation loss that was due to elevated incidences of both early and late resorptions. No developmental toxicity was observed in rabbits at an exposure approximately 7 times the MRHD (on an AUC basis at a maternal oral dose of 10 mg/kg/day).
In a pre- and post-natal development study in pregnant female rats dosed orally from gestation day 6 through lactation day 20, adverse findings observed in pups included decreased survival from birth to post-natal day 4 (due to increased stillbirths and early neonatal deaths), decreased birth weight, decreased body weight gain during the pre-weaning phase, increased incidence of malrotated forelimbs during the pre-weaning phase, and decreased cytotoxic T cells on PND 35 with recovery by PND 65 at exposures approximately 24 times the MRHD (on an AUC basis at a maternal oral dose of 25 mg/kg/day). Developmental delays (that may be secondary to decreased body weight gain) were observed in males and females at exposures approximately 24 times the MRHD (on an AUC basis at a maternal oral dose of 25 mg/kg/day). These findings included decreased forelimb and hindlimb grip strengths, and delayed mean age of sexual maturity. No developmental toxicity was observed in rats at an exposure approximately 5 times the MRHD (on an AUC basis at a maternal oral dose of 5 mg/kg/day).
Risk Summary
No information is available on the presence of OLUMIANT in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production. Baricitinib is present in the milk of lactating rats (see Data). When a drug is present in animal milk, it is likely that the drug will be present in human milk. Because of the potential for serious adverse reactions in nursing infants advise women not to breastfeed during treatment with OLUMIANT and for 4 days after the last dose (approximately 5 to 6 elimination half-lives).
Data
A single oral dose of 25 mg/kg radiolabeled baricitinib was administered to lactating female Sprague-Dawley rats on post-partum day 13. Drug exposure was approximately 45-fold greater in milk than in plasma based on AUC0-t values. The concentration of baricitinib in animal milk does not necessarily predict the concentration of the drug in human milk.
Contraception
Based on animal studies, OLUMIANT may cause fetal harm when administered during pregnancy [see Use in Specific Populations (8.1)]. Consider pregnancy planning and prevention for females of reproductive potential.
Moderately to Severely Active Rheumatoid Arthritis and Severe Alopecia Areata – The recommended dosage of OLUMIANT in patients with moderate renal impairment (estimated glomerular filtration rate (GFR) between 30 and <60 mL/min/1.73 m2) should be reduced by half the recommended dose. OLUMIANT is not recommended for use in patients with moderately to severely active rheumatoid arthritis or severe alopecia areata and severe renal impairment (estimated GFR of less than 30 mL/min/1.73 m2) [see Dosage and Administration (2.6) and Clinical Pharmacology (12.3)].
COVID-19 – The recommended dosage of OLUMIANT in patients with moderate renal impairment (estimated GFR between 30 and <60 mL/min/1.73 m2) or severe renal impairment (estimated GFR between 15 and <30 mL/min/1.73 m2) is 2 mg once daily and 1 mg once daily, respectively. OLUMIANT is not recommended for use in patients who are on dialysis, have end-stage renal disease (ESRD), or with estimated GFR of <15 mL/min/1.73 m2 [see Dosage and Administration (2.6) and Clinical Pharmacology (12.3)].
Baricitinib inhibition of IL-6 induced STAT3 phosphorylation – Baricitinib administration resulted in a dose dependent inhibition of IL-6 induced STAT3 phosphorylation in whole blood from healthy subjects with maximal inhibition observed approximately 1 hour after dosing, which returned to near baseline by 24 hours. Similar levels of inhibition were observed using either IL-6 or TPO as the stimulus.
Immunoglobulins – Mean serum IgG, IgM, and IgA values decreased by 12 weeks after starting treatment with OLUMIANT, and remained stable through at least 52 weeks. For most subjects, changes in immunoglobulins occurred within the normal reference range.
C-reactive protein – In subjects with rheumatoid arthritis, decreases in serum C-reactive protein (CRP) were observed as early as one week after starting treatment with OLUMIANT and were maintained throughout dosing.
Cardiac Electrophysiology – At a dose 10 times the maximum recommended dose, baricitinib does not prolong the QT interval to any clinically relevant extent.
Absorption – The absolute bioavailability of baricitinib is approximately 80%. An assessment of food effects in healthy subjects showed that a high-fat meal decreased the mean AUC and Cmax of baricitinib by approximately 11% and 18%, respectively, and delayed the tmax by 0.5 hours. Administration with meals is not associated with a clinically relevant effect on exposure. In clinical studies, OLUMIANT was administered without regard to meals.
Distribution – After intravenous administration, the volume of distribution is 76 L, indicating distribution of baricitinib into tissues. Baricitinib is approximately 50% bound to plasma proteins and 45% bound to serum proteins. Baricitinib is a substrate of the Pgp, BCRP, OAT3 and MATE2-K transporters, which play roles in drug distribution.
Elimination
Moderately to Severely Active Rheumatoid Arthritis and Severe Alopecia Areata: The total body clearance of baricitinib is 8.9 L/h in subjects with moderately to severely active rheumatoid arthritis and 11 L/h in subjects with severe alopecia areata. Elimination half-life in subjects with moderately to severely active rheumatoid arthritis and severe alopecia areata is approximately 12 to 16 hours.
COVID-19: The total body clearance and half-life of baricitinib is 14.2 L/h and 10.8 hours, respectively, in subjects with COVID-19 who are intubated and have baricitinib administered via NG or OG tube.
Metabolism – Approximately 6% of the orally administered baricitinib dose is identified as metabolites (three from urine and one from feces), with CYP3A4 identified as the main metabolizing enzyme. No metabolites of baricitinib were quantifiable in plasma.
Excretion – Renal elimination is the principal clearance mechanism for baricitinib through filtration and active secretion as baricitinib is identified as a substrate of OAT3, Pgp, BCRP and MATE2-K from in vitro studies. In a clinical pharmacology study, approximately 75% of the administered dose was eliminated in the urine, while about 20% of the dose was eliminated in the feces. Baricitinib was excreted predominantly as unchanged drug in urine (69%) and feces (15%).
Specific Populations
Effects of Body Weight, Gender, Race, and Age
Body weight, gender, race, ethnicity, and age did not have a clinically relevant effect on the PK (AUC and Cmax) of baricitinib (Figure 1). The mean effects of intrinsic factors on PK parameters (AUC and Cmax) were generally within the inter-subject PK variability of baricitinib. The inter-subject variabilities (% coefficients of variation) in AUC and Cmax of baricitinib are approximately 41% and 22%, respectively, in subjects with rheumatoid arthritis [see Use in Specific Populations (8.5)].
Pediatric Patients 12 Years of Age and Older with Severe Alopecia Areata: The PK exposure of baricitinib is similar for pediatric subjects 12 years of age and older and adults with severe alopecia areata upon receiving a 2 mg or 4 mg dose.
Patients with Renal Impairment
Baricitinib systemic exposure in AUC was increased by 1.41-, 2.22-, 4.05- and 2.41-fold for mild (60 – <90 mL/minute/1.73 m2), moderate (30 – <60 mL/min/1.73 m2), severe (<30 mL/minute/1.73 m2), and ESRD (with hemodialysis) renal impairment sub-groups, respectively, compared to subjects with normal renal function. The corresponding values for increase in Cmax were 1.16-, 1.46-, 1.40- and 0.88-fold, respectively (Figure 1) [see Use in Specific Populations (8.7)].
Patients with Hepatic Impairment
Baricitinib systemic exposure and Cmax increased by 1.19- and 1.08-fold for the moderate (Child-Pugh B) hepatic impairment group, respectively, compared to subjects with normal hepatic function (Figure 1) [see Use in Specific Populations (8.6)].
Figure 1: Impact of Intrinsic Factors on OLUMIANT Pharmacokineticsa, b

Figure 1 (Olumiant Uspi F1 V3)
a Reference values for weight, age, gender, and race comparisons are 70 kg, 54 years, male, and white, respectively; reference groups for renal and hepatic impairment are subjects with normal renal and hepatic function, respectively.
b Effects of renal and hepatic impairment on baricitinib exposure were summarized from dedicated renal and hepatic impairment studies, respectively. Effects of other intrinsic factors on baricitinib exposure were summarized from population PK analysis.
c The recommended dose for subjects with COVID-19 and severe renal impairment (eGFR 15 - <30 mL/min/1.73m2) is 1 mg once daily. OLUMIANT is not recommended for use in subjects with COVID-19 who are on dialysis, have end-stage renal disease (ESRD), or acute kidney injury (eGFR <15 mL/min/1.73m2). [see Dosage and Administration (2.6)]
Drug Interactions
Potential for Baricitinib to Influence the PK of Other Drugs
In vitro, baricitinib did not significantly inhibit or induce the activity of cytochrome P450 enzymes (CYPs 3A, 1A2, 2B6, 2C8, 2C9, 2C19, and 2D6). In clinical pharmacology studies, there were no clinically meaningful changes in the pharmacokinetics (PK) of simvastatin, ethinyl estradiol, or levonorgestrel (CYP3A substrates) when co-administered with baricitinib.
In vitro studies suggest that baricitinib is not an inhibitor of the transporters, P-glycoprotein (Pgp) or Organic Anion Transporting Polypeptide (OATP) 1B1. In vitro data indicate baricitinib does inhibit organic anionic transporter (OAT) 1, OAT2, OAT3, organic cationic transporter (OCT) 1, OCT2, OATP1B3, Breast Cancer Resistance Protein (BCRP) and Multidrug and Toxic Extrusion Protein (MATE) 1 and MATE2-K, but clinically meaningful changes in the pharmacokinetics of drugs that are substrates for these transporters are unlikely. In clinical pharmacology studies there were no clinically meaningful effects on the PK of digoxin (Pgp substrate) or methotrexate (substrate of several transporters) when co-administered with baricitinib.
Exposure changes of drugs following co-administration with baricitinib are shown in Figure 2.
Figure 2: Impact of OLUMIANT on the Pharmacokinetics of Other Drugsa
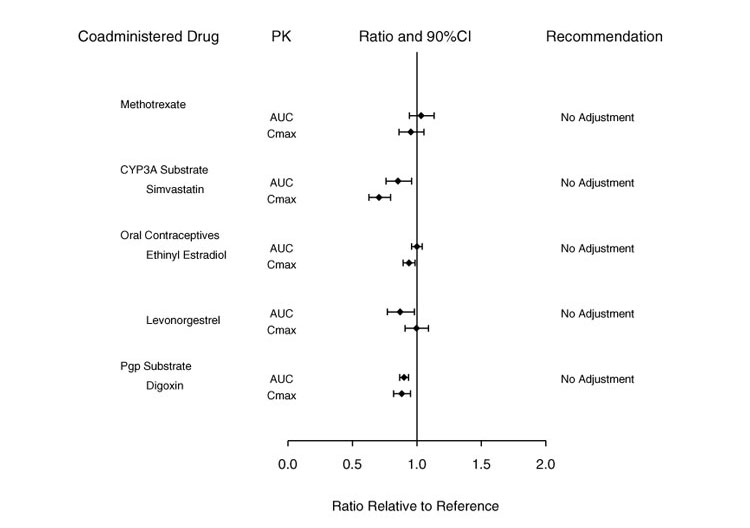
Figure 2 (Olumiant Uspi F2 V1)
a Reference group is administration of concomitant drug alone.
Potential for Other Drugs to Influence the PK of Baricitinib
In vitro studies suggest that baricitinib is a CYP3A4 substrate. In clinical pharmacology studies there was no effect on the PK of baricitinib when co-administered with ketoconazole (CYP3A inhibitor). There were no clinically meaningful changes in the PK of baricitinib when co-administered with fluconazole (CYP3A/CYP2C19/CYP2C9 inhibitor) or rifampin (CYP3A inducer).
In vitro studies suggest that baricitinib is a substrate for OAT3, Pgp, BCRP and MATE2-K. In a clinical study, probenecid administration (strong OAT3 inhibitor) resulted in an approximately 2-fold increase in baricitinib AUC0-∞ with no effect on Cmax and tmax [see Dosage and Administration (2.7) and Drug Interactions (7.1)]. However, simulations with diclofenac and ibuprofen (OAT3 inhibitors with less inhibition potential) predicted minimal effect on the PK of baricitinib. In clinical pharmacology studies there was no clinically meaningful effect on the PK of baricitinib when co-administered with cyclosporine (Pgp and BCRP inhibitor). Co-administration with methotrexate (substrate of several transporters) did not have a clinically meaningful effect on the PK of baricitinib.
Exposure changes of baricitinib following co-administration with CYP inhibitors or inducers, transporter inhibitors, as well as methotrexate and the proton pump inhibitor, omeprazole, are shown in Figure 3.
Figure 3: Impact of Other Drugs on the Pharmacokinetics of OLUMIANTb

Figure 3 (Olumiant Uspi F3 V3)
a Values are based on simulated studies.
b Reference group is administration of baricitinib alone.
Dose-Ranging Studies
The dose-ranging studies RA-1 (NCT01185353) and RA-2 (NCT01469013) included a 12-week randomized comparison of baricitinib 1, 2, 4, and 8 mg orally once daily versus placebo in 301 and 145 subjects, respectively.
The results from the dose-ranging studies are shown in Table 11. In dose-ranging Study RA-1, the observed ACR response was similar for baricitinib 1 and 2 mg daily and for baricitinib 4 and 8 mg daily, with the highest response for baricitinib 8 mg daily. In dose-ranging Study RA-2, there was not a clear trend of dose response, with similar response rates for 1 mg and 4 mg and 2 mg and 8 mg.
| % ACR20 Responders | |||||
| Dose-Ranging Study | Placebo | OLUMIANT 1 mg daily | OLUMIANT 2 mg daily | OLUMIANT 4 mg daily | OLUMIANT 8 mg daily |
| RA-1 (N=301) | 41 | 57 | 54 | 75 | 78 |
| RA-2 (N=145) | 31 | 67 | 83 | 67 | 88 |
Confirmatory Studies
The efficacy and safety of OLUMIANT 2 mg once daily was assessed in two confirmatory phase 3 trials. These trials were randomized, double-blind, multicenter studies in subjects with active rheumatoid arthritis diagnosed according to American College of Rheumatology (ACR)/European League Against Rheumatism 2010 criteria. Subjects over 18 years of age were eligible if at least 6 tender and 6 swollen joints were present at baseline. The two studies (Studies RA-3 and RA-4) evaluated OLUMIANT 2 mg and baricitinib 4 mg.
Study RA-3 (NCT01721057) was a 24-week trial in 684 subjects with moderately to severely active rheumatoid arthritis who had an inadequate response or intolerance to conventional DMARDs (cDMARDs). Subjects received OLUMIANT 2 mg or 4 mg once daily or placebo added to existing background cDMARD treatment. From Week 16, non-responding subjects could be rescued to receive baricitinib 4 mg once daily. The primary endpoint was the proportion of subjects who achieved an ACR20 response at Week 12.
Study RA-4 (NCT01721044) was a 24-week trial in 527 subjects with moderately to severely active rheumatoid arthritis who had an inadequate response or intolerance to 1 or more TNF inhibitor therapies with or without other biologic DMARDs (TNFi-IR). Subjects received OLUMIANT 2 mg or baricitinib 4 mg once daily or placebo added to background cDMARD treatment. From Week 16, non-responding subjects could be rescued to receive baricitinib 4 mg once daily. The primary endpoint was the proportion of subjects who achieved an ACR20 response at Week 12.
Clinical Response
The percentages of OLUMIANT-treated subjects achieving ACR20, ACR50, and ACR70 responses, and Disease Activity Score (DAS28-CRP) <2.6 in Studies RA-3 and RA-4 are shown in Table 12.
Subjects treated with OLUMIANT had higher rates of ACR response and DAS28-CRP <2.6 versus placebo-treated subjects at Week 12 (Studies RA-3 and RA-4) (Table 12).
In Study RA-4, higher ACR20 response rates (Figure 4) were observed as early as 1 week with OLUMIANT 2 mg versus placebo.
In Study RA-4, the proportions of subjects achieving DAS28-CRP <2.6 who had at least 3 active joints at the end of Week 24 were 18.2% and 10.5%, in the placebo and OLUMIANT 2 mg arms, respectively.
a Subjects who were rescued or discontinued treatment were considered as non-responders in the analyses. | ||||
b 95% confidence interval (CI) for the difference (∆) in response rate between OLUMIANT treatment and placebo (Study RA-3, Study RA-4). | ||||
| Percent of Subjects | ||||
| cDMARD-IR | TNFi-IR | |||
| Study RA-3 | Study RA-4 | |||
| Placebo + cDMARDs | OLUMIANT 2 mg/day + cDMARDs ∆ (95% CI)b | Placebo + cDMARDs | OLUMIANT 2 mg/day + cDMARDs ∆ (95% CI)b | |
| N | 228 | 229 | 176 | 174 |
| ACR 20 | ||||
| Week 12 % | 39 | 66 27 (18, 35) | 27 | 49 22 (12, 32) |
| Week 24 % | 42 | 61 19 (10, 28) | 27 | 45 18 (8, 27) |
| ACR 50 | ||||
| Week 12 % | 13 | 34 21 (13, 28) | 8 | 20 12 (5, 19) |
| Week 24 % | 21 | 41 20 (12, 28) | 13 | 23 10 (2, 18) |
| ACR 70 | ||||
| Week 12 % | 3 | 18 15 (9, 20) | 2 | 13 11 (5, 16) |
| Week 24 % | 8 | 25 17 (11, 24) | 3 | 13 10 (4, 16) |
| DAS28-CRP<2.6 | ||||
| Week 12 % | 9 | 26 (10, 24) | 4 | 11 (2, 12) |
| Week 24 % | 11 | 31 (13, 27) | 6 | 11 (-1, 11) |
The effects of OLUMIANT treatment on the components of the ACR response criteria for Studies RA-3 and RA-4 are shown in Table 13.
a Data shown are mean (standard deviation). | ||||
b Visual analog scale: 0=best, 100=worst. | ||||
c Health Assessment Questionnaire–Disability Index: 0=best, 3=worst; 20 questions; 8 categories: dressing and grooming, arising, eating, walking, hygiene, reach, grip, and activities. | ||||
| cDMARD-IR | TNFi-IR | |||
| Study RA-3 | Study RA-4 | |||
| Placebo + cDMARDs | OLUMIANT 2 mg/day + cDMARDs | Placebo + cDMARDs | OLUMIANT 2 mg/day + cDMARDs | |
| N | 228 | 229 | 176 | 174 |
| Number of Tender Joints (0-68) | ||||
| Baseline | 24 (15) | 24 (14) | 28 (16) | 31 (16) |
| Week 12 | 15 (14) | 11 (13) | 20 (16) | 19 (18) |
| Number of Swollen Joints (0-66) | ||||
| Baseline | 13 (7) | 14 (9) | 17 (11) | 19 (12) |
| Week 12 | 8 (8) | 5 (6) | 12 (10) | 10 (12) |
| Painb | ||||
| Baseline | 57 (23) | 60 (21) | 65 (19) | 62 (22) |
| Week 12 | 43 (24) | 34 (25) | 55 (25) | 46 (28) |
| Patient Global Assessmentb | ||||
| Baseline | 60 (21) | 62 (20) | 66 (19) | 67 (19) |
| Week 12 | 44 (23) | 36 (25) | 56 (25) | 46 (26) |
| Physician Global Assessmentb | ||||
| Baseline | 62 (17) | 64 (17) | 67 (19) | 67 (17) |
| Week 12 | 41 (24) | 33 (22) | 50 (26) | 36 (24) |
| Disability Index (HAQ-DI)c | ||||
| Baseline | 1.50 (0.60) | 1.51 (0.62) | 1.78 (0.57) | 1.71 (0.55) |
| Week 12 | 1.17 (0.62) | 0.96 (0.69) | 1.59 (0.68) | 1.31 (0.72) |
| hsCRP (mg/L) | ||||
| Baseline | 17.7 (20.4) | 18.2 (21.5) | 20.6 (25.3) | 19.9 (22.5) |
| Week 12 | 17.2 (19.3) | 8.6 (14.6) | 19.9 (23.0) | 13.5 (20.1) |
Figure 4: Percent of RA Subjects Who Achieved ACR20 in Study RA-4

Figure 4 (Olumiant Uspi F4 V2)
Physical Function Response
Improvement in physical function was measured by the Health Assessment Questionnaire-Disability Index (HAQ-DI). Subjects receiving OLUMIANT 2 mg demonstrated greater improvement from baseline in physical functioning compared to placebo at Week 24. The mean difference (95% CI) from placebo in HAQ-DI change from baseline at Week 24 was -0.24 (-0.35, -0.14) in Study RA-3 and -0.23 (-0.35, -0.12) in Study RA-4.
Other Health Related Outcomes
General health status was assessed by the Short Form health survey (SF-36). In Studies RA-3 and RA-4, compared to placebo, subjects treated with OLUMIANT 2 mg demonstrated greater improvement from baseline in the physical component summary (PCS) score and the physical function, role physical, bodily pain, vitality, and general health domains at Week 12, with no consistent improvements in the mental component summary (MCS) scores or the role emotional, mental health, and social functioning domains.
COVID I
A randomized, double-blind, placebo-controlled clinical trial (NCT04401579) of hospitalized adults with confirmed SARS-CoV-2 infection compared treatment with baricitinib plus remdesivir (n = 515) with placebo plus remdesivir (n = 518). Subjects had to have laboratory-confirmed SARS-CoV-2 infection as well as at least one of the following to be enrolled in the trial: radiographic infiltrates by imaging, SpO2 ≤94% on room air, a requirement for supplemental oxygen, or a requirement for mechanical ventilation or ECMO. Subjects treated with the combination received the following regimen:
In this study prophylaxis for venous thromboembolic event (VTEs) was recommended for all subjects unless a major contraindication was noted.
For the overall population (N = 1033 subjects) at randomization, mean age was 55 years (with 30% of subjects aged 65 or older); 63% of subjects were male, 51% were Hispanic or Latino, 48% were White, 15% were Black or African American, and 10% were Asian; 14% did not require supplemental oxygen, 55% required supplemental oxygen, 21% required non-invasive ventilation or high-flow oxygen, and 11% required invasive mechanical ventilation or ECMO. The most common comorbidities were obesity (56%), hypertension (52%), and type 2 diabetes (37%). Demographics and disease characteristics were balanced across the combination group and the placebo group.
The primary endpoint, for the intent to treat population, was time to recovery within 29 days after randomization. Recovery was defined as being discharged from the hospital without limitations on activities, being discharged from the hospital with limitations on activities and/or requiring home oxygen or hospitalized but not requiring supplemental oxygen and no longer requiring medical care. The key secondary endpoint was clinical status on Day 15 assessed on an 8-point ordinal scale (OS) consisting of the following categories:
For the overall population, the median time to recovery (defined as discharged from hospital or hospitalized but not requiring supplemental oxygen or ongoing medical care) was 7 days for baricitinib + remdesivir compared to 8 days for placebo + remdesivir [hazard ratio: 1.16 (95% CI 1.01, 1.33); p = 0.035].
Subjects assigned to baricitinib + remdesivir were more likely to have a better clinical status (according to an 8-point ordinal scale) at Day 15 compared to subjects assigned to placebo + remdesivir [odds ratio: 1.26 (95% CI 1.01, 1.57); p = 0.044].
The proportion of subjects who died or progressed to non-invasive ventilation/high-flow oxygen or invasive mechanical ventilation by Day 29 was lower in baricitinib + remdesivir (23%) compared to placebo + remdesivir (28%) [odds ratio: 0.74 (95% CI 0.56, 0.99); p = 0.039]. Subjects who required non-invasive ventilation/high-flow oxygen or invasive mechanical ventilation (including ECMO) at baseline needed to worsen by at least 1 point on an 8-point ordinal scale to progress.
The proportion of subjects who died by Day 29 was 4.7% (24/515) for baricitinib + remdesivir compared to 7.1% (37/518) for placebo + remdesivir [Kaplan Meier estimated difference in Day 29 probability of mortality: -2.6% (95% CI: -5.8%, 0.5%); hazard ratio = 0.65 (95% CI: 0.39, 1.09)].
COVID II
A randomized, double-blind, placebo-controlled clinical trial (NCT04421027) of hospitalized adults with confirmed SARS-CoV-2 infection compared treatment with baricitinib 4 mg once daily (n = 764) with placebo (n = 761) for 14 days or hospital discharge, whichever came first. Subjects could remain on background standard of care, as defined per local guidelines, including antimalarials, antivirals, corticosteroids, and/or azithromycin. In this study prophylaxis for venous thromboembolic event (VTE) was required for all subjects unless contraindicated.
The most frequently used therapies at baseline were:
Subjects had to have laboratory-confirmed SARS-CoV-2 infection, at least one instance of elevation in at least one inflammatory marker above the upper limit of normal according to local laboratory ranges (CRP, D-dimer, LDH, ferritin), and at least one of the following to be enrolled in the trial: radiographic infiltrates by imaging, SpO2 <94% on room air, evidence of active COVID infection (with clinical symptoms including any of the following: fever, vomiting, diarrhea, dry cough, tachypnea defined as respiratory rate >24 breaths/min) or requirement for supplemental oxygen.
For the overall population (N = 1525 subjects) at randomization, mean age was 58 years (with 33% of subjects aged 65 or older); 63% of subjects were male, 60% were White, 5% were Black or African American, 11% were Asian; 12% did not require supplemental oxygen (OS 4), 63% required supplemental oxygen (OS 5), 24% required non-invasive ventilation or high-flow oxygen (OS 6). The most common comorbidities were hypertension (48%), obesity (33%), and type 2 diabetes (29%). Demographics and disease characteristics were balanced across the baricitinib and placebo groups.
The primary endpoint was the proportion of subjects who died or progressed to non-invasive ventilation/high-flow oxygen or invasive mechanical ventilation within the first 28-days of the study. Subjects who required non-invasive ventilation/high-flow oxygen at baseline needed to worsen by at least 1 point on an 8-point OS to progress (refer to the description of COVID I for the definition of the 8-point OS). A key secondary endpoint was all-cause mortality by Day 28.
The estimated proportion of subjects who died or progressed to non-invasive ventilation/high-flow oxygen or invasive mechanical ventilation was lower in subjects treated with baricitinib (27.8%) compared to placebo (30.5%), but this effect was not statistically significant [odds ratio: 0.85 (95% CI 0.67, 1.08); p = 0.180].
The proportion of subjects who died by Day 28 was 8.1% (62/764) for baricitinib compared to 13.3% (101/761) for placebo [estimated difference in Day 28 probability of mortality = -4.9% (95% CI: -8.0%, -1.9%); hazard ratio = 0.56 (95% CI: 0.41, 0.77)].
COVID II Exploratory Sub-Study
In a separate group of subjects requiring invasive mechanical ventilation or ECMO at baseline and enrolled in an addendum to COVID II, a pre-specified exploratory analysis showed that the proportion who died by Day 28 was 39.2% (20/51) for baricitinib compared to 58.0% (29/50) for placebo [estimated difference in Day 28 risk of mortality = -18.8% (95% CI: -36.3%, 0.6%); hazard ratio = 0.54 (95% CI: 0.31, 0.96)].
Adults with Severe Alopecia Areata
Two randomized, double-blind, placebo-controlled trials [Trials AA-1 (NCT03570749) and AA-2 (NCT03899259)] enrolled a total of 1200 adults, with severe alopecia areata (AA), who had at least 50% scalp hair loss as measured by the Severity of Alopecia Tool (SALT) for more than 6 months. The trials enrolled males 18 to 60 years of age and females 18 to 70 years of age. Among the subjects enrolled, 61% were female, 2% were 65 years of age or older, and 52% were White, 36% were Asian, and 8% were Black. At baseline, 53% of subjects had at least 95% scalp hair loss, 34% had their current episode lasting at least 4 years, 69% had significant gaps in eyebrow hair or no notable eyebrow hair, and 58% had significant gaps in eyelashes or no notable eyelashes.
In the Phase 3 portion of Trial AA-1 and in Trial AA-2, subjects received OLUMIANT 2 mg, OLUMIANT 4 mg, or placebo orally once daily.
Both trials assessed the proportion of subjects who achieved at least 80% scalp hair coverage (SALT score of ≤20) at Week 36 as the primary endpoint. Other outcomes at Week 36 included the proportion of subjects who achieved at least 90% scalp hair coverage (SALT score of ≤10), subjects with Scalp Hair Assessment PRO™ score of 0 or 1 with at least 2-point reduction on the 5-point scale, and assessments of eyebrow and eyelash hair loss.
Clinical Response
The results of the OLUMIANT trials (AA-1 and AA-2) are provided in Table 14 and Figure 5.
a Not statistically significant under the multiplicity control plan | ||||||
b Subjects evaluated scalp hair coverage on a 5-point scale where 0 = No missing hair (0% of scalp hair missing; full head of hair), 1 = A limited area of scalp hair loss (1% to 20%), 2 = moderate scalp hair loss (21% to 49%), 3 = a large area of scalp hair loss (50% to 94%), and 4 = nearly all or all scalp hair loss (95% to 100%). | ||||||
| Trial AA-1 | Trial AA-2 | |||||
| Placebo | OLUMIANT 2 mg/day | OLUMIANT 4 mg/day | Placebo | OLUMIANT 2 mg/day | OLUMIANT 4 mg/day | |
| Number of subjects with at least 50% scalp hair loss at baseline | ||||||
| N | 189 | 184 | 281 | 156 | 156 | 234 |
| SALT ≤ 20 Difference from Placebo (95% CI) | 5% | 22% 16% (10, 23) | 35% 30% (23, 36) | 3% | 17% 15% (8, 22) | 32% 30% (23, 36) |
| SALT ≤ 10 Difference from Placebo (95% CI) | 4% | 13% 9% (3, 15) | 26% 22% (16, 28) | 1% | 11% 10% (5, 16)a | 24% 23% (17, 29) |
| Number of subjects reporting Scalp Hair Assessment PRO™ score ≥3 at baseline | ||||||
| N | 181 | 175 | 275 | 151 | 149 | 215 |
| Scalp Hair Assessment PRO score of 0 or 1b Difference from Placebo (95% CI) | 5% | 16% 11% (5, 18) | 33% 28% (21, 34) | 4% | 16% 12% (5, 19) | 34% 30% (23, 37) |
Among subjects with substantial eyebrow and eyelash hair loss at baseline, an improvement in eyebrow and eyelash coverage was observed on OLUMIANT 4 mg once daily dosage at Week 36.
Figure 5: Percent of Adults with Severe AA Achieving SALT ≤20 in Trials AA-1 and AA-2

Figure (Olumiant Uspi F5 V1)
Analyses by age, gender, race, and body weight did not identify differences in response to 36-weeks of treatment with OLUMIANT among these subgroups. SALT ≤20 response rates were higher in all dose groups in subjects with baseline SALT 50 to 94 versus SALT 95 to 100. See Table 15.
| Trials AA-1 and AA-2 | |||
| Placebo | OLUMIANT 2 mg/day | OLUMIANT 4 mg/day | |
| 50 % to 94% Scalp Hair Loss N SALT ≤20 | 166 8% | 147 33% | 248 48% |
| 95 % to 100% Scalp Hair Loss N SALT ≤20 | 178 1% | 193 10% | 267 21% |
In AA-2, subjects who achieved adequate response (SALT ≤20) to OLUMIANT 4 mg once daily at 52 weeks of treatment entered a randomized down-titration period and received OLUMIANT 2 mg once daily or remained on OLUMIANT 4 mg once daily. After an additional 24 weeks of treatment (76 weeks total), 75% (30/40) of subjects randomized to OLUMIANT 2 mg once daily maintained response and 98% (41/42) of subjects who remained on OLUMIANT 4 mg once daily maintained response.
Pediatric Subjects 12 Years of Age and Older with Severe Alopecia Areata
The efficacy and safety of OLUMIANT once daily was assessed in a single double-blind, randomized, placebo-controlled 36-week trial (AA-PEDS, NCT05723198). In the placebo-controlled portion of the trial, 257 pediatric subjects 12 years of age and older who weighed at least 30 kg with severe alopecia areata were randomized to placebo, OLUMIANT 2 mg, or OLUMIANT 4 mg in a 1:1:1 ratio.
The primary outcome of the trial was the proportion of subjects who achieved a SALT (Severity of Alopecia Tool) score of ≤ 20 (80% or more scalp coverage with hair) at Week 36. Other outcomes at Week 36 included the proportion of subjects who achieved at least 90% scalp hair coverage (SALT score of ≤10), and assessments of eyebrow and eyelash hair loss.
Baseline Characteristics
Across all treatment groups, the mean age was 14.7 years, and 49% of subjects were female, 60% were White, 7% were Black or African American, and 28% were Asian. At baseline, the mean duration of alopecia areata from onset and the mean duration of current episode of hair loss were 6.4 and 3.2 years, respectively. The median SALT score was 100 (this equals 100% scalp hair loss), and 64% of subjects had at least 95% scalp hair loss. Sixty-five (65)% of subjects had significant gaps in eyebrow hair or no notable eyebrow hair, and 57% had significant gaps in eyelashes or no notable eyelashes.
Clinical Response
The results of the OLUMIANT trial (AA-PEDS) in pediatric subjects 12 years of age and older with severe AA through Week 36 are provided in Table 16 and Figure 6.
| AA-PEDS | |||
|---|---|---|---|
| Placebo N=88 | OLUMIANT 2 mg/day N=84 | OLUMIANT 4 mg/day N=85 | |
| SALT ≤ 20 Difference from Placebo (95% CI) | 5% | 27% 23% (12, 34) | 42% 38% (26, 49) |
| SALT ≤ 10 Difference from Placebo (95% CI) | 2% | 21% 19% (10, 29) | 37% 34% (23, 45) |
Among subjects with substantial eyebrow and eyelash hair loss at baseline, an improvement in eyebrow and eyelash coverage was observed on OLUMIANT 4 mg once daily dosage at Week 36.
Figure 6: Proportion of Pediatric Subjects 12 Years of Age and Older with Severe AA with SALT ≤ 20 through Week 36 in Trial AA-PEDS
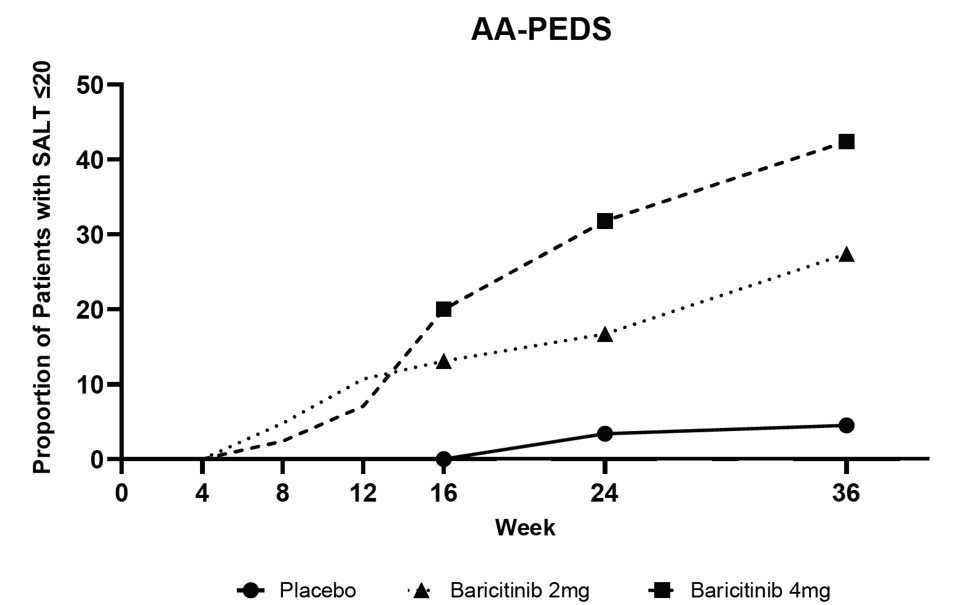
Figure (Olumiant Uspi F6 V1)
Analyses by gender and race did not identify differences in response to 36-weeks of treatment with OLUMIANT among these subgroups. SALT ≤20 response rates were higher in all dose groups in subjects with baseline SALT 50 to 94 versus SALT 95 to 100. See Table 17.
| Placebo | OLUMIANT 2 mg/day | OLUMIANT 4 mg/day | |
|---|---|---|---|
| 50% to 94% Scalp Hair Loss N SALT ≤20 | 32 6% | 29 52% | 31 68% |
| 95% to 100% Scalp Hair Loss N SALT ≤20 | 55 2% | 55 15% | 54 28% |
Infections
Inform patients that they may be more likely to develop infections when taking OLUMIANT. Instruct patients to tell their healthcare provider if they develop any signs or symptoms of an infection [see Warnings and Precautions (5.1)].
Advise patients that the risk of herpes zoster is increased in patients treated with OLUMIANT and some cases can be serious [see Warnings and Precautions (5.1)].
Malignancy and Lymphoproliferative Disorders
Inform patients that OLUMIANT may increase their risk of developing lymphomas and other malignancies, including of the skin and that periodic skin examinations should be performed while using OLUMIANT. Instruct patients to inform their healthcare provider if they have ever had any type of cancer [see Warnings and Precautions (5.3)].
Major Adverse Cardiovascular Events
Inform patients that OLUMIANT may increase their risk of major adverse cardiovascular events (MACE) including myocardial infarction, stroke, and cardiovascular death. Instruct all patients, especially current or past smokers or patients with other cardiovascular risk factors, to be alert for the development of signs and symptoms of cardiovascular events [see Warnings and Precautions (5.4)].
Thrombosis
Advise patients that OLUMIANT may increase their risk of thrombosis. Instruct patients to seek immediate medical attention if they develop any signs or symptoms of a thrombosis (sudden shortness of breath, chest pain worsened with breathing, swelling of leg or arm, leg pain or tenderness, red or discolored skin in the affected leg or arm) [see Warnings and Precautions (5.5)].
Hypersensitivity
Advise patients to discontinue OLUMIANT and seek immediate medical attention if they develop any signs and symptoms of serious allergic reactions [see Warnings and Precautions (5.6)].
Gastrointestinal Perforations
Inform patients that gastrointestinal perforations have been reported in clinical trials with OLUMIANT. Instruct patients to seek medical care immediately if they experience new onset of abdominal pain, fever, chills, nausea, or vomiting [see Warnings and Precautions (5.7)].
Hypoglycemia in Patients with Diabetes
Consider advising patients with diabetes to increase monitoring of blood glucose since hypoglycemia, including severe hypoglycemia, has been reported after starting OLUMIANT. Advise patients with diabetes to notify their healthcare provider if they develop signs or symptoms of hypoglycemia [see Warnings and Precautions (5.8)].
Laboratory Abnormalities
Inform patients that OLUMIANT may affect certain lab tests, and that blood tests are required before and during OLUMIANT treatment [see Warnings and Precautions (5.9)].
Vaccinations
Instruct patients to inform the healthcare practitioner that they are taking OLUMIANT prior to a potential vaccination since the use of live vaccine(s) is not recommended [see Warnings and Precautions (5.10)].
Pregnancy
Advise pregnant females and females of reproductive potential of the potential risk to a fetus and to inform their healthcare provider if they are pregnant or intend to become pregnant during treatment with OLUMIANT. Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to OLUMIANT during pregnancy [see Use in Specific Populations (8.1, 8.3)].
Lactation
Advise a woman not to breastfeed during treatment with OLUMIANT and for 4 days after the last dose [see Use in Specific Populations (8.2)].
Marketed by: Lilly USA, LLC, Indianapolis, IN 46285, USA
For more information, see www.olumiant.com
Copyright © 2018, 2026, Eli Lilly and Company. All rights reserved.
Pat.: www.lilly.com/patents
OLM-0010-USPI-20261009