If a planned dose of SARCLISA is missed, administer the dose as soon as possible and adjust the treatment schedule accordingly, maintaining the treatment interval.
Administer the following premedications prior to SARCLISA infusion to reduce the risk and severity of infusion-related reactions [see Warnings and Precautions (5.1)]:
- When administered in combination with SARCLISA and pomalidomide: Dexamethasone 40 mg orally or intravenously (or 20 mg orally or intravenously for patients ≥75 years of age).
When administered in combination with SARCLISA and carfilzomib: Dexamethasone 20 mg (intravenously on the days of SARCLISA and/or carfilzomib infusions, orally on day 22 in cycle 2 and beyond, and orally on day 23 in all cycles).
When administered in combination with SARCLISA, bortezomib, and lenalidomide: Dexamethasone 20 mg (intravenously on the days of SARCLISA infusions, orally on the other days). - Acetaminophen 650 mg to 1,000 mg orally (or equivalent).
- H2 antagonist
- Diphenhydramine 25 mg to 50 mg orally or intravenously (or equivalent). The intravenous route is preferred for at least the first 4 infusions.
The above recommended dose of dexamethasone (orally or intravenously) corresponds to the dose to be administered before infusion as part of the premedication and part of the backbone treatment. Administer dexamethasone before SARCLISA and pomalidomide, before SARCLISA and carfilzomib, and before SARCLISA, bortezomib, and lenalidomide administration.
Administer the recommended premedication agents 15 to 60 minutes prior to starting a SARCLISA infusion.
Recommended Antimicrobial Prophylaxis
Initiate antibacterial and antiviral prophylaxis (such as herpes zoster prophylaxis) if needed based on standard guidelines [see Warnings and Precautions (5.2)].
Infusion Rates
Following dilution, administer the SARCLISA infusion solution intravenously at the infusion rates presented in Table 3. Incremental escalation of the infusion rate should be considered only in the absence of infusion-related reactions [see Warnings and Precautions (5.1) and Adverse Reactions (6.1)].
Table 3: Infusion Rates of SARCLISA Administration | Dilution Volume | Initial Rate | Absence of Infusion-Related Reaction | Rate Increment | Maximum Rate |
|---|
| First infusion | 250 mL | 25 mL/hour | For 60 minutes | 25 mL/hour every 30 minutes | 150 mL/hour |
| Second infusion | 250 mL | 50 mL/hour | For 30 minutes | 50 mL/hour for 30 minutes then increase by 100 mL/hour | 200 mL/hour |
| Subsequent infusions | 250 mL | 200 mL/hour | – | – | 200 mL/hour |
Interference with Serological Testing (Indirect Antiglobulin Test)
SARCLISA binds to CD38 on red blood cells (RBCs) and may result in a false positive indirect antiglobulin test (indirect Coombs test). This interference with the indirect Coombs test may persist for approximately 6 months after the last infusion of SARCLISA. The indirect antiglobulin test was positive during Isa-Pd treatment in 68% of the tested patients, and during Isa-Kd treatment in 63% of patients. In patients with a positive indirect antiglobulin test, blood transfusions were administered without evidence of hemolysis. ABO/RhD typing was not affected by SARCLISA treatment.
Before the first SARCLISA infusion, conduct blood type and screen tests on SARCLISA-treated patients. Consider phenotyping prior to starting SARCLISA treatment. If treatment with SARCLISA has already started, inform the blood bank that the patient is receiving SARCLISA and SARCLISA interference with blood compatibility testing can be resolved using dithiothreitol-treated RBCs. If an emergency transfusion is required, non–cross-matched ABO/RhD-compatible RBCs can be given as per local blood bank practices [see Drug Interactions (7.1)].
Interference with Serum Protein Electrophoresis and Immunofixation Tests
SARCLISA is an IgG kappa monoclonal antibody that can be incidentally detected on both serum protein electrophoresis and immunofixation assays used for the clinical monitoring of endogenous M-protein. This interference can impact the accuracy of the determination of complete response in some patients with IgG kappa myeloma protein [see Drug Interactions (7.1)].
Relapsed and/or Refractory Multiple Myeloma
Combination treatment with pomalidomide and dexamethasone (Isa-Pd)
The safety of SARCLISA was evaluated in ICARIA-MM, a randomized, open-label clinical trial in patients with previously treated multiple myeloma. Patients received SARCLISA 10 mg/kg intravenously, weekly in the first cycle and every two weeks thereafter, in combination with pomalidomide and dexamethasone (Isa-Pd) (n=152) or pomalidomide and dexamethasone (Pd) (n=149) [see Clinical Studies (14)]. Among patients receiving Isa-Pd, 66% were exposed to SARCLISA for 6 months or longer and 24% were exposed for greater than 12 months or longer.
Serious adverse reactions occurred in 62% of patients receiving Isa-Pd. Serious adverse reactions in >5% of patients who received Isa-Pd included pneumonia (26%), upper respiratory tract infections (7%), and febrile neutropenia (7%). Fatal adverse reactions occurred in 11% of patients (those that occurred in more than 1% of patients were pneumonia and other infections [3%]).
Permanent treatment discontinuation due to an adverse reaction (grades 1–4) occurred in 7% of patients who received Isa-Pd. The most frequent adverse reactions requiring permanent discontinuation in patients who received Isa-Pd were infections (2.6%). SARCLISA alone was discontinued in 3% of patients due to infusion-related reactions.
Dosage interruptions due to an adverse reaction occurred in 31% of patients who received SARCLISA. The most frequent adverse reaction requiring dosage interruption was infusion-related reaction (28%).
The most common adverse reactions (≥20%) were upper respiratory tract infection, infusion-related reactions, pneumonia, and diarrhea.
Table 4 summarizes the adverse reactions in ICARIA-MM.
Table 4: Adverse Reactions (≥10%) in Patients Receiving SARCLISA, Pomalidomide, and Dexamethasone with a Difference Between Arms of ≥5% Compared to Control Arm in ICARIA-MM Trial| Adverse Reactions | SARCLISA + Pomalidomide + Dexamethasone (Isa-Pd) | Pomalidomide + Dexamethasone (Pd) |
|---|
| (N=152) | (N=149) |
|---|
| All Grades
(%) | Grade 3
(%) | Grade 4
(%) | All Grades
(%) | Grade 3
(%) | Grade 4
(%) |
|---|
| CTCAE version 4.03 |
| General disorders and administration site conditions |
| Infusion-related reaction Infusion-related reaction includes infusion-related reaction, cytokine release syndrome, and drug hypersensitivity. | 38 | 1.3 | 1.3 | 0 | 0 | 0 |
| Infections |
| Upper respiratory tract infection Upper respiratory tract infection includes bronchiolitis, bronchitis, bronchitis viral, chronic sinusitis, fungal pharyngitis, influenza-like illness, laryngitis, nasopharyngitis, parainfluenzae virus infection, pharyngitis, respiratory tract infection, respiratory tract infection viral, rhinitis, sinusitis, tracheitis, upper respiratory tract infection, and upper respiratory tract infection bacterial. | 57 | 9 | 0 | 42 | 3.4 | 0 |
| Pneumonia Pneumonia includes atypical pneumonia, bronchopulmonary aspergillosis, pneumonia, pneumonia haemophilus, pneumonia influenzal, pneumonia pneumococcal, pneumonia streptococcal, pneumonia viral, candida pneumonia, pneumonia bacterial, haemophilus infection, lung infection, pneumonia fungal, and pneumocystis jirovecii pneumonia. | 31 | 22 | 3.3 | 23 | 16 | 2.7 |
| Blood and lymphatic system disorders |
| Febrile neutropenia | 12 | 11 | 1.3 | 2 | 1.3 | 0.7 |
| Respiratory, thoracic and mediastinal disorders |
| Dyspnea Dyspnea includes dyspnea, dyspnea exertional, and dyspnea at rest. | 17 | 5 | 0 | 12 | 1.3 | 0 |
| Gastrointestinal disorders |
| Diarrhea | 26 | 2 | 0 | 19 | 0.7 | 0 |
| Nausea | 15 | 0 | 0 | 9 | 0 | 0 |
| Vomiting | 12 | 1.3 | 0 | 3.4 | 0 | 0 |
Table 5 summarizes the hematology laboratory abnormalities in ICARIA-MM.
Table 5: Hematology Laboratory Abnormalities During the Treatment Period in Patients Receiving Isa-Pd versus Pd in ICARIA-MM | Laboratory Parameter | SARCLISA + Pomalidomide + Dexamethasone (Isa-Pd) | Pomalidomide + Dexamethasone (Pd) |
|---|
| (N=152) | (N=149) |
|---|
| All Grades
(%) | Grade 3
(%) | Grade 4
(%) | All Grades
(%) | Grade 3
(%) | Grade 4
(%) |
|---|
| The denominator used to calculate the percentages was based on the safety population. |
| Hemoglobin decreased | 99 | 32 | 0 | 97 | 28 | 0 |
| Neutrophils decreased | 96 | 24 | 61 | 92 | 38 | 31 |
| Lymphocytes decreased | 92 | 42 | 13 | 92 | 35 | 8 |
| Platelets decreased | 84 | 14 | 16 | 79 | 9 | 15 |
Combination treatment with carfilzomib and dexamethasone (Isa-Kd)
The safety of SARCLISA was evaluated in IKEMA, a randomized, open-label clinical trial in patients with previously treated multiple myeloma. Patients received SARCLISA 10 mg/kg intravenously weekly in the first cycle, and every two weeks thereafter, in combination with carfilzomib and dexamethasone (Isa-Kd) (n=177) or carfilzomib and dexamethasone (Kd) (n=122) [see Clinical Studies (14)]. Among patients receiving Isa-Kd, 68% were exposed to SARCLISA for 12 months or longer and 51% were exposed for greater than 18 months.
Serious adverse reactions occurred in 59% of patients receiving Isa-Kd. The most frequent serious adverse reactions in >5% of patients who received Isa-Kd were pneumonia (25%) and upper respiratory tract infections (9%). Adverse reactions with a fatal outcome during treatment were reported in 3.4% of patients in the Isa-Kd group (those occurring in more than 1% of patients were pneumonia occurring in 1.7% and cardiac failure in 1.1% of patients).
Permanent treatment discontinuation due to an adverse reaction (grades 1–4) occurred in 8% of patients who received Isa-Kd. The most frequent adverse reactions requiring permanent discontinuation in patients who received Isa-Kd were infections (2.8%). SARCLISA alone was discontinued in 0.6% of patients due to infusion-related reactions.
Dosage interruptions due to an adverse reaction occurred in 33% of patients who received SARCLISA. The most frequent adverse reaction requiring dosage interruption was infusion-related reaction (30%).
The most common adverse reactions (≥20%) were upper respiratory tract infection, infusion-related reactions, fatigue, hypertension, diarrhea, pneumonia, dyspnea, insomnia, bronchitis, cough, and back pain.
Table 6 summarizes the adverse reactions in IKEMA.
Table 6: Adverse Reactions (≥10%) in Patients Receiving SARCLISA, Carfilzomib, and Dexamethasone with a Difference Between Arms of ≥5% Compared to Control Arm in IKEMA| Adverse Reactions | SARCLISA + Carfilzomib + Dexamethasone (Isa-Kd) | Carfilzomib + Dexamethasone (Kd) |
|---|
| (N=177) | (N=122) |
|---|
| All Grades
(%) | Grade 3
(%) | Grade 4
(%) | All Grades
(%) | Grade 3
(%) | Grade 4
(%) |
|---|
| General disorders and administration site conditions |
| Infusion-related reaction Infusion-related reaction includes infusion-related reaction, cytokine release syndrome, and hypersensitivity. | 46 | 0.6 | 0 | 3.3 | 0 | 0 |
| Fatigue Fatigue includes fatigue and asthenia. | 42 | 5 | 0 | 32 | 3.3 | 0 |
| Infections |
| Upper respiratory tract infection Upper respiratory tract infection includes acute sinusitis, chronic sinusitis, H1N1 influenza, H3N2 influenza, influenza, laryngitis, laryngitis viral, nasal herpes, nasopharyngitis, pharyngitis, pharyngotonsillitis, respiratory syncytial virus infection, rhinitis, sinusitis, sinusitis bacterial, tonsillitis, tracheitis, upper respiratory tract infection, viral rhinitis, respiratory tract infection, respiratory tract infection viral, influenza like illness, parainfluenzae virus infection, respiratory tract infection bacterial, and viral upper respiratory tract infection. | 67 | 9 | 0 | 57 | 7 | 0 |
| Pneumonia Pneumonia includes atypical pneumonia, lower respiratory tract infection, lower respiratory tract infection viral, pneumocystis jirovecii pneumonia, pneumonia, pneumonia influenzal, pneumonia legionella, pneumonia pneumococcal, pneumonia respiratory syncytial viral, pneumonia streptococcal, pneumonia viral, pulmonary sepsis, and pulmonary tuberculosis. | 36 | 19 | 3.4 | 30 | 15 | 2.5 |
| Bronchitis Bronchitis includes bronchitis, bronchitis viral, respiratory syncytial virus bronchitis, bronchitis chronic, and tracheobronchitis. | 24 | 2.3 | 0 | 13 | 0.8 | 0 |
| Vascular disorders |
| Hypertension Hypertension includes hypertension, blood pressure increased, and hypertensive crisis. | 37 | 20 | 0.6 | 32 | 18 | 1.6 |
| Respiratory, thoracic and mediastinal disorders |
| Dyspnea Dyspnea includes dyspnea and dyspnea exertional. | 29 | 5 | 0 | 24 | 0.8 | 0 |
| Cough Cough includes cough, productive cough, and allergic cough. | 23 | 0 | 0 | 15 | 0 | 0 |
| Gastrointestinal disorders |
| Diarrhea | 36 | 2.8 | 0 | 29 | 2.5 | 0 |
| Vomiting | 15 | 1.1 | 0 | 9 | 0.8 | 0 |
Table 7 summarizes the hematology laboratory abnormalities in IKEMA.
Table 7: Hematology Laboratory Abnormalities During the Treatment Period in Patients Receiving Isa-Kd versus Kd in IKEMA| Laboratory Parameter | SARCLISA + Carfilzomib + Dexamethasone (Isa-Kd) | Carfilzomib + Dexamethasone (Kd) |
|---|
| (N=177) | (N=122) |
|---|
| All Grades
(%) | Grade 3
(%) | Grade 4
(%) | All Grades
(%) | Grade 3
(%) | Grade 4
(%) |
|---|
| The denominator used to calculate the percentage was based on the safety population. |
| Hemoglobin decreased | 99 | 22 | 0 | 99 | 20 | 0 |
| Lymphocytes decreased | 94 | 52 | 17 | 95 | 43 | 14 |
| Platelets decreased | 94 | 19 | 11 | 88 | 16 | 8 |
| Neutrophils decreased | 55 | 18 | 1.7 | 43 | 7 | 0.8 |
Newly Diagnosed Multiple Myeloma not Eligible for Autologous Stem Cell Transplant
Combination treatment with bortezomib, lenalidomide, and dexamethasone (Isa-VRd)
The safety of SARCLISA was evaluated in IMROZ, a randomized, open-label clinical trial in patients with newly diagnosed multiple myeloma. Patients received SARCLISA 10 mg/kg intravenously on day 1, 8, 15, 22, and 29 in the first 42-day cycle, followed by every two weeks from cycle 2 to 4 (42-day cycles), followed by every two weeks from cycle 5 to 17 (28-day cycles), and then on day 1 from cycle 18 and onwards (28-day cycles), in combination with bortezomib, lenalidomide, and dexamethasone (Isa-VRd) (n=263) or bortezomib, lenalidomide, and dexamethasone (VRd) (n= 181) [see Clinical Studies (14)]. In IMROZ, median duration of exposure to treatment was 53 (range: 0.5–69) months in patients treated with Isa-VRd and 31 (range 0.6–67) months in patients treated with VRd.
Serious adverse reactions occurred in 71% of patients receiving Isa-VRd. The serious adverse reaction in > 5% of patients who received Isa-VRd was pneumonia (30%). Fatal adverse reactions occurred in 11% of patients with Isa-VRd (those occurring in more than 1% of patients were pneumonia (5%).
Permanent discontinuation of treatment due to an adverse reaction occurred in 22.8% of patients treated with Isa-VRd. The most frequent adverse reactions requiring permanent discontinuation in patients who received Isa-VRd were infections (8%). SARCLISA alone was discontinued in 2.3% of patients.
Dosage interruptions due to an adverse reaction occurred in 21% of patients who received SARCLISA. The most frequent adverse reaction requiring dosage interruption was infusion related reaction (21%).
The most common adverse reactions (≥20%) were upper respiratory tract infections, diarrhea, fatigue, peripheral sensory neuropathy, pneumonia, musculoskeletal pain, cataract, constipation, peripheral edema, rash, infusion-related reaction, insomnia, and COVID-19. The most common hematologic laboratory abnormalities (≥80%) were decreased hemoglobin, decreased leukocytes, decreased lymphocytes, decreased platelets, and decreased neutrophils.
Table 8 summarizes the adverse reactions in IMROZ.
Table 8: Adverse Reactions (≥ 20%) in Patients Receiving SARCLISA, Bortezomib, Lenalidomide, and Dexamethasone in IMROZ | IMROZ study |
|---|
| Adverse Reactions | SARCLISA + Bortezomib + Lenalidomide + Dexamethasone
(N=263) | Bortezomib + Lenalidomide + Dexamethasone
(N=181) |
|---|
| All Grades (%) | Grade 3 or 4 (%) | All Grades (%) | Grade 3 or 4 (%) |
|---|
| Infections and infestations |
| Upper respiratory tract infection Includes other related terms | 65 | 4.6 | 57 Includes 1 patient (0.6%) with fatal URTI. | 6 |
| Pneumonia Pneumonia includes Atypical pneumonia, Bronchopulmonary aspergillosis, COVID-19 pneumonia, Lower respiratory tract infection, Pneumocystis jirovecii pneumonia, Pneumonia, Pneumonia aspiration, Pneumonia bacterial, Pneumonia influenzal, Pneumonia klebsiella, Pneumonia legionella, Pneumonia parainfluenzae viral, Pneumonia pneumococcal, Pneumonia pseudomonal, Pneumonia respiratory syncytial viral, Pneumonia viral, Pulmonary sepsis. | 45 Includes 14 patients (5%) with fatal pneumonia. | 26 | 31 Includes 4 patients (2.2%) with fatal pneumonia. | 19 |
| COVID-19 COVID-19 includes COVID-19 infections other than COVID-19 pneumonia. | 22 | 0.8 | 17 Includes 2 patients (1.1%) with fatal COVID-19. | 1.7 |
| General disorders and administration site conditions |
| Fatigue Fatigue includes Fatigue, Asthenia, or Malaise. | 55 | 11 | 50 | 9 |
| Edema peripheral | 33 | 0 | 33 | 1.1 |
| Infusion-related reaction | 24 | 0.4 | 1.1 | 0 |
| Gastrointestinal disorders |
| Diarrhea | 55 | 8 | 49 | 8 |
| Constipation | 36 | 2.3 | 41 | 1.7 |
| Nervous system disorders |
| Peripheral sensory neuropathy | 54 | 7 | 61 | 6 |
| Eye disorders |
| Cataract | 38 | 16 | 25 | 11 |
| Musculoskeletal and connective tissue disorders |
| Musculoskeletal pain | 38 | 4.2 | 33 | 3.3 |
| Skin and subcutaneous tissue disorders |
| Rash Rash includes Dermatitis, Dermatitis acneiform, Dermatitis allergic, Dermatitis atopic, Dermatitis exfoliative generalized, Drug eruption, Rash, Rash erythematous, Rash macular, Rash maculo-papular, Rash pruritic, Rash pustular, Skin exfoliation, Skin hyperpigmentation, Skin lesion, Skin reaction, and Toxic skin eruption. | 32 | 5 | 34 | 5 |
| Psychiatric disorders |
| Insomnia | 22 | 3.8 | 24 | 2.2 |
Table 9 summarizes the hematology laboratory abnormalities in IMROZ.
Table 9: Hematology Laboratory Abnormalities During the Treatment Period in Patients Receiving Isa-VRd Versus VRd in IMROZ| Laboratory parameter | SARCLISA + Bortezomib + Lenalidomide + Dexamethasone The denominator used to calculate the rate is based on the number of patients with a baseline value and at least one post-baseline value. | Bortezomib + Lenalidomide + Dexamethasone |
|---|
| All Grades (%) | Grade 3–4
(%) | All Grades
(%) | Grade 3–4
(%) |
|---|
| Decreased hemoglobin | 99 | 17 | 98 | 16 |
| Decreased leukocytes | 97 | 32 | 88 | 17 |
| Decreased lymphocytes | 95 | 60 | 92 | 53 |
| Decreased platelets | 95 | 30 | 85 | 28 |
| Decreased neutrophils | 87 | 54 | 80 | 37 |
Description of Selected Adverse Reactions
Cardiac failure
In IKEMA, cardiac failure (including cardiac failure, cardiac failure congestive, cardiac failure acute, cardiac failure chronic, left ventricular failure, and pulmonary edema) was reported in 7% of patients with the Isa-Kd group (grade ≥3 in 4%) and in 7% of patients with the Kd group (grade ≥3 in 4.1%). Serious cardiac failure was observed in 4% of patients in the Isa-Kd group and in 3.3% of patients in the Kd group. See the current prescribing information for carfilzomib for more information.
Interference with Serological Testing
SARCLISA, an anti-CD38 antibody, may interfere with blood bank serologic tests with false positive reactions in indirect antiglobulin tests (indirect Coombs tests), antibody detection (screening) tests, antibody identification panels, and antihuman globulin crossmatches in patients treated with SARCLISA [see Warnings and Precautions (5.5)].
Interference with Serum Protein Electrophoresis and Immunofixation Tests
SARCLISA may be incidentally detected by serum protein electrophoresis and immunofixation assays used for the monitoring of M-protein and may interfere with accurate response classification based on International Myeloma Working Group (IMWG) criteria [see Warnings and Precautions (5.5)]. In patients with persistent very good partial response, where interference is suspected, consider using an FDA-cleared isatuximab-irfc-specific IFE assay to distinguish isatuximab from any remaining endogenous M protein in the patient's serum to facilitate determination of a complete response.
Risk Summary
SARCLISA can cause fetal harm when administered to a pregnant woman. The assessment of isatuximab-irfc-associated risks is based on the mechanism of action and data from target antigen CD38 knockout animal models (see Data). There are no available data on SARCLISA use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. Animal reproduction toxicity studies have not been conducted with isatuximab-irfc. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, miscarriage, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
The combination of SARCLISA and pomalidomide or lenalidomide is contraindicated in pregnant women because pomalidomide and lenalidomide may cause birth defects and death of the unborn child. Refer to the pomalidomide or lenalidomide prescribing information on use during pregnancy. Pomalidomide and lenalidomide are only available through a REMS program.
Clinical Considerations
Fetal/neonatal reactions
Immunoglobulin G1 monoclonal antibodies are known to cross the placenta. Based on its mechanism of action, SARCLISA may cause depletion of fetal CD38-positive immune cells and decreased bone density. Defer administration of live vaccines to neonates and infants exposed to SARCLISA in utero until a hematology evaluation is completed.
Data
Animal data
Mice that were genetically modified to eliminate all CD38 expression (CD38 knockout mice) had reduced bone density which recovered 5 months after birth. Data from studies using CD38 knockout animal models also suggest the involvement of CD38 in regulating humoral immune responses (mice), feto-maternal immune tolerance (mice), and early embryonic development (frogs).
Risk Summary
There are no available data on the presence of isatuximab-irfc in human milk, milk production, or the effects on the breastfed child. Maternal immunoglobulin G is known to be present in human milk. The effects of local gastrointestinal exposure and limited systemic exposure in the breastfed infant to SARCLISA are unknown. Because of the potential for serious adverse reactions in the breastfed child from isatuximab-irfc administered in combination with pomalidomide or lenalidomide and dexamethasone, advise lactating women not to breastfeed during treatment with SARCLISA. Refer to pomalidomide or lenalidomide prescribing information for additional information.
Pregnancy Testing
With the combination of SARCLISA with pomalidomide or lenalidomide, refer to the pomalidomide or lenalidomide labeling for pregnancy testing requirements prior to initiating treatment in females of reproductive potential.
Contraception
Females
Advise female patients of reproductive potential to use effective contraception during treatment and for 5 months after the last dose of SARCLISA. Additionally, refer to the pomalidomide or lenalidomide labeling for contraception requirements prior to initiating treatment in females of reproductive potential.
Males
Refer to the pomalidomide or lenalidomide prescribing information.
Cardiac Electrophysiology
Up to 2 times the approved recommended dose, SARCLISA does not prolong the QT interval to any clinically relevant extent.
A relationship between isatuximab-irfc exposure and overall response rate and progression-free survival was observed.
No apparent relationship was observed between an increase of isatuximab-irfc exposure and adverse reactions.
Distribution
The mean (CV%) predicted total volume of distribution of isatuximab-irfc is of 8.13 L (26.2%).
Metabolism
Isatuximab-irfc is expected to be metabolized into small peptides by catabolic pathways.
Elimination
Isatuximab-irfc total clearance decreased with increasing dose and with multiple doses. At steady state, the near elimination (≥99%) of isatuximab-irfc from plasma after the last dose is predicted to occur in approximately 2 months. The elimination of isatuximab-irfc was similar when given as a single agent or as combination therapy.
Specific Populations
The following factors have no clinically meaningful effect on the exposure of isatuximab-irfc: age (36 to 85 years, 70 patients were ≥75 years old), sex, renal impairment including patients with End-Stage Renal Disease (ESRD) or on dialysis (eGFR <90 mL/min/1.73 m2), and mild hepatic impairment (total bilirubin ≤ upper limit of normal [ULN] and aspartate aminotransferase [AST] >ULN, or total bilirubin >1 to 1.5 × ULN and any AST). The effect of moderate (total bilirubin >1.5 to 3 × ULN and any AST) and severe (total bilirubin >3 × ULN and any AST) hepatic impairment on isatuximab-irfc pharmacokinetics is unknown.
No dose adjustments are recommended in these specific patient populations.
Body weight
The clearance of isatuximab-irfc increased with increasing body weight.
Race
White (n=377, 79%) or Asian (n=25, 5%) race have no clinically meaningful effect on the exposure of isatuximab-irfc. The effect of Black (n=18, 4%) race on the exposure of isatuximab-irfc is unknown.
Relapsed and/or Refractory Multiple Myeloma
ICARIA-MM
The efficacy and safety of SARCLISA in combination with pomalidomide and dexamethasone (Isa-Pd) were evaluated in ICARIA-MM (NCT02990338), a multicenter, multinational, randomized, open-label, 2-arm, phase 3 study in patients with relapsed and/or refractory multiple myeloma. Patients had received at least two prior therapies including lenalidomide and a proteasome inhibitor. Patients were eligible for inclusion if they had an Eastern Cooperative Oncology Group (ECOG) status of 0–2, platelets ≥75,000 cells/mm3, absolute neutrophil count ≥1 × 10⁹/L, creatinine clearance ≥30 mL/min/1.73 m2 (MDRD formula), AST ≤3 × ULN, and ALT ≤3 × ULN.
A total of 307 patients were randomized in a 1:1 ratio to receive either SARCLISA in combination with pomalidomide and dexamethasone (Isa-Pd, 154 patients) or pomalidomide and dexamethasone (Pd, 153 patients). Treatment was administered in both groups in 28-day cycles until disease progression or unacceptable toxicity. SARCLISA 10 mg/kg was administered as an intravenous infusion weekly in the first cycle and every two weeks thereafter. Pomalidomide 4 mg was taken orally once daily from day 1 to day 21 of each 28-day cycle. Dexamethasone (orally or intravenously) 40 mg (20 mg for patients ≥75 years of age) was given on days 1, 8, 15, and 22 for each 28-day cycle.
Overall, demographic and disease characteristics at baseline were similar between the two treatment groups. The median patient age was 67 years (range 36–86), 20% of patients were ≥75 years; 79% of patients were White, 12% Asian, and 1% Black or African American; 10% of patients entered the study with a history of COPD or asthma. The proportion of patients with renal impairment (creatinine clearance <60 mL/min/1.73 m2) was 34%. The International Staging System (ISS) stage at study entry was I in 37%, II in 36% and III in 25% of patients. Overall, 20% of patients had high-risk chromosomal abnormalities at study entry; del(17p), t(4;14) and t(14;16) were present in 12%, 8% and 2% of patients, respectively.
The median number of prior lines of therapy was 3 (range 2–11). All patients received a prior proteasome inhibitor, all patients received prior lenalidomide, and 56% of patients received prior stem cell transplantation; the majority of patients (93%) were refractory to lenalidomide, 76% to a proteasome inhibitor, and 73% to both an immunomodulator and a proteasome inhibitor.
The median duration of treatment was 41 weeks for Isa-Pd group compared to 24 weeks for Pd group.
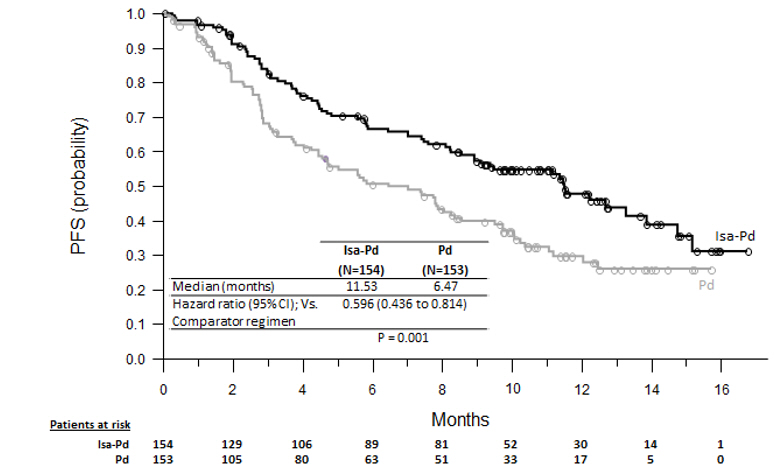
The efficacy of SARCLISA was based upon progression-free survival (PFS). PFS results were assessed by an Independent Response Committee based on central laboratory data for M-protein and central radiologic imaging review using the International Myeloma Working Group (IMWG) criteria. The improvement in PFS represented a 40% reduction in the risk of disease progression or death in patients treated with Isa-Pd.
Efficacy results are presented in Table 10 and Kaplan-Meier curve for PFS is provided in Figure 1.
Table 10: Efficacy of SARCLISA in Combination with Pomalidomide and Dexamethasone versus Pomalidomide and Dexamethasone in the Treatment of Multiple Myeloma (ICARIA-MM) | Endpoint | SARCLISA + Pomalidomide + Dexamethasone
N=154 | Pomalidomide + Dexamethasone
N=153 |
|---|
| Progression-Free Survival |
Median (months)
[95% CI] | 11.53 [8.94–13.9] | 6.47 [4.47–8.28] |
| Hazard ratio [95% CI] | 0.596 [0.44–0.81] |
| p-value (stratified log-rank test) | 0.0010 |
Overall Response Rate
Responders (sCR+CR+VGPR+PR) n (%)
[95% CI] | 93 (60.4)
[52.2–68.2] | 54 (35.3)
[27.8–43.4] |
| p-value (stratified Cochran-Mantel-Haenszel) | <0.0001 |
| Stringent Complete Response (sCR) + Complete Response (CR) n (%) | 7 (4.5) | 3 (2) |
| Very Good Partial Response (VGPR) n (%) | 42 (27.3) | 10 (6.5) |
| Partial Response (PR) n (%) | 44 (28.6) | 41 (26.8) |
The median time to first response in responders was 35 days in the Isa-Pd group versus 58 days in the Pd group. The median duration of response was 13.3 months (95% CI: 10.6-NR) in the Isa-Pd group versus 11.1 months (95% CI: 8.5-NR) in the Pd group. At a median follow-up time of 52.4 months, final median overall survival was 24.6 months in the Isa-Pd group and 17.7 months in the Pd group (HR=0.776; 95% CI: 0.594 to 1.015).
Figure 1: Kaplan-Meier Curves of PFS – ITT Population – ICARIA-MM (assessment by the IRC)
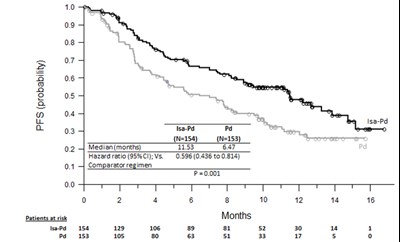
Figure 1 (A0473462 6f9d 4eca A5bf 8620aea68e8a 01)
IKEMA
The efficacy and safety of SARCLISA in combination with carfilzomib and dexamethasone were evaluated in IKEMA (NCT03275285), a multicenter, multinational, randomized, open-label, 2-arm, phase 3 study in patients with relapsed and/or refractory multiple myeloma. Patients had received one to three prior lines of therapy. Patients were eligible for inclusion if they had an ECOG status of 0–2, platelets ≥50,000 cells/mm3, absolute neutrophil count ≥1 × 10⁹/L, creatinine clearance ≥15 mL/min/1.73 m2 (MDRD formula), AST ≤3 × ULN, and ALT ≤3 × ULN.
A total of 302 patients were randomized in a 3:2 ratio to receive either SARCLISA in combination with carfilzomib and dexamethasone (Isa-Kd, 179 patients) or carfilzomib and dexamethasone (Kd, 123 patients). Treatment was administered in both groups in 28-day cycles until disease progression or unacceptable toxicity. SARCLISA 10 mg/kg was administered as an intravenous infusion weekly in the first cycle and every two weeks thereafter. Carfilzomib was administered as an intravenous infusion at the dose of 20 mg/m2 on days 1 and 2; 56 mg/m2 on days 8, 9, 15, and 16 of cycle 1; and at the dose of 56 mg/m2 on days 1, 2, 8, 9, 15, and 16 for subsequent cycles of each 28-day cycle. Dexamethasone (intravenously on the days of isatuximab-irfc and/or carfilzomib infusions, and orally on the other days) 20 mg was given on days 1, 2, 8, 9, 15, 16, 22, and 23 for each 28-day cycle. On the days where both SARCLISA and carfilzomib were administered, dexamethasone was administered first, followed by SARCLISA infusion, then followed by carfilzomib infusion.
Overall, demographic and disease characteristics at baseline were similar between the two treatment groups. The median patient age was 64 years (range 33–90), 9% of patients were ≥75 years, 71% were White, 17% Asian, and 3% Black or African American. The proportion of patients with renal impairment (eGFR<60 mL/min/1.73 m2) was 24% in the Isa-Kd group versus 15% in the Kd group. The International Staging System (ISS) stage at study entry was I in 53%, II in 31%, and III in 15% of patients. Overall, 24% of patients had high-risk chromosomal abnormalities at study entry; del(17p), t(4;14), t(14;16) were present in 11%, 14%, and 2% of patients, respectively. In addition, gain(1q21) was present in 42% of patients.
The median number of prior lines of therapy was 2 (range 1–4) with 44% of patients who received 1 prior line of therapy. Overall, 90% of patients received prior proteasome inhibitors, 78% received prior immunomodulators (including 43% who received prior lenalidomide), and 61% received prior stem cell transplantation. Overall, 33% of patients were refractory to prior proteasome inhibitors, 45% were refractory to prior immunomodulators (including 33% refractory to lenalidomide), and 21% were refractory to both a proteasome inhibitor and an immunomodulator.
The median duration of treatment was 80 weeks for the Isa-Kd group compared to 61 weeks for the Kd group.
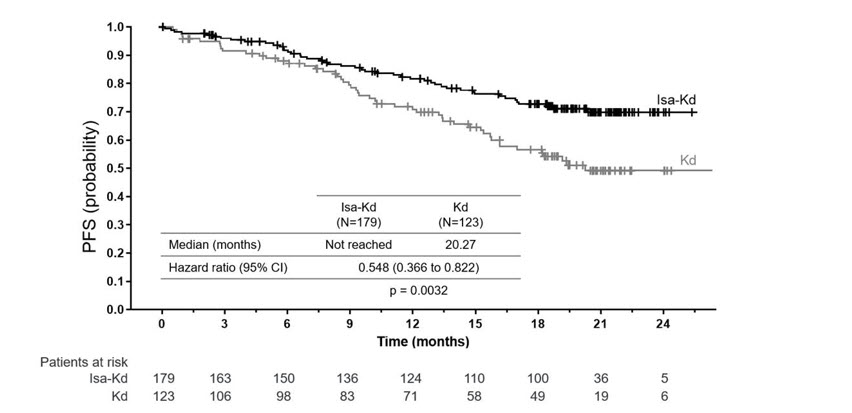
The efficacy of SARCLISA was based upon PFS. PFS results were assessed by an Independent Response Committee based on central laboratory data for M-protein and central radiologic imaging review using the IMWG criteria. The improvement in PFS represented a 45% reduction in the risk of disease progression or death in patients treated with Isa-Kd compared to patients treated with Kd.
Efficacy results are presented in Table 11 and Kaplan-Meier curves for PFS are provided in Figure 2.
Table 11Results are based on a prespecified interim analysis.
,Median follow-up time 20.7 months.
: Efficacy of SARCLISA in Combination with Carfilzomib and Dexamethasone versus Carfilzomib and Dexamethasone in the Treatment of Multiple Myeloma (IKEMA)| Endpoint | SARCLISA + Carfilzomib + Dexamethasone
N=179 | Carfilzomib + Dexamethasone
N=123 |
|---|
| NR: not reached. |
| Progression-Free Survival PFS results were assessed by the IRC based on central laboratory data for M-protein and central radiologic imaging review using the IMWG criteria. A comparison is considered statistically significant if the p-value is <0.008 (efficacy boundary). |
Median (months)
[95% CI] | NR
[NR– NR] | 20.27
[15.77– NR] |
| Hazard ratio [95% CI] | 0.548 [0.366–0.822] |
| p-value (stratified log-rank test) | 0.0032 |
Overall Response Rate
Responders (sCR+CR+VGPR+PR) n (%)
[95% CI]Estimated using Clopper-Pearson method. | 155 (86.6)
[80.7–91.2] | 102 (82.9)
[75.1–89.1] |
| p-value (stratified Cochran-Mantel-Haenszel) | 0.3859 |
| Complete Response (CR) n (%) | 71 (39.7) | 34 (27.6) |
| Very Good Partial Response (VGPR) n (%) | 59 (33) | 35 (28.5) |
| Partial Response (PR) n (%) | 25 (14) | 33 (26.8) |
Figure 2: Kaplan-Meier Curves of PFS – ITT Population – IKEMA (assessment by the IRC)
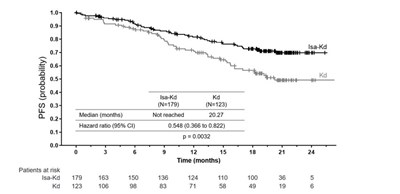
Figure 2 (A0473462 6f9d 4eca A5bf 8620aea68e8a 02)
At a median follow-up time of 44.0 months, final PFS analysis showed a median PFS of 41.7 months for Isa-Kd group compared to 20.8 months for Kd group, with a hazard ratio of 0.594 (95.4% CI: 0.424 to 0.832). Final complete response, determined using a FDA-cleared isatuximab-irfc-specific IFE assay [see Drug Interactions (7.1)], was 44.1% in Isa-Kd group compared to 28.5% in Kd group.
At a median follow-up time of 57 months, median overall survival was not reached in the Isa-Kd group (95% CI: 52.172–NR) and was 50.6 months in Kd group (95% CI: 38.932–NR) (HR=0.855; 95% CI: 0.608–1.202).
Newly Diagnosed Multiple Myeloma
IMROZ
The efficacy of SARCLISA in combination with bortezomib, lenalidomide, and dexamethasone was evaluated in IMROZ (NCT03319667), a multicenter, international, randomized, open-label, 2-arm, phase 3 study in patients with newly diagnosed multiple myeloma who are not eligible for stem cell transplantation. Patients were eligible for inclusion if they had an Eastern Cooperative Oncology Group (ECOG) status of 0 or 1, platelets ≥70,000 cells/mm3, absolute neutrophil count ≥1 × 10⁹/L, creatinine clearance ≥30 mL/min/1.73 m2 (MDRD formula), AST ≤3 × ULN, and ALT ≤3 × ULN.
A total of 446 patients were randomized in a 3:2 ratio to receive either SARCLISA in combination with bortezomib, lenalidomide, and dexamethasone (Isa-VRd, 265 patients) or bortezomib, lenalidomide, and dexamethasone (VRd, 181 patients). Treatment was administered in both groups during 4 cycles of 42-days each for the induction period. After completion of cycle 4, patients entered the continuous treatment period starting from cycle 5, in which 28-day cycles were administered up to disease progression or unacceptable toxicity. During the continuous treatment period, patients of the Isa-VRd group received SARCLISA in combination with lenalidomide, and dexamethasone (Isa-Rd), and patients in the VRd group received lenalidomide, and dexamethasone (Rd). During the induction period (cycle 1 to 4, 42-day cycles), SARCLISA 10 mg/kg was administered as an intravenous infusion on day 1, 8, 15, 22, and 29, in the first cycle and on day 1, 15, and 29, from cycle 2 to 4. Bortezomib was administered subcutaneously at the dose of 1.3 mg/m2 on days 1, 4, 8, 11, 22, 25, 29, and 32 of each cycle. Lenalidomide was administered orally at the dose of 25 mg/day from day 1 to 14 and from day 22 to 35 of each cycle. Dexamethasone (intravenously on the days of SARCLISA infusions, and orally on the other days) 20 mg/day was given on days 1, 2, 4, 5, 8, 9, 11, 12, 15, 22, 23, 25, 26, 29, 30, 32, and 33 of each cycle. During the continuous treatment period (from cycle 5, 28-day cycles), SARCLISA 10 mg/kg was administered as an IV infusion on day 1 and 15 from cycle 5 to 17, and on day 1 from cycle 18. Lenalidomide was administered orally at the dose of 25 mg/day from day 1 to 21 of each cycle. Dexamethasone (intravenously on the days of SARCLISA infusions, and orally on the other days) 20 mg/day was given on days 1, 8, 15, and 22 of each cycle.
The median patient age was 72 years (range 55–80), 28% of patients were ≥75 years; 72% of patients were White, 11% Asian, and 0.9% Black or African American. The proportion of patients with renal impairment (eGFR<60 mL/min/1.73m2) was 29%. The Revised International Staging System (R-ISS) stage at study entry was I in 23%, II in 64%, and III in 10% of patients. Overall, 17% of patients had high-risk chromosomal abnormalities at study entry; del(17p), t(4;14), and t(14;16) were present in 5%, 9% and 2% of patients, respectively. In addition, 1q21+ was present in 37% of patients.
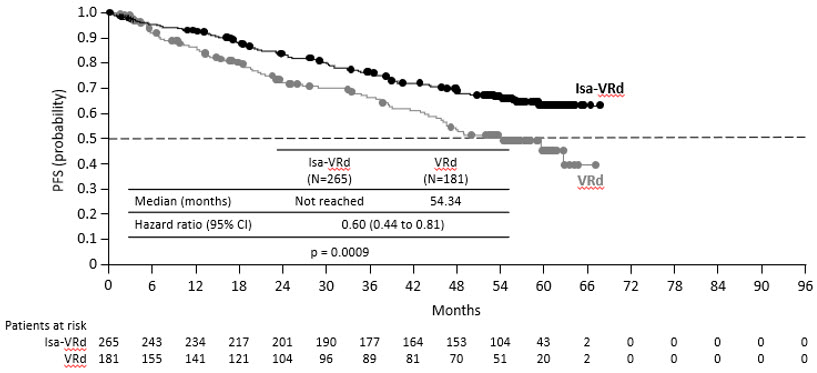
The efficacy of SARCLISA was established based upon progression-free survival (PFS). PFS results were assessed by an Independent Response Committee based on central laboratory data for M-protein and central radiologic imaging review using the International Myeloma Working Group (IMWG) criteria. The improvement in PFS represented a 40% reduction in the risk of disease progression or death in patients treated with Isa-VRd.
Efficacy results are presented in Table 12 and Kaplan-Meier curves for PFS are provided in Figure 3:
Table 12 – Efficacy Results of SARCLISA in combination with bortezomib, lenalidomide, and dexamethasone versus bortezomib, lenalidomide, and dexamethasone (IMROZ)| Endpoint | SARCLISA + Bortezomib + Lenalidomide + Dexamethasone
N =265 | Bortezomib + Lenalidomide + Dexamethasone
N = 181 |
|---|
| NR: not reached. |
| Median follow-up time=60 months. |
| Progression-Free Survival Based on ITT population. |
Median (months)
[95% CI] | NR
[NR–NR] | 54.34
[45.21–NR] |
| Hazard ratio Stratified by age (<70 years vs ≥70 years) and Revised International Staging System (R-ISS) stage (I or II vs. III or not classified) according to IRT. [95% CI] | 0.60 [0.44–0.81] |
| p-value (Stratified Log-Rank test) A comparison is considered statistically significant if the p-value is <0.0148. | 0.0009 |
| Overall Response Rate sCR, CR, VGPR, and PR were evaluated by the IRC using the IMWG response criteria. |
| Responders (sCR+CR+VGPR+PR) N(%) [95% CI] Estimated using Clopper-Pearson method. | 242 (91)
[87–94] | 167 (92)
[87–96] |
| Stringent Complete Response (sCR) N(%) | 29 (11) | 10 (6) |
| Complete Response (CR) N(%) | 169 (64) | 106 (59) |
| Very Good Partial Response (VGPR) N(%) | 38 (14) | 34 (19) |
| Partial Response (PR) N(%) | 6 (2.3) | 17 (9) |
| CR or better (sCR and CR) Other efficacy endpoints of CR and MRD negativity CR were tested hierarchically after PFS. N(%)
[95% CI] | 198 (75)
[69–80] | 116 (64)
[57–71] |
| p-value (Stratified Cochran-Mantel-Haenszel) | 0.0160 |
| Minimal Residual Disease (MRD) |
| MRD negativity rate Patients achieved both MRD negativity (threshold of 10-5) and response of CR or better. Based on a sensitivity level of 10-5 by the next-generation sequencing assay (clonoSEQ). N(%)
[95% CI] | 147 (55)
[49–62] | 74 (41)
[34–48] |
| p-value (Stratified Cochran-Mantel-Haenszel) | 0.0026 |
| Number of patients with CR or better (sCR and CR) | 198 | 116 |
| MRD negativity rate in patients with CR or better N(%) | 147 (74)
[68–80] | 74 (64)
[54–73] |
| [95% CI] | | |
Median overall survival was not reached for either treatment group. At a median follow-up time of 60 months, 26% of patients in the Isa-VRd group and 32.6% of patients in the VRd group had died (HR=0.78; 95% CI: 0.55 to 1.1).
Figure 3 – Kaplan-Meier Curves of PFS – ITT population – IMROZ
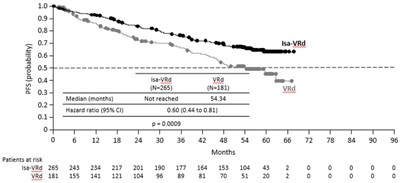
Figure 3 (A0473462 6f9d 4eca A5bf 8620aea68e8a 03)
How Supplied
SARCLISA (isatuximab-irfc) injection is a clear to slightly opalescent, colorless to slightly yellow solution, essentially free of visible particulates, supplied as follows:
- One 100 mg/5 mL (20 mg/mL) single-dose vial in a carton: NDC 0024-0654-01
- One 500 mg/25 mL (20 mg/mL) single-dose vial in a carton: NDC 0024-0656-01
Infusion-Related Reaction
Advise patients to seek immediate medical attention for any of the following signs and symptoms of infusion-related reactions: shortness of breath, wheezing or trouble breathing; swelling of the face, mouth, throat, or tongue; throat tightness; palpitations; dizziness, lightheadedness, or fainting; headache; cough; rash or itching; nausea; runny or stuffy nose; or chills [see Warnings and Precautions (5.1)].
Infections
Inform patients about the risk of developing infections during SARCLISA treatment, and to report immediately any fever or symptoms of infection to their healthcare provider [see Warnings and Precautions (5.2)].
Neutropenia
Inform patients about the risk of neutropenia and infection during SARCLISA treatment and the importance of reporting immediately any fever or symptoms of infection to their healthcare provider [see Warnings and Precautions (5.3) and Adverse Reactions (6.1)].
Second Primary Malignancies
Inform patients of the risk of developing second primary malignancies during treatment with SARCLISA when given with pomalidomide and dexamethasone or with carfilzomib and dexamethasone, or with bortezomib, lenalidomide, and dexamethasone [see Warnings and Precautions (5.4)].
Cardiac Toxicities
Inform patients about the risk of cardiac failure during treatment with SARCLISA when given with carfilzomib and dexamethasone, and the importance of reporting immediately any difficulty breathing, cough, or leg swelling to their healthcare provider [see Adverse Reactions (6.1)].
Interference with Laboratory Tests
Advise patients to inform healthcare providers and transfusion center personnel that they are treated with SARCLISA in case a red blood cell transfusion is planned. Advise patients that SARCLISA may affect the results of blood tests to match their blood type for approximately 6 months after their last infusion of SARCLISA [see Warnings and Precautions (5.5) and Drug Interactions (7.1)].
Embryo-Fetal Toxicity
Advise pregnant women and females of reproductive potential of the potential risk to a fetus and to use effective contraception during treatment and for 5 months after the last dose of SARCLISA [see Use in Specific Populations (8.1, 8.3)].
Advise patients that pomalidomide or lenalidomide have the potential to cause fetal harm and have specific requirements regarding contraception, pregnancy testing, blood and sperm donation, and transmission in sperm. Advise patients to report suspected or known pregnancies. Pomalidomide and lenalidomide are only available through a REMS program [see Use in Specific Populations (8.1, 8.3)].
Manufactured by:
sanofi-aventis U.S. LLC
Morristown, NJ 07960
A SANOFI COMPANY
U.S. License No. 1752
SARCLISA is a registered trademark of Sanofi
©2026 sanofi-aventis U.S. LLC