Other
Neutropenia: Neutropenic deaths have been reported. Monitor for neutropenia with frequent blood cell counts. JEVTANA is contraindicated in patients with neutrophil counts of ≤1,500 cells/mm3. Primary prophylaxis with G-CSF is recommended in patients with high-risk clinical features. Consider primary prophylaxis with G-CSF in all patients receiving a dose of 25 mg/m2 [see Contraindications (4) and Warnings and Precautions (5.1, 5.2)].
Severe hypersensitivity: Severe hypersensitivity reactions can occur and may include generalized rash/erythema, hypotension and bronchospasm. Severe hypersensitivity reactions require immediate discontinuation of the JEVTANA infusion and administration of appropriate therapy. Patients should receive premedication. JEVTANA is contraindicated in patients who have a history of severe hypersensitivity reactions to cabazitaxel or to other drugs formulated with polysorbate 80 [see Dosage and Administration (2.1), Contraindications (4), and Warnings and Precautions (5.3)].
Preparation
Read this entire section carefully before mixing and diluting. JEVTANA requires two dilutions prior to administration. Follow the preparation instructions provided below, as improper preparation may lead to overdose [see Overdosage (10)].
Note: Both the JEVTANA injection and the diluent vials contain an overfill to compensate for liquid loss during preparation. This overfill ensures that after dilution with the entire contents of the accompanying diluent, there is an initial diluted solution containing 10 mg/mL JEVTANA.
Inspect the JEVTANA injection and supplied diluent vials. The JEVTANA injection is a clear yellow to brownish-yellow viscous solution.
Step 1 – first dilution
Each vial of JEVTANA (cabazitaxel) 60 mg/1.5 mL must first be mixed with the entire contents of supplied diluent. Once reconstituted, the resultant solution contains 10 mg/mL of JEVTANA.
When transferring the diluent, direct the needle onto the inside wall of JEVTANA vial and inject slowly to limit foaming. Remove the syringe and needle and gently mix the initial diluted solution by repeated inversions for at least 45 seconds to assure full mixing of the drug and diluent. Do not shake.
Let the solution stand for a few minutes to allow any foam to dissipate, and check that the solution is homogeneous and contains no visible particulate matter. It is not required that all foam dissipate prior to continuing the preparation process.
The resulting initial diluted JEVTANA solution (cabazitaxel 10 mg/mL) requires further dilution before administration. The second dilution should be done immediately (within 30 minutes) to obtain the final infusion as detailed in Step 2.
Step 2 – second (final) dilution
Withdraw the recommended dose from the JEVTANA solution containing 10 mg/mL as prepared in Step 1 using a calibrated syringe and further dilute into a sterile 250 mL PVC-free container of either 0.9% sodium chloride solution or 5% dextrose solution for infusion. If a dose greater than 65 mg of JEVTANA is required, use a larger volume of the infusion vehicle so that a concentration of 0.26 mg/mL JEVTANA is not exceeded. The concentration of the JEVTANA final infusion solution should be between 0.10 mg/mL and 0.26 mg/mL.
Remove the syringe and thoroughly mix the final infusion solution by gently inverting the bag or bottle.
As the final infusion solution is supersaturated, it may crystallize over time. Do not use if this occurs and discard.
Fully prepared JEVTANA infusion solution (in either 0.9% sodium chloride solution or 5% dextrose solution) should be used within 8 hours at ambient temperature (including the one-hour infusion), or for a total of 24 hours (including the one-hour infusion) under the refrigerated conditions.
Discard any unused portion.
Administration
Inspect visually for particulate matter, any crystals and discoloration prior to administration. If the JEVTANA first diluted solution or second (final) infusion solution is not clear or appears to have precipitation, it should be discarded.
Use an in-line filter of 0.22 micrometer nominal pore size (also referred to as 0.2 micrometer) during administration.
The final JEVTANA infusion solution should be administered intravenously as a one-hour infusion at room temperature.
TROPIC Trial (JEVTANA 25 mg/m2)
In the TROPIC trial with G-CSF administered only at the investigator's discretion, 5 patients (1.3%) died from neutropenic infection (sepsis or septic shock); 4 of these patients died in the first 30 days of treatment. One additional patient's death was attributed to neutropenia without a documented infection. Twenty-two (6%) patients discontinued JEVTANA treatment due to neutropenia, febrile neutropenia, infection, or sepsis. Grade 3–4 neutropenia occurred in 82% of patients treated with JEVTANA in the randomized trial [see Adverse Reactions (6.1)].
PROSELICA Trial (comparison of JEVTANA 20 mg/m2 versus 25 mg/m2)
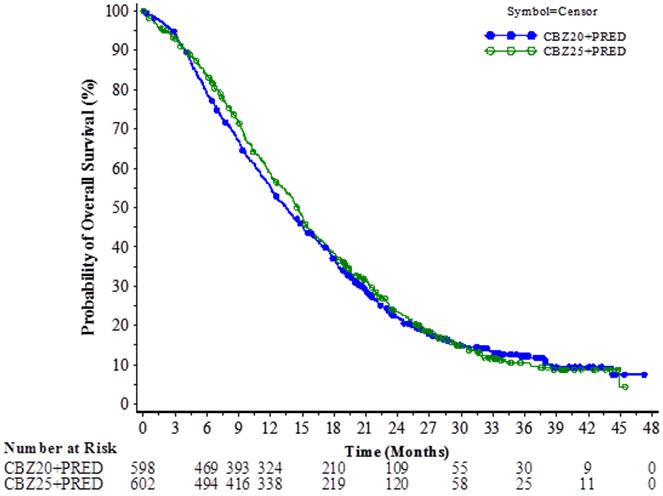
In the PROSELICA trial comparing two doses of JEVTANA, primary prophylaxis with G-CSF was not allowed, but could be administered after development of neutropenia at investigators discretion. Eight patients (1%) on the 20 mg/m2 arm and 15 patients (3%) on the 25 mg/m2 arm died from infection; of these, 4 deaths on the 20 mg/m2 arm and 8 deaths on the 25 mg/m2 arm occurred within the first 30 days of treatment. Clinically important neutropenia-related events occurred and included febrile neutropenia (2.1% on 20 mg/m2 arm and 9.2% on 25 mg/m2 arm), neutropenic infection/sepsis (2.1% on 20 mg/m2 arm and 6.4% on 25 mg/m2 arm), and neutropenic deaths (0.3% on 20 mg/m2 arm and 0.7% on 25 mg/m2 arm).
Fewer patients receiving JEVTANA 20 mg/m2 were reported to have infectious adverse reactions. Grade 1–4 infections were experienced by 160 patients (28%) on the 20 mg/m2 arm and 227 patients (38%) on the 25 mg/m2 arm. Grade 3–4 infections were experienced by 57 patients (10%) on the 20 mg/m2 arm and 120 patients (20%) on the 25 mg/m2 arm. Noninferiority for overall survival was demonstrated between these two arms [see Adverse Reactions (6.1)].
CARD Trial (JEVTANA 25 mg/m2 + primary prophylaxis G-CSF)
In the CARD trial where JEVTANA 25 mg/m2 was administered with primary prophylaxis of G-CSF, 1 patient (0.8%) died from sepsis within the first 30 days of treatment. Grade 1–4 neutropenia-related adverse reactions were experienced in 33 patients (26%). Grade 3–4 neutropenias were experienced by 26 patients (21%). Clinically important neutropenia-related events occurred and included febrile neutropenia (3.2%), neutropenic infection/sepsis (0.8%) and neutropenic deaths (0.8%) [see Adverse Reactions (6.1)].
Based on guidelines for the use of G-CSF and the adverse reactions profile of JEVTANA, primary prophylaxis with G-CSF is recommended in patients with high-risk clinical features (older patients, poor performance status, previous episodes of febrile neutropenia, extensive prior radiation ports, poor nutritional status, or other serious comorbidities) that predispose them to increased complications from prolonged neutropenia. Consider primary prophylaxis with G-CSF in all patients receiving JEVTANA 25 mg/m2.
Monitoring of complete blood counts is essential on a weekly basis during cycle 1 and before each treatment cycle thereafter so that the dose can be adjusted, if needed [see Dosage and Administration (2.2)].
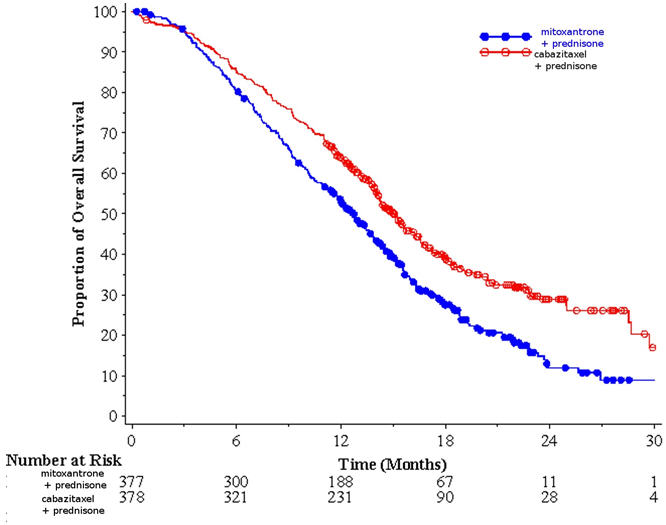
TROPIC Trial (JEVTANA 25 mg/m2 compared to mitoxantrone)
The safety of JEVTANA in combination with prednisone was evaluated in 371 patients with metastatic castration-resistant prostate cancer treated in the randomized TROPIC trial, compared to mitoxantrone plus prednisone.
Deaths due to causes other than disease progression within 30 days of last study drug dose were reported in 18 (5%) JEVTANA-treated patients and 3 (<1%) mitoxantrone-treated patients. The most common fatal adverse reactions in JEVTANA-treated patients were infections (n=5) and renal failure (n=4). The majority (4 of 5 patients) of fatal infection-related adverse reactions occurred after a single dose of JEVTANA. Other fatal adverse reactions in JEVTANA-treated patients included ventricular fibrillation, cerebral hemorrhage, and dyspnea.
The most common (≥10%) grade 1–4 adverse reactions were anemia, leukopenia, neutropenia, thrombocytopenia, diarrhea, fatigue, nausea, vomiting, constipation, asthenia, abdominal pain, hematuria, back pain, anorexia, peripheral neuropathy, pyrexia, dyspnea, dysgeusia, cough, arthralgia, and alopecia.
The most common (≥5%) grade 3–4 adverse reactions in patients who received JEVTANA were neutropenia, leukopenia, anemia, febrile neutropenia, diarrhea, fatigue, and asthenia.
Treatment discontinuations due to adverse reactions occurred in 18% of patients who received JEVTANA and 8% of patients who received mitoxantrone. The most common adverse reactions leading to treatment discontinuation in the JEVTANA group were neutropenia and renal failure. Dose reductions were reported in 12% of JEVTANA-treated patients and 4% of mitoxantrone-treated patients. Dose delays were reported in 28% of JEVTANA-treated patients and 15% of mitoxantrone-treated patients.
| Adverse Reactions | JEVTANA 25 mg/m2 every 3 weeks with prednisone 10 mg daily n=371 | Mitoxantrone 12 mg/m2 every 3 weeks with prednisone 10 mg daily n=371 | ||
|---|---|---|---|---|
| Grade 1–4 % | Grade 3–4 % | Grade 1–4 % | Grade 3–4 % | |
| Blood and Lymphatic System Disorders | ||||
| Anemia Based on laboratory values, JEVTANA: n=369, mitoxantrone: n=370. | 98 | 11 | 82 | 5 |
| Leukopenia | 96 | 69 | 93 | 42 |
| Neutropenia | 94 | 82 | 87 | 58 |
| Thrombocytopenia | 48 | 4 | 43 | 2 |
| Febrile Neutropenia | 7 | 7 | 1 | 1 |
| Gastrointestinal Disorders | ||||
| Diarrhea | 47 | 6 | 11 | <1 |
| Nausea | 34 | 2 | 23 | <1 |
| Vomiting | 22 | 2 | 10 | 0 |
| Constipation | 20 | 1 | 15 | <1 |
| Abdominal Pain Includes abdominal discomfort, abdominal pain lower, abdominal pain upper, abdominal tenderness, and GI pain. | 17 | 2 | 6 | 0 |
| Dyspepsia Includes gastroesophageal reflux disease and reflux gastritis. | 10 | 0 | 2 | 0 |
| General Disorders and Administration Site Conditions | ||||
| Fatigue | 37 | 5 | 27 | 3 |
| Asthenia | 20 | 5 | 12 | 2 |
| Pyrexia | 12 | 1 | 6 | <1 |
| Peripheral Edema | 9 | <1 | 9 | <1 |
| Mucosal Inflammation | 6 | <1 | 3 | <1 |
| Pain | 5 | 1 | 5 | 2 |
| Renal and Urinary Tract Disorders | ||||
| Hematuria | 17 | 2 | 4 | <1 |
| Dysuria | 7 | 0 | 1 | 0 |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Back Pain | 16 | 4 | 12 | 3 |
| Arthralgia | 11 | 1 | 8 | 1 |
| Muscle Spasms | 7 | 0 | 3 | 0 |
| Metabolism and Nutrition Disorders | ||||
| Anorexia | 16 | <1 | 11 | <1 |
| Dehydration | 5 | 2 | 3 | <1 |
| Nervous System Disorders | ||||
| Peripheral Neuropathy Includes peripheral motor neuropathy and peripheral sensory neuropathy. | 13 | <1 | 3 | <1 |
| Dysgeusia | 11 | 0 | 4 | 0 |
| Dizziness | 8 | 0 | 6 | <1 |
| Headache | 8 | 0 | 5 | 0 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Dyspnea | 12 | 1 | 4 | <1 |
| Cough | 11 | 0 | 6 | 0 |
| Skin and Subcutaneous Tissue Disorders | ||||
| Alopecia | 10 | 0 | 5 | 0 |
| Investigations | ||||
| Weight Decreased | 9 | 0 | 8 | <1 |
| Infections and Infestations | ||||
| Urinary Tract Infection Includes urinary tract infection enterococcal and urinary tract infection fungal. | 8 | 2 | 3 | 1 |
| Cardiac Disorders | ||||
| Arrhythmia Includes atrial fibrillation, atrial flutter, atrial tachycardia, atrioventricular block complete, bradycardia, palpitations, supraventricular tachycardia, tachyarrhythmia, and tachycardia. | 5 | 1 | 2 | <1 |
| Vascular Disorders | ||||
| Hypotension | 5 | <1 | 2 | <1 |
PROSELICA Trial (comparison of two doses of JEVTANA)
In a noninferiority, multicenter, randomized, open-label study (PROSELICA), 1175 patients with metastatic castration-resistant prostate cancer, previously treated with a docetaxel-containing regimen, were treated with either JEVTANA 25 mg/m2 (n=595) or the 20 mg/m2 (n=580) dose.
Deaths within 30 days of last study drug dose were reported in 22 (3.8%) patients in the 20 mg/m2 and 32 (5.4%) patients in the 25 mg/m2 arm. The most common fatal adverse reactions in JEVTANA-treated patients were related to infections, and these occurred more commonly on the 25 mg/m2 arm (n=15) than on the 20 mg/m2 arm (n=8). Other fatal adverse reactions in JEVTANA-treated patients included cerebral hemorrhage, respiratory failure, paralytic ileus, diarrhea, acute pulmonary edema, disseminated intravascular coagulation, renal failure, sudden death, cardiac arrest, ischemic stroke, diverticular perforation, and cardiorenal syndrome.
Grade 1–4 adverse reactions occurring ≥5% more commonly in patients on the 25 mg/m2 versus 20 mg/m2 arms were leukopenia, neutropenia, thrombocytopenia, febrile neutropenia, decreased appetite, nausea, diarrhea, asthenia, and hematuria.
Grade 3–4 adverse reactions occurring ≥5% more commonly in patients on the 25 mg/m2 versus 20 mg/m2 arms were leukopenia, neutropenia, and febrile neutropenia.
Treatment discontinuations due to adverse reactions occurred in 17% of patients in the 20 mg/m2 group and 20% of patients in the 25 mg/m2 group. The most common adverse reactions leading to treatment discontinuation were fatigue and hematuria. The patients in the 20 mg/m2 group received a median of 6 cycles (median duration of 18 weeks), while patients in the 25 mg/m2 group received a median of 7 cycles (median duration of 21 weeks). In the 25 mg/m2 group, 128 patients (22%) had a dose reduced from 25 to 20 mg/m2, 19 patients (3%) had a dose reduced from 20 to 15 mg/m2 and 1 patient (0.2%) had a dose reduced from 15 to 12 mg/m2. In the 20 mg/m2 group, 58 patients (10%) had a dose reduced from 20 to 15 mg/m2, and 9 patients (2%) had a dose reduced from 15 to 12 mg/m2.
| Adverse Reactions | JEVTANA 20 mg/m2 every 3 weeks with prednisone 10 mg daily n=580 | JEVTANA 25 mg/m2 every 3 weeks with prednisone 10 mg daily n=595 | ||
|---|---|---|---|---|
| Grade 1–4 % | Grade 3–4 % | Grade 1–4 % | Grade 3–4 % | |
| Blood and Lymphatic System Disorders | ||||
| Anemia Based on laboratory values, JEVTANA 20 mg/m2: n=577, JEVTANA 25 mg/m2: n=590. | 99.8 | 10 | 99.7 | 14 |
| Leukopenia | 80 | 29 | 95 | 60 |
| Neutropenia | 67 | 42 | 89 | 73 |
| Thrombocytopenia | 35 | 3 | 43 | 4 |
| Febrile Neutropenia | 2 | 2 | 9 | 9 |
| Gastrointestinal Disorders | ||||
| Diarrhea | 31 | 1 | 40 | 4 |
| Nausea | 25 | 0.7 | 32 | 1 |
| Constipation | 18 | 0.3 | 18 | 0.7 |
| Vomiting | 15 | 1.2 | 18 | 1 |
| Abdominal pain | 6 | 0.5 | 9 | 1 |
| Stomatitis | 5 | 0 | 5 | 0.3 |
| General Disorders and Administration Site Conditions | ||||
| Fatigue | 25 | 3 | 27 | 4 |
| Asthenia | 15 | 2 | 20 | 2 |
| Edema peripheral | 7 | 0.2 | 9 | 0.2 |
| Pyrexia | 5 | 0.2 | 6 | 0.2 |
| Renal and Urinary Disorders | ||||
| Hematuria | 14 | 2 | 21 | 4 |
| Dysuria | 5 | 0.3 | 4 | 0 |
| Metabolism and Nutrition Disorders | ||||
| Decreased appetite | 13 | 0.7 | 19 | 1 |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Back pain | 11 | 0.9 | 14 | 1 |
| Bone pain | 8 | 2 | 8 | 2 |
| Arthralgia | 8 | 0.5 | 7 | 0.8 |
| Pain in extremity | 5 | 0.2 | 7 | 0.5 |
| Nervous System Disorders | ||||
| Dysgeusia | 7 | 0 | 11 | 0 |
| Peripheral sensory neuropathy | 7 | 0 | 11 | 0.7 |
| Dizziness | 4 | 0 | 5 | 0 |
| Headache | 5 | 0.2 | 4 | 0.2 |
| Infections and Infestations | ||||
| Urinary tract infection Includes urinary tract infection staphylococcal, urinary tract infection bacterial, urinary tract infection fungal, and urosepsis. | 7 | 2 | 11 | 2 |
| Neutropenic infection Includes neutropenic sepsis. | 3 | 2 | 7 | 6 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Dyspnea | 5 | 0.9 | 8 | 0.7 |
| Cough | 6 | 0 | 6 | 0 |
| Investigations | ||||
| Weight decreased | 4 | 0.2 | 7 | 0 |
| Skin and Subcutaneous Tissue Disorders | ||||
| Alopecia | 3 | 0 | 6.1 | 0 |
| Injury, Poisoning and Procedural Complications | ||||
| Wrong technique in drug usage process | 0.3 | 0 | 5 | 0 |
CARD Trial (JEVTANA 25 mg/m2 + primary prophylaxis with G-CSF)
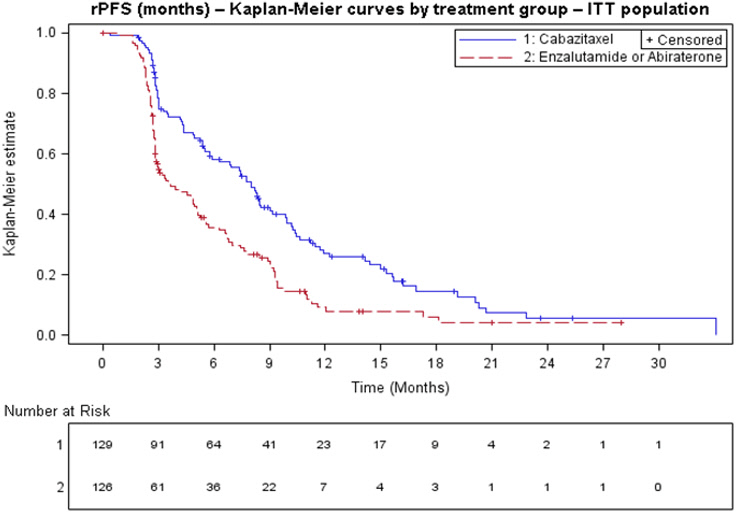
The safety of JEVTANA 25 mg/m2 in combination with prednisone/prednisolone and primary prophylaxis G-CSF was evaluated in a randomized, open-label study (CARD) in patients with metastatic castration-resistant prostate cancer who progressed after receiving prior docetaxel-containing regimens and abiraterone acetate or enzalutamide [see Clinical Studies 14.3]. This study compared JEVTANA 25 mg/m2 in combination with prednisone/prednisolone and primary prophylaxis with G-CSF to either abiraterone acetate 1000 mg once daily plus prednisone/prednisolone 5 mg twice daily or enzalutamide 160 mg once daily. Among patients receiving JEVTANA, 35% remained on treatment at 6 months and 4.7% remained on treatment at 12 months.
Serious adverse reactions occurred in 39% of patients receiving JEVTANA. Serious adverse reactions in ≥3% of patients included neutropenia (6%), infections (4.8%), and diarrhea, fatigue, pneumonia, and spinal cord compression (3.2% each). Deaths due to causes other than disease progression were reported in 2.4% of JEVTANA treated patients. Fatal adverse reactions in JEVTANA-treated patients were septic shock, urinary tract infection (UTI), and aspiration (0.8% each).
Treatment discontinuations due to adverse drug reactions occurred in 20% of patients who received JEVTANA and 8% of patients who received abiraterone acetate plus prednisone/prednisolone or enzalutamide. The adverse reactions leading to treatment discontinuation in >1% of patients in JEVTANA arm were nervous system disorders, infections/infestations, and gastrointestinal disorders.
Dose interruptions (alone or in combination with dose reduction) due to an adverse reaction occurred in 31% of patients receiving JEVTANA. Dose reductions were reported in 18% of JEVTANA-treated patients. The most frequent adverse reactions leading to dose interruption of JEVTANA were fatigue (7%) and hypersensitivity reaction (3.2%); the most frequent adverse reaction leading to reduction of JEVTANA were neutropenia and peripheral neuropathy (3.9% each).
Table 4 summarizes the adverse reactions and laboratory hematologic abnormalities in patients in CARD.
The most common (≥10%) adverse reactions were fatigue, diarrhea, musculoskeletal pain, nausea, infections, peripheral neuropathy, hematuria, constipation, abdominal pain, decreased appetite, vomiting, dysgeusia, edema peripheral and lower urinary tract symptoms.
The most common (≥10%) hematologic abnormalities were anemia, lymphopenia, neutropenia and thrombocytopenia.
| Adverse Reactions | JEVTANA 25 mg/m2 + prednisone/prednisolone + G-CSF | Abiraterone + prednisone/prednisolone or Enzalutamide | ||
|---|---|---|---|---|
| (N=126) | (N=124) | |||
| Grade 1–4 % | Grade 3–4 % | Grade 1–4 % | Grade 3–4 % | |
| Blood and Lymphatic System Disorders | ||||
| Anemia Based on laboratory values - % calculated using the number of patients with at least one event(n) over the number of patients assessed for each parameter during the on-treatment period. | 99 | 8 | 95 | 4.8 |
| Lymphopenia | 72 | 27 | 55 | 17 |
| Neutropenia | 66 | 45 | 7 | 3.2 |
| Thrombocytopenia | 41 | 3.2 | 16 | 1.6 |
| General Disorders and Administration Site Conditions | ||||
| Fatigue includes asthenia, fatigue, lethargy, malaise. | 53 | 4 | 36 | 2.4 |
| Edema peripheral includes lymphoedema, edema peripheral, peripheral swelling. | 11 | 0.8 | 10 | 1.6 |
| Pyrexia | 6 | 0 | 7 | 0 |
| Pain | 6 | 0 | 6 | 0.8 |
| Gastrointestinal Disorders | ||||
| Diarrhea includes colitis, diarrhea, diarrhea hemorrhagic, gastroenteritis. | 40 | 4.8 | 6 | 0 |
| Nausea | 23 | 0 | 23 | 0.8 |
| Constipation | 15 | 0 | 11 | 0 |
| Abdominal pain includes abdominal pain, abdominal pain lower, abdominal pain upper, flank pain, gastrointestinal pain. | 14 | 1.6 | 6 | 0.8 |
| Vomiting | 13 | 0 | 12 | 1.6 |
| Stomatitis | 8 | 0 | 1.6 | 0 |
| Dyspepsia | 4.8 | 0 | 2.4 | 0 |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Musculoskeletal pain includes arthralgia, back pain, bone pain, musculoskeletal chest pain, musculoskeletal discomfort, musculoskeletal pain, myalgia, neck pain, noncardiac chest pain. | 27 | 1.6 | 40 | 6 |
| Pain in extremity | 4.8 | 0 | 11 | 2.4 |
| Bone fracture includes femoral neck fracture, pathological fracture, rib fracture, spinal compression fracture, sternal fracture, thoracic vertebral fracture. | 3.2 | 1.6 | 8 | 2.4 |
| Infections and Infestations | ||||
| Infections includes bacteremia, bacteriuria, cellulitis, device related sepsis, Enterobacter sepsis, erysipelas, furuncle, influenza, influenza like illness, localized infection, oral fungal infection, perineal cellulitis, pulmonary sepsis, pyelocaliectasis, pyelonephritis, pyelonephritis acute, respiratory tract infection, respiratory tract infection viral, sepsis, septic shock, subcutaneous abscess, upper respiratory tract infection, ureteritis, urinary tract infection, urinary tract infection bacterial, urosepsis, viral infection. | 19 | 4 | 14 | 6 |
| Nervous System Disorders | ||||
| Peripheral neuropathy includes neuropathy peripheral, paresthesia, peripheral motor neuropathy, peripheral sensorimotor neuropathy, peripheral sensory neuropathy. | 18 | 1.6 | 4.8 | 0 |
| Dysgeusia | 11 | 0 | 4 | 0 |
| Polyneuropathy | 6 | 1.6 | 0 | 0 |
| Dizziness | 0.8 | 0 | 4.8 | 0 |
| Renal and Urinary Disorders | ||||
| Hematuria includes hematuria, cystitis hemorrhagic. | 16 | 0.8 | 6 | 1.6 |
| Lower urinary tract symptoms include lower urinary tract symptoms, micturition urgency, nocturia, pollakiuria, urinary incontinence, urinary retention, dysuria. | 10 | 0 | 9 | 0 |
| Acute kidney injury includes acute kidney injury, blood creatinine increased, renal failure, renal impairment. | 5 | 2.4 | 10 | 4 |
| Metabolism and Nutrition Disorders | ||||
| Decreased appetite | 14 | 0.8 | 15 | 2.4 |
| Hypokalemia | 3.2 | 0 | 6 | 0 |
| Neoplasms Benign, Malignant and Unspecified (incl cysts and polyps) | ||||
| Cancer pain | 8 | 1.6 | 9 | 2.4 |
| Cardiac disorders includes aortic valve incompetence, aortic valve stenosis, atrial fibrillation, atrial flutter, atrioventricular block complete, atrioventricular block second degree, bradycardia, sinus bradycardia, tachycardia, cardiac failure, acute coronary syndrome, angina pectoris. | 6 | 0.8 | 6 | 3.2 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Pneumonia includes lower respiratory tract infection, lung infection, lung infiltration, pneumonia. | 6 | 1.6 | 3.2 | 0.8 |
| Dyspnea | 6 | 0 | 2.4 | 0 |
| Skin and Subcutaneous Tissue Disorders | ||||
| Alopecia | 6 | 0 | 0 | 0 |
| Injury, Poisoning and Procedural Complications | ||||
| Fall | 4.8 | 0 | 0 | 0 |
| Vascular Disorders | ||||
| Hypertension includes hypertension, hypertensive crisis. | 4 | 2.4 | 8 | 2.4 |
| Investigations | ||||
| Weight decreased | 4 | 0 | 6 | 0 |
| Psychiatric Disorders | ||||
| Insomnia | 3.2 | 0 | 4.8 | 0 |
Clinically relevant ≥ Grade 3 adverse reactions in <5% of patients who received JEVTANA in combination with prednisone and primary prophylaxis G-CSF: febrile neutropenia (3.2%), pulmonary embolism (1.6%), and neutropenic infection (0.8%).
Hematuria
In study TROPIC, adverse reactions of hematuria, including those requiring medical intervention, were more common in JEVTANA-treated patients. The incidence of grade ≥2 hematuria was 6% in JEVTANA-treated patients and 2% in mitoxantrone-treated patients. Other factors associated with hematuria were well-balanced between arms and do not account for the increased rate of hematuria on the JEVTANA arm.
In study PROSELICA, hematuria of all grades was observed in 18% of patients overall.
In CARD, hematuria of all grades was observed in 16% of patients receiving JEVTANA.
Hepatic Laboratory Abnormalities
The incidences of grade 3–4 increased AST, increased ALT, and increased bilirubin were each ≤1%.
Risk Summary
The safety and efficacy of JEVTANA have not been established in females. There are no human data on the use of JEVTANA in pregnant women to inform the drug-associated risk. In animal reproduction studies, intravenous administration of cabazitaxel in pregnant rats during organogenesis caused embryonic and fetal death at doses lower than the maximum recommended human dose [see Data].
Data
Animal data
In an early embryonic developmental toxicity study in rats, cabazitaxel was administered intravenously for 15 days prior to mating through day 6 of pregnancy, which resulted in an increase in pre-implantation loss at 0.2 mg/kg/day and an increase in early resorptions at ≥0.1 mg/kg/day (approximately 0.06 and 0.02 times the Cmax in patients at the recommended human dose, respectively).
In an embryo-fetal developmental toxicity study in rats, cabazitaxel caused maternal and embryo-fetal toxicity consisting of increased postimplantation loss, embryolethality, and fetal deaths when administered intravenously at a dose of 0.16 mg/kg/day (approximately 0.06 times the Cmax in patients at the recommended human dose). Decreased mean fetal birthweight associated with delays in skeletal ossification was observed at doses ≥0.08 mg/kg. Cabazitaxel crossed the placenta barrier within 24 hours of a single intravenous administration of 0.08 mg/kg to pregnant rats at gestational day 17. A dose of 0.08 mg/kg in rats resulted in a Cmax approximately 0.02 times that observed in patients at the recommended human dose. Administration of cabazitaxel did not result in fetal abnormalities in rats or rabbits at exposure levels significantly lower than the expected human exposures.
Risk Summary
The safety and efficacy of JEVTANA have not been established in females. There is no information available on the presence of cabazitaxel in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production. Cabazitaxel or cabazitaxel metabolites are excreted in maternal milk of lactating rats [see Data].
Data
Animal data
In a milk excretion study, radioactivity related to cabazitaxel was detected in the stomachs of nursing pups within 2 hours of a single intravenous administration of cabazitaxel to lactating rats at a dose of 0.08 mg/kg (approximately 0.02 times the Cmax in patients at the recommended human dose). This was detectable 24 hours post dose. Approximately 1.5% of the dose delivered to the mother was calculated to be delivered in the maternal milk.
Contraception
Males
Based on findings in animal reproduction studies, advise male patients with female partners of reproductive potential to use effective contraception during treatment and for 4 months after the last dose of JEVTANA [see Use in Specific Populations (8.1)].
Infertility
Males
Based on animal toxicology studies, JEVTANA may impair human fertility in males of reproductive potential [see Nonclinical Toxicology (13.1)].
Cardiac Electrophysiology
The effect of cabazitaxel following a single dose of 25 mg/m2 administered by intravenous infusion on QTc interval was evaluated in 94 patients with solid tumors. No large changes in the mean QT interval (i.e., >20 ms) from baseline based on Fridericia correction method were detected. However, a small increase in the mean QTc interval (i.e., <10 ms) cannot be excluded due to study design limitations.
Absorption
Based on the population pharmacokinetic analysis, after an intravenous dose of cabazitaxel 25 mg/m2 every three weeks, the mean Cmax in patients with metastatic prostate cancer was 226 ng/mL (CV 107%) and was reached at the end of the one-hour infusion (Tmax). The mean AUC in patients with metastatic prostate cancer was 991 ng∙h/mL (CV 34%).
No major deviation from the dose proportionality was observed from 10 to 30 mg/m2 in patients with advanced solid tumors.
Distribution
The volume of distribution (Vss) was 4,864 L (2,643 L/m2 for a patient with a median BSA of 1.84 m2) at steady state.
In vitro, the binding of cabazitaxel to human serum proteins was 89% to 92% and was not saturable up to 50,000 ng/mL, which covers the maximum concentration observed in clinical trials. Cabazitaxel is mainly bound to human serum albumin (82%) and lipoproteins (88% for HDL, 70% for LDL, and 56% for VLDL). The in vitro blood-to-plasma concentration ratio in human blood ranged from 0.90 to 0.99, indicating that cabazitaxel was equally distributed between blood and plasma.
Metabolism
Cabazitaxel is extensively metabolized in the liver (>95%), mainly by the CYP3A4/5 isoenzyme (80% to 90%), and to a lesser extent by CYP2C8. Cabazitaxel is the main circulating moiety in human plasma. Seven metabolites were detected in plasma (including the 3 active metabolites issued from O-demethylation), with the main one accounting for 5% of cabazitaxel exposure. Around 20 metabolites of cabazitaxel are excreted into human urine and feces.
Elimination
After a one-hour intravenous infusion [14C]-cabazitaxel 25 mg/m2, approximately 80% of the administered dose was eliminated within 2 weeks. Cabazitaxel is mainly excreted in the feces as numerous metabolites (76% of the dose); while renal excretion of cabazitaxel and metabolites account for 3.7% of the dose (2.3% as unchanged drug in urine).
Based on the population pharmacokinetic analysis, cabazitaxel has a plasma clearance of 48.5 L/h (CV 39%; 26.4 L/h/m2 for a patient with a median BSA of 1.84 m2) in patients with metastatic prostate cancer. Following a one-hour intravenous infusion, plasma concentrations of cabazitaxel can be described by a three-compartment pharmacokinetic model with α-, β-, and γ- half-lives of 4 minutes, 2 hours, and 95 hours, respectively.
Renal Impairment
Cabazitaxel is minimally excreted via the kidney. A population pharmacokinetic analysis carried out in 170 patients including 14 patients with moderate renal impairment (30 mL/min ≤CLCR <50 mL/min) and 59 patients with mild renal impairment (50 mL/min ≤CLCR <80 mL/min) showed that mild to moderate renal impairment did not have meaningful effects on the pharmacokinetics of cabazitaxel. This was confirmed by a dedicated comparative pharmacokinetic study in patients with solid tumors with normal renal function (n=8, CLCR >80 mL/min/1.73 m2), or moderate (n=8, 30 mL/min/1.73 m2 ≤CLCR <50 mL/min/1.73 m2) and severe (n=9, CLCR <30 mL/min/1.73 m2) renal impairment, who received several cycles of cabazitaxel in single IV infusion up to 25 mg/m2. Limited pharmacokinetic data were available in patients with end-stage renal disease (n=2, CLCR <15 mL/min/1.73 m2).
Hepatic Impairment
Cabazitaxel is extensively metabolized in the liver.
A dedicated study in 43 cancer patients with hepatic impairment showed no influence of mild (total bilirubin >1 to ≤1.5 × ULN or AST >1.5 × ULN) or moderate (total bilirubin >1.5 to ≤3.0 × ULN) hepatic impairment on cabazitaxel pharmacokinetics. The maximum tolerated dose (MTD) of cabazitaxel was 20 and 15 mg/m2, respectively.
In 3 patients with severe hepatic impairment (total bilirubin >3 × ULN), a 39% decrease in clearance was observed when compared to patients with mild hepatic impairment (ratio=0.61, 90% CI: 0.36–1.05), indicating some effect of severe hepatic impairment on cabazitaxel pharmacokinetics. The MTD of cabazitaxel in patients with severe hepatic impairment was not established. Based on safety and tolerability data, cabazitaxel dose should be maintained at 20 mg/m2 in patients with mild hepatic impairment and reduced to 15 mg/m2 in patients with moderate hepatic impairment [see Warnings and Precautions (5.8) and Use in Specific Populations (8.7)]. Cabazitaxel is contraindicated in patients with severe hepatic impairment [see Contraindications (4) and Use in Specific Populations (8.7)].
Drug Interactions
A drug interaction study of JEVTANA in 23 patients with advanced cancers has shown that repeated administration of ketoconazole (400 mg orally once daily), a strong CYP3A inhibitor, increased the exposure to cabazitaxel (5 mg/m2 intravenous) by 25%.
A drug interaction study of JEVTANA in 13 patients with advanced cancers has shown that repeated administration of aprepitant (125 or 80 mg once daily), a moderate CYP3A inhibitor, did not modify the exposure to cabazitaxel (15 mg/m2 intravenous).
A drug interaction study of JEVTANA in 21 patients with advanced cancers has shown that repeated administration of rifampin (600 mg once daily), a strong CYP3A inducer, decreased the exposure to cabazitaxel (15 mg/m2 intravenous) by 17%.
A drug interaction study of JEVTANA in 11 patients with advanced cancers has shown that cabazitaxel (25 mg/m2 administered as a single 1-hour infusion) did not modify the exposure to midazolam, a probe substrate of CYP3A.
Prednisone or prednisolone administered at 10 mg daily did not affect the pharmacokinetics of cabazitaxel.
Based on in vitro studies, the potential for cabazitaxel to inhibit drugs that are substrates of other CYP isoenzymes (1A2, -2B6, -2C9, -2C8, -2C19, -2E1, -2D6, and CYP3A4/5) is low. In addition, cabazitaxel did not induce CYP isozymes (-1A, -2C9 and -3A) in vitro.
In vitro, cabazitaxel did not inhibit the multidrug-resistance protein 1 (MRP1), 2 (MRP2) or organic cation transporter (OCT1). In vitro, cabazitaxel inhibited P-gp, BRCP, and organic anion transporting polypeptides (OATP1B1, OATP1B3). However, the in vivo risk of cabazitaxel inhibiting MRPs, OCT1, P-gp, BCRP, OATP1B1 or OATP1B3 is low at the dose of 25 mg/m2.
In vitro, cabazitaxel is a substrate of P-gp, but not a substrate of MRP1, MRP2, BCRP, OCT1, OATP1B1 or OATP1B3.
Hypersensitivity Reactions
Educate patients about the risk of potential hypersensitivity associated with JEVTANA. Confirm patients do not have a history of severe hypersensitivity reactions to cabazitaxel or to other drugs formulated with polysorbate 80. Instruct patients to immediately report signs of a hypersensitivity reaction [see Contraindications (4) and Warnings and Precautions (5.3)].
Bone Marrow Suppression
Inform patients that JEVTANA decreases blood count such as white blood cells, platelets and red blood cells. Thus, it is important that periodic assessment of their blood count be performed to detect the development of neutropenia, thrombocytopenia, anemia, and/or pancytopenia [see Contraindications (4) and Warnings and Precautions (5.1)]. Instruct patients to monitor their temperature frequently and immediately report any occurrence of fever to their healthcare provider.
Increased Toxicities in Elderly Patients
Inform elderly patients that certain side effects may be more frequent or severe [see Warnings and Precautions (5.2) and Use in Specific Populations (8.5)].
Importance of Prednisone
Explain that it is important to take the oral prednisone as prescribed. Instruct patients to report if they were not compliant with oral corticosteroid regimen [see Dosage and Administration (2.1)].
Infections, Dehydration, Renal Failure
Explain to patients that severe and fatal infections, dehydration, and renal failure have been associated with cabazitaxel exposure. Patients should immediately report fever, significant vomiting or diarrhea, decreased urinary output, and hematuria to their healthcare provider [see Warnings and Precautions (5.1, 5.4, 5.5)].
Urinary Disorders Including Cystitis
Inform patients that hematuria may occur during treatment with JEVTANA. Inform patients that previously received pelvic radiation that cystitis and radiation cystitis may occur during treatment with JEVTANA. Advise patients to report any occurrence of hematuria, or any signs and symptoms of cystitis or radiation cystitis, to their healthcare provider [see Warnings and Precautions (5.6)].
Respiratory Disorders
Explain to patients that severe and fatal interstitial pneumonia/pneumonitis, interstitial lung disease and acute respiratory distress syndrome have occurred with JEVTANA. Instruct patients to immediately report new or worsening pulmonary symptoms to their healthcare provider [see Warnings and Precautions (5.7)].
Drug Interactions
Inform patients about the risk of drug interactions and the importance of providing a list of prescription and non-prescription drugs to their healthcare provider [see Drug Interactions (7.1)].
Embryo-Fetal Toxicity
Advise male patients with female partners of reproductive potential to use effective contraception during treatment and for 4 months after the last dose of JEVTANA [see Use in Specific Populations (8.3)].
Infertility
Advise male patients that JEVTANA may impair fertility [see Use in Specific Populations (8.3)].
Manufactured by:
sanofi-aventis U.S. LLC
Morristown, NJ 07960
A SANOFI COMPANY
JEVTANA is a registered trademark of sanofi-aventis
©2025 sanofi-aventis U.S. LLC