Prophylaxis of VTE Following Hip Replacement Surgery: Table 2 presents the dosing options for patients undergoing hip replacement surgery. The usual duration of administration is 5 days to 10 days after surgery; up to 14 days of treatment with FRAGMIN have been well tolerated in clinical trials.
| Table 2 |
|---|
| Dosing Options for Patients Undergoing Hip Replacement Surgery |
|---|
Timing of First Dose of FRAGMIN | Dose of FRAGMIN to be Given Subcutaneously |
10 Hours to 14 Hours Before Surgery | Within 2 Hours Before Surgery | 4 Hours to 8 Hours After Surgery Or later, if hemostasis has not been achieved. | Postoperative Period Up to 14 days of treatment was well tolerated in controlled clinical trials, where the usual duration of treatment was 5 days to 10 days postoperatively. |
Postoperative Start | --- | --- | 2,500 units Allow a minimum of 6 hours between this dose and the dose to be given on Postoperative Day 1. Adjust the timing of the dose on Postoperative Day 1 accordingly. | 5,000 units once daily |
Preoperative Start - Day of Surgery | --- | 2,500 units | 2,500 units | 5,000 units once daily |
Preoperative Start - Evening Before Surgery Allow approximately 24 hours between doses. | 5,000 units | --- | 5,000 units | 5,000 units once daily |
Abdominal Surgery: In patients undergoing abdominal surgery with a risk of thromboembolic complications, the recommended dose of FRAGMIN is 2,500 units administered by subcutaneous injection once daily, starting 1 hour to 2 hours prior to surgery and repeated once daily postoperatively. The usual duration of administration is 5 days to 10 days.
In patients undergoing abdominal surgery associated with a high risk of thromboembolic complications, such as malignant disorder, the recommended dose of FRAGMIN is 5,000 units subcutaneously the evening before surgery, then once daily postoperatively. The usual duration of administration is 5 days to 10 days. Alternatively, in patients with malignancy, 2,500 units of FRAGMIN can be administered subcutaneously 1 hour to 2 hours before surgery followed by 2,500 units subcutaneously 12 hours later, and then 5,000 units once daily postoperatively. The usual duration of administration is 5 days to 10 days.
Medical Patients During Acute Illness: In medical patients with severely restricted mobility during acute illness, the recommended dose of FRAGMIN is 5,000 units administered by subcutaneous injection once daily. In clinical trials, the usual duration of administration was 12 days to 14 days.
Month 1
| Table 3 |
|---|
| Dose of FRAGMIN to be Administered Subcutaneously by Patient Weight during the First Month |
|---|
Body Weight (kg) | FRAGMIN Dose (units)
(prefilled syringe) once daily |
≤56 kg | 10,000 units |
57 kg to 68 kg | 12,500 units |
69 kg to 82 kg | 15,000 units |
83 kg to 98 kg | 18,000 units |
≥99 kg | 18,000 units |
Months 2 to 6
Administer FRAGMIN at a dose of approximately 150 units/kg, subcutaneously once daily during Months 2 through 6. The total daily dose should not exceed 18,000 units. Table 4 lists the dose of FRAGMIN to be administered once daily for a range of patient weights during months 2 to 6.
| Table 4 |
|---|
| Dose of FRAGMIN to be Administered Subcutaneously by Patient Weight during Months 2 to 6 |
|---|
Body Weight (kg) | FRAGMIN Dose (units)
(prefilled syringe)
once daily |
≤56 kg | 7,500 units |
57 kg to 68 kg | 10,000 units |
69 kg to 82 kg | 12,500 units |
83 kg to 98 kg | 15,000 units |
≥99 kg | 18,000 units |
Safety and efficacy beyond six months have not been evaluated in patients with cancer and acute symptomatic VTE [see Warnings and Precaution (5) and Adverse Reactions (6.1)].
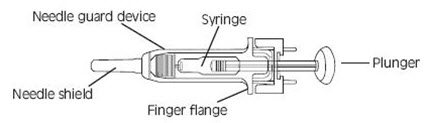
Instructions for using the prefilled single-dose syringes preassembled with needle guard devices
Fixed dose syringes: To ensure delivery of the full dose, do not expel the air bubble from the prefilled syringe before injection. Hold the syringe assembly by the open sides of the device. Remove the needle shield. Insert the needle into the injection area as instructed above. Depress the plunger of the syringe while holding the finger flange until the entire dose has been given. The needle guard will not be activated unless the entire dose has been given. Remove needle from the patient. Let go of the plunger and allow syringe to move up inside the device until the entire needle is guarded. Discard the syringe assembly in approved containers.
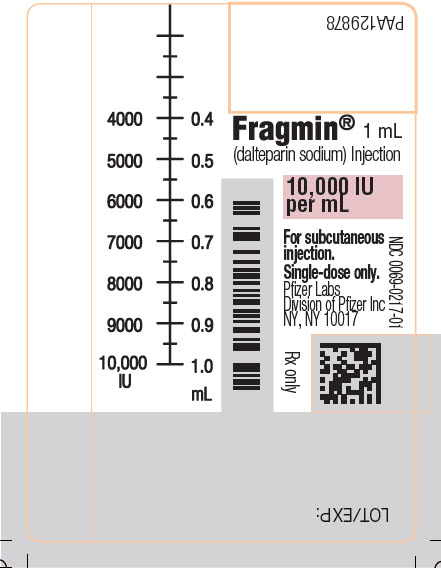
Graduated syringes: Hold the syringe assembly by the open sides of the device. Remove the needle shield. With the needle pointing up, prepare the syringe by expelling the air bubble and then continuing to push the plunger to the desired dose or volume, discarding the extra solution in an appropriate manner. Insert the needle into the injection area as instructed above. Depress the plunger of the syringe while holding the finger flange until the entire dose remaining in the syringe has been given. The needle guard will not be activated unless the entire dose has been given. Remove needle from the patient. Let go of the plunger and allow syringe to move up inside the device until the entire needle is guarded. Discard the syringe assembly in approved containers.
Hemorrhage
The most commonly reported adverse reactions are hematoma at the injection site and hemorrhagic complications. The risk for bleeding varies with the indication and may increase with higher doses.
Unstable Angina and Non-Q-Wave Myocardial Infarction
Table 7 summarizes major bleeding reactions that occurred with FRAGMIN, heparin, and placebo in clinical trials of unstable angina and non-Q-wave myocardial infarction.
| Table 7 |
|---|
| Major Bleeding Reactions in Unstable Angina and Non-Q-Wave Myocardial Infarction |
|---|
Indication | Dosing Regimen |
Unstable Angina and Non-Q-Wave MI | FRAGMIN
120 units/kg/12 hours subcutaneous Treatment was administered for 5 days to 8 days.
n (%) | Heparin Heparin intravenous infusion for at least 48 hours, APTT 1.5 to 2 times control, then 12,500 units subcutaneously every 12 hours for 5 days to 8 days.
intravenous and subcutaneous
n (%) | Placebo
every 12 hours subcutaneous
n (%) |
Major Bleeding Reactions Aspirin (75 mg to 165 mg per day) and beta blocker therapies were administered concurrently. ,Bleeding reactions were considered major if: 1) accompanied by a decrease in hemoglobin of ≥2 g/dL in connection with clinical symptoms; 2) a transfusion was required; 3) bleeding led to interruption of treatment or death; or 4) intracranial bleeding. | 15/1497 (1.0) | 7/731 (1.0) | 4/760 (0.5) |
Hip Replacement Surgery
Table 8 summarizes: 1) all major bleeding reactions and, 2) other bleeding reactions possibly or probably related to treatment with FRAGMIN (preoperative dosing regimen), warfarin sodium, or heparin in two hip replacement surgery clinical trials.
| Table 8 |
|---|
| Bleeding Reactions Following Hip Replacement Surgery |
|---|
Indication | FRAGMIN vs Warfarin Sodium | FRAGMIN vs Heparin |
Dosing Regimen | Dosing Regimen |
Hip Replacement Surgery | FRAGMIN Includes three treated patients who did not undergo a surgical procedure.
5,000 units once daily subcutaneous | Warfarin
Sodium Warfarin sodium dosage was adjusted to maintain a prothrombin time index of 1.4 to 1.5, corresponding to an International Normalized Ratio (INR) of approximately 2.5. oral | FRAGMIN Includes two treated patients who did not undergo a surgical procedure.
5,000 units once daily subcutaneous | Heparin
5,000 units three times a day subcutaneous |
n (%) | n (%) | n (%) | n (%) |
Major Bleeding Reactions A bleeding event was considered major if: 1) hemorrhage caused a significant clinical event, 2) it was associated with a hemoglobin decrease of ≥2 g/dL or transfusion of 2 or more units of blood products, 3) it resulted in reoperation due to bleeding, or 4) it involved retroperitoneal or intracranial hemorrhage. | 7/274 (2.6) | 1/279 (0.4) | 0 | 3/69 (4.3) |
Other Bleeding Reactions Occurred at a rate of at least 2% in the group treated with FRAGMIN 5,000 units once daily.
Hematuria | 8/274 (2.9) | 5/279 (1.8) | 0 | 0 |
Wound Hematoma | 6/274 (2.2) | 0 | 0 | 0 |
Injection Site Hematoma | 3/274 (1.1) | NA | 2/69 (2.9) | 7/69 (10.1) |
Six of the patients treated with FRAGMIN experienced seven major bleeding reactions. Two of the reactions were wound hematoma (one requiring reoperation), three were bleeding from the operative site, one was intraoperative bleeding due to vessel damage, and one was gastrointestinal bleeding.
In the third hip replacement surgery clinical trial, the incidence of major bleeding reactions was similar in all three treatment groups: 3.6% (18/496) for patients who started FRAGMIN before surgery; 2.5% (12/487) for patients who started FRAGMIN after surgery; and 3.1% (15/489) for patients treated with warfarin sodium.
Abdominal Surgery
Table 9 summarizes bleeding reactions that occurred in clinical trials which studied FRAGMIN 2,500 units and 5,000 units administered once daily to abdominal surgery patients.
| Table 9 |
|---|
| Bleeding Reactions Following Abdominal Surgery |
|---|
Indication | FRAGMIN vs Placebo | FRAGMIN vs FRAGMIN |
Dosing Regimen | Dosing Regimen |
Abdominal Surgery | FRAGMIN
2,500 units
once daily subcutaneous
n (%) | Placebo
once daily subcutaneous
n (%) | FRAGMIN
2,500 units
once daily subcutaneous
n (%) | FRAGMIN
5,000 units
once daily subcutaneous
n (%) |
Postoperative Transfusions | 14/182
(7.7) | 13/182
(7.1) | 89/1,025
(8.7) | 125/1,033
(12.1) |
Wound Hematoma | 2/79
(2.5) | 2/77
(2.6) | 1/1,030
(0.1) | 4/1,039
(0.4) |
Reoperation Due to Bleeding | 1/79
(1.3) | 1/78
(1.3) | 2/1,030
(0.2) | 13/1,038
(1.3) |
Injection Site Hematoma | 8/172
(4.7) | 2/174
(1.1) | 36/1,026
(3.5) | 57/1,035
(5.5) |
| Table 9 Cont. |
|---|
| Bleeding Reactions Following Abdominal Surgery |
|---|
Indication | FRAGMIN vs Heparin |
Dosing Regimen |
Abdominal Surgery | FRAGMIN
2,500 units
once daily subcutaneous
n (%) | Heparin
5,000 units
twice daily subcutaneous
n (%) | FRAGMIN
5,000 units
once daily subcutaneous
n (%) | Heparin
5,000 units
twice daily subcutaneous
n (%) |
Postoperative Transfusions | 26/459
(5.7) | 36/454
(7.9) | 81/508
(15.9) | 63/498
(12.7) |
Wound Hematoma | 16/467
(3.4) | 18/467
(3.9) | 12/508
(2.4) | 6/498
(1.2) |
Reoperation Due to Bleeding | 2/392
(0.5) | 3/392
(0.8) | 4/508
(0.8) | 2/498
(0.4) |
Injection Site Hematoma | 1/466
(0.2) | 5/464
(1.1) | 36/506
(7.1) | 47/493
(9.5) |
In a trial comparing FRAGMIN 5,000 units once daily to FRAGMIN 2,500 units once daily in patients undergoing surgery for malignancy, the incidence of bleeding reactions was 4.6% and 3.6%, respectively (n.s.). In a trial comparing FRAGMIN 5,000 units once daily to heparin 5,000 units twice daily, in the malignancy subgroup the incidence of bleeding reactions was 3.2% and 2.7%, respectively for FRAGMIN and Heparin (n.s.).
Medical Patients with Severely Restricted Mobility During Acute Illness
Table 10 summarizes major bleeding reactions that occurred in a clinical trial of medical patients with severely restricted mobility during acute illness.
| Table 10 |
|---|
| Bleeding Reactions in Medical Patients with Severely Restricted Mobility During Acute Illness |
|---|
Indication | Dosing Regimen |
Medical Patients with Severely Restricted Mobility | FRAGMIN
5,000 units once daily subcutaneous
n (%) | Placebo
once daily subcutaneous
n (%) |
Major Bleeding Reactions A bleeding event was considered major if: 1) it was accompanied by a decrease in hemoglobin of ≥2 g/dL in connection with clinical symptoms; 2) intraocular, spinal/epidural, intracranial, or retroperitoneal bleeding; 3) required transfusion of ≥2 units of blood products; 4) required significant medical or surgical intervention; or 5) led to death. at Day 14 | 8/1,848 (0.4) | 0/1,833 (0) |
Major Bleeding Reactions at Day 21 | 9/1,848 (0.5) | 3/1,833 (0.2) |
Three of the major bleeding reactions that occurred by Day 21 were fatal, all due to gastrointestinal hemorrhage (two patients in the group treated with FRAGMIN and one in the group receiving placebo).
Adult Patients with Cancer and Acute Symptomatic VTE
Table 11 summarizes the number of patients with bleeding reactions that occurred in the clinical trial of adult patients with cancer and acute symptomatic VTE. A bleeding event was considered major if it: 1) was accompanied by a decrease in hemoglobin of ≥2 g/dL in connection with clinical symptoms; 2) occurred at a critical site (intraocular, spinal/epidural, intracranial, retroperitoneal, or pericardial bleeding); 3) required transfusion of ≥2 units of blood products; or 4) led to death. Minor bleeding was classified as clinically overt bleeding that did not meet criteria for major bleeding.
At the end of the six-month study, a total of 46 (13.6%) patients in the FRAGMIN arm and 62 (18.5%) patients in the OAC arm experienced any bleeding event. One bleeding event (hemoptysis in a patient in the FRAGMIN arm at Day 71) was fatal.
| Table 11 |
|---|
| Bleeding Reactions (Major and Any) (As treated population) Patients with multiple bleeding episodes within any time interval were counted only once in that interval. However, patients with multiple bleeding episodes that occurred at different time intervals were counted once in each interval in which the event occurred. |
|---|
Study period | FRAGMIN 200 units/kg (max. 18,000 units) subcutaneous once daily x 1 month, then 150 units/kg (max. 18,000 units) subcutaneous once daily x 5 months | OAC FRAGMIN 200 units/kg (max 18,000 units) subcutaneous once daily x 5 to 7 days and OAC for 6 months (target INR 2 to 3) |
Number at risk | Patients with Major Bleeding n (%) | Patients with Any Bleeding n (%) | Number at risk | Patients with Major Bleeding n (%) | Patients with Any Bleeding n (%) |
Total during study | 338 | 19 (5.6) | 46 (13.6) | 335 | 12 (3.6) | 62 (18.5) |
Week 1 | 338 | 4 (1.2) | 15 (4.4) | 335 | 4 (1.2) | 12 (3.6) |
Weeks 2 to 4 | 332 | 9 (2.7) | 17 (5.1) | 321 | 1 (0.3) | 12 (3.7) |
Weeks 5 to 28 | 297 | 9 (3.0) | 26 (8.8) | 267 | 8 (3) | 40 (15) |
Elevations of Serum Transaminases
In FRAGMIN clinical trials supporting non-cancer indications, where hepatic transaminases were measured, asymptomatic increases in transaminase levels (SGOT/AST and SGPT/ALT) greater than three times the upper limit of normal of the laboratory reference range were seen in 4.7% and 4.2%, respectively, of patients during treatment with FRAGMIN.
In the FRAGMIN clinical trial of patients with cancer and acute symptomatic venous thromboembolism treated with FRAGMIN for up to 6 months, asymptomatic increases in transaminase levels, AST and ALT, greater than three times the upper limit of normal of the laboratory reference range were reported in 8.9% and 9.5% of patients, respectively. The frequencies of Grades 3 and 4 increases in AST and ALT, as classified by the National Cancer Institute, Common Toxicity Criteria (NCI-CTC) Scoring System, were 3% and 3.8%, respectively. Grades 2, 3 & 4 combined have been reported in 12% and 14% of patients, respectively.
Other
Allergic Reactions: Allergic reactions (i.e., pruritus, rash, fever, injection site reaction, bullous eruption) have occurred. Cases of anaphylactoid reactions have been reported.
Local Reactions: Pain at the injection site was reported in 4.5% of patients treated with FRAGMIN 5,000 units once daily vs 11.8% of patients treated with heparin 5,000 units twice daily in the abdominal surgery trials. In the hip replacement trials, pain at injection site was reported in 12% of patients treated with FRAGMIN 5,000 units once daily vs 13% of patients treated with heparin 5,000 units three times a day.
Pediatric Patients with Symptomatic VTE
The data below reflect exposure to FRAGMIN from two studies in pediatric patients from newborn to less than 18 years of age with or without cancer and symptomatic VTE (n = 50). Patients were started on FRAGMIN using age and weight-based dosing via subcutaneous injection twice daily. Anti-Xa levels were measured prior to the 4th dose and then periodically to determine whether dose adjustments were required, using 25 units/kg increments, to achieve a target anti-Xa level of 0.5 units/mL to 1.0 units/mL. The median time on treatment with FRAGMIN was 86 days (range 2 days to 170 days).
In pediatric patients with symptomatic VTE, the most common (greater than 10%) adverse reactions were injection site bruising (30%), contusion (12%), and epistaxis (10%).
Major bleeding was defined as any fatal bleeding, clinically overt bleeding with a decrease in hemoglobin of ≥2g/dL in 24 hours, overt bleeding deemed by the attending physician to be unrelated to the subject's underlying condition and accompanied by blood product administration, overt bleeding that was retroperitoneal, intracranial, intraspinal, intraocular, or intraarticular, or overt bleeding deemed by the attending physician to necessitate permanent discontinuation of trial medication. Major bleeding (intestinal hematoma) occurred in one patient (2%). Discontinuation due to adverse reactions occurred in 12% of patients, most often due to thrombocytopenia (4%).
Risk Summary
Available data from published literature and postmarketing reports have not reported a clear association with FRAGMIN and adverse developmental outcomes. There are risks to the mother associated with untreated VTE in pregnancy, and a potential for adverse effects on the preterm infant when FRAGMIN is used in pregnancy (see Clinical Considerations). In animal reproduction studies, there was no evidence of embryo-fetal toxicity or teratogenicity when dalteparin sodium was administered to pregnant rats and rabbits during organogenesis at doses 2 to 4 times (rats) and 4 times (rabbits) the human dose of 100 units/kg dalteparin based on the body surface area (see Data). Because animal reproduction studies are not always predictive of human response, FRAGMIN should be used during pregnancy only if clearly needed.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
Published data describe that women with a previous history of VTE in pregnancy are at higher risk for recurrence during subsequent pregnancies compared to those with no risk factor for VTE (4.5% versus 2.7% respectively, relative risk 1.7, 95% CI: 1.0–2.8).
Fetal/Neonatal Adverse Reactions
Cases of "gasping syndrome" have occurred in premature infants when large amounts of benzyl alcohol have been administered (99 mg/kg/day to 404 mg/kg/day). The 3.8 mL multiple-dose vials of FRAGMIN contain 14 mg/mL of benzyl alcohol [see Warnings and Precautions (5.3)].
Data
Animal Data
In reproductive and developmental toxicity studies, pregnant rats and rabbits received dalteparin sodium during organogenesis at intravenous doses up to 2,400 units/kg (14,160 units/m2) (rats) and 4,800 units/kg (40,800 units/m2) (rabbits). These exposures were 2 to 4 times (rats) and 4 times (rabbits) the human dose of 100 units/kg dalteparin based on the body surface area. These studies revealed no evidence of teratogenicity or embryo-fetal toxicity.
Risk Summary
Limited published data indicate that dalteparin is present in human milk in small amounts (see Data). No adverse effects on the breastfed infant have been reported. There are no data on the effects of the drug on milk production. Oral absorption of dalteparin is expected to be low, but the clinical implications, if any, of this small amount of anticoagulant activity on a breastfed infant are unknown. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for FRAGMIN and any potential adverse effects on the breastfed child from FRAGMIN or from the underlying maternal condition.
Data
A study evaluated samples of maternal blood and breast milk in 15 lactating women receiving prophylactic doses of dalteparin in the immediate postpartum period (days 4 to 8 after Cesarean-section). The samples were collected before and 3 hours to 4 hours after daily injections of 2500 units dalteparin. Small amounts of anti-Xa activity (range <0.005 to 0.037 units/mL) in breast milk were detected in 11 of the 15 women. Because this study evaluated colostrum or transitional milk at a single timepoint during the 24 hours dosing interval, the clinical relevance of this data is unclear in regard to passage of drug into mature milk and the quantification of drug exposure to the infant over the full dosing interval.
Adults
Mean peak levels of plasma anti-Xa activity following single subcutaneous doses of 2,500 units, 5,000 units and 10,000 units were 0.19 ± 0.04 units/mL, 0.41 ± 0.07 units/mL and 0.82 ± 0.10 units/mL, respectively, and were attained in about 4 hours in most subjects. Absolute bioavailability in healthy volunteers, measured as the anti-Xa activity, was 87 ± 6%. Increasing the dose from 2,500 units to 10,000 units resulted in an overall increase in anti-Xa AUC that was greater than proportional by about one-third.
Peak anti-Xa activity increased more or less linearly with dose over the same dose range. There appeared to be no appreciable accumulation of anti-Xa activity with twice-daily dosing of 100 units/kg subcutaneously for up to 7 days.
The volume of distribution for dalteparin anti-Xa activity was 40 mL/kg to 60 mL/kg. The mean plasma clearances of dalteparin anti-Xa activity in normal volunteers following single intravenous bolus doses of 30 and 120 anti-Xa units/kg were 24.6 ± 5.4 mL/hr/kg and 15.6 ± 2.4 mL/hr/kg, respectively. The corresponding mean disposition half-lives were 1.47 ± 0.3 hours and 2.5 ± 0.3 hours.
Following intravenous doses of 40 units/kg and 60 units/kg, mean terminal half-lives were 2.1 ± 0.3 hours and 2.3 ± 0.4 hours, respectively. Longer apparent terminal half-lives (3 hours to 5 hours) are observed following subcutaneous dosing, possibly due to delayed absorption. In patients with chronic renal insufficiency requiring hemodialysis, the mean terminal half-life of anti-Xa activity following a single intravenous dose of 5,000 units FRAGMIN was 5.7 ± 2.0 hours, i.e., considerably longer than values observed in healthy volunteers, therefore, greater accumulation can be expected in these patients.
Pediatric Patients
The pharmacokinetics of twice-daily subcutaneous dalteparin, measured as anti-Xa activity, was characterized in 89 pediatric patients with or without cancer from two clinical studies and 1 observational study. Dalteparin pharmacokinetics (PK) were described by a 1-compartment model with linear absorption and elimination and PK parameters are shown in Table 12. After correcting for the body weight, clearance (CL/F) decreased with increasing age, while volume of distribution at steady-state (Vd/F) remained similar. The mean elimination half-life increased with age.
| Table 12 |
|---|
| Pharmacokinetic Parameters of Dalteparin in Pediatric Population |
|---|
| Abbreviations: CL=clearance; F=absolute bioavailability; SD=standard deviation; t½β=elimination half-life; Vd=volume of distribution. |
Parameter | 3 Weeks to <8 Weeks | ≥8 Weeks to <2 Years | ≥2 Years to <8 Years | ≥8 Years to <12 Years | ≥12 Years to <20 Years |
Median Age (range) (years) | 0.06 (0.04 – 0.14) | 0.5 (0.2 – 1.91) | 4.47 (2.01 – 7.6) | 9.62 (8.01 – 10.5) | 15.9 (12.0 – 19.5) |
Derived Mean (SD) CL/F (mL/h/kg) | 55.8 (3.91) | 40.4 (8.49) | 26.7 (4.75) | 22.4 (3.40) | 18.8 (3.01) |
Derived Mean (SD) Vd/F (mL/kg) | 181 (15.3) | 175 (55.3) | 160 (25.6) | 165 (27.3) | 171 (38.9) |
Derived Mean (SD) t½β (h) | 2.25 (0.173) | 3.02 (0.688) | 4.27 (1.05) | 5.11 (0.509) | 6.28 (0.937) |
Advise the patient to read the FDA-approved patient labeling (Patient Information).
Risk of Hemorrhage including Spinal/Epidural Hematomas
If patients have had neuraxial anesthesia or spinal puncture, and particularly, if they are taking concomitant NSAIDs, platelet inhibitors, or other anticoagulants, inform the patients to watch for signs and symptoms of spinal or epidural hematoma, such as tingling, numbness (especially in the lower limbs) and muscular weakness. If any of these symptoms occur the patient should contact his or her physician immediately.
Additionally, the use of aspirin and other NSAIDs may enhance the risk of hemorrhage. Discontinue their use prior to FRAGMIN therapy whenever possible; if co-administration is essential, the patient's clinical and laboratory status should be closely monitored [see Drug Interactions (7)].
Inform Patients:
- of the instructions for injecting FRAGMIN if their therapy is to continue after discharge from the hospitals.
- it may take them longer than usual to stop bleeding.
- they may bruise and/or bleed more easily when they are treated with FRAGMIN.
- they should report any unusual bleeding, bruising, or signs of thrombocytopenia (such as a rash of dark red spots under the skin) to their physician [see Warnings and Precautions (5.1, 5.2)].
- to tell their physicians and dentists they are taking FRAGMIN and/or any other product known to affect bleeding before any surgery is scheduled and before any new drug is taken [see Warnings and Precautions (5.1)].
- to tell their physicians and dentists of all medications they are taking, including those obtained without a prescription, such as aspirin or other NSAIDs [see Drug Interactions (7)].
- Risks are associated with benzyl alcohol in neonates, infants, and pregnant women [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1)].
- to tell their physicians and care givers if they are allergic to natural rubber latex [see Dosage and Administration (2.7)].
This product's labeling may have been updated. For the most recent prescribing information, please visit www.pfizer.com.
FRAGMIN is a registered trademark of Pfizer Health AB.
LAB-0058-25.0