Limitations of Use: The safety and efficacy of XALKORI have not been established in older adults with relapsed or refractory, systemic ALK-positive ALCL.
ALK- or ROS1-Positive Metastatic NSCLC
The data described below is based primarily on 343 patients with ALK-positive metastatic NSCLC who received XALKORI 250 mg orally twice daily from 2 open-label, randomized, active-controlled trials (Studies 1 and 2). The safety of XALKORI was also evaluated in 50 patients with ROS1-positive metastatic NSCLC from a single-arm study (Study 3).
The most common adverse reactions (≥25%) of XALKORI in patients with NSCLC are vision disorders, nausea, diarrhea, vomiting, edema, constipation, elevated transaminases, fatigue, decreased appetite, upper respiratory infection, dizziness, and neuropathy.
Previously Untreated ALK-Positive Metastatic NSCLC - Study 1 (PROFILE 1014)
The data in Table 9 are derived from 340 patients with ALK-positive metastatic NSCLC who had not received previous systemic treatment for advanced disease who received treatment in a randomized, multicenter, open-label, active-controlled trial (Study 1). Patients in the XALKORI arm (n=171) received XALKORI 250 mg orally twice daily until documented disease progression, intolerance to therapy, or the investigator determined that the patient was no longer experiencing clinical benefit. A total of 169 patients in the chemotherapy arm received pemetrexed 500 mg/m2 with cisplatin 75 mg/m2 (n=91) or carboplatin at a dose calculated to produce an AUC of 5 or 6 mg×min/mL (n=78). Chemotherapy was given by intravenous infusion every 3 weeks for up to 6 cycles, in the absence of dose-limiting chemotherapy-related toxicities. After 6 cycles, patients remained on study with no additional anticancer treatment, and tumor assessments continued until documented disease progression.
The median duration of study treatment was 10.9 months for patients in the XALKORI arm and 4.1 months for patients in the chemotherapy arm. Median duration of treatment was 5.2 months for patients who received XALKORI after cross over from chemotherapy. Across the 340 patients who were treated in Study 1, the median age was 53 years; 16% of patients were older than 65 years. A total of 62% of patients were female and 46% were Asian.
Serious adverse events were reported in 34% of patients treated with XALKORI. The most frequent serious adverse events reported in patients treated with XALKORI were dyspnea (4.1%) and pulmonary embolism (2.9%). Fatal adverse events in XALKORI-treated patients occurred in 2.3% patients, consisting of septic shock, acute respiratory failure, and diabetic ketoacidosis.
Dose reductions due to adverse reactions were required in 6% of XALKORI-treated patients. The most frequent adverse reactions that led to dose reduction in these patients were nausea (1.8%) and elevated transaminases (1.8%).
Permanent discontinuation of XALKORI treatment for adverse reactions was 8%. The most frequent adverse reactions that led to permanent discontinuation in XALKORI-treated patients were elevated transaminases (1.2%), hepatotoxicity (1.2%), and ILD (1.2%).
Tables 9 and 10 summarize common adverse reactions and laboratory abnormalities in XALKORI-treated patients.
Table 9. Adverse Reactions Reported at a Higher Incidence (≥5% Higher for All Grades or ≥2% Higher for Grades 3–4) with XALKORI than Chemotherapy in Study 1Adverse reactions were graded using NCI CTCAE version 4.0.
Includes cases reported within the clustered terms:
| Adverse Reaction | XALKORI
(N=171) | Chemotherapy
(Pemetrexed/Cisplatin or Pemetrexed/Carboplatin)
(N=169) |
|---|
All Grades
(%) | Grade 3–4
(%) | All Grades
(%) | Grade 3–4
(%) |
|---|
Cardiac | | | | |
Bradycardia Bradycardia (Bradycardia, Sinus bradycardia). | 14 | 1 | 1 | 0 |
Electrocardiogram QT prolonged | 6 | 2 | 2 | 0 |
Eye | | | | |
Vision disorder Vision Disorder (Diplopia, Photophobia, Photopsia, Reduced visual acuity, Blurred vision, Vitreous floaters, Visual impairment). | 71 | 1 | 10 | 0 |
Gastrointestinal | | | | |
Diarrhea | 61 | 2 | 13 | 1 |
Vomiting | 46 | 2 | 36 | 3 |
Constipation | 43 | 2 | 30 | 0 |
Abdominal pain Abdominal pain (Abdominal discomfort, Abdominal pain, Lower abdominal pain, Upper abdominal pain, Abdominal tenderness). | 26 | 0 | 12 | 0 |
Dyspepsia | 14 | 0 | 2 | 0 |
Dysphagia | 10 | 1 | 2 | 1 |
Esophagitis Esophagitis (Esophagitis, Esophageal ulcer). | 6 | 2 | 1 | 0 |
General | | | | |
Edema Edema (Edema, Peripheral edema, Face edema, Generalized edema, Local swelling, Periorbital edema). | 49 | 1 | 12 | 1 |
Pyrexia | 19 | 0 | 11 | 1 |
Infections | | | | |
Upper respiratory infection Upper respiratory infection (Nasopharyngitis, Pharyngitis, Rhinitis, Upper respiratory tract infection). | 32 | 0 | 12 | 1 |
Investigations | | | | |
Increased weight | 8 | 1 | 2 | 0 |
Musculoskeletal and Connective Tissue | | | | |
Pain in extremity | 16 | 0 | 7 | 0 |
Muscle spasm | 8 | 0 | 2 | 1 |
Nervous System | | | | |
Dysgeusia | 26 | 0 | 5 | 0 |
Headache | 22 | 1 | 15 | 0 |
Dizziness Dizziness (Balance disorder, Dizziness, Postural dizziness, Presyncope). | 18 | 0 | 10 | 1 |
Additional adverse reactions occurring at an overall incidence between 1% and 60% in patients treated with XALKORI included nausea (56%), decreased appetite (30%), fatigue (29%), neuropathy (21%; gait disturbance, hypoesthesia, muscular weakness, neuralgia, neuropathy peripheral, paresthesia, peripheral sensory neuropathy, polyneuropathy, sensory disturbance), rash (11%), renal cyst (5%), ILD (1%; ILD, pneumonitis), syncope (1%), and decreased blood testosterone (1%; hypogonadism).
Clinically relevant adverse reactions in <1% of patients who received XALKORI included photosensitivity (0.3%).
Table 10. Laboratory Abnormalities with Grades 3–4 Occurring in ≥4% of XALKORI-Treated Patients in Study 1 | XALKORI | Chemotherapy |
|---|
| Laboratory Abnormality | Any Grade
(%) | Grade 3–4
(%) | Any Grade
(%) | Grade 3–4
(%) |
|---|
| Additional laboratory test abnormality in patients treated with XALKORI was an increase in creatinine (Any Grade: 99%; Grade 3: 2%; Grade 4: 0%) compared to the chemotherapy arm (Any Grade: 92%; Grade 3: 0%; Grade 4: 1%). |
Hematology | | | | |
Neutropenia | 52 | 11 | 59 | 16 |
Lymphopenia | 48 | 7 | 53 | 13 |
Chemistry | | | | |
Increased ALT | 79 | 15 | 33 | 2 |
Increased AST | 66 | 8 | 28 | 1 |
Hypophosphatemia | 32 | 10 | 21 | 6 |
Previously Treated ALK-Positive Metastatic NSCLC - Study 2 (PROFILE 1007)
The data in Table 11 are derived from 343 patients with ALK-positive metastatic NSCLC enrolled in a randomized, multicenter, active-controlled, open-label trial (Study 2). Patients in the XALKORI arm (n=172) received XALKORI 250 mg orally twice daily until documented disease progression, intolerance to therapy, or the investigator determined that the patient was no longer experiencing clinical benefit. A total of 171 patients in the chemotherapy arm received pemetrexed 500 mg/m2 (n=99) or docetaxel 75 mg/m2 (n=72) by intravenous infusion every 3 weeks until documented disease progression, intolerance to therapy, or the investigator determined that the patient was no longer experiencing clinical benefit. Patients in the chemotherapy arm received pemetrexed unless they had received pemetrexed as part of first-line or maintenance treatment.
The median duration of study treatment was 7.1 months for patients who received XALKORI and 2.8 months for patients who received chemotherapy. Across the 347 patients who were randomized to study treatment (343 received at least 1 dose of study treatment), the median age was 50 years; 14% of patients were older than 65 years. A total of 56% of patients were female and 45% of patients were Asian.
Serious adverse reactions were reported in 37% of patients treated with XALKORI and 23% of patients in the chemotherapy arm. The most frequent serious adverse reactions reported in patients treated with XALKORI were pneumonia (4.1%), pulmonary embolism (3.5%), dyspnea (2.3%), and ILD (2.9%). Fatal adverse reactions in XALKORI-treated patients in Study 2 occurred in 5% of patients, consisting of: acute respiratory distress syndrome, arrhythmia, dyspnea, pneumonia, pneumonitis, pulmonary embolism, ILD, respiratory failure, and sepsis.
Dose reductions due to adverse reactions were required in 16% of XALKORI-treated patients. The most frequent adverse reactions that led to dose reduction in the patients treated with XALKORI were increased ALT (8%) including some patients with concurrent increased AST, QTc prolongation (2.9%), and neutropenia (2.3%).
XALKORI was discontinued for adverse reactions in 15% of patients. The most frequent adverse reactions that led to discontinuation of XALKORI were ILD (1.7%), increased ALT and AST (1.2%), dyspnea (1.2%), and pulmonary embolism (1.2%).
Tables 11 and 12 summarize common adverse reactions and laboratory abnormalities, respectively, in XALKORI-treated patients.
Table 11. Adverse Reactions Reported at a Higher Incidence (≥5% Higher for All Grades or ≥2% Higher for Grades 3–4) with XALKORI than Chemotherapy in Study 2Adverse reactions were graded using NCI CTCAE version 4.0.
Includes cases reported within the clustered terms:
Adverse Reaction | XALKORI
(N=172) | Chemotherapy
(Pemetrexed or Docetaxel)
(N=171) |
All Grades
(%) | Grade 3–4
(%) | All Grades
(%) | Grade 3–4
(%) |
Nervous System | | | | |
Dysgeusia | 26 | 0 | 9 | 0 |
Dizziness Dizziness (Balance disorder, Dizziness, Postural dizziness). | 22 | 1 | 8 | 0 |
Syncope | 3 | 3 | 0 | 0 |
Eye | | | | |
Vision disorder Vision Disorder (Diplopia, Photophobia, Photopsia, Blurred vision, Reduced visual acuity, Visual impairment, Vitreous floaters). | 60 | 0 | 9 | 0 |
Cardiac | | | | |
Electrocardiogram QT prolonged | 5 | 3 | 0 | 0 |
Bradycardia Bradycardia (Bradycardia, Sinus bradycardia). | 5 | 0 | 0 | 0 |
Investigations | | | | |
Decreased weight | 10 | 1 | 4 | 0 |
Gastrointestinal | | | | |
Diarrhea | 60 | 0 | 19 | 1 |
Nausea | 55 | 1 | 37 | 1 |
Vomiting | 47 | 1 | 18 | 0 |
Constipation | 42 | 2 | 23 | 0 |
Dyspepsia | 8 | 0 | 3 | 0 |
Infections | | | | |
Upper respiratory infection Upper respiratory infection (Laryngitis, Nasopharyngitis, Pharyngitis, Rhinitis, Upper respiratory tract infection). | 26 | 0 | 13 | 1 |
Respiratory, Thoracic and Mediastinal | | | | |
Pulmonary embolism Pulmonary embolism (Pulmonary artery thrombosis, Pulmonary embolism). | 6 | 5 | 2 | 2 |
General | | | | |
Edema Edema (Face edema, Generalized edema, Local swelling, Localized edema, Edema, Peripheral edema, Periorbital edema). | 31 | 0 | 16 | 0 |
Additional adverse reactions occurring at an overall incidence between 1% and 30% in patients treated with XALKORI included decreased appetite (27%), fatigue (27%), neuropathy (19%; dysesthesia, gait disturbance, hypoesthesia, muscular weakness, neuralgia, peripheral neuropathy, paresthesia, peripheral sensory neuropathy, polyneuropathy, burning sensation in skin), rash (9%), ILD (4%; acute respiratory distress syndrome, ILD, pneumonitis), renal cyst (4%), esophagitis (2%), hepatic failure (1%), and decreased blood testosterone (1%; hypogonadism).
Clinically relevant adverse reactions in <1% of patients who received XALKORI included photosensitivity (0.4%).
Table 12. Laboratory Abnormalities with Grades 3–4 Occurring in ≥4% of XALKORI-Treated Patients in Study 2| Additional laboratory test abnormality in patients treated with XALKORI was an increase in creatinine (Any Grade: 96%; Grade 3: 1%; Grade 4: 0%) compared to the chemotherapy arm (Any Grade: 72%; Grade 3: 0%; Grade 4: 0%). |
| XALKORI | Chemotherapy |
Laboratory Abnormality | Any Grade
(%) | Grade 3–4
(%) | Any Grade
(%) | Grade 3–4
(%) |
Hematology | | | | |
Lymphopenia | 51 | 9 | 60 | 25 |
Neutropenia | 49 | 12 | 28 | 12 |
Chemistry | | | | |
Increased ALT | 76 | 17 | 38 | 4 |
Increased AST | 61 | 9 | 33 | 0 |
Hypophosphatemia | 28 | 5 | 25 | 6 |
Hypokalemia | 18 | 4 | 10 | 1 |
ROS1-Positive Metastatic NSCLC - Study 3 (PROFILE 1001)
The safety profile of XALKORI from Study 3, which was evaluated in 50 patients with ROS1-positive metastatic NSCLC, was generally consistent with the safety profile of XALKORI evaluated in patients with ALK-positive metastatic NSCLC (n=1669). Vision disorders occurred in 92% of patients in Study 3; 90% were Grade 1 and 2% were Grade 2. The median duration of exposure to XALKORI was 34.4 months.
Description of Selected Adverse Reactions in Patients with Metastatic NSCLC
Vision disorders: Vision disorders, most commonly visual impairment, photopsia, blurred vision, or vitreous floaters, occurred in 63% of 1719 patients. The majority (95%) of these patients had Grade 1 visual adverse reactions. There were 0.8% of patients with Grade 3 and 0.2% of patients with Grade 4 visual impairment. Based on the Visual Symptom Assessment Questionnaire (VSAQ-ALK), patients treated with XALKORI in Studies 1 and 2 reported a higher incidence of visual disturbances compared to patients treated with chemotherapy. The onset of vision disorder generally was within the first week of drug administration. The majority of patients on the XALKORI arms in Studies 1 and 2 (>50%) reported visual disturbances which occurred at a frequency of 4–7 days each week, lasted up to 1 minute, and had mild or no impact (scores 0 to 3 out of a maximum score of 10) on daily activities as captured in the VSAQ-ALK questionnaire.
Neuropathy: Neuropathy, most commonly sensory in nature, occurred in 25% of 1719 patients. Most events (95%) were Grade 1 or Grade 2 in severity.
Renal cysts: Renal cysts were experienced by 3.0% of 1719 patients. The majority of renal cysts in XALKORI-treated patients were complex. Local cystic invasion beyond the kidney occurred, in some cases with imaging characteristics suggestive of abscess formation. However, across clinical trials no renal abscesses were confirmed by microbiology tests.
Renal toxicity: The estimated glomerular filtration rate (eGFR) decreased from a baseline median of 96.42 mL/min/1.73 m2 (n=1681) to a median of 80.23 mL/min/1.73 m2 at 2 weeks (n=1499) in patients with ALK-positive advanced NSCLC who received XALKORI in clinical trials. No clinically relevant changes occurred in median eGFR from 12 to 104 weeks of treatment. Median eGFR slightly increased (83.02 mL/min/1.73 m2) 4 weeks after the last dose of XALKORI. Overall, 76% of patients had a decrease in eGFR to <90 mL/min/1.73 m2, 38% had a decrease to eGFR to <60 mL/min/1.73 m2, and 3.6% had a decrease to eGFR to <30 mL/min/1.73 m2.
Relapsed or Refractory, Systemic ALK-Positive ALCL - Study ADVL0912
The safety of XALKORI was evaluated in Study ADVL0912 [see Clinical Studies 14.2], which included 26 patients with relapsed or refractory, systemic ALCL after at least one systemic therapy. Eligible patients were 1 to ≤21 years of age and were required to have an absolute neutrophil count ≥1000/mm3 (750/mm3 if bone marrow was involved), platelet count ≥75,000/mm3 (25,000/mm3 if bone marrow was involved), creatinine clearance ≥70ml/min/1.73m2, and QTc ≤480 msec. The study excluded patients with ALT >2.5 times upper limit of normal (ULN), bilirubin ≤1.5 times ULN, and central nervous system tumors.
Patients with ALCL received XALKORI 165 mg/m2 or 280 mg/m2 orally twice daily until disease progression or unacceptable toxicity. The median duration of exposure was 5.4 months (range 1.8, 82.3 months), with 46% of patients treated for at least 6 months and 35% of patients treated for at least 12 months.
Serious adverse reactions occurred in 35% of patients with ALCL treated with XALKORI. The most frequent serious adverse reactions were neutropenia (12%) and hypotension (8%).
Dose interruptions and dose reductions occurred in 77% and 19% of patients with ALCL, respectively. XALKORI was discontinued for an adverse reaction in 8% of patients.
The most common adverse reactions (≥35%), excluding laboratory abnormalities, were diarrhea, vomiting, nausea, vision disorder, headache, musculoskeletal pain, stomatitis, fatigue, decreased appetite, pyrexia, abdominal pain, cough, and pruritis.
The most common Grade 3 or 4 laboratory abnormalities (≥15%) included neutropenia, lymphopenia, and thrombocytopenia. Grade 4 laboratory abnormalities (≥15%) included neutropenia (62%), lymphopenia (35%), and thrombocytopenia (19%).
Selected adverse reactions are summarized in Table 13.
Table 13. Adverse Reactions in ≥20% of Patients with Systemic ALCL in Study ADVL0912| Adverse reactions were graded using NCI CTCAE version 4.0. |
Adverse Reaction | XALKORI
N=26 |
All Grades
(%) | Grade 3–4
(%) |
Blood and Lymphatic System Disorders Derived from laboratory values collected in Cycle 1 and adverse reaction data. | | |
Neutropenia Includes neutrophil count decreased. | 100 | 77 |
Lymphopenia Includes lymphocyte count decreased. | 58 | 38 |
Anemia | 54 | 3.8 |
Thrombocytopenia Includes platelet count decreased. | 38 | 19 |
Gastrointestinal Disorders | | |
Diarrhea | 92 | 12 |
Vomiting | 92 | 3.8 |
Nausea | 77 | 3.8 |
Abdominal Pain | 50 | 0 |
Stomatitis Includes oral pain, oropharyngeal pain, stomatitis. | 46 | 8 |
Constipation | 31 | 0 |
Renal Disorders | | |
Blood creatinine increased | 100 | 0 |
Investigations | | |
ALT increased | 81 | 3.8 |
AST increased | 65 | 3.8 |
Hypocalcemia | 62 | 3.8 |
Hypoalbuminemia | 54 | 0 |
Hyperglycemia | 46 | 0 |
Hypomagnesemia | 46 | 0 |
Hypoglycemia | 35 | 0 |
Hypokalemia | 31 | 3.8 |
Hypermagnesemia | 27 | 0 |
Hyperkalemia | 23 | 0 |
Nervous System Disorders | | |
Headache | 58 | 3.8 |
Dysgeusia | 23 | 0 |
Dizziness | 23 | 0 |
Eye Disorders | | |
Vision disorders Includes blurred vision, visual impairment, photophobia, photopsia, reduced visual acuity, vitreous floaters, cyanopsia, heterophoria, visual field defect. | 65 | 0 |
Musculoskeletal Disorders | | |
Musculoskeletal pain Includes arthralgia, back pain, myalgia, non-cardiac chest pain, pain in extremity. | 58 | 12 |
General Disorders | | |
Fatigue | 46 | 0 |
Pyrexia | 38 | 0 |
Edema Includes peripheral edema, face edema, periorbital edema, localized edema. | 27 | 0 |
Chills | 23 | 0 |
Metabolism and Nutrition Disorders | | |
Decreased appetite | 42 | 0 |
Skin and Subcutaneous Disorders | | |
Pruritus | 35 | 0 |
Rash Includes rash maculopapular, rash pustular. | 23 | 0 |
Infections | | |
Upper respiratory tract infection Includes upper respiratory tract infection, pharyngitis, rhinitis, sinusitis. | 31 | 0 |
Respiratory Disorders | | |
Cough | 35 | 0 |
Rhinitis allergic | 23 | 0 |
Vascular Disorders | | |
Hypertension | 31 | 0 |
Clinically relevant adverse reactions in <20% of patients treated with XALKORI included:
- Cardiac disorders: Bradycardia (19%), electrocardiogram QT prolonged (8%)
- Vascular disorders: Hypotension (19%)
- Investigations: Alkaline phosphatase increase (19%), hypernatremia (19%), GGT increase (8%), hyponatremia (12%), hyperuricemia (12%), hypophosphatemia (12%)
- Nervous system disorders: Peripheral neuropathy (12%)
- Gastrointestinal disorders: Esophagitis (8%)
- Blood and lymphatic disorders: Febrile neutropenia (3.8%)
- Musculoskeletal disorders: Muscular weakness (8%)
- Renal disorders: Acute renal injury (8%)
Unresectable, Recurrent, or Refractory ALK-Positive IMT
Study ADVL0912
The safety of XALKORI was evaluated in Study ADVL0912 [see Clinical Studies (14.3)] that included 14 pediatric patients with unresectable, recurrent, or refractory IMT.
Pediatric patients with IMT received XALKORI 280 mg/m2 orally twice daily until disease progression or unacceptable toxicity. Two patients received a lower dose. The median duration of treatment with XALKORI was 20.5 months.
Serious adverse reactions occurred in 7% of pediatric patients with IMT treated with XALKORI. The most frequent serious adverse reaction was neutropenia and hypotension (7% for each).
Dose interruptions due to an adverse reaction occurred in 71% of patients. Dose reductions due to an adverse reaction occurred in 29% of patients. Permanent discontinuation occurred in 29% of patients.
The most common adverse reactions (≥35%) were vomiting, nausea, diarrhea, abdominal pain, rash, vision disorder, upper respiratory tract infection, cough, pyrexia, musculoskeletal pain, fatigue, edema, constipation, and headache.
The most common Grade 3 or 4 laboratory abnormality (>15%) was neutropenia.
Table 14 and Table 15 summarize the adverse reactions and laboratory abnormalities, respectively, in Study ADVL0912.
Table 14. Adverse Reactions in ≥20% of Pediatric Patients with IMT Treated With XALKORI in Study ADVL0912| Adverse reactions were graded using NCI CTCAE version 4.0. |
Adverse Reaction | XALKORI
N=14 |
| All Grades
(%) | Grade 3–4
(%) |
Gastrointestinal Disorders | | |
Vomiting | 93 | 0 |
Nausea | 86 | 0 |
Diarrhea | 64 | 7 |
Abdominal pain Includes abdominal pain and abdominal pain upper. | 57 | 0 |
Constipation | 36 | 0 |
Stomatitis Includes oral pain and oropharyngeal pain. | 29 | 0 |
Infections | | |
Upper respiratory tract infection Includes upper respiratory tract infection, pharyngitis, rhinitis. | 64 | 0 |
Skin Infection | 29 | 0 |
Respiratory Disorders | | |
Cough Includes cough and productive cough. | 64 | 0 |
Rhinitis allergic | 29 | 0 |
Skin and Subcutaneous Disorders | | |
Rash Includes rash maculopapular, rash pustular, dermatitis acneiform. | 57 | 0 |
General Disorders | | |
Pyrexia | 50 | 0 |
Fatigue | 43 | 0 |
Edema Includes face edema, localized edema, periorbital edema, peripheral edema. | 36 | 7 |
Pain Includes pain, bone pain, ear pain. | 29 | 0 |
Eye Disorders | | |
Vision disorders Includes photophobia, photopsia, vision blurred, visual impairment, vitreous floaters. | 50 | 0 |
Musculoskeletal Disorders | | |
Musculoskeletal pain Includes arthralgia, myalgia, non-cardiac chest pain, pain in extremity. | 43 | 0 |
Nervous System Disorders | | |
Headache | 36 | 0 |
Metabolism and Nutrition Disorders | | |
Decreased appetite | 29 | 0 |
Vascular Disorders | | |
Hypotension | 21 | 7 |
Clinically relevant adverse reactions in <20% of pediatric patients with IMT treated with XALKORI included:
Cardiac disorders: Bradycardia (14%), electrocardiogram QT prolonged (7%)
Gastrointestinal disorders: Dyspepsia (14%), esophagitis (7%)
Vascular disorders: Hypertension (14%)
Nervous system disorders: Peripheral neuropathy (7%)
Blood and lymphatic disorders: Febrile neutropenia (7%)
Musculoskeletal disorders: Muscular weakness (7%)
Table 15. Laboratory Abnormalities (≥15%) That Worsened from Baseline in Pediatric Patients with IMT Treated With XALKORI in Study ADVL0912Laboratory Abnormality | XALKORI The incidence is based on the number of patients who had both a baseline and at least one on-study laboratory measurement and varied from 13 to 14. ,Laboratory abnormality data were only collected for the 1st cycle (28 days) of treatment for the duration of the study. |
Any Grade
(%) | Grade 3–4
(%) |
Chemistry | | |
Increased creatinine | 100 | 0 |
Decreased calcium | 36 | 0 |
Increased magnesium | 23 | 0 |
Decreased phosphate | 15 | 0 |
Hematology | | |
Decreased neutrophils | 64 | 36 |
Hepatic | | |
Increased ALT | 36 | 0 |
Study A8081013
The safety of XALKORI for adult patients with ALK-positive IMT was evaluated in Study A8081013 [see Clinical Studies (14.3)] that included 7 patients with IMT with a median age of 38 years (range 23 to 73). The safety profile of this patient group was generally consistent with the safety profile of XALKORI evaluated in patients with ALK-positive or ROS1-positive NSCLC.
The most frequent adverse reactions (≥20%) were vision disorders, nausea, and edema.
Strong or Moderate CYP3A Inhibitors
Concomitant use of crizotinib with strong CYP3A inhibitors increases crizotinib plasma concentrations [see Clinical Pharmacology (12.3)], which may increase the risk of adverse reactions of XALKORI. Avoid concomitant use of strong CYP3A inhibitors. If concomitant use of strong CYP3A inhibitors is unavoidable, reduce the XALKORI dosage [see Dosage and Administration (2.9)]. Avoid grapefruit or grapefruit juice which may also increase plasma concentrations of crizotinib. Use caution with concomitant use of moderate CYP3A inhibitors.
Strong CYP3A Inducers
Concomitant use of crizotinib with strong CYP3A inducers decreases crizotinib plasma concentrations [see Clinical Pharmacology (12.3)], which may decrease the efficacy of XALKORI. Avoid concomitant use of strong CYP3A inducers.
CYP3A Substrates
Concomitant use of crizotinib increases plasma concentrations of CYP3A substrates [see Clinical Pharmacology (12.3)], which may increase the risk of adverse reactions of these substrates. Avoid concomitant use of XALKORI with CYP3A substrates where minimal concentration changes may lead to serious adverse reactions. If concomitant use of XALKORI is unavoidable, decrease the CYP3A substrate dosage in accordance with approved product labeling.
Risk Summary
Based on findings from animal studies and its mechanism of action, XALKORI can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. There are no available data on the use of XALKORI in pregnant women. In animal reproduction studies, oral administration of crizotinib to pregnant rats during organogenesis at exposures similar to those expected with the maximum recommended human dose resulted in embryotoxicity and fetotoxicity (see Data). Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
Crizotinib was administered to pregnant rats and rabbits during organogenesis to study the effects on embryo-fetal development. Postimplantation loss was increased at doses ≥50 mg/kg/day (approximately 0.6 times the recommended human dose based on AUC) in rats. No teratogenic effects were observed in rats at doses up to the maternally toxic dose of 200 mg/kg/day (approximately 2.7 times the recommended human dose based on AUC) or in rabbits at doses of up to 60 mg/kg/day (approximately 1.6 times the recommended human dose based on AUC), though fetal body weights were reduced at these doses.
Risk Summary
There is no information regarding the presence of crizotinib or its metabolites in human milk, or the effects on the breastfed child or on milk production. Because of the potential for adverse reactions in breastfed children, advise women not to breastfeed during treatment with XALKORI and for 45 days after the last dose.
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to initiating XALKORI [see Use in Specific Population (8.1)].
Contraception
XALKORI can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Females
Advise females of reproductive potential to use effective contraception during treatment with XALKORI and for 45 days after the last dose.
Males
Because of the potential for genotoxicity, advise male patients with female partners of reproductive potential to use condoms during treatment with XALKORI and for 90 days after the last dose [see Nonclinical Toxicology (13.1)].
Infertility
Based on reproductive organ findings in animals, XALKORI may cause reduced fertility in females and males of reproductive potential. It is not known whether these effects on fertility are reversible [see Nonclinical Toxicology (13.1)].
Juvenile Animal Toxicity Data
Decreased bone formation in growing long bones was observed in immature rats at 150 mg/kg/day following once daily dosing for 28 days (approximately 5.4 times the recommended human dose based on AUC). Other toxicities of potential concern to pediatric patients have not been evaluated in juvenile animals.
Cardiac Electrophysiology
In an ECG substudy conducted in 52 patients with ALK-positive NSCLC, the maximum mean QTcF (corrected QT by the Fridericia method) change from baseline was 12.3 ms (2-sided 90% upper CI: 19.5 ms) following administration of XALKORI 250 mg orally twice daily. An exposure-QT analysis suggested a crizotinib plasma concentration-dependent increase in QTcF [see Warnings and Precautions (5.3)].
Absorption
A single crizotinib capsule dose was absorbed with median time to achieve peak concentration (Tmax) of 4 to 6 hours, and the mean absolute bioavailability of 43% (range: 32% to 66%).
The oral pellets had a comparable crizotinib bioavailability compared with the capsules.
Effect of Food
A high-fat meal, reduced AUC0-INF and maximum plasma concentration (Cmax) of crizotinib each by 14% for the capsule formulation; reduced AUC0-INF and Cmax of crizotinib by 15% and 23%, respectively, for the pellet formulation as compared to those under fasted conditions.
Distribution
The geometric mean volume of distribution (Vss) of crizotinib was 1772 L following a single intravenous dose. Protein binding of crizotinib is 91% and is independent of drug concentration in vitro. Crizotinib is a substrate for P-glycoprotein (P-gp) in vitro. The blood-to-plasma concentration ratio is approximately 1.
Elimination
The mean apparent plasma terminal half-life of crizotinib was 42 hours following single doses of crizotinib in patients. The mean apparent clearance (CL/F) of crizotinib was lower at steady-state (60 L/h) after 250 mg twice daily than after a single 250 mg oral dose (100 L/h).
Metabolism
Crizotinib is predominantly metabolized by CYP3A.
Excretion
Following administration of a single oral 250 mg dose of radiolabeled crizotinib dose to healthy subjects, 63% (53% as unchanged) of the administered dose was recovered in feces and 22% (2.3% as unchanged) in urine.
Specific Populations
No clinically significant difference in crizotinib pharmacokinetics were observed based on age, sex, or ethnicity (Asian, non-Asian). For patients <18 years of age, body weight has a significant effect on the pharmacokinetics of crizotinib, with lower crizotinib exposures observed in patients with higher body weight.
Pediatric Patients
In pediatric patients, crizotinib steady-state exposure increased proportionally with dose over the dose range of 165 mg/m2 to 280 mg/m2 orally twice daily. At a dosing regimen of 280 mg/m2 (approximately 2 times the recommended adult dose), geometric mean (CV%) steady-state maximum plasma concentrations (Cmax) of crizotinib was 621 (73%) ng/mL and AUC0–tau was 6530 (34%) ng∙hr/mL.
Patients with Hepatic Impairment
Steady-state mean crizotinib AUC and Cmax decreased by 9% in patients with mild hepatic impairment (AST >ULN and total bilirubin ≤1 times ULN or any AST and total bilirubin >1 times ULN but ≤1.5 times ULN) compared to patients with normal hepatic function following XALKORI 250 mg orally twice daily.
Steady-state mean crizotinib AUC increased by 14% and Cmax increased by 9% in patients with moderate hepatic impairment (any AST and total bilirubin >1.5 times ULN and ≤3 times ULN) following XALKORI 200 mg orally twice daily compared with patients with normal hepatic function following XALKORI 250 mg orally twice daily.
Mean crizotinib AUC decreased by 35% and Cmax decreased by 27% in patients with severe hepatic impairment (any AST and total bilirubin >3 times ULN) following XALKORI 250 mg orally once daily compared with patients with normal hepatic function following XALKORI 250 mg orally twice daily [see Dosage and Administration (2.7), Use in Specific Populations (8.6)].
Patients with Renal Impairment
Mild or moderate renal impairment (CLcr of 60–89 ml/min or 30–59 ml/min, respectively, calculated using the modified Cockcroft-Gault equation) has no clinically significant effect on the exposure of crizotinib. Following a single 250 mg dose, the mean AUC0–INF of crizotinib increased by 79% and the mean Cmax increased by 34% in patients with severe renal impairment (CLcr <30 mL/min) who did not require dialysis compared to those with normal renal function (CLcr ≥90 mL/min). Similar changes in AUC0–INF and Cmax were observed for the active metabolite of crizotinib [see Dosage and Administration (2.8), Use in Specific Populations (8.7)].
Drug Interaction Studies
Clinical Studies
Gastric Acid Reducing Agents: No clinically significant differences in crizotinib pharmacokinetics were observed when used concomitantly with esomeprazole, a proton pump inhibitor.
Strong CYP3A Inhibitors: Coadministration of a single 150 mg oral dose of crizotinib with ketoconazole, a strong CYP3A inhibitor, increased crizotinib AUC0–INF by 216% and Cmax by 44% compared to crizotinib alone. Coadministration of XALKORI 250 mg orally once daily with itraconazole, a strong CYP3A inhibitor, increased crizotinib steady-state AUC by 57% and Cmax by 33% compared to crizotinib alone [see Drug Interactions (7.1)].
Strong CYP3A Inducers: Coadministration of XALKORI 250 mg orally twice daily with rifampin, a strong CYP3A inducer, decreased crizotinib steady-state AUC0–Tau by 84% and Cmax by 79%, compared to crizotinib alone [see Drug Interactions (7.1)].
CYP3A Substrates: Coadministration of XALKORI 250 mg orally twice daily for 28 days increased AUC0–INF of oral midazolam (CYP3A substrate) 3.7-fold compared to midazolam alone [see Drug Interactions (7.2)].
In Vitro Studies
CYP Enzymes: Crizotinib inhibits CYP2B6 in vitro. Crizotinib does not inhibit CYP1A2, CYP2C8, CYP2C9, CYP2C19, or CYP2D6. Crizotinib does not induce CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, or CYP3A.
UDP-glucuronosyltransferase (UGT): Crizotinib does not inhibit UGT1A1, UGT1A4, UGT1A6, UGT1A9 or UGT2B7.
Transporters: Crizotinib inhibits P-gp, organic cation transporter (OCT) 1, and OCT2. Crizotinib does not inhibit organic anion transporting polypeptides (OATP) B1, OATP1B3, organic anion transporter (OAT) 1, OAT3, or bile salt export pump transporter (BSEP).
Previously Untreated ALK-Positive Metastatic NSCLC - Study 1 (PROFILE 1014; NCT01154140)
The efficacy of XALKORI for the treatment of patients with ALK-positive metastatic NSCLC, who had not received previous systemic treatment for advanced disease, was demonstrated in a randomized, multicenter, open-label, active-controlled study (Study 1). Patients were required to have ALK-positive NSCLC as identified by the FDA-approved assay, Vysis ALK Break-Apart fluorescence in situ hybridization (FISH) Probe Kit, prior to randomization. The major efficacy outcome measure was progression-free survival (PFS) according to Response Evaluation Criteria in Solid Tumors (RECIST) version 1.1 as assessed by independent radiology review (IRR) committee. Additional efficacy outcome measures included objective response rate (ORR) as assessed by IRR, DOR, and overall survival (OS). Patient-reported lung cancer symptoms were assessed at baseline and periodically during treatment.
Patients were randomized to receive XALKORI (n=172) or chemotherapy (n=171). Randomization was stratified by Eastern Cooperative Oncology Group (ECOG) performance status (0–1, 2), race (Asian, non-Asian), and brain metastases (present, absent). Patients in the XALKORI arm received XALKORI 250 mg orally twice daily until documented disease progression, intolerance to therapy, or the investigator determined that the patient was no longer experiencing clinical benefit. Chemotherapy consisted of pemetrexed 500 mg/m2 with cisplatin 75 mg/m2 or carboplatin AUC of 5 or 6 mg×min/mL by intravenous infusion every 3 weeks for up to 6 cycles. Patients in the chemotherapy arm were not permitted to receive maintenance chemotherapy. At the time of documented disease progression, as per independent radiology review, patients randomized to chemotherapy were offered XALKORI.
The demographic characteristics of the overall study population were 62% female, median age of 53 years, baseline ECOG performance status 0 or 1 (95%), 51% White and 46% Asian, 4% current smokers, 32% past smokers, and 64% never smokers. The disease characteristics of the overall study population were metastatic disease in 98% of patients, 92% of patients' tumors were classified as adenocarcinoma histology, 27% of patients had brain metastases, and 7% received systemic chemotherapy as adjuvant or neoadjuvant therapy. At the time of the final analysis of overall survival, 84% of patients randomized to the chemotherapy arm subsequently received XALKORI.
Study 1 demonstrated a statistically significant improvement in PFS in patients treated with XALKORI. There was no statistically significant difference in OS between patients treated with XALKORI and patients treated with chemotherapy. Table 16 and Figure 1 summarize the efficacy results. Exploratory patient-reported symptom measures of baseline and post-treatment dyspnea, cough, and chest pain suggested a delay in time to development of or worsening of dyspnea, but not cough or chest pain, in patients treated with XALKORI as compared to chemotherapy. The patient-reported delay in onset or worsening of dyspnea may be an overestimation because patients were not blinded to treatment assignment.
Table 16. Previously Untreated ALK-Positive Metastatic NSCLC - Efficacy Results in Study 1 | XALKORI
(N=172) | Chemotherapy
(N=171) |
|---|
| HR=hazard ratio; CI=confidence interval; IRR=independent radiology review; NR=not reached; CR=complete response; PR=partial response. |
Progression-Free Survival (Based on IRR) |
Number of Events (%) | 100 (58%) | 137 (80%) |
Progressive Disease | 89 (52%) | 132 (77%) |
Death | 11 (6%) | 5 (3%) |
Median, Months (95% CI) | 10.9 (8.3, 13.9) | 7.0 (6.8, 8.2) |
HR (95% CI) Based on the Cox proportional hazards stratified analysis. | 0.45 (0.35, 0.60) |
p-value Based on the stratified log-rank test. | <0.001 |
Overall Survival |
Number of Events (%) | 71 (41%) | 81 (47%) |
Median, Months (95% CI) | NR (45.8, NR) | 47.5 (32.2, NR) |
HR (95% CI) | 0.76 (0.55, 1.05) |
p-value | 0.098 |
Tumor Responses (Based on IRR) |
Objective Response Rate % (95% CI) | 74% (67, 81) | 45% (37, 53) |
CR, n (%) | 3 (1.7%) | 2 (1.2%) |
PR, n (%) | 125 (73%) | 75 (44%) |
p-value Based on the stratified Cochran-Mantel-Haenszel test. | <0.001 |
Duration of Response |
Median, Months (95% CI) | 11.3 (8.1, 13.8) | 5.3 (4.1, 5.8) |
Figure 1. Kaplan-Meier Curves of Progression-Free Survival as Assessed by IRR in Study 1 |
|
Previously Treated ALK-Positive Metastatic NSCLC - Study 2 (PROFILE 1007; NCT00932893)
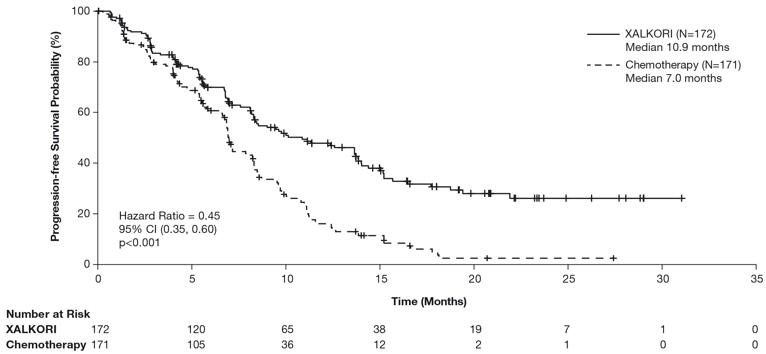
The efficacy of XALKORI as monotherapy for the treatment of 347 patients with ALK-positive metastatic NSCLC, previously treated with 1 platinum-based chemotherapy regimen, were demonstrated in a randomized, multicenter, open-label, active-controlled study (Study 2). The major efficacy outcome was PFS according to RECIST version 1.1 as assessed by IRR. Additional efficacy outcomes included ORR as assessed by IRR, DOR, and OS.
Patients were randomized to receive XALKORI 250 mg orally twice daily (n=173) or chemotherapy (n=174). Chemotherapy consisted of pemetrexed 500 mg/m2 (if pemetrexed-naïve; n=99) or docetaxel 75 mg/m2 (n=72) intravenously (IV) every 21 days. Patients in both treatment arms continued treatment until documented disease progression, intolerance to therapy, or the investigator determined that the patient was no longer experiencing clinical benefit. Randomization was stratified by ECOG performance status (0–1, 2), brain metastases (present, absent), and prior EGFR tyrosine kinase inhibitor treatment (yes, no). Patients were required to have ALK-positive NSCLC as identified by the FDA-approved assay, Vysis ALK Break-Apart FISH Probe Kit, prior to randomization.
The demographic characteristics of the overall study population were 56% female, median age of 50 years, baseline ECOG performance status 0 or 1 (90%), 52% White and 45% Asian, 4% current smokers, 33% past smokers, and 63% never smokers. The disease characteristics of the overall study population were metastatic disease in at least 95% of patients and at least 93% of patients' tumors were classified as adenocarcinoma histology. At the time of the final analysis of overall survival, 89% of patients randomized to the chemotherapy arm subsequently received XALKORI.
Study 2 demonstrated a statistically significant improvement in PFS in the patients treated with XALKORI. Table 17 and Figure 2 summarize the efficacy results.
Table 17. Previously Treated ALK-Positive Metastatic NSCLC - Efficacy Results in Study 2 | XALKORI
(N=173) | Chemotherapy
(N=174) |
|---|
| HR=hazard ratio; CI=confidence interval; IRR=independent radiology review; CR=complete response; PR=partial response. |
Progression-Free Survival (Based on IRR) |
Number of Events (%) | 100 (58%) | 127 (73%) |
Progressive Disease | 84 (49%) | 119 (68%) |
Death | 16 (9%) | 8 (5%) |
Median, Months (95% CI) | 7.7 (6.0, 8.8) | 3.0 For pemetrexed, the median PFS was 4.2 months. For docetaxel, the median PFS was 2.6 months. (2.6, 4.3) |
HR (95% CI) Based on the Cox proportional hazards stratified analysis. | 0.49 (0.37, 0.64) |
p-value Based on the stratified log-rank test. | <0.001 |
Overall Survival |
Number of Events (%) | 116 (67%) | 126 (72%) |
Median, Months (95% CI) | 21.7 (18.9,30.5) | 21.9 (16.8,26.0) |
HR (95% CI) | 0.85 (0.66, 1.10) |
p-value | 0.229 |
Tumor Responses (Based on IRR) |
Objective Response Rate % (95% CI) | 65% (58, 72) | 20% (14, 26) |
CR, n (%) | 1 (0.6%) | 0 |
PR, n (%) | 112 (65%) | 34 (20%) |
p-value Based on the stratified Cochran-Mantel-Haenszel test. | <0.001 |
Duration of Response |
Median, Months (95% CI) | 7.4 (6.1, 9.7) | 5.6 (3.4, 8.3) |
Figure 2. Kaplan-Meier Curves of Progression-Free Survival as Assessed by IRR in Study 2 |
|
ROS1-Positive Metastatic NSCLC - Study 3 (PROFILE 1001; NCT00585195)
The efficacy and safety of XALKORI was investigated in a multicenter, single-arm study (Study 3), in which patients with ROS1-positive metastatic NSCLC received XALKORI 250 mg orally twice daily. Patients were required to have histologically-confirmed advanced NSCLC with a ROS1 rearrangement, age 18 years or older, ECOG performance status of 0, 1, or 2, and measurable disease. The efficacy outcome measures were ORR and DOR according to RECIST version 1.0 as assessed by IRR and investigator, with imaging performed every 8 weeks for the first 60 weeks.
Baseline demographic and disease characteristics were female (56%), median age of 53 years, baseline ECOG performance status of 0 or 1 (98%), White (54%), Asian (42%), past smokers (22%), never smokers (78%), metastatic disease (92%), adenocarcinoma (96%), no prior systemic therapy for metastatic disease (14%), and prior platinum-based chemotherapy for metastatic disease (80%). The ROS1 status of NSCLC tissue samples was determined by laboratory-developed break-apart FISH (96%) or RT-PCR (4%) clinical trial assays. For assessment by FISH, ROS1 positivity required that ≥15% of a minimum of 50 evaluated nuclei contained a ROS1 gene rearrangement.
Efficacy results are summarized in Table 18.
Table 18. ROS1-Positive Metastatic NSCLC - ResultsAs assessed by RECIST version 1.0.
in Study 3| Efficacy Parameters | IRR
(N=50) | Investigator-Assessed
(N=50) |
|---|
| IRR=independent radiology review; CI=confidence interval; NR=not reached. |
Objective Response Rate (95% CI) | 66% (51, 79) | 72% (58, 84) |
Complete Response, n | 1 | 5 |
Partial Response, n | 32 | 31 |
Duration of Response | | |
Median, Months (95% CI) | 18.3 (12.7, NR) | NR (14.5, NR) |
Pediatric Patients with ALK-positive IMT
Study ADVL0912
The efficacy of XALKORI was evaluated in Study ADVL0912 (NCT00939770), a multicenter, single-arm, open-label study in patients 1 to ≤21 years of age that included 14 pediatric patients with unresectable, recurrent, or refractory ALK-positive IMT. Patients were required to have an ALK fusion determined locally by immunohistochemistry or fluorescence in situ hybridization. Patients (n=12) received XALKORI 280 mg/m2 twice daily until disease progression or unacceptable toxicity. Two patients received a lower dose.
The demographic characteristics were median age 6.5 years (range: 2 to 13); 64% female; 71% White; 7% Black, 21% unknown; 21% Hispanic; and 71% had a Lansky/Karnofsky Score of 100. Patient enrollment by age was 4 patients from 2 to <6 years, 8 patients from 6 to <12 years, and 2 patients from 12 to <18 years.
A total of 12 (86%) patients received prior therapy. The most common prior therapy was surgery (57%).
The major efficacy outcome was objective response rate according to RECIST version 1.0 as assessed by an independent review committee (Table 20).
Table 20. Efficacy in Pediatric Patients with Unresectable, Recurrent, or Relapsed ALK-Positive IMT | Efficacy Parameter | N=14 |
|---|
| CI=confidence interval; N/n=number of patients. |
Objective response rate (95% CI, %) 95% CI based on Clopper–Pearson exact method. | 86% (57, 98) |
Complete response, n (%) | 5 (36) |
Partial response n (%) | 7 (50) |
Duration of response Estimated using descriptive statistics. | N=12 |
≥6 months, n (%) | 7 (58) |
≥12 months, n (%) | 7 (58) |
Adult Patients with ALK-positive IMT
Study A8081013
The efficacy of XALKORI was evaluated in Study A8081013 (NCT01121588), a multicenter, single-arm, open-label study that included 7 adult patients with unresectable, recurrent, or refractory ALK-positive IMT. ALK fusion was determined locally by immunohistochemistry or fluorescence in situ hybridization. Patients received XALKORI 250 mg twice daily.
The demographic characteristics were median age 38 years (range: 23 to 73); 57% male; 57% White, 43% Asian; and 86% ECOG performance status of 0 or 1. Two (29%) patients had at least one prior systemic treatment.
The major efficacy outcome was objective response rate according to RECIST version 1.1 per investigator assessment. For the 7 patients with ALK-positive IMT, 5 experienced a response including 1 complete response. The DOR was ≥6 months for all 5 patients and ≥12 months for 2 patients.
Hepatotoxicity
Inform patients to immediately report symptoms of hepatotoxicity [see Warnings and Precautions (5.1)].
Interstitial Lung Disease (Pneumonitis)
Advise patients to immediately report any new or worsening pulmonary symptoms [see Warnings and Precautions (5.2)].
Bradycardia
Advise patients to report any symptoms of bradycardia and to inform their healthcare provider about the use of any heart or blood pressure medications [see Warnings and Precautions (5.4)].
Severe Visual Loss
Inform patients of the potential risk of severe visual loss and to immediately contact their healthcare provider if they develop severe visual loss. Inform patients that visual changes such as perceived flashes of light, blurry vision, light sensitivity, and floaters are commonly reported adverse reactions and may occur while driving or operating machinery. The onset of visual disorders most commonly occurs during the first week of treatment [see Warnings and Precautions (5.5), Adverse Reactions (6)].
Gastrointestinal Toxicity in Pediatric and Young Adult Patients with ALCL or Pediatric Patients with IMT
Inform patients with ALCL or pediatric patients with IMT of the risk of severe nausea, vomiting, diarrhea, and stomatitis. Advise patients to immediately inform their healthcare provider of problems with swallowing, vomiting, or diarrhea [see Warnings and Precautions (5.6)].
Drug Interactions
Inform patients to avoid grapefruit or grapefruit juice while taking XALKORI. Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products [see Drug Interactions (7)].
Photosensitivity
Inform patients of the signs and symptoms of photosensitivity. Advise patients to avoid prolonged sun exposure and to use sunscreen or protective clothing during treatment with XALKORI [see Adverse Reactions (6.1)].
Dosage and Administration
Advise patients to take XALKORI with or without food. If a patient misses a dose, advise the patient to take it as soon as remembered unless it is less than 6 hours until the next dose, in which case, advise the patient not to take the missed dose. If a patient vomits after taking a dose of XALKORI, advise the patient not to take an extra dose, but to take the next dose at the regular time [see Dosage and Administration (2.4)].
Capsules:
Advise patients to swallow XALKORI capsules whole [see Dosage and Administration (2.4)].
Oral Pellets:
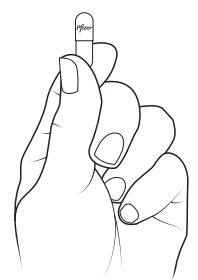
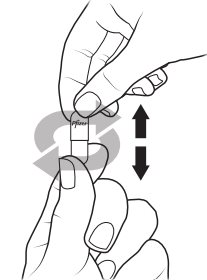
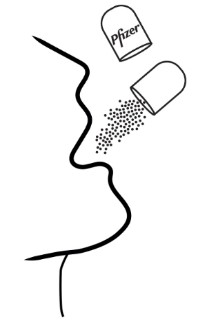
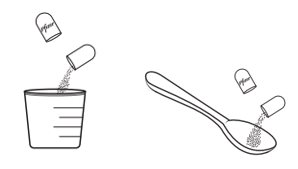
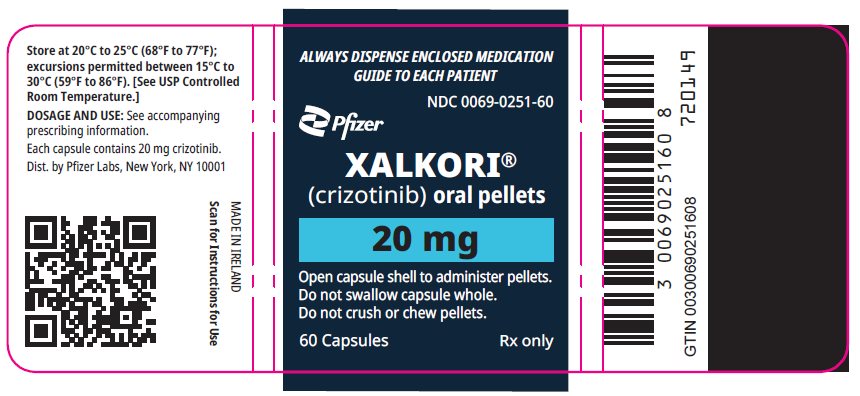
Inform patient or caregiver to open the encapsulated XALKORI oral pellets and administer the oral pellets directly in the patient’s mouth or with a consumer-supplied oral dosing aid, for example a spoon or medicine cup. Advise patient or caregiver that the oral pellets are not to be chewed and to give a sufficient amount of water after pellets are administered to ensure all oral pellets are swallowed [see Dosage and Administration (2.4)].
Embryo-Fetal Toxicity
Advise females of reproductive potential of the potential risk to a fetus and to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.7), Use in Specific Populations (8.1)].
Females and Males of Reproductive Potential
Advise females of reproductive potential to use effective contraception during treatment with XALKORI and for 45 days after the last dose [see Use in Specific Populations (8.3)].
Advise male patients with female partners of reproductive potential to use condoms during treatment with XALKORI and for 90 days after the last dose [see Use in Specific Populations (8.3), Nonclinical Toxicology (13.1)].
Lactation
Advise females not to breastfeed during treatment with XALKORI and for 45 days after the last dose [see Use in Specific Populations (8.2)].
Infertility
Advise females and males of reproductive potential of the potential for reduced fertility from XALKORI [see Use in Specific Populations (8.3), Nonclinical Toxicology (13.1)].
This product's labeling may have been updated. For the most recent prescribing information, please visit www.Pfizer.com. For medical information about XALKORI, please visit www.pfizermedinfo.com or call 1-800-438-1985.
LAB-0440-28.0