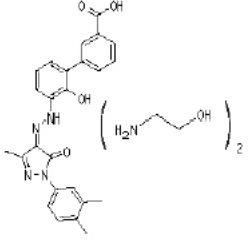
Eltrombopag demonstrated a dose-proportional increase in exposure between doses of 50 to 150 mg/day in healthy adult subjects. Eltrombopag AUC was approximately 2.8-fold higher in patients with HCV compared to healthy subjects. Steady-state was achieved after approximately 1 week of once daily treatment, with geometric mean accumulation ratio of 1.56 (90% confidence interval 1.20, 1.63) at 75 mg/day. Eltrombopag AUC was approximately 3.2-fold higher in patients with definitive immunosuppressive therapy-naïve severe aplastic anemia compared to healthy subjects suggesting higher relative exposure compared to healthy subjects and similar exposure compared to patients with chronic hepatitis C. Eltrombopag for oral suspension delivered 22% higher plasma AUC0-INF than the tablet formulation.
Absorption
Eltrombopag is absorbed with a peak concentration occurring 2 to 6 hours after oral administration.
Oral absorption of drug-related material following administration of a single 75 mg solution dose was estimated to be at least 52%.
Effect of Food
A standard high-fat breakfast (876 calories, 52 g fat, 71 g carbohydrate, 34 g protein, and 427 mg calcium) significantly decreased plasma eltrombopag AUC0-INF by approximately 59% and Cmax by 65% and delayed Tmax by 1 hour. The decrease in exposure is primarily due to the high calcium content.
A meal low in calcium (≤ 50 mg calcium) did not significantly impact plasma eltrombopag exposure, regardless of calorie and fat content.
The effect of administration of a single 25 mg dose of eltrombopag for oral suspension with a high-calcium, moderate-fat, moderate calorie meal on AUC0-INF and Cmax in healthy adult subjects is presented in Table 14.
| Table 14. Effect on Plasma Eltrombopag Pharmacokinetic Parameters After Administration of a Single 25 mg Dose of Eltrombopag for Oral Suspension with a High Calcium Meala in Healthy Adult Subjects |
Timing of eltrombopag for oral suspension dose | Mean (90% CI) reduction in plasma eltrombopag AUC0-INF | Mean (90% CI) reduction in plasma eltrombopag Cmax |
With a high-calcium, moderate-fat, moderate-calorie meal | 75% (71%, 88%) | 79% (76%, 82%) |
2 hours after the high-calcium, moderate-fat, moderate-calorie meal | 47% (40%, 53%) | 48% (40%, 54%) |
2 hours before the high-calcium, moderate-fat, moderate-calorie meal | 20% (9%, 29%) | 14% (2%, 25%) |
| a372 calories, 9 g fat, and 448 mg calcium. |
Distribution
The concentration of eltrombopag in blood cells is approximately 50% to 79% of plasma concentrations based on a radiolabel study. In vitro studies suggest that eltrombopag is highly bound to human plasma proteins (greater than 99%). Eltrombopag is a substrate of BCRP, but is not a substrate for P-glycoprotein (P-gp) or OATP1B1.
Elimination
The plasma elimination half-life of eltrombopag is approximately 21 to 32 hours in healthy subjects.
Metabolism: Absorbed eltrombopag is extensively metabolized, predominantly through pathways, including cleavage, oxidation, and conjugation with glucuronic acid, glutathione, or cysteine. In vitro studies suggest that CYP1A2 and CYP2C8 are responsible for the oxidative metabolism of eltrombopag. UGT1A1 and UGT1A3 are responsible for the glucuronidation of eltrombopag.
Excretion: The predominant route of eltrombopag excretion is via feces (59%), and 31% of the dose is found in the urine. Unchanged eltrombopag in feces accounts for approximately 20% of the dose; unchanged eltrombopag is not detectable in urine.
Specific Populations
Ethnicity
Eltrombopag concentrations in East-/Southeast-Asian ancestry patients with chronic hepatitis C were 50% to 55% higher compared with non-Asian subjects [see Dosage and Administration (2.3)].
Eltrombopag exposure in healthy African-American subjects was approximately 40% higher than that observed in Caucasian subjects in one clinical pharmacology trial and similar in three other clinical pharmacology trials. The effect of African-American ethnicity on exposure and related safety and efficacy of eltrombopag has not been established.
Hepatic Impairment
Following a single dose of eltrombopag (50 mg), plasma eltrombopag AUC0-INF was 41% higher in patients with mild hepatic impairment (Child-Pugh class A) compared with subjects with normal hepatic function. Plasma eltrombopag AUC0-INF was approximately 2-fold higher in patients with moderate (Child-Pugh class B) and severe hepatic impairment (Child-Pugh class C) compared with subjects with normal hepatic function. The half-life of eltrombopag was prolonged 2-fold in these patients. This clinical trial did not evaluate protein- binding effects.
Chronic Liver Disease
Following repeat doses of eltrombopag in patients with thrombocytopenia and with chronic liver disease, mild hepatic impairment resulted in an 87% to 110% higher plasma eltrombopag AUC(0-τ) and moderate hepatic impairment resulted in approximately 141% to 240% higher plasma eltrombopag AUC(0-τ) values compared with patients with normal hepatic function. The half-life of eltrombopag was prolonged 3-fold in patients with mild hepatic impairment and 4-fold in patients with moderate hepatic impairment. This clinical trial did not evaluate protein-binding effects.
Chronic Hepatitis C
Patients with chronic hepatitis C treated with eltrombopag had higher plasma AUC(0-τ) values as compared with healthy subjects, and AUC(0-τ) increased with increasing Child-Pugh score. Patients with chronic hepatitis C and mild hepatic impairment had approximately 100% to 144% higher plasma AUC(0-τ) compared with healthy subjects. This clinical trial did not evaluate protein-binding effects.
Renal Impairment
Following a single dose of eltrombopag (50 mg), the average total plasma eltrombopag AUC0-INF was 32% to 36% lower in subjects with mild (estimated creatinine clearance (CLCr) by Cockcroft-Gault equation: 50 to 80 mL/min), to moderate (CLCr of 30 to 49 mL/min) renal impairment and 60% lower in subjects with severe (CLCr less than 30 mL/min) renal impairment compared with healthy subjects. The effect of renal impairment on unbound (active) eltrombopag exposure has not been assessed.
Drug Interaction Studies
Clinical Studies
Effect of Drugs on Eltrombopag
Effect of Polyvalent Cation-containing Antacids on Eltrombopag:
The coadministration of a single dose of eltrombopag (75 mg) with a polyvalent cation-containing antacid (1,524 mg aluminum hydroxide, 1,425 mg magnesium carbonate, and sodium alginate) decreased plasma eltrombopag AUC0-INF and Cmax by approximately 70%. The contribution of sodium alginate to this interaction is not known.
Effect of HIV Protease Inhibitors on Eltrombopag:
The coadministration of repeat-dose lopinavir 400 mg/ritonavir 100 mg (twice daily) with a single dose of eltrombopag (100 mg) decreased plasma eltrombopag AUC0-INF by 17%.
Effect of HCV Protease Inhibitors on Eltrombopag:
The coadministration of repeat-dose telaprevir (750 mg every 8 hours) or boceprevir (800 mg every 8 hours) with a single dose of eltrombopag (200 mg) to healthy adult subjects in a clinical trial did not alter plasma eltrombopag AUC0-INF or Cmax to a significant extent.
Effect of Cyclosporine on Eltrombopag:
The coadministration of a single dose of eltrombopag (50 mg) with a single dose of an OATP and BCRP inhibitor cyclosporine (200 mg or 600 mg) decreased plasma eltrombopag AUC0-INF by 18% to 24% and Cmax by 25% to 39%.
Effect of Pegylated Interferon alfa-2a + Ribavirin and Pegylated Interferon alfa-2b + Ribavirin on Eltrombopag:
The presence of pegylated interferon alfa + ribavirin therapy did not significantly affect the clearance of eltrombopag.
Effect of Eltrombopag on Other Drugs
Effect of Eltrombopag on Cytochrome P450 Enzymes Substrates:
The coadministration of multiple doses of eltrombopag (75 mg once daily for 7 days) did not result in the inhibition or induction of the metabolism of a combination of probe substrates for CYP1A2 (caffeine), CYP2C19 (omeprazole), CYP2C9 (flurbiprofen), or CYP3A4 (midazolam) in humans.
Effect of Eltrombopag on Rosuvastatin:
The coadministration of multiple doses of eltrombopag (75 mg once daily for 5 days) with a single dose of rosuvastatin (OATP1B1 and BCRP substrate; 10 mg) increased plasma rosuvastatin AUC0-INF by 55% and Cmax by 103%.
Effect of Eltrombopag on HCV Protease Inhibitors:
The coadministration of repeat-dose telaprevir (750 mg every 8 hours) or boceprevir (800 mg every 8 hours) with a single dose of eltrombopag (200 mg) to healthy adult subjects in a clinical trial did not alter plasma telaprevir or boceprevir AUC0-INF or Cmax to a significant extent.
In vitro Studies
Eltrombopag Effect on Metabolic Enzymes
Eltrombopag has demonstrated the potential to inhibit CYP2C8, CYP2C9, UGT1A1, UGT1A3, UGT1A4, UGT1A6, UGT1A9, UGT2B7, and UGT2B15.
Eltrombopag Effect on Transporters
Eltrombopag has demonstrated the potential to inhibit OATP1B1 and BCRP.