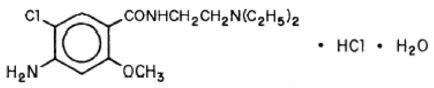Metoclopramide is rapidly and well absorbed. Relative to an intravenous dose of 20 mg, the absolute oral bioavailability of metoclopramide is 80% ± 15.5% as demonstrated in a crossover study of 18 subjects. Peak plasma concentrations occur at about 1 to 2 hr after a single oral dose. Similar time to peak is observed after individual doses at steady state.
In a single dose study of 12 subjects, the area under the drug concentration-time curve increases linearly with doses from 20 to 100 mg. Peak concentrations increase linearly with dose; time to peak concentrations remains the same; whole body clearance is unchanged; and the elimination rate remains the same. The average elimination half-life in individuals with normal renal function is 5 to 6 hr. Linear kinetic processes adequately describe the absorption and elimination of metoclopramide.
Approximately 85% of the radioactivity of an orally administered dose appears in the urine within 72 hr. Of the 85% eliminated in the urine, about half is present as free or conjugated metoclopramide.
The drug is not extensively bound to plasma proteins (about 30%). The whole body volume of distribution is high (about 3.5 L/kg) which suggests extensive distribution of drug to the tissues (see Table 1).
Table 1. Adult Pharmacokinetic Data| Parameter | Value |
Vd (L/kg) | ~ 3.5 |
Plasma Protein Binding | ~ 30% |
t1/2 (hr) | 5 to 6 |
Oral Bioavailability | 80%±15.5% |
Patients with Renal Impairment
In a study of 24 patients with varying degrees of renal impairment (moderate, severe, and end-stage renal disease (ESRD) requiring dialysis), the systemic exposure (AUC) of metoclopramide following intravenous administration in patients with moderate to severe renal impairment was about 2-fold the AUC in subjects with normal renal function. The AUC of metoclopramide in patients with ESRD in dialysis was about 3.5-fold the AUC in subjects with normal renal function.
Patients with Hepatic Impairment
In a group of 8 patients with severe hepatic impairment (Child-Pugh C) administered intravenous metoclopramide, the average metoclopramide clearance was reduced by approximately 50% compared to patients with normal hepatic function.
Effect of CYP2D6 Inhibitors on Metoclopramide
In healthy subjects, 20 mg of oral metoclopramide and 60 mg of fluoxetine (a strong CYP2D6 inhibitor) were administered, following prior exposure to 60 mg fluoxetine orally for 8 days. The patients who received concomitant metoclopramide and fluoxetine had a 40% and 90% increase in metoclopramide Cmax and AUC0-∞, respectively, compared to patients who received metoclopramide alone (see Table 2).
Table 2. Oral Metoclopramide Pharmacokinetic Parameters in Healthy Subjects with and without FluoxetineParameter | Metoclopramide alone (mean ±SD) | Metoclopramide with fluoxetine (mean ±SD) |
Cmax (ng/mL) | 44±15 | 62.7±9.2 |
AUC0-∞ (ng∙h/mL) | 313±113 | 591±140 |
T1/2(h) | 5.5±1.1 | 8.5±2.2 |
Pediatric Patients
In pediatric patients, the pharmacodynamics of metoclopramide following oral and intravenous administration are highly variable and a concentration-effect relationship has not been established.
There are insufficient reliable data to conclude whether the pharmacokinetics of metoclopramide in adults and the pediatric population are similar.