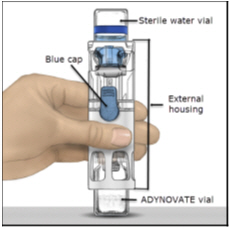
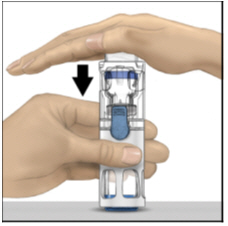
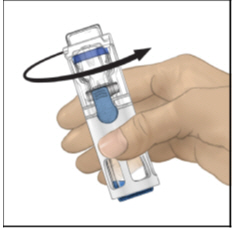
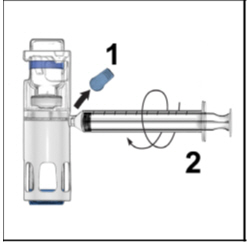
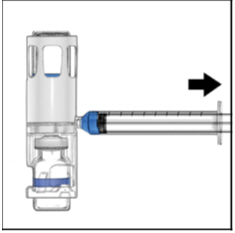
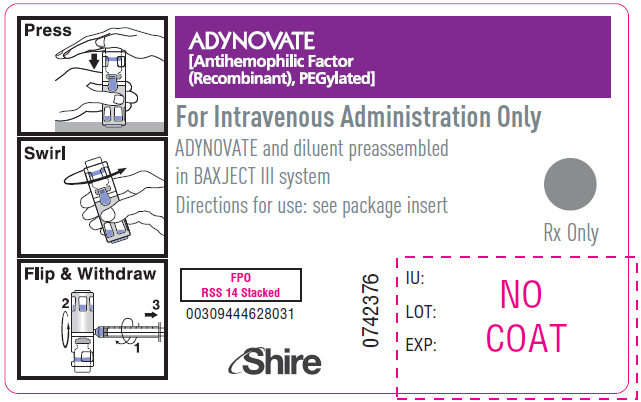
- Remove the blue cap from the housing. Connect the syringe to the system (Figure D). Do not inject air into the ADYNOVATE.
- Turn the system upside down (ADYNOVATE vial now on top). Draw the ADYNOVATE solution into the syringe by pulling the plunger back slowly (Figure E).
- Disconnect the syringe, attach a suitable needle, and inject intravenously as instructed. If a patient is to receive more than one ADYNOVATE -BAXJECT® III system or a combination of an ADYNOVATE -BAXJECT II and an ADYNOVATE -BAXJECT III system, the contents may be drawn into the same syringe.
- Administer ADYNOVATE intravenously over a period of less than or equal to 5 minutes (maximum infusion rate 10 mL per min).
Risk Summary
There are no data with ADYNOVATE use in pregnant women to inform a drug-associated risk. Animal reproduction studies have not been conducted with ADYNOVATE. It is unknown whether ADYNOVATE can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity.
In the U.S. general population, the estimated background risk of major birth defect and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Risk Summary
There is no information regarding the presence of ADYNOVATE in human milk, the effect on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for ADYNOVATE and any potential adverse effects on the breastfed infant from ADYNOVATE or from the underlying maternal condition.
Pediatric Pharmacokinetics
Pharmacokinetic parameters calculated from 39 patients <18 years of age (intent-to-treat analysis) are available for 14 children (2 to <6 years), 17 older children (6 to <12 years) from Study 2 [see Clinical Studies (14)] and 8 adolescent patients (12 to <18 years of age) from Study 1 [see Clinical Studies (14)], as shown in Table 4. The mean clearance (based on body weight) of ADYNOVATE was higher and the mean half-life was lower in children <12 years of age than adults. A dose adjustment may be required in children <12 years of age.
Table 4: Pharmacokinetic Parameters (Arithmetic Mean ± SD)| PK Parameters | Pediatric
Population PK with Sparse SamplingPopulation PK model with 3 post-infusion samples based on randomized drawing schedule. | Adult and Adolescent
Individual PK with Full SamplingIndividual PK with 12 post-infusion samples. |
|---|
<6 years
N=14 | 6 to <12 years
N=17 | 12 to <18 years
N = 8 | ≥18 years
N = 18 |
|---|
| Abbreviations: MRT: mean residence time; CL: clearance; CI: confidence interval; AUC: area under the curve; Vss: body weight adjusted volume of distribution at steady-state; Cmax: maximum observed activity; Tmax: time to reach the maximum concentration. |
| Terminal half-life [h] | 11.8 ± 2.43 | 12.4 ± 1.67 | 13.43 ± 4.05 | 14.69 ± 3.79 |
| MRT [h] | 17.0 ± 3.50 | 17.8 ± 2.42 | 17.96 ± 5.49 | 20.27 ± 5.23 |
| CL [mL/(kg∙h)] | 3.53 ± 1.29 | 3.11 ± 0.76 | 3.87 ± 3.31
(2.73 ± 0.93)Estimated mean and SD calculated not including one patient whose clearance estimate was 11.8 mL/(kg.h). Median including all patients is 2.78 mL/(kg.h). | 2.27 ± 0.84 |
| Incremental Recovery [(IU/dL)/(IU/kg)] | 1.89 ± 0.49 | 1.95 ± 0.47 | 2.12 ± 0.60 | 2.66 ± 0.68 |
| AUC0-Inf [IU∙h/dL] | 1947 ± 757 | 2012 ± 495 | 1642 ± 752 | 2264 ± 729 |
| Vss [dL/kg] | 0.56 ± 0.12 | 0.54 ± 0.09 | 0.56 ± 0.18 | 0.43 ± 0.11 |
| Cmax [IU/dL] | 115 ± 30 | 115 ± 33 | 95 ± 25 | 122 ± 29 |
| Tmax [h] | - | - | 0.26 ± 0.10 | 0.46 ± 0.29 |
Incremental recovery was further evaluated in 99 patients (PUP) <6 years of age in a prospective, uncontrolled, open-label, multicenter trial. Incremental recovery remained relatively stable over time of treatment with mean (SD) incremental recovery values (1‑stage clotting method) of 1.670 (0.594) (IU/dL)/(IU/kg) (n=99), 1.617 (0.640) (IU/dL)/(IU/kg) (n=47), 1.805 (0.593) (IU/dL)/(IU/kg) (n=87), and 1.873 (0.440) (IU/dL)/(IU/kg) (n=89), at baseline, visit 3 (ED 15 ± 1), visit 6 (ED 40 ± 3), and trial completion/termination (ED 100 to 110), respectively.
The efficacy of ADYNOVATE was evaluated in 4 clinical studies, as described below.
Study 1
The safety, efficacy, and PK of ADYNOVATE were evaluated in a multicenter, open-label, prospective, non-randomized, two-arm clinical trial (Study 261201, NCT01736475) that compared the efficacy of a twice weekly prophylactic treatment regimen to on-demand treatment and determined hemostatic efficacy in the treatment of bleeding episodes. A total of 137 male PTPs (12 to 65 years of age) with severe hemophilia A received at least one infusion with ADYNOVATE. Twenty-five of the 137 patients were adolescents (12 to less than 18 years of age).
Patients received either prophylactic treatment (n = 120) with ADYNOVATE at a dose of 40-50 IU per kg twice weekly or on-demand treatment (n = 17) with ADYNOVATE at a dose of 10-60 IU per kg for a 6-month period. The mean (SD) dose per prophylaxis infusion was 44.4 (3.9) IU per kg with a median dosing interval of 3.6 days. There were 91 out of 98 (93%) patients previously treated prophylactically prior to enrollment, who experienced a reduction in dosing frequency during routine prophylaxis in the trial, with a median reduction of 33.7% (approximately one more day between doses). One hundred eighteen of 120 (98%) prophylaxis patients remained on the starting recommended regimen without dose adjustment, and 2 patients increased their dose to 60 IU/kg during prophylaxis due to bleeding in target joints.
On-demand Treatment and Control of Bleeding Episodes
A total of 518 bleeding episodes were treated with ADYNOVATE in the per-protocol population, i.e. dosed according to the protocol specific dosing requirements. Of these, 361 bleeding episodes (n=17 patients) occurred in the on-demand arm and 157 (n=61 patients) occurred in the prophylaxis arm. The median dose per infusion to treat all bleeding episodes in the per-protocol population was 29 (Q1: 20.0; Q3: 39.2) IU per kg. The median dose per infusion to treat a minor, moderate, or severe/major bleeding episode in the per-protocol population was 25.5 (Q1: 16.9; Q3: 37.6) IU/kg, 30.9 (Q1: 23.0; Q3: 43.1) IU/kg, or 36.4 (Q1: 29.0; Q3: 44.5) IU/kg, respectively.
A total of 591 bleeding episodes were treated with ADYNOVATE in the treated population, which was identical to the safety analysis set of patients assigned to routine prophylaxis or on-demand treatment with ADYNOVATE and who received at least one dose of the product. Of these, 361 bleeding episodes (n=17 patients) occurred in the on-demand arm and 230 bleeding episodes (n=75 patients) occurred in the routine prophylaxis arm. Efficacy in control of bleeding episodes is summarized in Table 5.
Table 5: Summary of Efficacy in Control of Bleeding (Treated Population)| Bleeding Episode Etiology | All | Joint | Non-joint |
|---|
| Number of bleeds treated | 591 | 455 | 136 |
| Number of infusions to treat bleeding episodes | 1 infusions: | 85.4% | 85.9% | 83.8% |
| 2 infusions: | 10.8% | 10.8% | 11.0% |
| Total (1 or 2 infusions): | 96.2% | 96.7% | 94.8% |
| Rate of success to treat bleeding episodes Excellent defined as full relief of pain and objective signs of bleeding cessation; Good defined as definite pain relief and/or improvement in signs of bleeding; Fair defined as probable and/or slight relief of pain and slight improvement in signs of bleeding after a single infusion. Required more than 1 infusion for complete resolution; None defined as no improvement or condition worsened. | Excellent or good | 95.3% | 95.8% | 93.4% |
Routine Prophylaxis
A total of 120 patients (treated population) received a twice a week regimen in the prophylaxis arm, and an additional 17 patients were treated episodically in the on-demand arm. In the treated population, the median [mean] annualized bleed rate (ABR) in the on-demand treatment arm was 41.5 [40.8] compared to 1.9 [4.7] while on a twice a week prophylaxis regimen (Table 6). In the per-protocol population, the median [mean] annualized bleed rate (ABR) in the on-demand treatment arm was 41.5 [40.8] compared to 1.9 [3.7] while on a twice a week prophylaxis regimen. Using a negative binomial model to estimate the ABR, there was a significant reduction in the ABR (p <0.0001) for patients in the prophylaxis arm compared to the on-demand arm.
Table 6: Annualized Bleed Rate by Treatment for ≥ 12 Years of Age (Treated Population)| Bleeding Episode Etiology | On-Demand Treatment | Routine Prophylaxis Treatment |
|---|
| Median | Mean (SD) | Median | Mean (SD) |
|---|
| Overall | 41.5 | 40.8 (16.3) | 1.9 | 4.7 (8.6) |
| Joint | 38.1 | 34.7 (15.1) | 0.0 | 2.9 (8.0) |
| Non-Joint | 3.7 | 6.1 (6.7) | 0.0 | 1.8 (3.0) |
| Spontaneous | 21.6 | 26.0 (19.6) | 0.0 | 2.9 (7.1) |
| Traumatic | 9.3 | 14.9 (15.3) | 0.0 | 1.8 (3.1) |
In the treated population, the median [mean] ABR for the 23 adolescent patients age 12 to <18 years of age on routine prophylaxis was 2.1 [5.2] compared to a median [mean] ABR of 1.9 [4.6] for the 97 patients 18 years and older. Reduction in ABR between the treatment arms was observed regardless of baseline subgroups examined, including age, presence or absence of target joints, and pre-trial treatment regimen. The majority of the bleeding episodes during prophylaxis (95%) were of minor/moderate severity. Forty-five out of 120 patients (38%) experienced no bleeding episodes and 68 out of 120 patients (57%) experienced no joint bleeding episodes in the prophylaxis arm. Of those patients who were compliant to regimen (per-protocol population), 40 out of 101 patients (40%) experienced no bleeding episodes. All patients in the on-demand arm experienced a bleeding episode, including a joint bleeding episode.
Study 2
Routine Prophylaxis Clinical Trial in Pediatric Patients (<12 years of age)
The safety and efficacy of ADYNOVATE was evaluated in a total of 73 pediatric PTPs with severe hemophilia A, of which 66 patients were dosed (32 patients aged <6 years and 34 patients aged 6 to <12 years) in a separate pediatric clinical trial (Study 261202, NCT02210091). The prophylactic regimen was 40 to 60 IU/kg of ADYNOVATE twice a week, with a mean (SD) dose of 51.1 IU/kg (5.5). The median [mean] overall ABR was 2.0 [3.61] for the 66 patients in the treated population and the median [mean] ABRs for spontaneous and joint bleeding episodes were both 0 [1.18 and 1.12, respectively]. Of the 66 patients treated prophylactically, 25 (38%) experienced no bleeding episodes, 44 (67%) experienced no spontaneous bleeding episodes, and 48 (73%) experienced no joint bleeding episodes.
Of the 70 bleeding episodes observed during the pediatric trial, 82.9% were controlled with 1 infusion and 91.4% were controlled with 1 or 2 infusions. Control of bleeding was rated excellent or good in 63 out of 70 (90%) bleeding episodes. The definitions of excellent or good in the pediatric clinical trial were unchanged as compared to the previously conducted prophylaxis clinical trial in adolescent and adult patients.
Study 3
An extension study (Study 261302, NCT01945593) in adult and pediatric patients evaluated the safety and efficacy of prophylactic treatment regimen in 216 previously treated patients with severe hemophilia A. Majority had completed the adult and adolescent study or the pediatric study. Similar efficacy was noted in this extension study.
Study 4
Perioperative Management Clinical Trial
The safety and efficacy of ADYNOVATE in PTPs (aged 12 to 65 years) with severe hemophilia A, who were undergoing elective surgical or other invasive procedures, was evaluated in a multicenter, open-label clinical trial (Study 261204, NCT01913405). In this clinical trial 21 major surgical procedures comprising of 14 orthopedic, and 7 non-orthopedic procedures, and 5 additional minor surgeries were performed in 21 patients. The preoperative loading dose ranged from 36 IU/kg to 99 IU/kg (median: 60 IU/kg) and the total post-operative dose ranged from 23 IU/kg to 769 IU/kg (median: 183 IU/kg). The median total dose (including all administrations from pre-surgical PK and loading doses to post-hospital follow up) was 629 IU/kg (range: 464 – 1,457 IU/kg) for major orthopedic surgeries, 489 IU/kg (range: 296 – 738 IU/kg) for major non-orthopedic surgeries.
Overall hemostatic efficacy was rated as excellent (blood loss less than or equal to that expected for the same type of procedure performed in a non-hemophilic patient, for all 24 (21 major, 3 minor) procedures with available assessments.
How Supplied
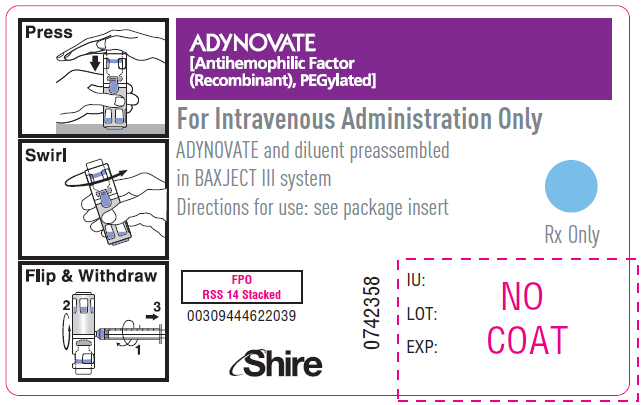
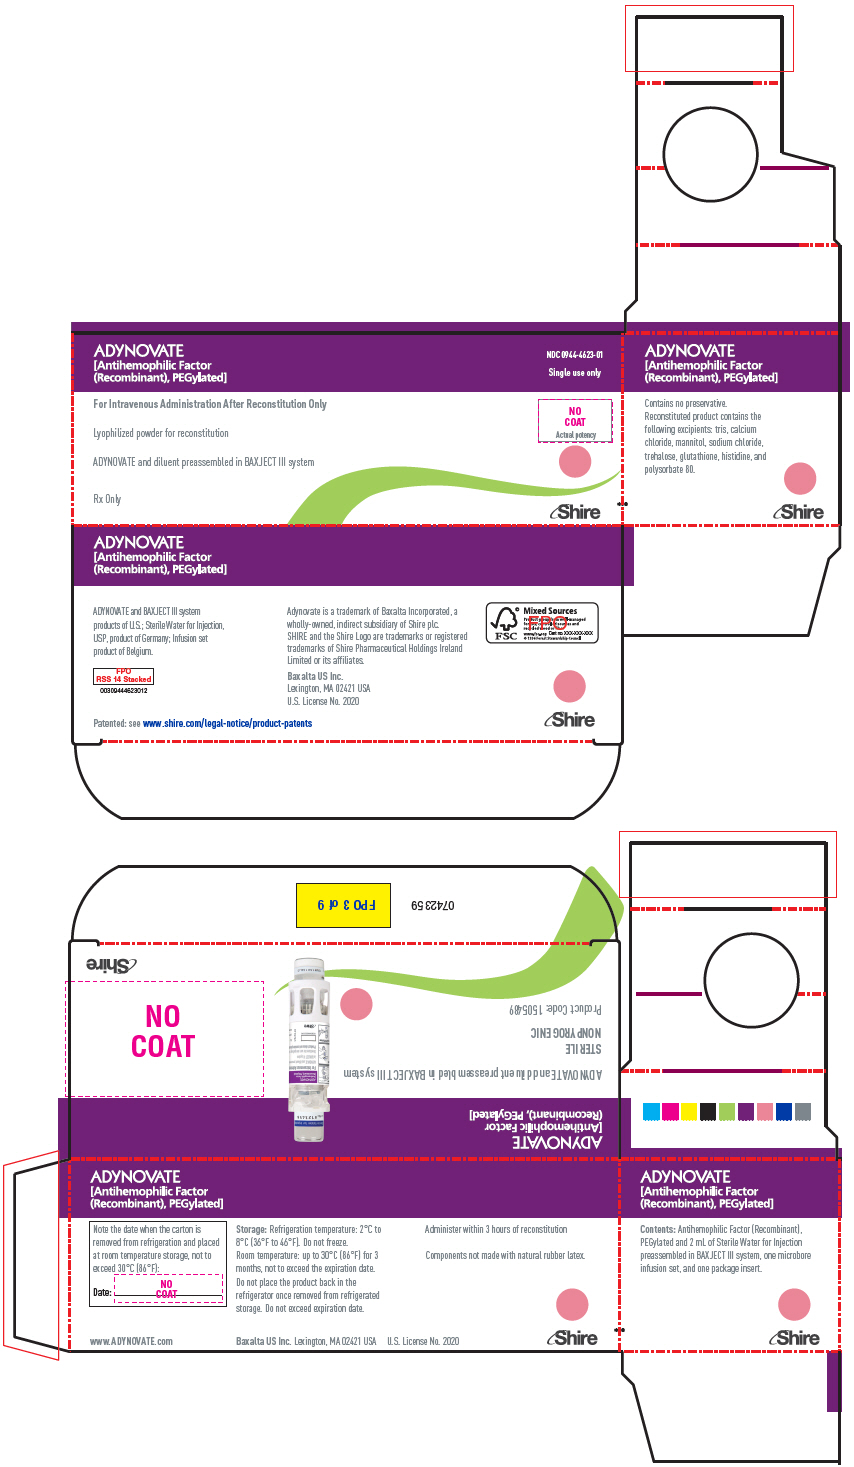
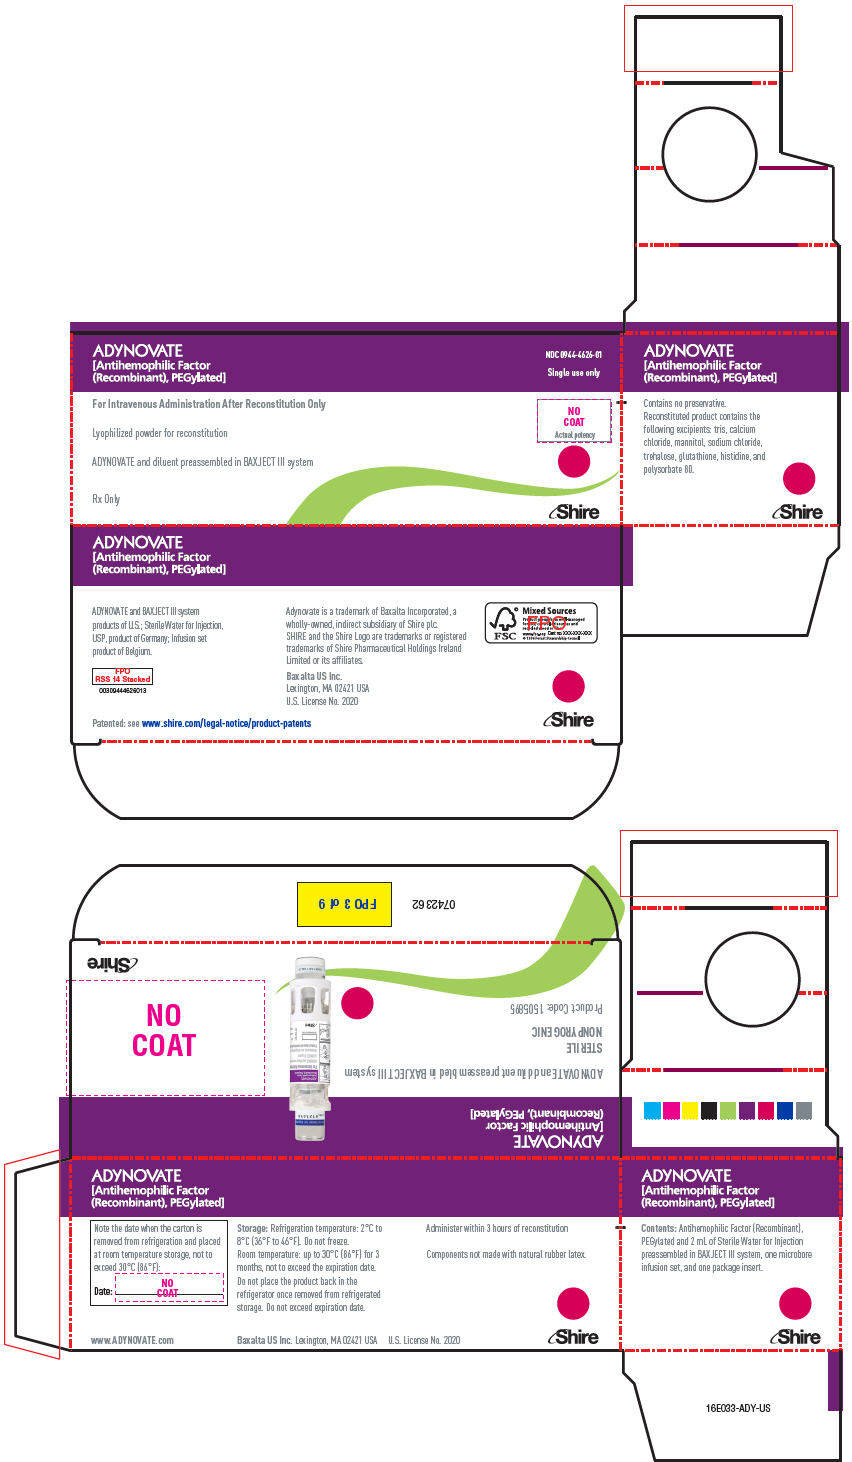
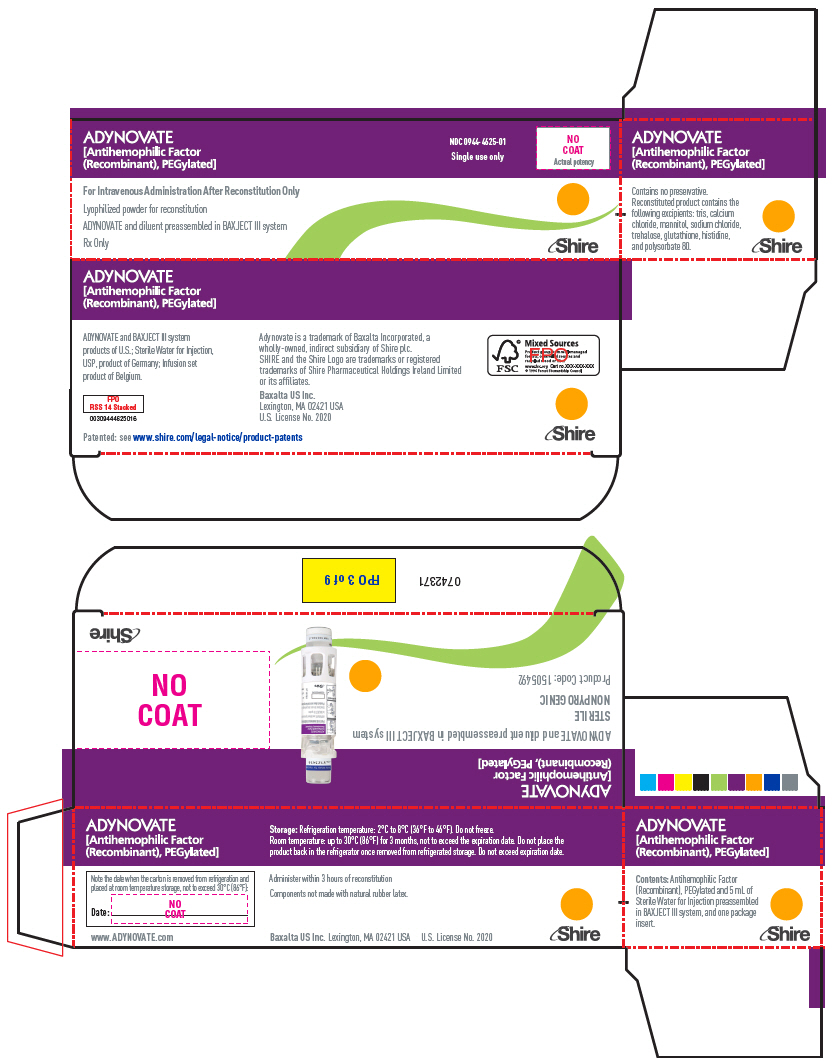
ADYNOVATE in a BAXJECT III system is packaged with 2 mL or 5 mL of Sterile Water for Injection, one Terumo Microbore Infusion set (2 mL only), one full prescribing physician insert and one patient insert. Components not made with natural rubber latex.
ADYNOVATE is available in single-dose vials that contain the following nominal product strengths:
| Nominal Strength | Potency Color Code | Carton NDC
(Includes 2 mL sWFI Diluent) | Carton NDC
(Includes 5 mL sWFI Diluent) |
|---|
| 250 IU | Light Blue | 0944-4622-01 | |
| 500 IU | Pink | 0944-4623-01 | |
| 750 IU | Red | 0944-4626-01 | |
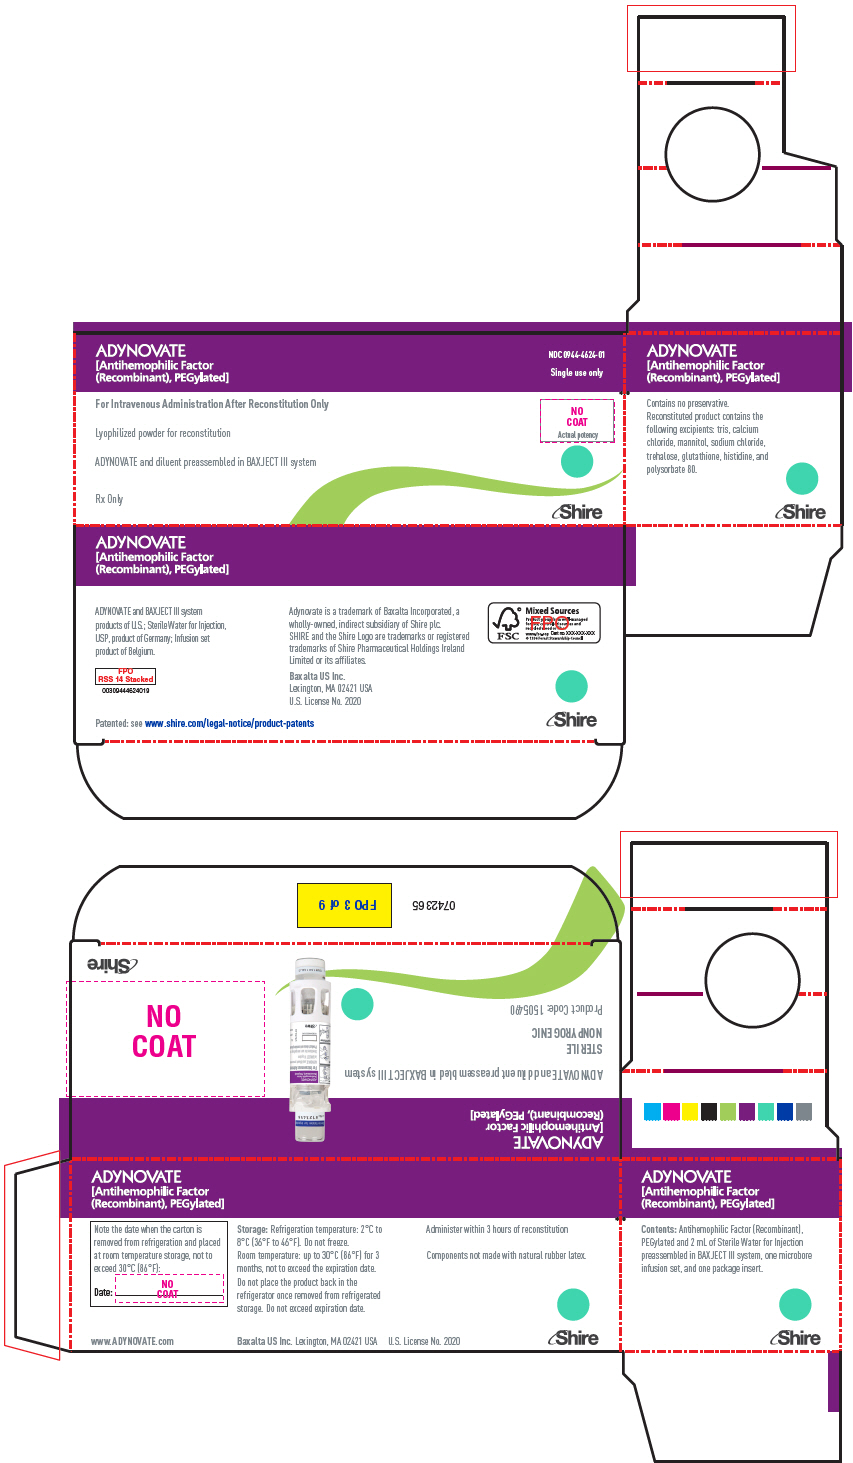
| 1000 IU | Light Green | 0944-4624-01 | |
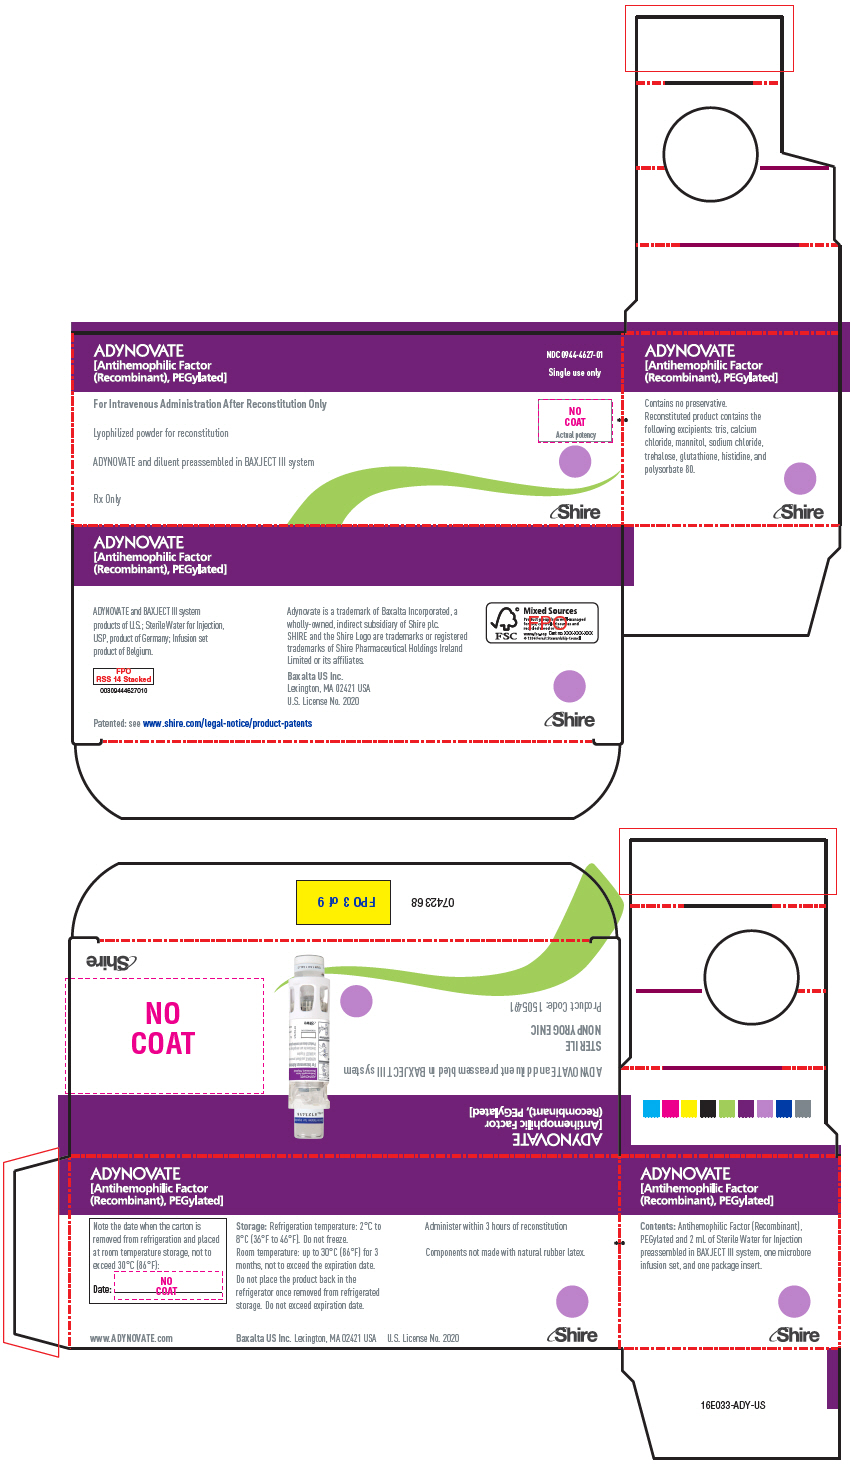
| 1500 IU | Purple | 0944-4627-01 | |
| 2000 IU | Orange | | 0944-4625-01 |
| 3000 IU | Silver | | 0944-4628-01 |
Actual factor VIII activity in IU is stated on the label of each ADYNOVATE carton and housing.
Takeda Pharmaceuticals U.S.A., Inc.
Cambridge, MA 02142
U.S. License No. 1898
ADYNOVATE, ADVATE and BAXJECT are registered trademarks of Baxalta Incorporated.
Takeda and are registered trademarks of Takeda Pharmaceutical Company Limited.
©2025 Takeda Pharmaceutical Company Limited. All rights reserved.
Patented: see www.takeda.com/en-us/patents