Adults with HoFH
The safety and effectiveness of JUXTAPID as an adjunct to a low-fat diet and other lipid-lowering treatments, including LDL apheresis where available, were evaluated in a multinational, single-arm, open-label, 78-week trial involving 29 adults with HoFH. A diagnosis of HoFH was defined by the presence of at least one of the following clinical criteria: (1) documented functional mutation(s) in both LDL receptor alleles or alleles known to affect LDL receptor functionality, or (2) skin fibroblast LDL receptor activity <20% normal, or (3) untreated TC >500 mg/dL and TG <300 mg/dL and both parents with documented untreated TC >250 mg/dL.
Among the 29 patients enrolled, the mean age was 31 years (range, 18 to 55 years), 16 (55%) were male, and the majority (86%) were White. The mean body mass index (BMI) was 25.8 kg/m2, with four patients meeting BMI criteria for obesity; one patient had type 2 diabetes. Concomitant lipid-lowering treatments at baseline included one or more of the following: statins (93%), ezetimibe (76%), nicotinic acid (10%), bile acid sequestrant (3%), and fibrate (3%); 18 (62%) were receiving apheresis.
After a six-week run-in period to stabilize lipid-lowering treatments, including the establishment of an LDL apheresis schedule if applicable, JUXTAPID was initiated at 5 mg daily and titrated to daily doses of 10 mg, 20 mg, 40 mg, and 60 mg at weeks 2, 6, 10, and 14, respectively, based on tolerability and acceptable levels of transaminases. Patients were instructed to maintain a low-fat diet (<20% calories from fat) and to take dietary supplements that provided approximately 400 international units vitamin E, 210 mg ALA, 200 mg linoleic acid, 110 mg EPA, and 80 mg (DHA per day [see Dosage and Administration (2.2), Warnings and Precautions (5.4)]. After efficacy was assessed at Week 26, patients remained on JUXTAPID for an additional 52 weeks to assess long-term safety. During this safety phase, the dose of JUXTAPID was not increased above each patient's maximum tolerated dose established during the efficacy phase, but changes to concomitant lipid-lowering treatments were allowed.
Twenty-three (79%) patients completed the efficacy endpoint at Week 26, all of whom went on to complete 78 weeks of treatment. Adverse events contributed to premature discontinuation for five patients [see Adverse Reactions (6.1)]. The maximum tolerated doses during the efficacy period were 5 mg (10%), 10 mg (7%), 20 mg (21%), 40 mg (24%), and 60 mg (34%).
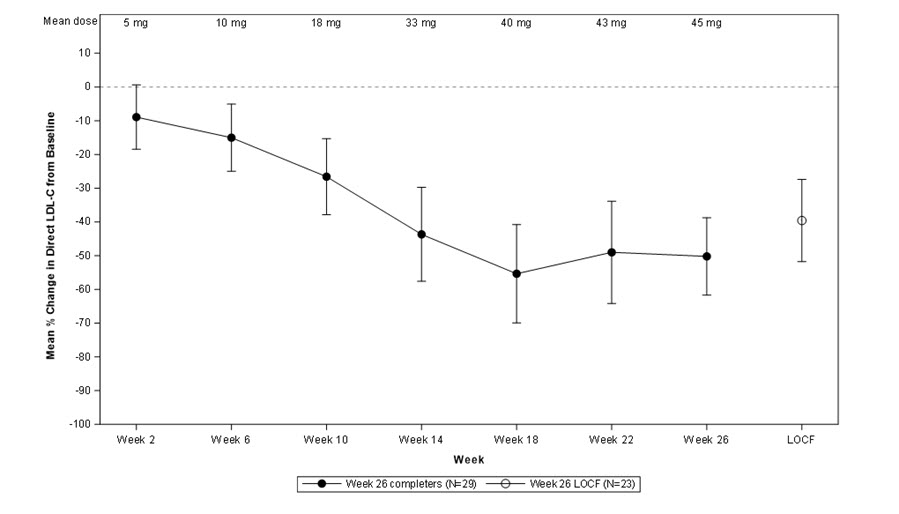
The primary efficacy endpoint was percent change in LDL-C from baseline to Week 26. At Week 26, the mean and median percent changes in LDL-C from baseline were -40% (paired t-test p<0.001) and -50%, respectively, based on the intent-to-treat population with last observation carried forward (LOCF) for patients who discontinued prematurely. The mean percent change in LDL-C from baseline through Week 26 is shown in Figure 1 for the 23 patients who completed the efficacy period.
| Figure 1: Mean Percent Change in LDL-C from Baseline (Week 26 Completers) |
|---|
| Error bars represent 95% confidence intervals of the mean. |
|
Changes in lipids and lipoproteins through the efficacy endpoint at Week 26 are presented in Table 14.
Table 14: Absolute Values and Percent Changes from Baseline in Lipids and Lipoproteins | PARAMETER | BASELINE | WEEK 26/LOCF
(N=29) |
|---|
| Mean (SD) | Mean (SD) | Mean % Change |
|---|
| LDL-C, direct (mg/dL) | 336 (114) | 190 (104) | -40 Statistically significant compared with baseline based on the pre-specified gatekeeping method for controlling Type I error among the primary and key secondary endpoints. |
| TC (mg/dL) | 430 (135) | 258 (118) | -36 |
| apo B (mg/dL) | 259 (80) | 148 (74) | -39 |
| Non-HDL-C (mg/dL) | 386 (132) | 217 (113) | -40 |
| VLDL-C (mg/dL) | 21 (10) | 13 (9) | -29 |
| TG (mg/dL) Median values with interquartile range and median % change presented for TG. | 92 [72, 128] | 57 [36, 78] | -45 |
| HDL-C (mg/dL) | 44 (11) | 41 (13) | -7 |
After Week 26, during the safety phase of the trial, adjustments to concomitant lipid-lowering treatments were allowed. For the study population overall, average reductions in LDL-C, TC, apo B, and non-HDL-C were sustained during chronic therapy.
Pediatric Patients with HoFH
A single-arm, open-label, 104-week trial evaluated the efficacy of JUXTAPID when co-administered with a low-fat diet in pediatric patients aged 5 to 17 years of age with HoFH on stable lipid lowering therapy (LLT), including low density lipoprotein (LDL) apheresis, when applicable. A diagnosis of HoFH was defined by any of the following criteria: (1) genetic confirmation of 2 mutant alleles at the LDLR, apo B, PCSK9, or LDLR adapter protein 1 (LDLRAP1) gene loci, or (2) an untreated LDL-C >500 mg/dL or treated LDL-C ≥300 mg/dL together with either a cutaneous or tendon xanthoma before age 10 years or untreated LDL-C levels consistent with heterozygous familial hypercholesterolemia in both parents.
A total of 43 patients (19 males, 44% and 24 females, 56%) between 5 and 17 years of age (mean age of 11 years) were treated in this trial. The majority (98%) of patients were White (one [2%] patient was Black or African American and one [2%] patient identified as Hispanic/Latino ethnicity). The mean BMI was 19 kg/m2. Concomitant LLT at baseline included one or more of the following: statins (91%), ezetimibe (74%), and evolocumab (12%); 19 (44%) patients were receiving apheresis through Week 24.
The trial consisted of a 6-week run-in period, followed by a 24-week efficacy phase, and then an 80-week safety phase. The dose of JUXTAPID was escalated from an age-dependent starting dose to a maximum tolerated dose as applicable to the pediatric age group (see Table 2). Patients were instructed to maintain a low-fat diet (<20% calories from fat or <30g fat, whichever was the lesser amount) and to take dietary supplements that provided vitamin E (200 IU for patients for 5 to 8 years of age, 400 IU for patients 9 years of age and older) and approximately 200 mg linoleic acid, 210 mg ALA, 110 mg EPA, and 80 mg DHA [see Dosage and Administration 2.2, Warnings and Precautions (5.4)]. After Week 24, patients entered the 80-week safety phase and remained on JUXTAPID to determine the effects of longer-term treatment. At the discretion of the investigator, patients were allowed to change their background LLT and/or increase the JUXTAPID dose (in exceptional cases only) during the safety phase. There was no significant change in LLTs, however apheresis was reduced or discontinued in 47% of patients receiving apheresis at Week 24 (refer to the subgroup analysis below which showed that mean LDL-C levels in the LDL apheresis group showed a gradual increase over time when apheresis was reduced or discontinued).
Forty-six (46) patients were enrolled, of whom 43 completed the run-in period, 41 completed Week 24, and 39 completed the safety phase. In the efficacy phase, 95% of patients aged 5 to 10 years received the MTD of 20 mg, 76% of patients aged 11 to 15 years received the MTD of 40 mg, and 50% of patients aged 16 to 17 years received the MTD of 60 mg but had to down-titrate soon after reaching this dose.
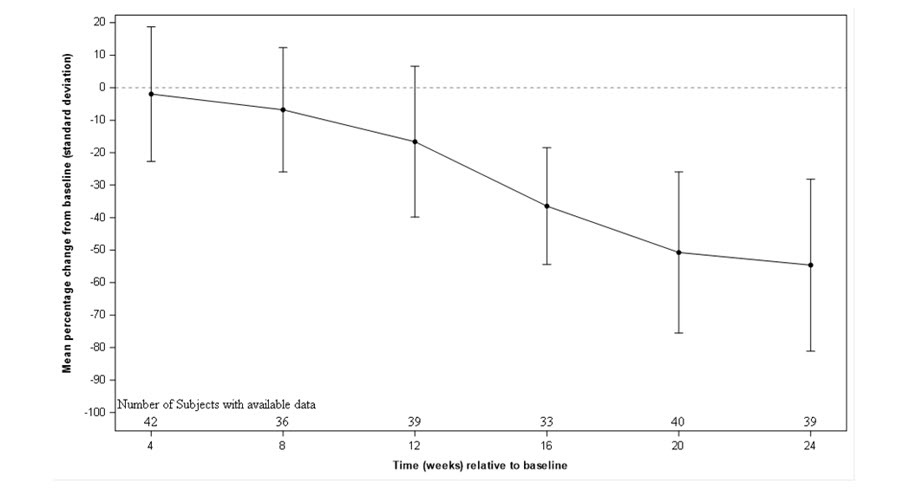
The primary endpoint was percent change in LDL-C from baseline to Week 24. At Week 24, the mean percent change in LDL-C from baseline was -49% (95% CI: -59%, -38%) (see Figure 2 which presents mean percentage change from baseline of observed LDL-C values).
Figure 2: Observed Mean Percent Change in LDL-C from Baseline in Pediatric Patients Aged 5 to 17 years
Subgroup analysis was carried out on patients aged 5 to 10 years (N=20) and 11 to 17 years (N=23). Mean decreases from baseline in LDL-C at Week 24 were 52% and 46%, respectively. Subgroup analysis also demonstrated mean decreases from baseline in LDL-C at Week 24 of approximately 36% in patients receiving LDL apheresis at baseline and 62% in patients not receiving LDL apheresis at baseline. During the long-term treatment (over 2 years), mean LDL-C levels in the LDL apheresis group showed a gradual increase over time.
The key secondary endpoint was the mean percent change in lipid parameters (non-HDL-C, total cholesterol, VLDL-C, apo B, and triglycerides) from baseline to Week 24. At Week 24, there were mean percent decreases from baseline in each of the lipid parameters assessed (summarized in Table 15).
Table 15: Absolute Values and Percent Changes from Baseline to Week 24 in Lipids and Lipoproteins in Pediatric Patients Aged 5 to 17 Years| PARAMETER (UNITS) | BASELINE | WEEK 24 (N = 43) |
|---|
MEAN
(SD) | MEAN
(95% CI) | % CHANGE
(95% CI) |
|---|
LDL-C = Low Density Lipoprotein-C; SD = standard deviation
Missing values at Week 24 were imputed using a return to baseline multiple imputation approach. |
| LDL-C, direct (mg/dL) | 436
(189) | 195
(160, 230) | -49
(-59%, -38%) |
| Total Cholesterol (TC) (mg/dL) | 486
(188) | 237
(200, 275) | -45
(-55%, -36%) |
| Apolipoprotein B (apo B) (mg/dL) | 317
(133) | 146
(121, 171) | -48
(-58%, -37%) |
| Triglycerides (TG) (mg/dL) | 92
(39) | 45
(37, 53) | -46
(-57%, -35%) |
| Non-high-density lipoprotein cholesterol (Non-HDL-C) (mg/dL) | 454
(192) | 204
(167, 241) | -49
(-59%, -39%) |
| Very-low-density lipoprotein cholesterol (VLDL-C) (mg/dL) | 18
(8) | 9
(7, 11) | -46
(-57%, -36%) |
Average reductions in LDL-C, TC, apo B, TG, non-HDL-C, and VLDL-C were sustained during long-term treatment (over 2 years) particularly in patients not receiving LDL apheresis at baseline.