Other
Addiction, Abuse, and Misuse
Because the use of XTAMPZA ER exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death, assess each patient's risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions [see Warnings and Precautions (5.1)].
Life-Threatening Respiratory Depression
Serious, life-threatening, or fatal respiratory depression may occur with use of XTAMPZA ER, especially during initiation or following a dosage increase. To reduce the risk of respiratory depression, proper dosing and titration of XTAMPZA ER are essential [see Warnings and Precautions (5.2)].
Accidental Ingestion
Accidental ingestion of even one dose of XTAMPZA ER, especially by children, can result in a fatal overdose of oxycodone [see Warnings and Precautions (5.2)].
Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants
Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of XTAMPZA ER and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate. [see Warnings and Precautions (5.3), Drug Interactions (7)].
Neonatal Opioid Withdrawal Syndrome (NOWS)
Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery [see Warnings and Precautions (5.4)].
Opioid Analgesic Risk Evaluation and Mitigation Strategy (REMS)
Healthcare providers are strongly encouraged to complete a REMS-compliant education program and to counsel patients and caregivers on serious risks, safe use, and the importance of reading the Medication Guide with each prescription [see Warnings and Precautions (5.5)].
Cytochrome P450 3A4 Interaction
The concomitant use of XTAMPZA ER with all cytochrome P450 3A4 inhibitors may result in an increase in oxycodone plasma concentrations, which could increase or prolong adverse drug effects and may cause potentially fatal respiratory depression. In addition, discontinuation of a concomitantly used cytochrome P450 3A4 inducer may result in an increase in oxycodone plasma concentration. Regularly evaluate patients receiving XTAMPZA ER and any CYP3A4 inhibitor or inducer [see Warnings and Precautions (5.6), Drug Interactions (7),Clinical Pharmacology (12.3)].
Limitations of Use
- Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration and persist over the course of therapy [see Warnings and Precautions (5.1)], reserve opioid analgesics, including XTAMPZA ER, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
- XTAMPZA ER is not indicated as an as-needed (prn) analgesic.
- approximately 1% to 6% of participants across the two cohorts newly met criteria for addiction, as assessed with two validated interview-based measures of moderate-to-severe opioid use disorder based on Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) criteria, and
- approximately 9% and 22% of participants across the two cohorts newly met criteria for prescription opioid abuse and misuse [defined in Drug Abuse and Dependence (9.2)], respectively, as measured with a validated self-reported instrument.
- how to treat with the overdose reversal agent in the event of an opioid overdose.
- to tell family and friends about the opioid overdose reversal agent, and to keep it in a place where family and friends can access it in an emergency.
- to read the Patient Information (or other educational material) that will come with their opioid overdose reversal agent. Emphasize the importance of doing this before an opioid emergency happens, so the patient and caregiver will know what to do.
- Taking XTAMPZA ER with food
- Swallowing XTAMPZA ER capsules whole or sprinkling the capsule contents on soft food or into a cup and administering directly into the mouth
- Using XTAMPZA ER exactly as prescribed to reduce the risk of life-threatening adverse reactions (e.g., respiratory depression)
Use of XTAMPZA ER in Patients who are not Opioid Tolerant
The starting dose for patients who are not opioid tolerant is XTAMPZA ER 9 mg orally every 12 hours with food. Use of higher starting doses in patients who are not opioid tolerant may cause fatal respiratory depression [see Warnings and Precautions (5.2)].
Conversion from other Oral Oxycodone Formulations to XTAMPZA ER
XTAMPZA ER is formulated with oxycodone base. The following table describes the equivalent amount of oxycodone HCl present in other oxycodone products.
| Oxycodone Hydrochloride | Oxycodone base (XTAMPZA ER) |
|---|---|
| 10 mg | 9 mg |
| 15 mg | 13.5 mg |
| 20 mg | 18 mg |
| 30 mg | 27 mg |
| 40 mg | 36 mg |
Patients receiving other oral oxycodone formulations may be converted to XTAMPZA ER, using the same total daily dose of oxycodone, by administering one-half of the patient's total daily oral oxycodone dose as XTAMPZA ER every 12 hours with food. Because XTAMPZA ER is not bioequivalent to other oxycodone extended-release products (refer to Table 1), monitor patients for possible dosage adjustment.
Conversion from Methadone to XTAMPZA ER
Frequent evaluation is of particular importance when converting from methadone to other opioid agonists. The ratio between methadone and other opioid agonists may vary widely as a function of previous dose exposure. Methadone has a long half-life and can accumulate in the plasma.
Conversion from Fentanyl Transdermal System to XTAMPZA ER
Eighteen hours following the removal of the fentanyl transdermal system, XTAMPZA ER treatment can be initiated. Although there has been no systematic assessment of such conversion, a conservative oxycodone dose, approximately 9 mg (equivalent to 10 mg oxycodone HCl) every 12 hours of XTAMPZA ER, should be initially substituted for each 25 mcg/hr fentanyl transdermal system. Follow the patient closely during conversion from fentanyl transdermal system to XTAMPZA ER, as there is limited documented experience with this conversion.
Conversion from Other Opioid Analgesics to XTAMPZA ER
When XTAMPZA ER therapy is initiated, discontinue all other opioid analgesics other than those used on an as needed basis for breakthrough pain when appropriate.
There are no established conversion ratios for conversion from other opioids to XTAMPZA ER defined by clinical trials. Initiate dosing using XTAMPZA ER 9 mg orally every 12 hours with food.
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose
Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene). Discuss the importance of having access to an opioid overdose reversal agent, especially if the patient has risk factors for overdose (e.g., concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose) or if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose. The presence of risk factors for overdose should not prevent the management of pain in any patient [see Warnings and Precautions (5.1, 5.2)].
Discuss the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter, or as part of a community-based program).
There are important differences among the opioid overdose reversal agents, such as route of administration, product strength, approved patient age range, and pharmacokinetics. Be familiar with these differences, as outlined in the approved labeling for those products, prior to recommending or prescribing such an agent. outlined in the approved labeling for those products, prior to recommending or prescribing such an agent.
Educate patients and caregivers on how to recognize respiratory depression, and how to use an opioid overdose reversal agent for the emergency treatment of opioid overdose. Emphasize the importance of calling 911 or getting emergency medical help, even if an opioid overdose reversal agent is administered [see Dosage and Administration (2.2), Warnings and Precautions (5.1, 5.3), Overdosage (10)].
Patients with Chronic Pulmonary Disease: XTAMPZA ER-treated patients with significant chronic obstructive pulmonary disease or cor pulmonale, and those with a substantially decreased respiratory reserve, hypoxia, hypercapnia, or pre-existing respiratory depression are at increased risk of decreased respiratory drive including apnea, even at recommended dosages of XTAMPZA ER [see Warnings and Precautions (5.2)].
Elderly, Cachectic, or Debilitated Patients: Life-threatening respiratory depression is more likely to occur in elderly, cachectic, or debilitated patients as they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients.
Regularly evaluate patients, particularly when initiating and titrating XTAMPZA ER and when XTAMPZA ER is given concomitantly with other drugs that depress respiration [see Warnings and Precautions (5.2, 5.3)]. Alternatively, consider the use of non-opioid analgesics in these patients. Use an alternative analgesic for patients who require a dose of XTAMPZA ER less than 9 mg.
Adverse Reactions from Observational Studies
A prospective, observational cohort study estimated the risks of addiction, abuse, and misuse in patients initiating long-term use of Schedule II opioid analgesics between 2017 and 2021. Study participants included in one or more analyses had been enrolled in selected insurance plans or health systems for at least one year, were free of at least one outcome at baseline, completed a minimum number of follow-up assessments, and either: 1) filled multiple extended-release/long-acting opioid analgesic prescriptions during a 90- day period (n=978); or 2) filled any Schedule II opioid analgesic prescriptions covering at least 70 of 90 days (n=1,244). Those included also had no dispensing of the qualifying opioids in the previous 6 months.
Over 12 months:
A retrospective, observational cohort study estimated the risk of opioid-involved overdose or opioid overdose-related death in patients with new long-term use of Schedule II opioid analgesics from 2006 through 2016 (n=220,249). Included patients had been enrolled in either one of two commercial insurance programs, one managed care program, or one Medicaid program for at least 9 months. New long-term use was defined as having Schedule II opioid analgesic prescriptions covering at least 70 days' supply over the 3 months prior to study entry and none during the preceding 6 months. Patients were excluded if they had an opioid-involved overdose in the 9 months prior to study entry. Overdose was measured using a validated medical code-based algorithm with linkage to the National Death Index database. The 5-year cumulative incidence estimates for opioid-involved overdose or opioid overdose-related death ranged from approximately 1.5% to 4% across study sites, counting only the first event during follow-up. Approximately 17% of first opioid overdoses observed over the entire study period (5-11 years, depending on the study site) were fatal. Higher baseline opioid dose was the strongest and most consistent predictor of opioid-involved overdose or opioid overdose-related death. Study exclusion criteria may have selected patients at lower risk of overdose, and substantial loss to follow-up (approximately 80%) also may have biased estimates.
The risk estimates from the studies described above may not be generalizable to all patients receiving opioid analgesics, such as those with exposures shorter or longer than the duration evaluated in the studies.
Risk Summary
Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions (5.4)]. There are no available data with XTAMPZA ER in pregnant women to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, there was no embryo-fetal toxicity when oxycodone hydrochloride was orally administered to rats and rabbits, during the period of organogenesis, at doses 1.3 to 40 times the adult human dose of 60 mg/day, respectively. In a pre- and postnatal toxicity study, when oxycodone was orally administered to rats, there was transiently decreased pup body weight during lactation and the early post-weaning period at the dose equivalent to an adult dose of 160 mg/day. In several published studies, treatment of pregnant rats with oxycodone hydrochloride at clinically relevant doses and below resulted in neurobehavioral effects in offspring [see Data]. Based on animal data, advise pregnant women of the potential risk to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations
Fetal/neonatal adverse reactions
Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high-pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration of use, and severity of neonatal opioid withdrawal syndrome may vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions (5.4)].
Labor or delivery
Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of opioid induced respiratory depression in the neonate. XTAMPZA ER is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate. Opioid analgesics, including XTAMPZA ER, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilatation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Data
Animal Data
Studies with oral doses of oxycodone hydrochloride in rats up to 8 mg/kg/day and rabbits up to 125 mg/kg/day, equivalent to 1.3 and 40 times an adult human dose of 160 mg/day, respectively on a mg/m2 basis, did not reveal evidence of harm to the fetus due to oxycodone. In a pre- and postnatal toxicity study, female rats received oxycodone during gestation and lactation. There were no drug-related effects on reproductive performance in these females or any long-term developmental or reproductive effects in pups born to these rats. Decreased body weight was found during lactation and the early post-weaning phase in pups nursed by dams given the highest dose used (6 mg/kg/day, equivalent to an adult human dose of 160 mg/day, on a mg/m2 basis). However, body weight of these pups recovered. In published studies, offspring of pregnant rats administered oxycodone hydrochloride during gestation have been reported to exhibit neurobehavioral effects including altered stress responses and increased anxiety-like behavior (2 mg/kg/day IV from Gestation Day 8 to 21 and Postnatal Day 1, 3, and 5; 0.3-times an adult human oral dose of 60 mg/day on a mg/m2 basis), and altered learning and memory (15 mg/kg/day orally from breeding through parturition; 2.4 times an adult human oral dose of 60 mg/day on a mg/m2 basis).
Risk Summary
Oxycodone is present in breast milk. Published lactation studies report variable concentrations of oxycodone in breast milk with administration of immediate-release oxycodone to nursing mothers in the early postpartum period. The lactation studies did not assess breastfed infants for potential adverse reactions. Lactation studies have not been conducted with extended–release oxycodone, including XTAMPZA ER, and no information is available on the effects of the drug on the breastfed infant or the effects of the drug on milk production. Because of the potential for serious adverse reactions, including excess sedation and respiratory depression in a breastfed infant, advise patients that breastfeeding is not recommended during treatment with XTAMPZA ER.
Clinical Considerations
Monitor infants exposed to XTAMPZA ER through breast milk for excess sedation and respiratory depression. Withdrawal symptoms can occur in breastfed infants when maternal administration of an opioid analgesic is stopped, or when breast-feeding is stopped.
Infertility
Use of opioids for an extended period of time may cause reduced fertility in females and males of reproductive potential. It is not known whether these effects on fertility are reversible [see Adverse Reactions (6.2), Clinical Pharmacology (12.2), Nonclinical Toxicology (13.1)].
Risks Specific to Abuse of XTAMPZA ER
Abuse of XTAMPZA ER poses a risk of overdose and death. The risk is increased with concurrent use of XTAMPZA ER with alcohol and/or other CNS depressants [see Warnings and Precautions (5.1, 5.3), Drug Interactions (7)].
XTAMPZA ER is approved for oral use only.
Parenteral drug abuse is commonly associated with transmission of infectious diseases such as hepatitis and HIV.
Abuse Deterrence Studies
XTAMPZA ER capsules contain microspheres formulated with inactive ingredients intended to make the formulation more difficult to manipulate for misuse and abuse.
In Vitro Testing
In vitro physical and chemical manipulation studies were performed to evaluate the success of different methods of defeating the extended-release formulation.
Results support that, relative to immediate-release oxycodone tablets, XTAMPZA ER is less susceptible to the effects of grinding, crushing, and extraction using a variety of tools and solvents.
XTAMPZA ER resisted attempts to pass the melted capsule contents or the microspheres suspended in water through a hypodermic needle.
Pharmacokinetic Studies
The pharmacokinetic profile of manipulated XTAMPZA ER capsule contents (36 mg; [equivalent to 40 mg oxycodone HCl]) was characterized following oral (three studies) and intranasal (two studies) administration. The studies were conducted in a randomized, cross-over design. In studies assessing manipulation by crushing, the most effective crushing method identified in previous in vitro studies was applied to the product(s).
Oral Pharmacokinetic Studies, Manipulated and Intact XTAMPZA ER
The effect of two types of product manipulation (crushing and chewing) on XTAMPZA ER pharmacokinetics was measured in three studies.
In one oral pharmacokinetic study, XTAMPZA ER capsule contents were crushed or chewed prior to oral administration in healthy, naltrexone-blocked volunteers. The two comparators in this study were intact XTAMPZA ER capsules and an immediate-release solution of oxycodone at an equivalent dose.
In two oral pharmacokinetic studies, XTAMPZA ER capsule contents were crushed prior to oral administration in healthy, naltrexone-blocked volunteers. The comparators in these studies included intact XTAMPZA ER capsules, intact and crushed reformulated OXYCONTIN (oxycodone hydrochloride) extended-release tablets at an equivalent dose, and crushed immediate-release oxycodone tablets at an equivalent dose.
The data displayed in Table 4 illustrate the findings from the oral pharmacokinetic studies (data were similar for the two oral pharmacokinetic studies comparing XTAMPZA ER to OXYCONTIN). Collectively, the data demonstrated that crushing or chewing XTAMPZA ER prior to administration did not increase the maximum observed plasma concentration (Cmax) or total exposure (AUC0-INF) relative to dosing the intact product under fed conditions. Relative to immediate-release oxycodone and crushed reformulated OXYCONTIN (oxycodone hydrochloride) extended-release tablets, the Cmax for all XTAMPZA ER treatments was lower and the Tmax longer, consistent with an extended-release profile.
| Cmax (ng/mL) | Tmax (hr) | AUC0-INF (hr∙ng/mL) | |
|---|---|---|---|
| Values shown for Cmax and AUC0-INF are mean (standard deviation); values shown for Tmax are median (minimum-maximum). | |||
| Treatment | Oral Pharmacokinetic Study 1 | ||
| Intact XTAMPZA ER Capsules (fed) | 62.3 (13.0) | 4.0 (1.5-6) | 561 (124) |
| Crushed XTAMPZA ER Capsule Contents (fed) | 57.6 (12.6) | 4.5 (2.5-6) | 553 (134) |
| Chewed XTAMPZA ER Capsule Contents (fed) | 55.6 (10.9) | 4.5 (2.5-8) | 559 (113) |
| Immediate-Release Oxycodone Solution (fasted) | 115 (27.3) | 0.75 (0.5-2) | 489 (80.2) |
| Oral Pharmacokinetic Study 2 | |||
| Intact XTAMPZA ER Capsules (fed) | 67.5 (17.6) | 3.5 (1.25-6.0) | 581 (138) |
| Crushed XTAMPZA ER Capsule Contents (fed) | 62.9 (12.6) | 4.0 (2.0-7.0) | 597 (149) |
| Intact reformulated OXYCONTIN (oxycodone hydrochloride) extended-release tablets (fed) | 64.9 (13.8) | 5.0 (2.0-10.0) | 611 (145) |
| Crushed reformulated OXYCONTIN (oxycodone hydrochloride) extended-release tablets (fed) | 78.4 (12.9) | 1.75 (0.5-5.0) | 587 (132) |
| Crushed Immediate-Release Oxycodone Tablets (fed) | 79.4 (17.1) | 1.75 (0.5-4.0) | 561 (146) |
Nasal Pharmacokinetic Studies
The pharmacokinetic profile following intranasal administration of crushed XTAMPZA ER capsule contents was characterized in two clinical studies.
In Nasal Pharmacokinetic Study 1, XTAMPZA ER capsule contents (36 mg) were crushed and intranasally administered by non-dependent, naltrexone-blocked subjects with a history of nasal abuse of opioids. The two comparators in this study were intact XTAMPZA ER capsules (oral) and oxycodone HCl powder (intranasal) at an equivalent dose.
In Nasal Pharmacokinetic Study 2, XTAMPZA ER capsule contents (36 mg) were crushed and intranasally administered by non-dependent subjects with a history of nasal abuse of opioids. The two comparators in this study were intact XTAMPZA ER capsules (oral) and crushed oxycodone immediate-release tablets (intranasal) at an equivalent dose.
The results of Nasal Pharmacokinetic Studies 1 and 2 are comparable and both studies demonstrated that intranasal administration of crushed XTAMPZA ER capsule contents did not result in higher peak plasma concentration (Cmax) or shorter time to peak concentration (Tmax) than taking XTAMPZA ER orally. The data from Nasal Pharmacokinetic Study 2 are displayed in Table to represent these findings.
| Treatment | Cmax (ng/mL) | Tmax (hr) | AUC0-INF (hr∙ng/mL) |
|---|---|---|---|
| Values shown for Cmax and AUC0-INF are mean (standard deviation); values shown for Tmax are median (minimum-maximum). | |||
| Intact XTAMPZA ER Capsules (oral) | 41.0 (10.0) | 5.1 (1.6-8.1) | 477 (89.6) |
| Crushed XTAMPZA ER Capsule Contents (nasal) | 29.8 (6.6) | 5.1 (1.6-12.1) | 459 (106) |
| Crushed Immediate-Release Tablets (nasal) | 60.9 (11.9) | 2.6 (0.3-6.1) | 577 (124) |
Clinical Studies
Oral Abuse Potential Studies:
The oral abuse potential of chewed XTAMPZA ER was evaluated in two studies.
In a randomized, double-blind, active- and placebo-controlled, single-dose, six-way crossover pharmacodynamic study, 52 non-dependent recreational opioid users received orally-administered active and placebo treatment. The six treatment arms were intact XTAMPZA ER (36 mg, fed and fasted); chewed XTAMPZA ER (36 mg, fed and fasted); crushed immediate-release (IR) oxycodone HCl in solution (40 mg, fasted, equivalent to 36 mg of XTAMPZA ER), and placebo. Data for chewed and intact XTAMPZA ER and crushed IR oxycodone in the fasted state are described below.
Drug Liking was measured on a bipolar 100-point Visual Analog Scale (VAS) where 50 represents a neutral response, 0 represents maximum disliking, and 100 represents maximum liking. Response to whether the subject would take the study drug again was also measured on a bipolar 100-point VAS where 50 represents a neutral response, 0 represents the strongest negative response (e.g., 'definitely would not take drug again'), and 100 represents the strongest positive response (e.g., 'definitely would take drug again').
Fifty-two subjects completed the study, and the results are summarized in Table 5. The oral administration of chewed and intact XTAMPZA ER in the fasted state was associated with statistically lower mean Drug Liking and Take Drug Again VAS scores compared with crushed immediate-release oxycodone. In addition, the Drug Liking and Take Drug Again scores were similar for XTAMPZA ER taken in the intact and chewed states.
| XTAMPZA ER Intact (Fasted) | XTAMPZA ER Chewed (Fasted) | Crushed IR Oxycodone (Fasted) | Placebo | ||
|---|---|---|---|---|---|
| Emax = maximum (peak) effect; ER = extended-release; IR = immediate-release; VAS = visual analogue scale; SD=Standard Deviation. | |||||
| Drug Liking Bipolar scale (0=maximum negative response, 50=neutral response, 100=maximum positive response) (Emax) | Mean (SD) | 73.9 (15.10) | 73.3 (14.93) | 86.40 (12.01) | 55.8 (9.94) |
| Median (Range) | 73.5 (50-100) | 73.5 (50-100) | 88.5 (52-100) | 50.0 (50-86) | |
| Take Drug Again (Emax) | Mean (SD) | 77.98 (21.07) | 77.85 (18.30) | 87.69 (12.90) | 50.79 (21.41) |
| Median (Range) | 80.5 (1-100) | 81.5 (50-100) | 90.5 (50-100) | 50.0 (0-100) | |
A prior, similarly-designed study was also conducted to evaluate the oral abuse potential of chewed XTAMPZA ER. Although the oral administration of chewed and intact XTAMPZA ER in the fasted state was associated with statistically lower mean Drug Liking scores compared with crushed immediate-release oxycodone, the results for Take Drug Again showed small differences that were not statistically significant.
Nasal Abuse Potential Study:
In a randomized, double-blind, active- and placebo-controlled, single-dose, four-way crossover pharmacodynamic study, 39 recreational opioid users with a history of intranasal drug abuse received nasally administered active and placebo drug treatment. The four treatment arms were crushed XTAMPZA ER 36 mg dosed intranasally; intact XTAMPZA ER 36 mg dosed orally; crushed immediate-release oxycodone HCl 40 mg (equivalent to 36 mg of XTAMPZA ER) dosed intranasally; and placebo. Data for intranasal XTAMPZA ER and crushed immediate-release oxycodone are described below.
Thirty-six subjects completed the study. Intranasal administration of crushed XTAMPZA ER was associated with statistically lower mean Drug Liking and Take Drug Again scores compared with crushed immediate-release oxycodone (summarized in 7).
| XTAMPZA ER Intranasal | Crushed IR Oxycodone Intranasal | Placebo | ||
|---|---|---|---|---|
| Emax = maximum (peak) effect; ER = extended-release; IR = immediate-release; VAS = visual analogue scale; SD=Standard Deviation. | ||||
| Drug Liking Bipolar scale (0=maximum negative response, 50=neutral response, 100=maximum positive response). (Emax) | Mean (SD) | 61.81 (15.64) | 82.72 (10.95) | 54.5 (11.77) |
| Median (Range) | 59.5 (16-94) | 84 (60-100) | 51 (28-93) | |
| Take Drug Again | Mean (SD) | 47.67 (27.84) | 71.36 (23.49) | 45.92 (17.50) |
| Median (Range) | 50 (0-100) | 78.5 (18-100) | 50 (0-97) | |
Figure 1 demonstrates a comparison of Drug Liking for intranasal administration of crushed XTAMPZA ER compared to crushed immediate-release oxycodone in subjects who received both treatments (N=36). The Y-axis represents the percent of subjects attaining a percent reduction in drug liking for XTAMPZA ER vs. immediate-release oxycodone greater than or equal to the value on the X-axis. Approximately 92% (n = 33) of subjects had some reduction in drug liking with XTAMPZA ER relative to crushed immediate-release oxycodone HCl. Approximately 78% (n = 28) of subjects had a reduction of at least 30% in drug liking with XTAMPZA ER compared to crushed immediate-release oxycodone HCl, and approximately 58% (n = 21) of subjects had a reduction of at least 50% in drug liking with XTAMPZA ER compared to crushed immediate-release oxycodone HCl.
Figure 1: Percent Reduction Profiles for Emax of Drug Liking VAS for Crushed XTAMPZA ER vs. Crushed Immediate-release Oxycodone, N=36 Following Intranasal Administration
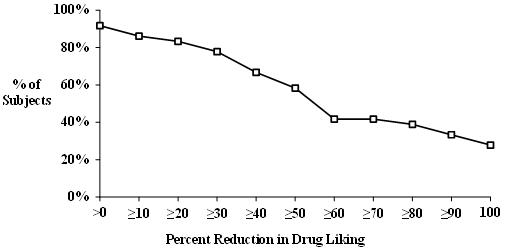
Figure 1 (Xtampza 01)
Summary
The in vitro data demonstrate that XTAMPZA ER has physicochemical properties expected to make abuse by injection difficult. The data from pharmacokinetic and human abuse potential studies, along with support from the in vitro data, also indicate that XTAMPZA ER has physicochemical properties that are expected to reduce abuse via the oral and intranasal routes. The data from the oral pharmacokinetic studies of crushed or chewed XTAMPZA ER demonstrated a lack of dose dumping with no increase in oxycodone levels compared to intact XTAMPZA ER.
However, abuse of XTAMPZA ER by injection and by the oral and nasal routes of administration is still possible.
Additional data, including epidemiological data, when available, may provide further information on the impact of the current formulation of XTAMPZA ER on the abuse liability of the drug. Accordingly, this section may be updated in the future as appropriate.
XTAMPZA ER contains oxycodone, an opioid agonist and Schedule II controlled substance with an abuse liability similar to other opioid agonists, legal or illicit, including fentanyl, hydromorphone, methadone, morphine, and oxymorphone. XTAMPZA ER can be abused and is subject to misuse, addiction, and criminal diversion [see Warnings and Precautions (5.1) and Drug Abuse and Dependence (9.3)].
Clinical Presentation
Acute overdosage with oxycodone can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen due to severe hypoxia in overdose situations [see Clinical Pharmacology (12.2)]. Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Treatment of Overdose
In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation if needed. Employ other supportive measures (including oxygen, vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support measures.
For clinically significant respiratory or circulatory depression secondary to oxycodone overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene.
Because the duration of reversal would be expected to be less than the duration of action of oxycodone in XTAMPZA ER, carefully monitor the patient until spontaneous respiration is reliably reestablished. XTAMPZA ER will continue to release oxycodone and add to the oxycodone load for 24 to 48 hours or longer following ingestion necessitating prolonged monitoring. If the response to opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed in the product's prescribing information.
In an individual physically dependent on opioids, administration of the usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the reversal agent should be begun with care and by titration with smaller than usual doses of the reversal agent.
Effects on the Central Nervous System
Oxycodone produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in CO2 tension and to electrical stimulation.
Oxycodone causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations [see Overdosage (10)].
Effects on the Gastrointestinal Tract and Other Smooth Muscle
Oxycodone causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects on the Cardiovascular System
Oxycodone produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes and sweating and/or orthostatic hypotension.
Effects on the Endocrine System
Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse Reactions (6.2)]. They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon.
Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions (6.2)].
Effects on the Immune System
Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration–Efficacy Relationships
Studies in normal volunteers and patients reveal predictable relationships between oxycodone dosage and plasma oxycodone concentrations, as well as between concentration and certain expected opioid effects, such as pupillary constriction, sedation, overall subjective "drug effect," analgesia, and feelings of relaxation.
The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with opioid agonists. The minimum effective analgesic concentration of oxycodone for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome, and/or the development of analgesic tolerance [see Dosage and Administration (2.1, 2.5)].
Concentration–Adverse Reaction Relationships
There is a relationship between increasing oxycodone plasma concentration and increasing frequency of dose-related opioid adverse reactions such as nausea, vomiting, CNS effects, and respiratory depression. In opioid-tolerant patients, the situation may be altered by the development of tolerance to opioid-related adverse reactions.
Absorption
XTAMPZA ER is not bioequivalent to oxycodone extended-release tablets. In the fasted state, both peak serum concentration (Cmax) and extent of absorption (AUC) are lower for XTAMPZA ER, and in the fed state, Cmax is lower, but AUC is similar.
Compared to immediate-release oxycodone solution dosed under fasted conditions the mean Cmax of oxycodone from XTAMPZA ER is lower (73% and 43% lower for fasted and fed administration, respectively) and the median time to peak plasma concentration (Tmax) is approximately 3 hours longer. The extent of absorption of oxycodone from XTAMPZA ER is less than from immediate-release oxycodone oral solution in the fasted state (relative bioavailability of 75%), but comparable in the fed state (relatively bioavailability of 114%).
The peak plasma concentration of oxycodone from XTAMPZA ER occurs approximately 4.5 hours after fed dose administration. Upon repeated dosing with XTAMPZA ER in healthy subjects in pharmacokinetic studies, steady-state levels were achieved within 24-36 hours. Oxycodone is extensively metabolized and eliminated primarily in the urine as both conjugated and unconjugated metabolites. The apparent elimination half-life (t½) of oxycodone following the administration of XTAMPZA ER when dosed in the fed state was 5.6 hours compared to 3.2 hours for immediate-release oxycodone.
Food Effects
The oral bioavailability of oxycodone from XTAMPZA ER is greater when taken with food than when taken in the fasted state. The oral bioavailability is dependent on the food consumed and is greatest following a high-fat and high-calorie meal with an increase in Cmax of 100-150% and AUC of 50-60% compared to the fasted state. Following a medium-fat medium-calorie meal, the Cmax increased by 84% and AUC by 28% compared to the fasted state. Following a low-fat low-calorie meal, Cmax was 19% higher and AUC was comparable, relative to the fasted state.
Pharmacokinetic Profile of XTAMPZA ER Intact and Sprinkled
Plasma concentration over time has been measured following administration of XTAMPZA ER capsule contents intact with food and sprinkled. The pharmacokinetic profile for the capsule contents sprinkled was equivalent to intact capsule administration (Table 8).
| Treatment | Cmax (ng/mL) | Tmax (hr) | AUC0-INF (hr∙ng/mL) |
|---|---|---|---|
| Values shown for Cmax and AUC0-INF are mean (standard deviation); values shown for Tmax are median (minimum – maximum). | |||
| Intact XTAMPZA ER Capsules (fed) | 55.3 (13.6) | 4.5 (1.5 – 9.0) | 540 (143) |
| Sprinkled XTAMPZA ER Capsule Contents (fed) | 48.1 (12.0) | 4.5 (2.5 – 9.0) | 528 (130) |
Distribution
Following intravenous administration, the steady-state volume of distribution (Vss) for oxycodone was 2.6 L/kg. Oxycodone binding to plasma protein at 37°C and a pH of 7.4 was about 45%. Once absorbed, oxycodone is distributed to skeletal muscle, liver, intestinal tract, lungs, spleen, and brain. Oxycodone has been found in breast milk [see Use in Specific Populations (8.2)].
Elimination
In humans, oxycodone is extensively metabolized. Oxycodone and its metabolites are excreted primarily via the kidney.
Metabolism
Oxycodone is extensively metabolized by multiple metabolic pathways to produce noroxycodone, oxymorphone, and noroxymorphone, which are subsequently glucuronidated. Noroxycodone and noroxymorphone are the major circulating metabolites. CYP3A mediated N-demethylation to noroxycodone is the primary metabolic pathway of oxycodone with a lower contribution from CYP2D6-mediated O-demethylation to oxymorphone. Therefore, the formation of these and related metabolites can, in theory, be affected by other drugs [see Drug Interactions (7)].
Noroxycodone exhibits very weak anti-nociceptive potency compared to oxycodone; however, it undergoes further oxidation to produce noroxymorphone, which is active at opioid receptors. Although noroxymorphone is an active metabolite and present at relatively high concentrations in circulation, it does not appear to cross the blood-brain barrier to a significant extent. Oxymorphone is present in the plasma only at low concentrations and undergoes further metabolism to form its glucuronide and noroxymorphone. Oxymorphone has been shown to be active and to possess analgesic activity but its contribution to analgesia following oxycodone administration is thought to be clinically insignificant. Other metabolites (α- and ß-oxycodol, noroxycodol, and oxymorphol) may be present at very low concentrations and demonstrate limited penetration into the brain as compared to oxycodone. The enzymes responsible for keto-reduction and glucuronidation pathways in oxycodone metabolism have not been established.
Excretion
Oxycodone and its metabolites are excreted primarily via the kidney. The amounts measured in the urine have been reported as follows: free and conjugated oxycodone 8.9%, free noroxycodone 23%, free oxymorphone less than 1%, conjugated oxymorphone 10%, free and conjugated noroxymorphone 14%, reduced free and conjugated metabolites up to 18%. The total plasma clearance was approximately 1.4 L/min in adults.
Specific Populations
Age: Geriatric Population
The plasma concentrations of oxycodone are nominally affected by age, being 15% greater in elderly as compared to young subjects (age 21-45).
Sex
Across individual pharmacokinetic studies, oxycodone plasma exposures for female subjects were up to 20% higher than for male subjects, even after considering differences in body weight or BMI. The reason for this difference is unknown [see Use in Specific Populations (8)].
Renal Impairment
Data from a pharmacokinetic study involving 13 patients with mild to severe renal dysfunction (creatinine clearance <60 mL/min) showed peak plasma oxycodone and noroxycodone concentrations 50% and 20% higher, respectively, and AUC values for oxycodone, noroxycodone, and oxymorphone 60%, 50%, and 40% higher than normal subjects, respectively. This was accompanied by an increase in sedation, but not by differences in respiratory rate, pupillary constriction, or several other measures of drug effect. There was an increase in mean elimination t½ for oxycodone of 1 hour.
Hepatic Impairment
Data from a study involving 24 patients with mild to moderate hepatic dysfunction show peak plasma oxycodone and noroxycodone concentrations 50% and 20% higher, respectively, than healthy subjects. AUC values are 95% and 65% higher, respectively. Oxymorphone peak plasma concentrations and AUC values are lower by 30% and 40%. The mean elimination t½ for oxycodone increased by 2.3 hours.
Drug Interaction Studies
CYP3A4 Inhibitors
CYP3A4 is the major enzyme involved in noroxycodone formation. Co-administration of a 10 mg single dose of oxycodone extended –release tablet and the CYP3A4 inhibitor ketoconazole (200 mg BID) increased oxycodone AUC and Cmax by 170% and 100%, respectively [see Drug Interactions (7)].
CYP3A4 Inducers
A published study showed that the co-administration of rifampin, a drug metabolizing enzyme inducer, decreased oxycodone AUC and Cmax values by 86% and 63%, respectively [see Drug Interactions (7)].
CYP2D6 Inhibitors
Oxycodone is metabolized in part to oxymorphone via CYP2D6. While this pathway may be blocked by a variety of drugs such as certain cardiovascular drugs (e.g., quinidine) and antidepressants (e.g., fluoxetine), such blockade is not expected to be of clinical significance for XTAMPZA ER [see Drug Interactions (7)].
Carcinogenesis
Long term studies in animals to evaluate the carcinogenic potential of oxycodone have not been conducted.
Mutagenesis
Oxycodone was genotoxic in the in vitro mouse lymphoma assay. Oxycodone was negative when tested at appropriate concentrations in the in vitro chromosomal aberration assay, the in vitro bacterial reverse mutation assay (Ames test), and the in vivo bone marrow micronucleus assay in mice.
Impairment of Fertility
In a study of reproductive performance, rats were administered a once daily gavage dose of the vehicle or oxycodone hydrochloride (0.5, 2, and 8 mg/kg). Male rats were dosed for 28 days before cohabitation with females, during the cohabitation and until necropsy (2-3 weeks post-cohabitation). Females were dosed for 14 days before cohabitation with males, during cohabitation and up to Gestation Day 6. Oxycodone HCl did not affect reproductive function in male or female rats at any dose tested (≤8 mg/kg/day), up to 1.3 times a human dose of 60 mg/day.
Storage and Disposal
Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store XTAMPZA ER securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home. Inform patients that leaving XTAMPZA ER unsecured can pose a deadly risk to others in the home [see Warnings and Precautions (5.1, 5.2), Drug Abuse and Dependence (9.2)].
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Expired, unwanted, or unused XTAMPZA ER should be disposed of by flushing the unused medication down the toilet if a drug take-back option is not readily available. Inform patients that they can visit www.fda.gov/drugdisposal for a complete list of medicines recommended for disposal by flushing, as well as additional information on disposal of unused medicines.
Addiction, Abuse, and Misuse
Inform patients that the use of XTAMPZA ER, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions (5.1)]. Instruct patients not to share XTAMPZA ER with others and to take steps to protect XTAMPZA ER from theft or misuse.
Life-Threatening Respiratory Depression
Inform patients of the risk of life-threatening respiratory depression including information that the risk is greatest when starting XTAMPZA ER or when the dosage is increased, and that it can occur even at recommended dosages.
Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Warnings and Precautions (5.2)].
Accidental Ingestion
Inform patients that accidental ingestion, especially by children, may result in respiratory depression or death [see Warnings and Precautions (5.2)].
Interactions with Benzodiazepines and other CNS Depressants
Inform patients and caregivers that potentially fatal additive effects may occur if XTAMPZA ER is used with benzodiazepines or other CNS depressants, including alcohol (e.g., non-benzodiazepine sedative/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids), and not to use these concomitantly unless supervised by a healthcare provider [see Warnings and Precautions (5.3), Drug Interactions (7)].
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose
Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene). Discuss the importance of having access to an opioid overdose reversal agent, especially if the patient has risk factors for overdose (e.g., concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose) or if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose.
Discuss with the patient the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter, or as part of a community-based program) [see Dosage and Administration (2.2), Warnings and Precautions (5.3)].
Educate patients and caregivers on how to recognize the signs and symptoms of an overdose.
Explain to patients and caregivers that effects of opioid overdose reversal agents like naloxone and nalmefene are temporary, and that they must call 911 or get emergency medical help right away in cases of known or suspected opioid overdose, even if an opioid overdose reversal agent is administered [see Overdosage (10)].
Advise patients and caregivers:
Hyperalgesia and Allodynia
Inform patients and caregivers not to increase opioid dosage without first consulting a clinician. Advise patients to seek medical attention if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see Warnings and Precautions (5.7), Adverse Reactions (6.2)].
Serotonin Syndrome
Inform patients that XTAMPZA ER could cause a rare but potentially life-threatening condition called serotonin syndrome resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop. Instruct patients to inform their physicians if they are taking, or plan to take serotonergic medications. [see Drug Interactions (7)].
MAOI Interaction
Inform patients to avoid taking XTAMPZA ER while using any drugs that inhibit monoamine oxidase. Patients should not start MAOIs while taking XTAMPZA ER [see Drug Interactions (7)].
Food Effect
Because food has an effect on absorption of oxycodone from XTAMPZA ER, each dose of XTAMPZA ER should be taken with food in order to ensure that appropriate plasma levels are consistently achieved. Instruct patients to take XTAMPZA ER with approximately the same amount of food regardless of whether they swallow the capsule whole or sprinkle on soft food or into a cup and then administer directly into the mouth.
XTAMPZA ER may be taken as intact capsules or, alternately, may be administered as a sprinkle on soft foods or sprinkled into a cup and administered directly into the mouth, or through a nasogastric or gastric feeding tube [see Dosage and Administration (2.1,2.7)].
Important Administration Instructions [see Dosage and Administration (2.1, 2.6, 2.7), Warnings and Precautions (5.2)]
Instruct patients how to properly take XTAMPZA ER, including the following:
Important Discontinuation Instructions
In order to avoid developing withdrawal symptoms, instruct patients not to discontinue XTAMPZA ER without first discussing a tapering plan with the prescriber [see Dosage and Administration (2.6)]
Driving or Operating Heavy Machinery
Inform patients that XTAMPZA ER may impair the ability to perform potentially hazardous activities such as driving a car or operating heavy machinery. Advise patients not to perform such tasks until they know how they will react to the medication [see Warnings and Precautions (5.15)].
Constipation
Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention.
Adrenal Insufficiency
Inform patients that XTAMPZA ER could cause adrenal insufficiency, a potentially life-threatening condition. Adrenal insufficiency may present with non-specific symptoms and signs such as nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. Advise patients to seek medical attention if they experience a constellation of these symptoms [see Warnings and Precautions (5.9)].
Hypotension
Inform patients that XTAMPZA ER may cause orthostatic hypotension and syncope. Instruct patients how to recognize symptoms of low blood pressure and how to reduce the risk of serious consequences should hypotension occur (e.g., sit or lie down, carefully rise from a sitting or lying position) [see Warnings and Precautions (5.10)].
Anaphylaxis
Inform patients that anaphylaxis has been reported with ingredients contained in XTAMPZA ER. Advise patients how to recognize such a reaction and when to seek medical attention [see Contraindications (4), Adverse Reactions (6)].
Pregnancy
Neonatal Opioid Withdrawal Syndrome
Inform female patients of reproductive potential that use of XTAMPZA ER for an extended period of time during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated [see Warnings and Precautions (5.4), Use in Specific Populations (8.1)].
Embryofetal Toxicity
Advise females of reproductive potential that XTAMPZA ER can cause fetal harm and to inform their healthcare provider of a known or suspected pregnancy [see Use in Specific Populations (8.1)].
Lactation
Advise patients that breastfeeding is not recommended during treatment with XTAMPZA ER [see Use in Specific Populations (8.2)].
Infertility
Inform patients that use of opioids for an extended period of time may cause reduced fertility. It is not known whether these effects on fertility are reversible [see Adverse Reactions (6.2)].
Healthcare professionals can telephone Collegium Pharmaceutical's Medical Affairs Department (1-855-331-5615) for information on this product.
Manufactured by: Patheon Pharmaceuticals, Cincinnati, OH 45237
U.S. Patent Nos. 7,399,488; 7,771,707; 8,449,909; 8,557,291; 8,758,813; 8,840,928; 9,044,398; 9,248,195; 9,592,200; 9,682,075; 9,737,530; 9,763,883; 9,968,598; 10,004,729; 10,188,644; 10,525,052; 10,525,053; 10,646,485; and 10,668,060