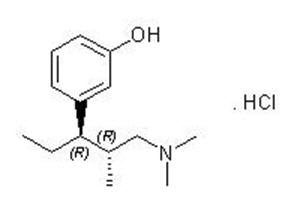
Other
Addiction, Abuse, and Misuse
Because the use of NUCYNTA ER exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death assess, each patient's risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions [see Warnings and Precautions (5.1)].
Life-Threatening Respiratory Depression
Serious, life-threatening, or fatal respiratory depression may occur with use of NUCYNTA ER, especially during initiation or following a dosage increase. To reduce the risk of respiratory depression, proper dosing and titration of NUCYNTA ER are essential. Instruct patients to swallow NUCYNTA ER tablets whole; crushing, chewing, or dissolving NUCYNTA ER tablets can cause rapid release and absorption of a potentially fatal dose of tapentadol [see Warnings and Precautions (5.2)].
Accidental Ingestion
Accidental ingestion of even one dose of NUCYNTA ER, especially by children, can result in a fatal overdose of tapentadol [see Warnings and Precautions (5.2)].
Interaction with Alcohol
Instruct patients not to consume alcoholic beverages or use prescription or nonprescription products that contain alcohol while taking NUCYNTA ER. The co-ingestion of alcohol with NUCYNTA ER may result in increased plasma tapentadol levels and a potentially fatal overdose of tapentadol [see Warnings and Precautions (5.3)].
Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants
Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of NUCYNTA ER and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate [see Warnings and Precautions (5.3), Drug Interactions (7)].
Neonatal Opioid Withdrawal Syndrome (NOWS)
Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery [see Warnings and Precautions (5.4)].
Opioid Analgesic Risk Evaluation and Mitigation Strategy (REMS)
Healthcare providers are strongly encouraged to complete a REMS-compliant education program and to counsel patients and caregivers on serious risks, safe use, and the importance of reading the Medication Guide with each prescription [see Warnings and Precautions (5.5)].
Limitations of Use
- Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration and persist over the course of therapy [see Warnings and Precautions (5.1)], reserve opioid analgesics, including NUCYNTA ER, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
- NUCYNTA ER is not indicated as an as-needed (prn) analgesic.
- approximately 1% to 6% of participants across the two cohorts newly met criteria for addiction, as assessed with two validated interview-based measures of moderate-to-severe opioid use disorder based on Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) criteria, and
- approximately 9% and 22% of participants across the two cohorts newly met criteria for prescription opioid abuse and misuse [defined in Drug Abuse and Dependence (9.2)], respectively, as measured with a validated self-reported instrument.
- how to treat with the overdose reversal agent in the event of an opioid overdose.
- to tell family and friends about their opioid overdose reversal agent, and to keep it in a place where family and friends can access it in an emergency.
- to read the Patient Information (or other educational material) that will come with their opioid overdose reversal agent. Emphasize the importance of doing this before an opioid emergency happens, so the patient and caregiver will know what to do.
- Using NUCYNTA ER exactly as prescribed to reduce the risk of life-threatening adverse reactions (e.g., respiratory depression) [see Dosage and Administration (2)]
- Swallowing NUCYNTA ER tablets whole [see Dosage and Administration (2.1)]
- To take each tablet with enough water to ensure complete swallowing immediately after placing in mouth [see Dosage and Administration (2.1)]
- Not cutting, crushing, chewing, or dissolving the tablets [see Dosage and Administration (2.1)]
Use of NUCYNTA ER in Patients who are not Opioid Tolerant
The starting dose for patients who are not opioid tolerant is NUCYNTA ER 50 mg orally twice daily (approximately every 12 hours). Use of higher starting doses in patients who are not opioid tolerant may cause fatal respiratory depression.
Conversion from Tapentadol Immediate-Release (IR) products to NUCYNTA ER
Patients can be converted from tapentadol IR to NUCYNTA ER using the equivalent total daily dose of tapentadol IR and dividing it into two equal doses of NUCYNTA ER separated by approximately 12-hour intervals. As an example, a patient receiving 50 mg of tapentadol IR four times per day (200 mg/day) may be converted to 100 mg NUCYNTA ER twice a day.
Conversion from Methadone to NUCYNTA ER
Frequent evaluation is of particular importance when converting from methadone to other opioid agonists. The ratio between methadone and other opioid agonists may vary widely as a function of previous dose exposure. Methadone has a long half-life and can accumulate in the plasma.
Conversion from Other Opioid Analgesics to NUCYNTA ER
When NUCYNTA ER therapy is initiated, discontinue all other opioid analgesics other than those used on an as needed basis for breakthrough pain when appropriate. There are no established conversion ratios for conversion from other opioids to NUCYNTA ER defined by clinical trials. Initiate dosing using NUCYNTA ER 50 mg orally every 12 hours.
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose
Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene). Discuss the importance of having access to an opioid overdose reversal agent, especially if the patient has risk factors for overdose (e.g., concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose) or if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose. The presence of risk factors for overdose should not prevent the management of pain in any patient [see Warnings and Precautions (5.1, 5.3)].
Discuss the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter, or as part of a community-based program).
There are important differences among the opioid overdose reversal agents, such as route of administration, product strength, approved patient age range, and pharmacokinetics. Be familiar with these differences, as outlined in the approved labeling for those products, prior to recommending or prescribing such an agent.
Educate patients and caregivers on how to recognize respiratory depression, and how to use an opioid overdose reversal agent for the emergency treatment of opioid overdose. Emphasize the importance of calling 911 or getting emergency medical help, even if an opioid overdose reversal agent is administered [see Dosage and Administration (2.2), Warnings and Precautions (5.1, 5.3), Overdosage (10)].
Patients with Chronic Pulmonary Disease: NUCYNTA ER treated patients with significant chronic obstructive pulmonary disease or cor pulmonale, and those with a substantially decreased respiratory reserve, hypoxia, hypercapnia, or pre-existing respiratory depression are at increased risk of decreased respiratory drive including apnea, even at recommended dosages of NUCYNTA ER [see Warnings and Precautions (5.2)].
Elderly, Cachectic, or Debilitated Patients: Life-threatening respiratory depression is more likely to occur in elderly, cachectic, or debilitated patients because they may have altered pharmacokinetics or altered clearance compared to younger, healthier patients [see Warnings and Precautions (5.2)].
Regularly evaluate patients, particularly when initiating and titrating NUCYNTA ER and when NUCYNTA ER is given concomitantly with other drugs that depress respiration [see Warnings and Precautions (5.2), Drug Interactions (7)]. Alternatively, consider the use of non-opioid analgesics in these patients.
Commonly-Observed Adverse Reactions in Clinical Studies with NUCYNTA ER in Patients with Chronic Pain due to Low Back Pain or Osteoarthritis
The safety data described in Table 1 below are based on three pooled, randomized, double-blind, placebo-controlled, parallel group, 15-week studies of NUCYNTA ER (dosed 100 to 250 mg BID after a 50 mg BID starting dose) in patients with chronic pain due to low back pain (LBP) and osteoarthritis (OA). These trials included 980 NUCYNTA ER-treated patients and 993 placebo-treated patients. The mean age was 57 years old; 63% were female and 37% were male; 83% were White, 10% were Black, and 5% were Hispanic. The most common adverse reactions (reported by ≥10% in any NUCYNTA ER dose group) were: nausea, constipation, dizziness, headache, and somnolence.
The most common reasons for discontinuation due to adverse reactions in eight Phase 2/3 pooled studies reported by ≥1% in any NUCYNTA ER dose group for NUCYNTA ER- and placebo-treated patients were nausea (4% vs. 1%), dizziness (3% vs. <1%), vomiting (3% vs. <1%), somnolence (2% vs. <1%), constipation (1% vs. <1%), headache (1% vs. <1%), and fatigue (1% vs. <1%), respectively.
| NUCYNTA ER 50 to 250 mg BID NUCYNTA ER dosed between 100 and 250 mg BID after a starting dose of 50 mg BID (n=980) | Placebo (n=993) | |
|---|---|---|
| Nausea | 21% | 7% |
| Constipation | 17% | 7% |
| Dizziness | 17% | 6% |
| Headache | 15% | 13% |
| Somnolence | 12% | 4% |
| Fatigue | 9% | 4% |
| Vomiting | 8% | 3% |
| Dry mouth | 7% | 2% |
| Hyperhidrosis | 5% | <1% |
| Pruritus | 5% | 2% |
| Insomnia | 4% | 2% |
| Dyspepsia | 3% | 2% |
| Lethargy | 2% | <1% |
| Asthenia | 2% | <1% |
| Anxiety | 2% | 1% |
| Decreased appetite | 2% | <1% |
| Vertigo | 2% | <1% |
| Hot flush | 2% | <1% |
| Disturbance in attention | 1% | <1% |
| Tremor | 1% | <1% |
| Chills | 1% | 0% |
| Abnormal dreams | 1% | <1% |
| Depression | 1% | <1% |
| Vision blurred | 1% | <1% |
| Erectile dysfunction | 1% | <1% |
Commonly-Observed Adverse Reactions in Clinical Studies with NUCYNTA ER in Patients with Neuropathic Pain Associated with Diabetic Peripheral Neuropathy
The types of adverse reactions seen in the studies of patients with painful diabetic peripheral neuropathy (DPN) were similar to what was seen in the low back pain and osteoarthritis trials. The safety data described in Table 2 below are based on two pooled, randomized withdrawal, double-blind, placebo-controlled, 12-week studies of NUCYNTA ER (dosed 100 to 250 mg BID) in patients with neuropathic pain associated with diabetic peripheral neuropathy. These trials included 1040 NUCYNTA ER-treated patients and 343 placebo- treated patients. The mean age was 60 years old; 40% were female and 60% were male; 76% were White, 12% were Black, and 12% were "Other". The most commonly reported ADRs (incidence ≥10% in NUCYNTA ER-treated subjects) were: nausea, constipation, vomiting, dizziness, somnolence, and headache.
Table 2 lists the common adverse reactions reported in 1% or more of NUCYNTA ER-treated patients and greater than placebo-treated patients with neuropathic pain associated with diabetic peripheral neuropathy in the two pooled studies.
| NUCYNTA ER 50 to 250 mg BID NUCYNTA ER dosed between 100 and 250 mg BID after a starting dose of 50 mg BID. It includes ADR reported in the open-label titration period for all subjects and in the double-blind maintenance period for the subjects who were randomized to NUCYNTA ER. (n=1040) | Placebo It includes ADR reported in the double-blind maintenance period for the subjects who were randomized to placebo after receiving NUCYNTA ER during the open-label titration period. (n=343) | |
|---|---|---|
| Nausea | 27% | 8% |
| Dizziness | 18% | 2% |
| Somnolence | 14% | <1% |
| Constipation | 13% | <1% |
| Vomiting | 12% | 3% |
| Headache | 10% | 5% |
| Fatigue | 9% | <1% |
| Pruritus | 8% | 0% |
| Dry mouth | 7% | <1% |
| Diarrhea | 7% | 5% |
| Decreased appetite | 6% | <1% |
| Anxiety | 5% | 4% |
| Insomnia | 4% | 3% |
| Hyperhidrosis | 3% | 2% |
| Hot flush | 3% | 2% |
| Tremor Tremor was observed in 3.4% of NUCYNTA ER-treated subjects vs. 3.2% in placebo group, chills- in 1.3% vs.1.2% in placebo, and feeling cold- in 1.3% vs.1.2% in placebo. | 3% | 3% |
| Abnormal dreams | 2% | 0% |
| Lethargy | 2% | 0% |
| Asthenia | 2% | <1% |
| Irritability | 2% | 1% |
| Dyspnea | 1% | 0% |
| Nervousness | 1% | 0% |
| Sedation | 1% | 0% |
| Vision blurred | 1% | 0% |
| Pruritus generalized | 1% | 0% |
| Vertigo | 1% | <1% |
| Abdominal discomfort | 1% | <1% |
| Hypotension | 1% | <1% |
| Dyspepsia | 1% | <1% |
| Hypoesthesia | 1% | <1% |
| Depression | 1% | <1% |
| Rash | 1% | <1% |
| Chills | 1% | 1% |
| Feeling cold | 1% | 1% |
| Drug withdrawal syndrome | 1% | <1% |
Other Adverse Reactions Observed During the Premarketing Evaluation of NUCYNTA ER
The following additional adverse drug reactions occurred in less than 1% of NUCYNTA ER-treated patients in ten Phase 2/3 clinical studies:
Nervous system disorders: paresthesia, balance disorder, syncope, memory impairment, mental impairment, depressed level of consciousness, dysarthria, presyncope, coordination abnormal
Gastrointestinal disorders: impaired gastric emptying
General disorders and administration site conditions: feeling abnormal, feeling drunk
Psychiatric disorders: perception disturbances, disorientation, confusional state, agitation, euphoric mood, drug dependence, thinking abnormal, nightmare
Skin and subcutaneous tissue disorders: urticaria
Metabolism and nutrition disorders: weight decreased
Cardiac disorders: heart rate increased, palpitations, heart rate decreased, left bundle branch block
Vascular disorder: blood pressure decreased
Respiratory, thoracic and mediastinal disorders: respiratory depression
Renal and urinary disorders: urinary hesitation, pollakiuria
Reproductive system and breast disorders: sexual dysfunction
Eye disorders: visual disturbance
Immune system disorders: drug hypersensitivity
Adverse Reactions from Observational Studies
A prospective, observational cohort study estimated the risks of addiction, abuse, and misuse in patients initiating long-term use of Schedule II opioid analgesics between 2017 and 2021. Study participants included in one or more analyses had been enrolled in selected insurance plans or health systems for at least one year, were free of at least one outcome at baseline, completed a minimum number of follow-up assessments, and either: 1) filled multiple extended-release/long-acting opioid analgesic prescriptions during a 90-day period (n=978); or 2) filled any Schedule II opioid analgesic prescriptions covering at least 70 of 90 days (n=1,244). Those included also had no dispensing of the qualifying opioids in the previous 6 months.
Over 12 months:
A retrospective, observational cohort study estimated the risk of opioid involved overdose or opioid overdose-related death in patients with new long-term use of Schedule II opioid analgesics from 2006 through 2016 (n=220,249). Included patients had been enrolled in either one of two commercial insurance programs, one managed care program, or one Medicaid program for at least 9 months. New long-term use was defined as having Schedule II opioid analgesic prescriptions covering at least 70 days' supply over the 3 months prior to study entry and none during the preceding 6 months. Patients were excluded if they had an opioid-involved overdose in the 9 months prior to study entry. Overdose was measured using a validated medical code-based algorithm with linkage to the National Death Index database. The 5-year cumulative incidence estimates for opioid-involved overdose or opioid overdose-related death ranged from approximately 1.5% to 4% across study sites, counting only the first event during follow-up. Approximately 17% of first opioid overdoses observed over the entire study period (5-11 years, depending on the study site) were fatal. Higher baseline opioid dose was the strongest and most consistent predictor of opioid-involved overdose or opioid overdose-related death. Study exclusion criteria may have selected patients at lower risk of overdose, and substantial loss to follow-up (approximately 80%) also may have biased estimates.
The risk estimates from the studies described above may not be generalizable to all patients receiving opioid analgesics, such as those with exposures shorter or longer than the duration evaluated in the studies.
Risk Summary
Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions (5.4)]. Available data with NUCYNTA ER are insufficient to inform a drug- associated risk for major birth defects and miscarriage or adverse maternal outcomes. In animal reproduction studies, embryofetal mortality and structural malformations were observed with subcutaneous administration of tapentadol during organogenesis to rabbits and delays in skeletal maturation were observed in rats at exposures equivalent to and less than the maximum recommended human dose (MRHD), respectively. When administered to pregnant rats during organogenesis and through lactation, increased pup mortality was noted following oral tapentadol exposures to doses equivalent to the MRHD [see Data]. Based on animal data, advise pregnant women of the potential risk to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse reaction. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations
Fetal/neonatal adverse reactions
Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth. Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions (5.4)].
Labor or Delivery
Opioids cross the placenta and may produce respiratory depression and psychophysiological effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene must be available for reversal of opioid-induced respiratory depression in the neonate. NUCYNTA ER is not recommended for use in pregnant women during and immediately prior to labor, when use of shorter-acting analgesics or other analgesic techniques are more appropriate. Opioid analgesics, including NUCYNTA ER, can prolong labor through actions that temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilatation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Data
Animal Data
Tapentadol HCl was evaluated for teratogenic effects in pregnant rats and rabbits following intravenous and subcutaneous exposure during the period of embryofetal organogenesis. When tapentadol was administered twice daily by the subcutaneous route in rats at dose levels of 10, 20, or 40 mg/kg/day [producing up to 1.36 times the plasma exposure at the maximum recommended human dose (MRHD) of 500 mg/day for NUCYNTA ER based on an area under the time-curve (AUC) comparison], no teratogenic effects were observed. Evidence of embryofetal toxicity included transient delays in skeletal maturation (i.e., reduced ossification) at the 40 mg/kg/day dose which was associated with significant maternal toxicity. Administration of tapentadol HCl in rabbits at doses of 4, 10, or 24 mg/kg/day by subcutaneous injection [producing 0.3, 0.8, and 2.5 times the plasma exposure at the MRHD based on an AUC comparison, respectively] revealed embryofetal toxicity at doses ≥10 mg/kg/day. Findings included reduced fetal viability, skeletal delays and other variations. In addition, there were multiple malformations including gastroschisis/thoracogastroschisis, amelia/phocomelia, and cleft palate at doses ≥10 mg/kg/day and above, and ablepharia, encephalopathy, and spina bifida at the high dose of 24 mg/kg/day.
Embryofetal toxicity, including malformations, may be secondary to the significant maternal toxicity observed in the study.
In a study of pre- and postnatal development in rats, oral administration of tapentadol at doses of 20, 50, 150, or 300 mg/kg/day to pregnant and lactating rats during the late gestation and early postnatal period [resulting in up to 2.28 times the plasma exposure at the MRHD on an AUC basis] did not influence physical or reflex development, the outcome of neurobehavioral tests or reproductive parameters. At maternal tapentadol doses ≥150 mg/kg/day, a dose-related increase in pup mortality was observed to postnatal Day 4. Treatment-related developmental delay was observed in the dead pups, including incomplete ossification. In addition, significant reductions in pup body weights and body weight gains at doses associated with maternal toxicity (150 mg/kg/day and above) were seen throughout lactation.
Risk Summary
There is insufficient/limited information on the excretion of tapentadol in human or animal breast milk. Physicochemical and available pharmacodynamic/toxicological data on tapentadol point to excretion in breast milk and risk to the breastfeeding child cannot be excluded.
Because of the potential for serious adverse reactions including excess sedation and respiratory depression in a breastfed infant, advise patients that breast feeding is not recommended during treatment with NUCYNTA ER.
Clinical Considerations
Monitor infants exposed to NUCYNTA ER through breast milk for excess sedation and respiratory depression. Withdrawal symptoms can occur in breastfed infants when maternal administration of an opioid analgesic is stopped, or when breast-feeding is stopped.
Infertility
Use of opioids for an extended period of time may cause reduced fertility in females and males of reproductive potential. It is not known whether these effects on fertility are reversible [see Adverse Reactions(6.2), Nonclinical Toxicology (13.1)].
Risks Specific to Abuse of NUCYNTA ER
Abuse of NUCYNTA ER poses a risk of overdose and death. This risk is increased with the concurrent use of NUCYNTA ER with alcohol and/or other CNS depressants [see Warnings and Precautions (5.1, 5.3), Drug Interactions (7)].
NUCYNTA ER is approved for oral use only. With parenteral abuse, the inactive ingredients in NUCYNTA ER can result in local tissue necrosis, infection, pulmonary granulomas, increased risk of endocarditis and valvular heart injury, embolism and death.
Parenteral drug abuse is commonly associated with transmission of infectious diseases such as hepatitis and HIV.
Clinical Presentation
Acute overdosage with tapentadol can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see Clinical Pharmacology (12.2)]. Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Treatment of Overdose
In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen, vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life support measures.
For clinically significant respiratory or circulatory depression secondary to tapentadol overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene.
Because the duration of reversal would be expected to be less than the duration of action of tapentadol in NUCYNTA ER, carefully monitor the patient until spontaneous respiration is reliably reestablished.
NUCYNTA ER will continue to release tapentadol and add to the tapentadol load for 24 to 48 hours or longer following ingestion, necessitating prolonged monitoring. If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, additional reversal agent should be given as directed in the product's prescribing information.
In an individual physically dependent on opioids, administration of the recommended usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the reversal agent should be initiated with care and by titration with smaller than usual doses of the reversal agent.
Effects on the Central Nervous System (CNS)
Tapentadol produces respiratory depression, by direct action on the brainstem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation.
Tapentadol causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings).
Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations.
Effects on the Gastrointestinal Tract and on Other Smooth Muscle
Tapentadol causes a reduction in motility and is associated with an increase in tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone is increased to the point of spasm, resulting in constipation. Other opioid induced effects may include a reduction in biliary and pancreatic secretions, spasm of the sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects on the Cardiovascular System
There was no effect of therapeutic and supratherapeutic doses of tapentadol on the QT interval. In a randomized, double-blind, placebo- and positive-controlled crossover study, healthy subjects were administered five consecutive immediate-release formulation doses of tapentadol 100 mg every 6 hours, tapentadol 150 mg every 6 hours, placebo and a single oral dose of moxifloxacin. Similarly, the immediate- release formulation tapentadol had no relevant effect on other ECG parameters (heart rate, PR interval, QRS duration, T-wave or U-wave morphology).
Tapentadol produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes, sweating, and/or orthostatic hypotension.
Effects on the Endocrine System
Opioids inhibit the secretion of adrenocorticortropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse Reactions (6.2)]. They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon.
Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions (6.2)].
Effects on the ImmuneSystem
Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration-Efficacy Relationships
The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with opioid agonists. The minimum effective analgesic concentration of tapentadol for any individual patient may increase over time due to an increase in pain, development of a new pain syndrome, and/or potential development of analgesic tolerance [see Dosage and Administration (2.1, 2.4)].
Concentration-Adverse Experience Relationships
There is a relationship between increasing tapentadol plasma concentration and increasing frequency of dose- related adverse reactions such as nausea, vomiting, CNS effects, and respiratory depression. In opioid- tolerant patients, the situation may be altered by the development of tolerance to opioid-related adverse reactions [see Dosage and Administration (2.1, 2.3, 2.4)].
Absorption
The mean absolute bioavailability after single-dose administration (fasting) of NUCYNTA ER is approximately 32% due to extensive first-pass metabolism. Maximum serum concentrations of tapentadol are observed between 3 and 6 hours after administration of NUCYNTA ER. Dose proportional increases for AUC have been observed after administration of NUCYNTA ER over the therapeutic dose range.
Steady-state exposure of tapentadol is attained after the third dose (i.e., 24 hours after first twice daily multiple dose administration). Following dosing with 250 mg every 12 hours, minimal accumulation was observed.
Food Effect
The AUC and Cmax increased by 6% and 17%, respectively, when NUCYNTA ER tablet was administered after a high-fat, high-calorie breakfast. NUCYNTA ER may be given with or without food.
Distribution
Tapentadol is widely distributed throughout the body. Following intravenous administration, the volume of distribution (Vz) for tapentadol is 540 +/- 98 L. The plasma protein binding is low and amounts to approximately 20%.
Elimination
Metabolism
In humans, about 97% of the parent compound is metabolized. Tapentadol is mainly metabolized via Phase 2 pathways, and only a small amount is metabolized by Phase 1 oxidative pathways. The major pathway of tapentadol metabolism is conjugation with glucuronic acid to produce glucuronides. After oral administration approximately 70% (55% O-glucuronide and 15% sulfate of tapentadol) of the dose is excreted in urine in the conjugated form. A total of 3% of drug was excreted in urine as unchanged drug. Tapentadol is additionally metabolized to N-desmethyl tapentadol (13%) by CYP2C9 and CYP2C19 and to hydroxy tapentadol (2%) by CYP2D6, which are further metabolized by conjugation. Therefore, drug metabolism mediated by cytochrome P450 system is of less importance than phase 2 conjugation.
None of the metabolites contribute to the analgesic activity.
Excretion
Tapentadol and its metabolites are excreted almost exclusively (99%) via the kidneys. The terminal half-life is on average 5 hours after oral administration. The total clearance of tapentadol is 1603 +/-227 mL/min.
Specific Populations
Age: Geriatric Population
The mean exposure (AUC) to tapentadol was similar in elderly subjects compared to young adults, with a 16% lower mean Cmax observed in the elderly subject group compared to young adult subjects.
Hepatic Impairment
Administration of tapentadol resulted in higher exposures and serum levels to tapentadol in subjects with impaired hepatic function compared to subjects with normal hepatic function. The ratio of tapentadol pharmacokinetic parameters for the mild hepatic impairment group (Child-Pugh Score 5 to 6) and moderate hepatic impairment group (Child-Pugh Score 7 to 9) in comparison to the normal hepatic function group were 1.7 and 4.2, respectively, for AUC; 1.4 and 2.5, respectively, for Cmax; and 1.2 and 1.4, respectively, for t1/2. The rate of formation of tapentadol-O-glucuronide was lower in subjects with increased liver impairment.
Renal Impairment
AUC and Cmax of tapentadol were comparable in subjects with varying degrees of renal function (from normal to severely impaired). In contrast, increasing exposure (AUC) to tapentadol-O-glucuronide was observed with increasing degree of renal impairment. In subjects with mild (CLCR= 50 to <80 mL/min), moderate (CLCR= 30 to<50 mL/min), and severe (CLCR= <30 mL/min) renal impairment, the AUC of tapentadol-O-glucuronide was 1.5-, 2.5-, and 5.5-fold higher compared with normal renal function, respectively.
Drug Interaction Studies
Tapentadol is mainly metabolized by Phase 2 glucuronidation, a high capacity/low affinity system; therefore, clinically relevant interactions caused by Phase 2 metabolism are unlikely to occur. Naproxen and probenecid increased the AUC of tapentadol by 17% and 57%, respectively. These changes are not considered clinically relevant and no change in dose is required.
No changes in the pharmacokinetic parameters of tapentadol were observed when acetaminophen and acetylsalicylic acid were given concomitantly.
In vitro studies did not reveal any potential of tapentadol to either inhibit or induce cytochrome P450 enzymes. Only a minor amount of tapentadol is metabolized via the oxidative pathway. Thus, clinically relevant interactions mediated by the cytochrome P450 system are unlikely to occur.
The pharmacokinetics of tapentadol were not affected when gastric pH or gastrointestinal motility were increased by omeprazole and metoclopramide, respectively.
Plasma protein binding of tapentadol is low (approximately 20%). Therefore, the likelihood of pharmacokinetic drug-drug interactions by displacement from the protein binding site is low.
Alcohol
NUCYNTA ER may be expected to have additive effects when used in conjunction with alcohol, other opioids, or illicit drugs that cause central nervous system depression, because respiratory depression, hypotension, hypertension, and profound sedation, coma or death may result [see Warnings and Precautions (5.5)].
An in vivo study examined the effect of alcohol (240 mL of 40%) on the bioavailability of a single dose of 100 mg and 250 mg of NUCYNTA ER tablet in healthy, fasted volunteers. After co-administration of a 100 mg NUCYNTA ER tablet and alcohol, the mean Cmax value increased by 48% compared to control with a range of 0.99-fold to 4.38-fold. The mean tapentadol AUClast and AUCinf were increased by 17%; the Tmax and t½ were unchanged. After co-administration of a 250 mg NUCYNTA ER tablet and alcohol, the mean Cmax value increased by 28% compared to control with a range of 0.90-fold to 2.67-fold. The mean tapentadol AUClast and AUCinf were increased by 16%; the Tmax and t½ were unchanged.
Carcinogenesis
In mice, tapentadol HCl was administered by oral gavage at dosages of 50, 100 and 200 mg/kg/day for 2 years (up to 0.34 times in the male mice and 0.25 times in the female mice the plasma exposure at the maximum recommended human dose [MRHD] for NUCYNTA ER on an area under the time-curve [AUC] basis). No increase in tumor incidence was observed at any dose level.
In rats, tapentadol HCl was administered in diet at dosages of 10, 50, 125 and 250 mg/kg/day for two years (up to 0.20 times in the male rats and 0.75 times in the female rats the plasma exposure at the MRHD on an AUC basis). No increase in tumor incidence was observed at any dose level.
Mutagenesis
Tapentadol did not induce gene mutations in bacteria but was clastogenic with metabolic activation in a chromosomal aberration test in V79 cells. The test was repeated and was negative in the presence and absence of metabolic activation. The one positive result for tapentadol was not confirmed in vivo in rats, using the two endpoints of chromosomal aberration and unscheduled DNA synthesis, when tested up to the maximum tolerated dose.
Impairment of Fertility
Tapentadol HCl was administered intravenously to male or female rats at dosages of 3, 6, or 12 mg/kg/day (representing exposures of up to approximately 0.56 times in the male rats and 0.50 times in the female rats the exposure at the MRHD on an AUC basis, based on extrapolation from toxicokinetic analyses in a separate 4-week intravenous study in rats).
Tapentadol did not alter fertility at any dose level. Maternal toxicity and adverse effects on embryonic development, including decreased number of implantations, decreased numbers of live conceptuses, and increased pre- and post-implantation losses occurred at dosages ≥6 mg/kg/day.
Study DPN-1: A total of 591 patients entered open-label treatment and 389 patients met the criteria for randomization into the double-blind treatment period. The mean age of the randomized population was 60 (range 29 to 87) years; approximately two-thirds of the patients had not taken opioids during the three months prior to the screening visit.
During the titration period, 34% of patients discontinued open-label NUCYNTA ER. The most common reasons for discontinuation in the double-blind treatment period were lack of efficacy in the placebo group (14%) and adverse events in the NUCYNTA ER group (15%).
After 12 weeks of treatment, NUCYNTA ER provided a significantly greater reduction in pain intensity from baseline to the end of the 12-week double-blind period compared to placebo. Figure 2 displays the proportion of randomized patients achieving various degrees of improvement in pain intensity from the start of the open-label titration period to the last week of the randomized withdrawal period. The figure is cumulative, such that patients, whose change from baseline is, for example 50%, are also included at every level of improvement below 50%. Patients who did not complete the study were assigned 0% improvement.
Figure 2. Percentage of Patients Achieving Various Levels of Improvement in Pain Intensity - PN-1ACCE
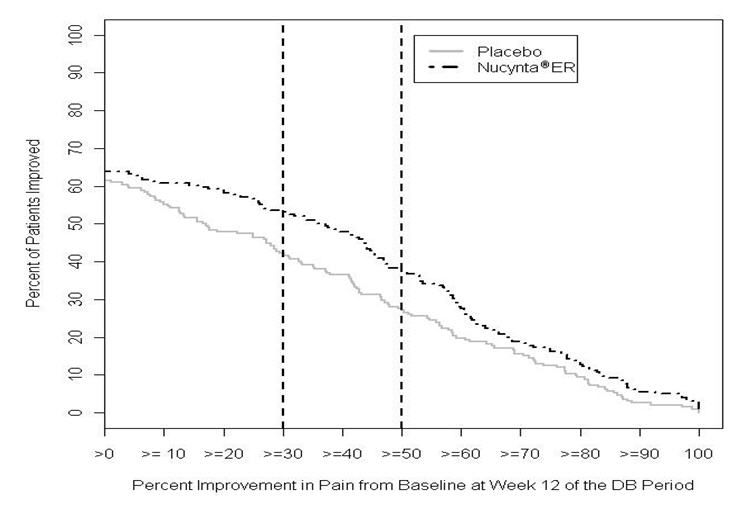
Figure 2 (Nucynta 03)
Study DPN-2: A total of 459 patients entered open-label treatment and 320 patients met the criteria for randomization into the double-blind treatment period. The mean age of the randomized population was 59 (range 28 to 83) years; approximately two-thirds of the patients had not taken opioids during the three months prior to the screening visit.
During the titration period, 22% of patients discontinued open-label NUCYNTA ER and 6% of patients were not subsequently randomized because they failed to have at least 1-point improvement in pain intensity. The most common reason for discontinuation in the double-blind treatment period was adverse events in both the placebo group (9%) and the NUCYNTA ER group (14%).
After 12 weeks of treatment, NUCYNTA ER provided a significantly greater reduction in pain intensity from baseline to the end of the 12-week double-blind period compared to placebo. Figure 3 displays the proportion of randomized patients achieving various degrees of improvement in pain intensity from the start of the open-label titration period to the last week of the randomized withdrawal period. The figure is cumulative, such that patients, whose change from baseline is, for example 50%, are also included at every level of improvement below 50%. Patients who did not complete the study were assigned 0% improvement.
Figure 3. Percentage of Patients Achieving Various Levels of Improvement in Pain Intensity - DPN-2
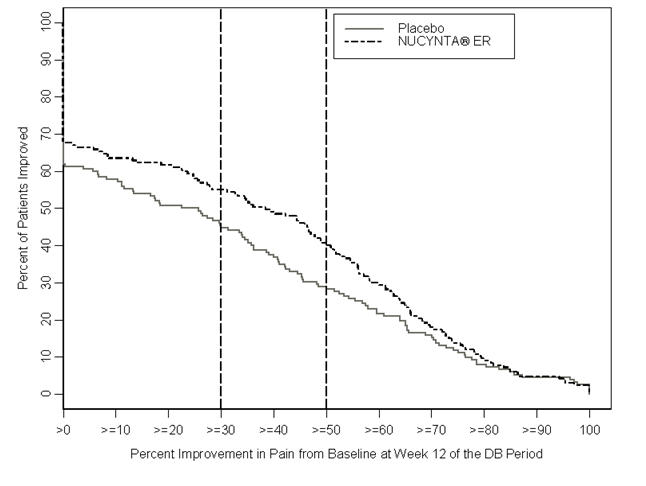
Figure 3 (Nucynta 04)
Storage and Disposal
Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store NUCYNTA ER securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home. Inform patients that leaving NUCYNTA ER unsecured can pose a deadly risk to others in the home [see Warnings and Precautions (5.1, 5.2), Drug Abuse and Dependence (9.2)].
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Expired, unwanted, or unused NUCYNTA ER Tablets should be disposed of by flushing the unused medication down the toilet if a drug take-back option is not readily available. Inform patients that they can visit www.fda.gov/drugdisposal for a complete list of medicines recommended for disposal by flushing, as well as additional information on disposal of unused medicines.
Addiction, Abuse, and Misuse
Inform patients that the use of NUCYNTA ER, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose or death [see Warnings and Precautions (5.1)]. Instruct patients not to share NUCYNTA ER with others and to take steps to protect NUCYNTA ER from theft or misuse.
Life-threatening Respiratory Depression
Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting NUCYNTA ER or when the dosage is increased, and that it can occur even at recommended dosages.
Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Warnings and Precautions (5.2)].
Accidental Ingestion
Inform patients that accidental ingestion, especially by children, may result in respiratory depression or death [see Warnings and Precautions (5.2)].
Interactions with Benzodiazepines and other CNS Depressants
Instruct patients not to consume alcoholic beverages, as well as prescription and over-the-counter products that contain alcohol, during treatment with NUCYNTA ER. The co-ingestion of alcohol with NUCYNTA ER may result in increased plasma levels and a potentially fatal overdose of oxymorphone [see Warnings and Precautions (5.3)].
Inform patients and caregivers that potentially fatal additive effects may occur if NUCYNTA ER is used with benzodiazepines or other CNS depressants, including alcohol (e.g., non-benzodiazepine sedative/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids), and not to use these concomitantly unless supervised by a health care provider [see Warnings and Precautions (5.3), Drug Interactions (7)].
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose
Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene). Discuss the importance of having access to an opioid overdose reversal agent, especially if the patient has risk factors for overdose (e.g., concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose) or if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose.
Discuss with the patient the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter, or as part of a community-based program) [see Dosage and Administration (2.2), Warnings and Precautions (5.2)].
Educate patients and caregivers on how to recognize the signs and symptoms of an overdose.
Explain to patients and caregivers that effects of opioid overdose reversal agent like naloxone and nalmefene are temporary, and that they must call 911 or get emergency medical help right away in all cases of known or suspected opioid overdose, even if an opioid overdose reversal agent is administered [see Overdosage (10)].
Advise patients and caregivers:
Hyperalgesia and Allodynia
Inform patients and caregivers not to increase opioid dosage without first consulting a clinician. Advise patients to seek medical attention if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see Warnings and Precautions (5.6); Adverse Reactions (6.2)].
Serotonin Syndrome
Inform patients that opioids could cause a rare but potentially life-threatening condition called serotonin syndrome resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop. Instruct patients to inform their healthcare providers if they are taking, or plan to take serotonergic medications [see Warnings and Precautions (5.7), Drug Interactions (7)].
Seizures
Inform patients that NUCYNTA ER could cause seizures if they are at risk for seizures or have epilepsy. Patients should be advised to stop taking NUCYNTA ER if they have a seizure while taking NUCYNTA ER and call their healthcare provider right away [see Warnings and Precautions (5.13)].
MAOI Interaction
Inform patients not to take NUCYNTA ER while using any drugs that inhibit monoamine oxidase. Patients should not start MAOIs while taking NUCYNTA ER [see Drug Interactions (7)].
Important Administration Instructions
Instruct patients how to properly take NUCYNTA ER, including the following:
Important Discontinuation Instructions
In order to avoid developing withdrawal symptoms, instruct patients not to discontinue NUCYNTA ER without first discussing a tapering plan with the prescriber [see Dosage and Administration (2.6)]
Driving or Operating Heavy Machinery
Inform patients that NUCYNTA ER may impair the ability to perform potentially hazardous activities such as driving a car or operating heavy machinery. Advise patients not to perform such tasks until they know how they will react to the medication [see Warnings and Precautions (5.15)].
Constipation
Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention.
Adrenal Insufficiency
Inform patients that NUCYNTA ER could cause adrenal insufficiency, a potentially life- threatening condition. Adrenal insufficiency may present with non-specific symptoms and signs such as nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. Advise patients to seek medical attention if they experience a constellation of these symptoms [see Warnings and Precautions (5.9)].
Hypotension
Inform patients that NUCYNTA ER may cause orthostatic hypotension and syncope. Instruct patients how to recognize symptoms of low blood pressure and how to reduce the risk of serious consequences should hypotension occur (e.g., sit or lie down, carefully rise from a sitting or lying position) [see Warnings and Precautions (5.10)].
Anaphylaxis
Inform patients that anaphylaxis has been reported with ingredients contained in NUCYNTA ER. Advise patients how to recognize such a reaction and when to seek medical attention [see Contraindications (4), Adverse Reactions (6.2)].
Pregnancy
Neonatal Opioid Withdrawal Syndrome
Inform female patients of reproductive potential that use of NUCYNTA ER for an extended period of time during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated [see Warnings and Precautions (5.4), Use in Specific Populations (8.1)].
Embryo-Fetal Toxicity
Advise female patients that NUCYNTA ER can cause fetal harm and to inform the prescriber if they are pregnant or plan to become pregnant [see Use in Specific Populations (8.1)].
Lactation
Advise patients that breastfeeding is not recommended during treatment with NUCYNTA ER [see Use in Specific Populations (8.2)]
Infertility
Inform patients that use of opioids for an extended period of time may cause reduced fertility. It is not known whether these effects on fertility are reversible [see Use in Specific Populations (8.3)].
Distributed by: Collegium Pharmaceutical, Inc., Stoughton, MA 02072
U.S. Patent Nos. 6071970, 7994364, 8075872, 8114383, 8309060, 8420056, 8536130, and RE39593.
NUCX-011-C.11
Revised: Month 2026