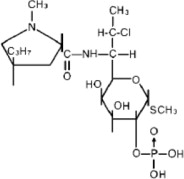
Other
sagent®
Rx only
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Clindamycin Injection, USP and other antibacterial drugs, Clindamycin Injection, USP should be used only to treat or prevent infections that are proven or strongly suspected to be caused by bacteria.
Sterile Solution is for Intramuscular and Intravenous Use
Hypersensitivity Reactions: Maculopapular rash and urticaria have been observed during drug therapy. Generalized mild to moderate morbilliform-like skin rashes are the most frequently reported of all adverse reactions.
Severe skin reactions such as toxic epidermal necrolysis, some with fatal outcome, have been reported (see WARNINGS). Cases of acute generalized exanthematous pustulosis (AGEP), erythema multiforme, some resembling Stevens-Johnson syndrome, have been associated with clindamycin. Anaphylactic shock, anaphylactic reaction, hypersensitivity, and acute myocardial ischemia with or without myocardial infarction occurring as part of an allergic reaction have also been reported (see WARNINGS). Cutaneous vasculitis and symmetrical drug-related intertriginous and flexural exanthema have also been reported.
Skin and Mucous Membranes: Pruritus, vaginitis, angioedema and rare instances of exfoliative dermatitis have been reported (see Hypersensitivity Reactions).
Liver: Jaundice and abnormalities in liver function tests have been observed during clindamycin therapy.
Renal: Acute kidney injury (see WARNINGS).
Hematopoietic: Transient neutropenia (leukopenia) and eosinophilia have been reported. Reports of agranulocytosis and thrombocytopenia have been made. No direct etiologic relationship to concurrent clindamycin therapy could be made in any of the foregoing.
Immune System: Drug reaction with eosinophilia and systemic symptoms (DRESS) cases have been reported.
Local Reactions: Injection site irritation, pain, induration and sterile abscess have been reported after intramuscular injection and thrombophlebitis after intravenous infusion. Reactions can be minimized or avoided by giving deep intramuscular injections and avoiding prolonged use of indwelling intravenous catheters.
Musculoskeletal: Polyarthritis cases have been reported.
Cardiovascular: Cardiopulmonary arrest and hypotension have been reported following too rapid intravenous administration (see DOSAGE AND ADMINISTRATION).
To report SUSPECTED ADVERSE REACTIONS, contact Sagent Pharmaceuticals at 1-866-625-1618 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
Adults: Parenteral (IM or IV Administration): Serious infections due to aerobic gram-positive cocci and the more susceptible anaerobes (NOT generally including Bacteroides fragilis, Peptococcus species and Clostridium species other than Clostridium perfringens):
More severe infections, particularly those due to proven or suspected Bacteroides fragilis, Peptococcus species, or Clostridium species other than Clostridium perfringens:
For more serious infections, these doses may have to be increased. In life-threatening situations due to either aerobes or anaerobes these doses may be increased. Doses of as much as 4,800 mg daily have been given intravenously to adults. See Dilution for IV use and IV Infusion Rates section below.
Single intramuscular injections of greater than 600 mg are not recommended.
Alternatively, drug may be administered in the form of a single rapid infusion of the first dose followed by continuous IV infusion as follows:
| To maintain serum clindamycin levels | Rapid infusion rate | Maintenance infusion rate |
| Above 4 mcg per mL Above 5 mcg per mL Above 6 mcg per mL | 10 mg/min for 30 min 15 mg/min for 30 min 20 mg/min for 30 min | 0.75 mg/min 1 mg/min 1.25 mg/min |
Pediatric Patients 1 month of age to 16 years: Parenteral (IM or IV) Administration: 20 to 40 mg/kg/day in 3 or 4 equal doses. The higher doses would be used for more severe infections. Clindamycin should be dosed based on total body weight regardless of obesity. As an alternative to dosing on a body weight basis, pediatric patients may be dosed on the basis of square meters body surface: 350 mg/m2/day for serious infections and 450 mg/m2/day for more severe infections.
Parenteral therapy may be changed to oral clindamycin flavored granules (clindamycin palmitate hydrochloride) or clindamycin capsules (clindamycin hydrochloride) when the condition warrants and at the discretion of the physician.
In cases of β-hemolytic streptococcal infections, treatment should be continued for at least 10 days.
Pediatric Patients less than 1 month: The recommended dosage is 15 to 20 mg/kg/day in 3 to 4 equal doses. See Table 3 regarding the dosing regimen for pediatric patients with post-menstrual age (PMA) less than or equal to 32 weeks, or greater than 32 weeks to less than or equal to 40 weeks.
| PMA (weeks) | Dose (mg/kg) | Dosing Interval (hours) |
| Less than or equal to 32 | 5 | 8 |
| Greater than or equal to 32 to less than or equal to 40 | 7 | 8 |
PMA: Post-Menstrual age
Dilution for IV use and IV Infusion Rates: The concentration of clindamycin in diluent for infusion should not exceed 18 mg per mL. Infusion rates should not exceed 30 mg per minute. The usual infusion dilutions and rates are as follows:
| Dose | Diluent | Time |
| 300 mg 600 mg 900 mg 1200 mg | 50 mL 50 mL 50 to 100 mL 100 mL | 10 min 20 min 30 min 40 min |
Administration of more than 1200 mg in a single 1-hour infusion is not recommended.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Dilution and Compatibility: Physical and biological compatibility studies monitored for 24 hours at room temperature have demonstrated no inactivation or incompatibility with the use of clindamycin injection (clindamycin phosphate) in IV solutions containing sodium chloride, glucose, calcium or potassium, and solutions containing vitamin B complex in concentrations usually used clinically. No incompatibility has been demonstrated with the antibacterial drugs cephalothin, kanamycin, gentamicin, penicillin or carbenicillin.
The following drugs are physically incompatible with clindamycin phosphate: ampicillin sodium, phenytoin sodium, barbiturates, aminophylline, calcium gluconate, and magnesium sulfate.
The compatibility and duration of stability of drug admixtures will vary depending on concentration and other conditions. For current information regarding compatibilities of clindamycin phosphate under specific conditions, please contact the Medical Affairs department toll-free at 1-866-625-1618.
Room Temperature: 6, 9 and 12 mg per mL (equivalent to clindamycin base) in dextrose injection 5%, sodium chloride injection 0.9%, or Lactated Ringers Injection in glass bottles or Mini-Bag containers, demonstrated physical and chemical stability for at least 16 days at 25°C. Also, 18 mg per mL (equivalent to clindamycin base) in dextrose injection 5%, in Mini-Bag containers, demonstrated physical and chemical stability for at least 16 days at 25°C.
Refrigeration: 6, 9 and 12 mg per mL (equivalent to clindamycin base) in dextrose injection 5%, sodium chloride injection 0.9%, or Lactated Ringers Injection in glass bottles or Mini-Bag containers, demonstrated physical and chemical stability for at least 32 days at 4°C.
IMPORTANT: This chemical stability information in no way indicates that it would be acceptable practice to use this product well after the preparation time. Good professional practice suggests that compounded admixtures should be administered as soon after preparation as is feasible.
Frozen: 6, 9 and 12 mg per mL (equivalent to clindamycin base) in dextrose injection 5%, sodium chloride injection 0.9%, or Lactated Ringers Injection in Mini-Bag containers demonstrated physical and chemical stability for at least eight weeks at -10°C.
Frozen solutions should be thawed at room temperature and not refrozen.