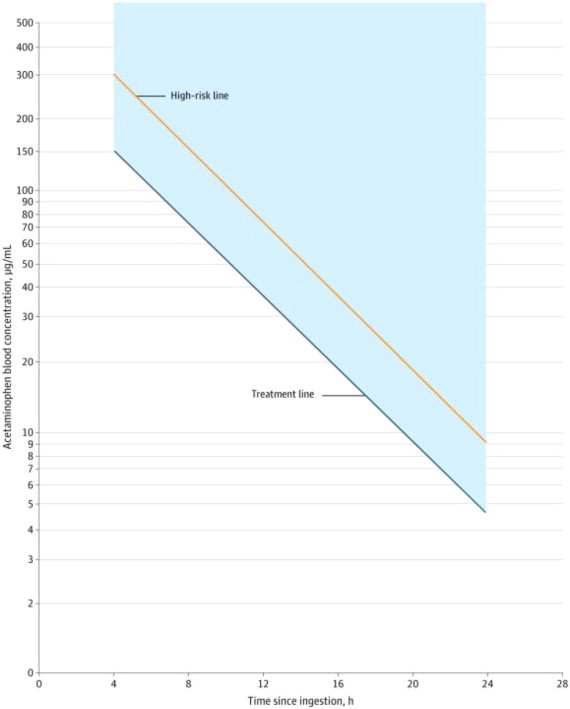
The acetaminophen concentration was in the non-toxic range, but time of ingestion was unknown or less than 4 hours:
- Obtain a second sample for acetaminophen concentration and consider the patient's clinical status to decide whether or not to continue acetylcysteine injection treatment.
- If there is any uncertainty as to patient's risk of developing hepatotoxicity, it is recommended to administer a complete treatment course.
Continued Therapy After Completion of Loading and Maintenance Doses
In cases of suspected massive overdose, or with concomitant ingestion of other substances, or in patients with preexisting liver disease; the absorption and/or the half-life of acetaminophen may be prolonged. In such cases, consideration should be given to the need for continued treatment with acetylcysteine injection beyond the total 300 mg/kg dose.
Acetaminophen levels and ALT/AST and INR should be checked after the last maintenance dose. If acetaminophen levels are still detectable, or if the ALT/AST are still increasing or the INR remains elevated; dosing should be continued and the treating physician should contact a US regional poison center at 1-800-222-1222, alternatively, a “special health professional assistance line for acetaminophen overdose” at 1-800-525-6115 for assistance with dosing recommendations, or 1-866-625-1618 for additional information.
Acetylcysteine injection is for intravenous administration only.
The total recommended dosage of acetylcysteine injection is 300 mg/kg given intravenously as either a three-bag regimen administered as a loading, second, and third dose infused over a total of 21 hours or a two-bag regimen administered as a loading and second dose infused over a total of 20 hours.
For the recommended weight-based dosage and weight-based dilution in patients see Table 2 for the three-bag regimen (for patients 5 kg or greater) or Table 3 for the two-bag regimen (for patients 41 kg or greater).
Three-Bag Regimen
Table 2. Three-Bag Recommended Acetylcysteine Injection Dosage and Dilution for Patients 5 kg or greater
|
|
|
| Body Weight
| Bag 1 (Loading Dose) | Bag 2 (Second Dose) | Bag 3 (Third Dose) |
| Loading Dose
| Diluent Volume*
| Infusion time
| Second Dose
| Diluent Volume*
| Infusion time
| Third Dose
| Diluent Volume*
| Infusion time
|
| 5 kg** to 20 kg
| 150 mg/kg
| 3 mL/kg
|
Infused
over 1 hour
| 50 mg/kg
| 7 mL/kg
|
Infused
over 4 hours
| 100 mg/kg
| 14 mL/kg
|
Infused over 16 hours
|
| 21 kg to 40 kg
| 150 mg/kg
| 100 mL
| 50 mg/kg
| 250 mL
| 100 mg/kg
| 500 mL
|
| 41 kg to 99 kg
| 150 mg/kg
| 200 mL
| 50 mg/kg
| 500 mL
| 100 mg/kg
| 1,000 mL
|
| 100 kg or greater***
| 15,000 mg
| 200 mL
| 5,000 mg
| 500 mL
| 10,000 mg
| 1,000 mL
|
Two-Bag Regimen
Table 3. Alternative Regimen for Patients 41 kg or Greater: Two-Bag Recommended Acetylcysteine Injection Dosage and Dilution
|
|
| Body Weight
| Bag 1 (Loading Dose) | Bag 2 (Second Dose) |
| Loading Dose
| Diluent Volume*
| Infusion time
| Second Dose
| Diluent Volume*
| Infusion time
|
| 41 kg to 99 kg
| 200 mg/kg
| 1,000 mL
| Infused over 4 hours
| 100 mg/kg
| 500 mL
| Infused over 16 hours
|
| 100 kg or greater**
| 20,000 mg
| 1,000 mL
| 10,000 mg
| 500 mL
|
Loading Dose/Infusion Rate Study
In a randomized, open-label, multi-center clinical study conducted in Australia in patients with acetaminophen poisoning, the rates of hypersensitivity reactions between a 15-minute and 60-minute intravenous infusion for the 150 mg/kg loading dose of acetylcysteine were compared.
The incidence of drug-related adverse reactions occurring within the first 2 hours following acetylcysteine administration is presented in Table 4. Overall, 17% of patients developed an acute hypersensitivity reaction (18% in the 15-minute infusion group; 14% in the 60-minute infusion group) [see Warnings and Precautions (5.1), Clinical Studies (14)].
Table 4. Incidence of Drug-Related Adverse Reactions Occurring Within the First 2 Hours Following Study Drug Administration by Preferred Term: Loading Dose/Infusion Rate Study
|
| Treatment Group | 15-minutes | 60-minutes |
| Number of Patients
| n=109
| n=71
|
| Cardiac disorders
| 5 (5%)
| 2 (3%)
|
| Severity: | Unkn | Mild | Moderate | Severe | Unkn | Mild | Moderate | Severe |
| Tachycardia NOS
| | 4 (4%)
| 1 (1%)
| | | 2 (3%)
| | |
| Gastrointestinal disorders
| 16 (15%)
| 7 (10%)
|
| Severity: | Unkn | Mild | Moderate | Severe | Unkn | Mild | Moderate | Severe |
| Nausea
| 1 (1%)
| | 6 (6%)
| | | 1 (1%)
| 1 (1%)
| |
| Vomiting NOS
| | 2 (2%)
| 11 (10%)
| | | 2 (3%)
| 4 (6%)
| |
| Immune System Disorders
| 20 (18%)
| 10 (14%)
|
| Severity: | Unkn | Mild | Moderate | Severe | Unkn | Mild | Moderate | Severe |
| Hypersensitivity reaction
| 2 (2%)
| 6 (6%)
| 11 (10%)
| 1 (1%)
| | 4 (6%)
| 5 (7%)
| 1 (1%)
|
| Respiratory, thoracic and mediastinal disorders
| 2 (2%)
| 2 (3%)
|
| Severity: | Unkn | Mild | Moderate | Severe | Unkn | Mild | Moderate | Severe |
| Pharyngitis
| | | 1 (1%)
| | | | | |
| Rhinorrhea
| | 1 (1%)
| | | | | | |
| Rhonchi
| | | | | | 1 (1%)
| | |
| Throat tightness
| | | | | | 1 (1%)
| | |
| Skin & subcutaneous tissue disorders
| 6 (6%)
| 5 (7%)
|
| Severity: | Unkn | Mild | Moderate | Severe | Unkn | Mild | Moderate | Severe |
| Pruritus
| | 1 (1%)
| | | | 2 (3%)
| | |
| Rash NOS
| | 3 (3%)
| 2 (2%)
| | | 3 (4%)
| | |
| Vascular disorders
| 2 (2%)
| 3 (4%)
|
| Severity: | Unkn | Mild | Moderate | Severe | Unkn | Mild | Moderate | Severe |
| Flushing
| | 1 (1%)
| 1 (1%)
| | | 2 (3%)
| 1 (1%)
| |
Safety Study
A large multi-center study was performed in Canada where data were collected from patients who were treated with intravenous acetylcysteine for acetaminophen overdose between 1980 and 2005. This study evaluated 4,709 adult cases and 1,905 pediatric cases. The incidence of hypersensitivity reactions in adult (overall incidence 8%) and pediatric (overall incidence 10%) patients is presented in Table 5 and Table 6.
Table 5. Distribution of Reported Hypersensitivity Reactions in Adult Patients Receiving Intravenous Acetylcysteine
|
| Reaction | Incidence (%) n=4,709 |
| Urticaria/Facial Flushing
| 6.1%
|
| Pruritus
| 4.3%
|
| Respiratory Symptoms*
| 1.9%
|
| Edema
| 1.6%
|
| Hypotension
| 0.1%
|
| Anaphylaxis
| 0.1%
|
Table 6. Distribution of Reported Hypersensitivity Reactions in Pediatric Patients Receiving Intravenous Acetylcysteine
|
| Reaction | Incidence (%) n=1,905 |
| Urticaria/Facial Flushing
| 7.6%
|
| Pruritus
| 4.1%
|
| Respiratory Symptoms*
| 2.2%
|
| Edema
| 1.2%
|
| Anaphylaxis
| 0.2%
|
| Hypotension
| 0.1%
|
Adverse Reactions from Observational Studies
Observational studies from published literature have described rates of hypersensitivity reactions identified by retrospective chart review in subjects receiving the two-bag regimen after adoption of this regimen as institutional policy in three non-US settings and one US setting compared to a historical control group that received the three-bag regimen.
Table 7 displays the incidence of hypersensitivity reactions in patients who received two-bag or three-bag regimens of intravenous acetylcysteine admitted between 2009 to 2020.
Table 7. Incidence of Hypersensitivity Reactions in Patients who Received Two-bag or Three-bag Regimens of Intravenous Acetylcysteine in Published Literature
Study | Hypersensitivity Reactions in Patients Receiving Two-Bag Regimen | Hypersensitivity Reactions in Patients Receiving Three-Bag Regimen |
| Study 1 (Three Danish hospitals)
| 4% (19/507)
| 16% (47/292)
|
| Study 2 (Four Australian hospitals)
| 5% (8/163)
| 14% (45/313)
|
| Study 3 (Nine Australian hospitals)
| 1% (17/1300)
| 7% (65/911)
|
| Study 4 (One US hospital)
| 19% (18/93)
| 23% (34/150)
|
Adverse Reactions from Postmarketing Spontaneous Reports
The following adverse reactions have been identified during post-approval use of acetylcysteine. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Immune system disorders: fatal anaphylaxis
Risk Summary
Limited published case reports and case series of pregnant women exposed to acetylcysteine during various trimesters are not sufficient to inform any drug associated risk. Delaying treatment of acetaminophen overdose may increase the risk of maternal or fetal morbidity and mortality [see Clinical Considerations]. Reproduction studies in rats and rabbits following oral administration of acetylcysteine during the period of organogenesis at doses similar to the total intravenous dose (based on the body surface area) did not cause any adverse effects to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
Acetaminophen and acetylcysteine cross the placenta. Delaying treatment in pregnant women with acetaminophen overdose and potentially toxic acetaminophen plasma levels may increase the risk of maternal and fetal morbidity and mortality.
Data
Animal Data
Reproduction studies have been performed following administration of acetylcysteine during the period of organogenesis in rats at oral doses up to 2,000 mg/kg/day (1.1 times the recommended total human intravenous dose of 300 mg/kg based on body surface area comparison) and in rabbits at oral doses up to 1,000 mg/kg/day (1.1 times the recommended total human intravenous dose of 300 mg/kg based on body surface area comparison). No adverse developmental outcomes due to acetylcysteine were observed.
Risk Summary
There are no data on the presence of acetylcysteine in human milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for acetylcysteine and any potential adverse effects on the breastfed child from acetylcysteine or from the underlying maternal condition.
Clinical Considerations
Based on the pharmacokinetic data, acetylcysteine should be nearly completely cleared 30 hours after administration. Breastfeeding women may consider pumping and discarding their milk for 30 hours after administration.
Distribution
The steady-state volume of distribution (Vdss) following administration of an intravenous dose of acetylcysteine was 0.47 liter/kg. The protein binding of acetylcysteine ranges from 66 to 87%.
Elimination
Metabolism
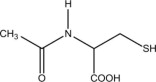
Acetylcysteine (i.e., N-acetylcysteine) is postulated to form cysteine and disulfides (N,N-diacetylcysteine and N-acetylcysteine). Cysteine is further metabolized to form glutathione and other metabolites.
Excretion
After a single oral dose of [35S]-acetylcysteine 100 mg, between 13 to 38% of the total radioactivity administered was recovered in urine within 24 hours. In a separate study, renal clearance was estimated to be approximately 30% of total body clearance.
Specific Populations
Hepatic Impairment
Following a 600 mg intravenous dose of acetylcysteine to subjects with mild (Child Pugh Class A, n=1), moderate (Child-Pugh Class B, n=4) or severe (Child-Pugh Class C; n=4) hepatic impairment and 6 healthy matched controls, mean T1/2 increased by 80%. Also, the mean CL decreased by 30% and the systemic acetylcysteine exposure (mean AUC) increased 1.6-fold in subjects with hepatic impairment compared to subjects with normal hepatic function. These changes are not considered to be clinically meaningful.
Renal Impairment
Hemodialysis may remove some of total acetylcysteine.
Carcinogenesis
Long-term studies in animals have not been performed to evaluate the carcinogenic potential of acetylcysteine.
Mutagenesis
Acetylcysteine was not genotoxic in the Ames test or the in vivo mouse micronucleus test. It was, however, positive in the in vitro mouse lymphoma cell (L5178Y/TK+/-) forward mutation test.
Impairment of Fertility
In a fertility study of acetylcysteine in rats, intravenous administration of 1,000 mg/kg/day (0.5 times the recommended human dose of 300 mg/kg based on body surface area) caused a profound reduction of fertility in females, which was correlated with morphological changes in oocytes and severe impairment of implantation (18 of 20 mated females had no implantations). The reversibility of this effect was not evaluated. No effects on fertility were observed in female rats at intravenous doses up to 300 mg/kg/day (0.2 times the recommended human dose based on body surface area), or in male rats at intravenous doses up to 1,000 mg/kg/day. Mating was unaffected in this study.
In a reproduction study of acetylcysteine, male rats were treated orally for 15 weeks prior to mating and during the mating period. A slight non-dose related reduction in fertility was observed at oral doses of 500 and 1,000 mg/kg/day (0.3 and 0.5 times the recommended human intravenous dose, respectively, based on body surface area). Treatment of male rats with acetylcysteine at an oral dose of 250 mg/kg/day for 15 weeks (0.1 times the recommended human intravenous dose based on body surface comparison) did not affect fertility or general reproductive performance.
Loading Dose/Infusion Rate Study
A randomized, open-label, multi-center clinical study was conducted in Australia in patients with acetaminophen poisoning to compare the rates of hypersensitivity reactions between two rates of infusion for the intravenous acetylcysteine loading dose. One hundred nine subjects were randomized to a 15-minute infusion rate and seventy-one subjects were randomized to a 60 minute infusion rate. The loading dose was 150 mg/kg followed by a maintenance dose of 50 mg/kg over 4 hours and then 100 mg/kg over 16 hours. Of the 180 patients, 27% were male and 73% were female. Ages ranged from 15 to 83 years, with the mean age being 30 years (±13.0).
A subgroup of 58 subjects (33 in the 15-minute infusion group; 25 in the 60-minute infusion group) was treated within 8 hours of acetaminophen ingestion. No hepatotoxicity occurred within this subgroup; however, with 95% confidence, the true hepatotoxicity rates could range from 0% to 9% for the 15-minute infusion group and from 0% to 12% for the 60-minute infusion group.
Observational Study
An open-label, observational database contained information on 1,749 patients who sought treatment for acetaminophen overdose over a 16-year period. Of the 1749 patients, 65% were female, 34% were male and less than 1% was transgender. Ages ranged from 2 months to 96 years, with 72% of the patients falling in the 16- to 40-year-old age bracket. A total of 399 patients received acetylcysteine treatment. A post-hoc analysis identified 56 patients who (1) were at high or probable risk for hepatotoxicity (APAP greater than 150 mg/L at the four hours line according to the Australian nomogram) and (2) had a liver function test. Of the 53 patients who were treated with intravenous acetylcysteine (300 mg/kg intravenous acetylcysteine administered over 20 to 21 hours) within 8 hours, two (4%) developed hepatotoxicity (AST or ALT greater than 1,000 U/L). Twenty-one of 48 (44%) patients treated with acetylcysteine after 15 hours developed hepatotoxicity. The actual number of hepatotoxicity outcomes may be higher than what is reported here. For patients with multiple admissions for acetaminophen overdose, only the first overdose treated with intravenous acetylcysteine was examined. Hepatotoxicity may have occurred in subsequent admissions.
Evaluable data were available from a total of 148 pediatric patients (less than 16 years of age) who were admitted for poisoning following ingestion of acetaminophen, of whom 23 were treated with intravenous acetylcysteine. There were no deaths of pediatric patients. None of the pediatric patients receiving intravenous acetylcysteine developed hepatotoxicity while two patients not receiving intravenous acetylcysteine developed hepatotoxicity. The number of pediatric patients is too small to provide a statistically significant finding of efficacy; however the results appear to be consistent to those observed for adults.
Three-Bag vs. Two-Bag Regimen Observational Study
A multi-center, observational, retrospective cohort study investigated rates of hypersensitivity reactions in 493 patients treated with a two-bag intravenous acetylcysteine regimen compared to 274 patients treated with a three-bag regimen in Denmark between January 2012 and December 2014. The two-bag regimen consisted of a 4 hour loading dose at 200 mg/kg followed by a 16 hour infusion at 100 mg/kg. The three-bag regimen used a 150 mg/kg loading dose administered over 15 minutes, followed by a second dose of 50 mg/kg over 4 hours and a final dose of 100 mg/kg for 16 hours. Patients in this study were treated with acetylcysteine regardless of plasma acetaminophen concentration. The median (range) serum acetaminophen concentration at presentation was <1 mcg/mL (0 to 353 mcg/mL) in the total study population, and only 12/767 patients (1.6%) had a serum acetaminophen level that would have warranted acetylcysteine treatment based on the revised Rumack-Mathew nomogram.
Hepatotoxicity was defined as peak ALT >1,000 U/L at any point during hospitalization. In this population that was low-risk for hepatotoxicity based on median acetaminophen level at presentation, no differences were observed in unadjusted hepatotoxicity rates between patients who received the two-bag regimen (4%, 20/493) compared to patients who received the three-bag regimen (4%, 11/274). However, this study has significant limitations and was not designed to establish non-inferiority.
Hypersensitivity Reactions
Advise patients and caregivers that hypersensitivity reactions related to administration and infusion may occur during and after acetylcysteine treatment, including hypotension, wheezing, shortness of breath and bronchospasm [see Warnings and Precautions (5.1)].
For specific treatment information regarding the clinical management of acetaminophen overdose, please contact your regional poison center at 1-800-222-1222, or alternatively, a special health professional assistance line for acetaminophen overdose at 1-800-525-6115.
sagent®
Mfd. for SAGENT Pharmaceuticals
Schaumburg, IL 60173 (USA)
Made in Italy
©2024 Sagent Pharmaceuticals
Revised: December 2024