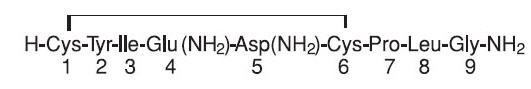Intravenous infusion (drip method) is the only acceptable method of parenteral administration of Pitocin for the induction or stimulation of labor. Accurate control of the rate of infusion is essential and is best accomplished by an infusion pump. It is convenient to piggyback the Pitocin infusion on a physiologic electrolyte solution, permitting the Pitocin infusion to be stopped abruptly without interrupting the electrolyte infusion. This is done in the following way.
1. Preparation
a. The standard solution for infusion of Pitocin is prepared by adding 1 mL (containing 10 units of oxytocin) to 1000 mL of 0.9% aqueous sodium chloride or Ringer’s lactate. The combined solution containing 10 milliunits (mU) of oxytocin/mL is rotated in the infusion bottle for thorough mixing.
b. Establish the infusion with a separate bottle of physiologic electrolyte solution not containing Pitocin.
c. Attach (piggyback) the Pitocin-containing bottle with the infusion pump to the infusion line as close to the infusion site as possible.
2. Administration
The initial dose should be 0.5–1 mU/min (equal to 3–6 mL of the dilute oxytocin solution per hour). At 30–60 minute intervals the dose should be gradually increased in increments of 1–2 mU/min until the desired contraction pattern has been established. Once the desired frequency of contractions has been reached and labor has progressed to 5–6 cm dilation, the dose may be reduced by similar increments.
Studies of the concentrations of oxytocin in the maternal plasma during Pitocin infusion have shown that infusion rates up to 6 mU/min give the same oxytocin levels that are found in spontaneous labor. At term, higher infusion rates should be given with great care, and rates exceeding 9–10 mU/min are rarely required. Before term, when the sensitivity of the uterus is lower because of a lower concentration of oxytocin receptors, a higher infusion rate may be required.
3. Monitoring
a. Electronically monitor the uterine activity and the fetal heart rate throughout the infusion of Pitocin. Attention should be given to tonus, amplitude and frequency of contractions, and to the fetal heart rate in relation to uterine contractions. If uterine contractions become too powerful, the infusion can be abruptly stopped, and oxytocic stimulation of the uterine musculature will soon wane (see PRECAUTIONS section).
b. Discontinue the infusion of Pitocin immediately in the event of uterine hyperactivity and/or fetal distress. Administer oxygen to the mother, who preferably should be put in a lateral position. The condition of mother and fetus should immediately be evaluated by the responsible physician and appropriate steps taken.