Exacerbation of Pre-Existing Psychosis
Administration of stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with pre-existing psychotic disorder.
Induction of a Manic Episode in Patients with Bipolar Disease
CNS stimulants may induce a manic or mixed episode in patients. Prior to initiating dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules treatment, screen patients for risk factors for developing a manic episode (e.g., comorbid or history of depressive symptoms or a family history of suicide, bipolar disorder, or depression).
New Psychotic or Manic Symptoms
CNS stimulants, at the recommended dosage, may cause psychotic or manic symptoms (e.g., hallucinations, delusional thinking, or mania) in patients without a prior history of psychotic illness or mania. In a pooled analysis of multiple short-term, placebo-controlled studies of CNS stimulants, psychotic or manic symptoms occurred in approximately 0.1% of CNS stimulant-treated patients compared to 0% of placebo-treated patients. If such symptoms occur, consider discontinuing dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules.
Adverse Reactions Leading to Discontinuation of Treatment
In two placebo-controlled studies of up to 5 weeks duration among children with ADHD, 2.4% (10/425) of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules-treated patients discontinued due to adverse reactions (including three patients with loss of appetite, one of whom also reported insomnia) compared to 2.7% (7/259) receiving placebo.
The most frequent adverse reactions leading to discontinuation of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules in controlled and uncontrolled, multiple-dose clinical trials of children (N=595) were anorexia (loss of appetite) (2.9%), insomnia (1.5%), weight loss (1.2%), emotional lability (1%), and depression (0.7%). Over half of these patients were exposed to dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules for 12 months or more.
In a separate placebo-controlled 4 week study in adolescents with ADHD, five patients (2.1%) discontinued treatment due to adverse events among dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules-treated patients (N=233) compared to none who received placebo (N=54). The most frequent adverse event leading to discontinuation and considered to be drug-related (i.e., leading to discontinuation in at least 1% of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules-treated patients and at a rate at least twice that of placebo) was insomnia (1.3%, n=3).
In one placebo-controlled 4 week study among adults with ADHD with doses 20 mg to 60 mg, 23 patients (12.0%) discontinued treatment due to adverse events among dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules-treated patients (N=191) compared to one patient (1.6%) who received placebo (N=64). The most frequent adverse events leading to discontinuation and considered to be drug-related (i.e., leading to discontinuation in at least 1% of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules-treated patients and at a rate at least twice that of placebo) were insomnia (5.2%, n=10), anxiety (2.1%, n=4), nervousness (1.6%, n=3), dry mouth (1.6%, n=3), anorexia (1.6%, n=3), tachycardia (1.6%, n=3), headache (1.6%, n=3), and asthenia (1.0%, n=2).
Adverse Reactions Occurring in Controlled Trials
Adverse reactions reported in a 3 week clinical trial of children and a 4 week clinical trial in adolescents and adults, respectively, treated with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules or placebo are presented in the tables below.
Table 1 Adverse Reactions Reported by 2% or More of Children (6 to 12 Years Old) Receiving Dextroamphetamine Saccharate, Amphetamine Aspartate Monohydrate, Dextroamphetamine Sulfate, and Amphetamine Sulfate Extended-Release Capsules with Higher Incidence Than on Placebo in a 584-Patient Clinical Study| Body System | Preferred Term | Dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules
(n=374) | Placebo
(n=210) |
|---|
| General | Abdominal Pain (stomachache) | 14% | 10% |
| Fever | 5% | 2% |
| Infection | 4% | 2% |
| Accidental Injury | 3% | 2% |
| Asthenia (fatigue) | 2% | 0% |
| Digestive System | Loss of Appetite | 22% | 2% |
| Vomiting | 7% | 4% |
| Nausea | 5% | 3% |
| Dyspepsia | 2% | 1% |
| Nervous System | Insomnia | 17% | 2% |
| Emotional Lability | 9% | 2% |
| Nervousness | 6% | 2% |
| Dizziness | 2% | 0% |
| Metabolic/Nutritional | Weight Loss | 4% | 0% |
Table 2 Adverse Reactions Reported by 5% or More of Adolescents (13 to 17 Years Old) Weighing ≤75 kg/165 lbs Receiving Dextroamphetamine Saccharate, Amphetamine Aspartate Monohydrate, Dextroamphetamine Sulfate, and Amphetamine Sulfate Extended-Release Capsules with Higher Incidence Than Placebo in a 287 Patient Clinical Forced Weekly-Dose Titration StudyIncluded doses up to 40 mg.
| Body System | Preferred Term | Dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules (n=233) | Placebo
(n=54) |
|---|
| Note: The following reactions did not meet the criterion for inclusion in Table 2 but were reported by 2 to 4% of adolescent patients receiving dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules with a higher incidence than patients receiving placebo in this study: accidental injury, asthenia (fatigue), dry mouth, dyspepsia, emotional lability, nausea, somnolence, and vomiting. |
| General | Abdominal Pain (stomachache) | 11% | 2% |
| Digestive System | Loss of Appetite Dose-related adverse reactions. | 36% | 2% |
| Nervous System | Insomnia
Nervousness | 12%
6% | 4%
6%Appears the same due to rounding. |
| Metabolic/Nutritional | Weight Loss | 9% | 0% |
Table 3 Adverse Reactions Reported by 5% or More of Adults Receiving Dextroamphetamine Saccharate, Amphetamine Aspartate Monohydrate, Dextroamphetamine Sulfate, and Amphetamine Sulfate Extended-Release Capsules with Higher Incidence Than on Placebo in a 255 Patient Clinical Forced Weekly-Dose Titration StudyIncluded doses up to 60 mg.
| Body System | Preferred Term | Dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules (n=191) | Placebo (n=64) |
|---|
| Note: The following reactions did not meet the criterion for inclusion in Table 3 but were reported by 2% to 4% of adult patients receiving dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules with a higher incidence than patients receiving placebo in this study: infection, photosensitivity reaction, constipation, tooth disorder (e.g., teeth clenching, tooth infection), emotional lability, libido decreased, somnolence, speech disorder (e.g., stuttering, excessive speech), palpitation, twitching, dyspnea, sweating, dysmenorrhea, and impotence. |
| General | Headache
Asthenia | 26%
6% | 13%
5% |
| Digestive System | Dry Mouth
Loss of Appetite
Nausea
Diarrhea | 35%
33%
8%
6% | 5%
3%
3%
0% |
| Nervous System | Insomnia
Agitation
Anxiety
Dizziness
Nervousness | 27%
8%
8%
7%
13% | 13%
5%
5%
0%
13%Appears the same due to rounding. |
| Cardiovascular System | Tachycardia | 6% | 3% |
| Metabolic/Nutritional | Weight Loss | 10% | 0% |
| Urogenital System | Urinary Tract Infection | 5% | 0% |
Hypertension
In a controlled 4 week outpatient clinical study of adolescents with ADHD, isolated systolic blood pressure elevations ≥15 mmHg were observed in 7/64 (11%) placebo-treated patients and 7/100 (7%) patients receiving dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules 10 or 20 mg. Isolated elevations in diastolic blood pressure ≥8 mmHg were observed in 16/64 (25%) placebo-treated patients and 22/100 (22%) dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules-treated patients. Similar results were observed at higher doses [see Warnings and Precautions (5.2)].
In a single-dose pharmacokinetic study in 23 adolescents with ADHD, isolated increases in systolic blood pressure (above the upper 95% CI for age, gender, and stature) were observed in 2/17 (12%) and 8/23 (35%), subjects administered 10 mg and 20 mg dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules, respectively. Higher single doses were associated with a greater increase in systolic blood pressure. All increases were transient, appeared maximal at 2 to 4 hours postdose and not associated with symptoms.
Allergic:
Urticaria, rash, hypersensitivity reactions including angioedema and anaphylaxis. Serious skin rashes, including Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported.
Cardiovascular:
Palpitations. There have been isolated reports of cardiomyopathy associated with chronic amphetamine use.
Central Nervous System:
Psychotic episodes at recommended doses, overstimulation, restlessness, irritability, euphoria, dyskinesia, dysphoria, depression, tremor, motor and verbal tics, aggression, anger, logorrhea, dermatillomania, paresthesia (including formication), and bruxism.
Endocrine:
Impotence, changes in libido, frequent or prolonged erections.
Eye Disorders:
Vision blurred, mydriasis.
Gastrointestinal:
Unpleasant taste, constipation, intestinal ischemia, and other gastrointestinal disturbances.
Musculoskeletal and Connective Tissue Disorders:
Rhabdomyolysis
Skin:
Alopecia.
Vascular Disorders:
Raynaud's phenomenon.
Pregnancy Exposure Registry
There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/othermedications/.
Risk Summary
Available data from published epidemiologic studies and postmarketing reports on use of prescription amphetamine in pregnant women have not identified a drug-associated risk of major birth defects and miscarriage (see Data). Adverse pregnancy outcomes, including premature delivery and low birth weight, have been seen in infants born to mothers taking amphetamines during pregnancy (see Clinical Considerations).
No apparent effects on morphological development were observed in embryo-fetal development studies, with oral administration of amphetamine to rats and rabbits during organogenesis at doses 2 and 12 times, respectively, the maximum recommended human dose (MRHD) of 20 mg/day given to adolescents, on a mg/m2 basis. However, in a pre- and postnatal development study, amphetamine (d- to l- ratio of 3:1) administered orally to pregnant rats during gestation and lactation caused a decrease in pup survival and a decrease in pup body weight that correlated with a delay in developmental landmarks at clinically relevant doses of amphetamine. In addition, adverse effects on reproductive performance were observed in pups whose mothers were treated with amphetamine. Long-term neurochemical and behavioral effects have also been reported in animal developmental studies using clinically relevant doses of amphetamine (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations
Fetal/Neonatal Adverse Reactions
Amphetamines, such as dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules, cause vasoconstriction and thereby may decrease placental perfusion. In addition, amphetamines can stimulate uterine contractions, increasing the risk of premature delivery. Infants born to mothers taking amphetamines during pregnancy have an increased risk of premature delivery and low birth weight.
Monitor infants born to mothers taking amphetamines for symptoms of withdrawal such as feeding difficulties, irritability, agitation, and excessive drowsiness.
Data
Animal Data
Amphetamine (d- to l- enantiomer ratio of 3:1) had no apparent effects on embryofetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis at doses of up to 6 and 16 mg/kg/day, respectively. These doses are approximately 2 and 12 times, respectively, the maximum recommended human dose (MRHD) of 20 mg/day given to adolescents, on a mg/m2 basis. Fetal malformations and death have been reported in mice following parenteral administration of d-amphetamine doses of 50 mg/kg/day (approximately 10 times the MRHD given to adolescents on a mg/m2 basis) or greater to pregnant animals. Administration of these doses was also associated with severe maternal toxicity.
A study was conducted in which pregnant rats received daily oral doses of amphetamine (d- to l-enantiomer ratio of 3:1) of 2, 6, and 10 mg/kg from gestation Day 6 to lactation Day 20. These doses are approximately 0.8, 2, and 4 times the MRHD of 20 mg/day given to adolescents, on a mg/m2 basis. All doses caused hyperactivity and decreased weight gain in the dams. A decrease in pup survival was seen at all doses. A decrease in pup body weight was seen at 6 and 10 mg/kg which correlated with delays in developmental landmarks, such as preputial separation and vaginal opening. Increased pup locomotor activity was seen at 10 mg/kg on Day 22 postpartum but not at 5 weeks postweaning. When pups were tested for reproductive performance at maturation, gestational weight gain, number of implantations, and number of delivered pups were decreased in the group whose mothers had been given 10 mg/kg.
A number of studies from the literature in rodents indicate that prenatal or early postnatal exposure to amphetamine (d- or d, l-) at doses similar to those used clinically can result in long-term neurochemical and behavioral alterations. Reported behavioral effects include learning and memory deficits, altered locomotor activity, and changes in sexual function.
Risk Summary
Based on limited case reports in published literature, amphetamine (d- or d, l-) is present in human milk, at relative infant doses of 2% to 13.8% of the maternal weight-adjusted dosage and a milk/plasma ratio ranging between 1.9 and 7.5. There are no reports of adverse effects on the breastfed infant. Long-term neurodevelopmental effects on infants from amphetamine exposure are unknown. It is possible that large dosages of amphetamine might interfere with milk production, especially in women whose lactation is not well established. Because of the potential for serious adverse reactions in nursing infants, advise patients that breastfeeding is not recommended during treatment with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules.
Long-Term Growth Suppression
Growth should be monitored during treatment with stimulants, including dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules, and pediatric patients aged 6 to 17 years who are not growing or gaining weight as expected may need to have their treatment interrupted [see Warnings and Precautions (5.5)].
Juvenile Animal Toxicity Data
Juvenile rats treated with mixed amphetamine salts early in the postnatal period through sexual maturation demonstrated transient changes in motor activity. Learning and memory was impaired at approximately 6 times the maximum recommended human dose (MRHD) given to children on a mg/m2 basis. No recovery was seen following a drug-free period. A delay in sexual maturation was observed at a dose approximately 6 times the MRHD given to children on a mg/m2 basis, although there was no effect on fertility.
In a juvenile developmental study, rats received daily oral doses of amphetamine (d to l enantiomer ratio of 3:1) of 2, 6, or 20 mg/kg on Days 7 to 13 of age; from Day 14 to approximately Day 60 of age these doses were given b.i.d. for total daily doses of 4, 12, or 40 mg/kg. The latter doses are approximately 0.6, 2, and 6 times the MRHD of 30 mg/day, given to children on a mg/m2 basis. Postdosing hyperactivity was seen at all doses; motor activity measured prior to the daily dose was decreased during the dosing period but the decreased motor activity was largely absent after an 18 day drug-free recovery period. Performance in the Morris water maze test for learning and memory was impaired at the 40 mg/kg dose, and sporadically at the lower doses, when measured prior to the daily dose during the treatment period; no recovery was seen after a 19 day drug-free period. A delay in the developmental milestones of vaginal opening and preputial separation was seen at 40 mg/kg but there was no effect on fertility.
Physical Dependence
Dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules may produce physical dependence. Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug.
Withdrawal signs and symptoms after abrupt discontinuation or dose reduction following prolonged use of CNS stimulants including dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules include dysphoric mood; depression; fatigue; vivid, unpleasant dreams; insomnia or hypersomnia; increased appetite; and psychomotor retardation or agitation.
Tolerance
Dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules may produce tolerance. Tolerance is a physiological state characterized by a reduced response to a drug after repeated administration (i.e., a higher dose of a drug is required to produce the same effect that was once obtained at a lower dose).
Clinical Effects of Overdose
Overdose of CNS stimulants is characterized by the following sympathomimetic effects:
- Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop.
- CNS effects including psychomotor agitation, confusion, and hallucinations. Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur.
- Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop.
Overdose Management
Consider the possibility of multiple drug ingestion. The pharmacokinetic profile of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules should be considered when treating patients with overdose. D-amphetamine is not dialyzable. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
Inactive Ingredients and Colors
The inactive ingredients in dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules include: sugar spheres (sucrose, sugar syrup, and corn starch), hypromellose, talc, triethyl citrate, methacrylic acid copolymer dispersion and gelatin capsules. Gelatin capsules contain titanium dioxide and FD&C Blue# 1. The 5 mg, 20 mg, 25 mg, and 30 mg capsules also contain FD&C Yellow#6. The 5 mg, 10 mg, and 15 mg also contain D&C Yellow#10 and D&C Red#33. Additionally, the imprint ink contains the following non-volatile ingredients: shellac, black iron oxide and potassium hydroxide.
Metabolism and Excretion
Amphetamine is reported to be oxidized at the 4 position of the benzene ring to form 4-hydroxyamphetamine, or on the side chain α or β carbons to form alpha-hydroxy-amphetamine or norephedrine, respectively. Norephedrine and 4-hydroxy-amphetamine are both active and each is subsequently oxidized to form 4-hydroxy-norephedrine. Alpha-hydroxy-amphetamine undergoes deamination to form phenylacetone, which ultimately forms benzoic acid and its glucuronide and the glycine conjugate hippuric acid. Although the enzymes involved in amphetamine metabolism have not been clearly defined, CYP2D6 is known to be involved with formation of 4-hydroxy-amphetamine. Since CYP2D6 is genetically polymorphic, population variations in amphetamine metabolism are a possibility.
Amphetamine is known to inhibit monoamine oxidase, whereas the ability of amphetamine and its metabolites to inhibit various P450 isozymes and other enzymes has not been adequately elucidated. In vitro experiments with human microsomes indicate minor inhibition of CYP2D6 by amphetamine and minor inhibition of CYP1A2, 2D6, and 3A4 by one or more metabolites. However, due to the probability of auto-inhibition and the lack of information on the concentration of these metabolites relative to in vivo concentrations, no predications regarding the potential for amphetamine or its metabolites to inhibit the metabolism of other drugs by CYP isozymes in vivo can be made.
With normal urine pHs, approximately half of an administered dose of amphetamine is recoverable in urine as derivatives of alpha-hydroxy-amphetamine and approximately another 30 to 40% of the dose is recoverable in urine as amphetamine itself. Since amphetamine has a pKa of 9.9, urinary recovery of amphetamine is highly dependent on pH and urine flow rates. Alkaline urine pHs result in less ionization and reduced renal elimination, and acidic pHs and high flow rates result in increased renal elimination with clearances greater than glomerular filtration rates, indicating the involvement of active secretion. Urinary recovery of amphetamine has been reported to range from 1 to 75%, depending on urinary pH, with the remaining fraction of the dose hepatically metabolized. Consequently, both hepatic and renal dysfunction have the potential to inhibit the elimination of amphetamine and result in prolonged exposures. In addition, drugs that effect urinary pH are known to alter the elimination of amphetamine, and any decrease in amphetamine's metabolism that might occur due to drug interactions or genetic polymorphisms is more likely to be clinically significant when renal elimination is decreased [see Drug Interactions (7)].
Special Populations
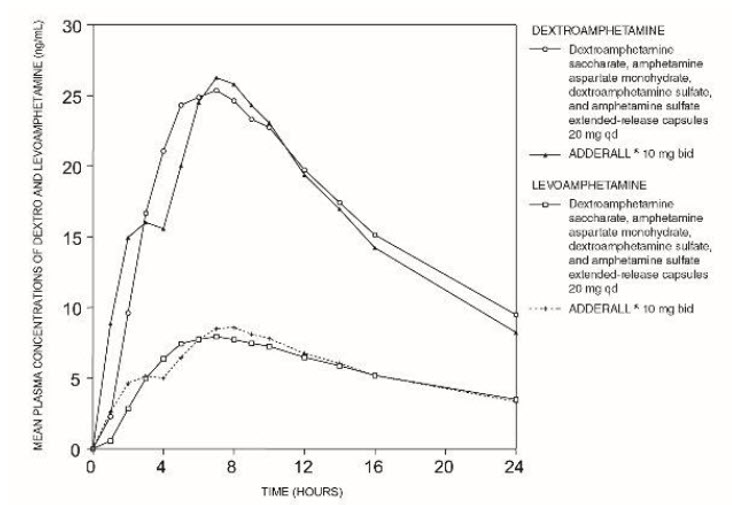
Comparison of the pharmacokinetics of d- and l-amphetamine after oral administration of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules in children (6 to 12 years) and adolescent (13 to 17 years) ADHD patients and healthy adult volunteers indicates that body weight is the primary determinant of apparent differences in the pharmacokinetics of d- and l-amphetamine across the age range. Systemic exposure measured by area under the curve to infinity (AUC∞) and maximum plasma concentration (Cmax) decreased with increases in body weight, while oral volume of distribution (VZ/F), oral clearance (CL/F), and elimination half-life (t1/2) increased with increases in body weight.
Pediatric Patients
On a mg/kg weight basis, children eliminated amphetamine faster than adults. The elimination half-life (t1/2) is approximately 1 hour shorter for d-amphetamine and 2 hours shorter for l-amphetamine in children than in adults. However, children had higher systemic exposure to amphetamine (Cmax and AUC) than adults for a given dose of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules, which was attributed to the higher dose administered to children on a mg/kg body weight basis compared to adults. Upon dose normalization on a mg/kg basis, children showed 30% less systemic exposure compared to adults.
Gender
Systemic exposure to amphetamine was 20 to 30% higher in women (N=20) than in men (N=20) due to the higher dose administered to women on a mg/kg body weight basis. When the exposure parameters (Cmax and AUC) were normalized by dose (mg/kg), these differences diminished. Age and gender had no direct effect on the pharmacokinetics of d- and l-amphetamine.
Race
Formal pharmacokinetic studies for race have not been conducted. However, amphetamine pharmacokinetics appeared to be comparable among Caucasians (N=33), Blacks (N=8), and Hispanics (N=10).
Patients with Renal Impairment
The effect of renal impairment on d- and l-amphetamine after administration of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules has not been studied. The impact of renal impairment on the disposition of amphetamine is expected to be similar between oral administration of lisdexamfetamine and dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules
In a pharmacokinetic study of lisdexamfetamine in adult subjects with normal and impaired renal function, mean d-amphetamine clearance was reduced from 0.7 L/hr/kg in normal subjects to 0.4 L/hr/kg in subjects with severe renal impairment (GFR 15 to <30 mL/min/1.73 m2). Dialysis did not significantly affect the clearance of d-amphetamine [see Use in Specific Populations (8.6)].
Carcinogenesis
No evidence of carcinogenicity was found in studies in which d, l-amphetamine (enantiomer ratio of 1:1) was administered to mice and rats in the diet for 2 years at doses of up to 30 mg/kg/day in male mice, 19 mg/kg/day in female mice, and 5 mg/kg/day in male and female rats. These doses are approximately 2.4, 1.5, and 0.8 times, respectively, the maximum recommended human dose of 30 mg/day given to children, on a mg/m2 basis.
Mutagenesis
Amphetamine, in the enantiomer ratio d- to l- ratio of 3:1, was not clastogenic in the mouse bone marrow micronucleus test in vivo and was negative when tested in the E. coli component of the Ames test in vitro. d, l-Amphetamine (1:1 enantiomer ratio) has been reported to produce a positive response in the mouse bone marrow micronucleus test, an equivocal response in the Ames test, and negative responses in the in vitro sister chromatid exchange and chromosomal aberration assays.
Impairment of Fertility
Amphetamine, in the enantiomer ratio d- to l- ratio of 3:1, did not adversely affect fertility or early embryonic development in the rat at doses of up to 20 mg/kg/day (approximately 8 times the maximum recommended human dose of 20 mg/day given to adolescents, on a mg/m2 basis).
Pediatric Patients
A double-blind, randomized, placebo-controlled, parallel-group study was conducted in children aged 6 to 12 (N=584) who met DSM-IV® criteria for ADHD (either the combined type or the hyperactive-impulsive type). Patients were randomized to fixed-dose treatment groups receiving final doses of 10 mg, 20 mg, or 30 mg of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules or placebo once daily in the morning for three weeks. Significant improvements in patient behavior, based upon teacher ratings of attention and hyperactivity, were observed for all dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules doses compared to patients who received placebo, for all three weeks, including the first week of treatment, when all dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules subjects were receiving a dose of 10 mg/day. Patients who received dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules showed behavioral improvements in both morning and afternoon assessments compared to patients on placebo.
In a classroom analogue study, patients (N=51) receiving fixed doses of 10 mg, 20 mg, or 30 mg dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules demonstrated statistically significant improvements in teacher-rated behavior and performance measures, compared to patients treated with placebo.
A double-blind, randomized, multicenter, parallel-group, placebo-controlled study was conducted in adolescents aged 13 to 17 (N=327) who met DSM-IV® criteria for ADHD. The primary cohort of patients (n=287, weighing ≤75 kg/165 lbs) was randomized to fixed-dose treatment groups and received four weeks of treatment. Patients were randomized to receive final doses of 10 mg, 20 mg, 30 mg, and 40 mg dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules or placebo once daily in the morning. Patients randomized to doses greater than 10 mg were titrated to their final doses by 10 mg each week. The secondary cohort consisted of 40 subjects weighing >75 kg/165 lbs who were randomized to fixed-dose treatment groups receiving final doses of 50 mg and 60 mg dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules or placebo once daily in the morning for 4 weeks. The primary efficacy variable was the Attention Deficit Hyperactivity Disorder-Rating Scale IV (ADHD-RS-IV) total score for the primary cohort. The ADHD-RS-IV is an 18-item scale that measures the core symptoms of ADHD. Improvements in the primary cohort were statistically significantly greater in all four primary cohort active treatment groups (dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules 10 mg, 20 mg, 30 mg, and 40 mg) compared with the placebo group. There was not adequate evidence that doses greater than 20 mg/day conferred additional benefit.
Adult Patients
A double-blind, randomized, placebo-controlled, parallel-group study was conducted in adults (N=255) who met DSM-IV® criteria for ADHD. Patients were randomized to fixed-dose treatment groups receiving final doses of 20 mg, 40 mg, or 60 mg of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules or placebo once daily in the morning for four weeks. Significant improvements, measured with the Attention Deficit Hyperactivity Disorder-Rating Scale (ADHD-RS), an 18-item scale that measures the core symptoms of ADHD, were observed at endpoint for all dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules doses compared to patients who received placebo for all four weeks. There was not adequate evidence that doses greater than 20 mg/day conferred additional benefit.
Abuse, Misuse, and Addiction
Educate patients and their families about the risks of abuse, misuse, and addiction of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules, which can lead to overdose and death, and proper disposal of any unused drug [see Warnings and Precautions (5.1), Drug Abuse and Dependence (9.2), Overdosage (10)]. Advise patients to store dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules in a safe place, preferably locked, and instruct patients to not give dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules to anyone else.
Risks to Patients with Serious Cardiac Disease
Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease [see Warnings and Precautions (5.2)].
Increased Blood Pressure and Heart Rate
Advise patients that dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules can cause elevations in blood pressure and heart rate [see Warnings and Precautions (5.3)].
Psychiatric Adverse Reactions
Prior to initiating treatment with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules, adequately screen patients with comorbid depressive symptoms to determine if they are at risk for bipolar disorder. Such screening should include a detailed psychiatric history, including a family history of suicide, bipolar disorder, and/or depression. Additionally, dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules therapy at usual doses may cause treatment-emergent psychotic or manic symptoms in patients without prior history of psychotic symptoms or mania [see Warnings and Precautions (5.4)].
Circulation Problems in Fingers and Toes [Peripheral Vasculopathy, including Raynaud's Phenomenon]
Instruct patients beginning treatment with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules about the risk of peripheral vasculopathy, including Raynaud's phenomenon, and in associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red. Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules. Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients [see Warnings and Precautions (5.7)].
Serotonin Syndrome
Caution patients about the risk of serotonin syndrome with concomitant use of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules and other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John's Wort, and with drugs that impair metabolism of serotonin (in particular MAOIs, both those intended to treat psychiatric disorders and also others such as linezolid) [see Contraindications (4), Warnings and Precautions (5.8), Drug Interactions (7.1)]. Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome.
Concomitant Medications
Advise patients to notify their physicians if they are taking, or plan to take, any prescription or over-the-counter drugs because there is a potential for interactions [see Drug Interactions (7.1)]. Advise patient or caregiver of steps to take with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules when a laboratory imaging procedure is ordered [see Drug Interactions (7.2)].
Growth
Monitor growth in children during treatment with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules, and patients who are not growing or gaining weight as expected may need to have their treatment interrupted [see Warnings and Precautions (5.5)].
Motor and Verbal Tics, and Worsening of Tourette's Syndrome
Advise patients that motor and verbal tics and worsening of Tourette's syndrome may occur during treatment with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules. Instruct patients to notify their healthcare provider if emergence of new tics or worsening of tics or Tourette's syndrome occurs [see Warnings and Precautions (5.9)].
Pregnancy Registry
Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules during pregnancy [see Use in Specific Populations (8.1)].
Pregnancy
Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during treatment with dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules. Advise patients of the potential fetal effects from the use of dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules during pregnancy [see Use in Specific Populations (8.1)].
Lactation
Advise women not to breastfeed if they are taking dextroamphetamine saccharate, amphetamine aspartate monohydrate, dextroamphetamine sulfate, and amphetamine sulfate extended-release capsules [see Use in Specific Populations (8.2)].
Marketed by:
Rhodes Pharmaceuticals LLC
Wilson, NC 27893
Rev.: 05/2026
For more information, call Rhodes Pharmaceuticals LLC at 1-888-873-5329.