When switching from another insulin to AFREZZA, a different insulin dosage may be needed and increased frequency of blood glucose monitoring and monitoring for signs and symptoms of hypoglycemia may be needed
[see Warnings and Precautions (
5.2,
5.3), Clinical Pharmacology (
12.2,
12.3)].
- Refer to the prescribing information for the pre-mixed insulin to estimate the mealtime subcutaneous insulin dosage based on the product’s pharmacokinetic and pharmacodynamic properties.
- Follow the recommendations in
Table 1 to convert each estimated injected mealtime dosage to an AFREZZA mealtime dose.
- If basal insulin is clinically indicated, refer to the prescribing information for the chosen basal insulin for dosage recommendations.
Table 1. Recommended Starting Mealtime Dosage of AFREZZA when Switching from Other Mealtime Insulin Regimens| Current Subcutaneous Mealtime Insulin Dosage | Starting Dosage of AFREZZA |
| Up to 3 units | 4 units
|
| 4 to 5 units
| 8 units |
| 6 to 7 units | 12 units |
| 8 or more units | 16 units |
* For AFREZZA doses exceeding the contents of a single cartridge at mealtime, use more than one cartridge. To achieve the required total mealtime dosage, use a combination of 4 unit, 8 unit, and 12 unit cartridges. When titrating dosages above 16 units after the initial conversion dosage, use combinations of different cartridges
[see Dosage and Administration (
2.4), Dosage Forms and Strengths (
3), How Supplied/Storage and Handling (
16)].
Risk Factors and Mitigation Strategies for Hypoglycemia
The risk of hypoglycemia after use of AFREZZA is related to the duration of action of the insulin and, in general, is highest when the glucose lowering effect of the insulin is maximal
[See Clinical Pharmacology (
12.3)]
. The glucose lowering effect time course of AFREZZA may vary in different individuals or at different times in the same individual and depends on many conditions
[see Clinical Pharmacology (
12.2)]
. Other factors which may increase the risk of hypoglycemia include changes in meal pattern (e.g., macronutrient content or timing of meals), changes in level of physical activity, or changes to concomitantly administered medication
[see Drug Interactions (
7)].
Patients with renal or hepatic impairment may be at higher risk of hypoglycemia
[see Use in Specific Populations (
8.6,
8.7)].
Advise patients to recognize and manage hypoglycemia and self-monitor glucose. In patients at higher risk for hypoglycemia and patients who have reduced symptomatic awareness of hypoglycemia, increased frequency of glucose monitoring is recommended.
Hypoglycemia
Hypoglycemia is the most commonly observed adverse reaction in patients treated with AFREZZA
[see Warnings and Precautions (
5.3)]
. The rates of reported hypoglycemia depend on the definition of hypoglycemia used, diabetes type, insulin dose, intensity of glucose control, background therapies, and other intrinsic and extrinsic patient factors. For these reasons, comparing rates of hypoglycemia across clinical trials of AFREZZA or with the incidence of hypoglycemia for other insulin products may be misleading and also, may not be representative of hypoglycemia rates that will occur in clinical practice.
The incidence of severe and non-severe hypoglycemia in AFREZZA-treated patients versus placebo-treated patients with type 2 diabetes mellitus is shown in
Table 4. A hypoglycemic episode was recorded if a patient reported symptoms of hypoglycemia with or without a blood glucose value consistent with hypoglycemia. Severe hypoglycemia was defined as an event with symptoms consistent with hypoglycemia requiring the assistance of another person and associated with either a blood glucose value consistent with hypoglycemia or prompt recovery after treatment for hypoglycemia.
Table 4. Incidence of Severe and Non-Severe Hypoglycemia in a Placebo-Controlled Study of Adult Patients with Type 2 Diabetes Mellitus| Hypoglycemia Severity | AFREZZA(N=177) | Placebo(N=176) |
Severe Hypoglycemia | 5% | 2% |
| Non-Severe Hypoglycemia | 67% | 30% |
Other Adverse Reactions in Adults with Type 1 or Type 2 Diabetes MellitusOther Adverse Reactions in Adults with Type 1 or Type 2 Diabetes Mellitus
Cough
Approximately 27% of adults treated with AFREZZA reported cough, compared to approximately 5% of patients treated with comparator. In clinical trials, cough was the most common reason for discontinuation of AFREZZA therapy (3% of adult AFREZZA-treated patients).
Pulmonary Function Decline
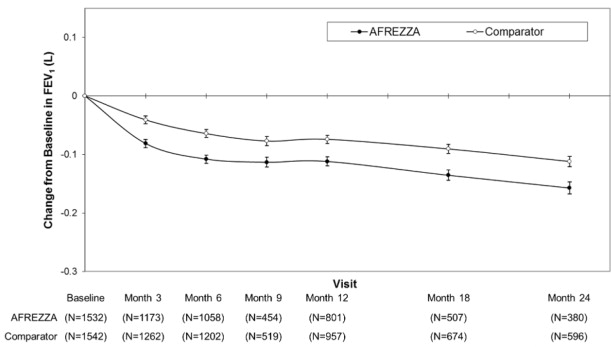
In clinical trials lasting up to 2 years, excluding patients with chronic lung disease, adults treated with AFREZZA had a 40 mL (95% CI: -80, -1) greater decline from baseline in forced expiratory volume in one second (FEV
1) compared to patients treated with comparator anti-diabetes treatments. The decline occurred during the first 3 months of therapy and persisted over 2 years (
Figure 1). A decline in FEV
1 of ≥ 15% occurred in 6% of AFREZZA-treated patients compared to 3% of comparator-treated patients
[see Warnings and Precautions (
5.4)].
Figure 1. Mean (+/-SE) Change in FEV1(Liters) from Baseline for Adult Patients with Type 1 and Type 2 Diabetes Mellitus
Weight Gain
Weight gain has occurred with some insulin therapies, including AFREZZA. Weight gain has been attributed to the anabolic effects of insulin and the decrease in glycosuria. In a clinical trial of adult patients with type 2 diabetes mellitus
[see Clinical Studies (
14.3)]
, there was a mean 0.49 kg weight gain among AFREZZA-treated patients compared with a mean 1.13 kg weight loss among placebo-treated patients.
Adverse Reactions in the Clinical Trial in Pediatric Patients Aged 6 Years and Older with Type 1 or Type 2 Diabetes Mellitus
A 26-week open-label, randomized clinical trial evaluated the safety of AFREZZA versus rapid-acting insulin analog (RAA), both in combination with basal insulin, in 230 pediatric patients with type 1 or type 2 diabetes mellitus
[see Clinical Studies (
14.4)].
The trial was followed by a 26-week safety extension. The mean age of patients was 12.6 years (range: 4 to 17 in the RAA arm, 6 to 17 in the AFREZZA arm). The majority (97.8%) had type 1 diabetes mellitus; a small subset (2.2%) had type 2 diabetes mellitus
[see Clinical Studies (
14.4)]
. The trial population had the following characteristics: 38% were female, 77% were White, 10% were Black or African American, 3% were Asian, 6% multiracial, and 20% were Hispanic or Latino ethnicity.
Table 5 shows the frequency of common adverse reactions, excluding hypoglycemia, associated with the use of AFREZZA during the pediatric clinical trial. Data observed for 52 weeks was consistent with the 26-week safety profile. These adverse reactions occurred more commonly on AFREZZA than the comparator and occurred in at least 5% of patients treated with AFREZZA. The overall safety profile was similar to that of adults. In this trial, the change in percent predicted FEV1 from baseline to Week 26 was similar in both groups.
Table 5. Common Adverse Reactions That Occurred in ≥ 5% of Pediatric Patients Aged 6 Years and Older With Type 1 and Type 2 Diabetes Mellitus (excluding Hypoglycemia) Treated with AFREZZA and More Commonly on AFREZZA Than on RAA| Adverse Reaction
a | AFREZZA(n=117)% | RAA(n=113)% |
| Cough | 21 | 3 |
| Upper respiratory tract infection | 18 | 14 |
| Oropharyngeal pain | 11 | 4 |
Headache | 8 | 5 |
| Vomiting | 5 | 3 |
a This study was not designed to evaluate meaningful comparisons of adverse reaction incidence between AFREZZA and RAA.
|
Hypoglycemia
In the pediatric clinical trial
[see Clinical Studies (
14.4)]
, events of severe hypoglycemia (level 3) were defined as an episode associated with severe cognitive impairment requiring external assistance for recovery. Level 3 hypoglycemia was reported in 2 (1.7%) AFREZZA-treated pediatric patients versus 1 (0.9%) RAA-treated patient during the randomized treatment period.
Risk Summary
Limited available data with AFREZZA use in pregnant women are insufficient to determine drug-associated risks for adverse developmental outcomes. Available information from published studies with human insulin use during pregnancy has not reported a clear association with human insulin and adverse developmental outcomes (
see
Data). There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (
see
Clinical Considerations). In animal reproduction studies, there were no adverse developmental outcomes with subcutaneous administration of carrier particles (vehicle without insulin) to pregnant rats during organogenesis at doses 21 times the human daily dose of 99 mg AFREZZA, based on AUC
(see
Data)
.
The estimated background risk of major birth defects is 6-10% in women with pre-gestational diabetes with HbA1c >7 and has been reported to be as high as 20-25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations
Disease-associated maternal and/or embryo/fetal risk
Poorly controlled diabetes in pregnancy increases the maternal risk for DKA, pre-eclampsia, spontaneous abortions, preterm delivery, stillbirth, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia- related morbidity.
Data
Human Data
There are limited data with AFREZZA use in pregnant women. Published data do not report a clear association with human insulin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when human insulin is used during pregnancy. However, these studies cannot definitely establish the absence of any risk because of methodological limitations including small sample size and lack of blinding.
Animal Data
In pregnant rats given subcutaneous doses of 10, 30, and 100 mg/kg/day of carrier particles (vehicle without insulin) from gestation day 6 through 17 (organogenesis), no major malformations were observed at doses up to 100 mg/kg/day (21 times the human systemic exposure at a daily dose of 99 mg AFREZZA, based on AUC).
In pregnant rabbits given subcutaneous doses of 2, 10, and 100 mg/kg/day of carrier particles (vehicle without insulin) from gestation day 7 through 19 (organogenesis), adverse maternal effects were observed in all dose groups (at human systemic exposure following a daily dose of 99 mg AFREZZA, based on AUC).
In pregnant rats given subcutaneous doses of 10, 30, and 100 mg/kg/day of carrier particles (vehicle without insulin) from gestation day 7 through lactation day 20 (weaning), decreased epididymis and testes weights were observed in F1 male offspring, however, no decrease in fertility was noted, and impaired learning were observed in F1 pups at
> 30 mg/kg/day (6 times the human systemic exposure at a daily dose of 99 mg AFREZZA, based on AUC).
Risk Summary
There are no data on the presence of AFREZZA in human milk, the effects on the breastfed infant, or the effects on milk production. One small published study reported that exogenous subcutaneous insulin was present in human milk. No adverse effects in infants were noted. The carrier particles are present in rat milk (
see
Data). Potential adverse reactions that are related to inhalational administration of AFREZZA are unlikely to be associated with potential exposure of AFREZZA through breast milk. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for AFREZZA and any potential adverse effects on the breastfed infant from AFREZZA or from the underlying maternal condition.
Data
Subcutaneous administration of the carrier particle in lactating rats resulted in excretion of the carrier particle in rat milk at levels that were approximately 10% of the maternal exposure. Given the results of the rat study, it is highly likely that the insulin and carrier in AFREZZA are excreted in human milk.
Absorption
The pharmacokinetic profiles for orally inhaled AFREZZA 4, 12, and 48 units from a study in 30 patients with type 1 diabetes mellitus are shown in
Figure 2(B). A higher maximum plasma insulin concentration was achieved at an earlier timepoint in this study when patients were switched from subcutaneous mealtime insulin to AFREZZA
[see Dosage and Administration (
2.3)].
The time to maximum serum insulin concentration (t
max) ranged from 10-20 minutes after oral inhalation of 4 to 48 units of AFREZZA.
Elimination
The apparent terminal half-life ranged from 120 to 206 minutes. Serum insulin concentrations declined to baseline by approximately 60 to 240 minutes.
Metabolism and Excretion
The metabolism and excretion of AFREZZA are comparable to regular human insulin.
Carrier Particles
Clinical pharmacology studies showed that carrier particles
[see Description (
11.1)]
are not metabolized and are eliminated unchanged in the urine following the lung absorption. Following oral inhalation of AFREZZA, a mean of 39% of the inhaled dose of carrier particles was distributed to the lungs and a mean of 7% of the dose was swallowed. The swallowed fraction was not absorbed from the GI tract and was eliminated unchanged in the feces.
Specific Populations
Pediatric Patients
In pediatric patients aged 8 years and older, insulin serum concentration profiles (T
max and time decline to baseline) showed a similar time course between adult and pediatric patients following administration of AFREZZA. Insulin Cmax and AUC increased in a dose-dependent manner following a single dose of 4 units to 12 units.
Drug Interaction Studies
Bronchodilators and Inhaled Steroids
Albuterol increased the AUC insulin after AFREZZA administration by 25% in patients with asthma
[see Drug Interactions (
7) ].
AFREZZA is contraindicated in patients with asthma.
In a study in healthy volunteers no significant change in insulin exposure was observed when fluticasone was administered following AFREZZA administration.
Results
At Week 24, treatment with mealtime AFREZZA and basal insulin provided a mean reduction in HbA1c that met the pre-specified non-inferiority margin of 0.4%. AFREZZA and basal insulin provided less HbA1c reduction than insulin aspart and basal insulin, and the difference was statistically significant. More patients in the insulin aspart and basal insulin group achieved the HbA1c target of ≤7% (
Table 8).
Table 8. Results at Week 24 in an Active-Controlled Study of Mealtime AFREZZA plus Basal Insulin in Adults with Type 1 Diabetes Mellitus| Efficacy Parameter | AFREZZA + Basal Insulin (N=174) | Insulin Aspart + Basal Insulin
(N=170)
|
| HbA1c (%) | | |
| Baseline (adjusted mean
a)
| 7.94 | 7.92 |
| Change from baseline (adjusted mean
a,b)
| -0.21 | -0.40 |
Difference from insulin aspart (adjusted mean
a,b)
(95% CI) | 0.19
(0.02, 0.36)
|
| Percentage of patients achieving HbA1c ≤ 7%
c | 14% | 27% |
|
Fasting Plasma Glucose (mg/dL) | | |
| Baseline (adjusted mean
a)
| 153.9 | 151.6 |
| Change from baseline (adjusted mean
a,b)
| -25.3 | 10.2 |
Difference from insulin aspart (adjusted mean
a,b)
(95% CI) | -35.4
(-56.3, -14.6)
|
a Adjusted mean was obtained using a Mixed Model Repeated Measures (MMRM) approach with HbA1c or FPG as the dependent variable and treatment, visit, region, basal insulin stratum, and treatment by visit interaction as fixed factors, and corresponding baseline as a covariate. An autoregression (1) [AR(1)] covariance structure was used.
b Data at 24 weeks were available from 131 (75%) and 150 (88%) patients randomized to the AFREZZA and insulin aspart groups, respectively.
c The percentage was calculated based on the number of patients randomized to the trial.
|
Results
At Week 24, treatment with AFREZZA plus OADs provided a mean reduction in HbA1c that was statistically significantly greater compared to the HbA1c reduction observed in the placebo plus OADs group (
Table 9).
Table 9. Results at Week 24 in a Placebo-Controlled Study of AFREZZA in Adults with Type 2 Diabetes Mellitus Inadequately Controlled on Oral Antidiabetic Agents| Efficacy Parameter | AFREZZA + Oral Anti-Diabetic Agents
(N=177)
| Placebo + Oral Anti-Diabetic Agents
(N=176)
|
| HbA1c (%) | | |
| Baseline (adjusted mean
a)
| 8.25 | 8.27 |
| Change from baseline (adjusted mean
a,b)
| -0.82 | -0.42 |
| Difference from placebo (adjusted mean
a,b)
(95% CI)
| -0.40
(-0.57, -0.23)
|
| Percentage (%) of patients achieving HbA1C ≤7%
c | 32% | 15% |
|
| Fasting Plasma Glucose (mg/dL) | | |
| Baseline (adjusted mean
a)
| 175.9 | 175.2 |
| Change from baseline (adjusted mean
a,b)
| -11.2 | -3.8 |
| Difference from placebo (adjusted mean
a,b)
(95% CI)
| -7.4
(-18.0, 3.2)
|
a Adjusted mean was obtained using a Mixed Model Repeated Measures (MMRM) approach with HbA1c or FPG as the dependent variable and treatment, visit, region, and treatment by visit interaction as fixed factors, and corresponding baseline as a covariate. An autoregression (1) [AR(1)] covariance structure was used.
b Data at 24 weeks without rescue therapy were available from 139 (79%) and 129 (73%) patients randomized to the AFREZZA and placebo groups, respectively.
c The percentage was calculated based on the number of patients randomized to the trial.
|
Storage:
Not in Use: Refrigerated Storage 2°C to 8°C (36°F to 46°F)
|
| Sealed (Unopened) Foil Package | May be stored until the Expiration Date* |
| Sealed (Unopened) Blister Cards and Strips | Must be used within 1 month* |
In Use: Room Temperature Storage 25°C (77°F), excursions permitted 15°C to 30°C (59°F to 86°F)
| Sealed (Unopened) Blister Cards and Strips | Must be used within 10 days |
| Opened Strips | Must be used within 3 days |
Do not put a blister card or strip back into the refrigerator after being stored at room temperature.
Inhaler Storage:
Store refrigerated or at room temperature 2°C to 25°C (36°F to 77°F); excursions permitted. Inhaler may be stored refrigerated, but should be at room temperature before use.
Handling:
Before use, cartridges should be at room temperature for 10 minutes.
Acute Bronchospasm in Patients with Chronic Lung Disease
Advise patients that if they experience any respiratory difficulty after inhalation of AFREZZA, they should report it to their healthcare provider immediately for assessment
[see Warnings and Precautions (
5.1)]
.
Hypoglycemia
Instruct patients on self-management procedures including glucose monitoring, proper inhalation technique, and management of hypoglycemia and hyperglycemia, especially at initiation of AFREZZA therapy. Instruct patients on handling of special situations such as intercurrent conditions (illness, stress, or emotional disturbances), an inadequate or skipped insulin dose, inadvertent administration of an increased insulin dose, inadequate food intake, or skipped meals
[see Warnings and Precautions (
5.3)]
.
Inform patients that their ability to concentrate and react may be impaired as a result of hypoglycemia. Advise patients who have frequent hypoglycemia or reduced or absent warning signs of hypoglycemia to use caution when driving or operating machinery.
Advise patients that changes in insulin regimen can predispose to hyperglycemia or hypoglycemia and that changes in insulin regimen should be made under close medical supervision
[see Warnings and Precautions (
5.2)].
Decline in Pulmonary Function
Inform patients that AFREZZA can cause a decline in lung function
[see Warnings and Precautions (
5.4)].
Lung Cancer
Inform patients to promptly report any signs or symptoms potentially related to lung cancer
[see Warnings and Precautions (
5.5)].
Diabetic Ketoacidosis
Instruct patients to carefully monitor their blood glucose during illness, infection, and other risk situations for DKA and to contact their healthcare provider if their blood glucose control worsens
[see Warnings and Precautions (
5.6)].
Hypersensitivity Reactions
Advise patients that hypersensitivity reactions can occur with insulin therapy including AFREZZA. Inform patients on the symptoms of hypersensitivity reactions
[see Warnings and Precautions (
5.7)].
Manufactured by: MannKind Corporation, Danbury, CT 06810
US License No. #2190
© 2016 – 2026 MannKind Corporation
AFREZZA is a registered trademark of MannKind Corporation
Patent: www.mannkindcorp.com/patent-notices