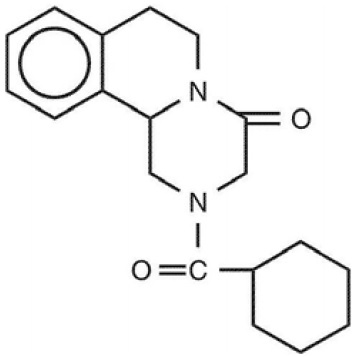
Absorption
After oral administration, 80% of an administered praziquantel dose is absorbed, with maximal serum concentrations of praziquantel achieved 1 to 3 hours after dosing.
Elimination
Following oral administration of praziquantel, the elimination half-life of praziquantel in serum ranges between 0.8 to 1.5 hours.
Metabolism
Praziquantel is rapidly metabolized by the cytochrome P450 enzyme system and undergoes a first pass effect after oral administration of praziquantel.
Excretion
Approximately 80% of an oral dose of praziquantel is excreted in the kidneys, almost exclusively (greater than 99%) in the form of praziquantel metabolites.
Specific Populations
Patients with Hepatic Impairment
The pharmacokinetics of praziquantel were studied in 40 patients with Schistosoma mansoni infections with varying degrees of hepatic impairment (See Table 1). In patients with schistosomiasis, the pharmacokinetic parameters did not differ significantly between those with normal hepatic function (Group 1) and those with mild (Child-Pugh class A) hepatic impairment. However, in patients with moderate-to-severe hepatic impairment (Child-Pugh class B and C), praziquantel half-life, Cmax, and AUC increased progressively with the degree of hepatic impairment. In Child-Pugh class B, the increases in mean half-life, Cmax, and AUC relative to Group 1 were 1.58-fold, 1.76-fold, and 3.55-fold, respectively. The corresponding increases in Child-Pugh class C patients were 2.82-fold, 4.29-fold, and 15-fold for half-life, Cmax, and AUC.
Table 1: Pharmacokinetic parameters of praziquantel in four groups of patients with varying degrees of liver function following administration of 40 mg/kg of praziquantel tablets under fasting conditions.
Patient Group | Half-life (hr) | Tmax (hr) | Cmax (mcg/mL) | AUC (mcg/mL* hr) |
Normal hepatic function (Group 1) | 2.99 ± 1.28 | 1.48 ± 0.74 | 0.83 ± 0.52 | 3.02 ± 0.59 |
Child-Pugh A (Group 2) | 4.66 ± 2.77 | 1.37 ± 0.61 | 0.93 ± 0.58 | 3.87 ± 2.44 |
Child-Pugh B (Group 3) | 4.74 ± 2.16a | 2.21 ± 0.78a,b | 1.47 ± 0.74a,b | 10.72 ± 5.53a,b |
Child-Pugh C (Group 4) | 8.45 ± 2.62a,b,c | 3.2 ± 1.05a,b,c | 3.57 ± 1.30a,b,c | 45.35 ± 17.50a,b,c |
a) p<0.05 compared to Group 1
b) p<0.05 compared to Group 2
c) p<0.05 compared to Group 3
Patients with Renal Impairment
Excretion of praziquantel following oral administration of praziquantel might be delayed in patients with impaired renal function, but accumulation of unchanged drug would not be expected.
Drug Interaction Studies
Rifampin (Strong CYP 3A Inducer)
In a crossover study with a 2-week washout period, 10 healthy subjects ingested a single 40 mg/kg oral dose of praziquantel following pre-treatment with oral rifampin (600 mg daily for 5 days). Plasma praziquantel concentrations were undetectable in 7 out of 10 subjects. When a single 40 mg/kg oral dose of praziquantel was administered to these same healthy subjects two weeks after discontinuation of rifampin, the mean praziquantel AUC and Cmax were 23% and 35% lower, respectively, then when praziquantel was given alone.
Efavirenz (Moderate CYP 3A Inducer)
In a crossover study, 20 healthy subjects ingested a single 40 mg/kg oral dose of praziquantel following pretreatment with oral efavirenz (400 mg daily for 13 days). Oral efavirenz reduced the mean praziquantel AUC and Cmax by 77% (95% confidence interval: 38% to 91%) and 79% (95% confidence interval: 41% to 92%), respectively, when coadministered with praziquantel compared to praziquantel given alone.