In GALLIUM, more Grade 3 to 5 infections were reported in the recipients of GAZYVA and bendamustine (117/410 patients, 29%) as compared to GAZYVA plus CHOP or CVP (43/281 patients, 15%). More fatal infections were reported in patients treated with GAZYVA and bendamustine (3%), as compared to GAZYVA plus CHOP or CVP (< 1%), including during the monotherapy phase and after completion of treatment.
Do not administer GAZYVA to patients with an active infection. Patients with a history of recurring or chronic infections may be at increased risk of infection. In patients who develop a serious infection while receiving GAZYVA, immediately discontinue GAZYVA and institute appropriate treatment. Consider the risk and benefit of resuming treatment with GAZYVA following resolution of serious infections.
The data below are based on a safety population of 773 previously untreated patients with CLL in the CLL11 study. Patients were treated with chlorambucil alone, GAZYVA in combination with chlorambucil, or rituximab product in combination with chlorambucil. The Stage 1 analysis compared GAZYVA in combination with chlorambucil vs. chlorambucil alone and Stage 2 compared GAZYVA in combination with chlorambucil vs. rituximab product in combination with chlorambucil. Adverse reactions rates and laboratory abnormalities from the Stage 2 phase are presented below and are consistent with the rates in Stage 1. In addition to the adverse reactions observed in Stage 2, in Stage 1, back pain (5% vs. 2%), anemia (12% vs. 10%) and cough (10% vs. 7%) were observed at a higher incidence in the GAZYVA treated patients. The incidence of Grade 3 to 4 back pain (< 1% vs. 0%), cough (0% vs. < 1%) and anemia (5% vs. 4%) was similar in both treatment arms. With regard to laboratory abnormalities, in Stage 1 hyperkalemia (33% vs. 18%), creatinine increased (30% vs. 20%) and alkaline phosphatase increased (18% vs. 11%) were observed at a higher incidence in patients treated with GAZYVA with similar incidences of Grade 3 to 4 abnormalities between the two arms.
Patients received three 1,000 mg doses of GAZYVA on the first cycle and a single dose of 1,000 mg once every 28 days for 5 additional cycles in combination with chlorambucil (6 cycles of 28 days each in total). In the last 140 patients enrolled, the first dose of GAZYVA was split between day 1 (100 mg) and day 2 (900 mg) [see Dosage and Administration (2.2)]. In total, 81% of patients received all 6 cycles (of 28 days each) of GAZYVA-based therapy.
Adverse reactions in ≥ 10% of patients in the GAZYVA containing arm were infusion-related reactions, neutropenia, thrombocytopenia, and diarrhea. The most common Grade 3 to 4 adverse reactions (incidence ≥ 10%) in the GAZYVA containing arm were neutropenia, infusion-related reactions, and thrombocytopenia.
The GADOLIN study evaluated safety in 407 patients with relapsed or refractory NHL, including FL (81%), small lymphocytic lymphoma and marginal zone lymphoma (a disease for which GAZYVA is not indicated), who did not respond to or progressed within 6 months of treatment with rituximab product or a rituximab product-containing regimen. In the population of patients with FL, the profile of adverse reactions was consistent with the overall NHL population. Patients received either GAZYVA in combination with bendamustine (204 patients), followed by GAZYVA monotherapy in patients that had not progressed, or bendamustine alone (203 patients).
Patients randomized to the GAZYVA + bendamustine arm received three weekly 1,000 mg doses of GAZYVA in the first cycle and a single dose of 1,000 mg once every 28 days for 5 additional cycles, in combination with bendamustine 90 mg/m2 intravenously on Days 1 and 2 in all 6 cycles. Patients who did not progress on the combination received a single 1,000 mg dose of GAZYVA monotherapy every two months until progression or for a maximum of two years. The control arm received bendamustine 120 mg/m2 on Days 1 and 2 of each cycle for 6 cycles, with a cycle length of 28 days. In the GAZYVA arm, 78% of patients received 6 cycles of bendamustine and 82% received their full 6 cycles of GAZYVA; 72 (46%) of the 158 patients who began GAZYVA monotherapy received all planned doses. In the control arm, 72% of patients received 6 cycles of bendamustine.
Serious adverse reactions occurred in 45% of the GAZYVA arm and 37% of the bendamustine-only arm. Fatal adverse reactions within 90 days of treatment occurred in 3.4% and 2.5%, respectively. During treatment and follow-up combined, fatal adverse reactions occurred in 10% of GAZYVA recipients and in 7.4% of recipients of bendamustine alone, with infection and second primary malignancies being the leading causes.
Dose modification due to adverse reactions occurred in 50% of the GAZYVA arm and 42% of the control arm, and discontinuation of any study drug due to adverse reactions occurred in 20% and 17%, respectively.
Other clinically relevant adverse reactions (incidence < 10% and ≥ 2% greater in the GAZYVA arm) included:
- Blood and lymphatic system disorders: febrile neutropenia (6%)
- Infection: sepsis (7%)
During GAZYVA monotherapy (158 patients), adverse reactions in ≥ 10% of patients included upper and lower respiratory tract infections, cough, neutropenia, musculoskeletal pain, fatigue, diarrhea, rash, and urinary tract infection.
Table 11 presents selected new or worsening laboratory abnormalities in the GADOLIN trial.
Table 11 New or Worsening Laboratory Abnormalities (Incidence ≥ 10% and ≥ 2% Greater in the GAZYVA ArmTwo percent difference in either any-grade or Grade 3 to 4 laboratory abnormalities.
) in Patients with Relapsed or Refractory NHL (GADOLIN)| Laboratory Abnormalities | GAZYVA + Bendamustine followed by GAZYVA monotherapy
n = 204 | Bendamustine
n = 203 |
|---|
| All Grades % | Grades 3 to 4 % | All Grades % | Grades 3 to 4 % |
|---|
| Hematology |
| Lymphopenia | 97 | 92 | 96 | 84 |
| Leukopenia | 84 | 47 | 87 | 34 |
| Neutropenia | 76 | 53 | 75 | 42 |
| Chemistry |
| Hypophosphatemia | 41 | 8 | 38 | 7 |
| Hypocalcemia | 39 | 3 | 24 | 1 |
| ALT/SGPT increased | 36 | 2 | 31 | 3 |
| Alkaline phosphatase increased | 27 | 0 | 23 | 0 |
| Hyperbilirubinemia | 21 | 2 | 17 | 2 |
| Hyperkalemia | 20 | 3 | 18 | 0 |
In the GAZYVA monotherapy phase, new or worsening grade 3 or 4 abnormalities included neutropenia in 25% of patients (Grade 4, 10%) and lymphopenia in 23% (Grade 4, 5%).
GALLIUM Study
A randomized, open-label multicenter trial (GALLIUM) evaluated the safety of GAZYVA as compared to rituximab product in 1385 patients with previously untreated follicular lymphoma (86%) or marginal zone lymphoma (14%). Patients received chemotherapy (bendamustine, CHOP, or CVP) combined with either GAZYVA (691 patients) or rituximab product (694 patients), followed in responding patients by GAZYVA or rituximab product monotherapy every two months until disease progression or for a maximum of two years. The study excluded patients having an absolute neutrophil count (ANC) < 1500 / µL, platelets < 75,000 / µL, CLcr < 40 mL/min and, unless attributable to lymphoma, hepatic transaminases > 2.5 × upper limit of normal.
The median age was 60 (range: 23-88), 47% were male, 82% were white, and 97% had an ECOG performance status of 0 or 1. The chemotherapy was bendamustine in 59%, CHOP in 31% and CVP in 10% of patients. Following combination therapy, 624 patients (90%) in the GAZYVA arm and 612 patients (88%) in the rituximab product arm received monotherapy.
Serious adverse reactions occurred in 50% of patients on the GAZYVA arm and 43% of patients on the rituximab product arm. Fatal adverse reactions were reported during treatment in 3% in the GAZYVA arm and 2% in the rituximab product arm, most often from infections in the GAZYVA arm. During treatment and follow-up combined, fatal adverse reactions were reported in 5% of the GAZYVA arm and 4% of the rituximab product arm, with infections and second malignancies being leading causes. In the GAZYVA arm, fatal infections occurred in 2% of patients compared to < 1% in the rituximab product arm.
During combination therapy, 93% of patients received all treatment cycles in the GAZYVA arm, and 92% received all treatment cycles in the rituximab product arm. Of the responding patients who began monotherapy with GAZYVA or rituximab product, 76% and 73%, respectively, completed the full course. Dose modification due to adverse reactions occurred in 74% of the GAZYVA arm and 63% of the rituximab product arm throughout study treatment, and discontinuation of any study drug due to adverse reactions occurred in 18% and 15%, respectively.
Throughout treatment and follow-up, the most common adverse reactions (incidence ≥ 20%) observed at least 2% more in the GAZYVA arm included infusion-related reactions, neutropenia, upper respiratory tract infections, constipation and diarrhea (Table 12). Neutropenia, infusion-related reactions, febrile neutropenia and thrombocytopenia were the most common Grade 3 to 5 adverse reactions (incidence ≥ 5%) observed more frequently in the GAZYVA arm.
Table 12 Adverse Reactions (Incidence ≥ 10% and ≥ 2% Greater in the GAZYVA Arm) in Patients with Previously Untreated NHL (GALLIUM)Body System
Adverse Reactions Includes adverse reactions reported throughout study treatment and follow-up. , Includes grouped terms. | GAZYVA + chemotherapy followed by GAZYVA monotherapy
n = 691 | Rituximab product + chemotherapy followed by rituximab product monotherapy
n = 694 |
|---|
All Grades
% | Grades 3 to 5
% | All Grades
% | Grades 3 to 5
% |
|---|
| Injury, Poisoning and Procedural Complications |
| Infusion-Related Reaction Except where noted, individual events that meet the definition of "infusion-related reaction" are excluded from Table 12 above, as they are already included in the grouped term "Infusion-Related Reaction". The most common individual terms within the grouped term "Infusion-Related Reaction" in decreasing order of frequency are nausea, chills, pyrexia and vomiting. | 72 | 12 | 60 | 8 |
| Blood and Lymphatic System Disorders |
| Neutropenia Includes adverse reactions reported as infusion-related reactions. | 53 | 49 | 47 | 41 |
| Thrombocytopenia | 14 | 7 | 8 | 3 |
| Infections and Infestations |
| Upper Respiratory Tract Infection | 50 | 3 | 43 | 1 |
| Herpesvirus Infection | 18 | 3 | 14 | 1 |
| Pneumonia | 14 | 7 | 12 | 6 |
| Respiratory, Thoracic and Mediastinal Disorders |
| Cough | 35 | < 1 | 28 | < 1 |
| Gastrointestinal Disorders |
| Constipation | 32 | < 1 | 29 | < 1 |
| Diarrhea | 30 | 3 | 26 | 2 |
| Nervous System Disorders |
| Headache | 18 | < 1 | 15 | < 1 |
| Musculoskeletal and Connective Tissue Disorders |
| Arthralgia | 16 | 0 | 14 | < 1 |
| Psychiatric Disorders | | | | |
| Insomnia | 15 | < 1 | 12 | < 1 |
| Metabolism and Nutrition Disorders |
| Decreased Appetite | 14 | < 1 | 12 | < 1 |
| Skin and Subcutaneous Tissue Disorders |
| Pruritus | 11 | < 1 | 9 | 0 |
Infusion-related reactions are defined as any related adverse reaction that occurred during or within 24 hours of infusion.
Neutropenia includes neutropenia, agranulocytosis, granulocytopenia, and neutrophil count decreased.
Febrile neutropenia includes febrile neutropenia, neutropenic infection, neutropenic sepsis, and febrile bone marrow aplasia.
Thrombocytopenia includes thrombocytopenia and platelet count decreased.
Upper respiratory tract infection includes upper respiratory tract congestion, upper respiratory tract inflammation, upper respiratory tract infection, rhinovirus infection, and all terms containing: laryngitis, nasopharyngitis, pharyngitis, rhinitis, tonsillitis, and sinusitis with the exception of sinobronchitis.
Herpesvirus infection includes all terms containing "herpes" or "varicella."
Pneumonia includes all terms containing "pneumonia," bacterial, pneumonia haemophilus, pneumonia pneumococcal, pneumonia fungal, pneumocystis jirovecii infection, lung infection, and lung infiltration.
Diarrhea includes diarrhea, defecation urgency, frequent bowel movement, and all terms containing "gastroenteritis".
Headache includes all terms containing "headache" and migraine.
Insomnia includes all terms containing "insomnia" and sleep disorder.
Pruritus includes pruritus and pruritus generalized.
During the monotherapy period, the common adverse reactions (incidence ≥ 10%) observed at least 2% more with GAZYVA were upper respiratory tract infection (40%), cough (23%), musculoskeletal pain (20%), neutropenia (19%), and herpesvirus infection (13%).
Table 13 summarizes treatment-emergent laboratory abnormalities during treatment and follow-up. The Grade 3 to 4 abnormalities reported at least 2% more in the GAZYVA arm were lymphopenia, leukopenia, neutropenia, thrombocytopenia, and hyperuricemia. Patients in the GAZYVA arm, as compared to the rituximab product arm, had higher incidences of Grade 4 neutropenia (38% vs. 30%, respectively), Grade 4 lymphopenia (33% vs. 22%), and Grade 4 leukopenia (17% vs. 12%).
Table 13 New or Worsening Laboratory Abnormalities (Incidence ≥ 10% and ≥ 2% Greater in the GAZYVA Arm) in Patients with Previously Untreated NHL (GALLIUM)| Laboratory Abnormalities Includes lab abnormalities, reported throughout treatment and follow-up, that were new or worsening, or worsening from baseline unknown. | GAZYVA+ chemotherapy followed by GAZYVA monotherapy
n = 691 | Rituximab product + chemotherapy followed by rituximab product monotherapy
n = 694 |
|---|
| All Grades % | Grades 3 to 4 % | All Grades % | Grades 3 to 4 % |
|---|
| Hematology |
| Lymphopenia | 97 | 83 | 95 | 67 |
| Leukopenia | 92 | 49 | 89 | 39 |
| Neutropenia | 84 | 59 | 76 | 50 |
| Thrombocytopenia | 68 | 11 | 50 | 4 |
| Chemistry |
| ALT increased | 50 | 3 | 43 | 2 |
| AST increased | 44 | 1 | 41 | 1 |
| Hypophosphatemia | 36 | 5 | 33 | 5 |
| Hypoalbuminemia | 33 | 1 | 25 | 1 |
| Hypoproteinemia | 32 | 0 | 30 | 0 |
| Hypocalcemia | 32 | 1 | 26 | 1 |
| Hyperuricemia | 28 | 28 | 22 | 22 |
| Hyponatremia | 26 | 4 | 20 | 3 |
| Hyperkalemia | 23 | 1 | 17 | 1 |
| Hypernatremia | 16 | < 1 | 13 | 0 |
In the monotherapy phase, new-onset Grade 3 or 4 neutropenia was reported in 21% of patients in the GAZYVA arm (Grade 4, 10%) and 17% of patients in the rituximab product arm (Grade 4, 9%).
GAZELLE Study
GAZELLE (NCT03817853) is a single-arm study designed to characterize the safety of GAZYVA administered as a shortened-duration infusion (approximately 90 minutes) in patients with previously untreated FL. All patients received GAZYVA at the standard infusion rate with premedication during Cycle 1. If no Grade 3 or higher IRR occurred with any infusion during Cycle 1, GAZYVA was administered over approximately 90 minutes in Cycle 2 and subsequent cycles. The primary safety measure was the proportion of patients who experienced Grade 3 or higher IRRs with the 90-minute infusion at Cycle 2. GAZYVA was administered in combination with CHOP, CVP or bendamustine for 6 to 8 cycles (induction), followed by monotherapy for up to 2 years.
Of the 113 patients treated with GAZYVA, 99 (88%) received the 90-minute infusion starting in Cycle 2. In total, 97% of patients who received GAZYVA at either a standard or shorter infusion duration received premedication in Cycle 2. IRRs were observed in 63% of patients throughout induction (including IRRs observed after standard-duration infusion). In cycle 1, 58% of patients developed IRRs with the standard infusion rate (Grade ≥3 IRR, 5%). Of the patients who received the 90-minute infusion, 10% had IRRs of any grade in Cycle 2, with 8% and 2% of patients having a Grade 1 IRR or Grade 2 IRR, respectively. Following Cycle 2, one (1%) patient experienced a Grade 3 IRR, which occurred after the 90-minute infusion at Cycle 5.
Lupus Nephritis
The data below reflects exposure to GAZYVA administered intravenously in patients with ISN/RPS 2003 Class III or IV with or without concomitant Class V lupus nephritis in the REGENCY and NOBILITY studies, up to week 76.
REGENCY (NCT04221477) is a Phase III study which included 136 patients treated with GAZYVA plus standard therapy consisting of mycophenolate mofetil (MMF) and corticosteroids [see Clinical Studies (14.3)].
NOBILITY (NCT02550652) is a Phase II study which included 64 patients treated with GAZYVA plus standard therapy consisting of MMF/mycophenolic acid (MPA) and corticosteroids.
The most common adverse reactions (incidence ≥ 5% in the GAZYVA arm) were upper respiratory tract infection, COVID-19, urinary tract infection, bronchitis, pneumonia, infusion related reactions and neutropenia.
The most common serious adverse reactions in the GAZYVA arm were: COVID-19 (11 patients [5.5%]), pneumonia (9 patients [4.5%]), neutropenia (7 patients [3.5%]), urinary tract infections (5 patients [2.5%]) and infusion-related reactions (1 patient [0.5%]). No serious adverse reactions were reported for bronchitis, herpes simplex and upper respiratory tract infections. Two fatal adverse reactions of COVID-19 were reported in the GAZYVA arm.
Adverse reaction rates are presented in Table 14.
Table 14 Adverse Reactions in Adults with Active Lupus Nephritis Treated with GAZYVA Versus Placebo (≥ 2% Greater in the GAZYVA Arm) in REGENCY and NOBILITY StudiesBody System
Adverse Reactions | GAZYVA + standard therapy
n = 200 | Placebo + standard therapy
n = 193 |
|---|
All Grades
(%) | Grades 3-5(%) | All Grades
(%) | Grades 3-5
(%) |
|---|
| Infections and Infestations |
|---|
| Upper Respiratory Tract Infection | 29 | 0 | 24 | 0 |
| COVID-19 | 23 | 5 Includes 2 fatal events in the GAZYVA arm and 1 fatal event in the placebo arm | 16 | 0.5 |
| Urinary Tract Infection | 21 | 3 | 18 | 4 |
| Bronchitis | 14 | 0 | 8 | 0.5 |
| Pneumonia | 10 | 2 | 6 | 2 |
| Herpes Simplex | 3 | 0 | 0 | 0 |
| Injury, Poisoning and Procedural Complications |
| Infusion Related Reaction | 14 | 2 | 10 | 0.5 |
| Blood and Lymphatic System Disorders |
| Neutropenia | 14 | 7 | 6 | 0.5 |
Childhood-Onset Idiopathic Nephrotic Syndrome
The data described in Table 15 reflect exposure to GAZYVA administered intravenously in patients with childhood-onset INS in the INSHORE study (NCT05627557). In INSHORE, 44 patients received GAZYVA, of which 41 patients were 4 to 18 years of age [see Clinical Studies (14.4)]. Adverse event severity was graded as Grades 1 to 5 defined as mild (1), moderate (2), severe (3), life-threatening (4), and fatal (5).
The most common adverse reactions (incidence ≥ 10% in the GAZYVA arm) are shown in Table 15. There were no Grade 5 adverse reactions in INSHORE.
Table 15 Adverse Reactions in Patients with Childhood-Onset Idiopathic Nephrotic Syndrome Treated with GAZYVA Versus Mycophenolate Mofetil (≥ 10% in the GAZYVA Arm) in the INSHORE studyBody System
Adverse Drug Reactions | GAZYVA
n = 44 | MMF
n = 41 |
|---|
All Grades
(%) | Grades 3-4
(%) | All Grades
(%) | Grades 3-4
(%) |
|---|
| NA: Not Applicable |
| Infections and Infestations |
| Upper Respiratory Tract Infection | 59 | 2 | 63 | 2 |
| Ear Infection | 32 | 2 | 15 | 0 |
| Pneumonia | 25 | 9 | 5 | 0 |
| Influenza | 20 | 0 | 10 | 0 |
| Bronchitis | 14 | 2 | 5 | 0 |
| COVID-19 | 14 | 0 | 12 | 0 |
| Conjunctivitis | 14 | 0 | 7 | 0 |
| Urinary Tract Infection | 11 | 0 | 0 | 0 |
| Injury, Poisoning and Procedural Complications |
| Infusion Related Reaction | 36 | 0 | NA | NA |
| Blood and Lymphatic System Disorders |
| Neutropenia Total neutrophil counts < 1000 cells/µL occurred in 8 (18%) patients in the GAZYVA arm compared to 2 (5%) in the MMF arm. | 18 | 16 | 2 | 2 |
Specific Adverse Reactions
Infusion-Related Reactions
Chronic Lymphocytic Leukemia
The incidence of IRRs in the CLL11 study was 65% with the first infusion of GAZYVA. The incidence of Grade 3 or 4 IRRs was 20% with 7% of patients discontinuing therapy. The incidence of reactions with subsequent infusions was 3% with the second 1,000 mg and < 1% thereafter. No Grade 3 or 4 IRRs were reported beyond the first 1,000 mg infused.
Of the first 53 patients receiving GAZYVA in CLL11, 47 (89%) experienced an IRR. After this experience, study protocol modifications were made to require pre-medication with a corticosteroid, antihistamine, and acetaminophen. The first dose was also divided into two infusions (100 mg on day 1 and 900 mg on day 2). For the 140 patients for whom these mitigation measures were implemented, 74 patients (53%) experienced a reaction with the first 1,000 mg (64 patients on day 1, 3 patients on day 2, and 7 patients on both days) and < 3% thereafter [see Dosage and Administration (2.2)].
Non-Hodgkin Lymphoma
Overall, 67% of patients in the GADOLIN study experienced an IRR (all grades) during treatment with GAZYVA in combination with bendamustine. The incidence of Grade 3 to 4 IRRs in GADOLIN was 11%. In Cycle 1, the incidence of IRRs (all grades) was 53% in patients receiving GAZYVA in combination with bendamustine of which 34 (9%) were Grade 3 to 4 in severity. In patients receiving GAZYVA in combination with bendamustine, the incidence of IRRs was highest on Day 1 (37%), and gradually decreased on Days 2, 8 and 15 (23%, 6% and 4%, respectively).
During Cycle 2, the incidence of IRRs was 24% in patients receiving GAZYVA in combination with bendamustine and decreased with subsequent cycles.
During GAZYVA monotherapy in GADOLIN, IRRs (all grades) were observed in 8% of patients. One Grade 3 and no Grade 4 IRRs were reported during GAZYVA monotherapy.
Overall, 2% of patients in GADOLIN experienced an IRR leading to discontinuation of GAZYVA.
In GALLIUM, 72% of patients in the GAZYVA treated arm experienced an IRR (all grades). The incidence of Grade 3 to 4 IRRs for these patients was 12%. In Cycle 1, the incidence of IRRs (all grades) was 62% in the GAZYVA treated arm with Grade 3 to 4 IRRs reported in 10%. The incidence of IRRs (all grades) was highest on Day 1 (60%) and decreased on Days 8 and 15 (9% and 6%, respectively).
During Cycle 2, the incidence of IRRs (all grades) in the GAZYVA treated arm was 13% and decreased with subsequent cycles.
During GAZYVA monotherapy treatment in GALLIUM, IRRs (all grades) were observed in 9% of patients.
Overall, 1% of patients in GALLIUM experienced an IRR leading to discontinuation of GAZYVA.
In GAZELLE, 10% of patients with FL experienced IRRs of any grade at Cycle 2 when GAZYVA was administered over approximately 90 minutes.
Lupus Nephritis
In the pooled REGENCY and NOBILITY studies, infusion-related reactions (IRRs) were reported in 14% of patients in the GAZYVA arm versus 10% of patients in the placebo arm. IRRs in both arms were predominantly Grade 1-2 and occurred during or after the first infusion. Grade 3-4 IRRs were reported in 1.5% of patients in the GAZYVA arm vs 0.5% of patients in the placebo arm. All Grade 3-4 events occurred during or after either the first or second infusion.
The incidence of IRRs in the GAZYVA arm decreased from 11% during the first infusion to 3% during the second infusion, decreasing further with subsequent infusions to 0.5% during the sixth infusion. The severity of IRRs in the GAZYVA arm also decreased with subsequent infusions with 1% patients reporting Grade 3-4 IRRs during the first infusion and 0.5% patients reporting Grade 3-4 IRRs during the second infusion. In subsequent infusions all IRRs were Grade 1-2 in severity. No Grade 5 IRRs were reported [see Warnings and Precautions (5.3)].
In the REGENCY study, most common IRR signs or symptoms included headache, nausea and vomiting. In the NOBILITY study, the most common IRR symptoms were pyrexia and tachycardia.
Childhood-Onset Idiopathic Nephrotic Syndrome
In the INSHORE study, all IRRs were Grade 1-2 (mild or moderate) and predominately occurred during/after the first infusion [see Table 15 and Warnings and Precautions (5.3)]. IRRs requiring GAZYVA infusion interruption, rate reduction, or stoppage occurred in 23% of patients. The most common IRR signs or symptoms included pyrexia, vomiting and nausea.
Neutropenia
Chronic Lymphocytic Leukemia
The incidence of neutropenia reported as an adverse reaction in CLL11 was 38% in the GAZYVA treated arm and 32% in the rituximab product treated arm, with the incidence of serious adverse reactions being 1% and < 1%, respectively (Table 9). Cases of late-onset neutropenia (occurring 28 days after completion of treatment or later) were 16% in the GAZYVA treated arm and 12% in the rituximab product treated arm.
Non-Hodgkin Lymphoma
The incidence of neutropenia in GADOLIN was higher in the GAZYVA plus bendamustine arm (37%) compared to the arm treated with bendamustine alone (30%). Cases of prolonged neutropenia (3%) and late onset neutropenia (8%) were also reported in the GAZYVA plus bendamustine arm. The incidence of neutropenia was higher during treatment with GAZYVA in combination with bendamustine (30%) compared to the GAZYVA monotherapy treatment phase (13%).
The incidence of neutropenia in GALLIUM was higher in the GAZYVA treated arm (53%) compared to the rituximab product treated arm (47%). Cases of prolonged neutropenia (1%) and late onset neutropenia (4%) were also reported in the GAZYVA treated arm. The incidence of neutropenia was higher during treatment with GAZYVA in combination with chemotherapy (45%) compared to the GAZYVA monotherapy treatment phase (20%).
Lupus Nephritis
In the pooled REGENCY and NOBILITY studies, neutropenia and related adverse reactions (i.e., leukopenia, lymphopenia, lymphocyte count decreased, febrile neutropenia, and neutrophil count decreased) were reported in 14% of patients in the GAZYVA arm versus 6% of patients in the placebo arm. Grade 3-4 neutropenia was reported in 7% of patients treated with GAZYVA versus 0.5% of patients in the placebo arm. Neutropenia and related adverse reactions resolved/improved spontaneously or with use of granulocyte colony-stimulating factor in 96% of patients [see Warnings and Precautions (5.7)].
Childhood-Onset Idiopathic Nephrotic Syndrome
In the INSHORE study, the majority of neutropenia and related adverse reactions (i.e., neutrophil count decreased and agranulocytosis) in both arms were Grade 3 or 4 (severe or life-threatening or due to neutrophil count < 1000 cells/µL; see Table 15). The majority of neutropenia and related events resolved/improved spontaneously and one event resolved with the use of granulocyte colony-stimulating factor [see Warnings and Precautions (5.7)].
Infection
Chronic Lymphocytic Leukemia
The incidence of infections was similar between GAZYVA and rituximab product treated arms. Thirty-eight percent of patients in the GAZYVA treated arm and 37% in the rituximab product treated arm experienced an infection, with Grade 3 to 4 rates being 11% and 13%, respectively. Fatal events were reported in 1% of patients in both arms.
Non-Hodgkin Lymphoma
The incidence of infection in GADOLIN was 68% in the GAZYVA plus bendamustine arm and 59% in the bendamustine arm, with Grade 3 to 4 events reported in 20% and 16%, respectively. Fatal events were reported in 3% of patients in the GAZYVA plus bendamustine arm and 3% in the bendamustine arm.
The incidence of infections in GALLIUM was 82% in the GAZYVA treated arm and 73% in the rituximab product treated arm, with Grade 3 to 4 events reported in 21% and 17%, respectively. In the GAZYVA arm, fatal infections occurred in 2% of patients compared to <1% in the rituximab product arm.
The incidence of Grade 3 to 4 infections in the GAZYVA and rituximab product treated arms was lower in patients receiving GCSF prophylaxis (14%; 16%) compared with patients not receiving GCSF prophylaxis (24%; 18%). The incidence of fatal infections in patients receiving GCSF prophylaxis in the GAZYVA and rituximab product treated arms was 2% and 0%, respectively, and was 2% and < 1% in patients not receiving GCSF prophylaxis.
Lupus Nephritis
In the pooled REGENCY and NOBILITY studies, infections were reported in 72% of patients in the GAZYVA arm versus 62% of patients in the placebo arm. The most frequently reported infections were upper and lower respiratory tract infections. Grade 3-5 infections were reported in 11% of patients in the GAZYVA arm versus 10% of patients in the placebo arm. Fatal infection events were reported in 1% of patients in the GAZYVA arm versus 0.5% of patients in the placebo arm [see Warnings and Precautions (5.6)].
Childhood-Onset Idiopathic Nephrotic Syndrome
In the INSHORE study, infections were reported in 89% of patients in the GAZYVA arm compared to 76% in the MMF arm. The most frequently reported infections are shown in Table 15 [see Warnings and Precautions (5.6)].
Thrombocytopenia
Chronic Lymphocytic Leukemia
The overall incidence of thrombocytopenia reported as an adverse reaction was higher in the GAZYVA treated arm (14%) compared to the rituximab product treated arm (7%), with the incidence of Grade 3 to 4 events being 10% and 3%, respectively (Table 8). The difference in incidences between the treatment arms is driven by events occurring during the first cycle. The incidence of thrombocytopenia (all grades) in the first cycle was 11% in the GAZYVA and 3% in the rituximab product treated arms, with Grade 3 to 4 rates being 8% and 2%, respectively. Four percent of patients in the GAZYVA treated arm experienced acute thrombocytopenia (occurring within 24 hours after the GAZYVA infusion).
The overall incidence of hemorrhagic events and the number of fatal hemorrhagic events were similar between the treatment arms, with 3 in the rituximab product and 4 in the GAZYVA treated arms. However, all fatal hemorrhagic events in patients treated with GAZYVA occurred in Cycle 1.
Non-Hodgkin Lymphoma
The incidence of thrombocytopenia in GADOLIN was lower in the GAZYVA plus bendamustine arm (15%) compared to the arm treated with bendamustine alone (25%). The incidence of hemorrhagic events in GAZYVA plus bendamustine treated patients compared to bendamustine alone was 12% and 11%, respectively. Grade 3 to 4 hemorrhagic events were similar in both treatment arms (4% in the GAZYVA plus bendamustine arm and 2% in the bendamustine arm).
In GALLIUM, thrombocytopenia was reported as an adverse reaction in 14% of the GAZYVA treated arm and 8% of the rituximab product treated arm, with the incidence of Grade 3 to 4 events being 7% and 3%, respectively. The difference in incidences between the treatment arms is driven by events occurring during the first cycle. The incidence of thrombocytopenia (all grades) in the first cycle was 9% in the GAZYVA and 3% in the rituximab product treated arms, with Grade 3 to 4 rates being 5% and 1%, respectively. In GALLIUM, both treatment arms had a 12% overall incidence of hemorrhagic events and a < 1% incidence of fatal hemorrhagic events.
Disseminated Intravascular Coagulation
In GALLIUM, DIC was reported as an adverse reaction in 0.3% of the GAZYVA treated patients. All events occurred within 1-2 days after the first infusion.
Tumor Lysis Syndrome
The incidence of Grade 3 or 4 tumor lysis syndrome in GAZYVA treated patients was 2% in CLL11, 0.5% in GADOLIN and 0.9% in GALLIUM.
Musculoskeletal Disorders
Chronic Lymphocytic Leukemia
Adverse reactions related to musculoskeletal disorders (all events from the body system), including pain, have been reported in the GAZYVA treated arm with higher incidence than in the rituximab product treated arm (18% vs. 15%).
Non-Hodgkin Lymphoma
In GADOLIN, adverse reactions related to musculoskeletal disorders (all events from the body system), including pain, have been reported in the GAZYVA plus bendamustine treated arm with higher incidence than in the bendamustine alone arm (44% vs. 30%).
In GALLIUM, musculoskeletal disorders were reported in 54% of patients in the GAZYVA treated arm and 49% of patients in the rituximab product treated arm.
Liver Enzyme Elevations
Hepatic enzyme elevations have occurred in CLL patients who received GAZYVA in clinical trials and had normal baseline hepatic enzyme levels (AST, ALT and ALP). The events occurred most frequently within 24–48 hours of the first infusion. In some patients, elevations in liver enzymes were observed concurrently with IRRs or tumor lysis syndrome. In the CLL11 study, there was no clinically meaningful difference in overall hepatotoxicity adverse reactions between all arms (4% of patients in the GAZYVA treated arm). Medications commonly used to prevent IRRs (e.g., acetaminophen) may also be implicated in these events. Monitor liver function tests during treatment, especially during the first cycle. Consider treatment interruption or discontinuation for hepatotoxicity.
Gastrointestinal Perforation
Cases of gastrointestinal perforation have been reported in patients receiving GAZYVA, mainly in NHL.
Worsening of Pre-existing Cardiac Conditions
Fatal cardiac events have been reported in patients treated with GAZYVA.
Risk Summary
Based on findings from animal studies and its mechanism of action, GAZYVA can cause fetal B-cell depletion [see Clinical Pharmacology (12.1)]. There are no data with GAZYVA use in pregnant women to inform a drug-associated risk. Monoclonal antibodies are transferred across the placenta. In animal reproduction studies, weekly intravenous administration of obinutuzumab to pregnant cynomolgus monkeys from day 20 of pregnancy until parturition which includes the period of organogenesis at doses with exposures up to 2.4 times the exposure at the clinical dose of 1,000 mg monthly produced opportunistic infections and immune complex mediated hypersensitivity reactions. No embryo-toxic or teratogenic effects were observed in the monkeys (see Data). Advise pregnant women of the potential risk to the fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown; however, the estimated background risk in the U.S. general population of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
Pregnant women with systemic lupus erythematosus (SLE) are at increased risk of adverse pregnancy outcomes, including worsening of the underlying disease, premature birth, miscarriage, and intrauterine growth restriction. Maternal LN increases the risk of hypertension and preeclampsia/eclampsia. Passage of maternal autoantibodies across the placenta may result in adverse neonatal outcomes, including neonatal lupus and congenital heart block.
Fetal/Neonatal Adverse Reactions
GAZYVA is likely to cause fetal B-cell depletion (see Data). Avoid administering live vaccines to neonates and infants exposed to GAZYVA in utero until B-cell recovery occurs [see Warnings and Precautions (5.11), Use in Specific Populations (8.4) and Clinical Pharmacology (12.2)].
Data
Animal Data
In a pre- and post-natal development study, pregnant cynomolgus monkeys received weekly intravenous doses of 25 or 50 mg/kg obinutuzumab from day 20 of pregnancy until parturition, which includes the period of organogenesis. The high dose results in an exposure (AUC) that is 2.4 times the exposure in patients with CLL at the recommended label dose. There were no embryo-toxic or teratogenic effects in animals. Secondary opportunistic infections, immune complex mediated hypersensitivity reactions, or a combination of both were observed in exposed dams. When first measured on day 28 postpartum, obinutuzumab was detected in offspring at levels in the range of maternal serum levels on the same day, and B-cells were completely depleted. The B-cell counts returned to normal levels, and immunologic function was restored within 6 months after birth.
Risk Summary
There is no information regarding the presence of GAZYVA in human milk, the effects on the breastfed child, or the effects on milk production. However, low levels of obinutuzumab were present in the milk of lactating cynomolgus monkeys [see Data]. Human IgG is known to be present in human milk. Because of the potential of serious adverse reactions in the breastfed child, advise women not to breastfeed during treatment with GAZYVA and for 6 months after the last dose.
Data
Obinutuzumab was measured in the milk of lactating cynomolgus monkeys on day 28 postpartum after weekly intravenous administration from day 20 of pregnancy until parturition. Concentrations in milk were approximately 0.04% and 0.13% of concentrations in maternal serum in the 25 and 50 mg/kg groups, respectively.
GAZYVA can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with GAZYVA and for 6 months after the last dose.
Chronic Lymphocytic Leukemia
Of 336 patients with previously untreated CLL who received GAZYVA in combination with chlorambucil, 81% were 65 years and older, while 46% were 75 and older. Of the patients 75 years and older, 46% experienced serious adverse reactions and 7% experienced adverse reactions leading to death. Of the patients younger than 75, 33% experienced a serious adverse reaction and 2% an adverse reaction leading to death. No significant differences in efficacy were observed between younger and older patients [see Clinical Studies (14.1)].
Non-Hodgkin Lymphoma
Of 204 patients in GADOLIN with relapsed or refractory NHL treated with GAZYVA plus bendamustine, 44% were 65 and over, while 14% were 75 and over. In patients 65 and over, 55% of patients experienced serious adverse reactions and 28% experienced adverse reactions leading to treatment withdrawal while in patients under 65, 37% and 14% experienced serious adverse reactions and adverse reactions leading to treatment withdrawal, respectively. No clinically meaningful differences in efficacy were observed between these patients and younger patients in GADOLIN.
Of the 691 patients in GALLIUM treated with GAZYVA plus chemotherapy as first-line therapy, 33% were 65 and over, while 7% were 75 and over. Of patients 65 and over, 63% experienced serious adverse reactions and 26% experienced adverse reactions leading to treatment withdrawal, while in patients under 65, 43% experienced serious adverse reactions and 13% had an adverse reaction leading to treatment withdrawal. No clinically meaningful differences in efficacy were observed between these patients and younger patients in GALLIUM.
Lupus Nephritis and Childhood-Onset Idiopathic Nephrotic Syndrome
Clinical studies of GAZYVA in patients with active LN or childhood-onset INS did not include sufficient numbers of patients aged 65 years and older (1 patient and 0 patients, respectively) to determine whether they respond differently from younger adult patients.
Chronic Lymphocytic Leukemia
In patients with CLL, GAZYVA caused CD19 B-cell depletion (defined as CD19 B cell counts < 0.07 × 10⁹/L). Initial CD19 B cell recovery was observed in some patients approximately 9 months after the last GAZYVA dose. At 18 months of follow-up, some patients remain B cell depleted.
Although the depletion of B cells in the peripheral blood is a measurable pharmacodynamic effect, it is not directly correlated with the depletion of B-cells in solid organs or in malignant deposits. B cell depletion has not been shown to be directly correlated to clinical response.
Lupus Nephritis
In patients with LN (REGENCY study), total peripheral CD19+ B cell levels below the defined threshold of 10 cells/µl were achieved in 99% of patients treated with GAZYVA by Week 4 after treatment initiation and remained below this threshold in 95% of patients at Week 76.
Reductions in circulating naive B, memory B, and plasmablasts/plasma cells were observed by Week 4 and remained low through Week 76 after treatment initiation.
Treatment with GAZYVA led to improvements in complement (C3 and C4) and anti-double-stranded DNA antibodies (anti-dsDNA) by Week 4 and Week 12, respectively. These changes were sustained through Week 76.
In patients with low C3 at baseline, normalization of C3 levels occurred in 49% (by Week 12) and in 62% (by Week 76) of patients receiving GAZYVA compared to 33% and 29%, respectively, in the placebo group. In patients with low C4 at baseline, normalization of C4 levels occurred in 75% (by Week 12) and in 88% (by Week 76) of patients receiving GAZYVA compared to 55% and 55%, respectively, in the placebo group. Among patients with positive anti-dsDNA at baseline, 32% and 56% of patients treated with GAZYVA seroconverted by Week 4 and Week 76, respectively, compared with 16% and 16% of patients receiving placebo. The clinical relevance of the above mentioned pharmacodynamic biomarkers has not been established.
Childhood-Onset Idiopathic Nephrotic Syndrome
In evaluable patients aged 4 years and older with childhood-onset INS who received GAZYVA in INSHORE, 100% (43 out of 43) were B-cell depleted (defined as CD19+ B cell counts < 10 cells/µL) at Week 4, and 95% (40 out of 42) remained depleted at Week 52. At Week 64, 73% (19 out of 26) remained B-cell depleted, and at Week 76, 36% (8 out of 22) remained depleted.
Mean counts of circulating B-cell subsets such as naïve B cells, memory B cells, and plasmablasts/plasma cells were 0 cells/µL by Week 2 after treatment initiation and remained low (near 0 cells/µL) through Week 52.
Cardiac Electrophysiology
The potential effects of GAZYVA on the QTc interval have not been studied.
Distribution and Elimination
CLL and NHL
The elimination of obinutuzumab is comprised of a linear clearance pathway and a time-dependent non-linear clearance pathway. As GAZYVA treatment progresses, the impact of the time-dependent pathway diminishes in a manner suggesting target-mediated drug disposition (TMDD) and saturation of the TMDD at the end of the treatment cycle at the proposed clinical dosing regimen. The distribution and elimination parameters of obinutuzumab in patients with CLL and NHL are provided in Table 17.
Table 17 Distribution and Elimination Parameters of Obinutuzumab | CLL | NHL |
|---|
| Parameters are presented as geometric mean (% Coefficient of Variation). |
| Distribution |
| Volume of Distribution At steady state. , L | 4.1 (20) | 4.3 (21)
|
| Elimination |
| Terminal Half-life, days | 25.5 (48) | 35.3 (35)
|
| Clearance, L/day | 0.11 (53) | 0.08 (41)
|
LN and Childhood-Onset INS
The steady state clearance of obinutuzumab in LN and childhood-onset INS was approximately 0.13 and 0.058 L/day, respectively, with a terminal elimination t1/2 of 22.4 and 29.5 days, respectively.
GAZYVA elimination comprises two parallel pathways, a linear clearance pathway and a non-linear clearance pathway, which changes as a function of time. The time-varying clearance decreases with time with an exponential decay coefficient, likely related to CD20 target reduction and proteinuria improvement over time in patients with elevated baseline proteinuria, and a time-independent clearance related to the endogenous catabolic processes of IgG.
Specific Populations
CLL and NHL
Age (median [range]: 63 [22, 89] years) and baseline creatinine clearance (CLcr) (median [range] 84 [22, > 120] mL/min) did not affect the pharmacokinetics of GAZYVA. In patients with CLcr ≤ 30 mL/min, the pharmacokinetics of GAZYVA was unaffected. GAZYVA has not been studied in patients with hepatic impairment.
The volume of distribution and steady-state clearance increased with body weight; however, the expected change in exposure does not warrant a dosage modification.
LN and Childhood-Onset INS
The population pharmacokinetic analysis of GAZYVA did not identify CLcr (median [range] 108 [28.9 - 282 mL/min] in LN and 136 [62.3 - 346 mL/min] in childhood-onset INS) as a significant covariate on the pharmacokinetics of patients with LN or childhood-onset INS. The pharmacokinetics of obinutuzumab in patients with mild or moderate renal impairment were similar to those in patients with normal kidney function. The safety and efficacy of GAZYVA in patients with severe renal impairment has not been formally studied.
GADOLIN
The efficacy of GAZYVA was evaluated in GADOLIN (NCT01059630), an open-label, multicenter, randomized study that included 335 patients with follicular lymphoma (FL) who had no response to or have progressed during or within 6 months of rituximab product or a rituximab product-containing regimen. These patients were randomized to receive either bendamustine alone (n = 171) or GAZYVA in combination with bendamustine (n = 164) for 6 cycles, each of 28 days duration. Patients in the GAZYVA plus bendamustine arm who did not have disease progression [patients with a complete response (CR), partial response (PR) or stable disease (SD)] at the end of the 6 cycles continued receiving GAZYVA monotherapy for 2 years. Patients were stratified according to the type of refractoriness to rituximab product (refractory to rituximab product monotherapy versus rituximab product in combination with chemotherapy), the number of prior therapies (≤ 2 versus > 2), and geographic region.
GAZYVA was given by intravenous infusion as a flat dose of 1,000 mg on Days 1, 8 and 15 of Cycle 1, on Day 1 of Cycles 2–6, and then every 2 months until disease progression for up to 2 years. Bendamustine was given intravenously on Days 1 and 2 for all treatment cycles (1–6) at 90 mg/m2/day when given in combination with GAZYVA or 120 mg/m2/day when given alone.
The primary analysis included 321 FL patients, including 166 patients randomized to bendamustine alone and 155 patients randomized to GAZYVA in combination with bendamustine. In the primary analysis, patients had a median age of 63 years, 88% were White and 56% were male. Thirty-four percent had bulky disease (> 6 cm), 15% had at least one B-symptom at baseline and 95% had an ECOG performance status of 0–1 at baseline. The median time since initial diagnosis was 3 years and the median number of prior therapies was 2 (range 1 to 10). Forty-six percent of patients received 1 prior therapy and 33% of patients received 2 prior therapies. Twenty percent of patients were refractory to prior rituximab product monotherapy, 37% of patients were refractory to prior rituximab product plus chemotherapy induction treatment, and 41% of patients were refractory to rituximab product maintenance treatment received following rituximab product plus chemotherapy induction. Seventy-nine percent of patients were refractory to both rituximab product and an alkylating agent during any prior regimen (double refractory).
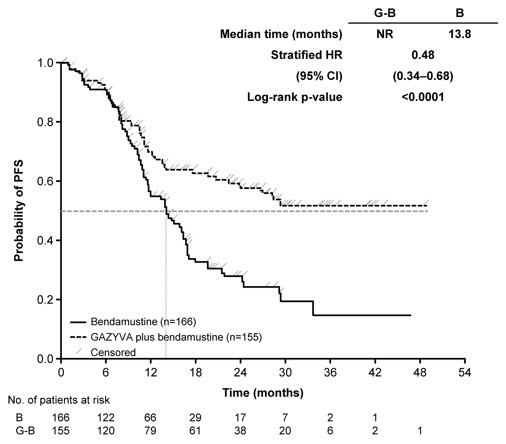
The major efficacy outcome measure was PFS as determined by an independent review committee (IRC). At the time of the primary analysis, median observation time was 21.1 months. The median PFS in the bendamustine arm was 13.8 months. Median PFS was not reached in the GAZYVA plus bendamustine arm (PFS HR = 0.48, 95% CI: 0.34-0.68; stratified log-rank test p-value < 0.0001). The investigator assessed PFS result was consistent with the IRC-assessed PFS. The median investigator-assessed PFS in the bendamustine arm was 13.7 months and the median in the GAZYVA containing arm was 29.2 months (PFS HR = 0.48, 95% CI: 0.35-0.67; stratified log-rank test p-value < 0.0001).
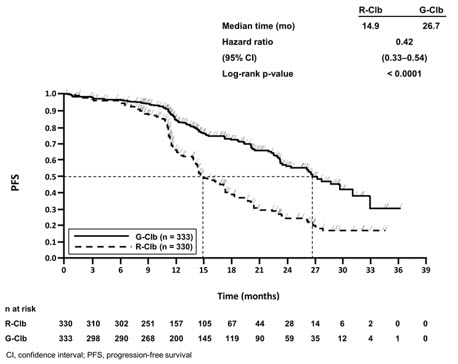
Efficacy results are summarized in Table 19. The Kaplan-Meier curve for IRC-PFS is shown in Figure 3.
Table 19 Primary Analysis Efficacy Results from GADOLINBased on FL population.
, As defined by independent review.
| Endpoint | GADOLIN |
|---|
GAZYVA + Bendamustine followed by GAZYVA monotherapy
n = 155 | Bendamustine
n = 166 |
|---|
| Median Progression-Free Survival (months) | Not Reached | 13.8 |
| (HR = 0.48 [0.34; 0.68], p-value < 0.0001 by stratified log-rank test) |
| Best Overall Response Best response of PR or CR within 12 months of study start. | 78.7% | 74.7% |
| Complete Response | 15.5% | 18.7% |
| Partial Response | 63.2% | 56.0% |
| Median duration of response (months) | Not Reached | 11.6 |
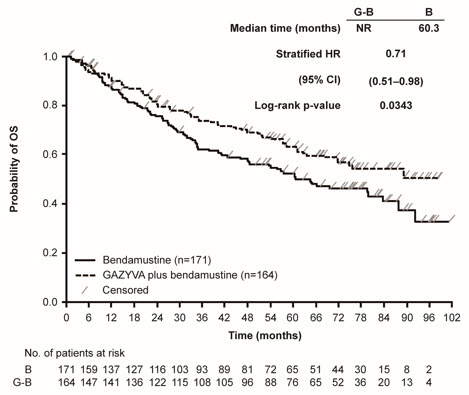
The final analysis included a total of 335 patients with 171 randomized to bendamustine alone and 164 to GAZYVA in combination with bendamustine. With an overall median observation time of 52.2 months (range: 0-100.9 months), there were 66 deaths (40.2%) in the GAZYVA arm and 85 deaths (51.3%) in the bendamustine-alone arm (OS HR = 0.71, 95% CI: 0.51, 0.98). The Kaplan-Meier curve for OS is presented in Figure 4.
GALLIUM
The efficacy of GAZYVA was evaluated in GALLIUM (NCT01332968), a multicenter, open-label, randomized study that included 1202 patients with previously untreated, stage II bulky, III or IV FL. Patients were randomized 1:1 to receive either GAZYVA (n = 601) or rituximab product (n = 601) in combination with chemotherapy (CHOP, CVP, or bendamustine) for 6–8 cycles. Patients were stratified by chemotherapy (selected by each site; all patients at that site received the chosen chemotherapy regimen), FLIPI (Follicular Lymphoma International Prognostic Index) risk group and geographic region. Patients with at least PR to combination therapy received monotherapy with GAZYVA (1,000 mg) or rituximab product every two months until disease progression or for a maximum of two years. The study excluded patients with follicular lymphoma grade 3b or transformed disease; patients having an ANC < 1500 / µL, platelets < 75,000 / µL, or CLcr < 40 mL/min; and patients with hepatic transaminases > 2.5 × upper limit of normal unless attributable to lymphoma.
GAZYVA was given by intravenous infusion as a flat dose of 1,000 mg on Days 1, 8 and 15 of Cycle 1 and Day 1 of subsequent treatment cycles.
GAZYVA and bendamustine were given in six 28-day cycles. Bendamustine was administered at 90 mg/m2/day on Days 1 and 2 of each cycle, with prednisone 100 mg orally or equivalent on Day 1 of Cycle 1.
GAZYVA and CHOP were given in six 21-day cycles. Subsequently, two additional cycles of GAZYVA were given for a total of 8 GAZYVA cycles. CHOP consisted of cyclophosphamide 750 mg/m2 intravenously, doxorubicin 50 mg/m2, and vincristine 1.4 mg/m2 (maximum dose, 2 mg) on Day 1 and prednisone 100 mg orally on Days 1-5.
GAZYVA and CVP were given in eight 21-day cycles. CVP consisted of cyclophosphamide 750 mg/m2 intravenously and vincristine 1.4 mg/m2 (maximum dose, 2 mg) on Day 1 and prednisone 100 mg orally on Days 1-5.
Patients had a median age of 59 years, 81% were White and 53% were female; 7% had Stage II, 35% had Stage III, and 56% had Stage IV disease, with 44% having bulky disease (≥ 7 cm) overall; 79% had a FLIPI score of > 2; and 97% had an ECOG performance status of 0–1. The chemotherapy was bendamustine in 57%, CHOP in 33%, and CVP in 10% of patients.
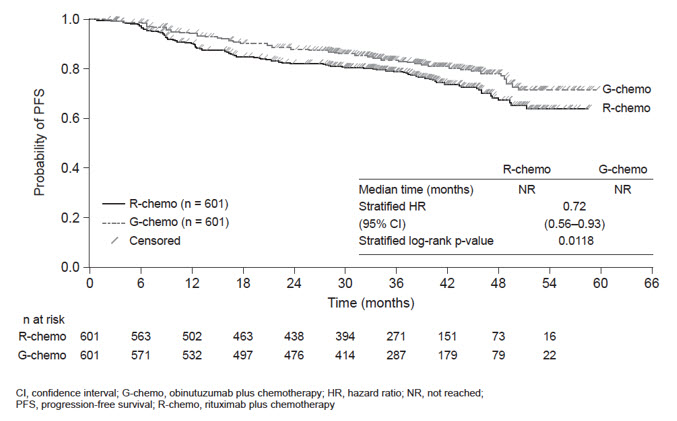
Efficacy was based on PFS per IRC, with a median observation time of 38 months. Upon interim analysis, the risk of progression or death was significantly reduced in the GAZYVA containing arm compared to the rituximab product containing arm (Table 20). Kaplan-Meier curves for PFS are shown in Figure 5. Overall response and complete remission rates were similar.
Table 20 Efficacy in Previously Untreated Follicular Lymphoma (GALLIUM) | Endpoint per IRC | GAZYVA + chemotherapy followed by GAZYVA monotherapy
n = 601 | Rituximab product + chemotherapy followed by rituximab product monotherapy
n = 601 |
|---|
| Progression-Free Survival Investigator-assessed PFS was consistent with data from independent review.
Number of events (%) | 108 (18%) | 141 (23%) |
| HR = 0.72 [95% CI: 0.56, 0.93], p-value = 0.0118 Stratified log-rank test. |
| Overall Response Rate | 91% | 88% |
| Complete Remission Rate | 28% | 27% |
Study Design and Population
The efficacy of GAZYVA was evaluated in REGENCY (NCT04221477), a Phase III, randomized, double-blind, placebo-controlled, parallel-group, multicenter study in 271 patients with ISN/RPS 2003 Class III or IV, with or without concomitant Class V lupus nephritis (LN), treated with standard therapy consisting of mycophenolate mofetil (MMF) and corticosteroids. Patients had active or active/chronic ISN/RPS 2003 Class III or IV, with or without concomitant Class V proliferative LN determined by kidney biopsy, current or past positive antinuclear antibody (ANA), urine protein-to-creatinine ratio (UPCR) ≥ 1 g/g, and had received at least one dose of pulse intravenous (IV) methylprednisolone (≥ 250 mg) or equivalent treatment for LN during the 6 months prior to screening or during screening.
Patients with estimated glomerular filtration rate (eGFR) <30 ml/min/1.73 m2 or in need of dialysis or transplantation, with sclerosis in > 50% of glomeruli on kidney biopsy, presence of rapidly progressive glomerulonephritis, evidence of active infection, receipt of anti-CD20 therapy < 9 months before or during screening, or receipt of cyclophosphamide, tacrolimus, ciclosporin, or voclosporin within 2 months of or during screening were excluded.
Patients were randomized 1:1 to receive GAZYVA 1,000 mg (N=135) or placebo (N=136) intravenously, in combination with MMF 2-2.5 g/day and a tapering course of corticosteroids and were evaluated over 76 weeks. Patients randomized to receive GAZYVA were further randomized in a 1:1 ratio to receive either GAZYVA 1,000 mg IV on Day 1, Weeks 2, 24, 26, 50, and 52 (Arm 1), or GAZYVA 1,000 mg IV on Day 1, Weeks 2, 24, 26, and 52 (Arm 2). The totality of the GAZYVA efficacy data combining both treatment arms is shown in Table 21.
All patients received oral prednisone 0.5 mg/kg/day (maximum 60 mg/day) and remained at this dose until Week 2. Beginning on Day 15, prednisone was tapered to achieve a target dose of 5 mg/day by Week 24. Prednisone was maintained at a low dose (5 mg/day) from Week 24 until Week 80.
The median age of patients was 31 years, 85% were female, 58% were Hispanic or Latino, 48% were White, 19% were American Indian or Alaska Native, 15% were Black or African American and 6% were Asian. The distribution by kidney biopsy class was 39% Class III, 61% Class IV and 31% had concomitant Class V. Mean (SD) eGFR at baseline 102.3 (±30.8) mL/min/1.73 m2. Mean (SD) UPCR at baseline was 3.3 (±2.9) mg/mg with 42% of patients exhibiting UPCR ≥3 mg/mg at baseline.
Efficacy Results
The primary endpoint measure was proportion of patients who achieved complete renal response (CRR) at Week 76, defined as meeting all of the following criteria: UPCR < 0.5 g/g; eGFR ≥ 85% of baseline, as calculated using the 2009 Chronic Kidney Disease Epidemiology Collaboration (CKD-EPI) equation; with no occurrence of the following intercurrent events: rescue therapy, treatment failure, death or early study withdrawal.
Key secondary endpoint measures included: proportion of patients who achieved CRR with successful prednisone taper at Week 76 (defined as achievement of CRR at Week 76 without receiving prednisone > 7.5 mg/day or equivalent from Week 64 through Week 76), proportion of patients who achieved a proteinuric response at Week 76 (defined as achievement of UPCR < 0.8g/g and no occurrence of the following intercurrent events: rescue therapy, treatment failure, death or early study withdrawal) and proportion of patients who experience "renal-related events or deaths" through Week 76 (defined as occurrence of death, treatment failure, ≥ 50% increase in UPCR to a value ≥ 3 g/g and/or ≥ 30% decrease in eGFR to < 60 ml/min/1.73 m2).
The proportion of patients achieving CRR at Week 76 was significantly greater in patients treated with GAZYVA in combination with standard therapy compared to patients who received placebo plus standard therapy. There were also a higher proportion of patients who achieved CRR with successful prednisone taper at Week 76 and proteinuric response at Week 76 in the GAZYVA plus standard therapy arm compared to the placebo plus standard therapy arm (see Table 21).
In the REGENCY study, patients who received GAZYVA were less likely to experience the outcome of "renal-related event or death" compared with placebo. Fewer patients in the GAZYVA arm experienced worsening kidney function or doubling of serum creatinine (see Table 22).
Table 21 Summary of Efficacy Results in Adult Patients with Active Lupus Nephritis (REGENCY Study) | GAZYVA + standard therapy
(N=135) | Placebo + standard therapy
(N=136) |
|---|
| Primary Endpoint |
|---|
| Complete renal response (CRR) at Week 76 (%) | 46.4 (38.0, 54.9) | 33.1 (25.2, 41) |
| Treatment difference (95% CI) Primary and key secondary endpoints were analyzed using the Cochran-Mantel-Haenszel (CMH) test, adjusted for stratification factors race and region. Multiple Imputation handled missing data. For the primary endpoint CRR and the key secondary endpoint CRR with successful prednisone taper, missing data (not due to an Intercurrent Event (ICE)) occurred in four patients in the GAZYVA arm and one in the placebo arm. For the key secondary endpoint proteinuric response, four GAZYVA patients and two placebo patients had non-ICE-related missing data. | 13.4 (2.0, 24.8) |
| p-value | 0.0232 |
| Components of CRR: | |
| UPCR < 0.5 g/g | 64 (47.4%) | 49 (36.0%) |
| eGFR ≥ 85% at baseline | 113 (83.7%) | 103 (75.7%) |
| No occurrence of intercurrent events | 120 (88.9%) | 102 (75%) |
| Key Secondary Endpoints |
| CRR with successful prednisone taper at Week 76 (%) | 42.7 (34.3, 51.1) | 30.9 (23.1, 38.7) |
| Treatment difference (95% CI) | 11.9 (0.6, 23.2) |
| p-value | 0.0421 |
| Proteinuric response at Week 76 (%) | 55.5 (47.1, 64) | 41.9 (33.6, 50.2) |
| Treatment difference (95% CI) | 13.7 (2.0, 25.4), |
| p-value | 0.0227 |
Table 22 Renal-Related Event or Death in Adult Patients with Active Lupus Nephritis (REGENCY Study) by Week 76 | Week 0-76 | Hazard Ratio (HR) vs. Placebo (95% CI)
Week 76 |
|---|
GAZYVA + standard therapy
N=135 (%) | Placebo + standard therapy
N=136 (%) |
|---|
| Renal-Related Event or Death | |
| Number (%) of patients with event | 24 (17.8%) | 46 (33.8%) | |
| Time to event | | | 0.5 (0.3, 0.8) |
| Components of Renal-Related Event or Death Endpoint | |
| Percentage of patients with: | |
| Death | 3 (2.2%) | 1 (0.7%) | |
| Treatment failure Treatment failure was prospectively defined as any of the following: 1) new ESRD or need for chronic dialysis or renal transplantation, 2) clinically significant, sustained worsening in UPCR and/or eGFR from Week 24 onward that leads the investigator to conclude the patient failed the randomized treatment period, or 3) receipt of rescue therapy, except corticosteroid-only rescue. | 6 (4.4%) | 25 (18.4%) | |
| End-stage renal disease (ESRD)1 | 0 | 2 (1.5%) | |
| Clinically significant, sustained worsening in UPCR and/or eGFR from Week 242 | 5 (3.7%) | 22(16.2%) | |
| Rescue Therapy except corticosteroid-only rescue3 | 5 (3.7%) | 22 (16.2%) | |
| Worsening proteinuria Worsening proteinuria was prospectively defined as a confirmed ≥ 50% increase in UPCR to a value ≥ 3 g/g. | 17 (12.6%) | 18 (13.2%) | |
| Worsening eGFR Worsening eGFR was prospectively defined as confirmed ≥ 30% decrease in eGFR to a value < 60mL/min/1.73m2. | 7 (5.2%) | 20 (14.7%) | |
| Additional Renal-Related Events | |
| Percentage of patients with event | |
| Doubling of serum creatinine from baseline through Week 76 | 4 (3.0%) | 8 (5.9%) | |
Subgroup Analyses
In pre-specified subgroup efficacy analyses, the primary endpoint in patients was examined based on 24-hour UPCR at baseline (< 3 g/g or ≥ 3 g/g), lupus nephritis class at baseline (Class III or IV), and concomitant Class V at baseline. The results are displayed in Figure 6 below.
Study Design and Population
The efficacy and safety of GAZYVA were evaluated in INSHORE (NCT05627557), a Phase III, randomized, controlled, open-label, multicenter study in 85 patients 2 years of age and older with frequently relapsing or steroid dependent childhood-onset idiopathic nephrotic syndrome (INS).
Frequently relapsing nephrotic syndrome (FRNS) was defined as two or more relapses in the first 6 months after disease onset (or after remission of the initial episode) or three or more relapses per 12 months thereafter. Steroid dependent nephrotic syndrome (SDNS) was defined as two consecutive relapses while on prednisone or prednisolone or within 14-15 days of prednisone or prednisolone discontinuation.
Patients had to be diagnosed before the age of 18 years, have a normal estimated glomerular filtration rate (eGFR) for age, and be in complete remission at study entry, as defined by the absence of edema, a urine protein-to-creatinine ratio (UPCR) of 0.2 g/g or less at screening, and trace or negative urine dipstick on 3 consecutive days within a week prior to randomization. Patients had to have had at least one relapse in the 6 months before screening.
Patients were excluded if they had secondary, steroid resistant, or genetic causes of nephrotic syndrome, treatment failure while receiving mycophenolate mofetil (MMF) (2 or more relapses in a 6 month period), received immunosuppressive medications other than MMF or oral corticosteroids within 2 months prior to randomization, or received biologic B cell-depleting therapy within 9 months prior to baseline. Patients with an active infection, or history of severe allergic or anaphylactic reactions to monoclonal antibodies were also excluded.
A total of 85 patients were randomized 1:1 to intravenous GAZYVA 1,000 mg (or 20 mg/kg if weighing less than 45 kg) on Day 1, Day 15, Week 24, and Week 26, or oral MMF titrated to a target dose of 1200 mg/m2/day divided in two doses (maximum 2,000 mg/day) by Week 4. Patients receiving GAZYVA received premedication with methylprednisolone 80 mg IV (or 1.5 mg/kg if less than 45 kg), acetaminophen/paracetamol 15 mg/kg orally (PO) (maximum dose 1,000 mg) and diphenhydramine 0.5 to 1 mg/kg (maximum dose 50 mg) orally or intravenous equivalent.
Patients who were receiving oral prednisone (or prednisolone equivalent) at randomization were tapered off steroids by Weeks 4−6 (and no later than Week 8) and were to remain off steroids to Week 52.
At baseline, the median age of patients was 9 years (range 2 to 22 years), 64% were 2 years to less than 12 years of age, 65% were male, median disease duration was 46 months, 25% were Hispanic or Latino, 27 % were Asian, 14% were Black or African American, and 55% were White. The mean eGFR was 171 mL/min/1.73 m2, mean UPCR was 0.05 g/g, 45% had FRNS, and 55% had SDNS.
A total of 75% had received prior immunosuppressive therapy other than steroids for INS and 85% were receiving glucocorticoids at baseline. Of the 85 patients, 1 (2%) in the GAZYVA arm and 9 (22%) in the MMF arm discontinued their randomized treatment during the 52-week treatment period.
The primary endpoint was the proportion of patients who did not relapse after Week 8 and were in complete remission at one year, defined as first morning void UPCR ≤ 0.2 g/g at Week 52. Relapse was defined as any of the following: (1) UPCR ≥ 2 g/g, or (2) 3 consecutive daily (home-monitoring) urine dipstick readings of 3+ proteinuria and UPCR > 0.2 g/g in the last of those three urines, or (3) urine dipstick reading of 3+ proteinuria on any single day accompanied by edema and most recent UPCR > 0.2 g/g. In addition, patients were non-responders if they had (1) used systemic corticosteroids for > 14 days in a 30 day period (after Week 8), (2) initiated rescue therapy other than systemic corticosteroids prior to 52 weeks, (3) died prior to 52 weeks, (4) missing UPCR assessments at Week 52.
Efficacy Results
The proportion of patients who did not relapse after Week 8 and were in complete remission at Week 52 was significantly greater (95%) in the GAZYVA as compared to the MMF arm (73%) (see Table 23). Key secondary outcome measures are shown in Table 23.
Table 23 Summary of Efficacy in Patients with Childhood-Onset Idiopathic Nephrotic Syndrome (INSHORE study) | GAZYVA
(N=44) | MMF
(N=41) |
|---|
| CI: confidence interval; PY: patient years; UPCR: urine protein to creatinine ratio; INS, idiopathic nephrotic syndrome. |
| Primary endpoint |
| Proportion without relapse Relapse was defined as any of the following (1) UPCR of 2 g/g or more, or (2) 3 consecutive daily (home-monitoring) urine dipstick readings of 3+ proteinuria and most recent UPCR greater than 0.2 g/g, or (3) urine dipstick reading of 3+ proteinuria on any single day accompanied by edema and most recent UPCR greater than 0.2 g/g. ,Patients were non-responders if they had used systemic corticosteroids for > 14 days in a 30-day period after Week 8, or initiated rescue therapy for INS other than systemic corticosteroids prior to 52 weeks. after Week 8 and were in complete remission at Week 52, number of patients (%) | 42 (95%) | 30 (73%) |
| Adjusted difference (95% CI) | 22 (6, 38) |
| p-value | 0.004 |
| Components of Primary Endpoint, n (%) | | |
| UPCR of 0.2 or less at Week 52 | 43 (98%) | 40 (98%) |
| No relapsea after week 8 | 44 (100%) | 32 (78%) |
| No systemic corticosteroids use after Week 8 | 43 (98%) | 30 (73%) |
| No use of rescue medication for INS (other than systemic corticosteroids) prior to week 52 | 44 (100%) | 32 (78%) |
| Key secondary endpoints |
| Number of patients with first relapse, Based on all relapse events until the clinical cutoff date (when the last patient completed the Week 52 study visit).
Hazard ratio, 95% confidence intervals, and p-value are derived from the pre-specified time-to-event analysis using Cox regression considering all relapse events until the clinical cutoff date (when the last patient completed the Week 52 study visit). (event rate per 100 PY) | 4 (7) | 15 (33) |
| Hazard ratio (95% CI) | 0.25 (0.08, 0.75) |
| p-value | 0.007 |
| Total number of relapses from randomization to Week 52 | 4 | 24 |
| Adjusted rate ratio (95% CI) | 0.16 (0.05, 0.44) |
| p-value | 0.0005 |
Infusion-related Reactions
Advise patients to seek immediate medical attention if signs and symptoms of infusion-related reactions occur [see Warnings and Precautions (5.3) and Adverse Reactions (6.1 and 6.2)].
Tumor Lysis Syndrome
Advise patients to seek immediate medical attention if symptoms of tumor lysis syndrome occur [see Warnings and Precautions (5.5) and Adverse Reactions (6.1)].
Infections
Advise patients to seek immediate medical attention if signs of an infection occur [see Warnings and Precautions (5.6) and Adverse Reactions (6.1 and 6.2)].
Hepatitis B Virus Reactivation
Advise patients to seek immediate medical attention if symptoms of hepatitis occur [see Warnings and Precautions (5.1)]. Advise patients of the need for hepatitis B virus screening and monitoring during treatment with GAZYVA.
Progressive Multifocal Leukoencephalopathy
Advise patients to seek immediate medical attention if new or changes in neurological symptoms occur [see Warnings and Precautions (5.2)].
Neutropenia, Thrombocytopenia and Disseminated Intravascular Coagulation
Advise patients to seek immediate medical attention if signs and symptoms of bleeding or thrombosis occur. Advise patients of the need for periodic monitoring of blood counts [see Warnings and Precautions (5.7, 5.8 and 5.9) and Adverse Reactions (6.1 and 6.2)].
Immunization
Advise patients to avoid vaccinations with live viral vaccines [see Warnings and Precautions (5.10)].
Embryo-Fetal Toxicity
Advise pregnant women of potential fetal B-cell depletion. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.11), Use in Specific Populations (8.1)].
Contraception
Advise females of reproductive potential to use effective contraception during treatment with GAZYVA and for 6 months after the last dose [see Use in Specific Populations (8.3)].
Lactation
Advise women not to breastfeed during treatment with GAZYVA and for 6 months after the last dose [see Use in Specific Populations (8.2)].
GAZYVA® (obinutuzumab)
Manufactured by:
Genentech, Inc.
A Member of the Roche Group
1 DNA Way
South San Francisco, CA 94080-4990
U.S. License No. 1048
GAZYVA is a registered trademark of Genentech, Inc.
© 2026 Genentech, Inc.