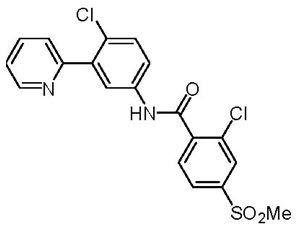
Females of Reproductive Potential
Verify the pregnancy status of females of reproductive potential within 7 days prior to initiating ERIVEDGE. Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during therapy with ERIVEDGE and for 24 months after the final dose [see Use in Specific Populations (8.1, 8.3)].
Males
Vismodegib is present in semen. It is not known if the amount of vismodegib in semen can cause embryo-fetal harm. Advise males to use condoms, even after a vasectomy, to avoid potential drug exposure in pregnant partners and female partners of reproductive potential during therapy and for 3 months after the final dose of ERIVEDGE. Advise male patients not to donate semen during and for 3 months after the final dose of ERIVEDGE [see Use in Specific Populations (8.3)].
Blood Donation
Advise patients not to donate blood or blood products while receiving ERIVEDGE and for 24 months after the final dose of ERIVEDGE.
Amenorrhea
Among patients from the clinical trials included in the pooled safety data analysis, 30% of 10 pre-menopausal women developed amenorrhea while receiving ERIVEDGE.
Laboratory Abnormalities
Grade 3 laboratory abnormalities observed in clinical trials were hyponatremia (4%), azotemia (2%) and hypokalemia (1%).
Additionally, in a post-approval clinical trial conducted in 1232 patients with locally advanced or metastatic BCC treated with ERIVEDGE, a subset of 29 patients had baseline values for blood creatine phosphokinase (CPK) reported. Within this subset of patients, 38% had a shift from baseline, including Grade 3 (3%) increased CPK. Grade 3 or 4 increased CPK occurred in 2.4% of the 453 patients across the entire study population with any CPK measurement.
Pregnancy Exposure Registry
There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ERIVEDGE during pregnancy. Report pregnancies to Genentech at 1-888-835-2555.
Risk Summary
Based on its mechanism of action and findings from animal reproduction studies, ERIVEDGE can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. In animal reproduction studies, oral administration of vismodegib during organogenesis at doses below the 150 mg clinical dose resulted in embryotoxicity, fetotoxicity, and teratogenicity in rats (see Data). There are no human data on the use of ERIVEDGE in pregnant women. Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data
Animal Data
In an embryo-fetal toxicity study, pregnant rats were administered vismodegib orally at doses of 10, 60, or 300 mg/kg/day during the period of organogenesis. Pre- and post-implantation loss were increased at doses of ≥ 60 mg/kg/day [approximately 2 times the human exposure at the 150 mg clinical dose based on area under the curve (AUC)], which included early resorption of 100% of the fetuses. A dose of 10 mg/kg/day [approximately 0.2 times the human exposure (AUC) at the recommended 150 mg clinical dose] resulted in malformations (including missing and/or fused digits, open perineum and craniofacial anomalies) and retardations or variations (including dilated renal pelvis, dilated ureter, and incompletely or unossified sternal elements, centra of vertebrae, or proximal phalanges and claws).
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential within 7 days prior to initiating ERIVEDGE.
Contraception
Based on its mechanism of action and animal data, ERIVEDGE can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Females
Advise females of reproductive potential to use effective contraception during therapy with ERIVEDGE and for 24 months after the final dose.
Males
Vismodegib is present in semen [see Clinical Pharmacology (12.3)]. It is not known if the amount of vismodegib in semen can cause embryo-fetal harm. Advise male patients to use condoms, even after a vasectomy, to avoid drug exposure to pregnant partners and female partners of reproductive potential during therapy with and for 3 months after the final dose of ERIVEDGE. Advise males of the potential risk to an embryo or fetus if a female partner of reproductive potential is exposed to ERIVEDGE. Advise males not to donate semen during therapy with ERIVEDGE and for 3 months after the final dose.
Infertility
Females
Amenorrhea can occur in females of reproductive potential. Reversibility of amenorrhea is unknown [see Adverse Reactions (6.1)].
Juvenile Animal Toxicity Data
In repeat-dose toxicology studies in rats, administration of oral vismodegib resulted in toxicities in bone and teeth. Effects on bone consisted of closure of the epiphyseal growth plate when oral vismodegib was administered for 26 weeks at ≥ 50 mg/kg/day (approximately ≥ 0.4 times the human exposure (AUC) at the 150 mg clinical dose). Abnormalities in growing incisor teeth (including degeneration/necrosis of odontoblasts, formation of fluid-filled cysts in the dental pulp, ossification of the root canal, and hemorrhage resulting in breakage or loss of teeth) were observed after administration of oral vismodegib at ≥ 15 mg/kg/day (approximately ≥ 0.2 times the human exposure (AUC) at the 150 mg clinical dose).
Cardiac Electrophysiology
ERIVEDGE did not prolong the QT interval to any clinically relevant extent following 7 days of 150 mg once-daily dosing (at steady state) .
Absorption
The single dose absolute bioavailability of vismodegib is 32%. Absorption is saturable as evidenced by the lack of dose proportional increase in exposure after a single dose of 270 mg or 540 mg vismodegib.
Effect of Food
Cmax and AUC0-24hr of vismodegib at steady state are not affected by food.
Distribution
The volume of distribution of vismodegib ranges from 16.4 to 26.6 L. Vismodegib plasma protein binding in patients is > 99%. Vismodegib binds to both human serum albumin and alpha-1-acid glycoprotein (AAG) and binding to AAG is saturable.
Male patients had an average concentration of vismodegib in semen on day 8 that was 6.5% of the average steady state concentration (Css) observed in plasma.
Elimination
The estimated elimination half-life (t1/2) of vismodegib is 4 days after continuous once-daily dosing and 12 days after a single dose.
Metabolism
Greater than 98% of the total circulating drug-related components are the parent drug. Metabolic pathways of vismodegib in humans include oxidation, glucuronidation, and pyridine ring cleavage. The two most abundant oxidative metabolites recovered in feces are produced in vitro by recombinant CYP2C9 and CYP3A.
Excretion
Vismodegib and its metabolites are eliminated primarily by the hepatic route with 82% of the administered dose recovered in the feces and 4.4% recovered in urine.
Specific Populations
Weight (41-140 kg), age (26-89 years), sex, mild to moderate renal impairment (creatinine clearance of 30 to 79 mL/min), mild hepatic impairment (normal total bilirubin and aspartate transaminase (AST) > upper limit of normal (ULN) or total bilirubin > 1 to 1.5 times ULN), moderate hepatic impairment (total bilirubin > 1.5 to 3 times ULN), or severe hepatic impairment (total bilirubin > 3 to 10 times ULN) had no clinically relevant effects on the systemic exposure of vismodegib. The impact of severe renal impairment on the pharmacokinetics of vismodegib is unknown.
Drug Interaction Studies
Clinical Studies
No clinically significant differences in vismodegib pharmacokinetics were observed when used concomitantly with fluconazole (moderate CYP2C9 and CYP3A4 inhibitor), itraconazole (strong CYP3A4 inhibitor and P-gp inhibitor) and rabeprazole (gastric acid reducing agent, proton pump inhibitor).
No clinically significant differences in the pharmacokinetics of the following drugs were observed when used concomitantly with vismodegib: rosiglitazone (a CYP2C8 substrate) or ethinyl estradiol and norethindrone (oral contraceptive).
In Vitro Studies
Vismodegib is an inhibitor of the transporter BCRP and is not an inducer of CYP1A2, CYP2B6, or CYP3A.
Embryo-Fetal Toxicity [see Warnings and Precautions (5.1), Use in Specific Populations (8.1, 8.3)]
Females of Reproductive Potential
- Advise women of the potential risk to a fetus. Advise female patients and female partners of male patients to contact their healthcare provider with a known or suspected pregnancy.
- Inform females there is a Pregnancy Exposure Registry that monitors pregnancy outcomes in females exposed to ERIVEDGE during pregnancy and that they can contact the Pregnancy Exposure Registry by calling 1-888-835-2555.
- Advise females of reproductive potential to use effective contraception during therapy with ERIVEDGE and for 24 months after the final dose.
Males
- Advise males, even those with prior vasectomy, to use condoms to avoid potential drug exposure in both pregnant partners and female partners of reproductive potential during therapy with ERIVEDGE and for 3 months after the final dose.
- Advise males not to donate semen during therapy with ERIVEDGE and for 3 months after the final dose.
Blood Donation