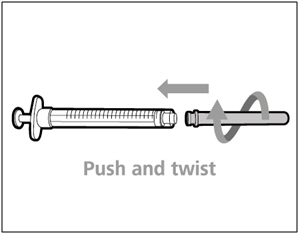
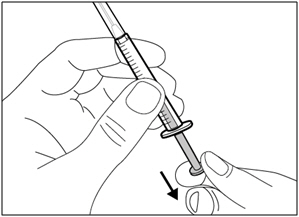
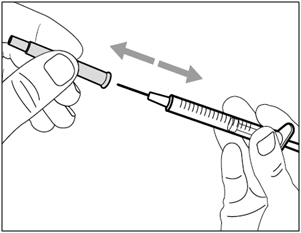
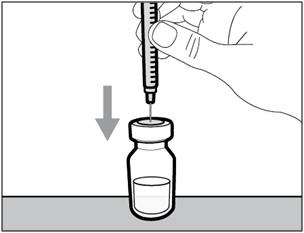
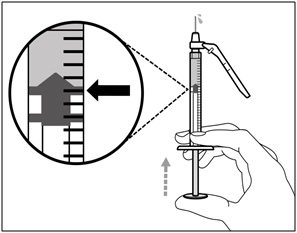
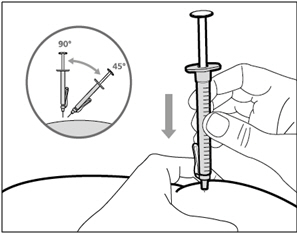
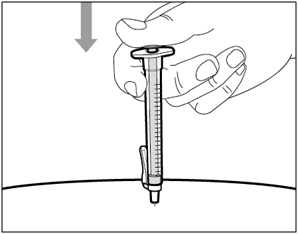
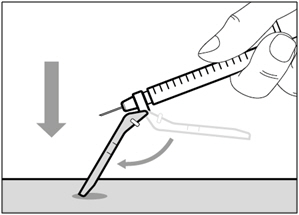
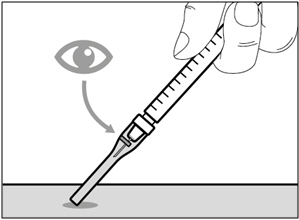
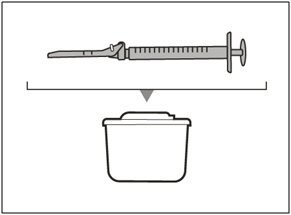
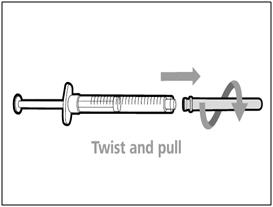
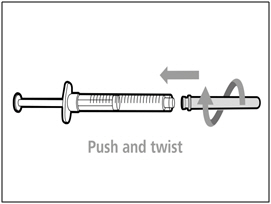
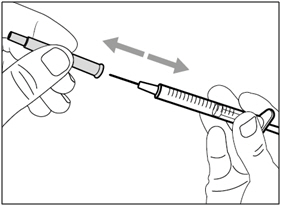
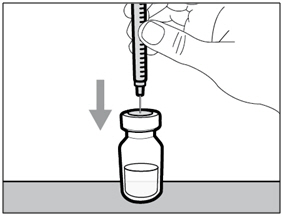
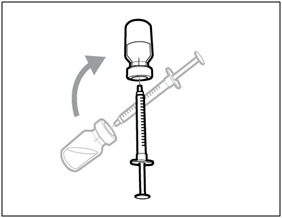
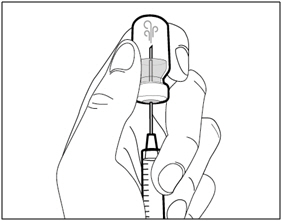
If a dose of HEMLIBRA is missed administer as soon as possible and then resume usual dosing schedule. Do not administer two doses on the same day to make up for a missed dose.
There were 130 instances of aPCC treatment in 37 patients, of which 13 instances (10%) consisted of on average a cumulative amount of >100 U/kg/24 hours of aPCC for 24 hours or more; two of the 13 were associated with thrombotic events and three of the 13 were associated with TMA (Table 3). No TMA or thrombotic events were associated with the remaining instances of aPCC treatment.
In total, 85 patients (22%) reported injection site reactions (ISRs). All ISRs observed in HEMLIBRA clinical trials were reported as mild to moderate intensity and 93% resolved without treatment. The commonly reported ISR symptoms were injection site erythema (11%), injection site pain (4%), and injection site pruritus (4%).
- Rhabdomyolysis
Rhabdomyolysis was reported in two adult patients with asymptomatic elevations in serum creatine kinase without associated renal or musculoskeletal symptoms. In both instances, the event occurred following an increase in physical activity.
Risk Summary
There are no available data on HEMLIBRA use in pregnant women to inform a drug-associated risk of major birth defects and miscarriage. Animal reproduction studies have not been conducted with emicizumab-kxwh. It is not known whether HEMLIBRA can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. HEMLIBRA should be used during pregnancy only if the potential benefit for the mother outweighs the risk to the fetus.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated background risk of major birth defect and miscarriage in clinically recognized pregnancies is 2 – 4% and 15 – 20%, respectively.
Risk Summary
There is no information regarding the presence of emicizumab-kxwh in human milk, the effects on the breastfed child, or the effects on milk production. Human IgG is known to be present in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for HEMLIBRA and any potential adverse effects on the breastfed child from HEMLIBRA or from the underlying maternal condition.
Contraception
Women of childbearing potential should use contraception while receiving HEMLIBRA.
Absorption
Following subcutaneous administration, the mean (± SD) absorption half-life was 1.6 ± 1 day.
The absolute bioavailability following subcutaneous administration of 1 mg/kg was between 80.4% and 93.1%. Similar pharmacokinetic profiles were observed following subcutaneous administration in the abdomen, upper arm, and thigh [see Dosage and Administration (2.2)].
Distribution
The mean apparent volume of distribution (% coefficient of variation [%CV]) was 10.4 L (26.0%).
Elimination
The mean apparent clearance (%CV) was 0.27 L/day (28.4%) and the mean elimination apparent half-life (± SD) was 26.9 ± 9.1 days.
Specific Populations
The pharmacokinetics of emicizumab-kxwh are not influenced by age (1 year to 77 years), race (White 62.7%, Asian 22.9%, and Black 8%), inhibitor status (inhibitor present, 50%), mild hepatic impairment (defined as total bilirubin 1× to ≤1.5× the upper limit of normal (ULN) and any aspartate transaminase (AST) level), moderate hepatic impairment (defined as total bilirubin 1.5× to ≤3× the ULN and any AST level), mild renal impairment (defined as creatinine clearance (CrCl) of 60 – 89 mL/min), and moderate renal impairment (defined as CrCl of 30 – 59 mL/min). Emicizumab-kxwh has not been studied in patients with severe hepatic or renal impairment.
In pediatric patients less than 6 months old, the predicted concentrations of emicizumab-kxwh were 19% to 33% lower than the older patients, especially with the 3 mg/kg once every two weeks or 6 mg/kg once every four weeks maintenance dose.
Body weight: The apparent clearance and volume of distribution of emicizumab-kxwh increased with increasing body weight (9 kg to 156 kg). Dosing in mg/kg provides similar emicizumab-kxwh exposure across body weight range.
Drug Interaction Studies
No drug-drug interaction studies have been conducted with HEMLIBRA.
Anti-Drug Antibody Effects on Pharmacokinetics
Antibody positive samples were further evaluated for neutralizing anti-emicizumab-kxwh antibodies using a modified FVIII chromogenic assay. A total of 668 patients were tested for anti-emicizumab-kxwh antibodies. 5.1% of patients (34/668) tested positive for anti-emicizumab-kxwh antibodies and 2.7% of patients (18/668) developed anti-emicizumab-kxwh antibodies that were neutralizing in vitro. Of these, 2.7% of patients (18/668), the neutralizing anti-emicizumab-kxwh antibodies did not have a clinically meaningful impact on the pharmacokinetics of HEMLIBRA in 2.1% of patients (14/668), while decreased emicizumab-kxwh plasma concentrations were observed in 0.6% of patients (4/668).
Anti-Drug Antibody Effects on Pharmacodynamics
One patient (1/668; 0.1%) developed neutralizing anti-emicizumab-kxwh antibodies and had decreased emicizumab-kxwh plasma concentrations, and experienced loss of efficacy (manifest as breakthrough bleeding) after 5 weeks of treatment and discontinued HEMLIBRA treatment. [see Warnings and Precautions (5.3), Clinical Studies (14.3)].
HAVEN 3 (Adult and Adolescent Patients)
The HAVEN 3 study (NCT02847637) was a randomized, multicenter, open-label, clinical trial in 152 adult and adolescent males (aged ≥ 12 years and ≥ 40 kg) with hemophilia A without FVIII inhibitors who previously received either episodic (on demand) or prophylactic treatment with FVIII. Patients received HEMLIBRA prophylaxis, 3 mg/kg once weekly for the first 4 weeks followed by either 1.5 mg/kg once every week [Arms A and D] or 3 mg/kg once every two weeks [Arm B] thereafter, or no prophylaxis (Arm C). Patients in Arm C could switch to HEMLIBRA prophylaxis (3 mg/kg once every two weeks) after completing at least 24 weeks without prophylaxis. For Arms A and B, dose up-titration to 3 mg/kg once every week was allowed after 24 weeks on HEMLIBRA prophylaxis for patients who experienced two or more qualified bleeds (i.e., spontaneous and clinically significant bleeds occurring at steady state). For Arm D patients, dose up-titration was allowed after the second qualifying bleed. During the study, five patients underwent up-titration of their maintenance dose; however, this study was not designed to investigate the 3 mg/kg once every week dosing regimen.
Eighty-nine patients previously treated with episodic (on demand) FVIII were randomized in a 2:2:1 ratio to receive HEMLIBRA prophylaxis 1.5 mg/kg once every week (Arm A), 3 mg/kg once every two weeks (Arm B), or no prophylaxis (Arm C), with stratification by prior 24-week bleed rate (< 9 or ≥ 9). Sixty-three patients previously treated with prophylactic FVIII were enrolled into Arm D to receive HEMLIBRA prophylaxis (1.5 mg/kg once every week).
Efficacy was evaluated after a minimum of 24 weeks of follow-up based on the bleed rate for bleeds requiring treatment with coagulation factors among patients previously treated with episodic (on-demand) FVIII who were randomized to HEMLIBRA prophylaxis 1.5 mg/kg once every week (Arm A) or 3 mg/kg once every two weeks (Arm B) compared with those receiving no prophylaxis (Arm C). The study also evaluated the randomized comparison of Arms A and C and Arms B and C for the efficacy of HEMLIBRA prophylaxis in reducing the number of all bleeds, spontaneous bleeds, joint bleeds, and target joint bleeds.
The efficacy of HEMLIBRA prophylaxis compared with previous prophylactic FVIII was also evaluated in patients who had participated in a non-interventional study (NIS) prior to enrollment (Arm D). Only patients from the NIS were included in this comparison, because bleed and treatment data were collected with the same level of granularity as that used in HAVEN 3.
The efficacy results of HEMLIBRA prophylaxis (1.5 mg/kg once every week and 3 mg/kg once every two weeks) compared with no prophylaxis with respect to rate of treated bleeds, all bleeds, treated spontaneous bleeds, treated joint bleeds, and treated target joint bleeds are shown in Table 5.
Table 5 Annualized Bleed Rate with HEMLIBRA Prophylaxis versus No Prophylaxis in Patients ≥ 12 Years of Age without Factor VIII Inhibitors| Endpoint | HEMLIBRA
1.5 mg/kg once every week (N = 36) | HEMLIBRA
3 mg/kg once every two weeks (N = 35) | No Prophylaxis
(N = 18) |
|---|
| ABR = annualized bleed rate; CI = confidence interval; IQR = interquartile range, 25th percentile to 75th percentile. |
| Treated Bleeds |
| ABR (95% CI) Based on negative binomial regression model. | 1.5 (0.9, 2.5) | 1.3 (0.8, 2.3) | 38.2 (22.9, 63.8) |
% reduction (95% CI)
p-value | 96% (92.5%, 98%)
< 0.0001 | 97% (93.4%, 98.3%)
< 0.0001 | - |
| % patients with 0 bleeds (95% CI) | 55.6 (38.1, 72.1) | 60 (42.1, 76.1) | 0 (0, 18.5) |
| Median ABR (IQR) | 0 (0, 2.5) | 0 (0, 1.9) | 40.4 (25.3, 56.7) |
| All Bleeds |
| ABR (95% CI) | 2.5 (1.6, 3.9) | 2.6 (1.6, 4.3) | 47.6 (28.5, 79.6) |
% reduction (95% CI)
p-value | 95% (90.1%, 97%)
< 0.0001 | 94% (89.7%, 97%)
< 0.0001 | - |
| % patients with 0 bleeds (95% CI) | 50 (32.9, 67.1) | 40 (23.9, 57.9) | 0 (0, 18.5) |
| Median ABR (IQR) | 0.6 (0, 3.9) | 1.6 (0, 4) | 46.9 (26.1, 73.9) |
| Treated Spontaneous Bleeds |
| ABR (95% CI) | 1.0 (0.5, 1.9) | 0.3 (0.1, 0.8) | 15.6 (7.6, 31.9) |
% reduction (95% CI)
p-value | 94% (84.9%, 97.5%)
< 0.0001 | 98% (94.4%, 99.4%)
< 0.0001 | - |
| % patients with 0 bleeds (95% CI) | 66.7 (49.0, 81.4) | 88.6 (73.3, 96.8) | 22.2 (6.4, 47.6) |
| Median ABR (IQR) | 0 (0, 1.3) | 0 (0, 0) | 10.8 (2.1, 26) |
| Treated Joint Bleeds |
| ABR (95% CI) | 1.1 (0.6, 1.9) | 0.9 (0.4, 1.7) | 26.5 (14.7, 47.8) |
% reduction (95% CI)
p-value | 96% (91.5%, 98.1%)
< 0.0001 | 97% (93%, 98.5%)
< 0.0001 | - |
| % patients with 0 bleeds (95% CI) | 58.3 (40.8, 74.5) | 74.3 (56.7, 87.5) | 0 (0, 18.5) |
| Median ABR (IQR) | 0 (0, 1.9) | 0 (0, 1.3) | 21.3 (14.5, 41.3) |
| Treated Target Joint Bleeds |
| ABR (95% CI) | 0.6 (0.3, 1.4) | 0.7 (0.3, 1.6) | 13 (5.2, 32.3) |
% reduction (95% CI)
p-value | 95% (85.7%, 98.4%)
< 0.0001 | 95% (85.3%, 98.2%)
< 0.0001 | - |
| % patients with 0 bleeds (95% CI) | 69.4 (51.9, 83.7) | 77.1 (59.9, 89.6) | 27.8 (9.7, 53.5) |
| Median ABR (IQR) | 0 (0, 1.4) | 0 (0, 0) | 12.8 (0, 39.1) |
In the HAVEN 3 intra-patient analysis, HEMLIBRA prophylaxis resulted in a statistically significant (p < 0.0001) reduction (68%) in bleed rate for treated bleeds compared with previous FVIII prophylaxis collected in the NIS prior to enrollment (see Table 6).
Table 6 Intra-Patient Comparison of Annualized Bleed Rate with HEMLIBRA Prophylaxis versus Previous FVIII Prophylaxis| Endpoint | HEMLIBRA
1.5 mg/kg once every week
(N = 48) | Previous FVIII Prophylaxis
(N = 48) |
|---|
| ABR = annualized bleed rate; CI = confidence interval; IQR = interquartile range, 25th percentile to 75th percentile. |
| Median Observation Period (weeks) | 33.7 | 30.1 |
| Treated Bleeds |
| ABR (95% CI) Based on negative binomial regression model. | 1.5 (1, 2.3) | 4.8 (3.2, 7.1) |
% reduction (95% CI)
p-value | 68% (48.6%, 80.5%)
< 0.0001 |
| % patients with 0 bleeds (95% CI) | 54.2 (39.2, 68.6) | 39.6 (25.8, 54.7) |
| Median ABR (IQR) | 0 (0, 2.1) | 1.8 (0, 7.6) |
HAVEN 4 (Adult and Adolescent Patients)
The HAVEN 4 study (NCT03020160) was a single-arm, multicenter, open-label, clinical trial in 41 adult and adolescent males (aged ≥ 12 years and ≥ 40 kg) with hemophilia A with or without FVIII inhibitors who previously received either episodic (on demand) or prophylactic treatment with FVIII or bypassing agents. Patients received HEMLIBRA prophylaxis at 3 mg/kg once weekly for the first 4 weeks followed by 6 mg/kg once every four weeks thereafter.
Efficacy was evaluated in a subgroup of 36 patients with hemophilia A without FVIII inhibitors based on the bleed rate for bleeds requiring treatment with coagulation factors. The study also evaluated the efficacy of HEMLIBRA prophylaxis on all bleeds, treated spontaneous bleeds, treated joint bleeds, and treated target joint bleeds.
The efficacy results of HEMLIBRA prophylaxis 6 mg/kg once every four weeks with respect to rate of treated bleeds, all bleeds, treated spontaneous bleeds, treated joint bleeds, and treated target joint bleeds are shown in Table 7. The median observation time was 25.6 weeks (range 24.1 – 29.4 weeks).
Table 7 Annualized Bleed Rate with HEMLIBRA Prophylaxis 6 mg/kg Once Every Four Weeks in Patients ≥ 12 Years of Age without Factor VIII Inhibitors| Endpoint | ABR Based on negative binomial regression model. (95% CI)
N = 36 | Median ABR (IQR)
N = 36 | % Zero Bleeds (95% CI)
N = 36 |
|---|
| ABR = annualized bleed rate; CI = confidence interval; IQR = interquartile range, 25th percentile to 75th percentile. |
| Treated Bleeds | 2.6 (1.5, 4.7) | 0 (0, 2.1) | 52.8 (35.5, 69.6) |
| All Bleeds | 4.8 (3.2, 7.1) | 2.1 (0, 6.1) | 27.8 (14.2, 45.2) |
| Treated Spontaneous Bleeds | 0.6 (0.2, 1.6) | 0 (0, 0) | 83.3 (67.2, 93.6) |
| Treated Joint Bleeds | 1.8 (0.8, 4) | 0 (0, 1.9) | 69.4 (51.9, 83.7) |
| Treated Target Joint Bleeds | 1.1 (0.4, 3.7) | 0 (0, 0) | 83.3 (67.2, 93.6) |
HAVEN 1 (Adult and Adolescent Patients)
The HAVEN 1 study (NCT02622321) was a randomized, multicenter, open-label, clinical trial in 109 adult and adolescent males (aged ≥ 12 years and ≥ 40 kg) with hemophilia A with FVIII inhibitors who previously received either episodic (on-demand) or prophylactic treatment with bypassing agents. Patients received HEMLIBRA prophylaxis (Arms A, C, and D), 3 mg/kg once weekly for the first 4 weeks followed by 1.5 mg/kg once every week thereafter, or no prophylaxis (Arm B). Patients in Arm B could switch to HEMLIBRA prophylaxis after completing at least 24 weeks without prophylaxis. Dose up-titration to 3 mg/kg once every week was allowed after 24 weeks on HEMLIBRA prophylaxis for patients who experienced two or more qualified bleeds (i.e., spontaneous and clinically significant bleeds occurring at steady state). During the study, two patients underwent up-titration of their maintenance dose; however, this study was not designed to investigate the 3 mg/kg once every week dosing regimen.
Fifty-three patients previously treated with episodic (on-demand) bypassing agents were randomized in a 2:1 ratio to receive HEMLIBRA prophylaxis (Arm A) or no prophylaxis (Arm B), with stratification by prior 24-week bleed rate (< 9 or ≥ 9). Forty-nine patients previously treated with prophylactic bypassing agents were enrolled into Arm C to receive HEMLIBRA prophylaxis. Seven patients previously treated with episodic (on-demand) bypassing agents who had participated in the NIS prior to enrollment, but were unable to enroll into HAVEN 1 prior to the closure of Arms A and B, were enrolled into Arm D to receive HEMLIBRA prophylaxis.
Efficacy was evaluated after a minimum of 24 weeks of follow-up based on the bleed rate for bleeds requiring treatment with coagulation factors among patients previously treated with episodic bypassing agents who were randomized to HEMLIBRA prophylaxis (Arm A) compared with those receiving no prophylaxis (Arm B). The study also evaluated the randomized comparison of Arms A and B for the efficacy of HEMLIBRA prophylaxis in reducing the number of all bleeds, spontaneous bleeds, joint bleeds, and target joint bleeds, as well as patient-reported symptoms and physical functioning.
The efficacy of HEMLIBRA prophylaxis compared with previous prophylactic bypassing agents was also evaluated in patients who had participated in the NIS prior to enrollment (Arm C). Only patients from the NIS were included in this comparison, because bleed and treatment data were collected with the same level of granularity as that used in HAVEN 1.
The efficacy results of HEMLIBRA prophylaxis 1.5 mg/kg once every week compared with no prophylaxis with respect to rate of treated bleeds, all bleeds, treated spontaneous bleeds, treated joint bleeds, and treated target joint bleeds are shown in Table 8.
Table 8 Annualized Bleed Rate with HEMLIBRA Prophylaxis versus No Prophylaxis in Patients ≥ 12 Years of Age with Factor VIII Inhibitors| Endpoint | HEMLIBRA
1.5 mg/kg once every week
(N = 35) | No Prophylaxis
(N = 18) |
|---|
| ABR = annualized bleed rate; CI = confidence interval; IQR = interquartile range, 25th percentile to 75th percentile. |
| Treated Bleeds |
| ABR (95% CI) Based on negative binomial regression model. | 2.9 (1.7, 5.0) | 23.3 (12.3, 43.9) |
% reduction (95% CI)
p-value | 87% (72.3%, 94.3%)
< 0.0001 |
| % patients with 0 bleeds (95% CI) | 62.9 (44.9, 78.5) | 5.6 (0.1, 27.3) |
| Median ABR (IQR) | 0 (0, 3.7) | 18.8 (13.0, 35.1) |
| All Bleeds |
| ABR (95% CI) | 5.5 (3.6, 8.6) | 28.3 (16.8, 47.8) |
% reduction (95% CI)
p-value | 80% (62.5%, 89.8%)
< 0.0001 |
| % patients with 0 bleeds (95% CI) | 37.1 (21.5, 55.1) | 5.6 (0.1, 27.3) |
| Median ABR (IQR) | 2 (0, 9.9) | 30.2 (18.3, 39.4) |
| Treated Spontaneous Bleeds |
| ABR (95% CI) | 1.3 (0.7, 2.2) | 16.8 (9.9, 28.3) |
% reduction (95% CI)
p-value | 92% (84.6%, 96.3%)
< 0.0001 |
| % patients with 0 bleeds (95% CI) | 68.6 (50.7, 83.1) | 11.1 (1.4, 34.7) |
| Median ABR (IQR) | 0 (0, 3.3) | 15.2 (6.6, 30.4) |
| Treated Joint Bleeds |
| ABR (95% CI) | 0.8 (0.3, 2.2) | 6.7 (2.0, 22.4) |
% reduction (95% CI)
p-value | 89% (48%, 97.5%)
0.0050 |
| % patients with 0 bleeds (95% CI) | 85.7 (69.7, 95.2) | 50.0 (26.0, 74.0) |
| Median ABR (IQR) | 0 (0, 0) | 1 (0, 14.4) |
| Treated Target Joint Bleeds |
| ABR (95% CI) | 0.1 (0.03, 0.6) | 3.0 (1.0, 9.1) |
% reduction (95% CI)
p-value | 95% (77.3%, 99.1%)
0.0002 |
| % patients with 0 bleeds (95% CI) | 94.3 (80.8, 99.3) | 50.0 (26.0, 74.0) |
| Median ABR (IQR) | 0 (0, 0) | 1 (0, 6.5) |
Descriptive analyses were conducted to assess HEMLIBRA prophylaxis once every week using 12-week treatment intervals up to Week 72. The descriptive mean ABRs for treated bleeds are shown in Table 9.
Table 9 Annualized Bleed Rate with HEMLIBRA Prophylaxis Once Every Week per 12-Week Intervals in Patients ≥ 12 Years of Age with Factor VIII Inhibitors| Endpoint | Time Interval (Weeks) |
|---|
1 – 12
(N = 109) | 13 – 24
(N = 108) | 25 – 36
(N = 93) | 37 – 48
(N = 93) | 49 – 60
(N = 57) | 61 – 72
(N = 42) |
|---|
| ABR = annualized bleed rate; CI = confidence interval based on Poisson distribution; N = number of patients who contributed data for analyses at each time interval. |
| Treated Bleeds |
| Mean ABR (95% CI) | 3.9
(1.1, 10.2) | 2.2
(0.3, 7.6) | 0.9
(0, 5.5) | 0.4
(0, 4.4) | 0.5
(0, 4.7) | 0.6
(0, 4.9) |
In the HAVEN 1 intra-patient analysis, HEMLIBRA prophylaxis resulted in a statistically significant (p = 0.0003) reduction (79%) in bleed rate for treated bleeds compared with previous bypassing agent prophylaxis collected in the NIS prior to enrollment (Table 10).
Table 10 Intra-Patient Comparison of Annualized Bleed Rate with HEMLIBRA Prophylaxis versus Previous Bypassing Agent Prophylaxis| Endpoint | HEMLIBRA
1.5 mg/kg once every week
(N = 24) | Previous Bypassing Agent Prophylaxis (N = 24) |
|---|
| ABR = annualized bleed rate; CI = confidence interval; IQR = interquartile range, 25th percentile to 75th percentile. |
| Median Observation Period (weeks) | 30.1 | 32.1 |
| Treated Bleeds |
| ABR (95% CI) Based on negative binomial regression model. | 3.3 (1.3, 8.1) | 15.7 (11.1, 22.3) |
% reduction (95% CI)
p-value | 79% (51.4%, 91.1%)
0.0003 |
| % patients with 0 bleeds (95% CI) | 70.8 (48.9, 87.4) | 12.5 (2.7, 32.4) |
| Median ABR (IQR) | 0 (0, 2.2) | 12 (5.7, 24.2) |
The HAVEN 1 study evaluated patient-reported hemophilia-related symptoms (painful swellings and presence of joint pain) and physical functioning (pain with movement and difficulty walking far) using the Physical Health Score of the Haemophilia-specific Quality of Life (Haem-A-QoL) questionnaire for patients ≥ 18 years of age. The HEMLIBRA prophylaxis arm (Arm A) showed an improvement compared with the no prophylaxis arm (Arm B) in the Haem-A-QoL Physical Health Subscale score at the Week 25 assessment (Table 11). The improvement in the Physical Health Score was further supported by the Total Score as measured by the Haem-A-QoL at Week 25.
Table 11 Change in Haem-A-QoL Physical Health Score with HEMLIBRA Prophylaxis versus No Prophylaxis in Patients (≥ 18 Years of Age) with Factor VIII Inhibitors at Week 25| Haem-A-QoL Scores at Week 25 | HEMLIBRA
1.5 mg/kg once every week
(N = 25Number of patients ≥ 18 years who completed the Haem-A-QoL questionnaire. ) | No Prophylaxis
(N = 14) |
|---|
| Physical Health Score (range 0 to 100) Lower scores are reflective of better functioning. |
| Adjusted mean Adjusted for baseline, and baseline by treatment group interaction. | 32.6 | 54.2 |
| Difference in adjusted means (95% CI) | 21.6 (7.9, 35.2) |
| p-value | 0.0029 |
HAVEN 2 (Pediatric Patients)
The HAVEN 2 study (NCT02795767) was a single-arm, multicenter, open-label, clinical trial in pediatric males (age < 12 years, or 12 – 17 years who weigh < 40 kg) with hemophilia A with FVIII inhibitors. Patients received HEMLIBRA prophylaxis at 3 mg/kg once weekly for the first 4 weeks followed by 1.5 mg/kg once every week thereafter.
The study evaluated the efficacy of HEMLIBRA prophylaxis, including the efficacy of HEMLIBRA prophylaxis compared with previous episodic (on-demand) and prophylactic bypassing agent treatment in patients who had participated in a non-interventional study (NIS) prior to enrollment (intra-patient analysis).
At the time of the interim analysis, efficacy was evaluated in 59 pediatric patients who were < 12 years of age and had been receiving HEMLIBRA prophylaxis for at least 12 weeks, including 38 patients age 6 to < 12 years, 17 patients age 2 to < 6 years, and four patients age < 2 years.
Annualized bleed rate (ABR) and percent of patients with zero bleeds were calculated for 59 patients (Table 12). The median observation time for these patients was 29.6 weeks (range 18.4 – 63 weeks).
Table 12 Annualized Bleed Rate with HEMLIBRA Prophylaxis 1.5 mg/kg Once Every Week in Pediatric Patients < 12 Years of Age with Factor VIII Inhibitors (Interim Analysis)| Endpoint | ABR Based on negative binomial regression model. (95% CI)
N = 59 | Median ABR (IQR)
N = 59 | % Zero Bleeds (95% CI)
N = 59 |
|---|
| ABR = annualized bleed rate; CI = confidence interval; IQR = interquartile range, 25th percentile to 75th percentile. |
| Treated Bleeds | 0.3 (0.1, 0.5) | 0 (0, 0) | 86.4 (75, 94) |
| All Bleeds | 3.8 (2.2, 6.5) | 0 (0, 3.4) | 55.9 (42.4, 68.8) |
| Treated Spontaneous Bleeds | 0 (0, 0.2) | 0 (0, 0) | 98.3 (90.9, 100) |
| Treated Joint Bleeds | 0.2 (0.1, 0.4) | 0 (0, 0) | 89.8 (79.2, 96.2) |
| Treated Target Joint Bleeds | 0.1 (0, 0.7) | 0 (0, 0) | 96.6 (88.3, 99.6) |
In the intra-patient analysis, 18 pediatric patients who had participated in the NIS had an ABR for treated bleeds of 19.8 (95% CI [15.3, 25.7]) on previous bypassing agent treatment (prophylactic treatment in 15 patients and on-demand treatment for 3 patients). HEMLIBRA prophylaxis resulted in an ABR for treated bleeds of 0.4 (95% CI [0.2, 0.9]) based on negative binomial regression, corresponding to a 98% reduction in bleed rate. On HEMLIBRA prophylaxis, 14 patients (77.8%) had zero treated bleeds.
The HAVEN 2 study evaluated patient-reported hemophilia-related symptoms (painful swellings and presence of joint pain) and physical functioning (pain with movement) using the Physical Health Score of the Hemophilia-specific Quality of Life Short Form (Haemo-QoL-SF) questionnaire for patients ≥ 8 to < 12 years of age. HEMLIBRA prophylaxis showed improvement from baseline in the Haemo-QoL-SF Physical Health Subscale score at the Week 25 assessment.
HAVEN 4 (Adult and Adolescent Patients)
The HAVEN 4 study (NCT03020160) was a single-arm, multicenter, open-label, clinical trial in 41 adult and adolescent males (aged ≥ 12 years and ≥ 40 kg) with hemophilia A with or without FVIII inhibitors who previously received either episodic (on demand) or prophylactic treatment with FVIII or bypassing agents. Patients received HEMLIBRA prophylaxis at 3 mg/kg once weekly for the first 4 weeks followed by 6 mg/kg once every four weeks thereafter.
Efficacy was evaluated in a subgroup of 5 patients with hemophilia A with FVIII inhibitors based on the bleed rate for bleeds requiring treatment with coagulation factors. The median observation time was 26.1 weeks (range 24.4 – 28.6 weeks). HEMLIBRA prophylaxis resulted in an ABR (95% CI) for treated bleeds of 1.2 (0.1, 14.8) based on negative binomial regression. On HEMLIBRA prophylaxis, 4 patients had zero treated bleeds.
The efficacy results of HEMLIBRA prophylaxis (1.5 mg/kg once every week, 3 mg/kg once every two weeks, and 6 mg/kg once every four weeks) with respect to rate of treated bleeds are shown in Table 13.
Table 13 Annualized Bleed Rate (Treated Bleeds) with HEMLIBRA Prophylaxis in Patients with or without Factor VIII Inhibitors| Endpoint | HAVEN 1 | HAVEN 2 | HAVEN 3 | HAVEN 4 |
|---|
HEMLIBRA 1.5 mg/kg once every week
(N = 35) | No Prophylaxis
(N = 18) | HEMLIBRA 1.5 mg/kg once every week
(N = 59) | HEMLIBRA 1.5 mg/kg once every week
(N = 36) | HEMLIBRA 3 mg/kg once every two weeks
(N = 35) | No Prophylaxis
(N = 18) | HEMLIBRA 6 mg/kg once every four weeks
(N = 41) |
|---|
| ABR = annualized bleed rate; CI = confidence interval; IQR = interquartile range, 25th percentile to 75th percentile; HAVEN 1 = adult and adolescent patients with factor VIII inhibitors; HAVEN 2 = pediatric patients with factor VIII inhibitors; HAVEN 3 = adult and adolescent patients without factor VIII inhibitors; HAVEN 4 = adult and adolescent patients with or without factor VIII inhibitors. |
| Median Efficacy Period (weeks) | 29.3 | 24 | 29.6 | 29.6 | 31.3 | 24 | 25.6 |
ABR
(95% CI) Based on negative binomial regression model. | 2.9
(1.7, 5) | 23.3
(12.3, 43.9) | 0.3
(0.1, 0.5) | 1.5
(0.9, 2.5) | 1.3
(0.8, 2.3) | 38.2
(22.9, 63.8) | 2.4
(1.4, 4.3) |
% reduction vs no prophylaxis (95% CI),
p-value | 87%
(72.3%, 94.3%)
< 0.0001 | - | - | 96%
(92.5%, 98%)
< 0.0001 | 97%
(93.4%, 98.3%)
< 0.0001 | - | - |
% patients with 0 bleeds
(95% CI) | 62.9
(44.9, 78.5) | 5.6
(0.1, 27.3) | 86.4
(75, 94) | 55.6
(38.1, 72.1) | 60
(42.1, 76.1) | 0
(0, 18.5) | 56.1
(39.7, 71.5) |
| % patients with 0 - 3 bleeds (95% CI) | 85.7
(69.7, 95.2) | 11.1
(1.4, 34.7) | 100
(93.9, 100) | 91.7
(77.5, 98.2) | 94.3
(80.8, 99.3) | 5.6
(0.1, 27.3) | 90.2
(76.9, 97.3) |
| Median ABR (IQR) | 0
(0, 3.7) | 18.8
(13, 35.1) | 0
(0, 0) | 0
(0, 2.5) | 0
(0, 1.9) | 40.4
(25.3, 56.7) | 0
(0, 2.1) |
How Supplied
HEMLIBRA (emicizumab-kxwh) injection is available as a sterile, preservative-free, colorless to slightly yellow solution in single-dose vials in the following dosage strengths:
| Strength | Nominal Volume | Concentration | Package Size (per carton) | Cap Color | NDC |
|---|
| 12 mg | 0.4 mL | 30 mg/mL | 1 vial | Grey | 50242-927-01 |
| 30 mg | 1 mL | 30 mg/mL | 1 vial | Sky Blue | 50242-920-01 |
| 60 mg | 0.4 mL | 150 mg/mL | 1 vial | Purple | 50242-921-01 |
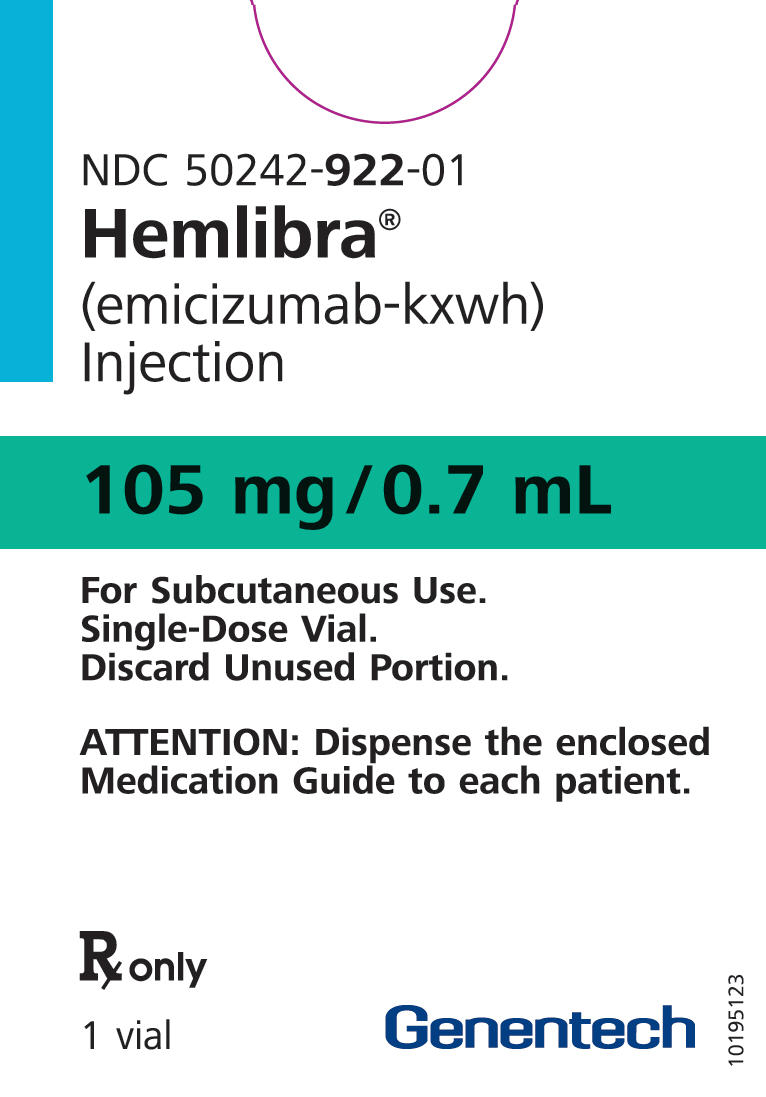
| 105 mg | 0.7 mL | 150 mg/mL | 1 vial | Turquoise | 50242-922-01 |
| 150 mg | 1 mL | 150 mg/mL | 1 vial | Brown | 50242-923-01 |
| 300 mg | 2 mL | 150 mg/mL | 1 vial | Yellow | 50242-930-01 |
Use of Bypassing Agents or FVIII
Inform the patient and/or caregiver that HEMLIBRA increases coagulation potential. Advise the patient and/or caregiver to discontinue prophylactic use of bypassing agents the day before starting HEMLIBRA prophylaxis. Advise the patient and/or caregiver that prophylactic use of FVIII may be continued for the first week of HEMLIBRA prophylaxis. Discuss the appropriate dosing of concomitant agents such as bypassing agents or FVIII with the patient and/or caregiver prior to starting HEMLIBRA prophylaxis [see Warnings and Precautions (5.1, 5.2) and Drug Interactions (7.1)].
Thrombotic Microangiopathy Associated with HEMLIBRA and aPCC
Inform the patient and/or caregiver of the potential risk of thrombotic microangiopathy if aPCC is administered while receiving HEMLIBRA prophylaxis. Instruct the patient and/or caregiver to consult their healthcare provider if aPCC is required in cumulative doses exceeding 100 U/kg. Advise the patient and/or caregiver to seek immediate medical attention if any signs or symptoms of thrombotic microangiopathy occur [see Warnings and Precautions (5.1)].
Thromboembolism Associated with HEMLIBRA and aPCC
Inform the patient and/or caregiver of the potential risk of thromboembolism if aPCC is administered while receiving HEMLIBRA prophylaxis. Instruct the patient and/or caregiver to consult their healthcare provider if aPCC is required in cumulative doses exceeding 100 U/kg. Advise the patient and/or caregiver to seek immediate medical attention if any signs or symptoms of thromboembolism occur [see Warnings and Precautions (5.2)].
Immunogenicity
Inform the patient and/or caregiver of the uncommon occurrence (incidence < 1%) of loss of efficacy while receiving HEMLIBRA prophylaxis due to immunogenicity (neutralizing anti-emicizumab-kxwh antibodies). Instruct the patient and/or caregiver to promptly report clinical signs of loss of efficacy (e.g., increase in breakthrough bleeding events) [see Warnings and Precautions (5.3)].
Laboratory Coagulation Test Interference
Inform the patient and/or caregiver that HEMLIBRA interferes with some laboratory tests that measure blood clotting and may cause a false reading. Advise the patient and/or caregiver that they should notify any healthcare provider about this possibility prior to any blood tests or medical procedures [see Warnings and Precautions (5.4)].
Instruction on Injection Technique
HEMLIBRA is intended for use under the guidance of a healthcare provider. If a patient or caregiver is to administer subcutaneous HEMLIBRA, instruct him/her in injection techniques and assess his/her ability to inject subcutaneously to ensure proper administration of subcutaneous HEMLIBRA and the suitability for home use [see Instructions for Use].
Advise the patient to follow the recommendations in the FDA-approved patient labeling regarding proper sharps disposal.
HEMLIBRA® [emicizumab-kxwh]
Manufactured by:
Genentech, Inc.
A Member of the Roche Group
1 DNA Way
South San Francisco, CA 94080-4990
HEMLIBRA® is a registered trademark of Chugai Pharmaceutical Co., Ltd., Tokyo, Japan
©2025 Genentech, Inc. All rights reserved.
U.S. License No.: 1048
Representative sample of labeling (see the HOW SUPPLIED section for complete listing):