Indomethacin Capsule
FDA Label NDC 50268-430

38 label sections · Submitted to the FDA by Avpak · Indications, Dosage, Usage, and Precautions

Structured Product Label

The following Structured Product Label (SPL) was submitted to the FDA by Avpak for the product Indomethacin (NDC 50268-430). This document serves as the official prescribing information, containing essential scientific data and clinical materials required for healthcare providers and patients.

This specific version of the label includes detailed information regarding boxed warning, indications and usage, dosage and administration, dosage forms & strengths, contraindications, warnings, 5.1 cardiovascular thrombotic events, 5.2 gastrointestinal bleeding, ulceration, and perforation, and other regulatory disclosures. Use the navigation below to review specific sections of the FDA submission.

Indications And Usage

Indomethacin Capsules are indicated for:
• Moderate to severe rheumatoid arthritis including acute flares of chronic disease
• Moderate to severe ankylosing spondylitis
• Moderate to severe osteoarthritis
• Acute painful shoulder (bursitis and/or tendinitis)
• Acute gouty arthritis

Dosage And Administration

2.1 General Dosing Instructions

Carefully consider the potential benefits and risks of indomethacin capsules and other treatment options before deciding to use indomethacin capsules. Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [ see Warnings and Precautions ( 5) ].
After observing the response to initial therapy with indomethacin, the dose and frequency should be adjusted to suit an individual patient’s needs.
Adverse reactions generally appear to correlate with the dose of indomethacin. Therefore, every effort should be made to determine the lowest effective dosage for the individual patient.
Dosage recommendations for active stages of the following:

2.2 Moderate to severe rheumatoid arthritis including acute flares of chronic disease;

Indomethacin capsules 25 mg twice a day or three times a day. If this is well tolerated, increase the daily dosage by 25 mg or by 50 mg, if required by continuing symptoms, at weekly intervals until a satisfactory response is obtained or until a total daily dose of 150 mg to 200 mg is reached. Doses above this amount generally do not increase the effectiveness of the drug.
In patients who have persistent night pain and/or morning stiffness, the giving of a large portion, up to a maximum of 100 mg, of the total daily dose at bedtime may be helpful in affording relief. The total daily dose should not exceed 200 mg. In acute flares of chronic rheumatoid arthritis, it may be necessary to increase the dosage by 25 mg or, if required, by 50 mg daily.
If minor adverse effects develop as the dosage is increased, reduce the dosage rapidly to a tolerated dose and observe the patient closely.
If severe adverse reactions occur, stop the drug. After the acute phase of the disease is under control, an attempt to reduce the daily dose should be made repeatedly until the patient is receiving the smallest effective dose or the drug is discontinued.
Careful instructions to, and observations of, the individual patient are essential to the prevention of serious, irreversible, including fatal, adverse reactions.
As advancing years appear to increase the possibility of adverse reactions, indomethacin should be used with greater care in the elderly. [ see Use in Specific Populations ( 8.5) ]

2.3 Acute painful shoulder (bursitis and/or tendinitis)

Indomethacin capsules 75 mg to 150 mg daily in 3 or 4 divided doses.
The drug should be discontinued after the signs and symptoms of inflammation have been controlled for several days. The usual course of therapy is 7 to 14 days.

2.4 Acute Gouty Arthritis

  • Indomethacin Capsules 50 mg three times a day, until pain is tolerable. The dose should then be rapidly reduced to complete cessation of the drug. Definite relief of pain has been reported within 2 to 4 hours. Tenderness and heat usually subside in 24 to 36 hours, and swelling gradually disappears in 3 to 5 days.
Contraindications

Indomethacin Capsule, USP is contraindicated in patients with known hypersensitivity to indomethacin or the excipients (see DESCRIPTION).

Indomethacin Capsule, USP should not be given to patients who have experienced asthma, urticaria, or allergic-type reactions after taking aspirin or other NSAIDs. Severe, rarely fatal, anaphylactic/anaphylactoid reactions to NSAIDs have been reported in such patients (see WARNINGS:Anaphylactic/Anaphylactoid Reactions, and PRECAUTIONS:General:Preexisting Asthma).

Indomethacin Capsule, USP is contraindicated for the treatment of perioperative pain in the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS).

Warnings

• Hepatotoxicity: Inform patients of warning signs and symptoms of hepatotoxicity. Discontinue if abnormal liver tests persist or worsen or if clinical signs and symptoms of liver disease develop ( 5.3)
• Hypertension: Patients taking some antihypertensive medications may have impaired response to these therapies when taking NSAIDs. Monitor blood pressure ( 5.4, 7)
• Heart Failure and Edema: Avoid use of indomethacin in patients with severe heart failure unless benefits are expected to outweigh risk of worsening heart failure ( 5.5)
• Renal Toxicity: Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia. Avoid use of indomethacin in patients with advanced renal disease unless benefits are expected to outweigh risk of worsening renal function ( 5.6)
• Anaphylactic Reactions: Seek emergency help if an anaphylactic reaction occurs ( 5.7)
• Exacerbation of Asthma Related to Aspirin Sensitivity: Indomethacin is contraindicated in patients with aspirin-sensitive asthma. Monitor patients with preexisting asthma (without aspirin sensitivity) ( 5.8)
• Serious Skin Reactions: Discontinue indomethacin at first appearance of skin rash or other signs of hypersensitivity ( 5.9)
• Premature Closure of Fetal Ductus Arteriosus: Avoid use in pregnant women starting at 30 weeks gestation ( 5.10, 8.1)
• Hematologic Toxicity: Monitor hemoglobin or hematocrit in patients with any signs or symptoms of anemia ( 5.11, 7)

5.1 Cardiovascular Thrombotic Events

Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease. However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as indomethacin, increases the risk of serious gastrointestinal (GI) events [ see Warnings and Precautions ( 5.2) ].
Status Post Coronary Artery Bypass Graft (CABG) Surgery
Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke. NSAIDs are contraindicated in the setting of CABG [ see Contraindications ( 4) ].
Post-MI Patients
Observational studies conducted in the Danish National Registry have demonstrated that patients treated with NSAIDs in the post-MI period were at increased risk of reinfarction, CV-related death, and all-cause mortality beginning in the first week of treatment. In this same cohort, the incidence of death in the first year post-MI was 20 per 100 person years in NSAID-treated patients compared to 12 per 100 person years in non-NSAID exposed patients. Although the absolute rate of death declined somewhat after the first year post-MI, the increased relative risk of death in NSAID users persisted over at least the next four years of follow-up.
Avoid the use of indomethacin capsules in patients with a recent MI unless the benefits are expected to outweigh the risk of recurrent CV thrombotic events. If indomethacin capsules are used in patients with a recent MI, monitor patients for signs of cardiac ischemia.

5.2 Gastrointestinal Bleeding, Ulceration, And Perforation

NSAIDs, including indomethacin, cause serious gastrointestinal (GI) adverse events including inflammation, bleeding, ulceration, and perforation of the esophagus, stomach, small intestine, or large intestine, which can be fatal. These serious adverse events can occur at any time, with or without warning symptoms, in patients treated with NSAIDs. Only one in five patients who develop a serious upper GI adverse event on NSAID therapy is symptomatic. Upper GI ulcers, gross bleeding, or perforation caused by NSAIDs occurred in approximately 1% of patients treated for 3 to 6 months, and in about 2% to 4% of patients treated for one year. However, even short-term NSAID therapy is not without risk.
Risk Factors for GI Bleeding, Ulceration, and Perforation
Patients with a prior history of peptic ulcer disease and/or GI bleeding who used NSAIDs had a greater than 10-fold increased risk for developing a GI bleed compared to patients without these risk factors. Other factors that increase the risk of GI bleeding in patients treated with NSAIDs include longer duration of NSAID therapy; concomitant use of oral corticosteroids, aspirin, anticoagulants, or selective serotonin reuptake inhibitors (SSRIs); smoking; use of alcohol; older age; and poor general health status. Most postmarketing reports of fatal GI events occurred in elderly or debilitated patients. Additionally, patients with advanced liver disease and/or coagulopathy are at increased risk for GI bleeding.
Strategies to Minimize the GI Risks in NSAID-treated patients:
• Use the lowest effective dosage for the shortest possible duration.
• Avoid administration of more than one NSAID at a time.
• Avoid use in patients at higher risk unless benefits are expected to outweigh the increased risk of bleeding. For such patients, as well as those with active GI bleeding, consider alternate therapies other than NSAIDs.
• Remain alert for signs and symptoms of GI ulceration and bleeding during NSAID therapy.
• If a serious GI adverse event is suspected, promptly initiate evaluation and treatment, and discontinue indomethacin until a serious GI adverse event is ruled out.
• In the setting of concomitant use of low-dose aspirin for cardiac prophylaxis, monitor patients more closely for evidence of GI bleeding [ see Drug Interactions ( 7) ].

5.6 Renal Toxicity And Hyperkalemia

Renal Toxicity
Long-term administration of NSAIDs has resulted in renal papillary necrosis and other renal injury.
Renal toxicity has also been seen in patients in whom renal prostaglandins have a compensatory role in the maintenance of renal perfusion. In these patients, administration of an NSAID may cause a dose-dependent reduction in prostaglandin formation and, secondarily, in renal blood flow, which may precipitate overt renal decompensation. Patients at greatest risk of this reaction are those with impaired renal function, dehydration, hypovolemia, heart failure, liver dysfunction, those taking diuretics and ACE inhibitors or ARBs, and the elderly. Discontinuation of NSAID therapy is usually followed by recovery to the pretreatment state.
No information is available from controlled clinical studies regarding the use of indomethacin in patients with advanced renal disease. The renal effects of indomethacin capsules may hasten the progression of renal dysfunction in patients with preexisting renal disease.
Correct volume status in dehydrated or hypovolemic patients prior to initiating indomethacin. Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia during use of indomethacin [ see Drug Interactions ( 7) ].
Avoid the use of indomethacin in patients with advanced renal disease unless the benefits are expected to outweigh the risk of worsening renal function. If indomethacin is used in patients with advanced renal disease, monitor patients for signs of worsening renal function.
It has been reported that the addition of the potassium-sparing diuretic, triamterene, to a maintenance schedule of indomethacin resulted in reversible acute renal failure in two of four healthy volunteers. Indomethacin and triamterene should not be administered together.
Hyperkalemia
Increases in serum potassium concentration, including hyperkalemia, have been reported with use of NSAIDs, even in some patients without renal impairment. In patients with normal renal function, these effects have been attributed to a hyporeninemic-hypoaldosteronism state.
Both indomethacin and potassium-sparing diuretics may be associated with increased serum potassium levels. The potential effects of indomethacin and potassium-sparing diuretics on potassium levels and renal function should be considered when these agents are administered concurrently.

5.7 Anaphylactic Reactions

Indomethacin has been associated with anaphylactic reactions in patients with and without known hypersensitivity to indomethacin and in patients with aspirin-sensitive asthma [ see Contraindications ( 4) and Warnings and Precautions ( 5.8) ].
Seek emergency help if an anaphylactic reaction occurs.

Adverse Reactions

The following adverse reactions are discussed in greater detail in other sections of the labeling:
• Cardiovascular Thrombotic Events [ see Warnings and Precautions ( 5.1) ]
• GI Bleeding, Ulceration and Perforation [ see Warnings and Precautions ( 5.2) ]
• Hepatotoxicity [ see Warnings and Precautions ( 5.3) ]
• Hypertension [ see Warnings and Precautions ( 5.4) ]
• Heart Failure and Edema [ see Warnings and Precautions ( 5.5) ]
• Renal Toxicity and Hyperkalemia [ see Warnings and Precautions ( 5.6) ]
• Anaphylactic Reactions [ see Warnings and Precautions ( 5.7) ]
• Serious Skin Reactions [ see Warnings and Precautions ( 5.9) ]
• Hematologic Toxicity [ see Warnings and Precautions ( 5.11) ]

Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice.
In a gastroscopic study in 45 healthy subjects, the number of gastric mucosal abnormalities was significantly higher in the group receiving indomethacin capsules than in the group taking indomethacin Suppositories or placebo.
In a double-blind comparative clinical study involving 175 patients with rheumatoid arthritis, however, the incidence of upper gastrointestinal adverse effects with indomethacin capsules Suppositories or Capsules was comparable. The incidence of lower gastrointestinal adverse effects was greater in the suppository group.
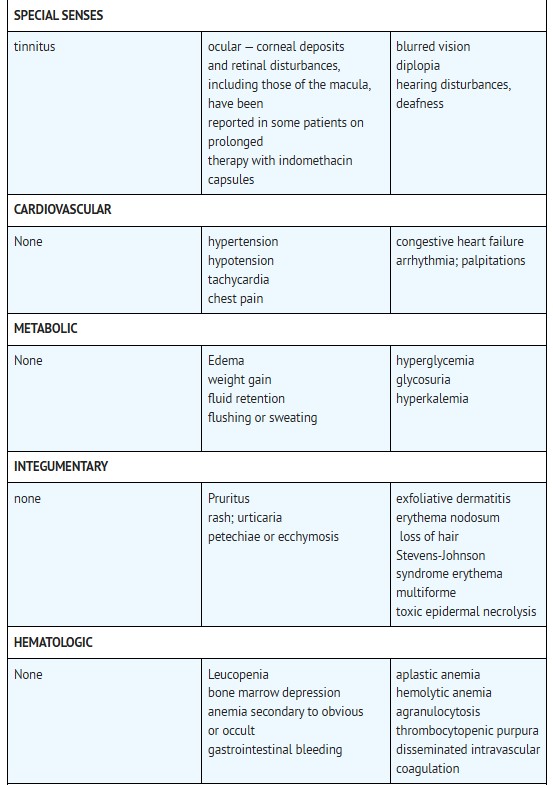
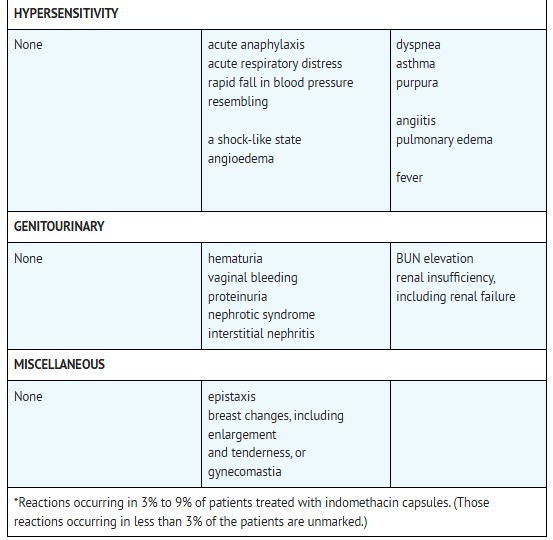
The adverse reactions for indomethacin capsules listed in the following table have been arranged into two groups: (1) incidence greater than 1%; and (2) incidence less than 1%. The incidence for group (1) was obtained from 33 double-blind controlled clinical trials reported in the literature (1,092 patients). The incidence for group (2) was based on reports in clinical trials, in the literature, and on voluntary reports since marketing. The probability of a causal relationship exists between indomethacin and these adverse reactions, some of which have been reported only rarely.
The adverse reactions reported with indomethacin capsules may occur with use of the suppositories. In addition, rectal irritation and tenesmus have been reported in patients who have received the capsules.
Table 1: Summary of Adverse reactions for Indomethacin Capsules

B (Table1b)

B (Table1b)

C (Table1c)

C (Table1c)

Causal relationship unknown: Other reactions have been reported but occurred under circumstances where a causal relationship could not be established. However, in these rarely reported events, the possibility cannot be excluded. Therefore, these observations are being listed to serve as alerting information to physicians:
Cardiovascular: Thrombophlebitis
Hematologic: Although there have been several reports of leukemia, the supporting information is weak
Genitourinary: Urinary frequency
A rare occurrence of fulminant necrotizing fasciitis, particularly in association with Group Aβ hemolytic streptococcus, has been described in persons treated with non-steroidal anti-inflammatory agents, including indomethacin, sometimes with fatal outcome.

To report SUSPECTED ADVERSE REACTIONS, contact AvKARE at 1-855-361-3993 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.

Description

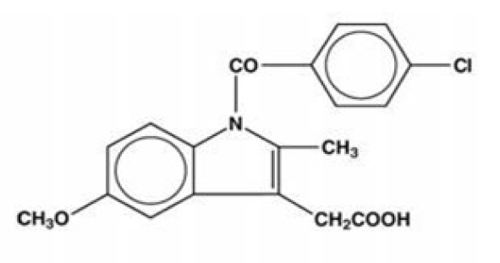
Indomethacin Capsules, USP are nonsteroidal anti-inflammatory drugs, available as capsules containing 25 mg or 50 mg of indomethacin USP, administered for oral use. The chemical name is 1-(4-chlorobenzoyl)-5-methoxy-2-methyl-1H-indole-3-acetic acid. The molecular weight is 357.79. Its molecular formula is C 19H 16ClNO 4, and it has the following chemical structure.

Structure (Structure)

Structure (Structure)

Indomethacin USP is a white to yellow crystalline powder. It is practically insoluble in water and sparingly soluble in alcohol, in chloroform and in ether. It has a pKa of 4.5 and is stable in neutral or slightly acidic media and decomposes in strong alkali.
The inactive ingredients in indomethacin capsules 25 mg or 50 mg include: lactose monohydrate, sodium lauryl sulfate, sodium starch glycolate, colloidal silicon dioxide, magnesium stearate. The hard gelatin shell consists of gelatin, titanium dioxide, FD & C Blue 1, D & C Yellow 10. The capsules are printed with black ink containing black iron oxide E172 dye.

Package Label.Principal Display Panel

50 (430 15)

50 (430 15)

50 (431 15)

50 (431 15)

* Please review the disclaimer below.