Distribution
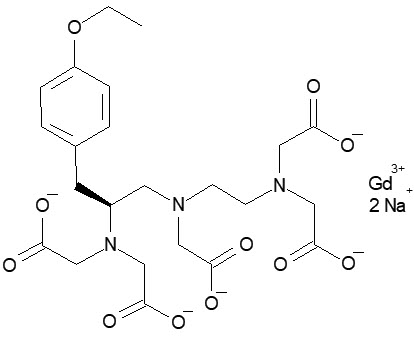
Gadoxetate exhibits a biphasic mode of action: first, distribution in the extracellular space after injection and subsequently, selective uptake by hepatocytes (and biliary excretion) due to the lipophilic (EOB) moiety. After intravenous administration, the plasma concentration time profile of gadoxetate is characterized by a bi-exponential decline. The total distribution volume of gadoxetate at steady state is about 0.21 L/kg (extracellular space); plasma protein binding is less than 10%. Following GBCA administration, gadolinium is present for months or years in brain, bone, skin, and other organs [see Warnings and Precautions (5.4)].
Elimination
The mean terminal elimination half-life of gadoxetate (0.01 to 0.1 mmol/kg) has been observed in healthy subjects of 22 to 39 years of age to be 0.91 to 0.95 hour. The pharmacokinetics are dose-linear up to a dose of 0.1 mmol/kg (4 times the recommended dose).
A total serum clearance (Cltot) was 250 mL/min, whereas the renal clearance (Clr) corresponds to about 120 mL/min, a value similar to the glomerular filtration rate in healthy subjects.
Metabolism
Gadoxetate is not metabolized.
Excretion
Gadoxetate is equally eliminated via the renal and hepatobiliary routes.
Specific Populations
Geriatric Patients
In a clinical pharmacology study, the AUC and terminal half-life of gadoxetate were slightly increased (1.2-fold and 1.3-fold, respectively) and total clearance was decreased by 0.8-fold in geriatric patients compared to non-geriatric patients.
Patients with Renal Impairment
In a study of patients with end-stage renal failure, the AUC was increased about 6-fold and the terminal half-life was prolonged about 12-fold. Approximately 30% of the injected dose was removed by dialysis in a single 3-hour dialysis session, which started 1 hour after an EOVIST dose. Gadoxetate was almost completely eliminated via hemodialysis and biliary excretion within the observation period of 6 days, predominantly within the first 3 days [see Use in Specific Populations (8.6)].
In patients with moderate renal impairment, a moderate increase in AUC and terminal half-life (1.5-fold and 1.2-fold, respectively) was observed in comparison to healthy subjects with normal renal function.
Patients with Hepatic Impairment
In patients with severe hepatic impairment, especially in patients with abnormally high (> 3 mg/dL) serum bilirubin levels, the AUC of gadoxetate was increased up to 60% and the elimination half-life was increased up to 49%. The hepatobiliary excretion substantially decreased to about 5% of the administered dose [see Use in Specific Populations (8.7)].
In patients with mild or moderate hepatic impairment, a slight to moderate increase in plasma AUC (1.6-fold), half-life (1.1-fold), and urinary excretion (1.3-fold), as well as decrease in hepatobiliary excretion (0.7-fold) was observed in comparison to healthy subjects with normal liver function.