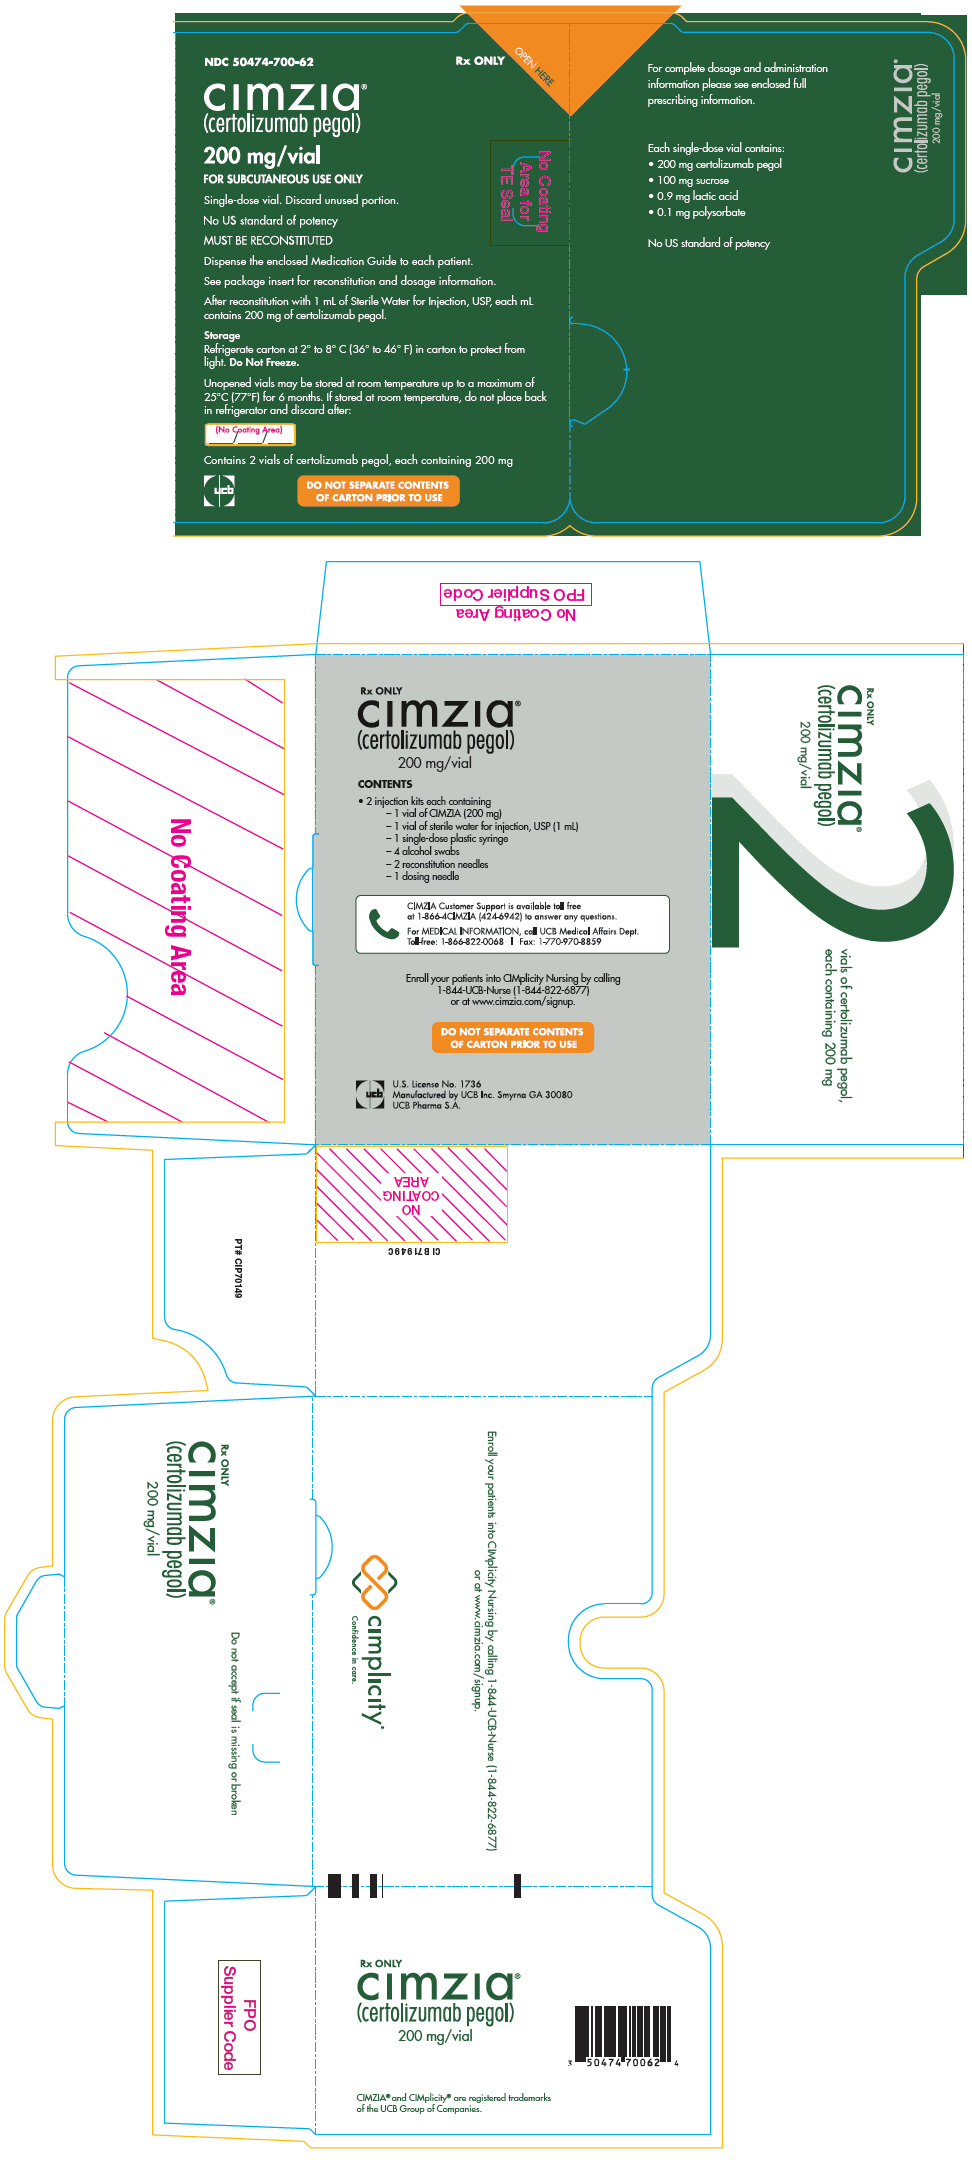
For Injection: 200 mg of white to off-white lyophilized powder in a single-dose vial for reconstitution
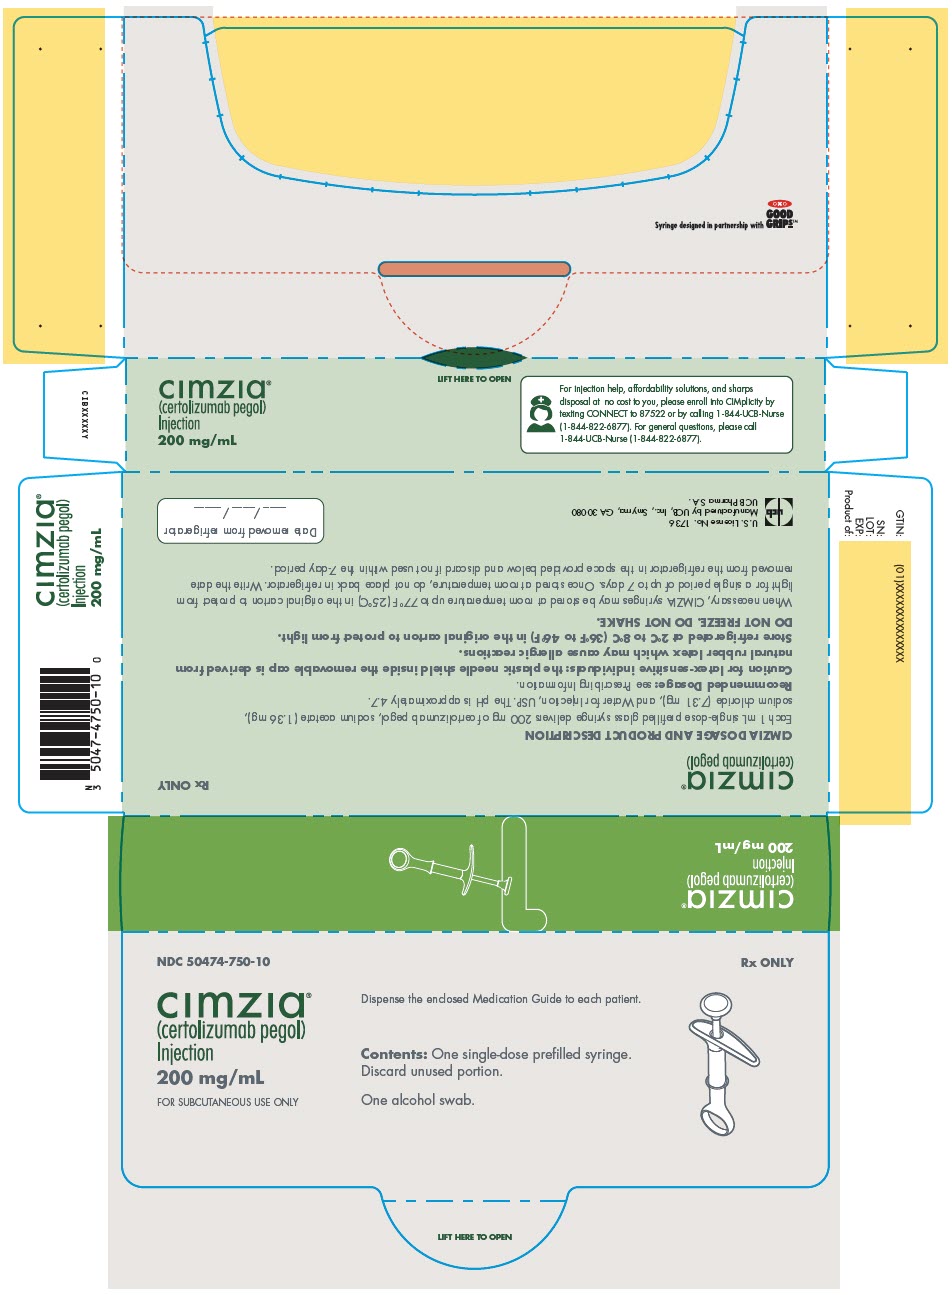
Injection: 200 mg/mL clear to opalescent, colorless to yellow solution in a single-dose prefilled syringe
Tuberculosis
Cases of reactivation of tuberculosis or new tuberculosis infections have been observed in patients receiving CIMZIA, including patients who have previously or concomitantly received treatment for latent or active tuberculosis. Reports included cases of pulmonary and extrapulmonary (i.e., disseminated) tuberculosis. Evaluate patients for tuberculosis risk factors and test for latent infection prior to initiating CIMZIA and periodically during therapy.
Treatment of latent tuberculosis infection prior to therapy with TNF-blocking agents has been shown to reduce the risk of tuberculosis reactivation during therapy. Prior to initiating CIMZIA, assess if treatment for latent tuberculosis is needed; and consider an induration of 5 mm or greater a positive tuberculin skin test result, even for patients previously vaccinated with Bacille Calmette-Guerin (BCG).
Consider anti-tuberculosis therapy prior to initiation of CIMZIA in patients with a past history of latent or active tuberculosis in whom an adequate course of treatment cannot be confirmed, and for patients with a negative test for latent tuberculosis but having risk factors for tuberculosis infection. Despite previous or concomitant treatment for latent tuberculosis, cases of active tuberculosis have occurred in patients treated with CIMZIA. Some patients who have been successfully treated for active tuberculosis have redeveloped tuberculosis while being treated with CIMZIA. Consultation with a physician with expertise in the treatment of tuberculosis is recommended to aid in the decision of whether initiating anti-tuberculosis therapy is appropriate for an individual patient.
Strongly consider tuberculosis in patients who develop a new infection during CIMZIA treatment, especially in patients who have previously or recently traveled to countries with a high prevalence of tuberculosis, or who have had close contact with a person with active tuberculosis.
Monitoring
Patients should be closely monitored for the development of signs and symptoms of infection during and after treatment with CIMZIA, including the development of tuberculosis in patients who tested negative for latent tuberculosis infection prior to initiating therapy. Tests for latent tuberculosis infection may also be falsely negative while on therapy with CIMZIA.
CIMZIA should be discontinued if a patient develops a serious infection or sepsis. A patient who develops a new infection during treatment with CIMZIA should be closely monitored, undergo a prompt and complete diagnostic workup appropriate for an immunocompromised patient, and appropriate antimicrobial therapy should be initiated.
Invasive Fungal Infections
For patients who reside or travel in regions where mycoses are endemic, invasive fungal infection should be suspected if they develop a serious systemic illness. Appropriate empiric antifungal therapy should be considered while a diagnostic workup is being performed. Antigen and antibody testing for histoplasmosis may be negative in some patients with active infection. When feasible, the decision to administer empiric antifungal therapy in these patients should be made in consultation with a physician with expertise in the diagnosis and treatment of invasive fungal infections and should take into account both the risk for severe fungal infection and risks of antifungal therapy.
Adverse Reactions Most Commonly Leading to Discontinuation of Treatment in Premarketing Controlled Trials
The proportion of patients with Crohn's disease who discontinued treatment due to adverse reactions in the controlled clinical studies was 8% for CIMZIA and 7% for placebo. The most common adverse reactions leading to the discontinuation of CIMZIA (for at least 2 patients and with a higher incidence than placebo) were abdominal pain (0.4% CIMZIA, 0.2% placebo), diarrhea (0.4% CIMZIA, 0% placebo), and intestinal obstruction (0.4% CIMZIA, 0% placebo).
The proportion of patients with rheumatoid arthritis who discontinued treatment due to adverse reactions in the controlled clinical studies was 5% for CIMZIA and 2.5% for placebo. The most common adverse reactions leading to discontinuation of CIMZIA were tuberculosis infections (0.5%); and pyrexia, urticaria, pneumonia, and rash (0.3%).
Controlled Studies with Crohn's Disease
The data described below reflect exposure to CIMZIA at 400 mg subcutaneous dosing in studies of patients with Crohn's disease. In the safety population in controlled studies, a total of 620 patients with Crohn's disease received CIMZIA at a dose of 400 mg, and 614 subjects received placebo (including subjects randomized to placebo in Study CD2 following open-label dosing of CIMZIA at Weeks 0, 2, 4). In controlled and uncontrolled studies, 1,564 patients received CIMZIA at some dose level, of whom 1,350 patients received 400 mg CIMZIA. Approximately 55% of subjects were female, 45% were male, and 94% were Caucasian. The majority of patients in the active group were between the ages of 18 and 64.
During controlled clinical studies, the proportion of patients with serious adverse reactions was 10% for CIMZIA and 9% for placebo. The most common adverse reactions (occurring in ≥ 5% of CIMZIA-treated patients, and with a higher incidence compared to placebo) in controlled clinical studies with CIMZIA were upper respiratory infections (e.g. nasopharyngitis, laryngitis, viral infection) in 20% of CIMZIA-treated patients and 13% of placebo-treated patients, urinary tract infections (e.g. bladder infection, bacteriuria, cystitis) in 7% of CIMZIA-treated patients and in 6% of placebo-treated patients, and arthralgia (6% CIMZIA, 4% placebo).
Other Adverse Reactions
The most commonly occurring adverse reactions in controlled trials of Crohn's disease were described above. Other serious or significant adverse reactions reported in controlled and uncontrolled studies in Crohn's disease and other diseases, occurring in patients receiving CIMZIA at doses of 400 mg or other doses include:
Blood and lymphatic system disorders:Anemia, leukopenia, lymphadenopathy, pancytopenia, and thrombophilia.
Cardiac disorders:Angina pectoris, arrhythmias, atrial fibrillation, cardiac failure, hypertensive heart disease, myocardial infarction, myocardial ischemia, pericardial effusion, pericarditis, stroke and transient ischemic attack.
Eye disorders:Optic neuritis, retinal hemorrhage, and uveitis.
General disorders and administration site conditions:Bleeding and injection site reactions.
Hepatobiliary disorders: Elevated liver enzymes and hepatitis.
Immune system disorders: Alopecia totalis.
Psychiatric disorders:Anxiety, bipolar disorder, and suicide attempt.
Renal and urinary disorders:Nephrotic syndrome and renal failure.
Reproductive system and breast disorders:Menstrual disorder.
Skin and subcutaneous tissue disorders:Dermatitis, erythema nodosum, and urticaria.
Vascular disorders:Thrombophlebitis, vasculitis.
Controlled Studies with Rheumatoid Arthritis
CIMZIA was studied primarily in placebo-controlled trials and in long-term follow-up studies. The data described below reflect the exposure to CIMZIA in 2,367 RA patients, including 2,030 exposed for at least 6 months, 1,663 exposed for at least one year and 282 for at least 2 years; and 1,774 in adequate and well-controlled studies. In placebo-controlled studies, the population had a median age of 53 years at entry; approximately 80% were females, 93% were Caucasian and all patients were suffering from active rheumatoid arthritis, with a median disease duration of 6.2 years. Most patients received the recommended dose of CIMZIA or higher.
Table 1 summarizes the reactions reported at a rate of at least 3% in patients treated with CIMZIA 200 mg every other week compared to placebo (saline formulation), given concomitantly with methotrexate.
Table 1: Adverse Reactions Reported by ≥3% of Patients Treated with CIMZIA Dosed Every Other Week during Placebo-Controlled Period of Rheumatoid Arthritis Studies, with Concomitant Methotrexate.Adverse Reaction
(Preferred Term)
| Placebo+ MTX
EOW = Every other Week, MTX = Methotrexate. (%)
N =324
| CIMZIA 200 mg EOW + MTX(%)
N =640
|
|---|
| Upper respiratory tract infection | 2 | 6 |
| Headache | 4 | 5 |
| Hypertension | 2 | 5 |
| Nasopharyngitis | 1 | 5 |
| Back pain | 1 | 4 |
| Pyrexia | 2 | 3 |
| Pharyngitis | 1 | 3 |
| Rash | 1 | 3 |
| Acute bronchitis | 1 | 3 |
| Fatigue | 2 | 3 |
Hypertensive adverse reactions were observed more frequently in patients receiving CIMZIA than in controls. These adverse reactions occurred more frequently among patients with a baseline history of hypertension and among patients receiving concomitant corticosteroids and non-steroidal anti-inflammatory drugs (NSAIDs).
Patients receiving CIMZIA 400 mg as monotherapy every 4 weeks in rheumatoid arthritis controlled clinical trials had similar adverse reactions to those patients receiving CIMZIA 200 mg every other week.
Other Adverse Reactions
Other infrequent adverse reactions (occurring in less than 3% of RA patients) were similar to those seen in Crohn's disease patients.
Polyarticular Juvenile Idiopathic Arthritis Clinical Study
CIMZIA has been studied in 193 patients with juvenile idiopathic arthritis (JIA) with active polyarthritis aged 2 years and older. In general, the safety profile for pediatric patients with JIA with active polyarthritis was similar to the safety profile seen in adult RA patients treated with CIMZIA.
Psoriatic Arthritis Clinical Study
CIMZIA has been studied in 409 patients with psoriatic arthritis (PsA) in a placebo-controlled trial. The safety profile for patients with PsA treated with CIMZIA was similar to the safety profile seen in patients with RA and previous experience with CIMZIA
.
Ankylosing Spondylitis Clinical Study
CIMZIA has been studied in 325 patients with axial spondyloarthritis of whom the majority had ankylosing spondylitis (AS) in a placebo-controlled study (AS-1). The safety profile for patients in study AS-1 treated with CIMZIA was similar to the safety profile seen in patients with RA.
Non-radiographic Axial Spondyloarthritis Clinical Study
CIMZIA has been studied in 317 patients with non-radiographic axial spondyloarthritis (nr-axSpA-1). The safety profile for patients with nr-axSpA treated with CIMZIA was similar to the safety profile seen in patients with RA and previous experience with CIMZIA.
Plaque Psoriasis Clinical Studies
In clinical studies, a total of 1112 subjects with plaque psoriasis were treated with CIMZIA. Of these, 779 subjects were exposed for at least 12 months, 551 for 18 months, and 66 for 24 months.
Data from three placebo-controlled studies (Studies PS-1, PS-2, and PS-3) in 1020 subjects (mean age 46 years, 66% males, 94% white) were pooled to evaluate the safety of CIMZIA
[see
Clinical Studies (14.7)]
.
Placebo-Controlled Period (Week 0-16)
In the placebo-controlled period of Studies PS-1, PS-2 and PS-3 in the 400 mg group, adverse events occurred in 63.5% of subjects in the CIMZIA group compared to 61.8% of subjects in the placebo group. The rates of serious adverse events were 4.7% in the CIMZIA group and 4.5% in the placebo group. Table 2 summarizes the adverse reactions that occurred at a rate of at least 1% and at a higher rate in the CIMZIA group than in the placebo group.
Table 2: Adverse Reactions Occurring in ≥1% of Subjects in the CIMZIA Group and More Frequently than in the Placebo Group in the Plaque Psoriasis Studies PS-1, PS-2, and PS-3.| Adverse Reactions | Cimzia 400 mg every other week
n (%)
N=342
| Cimzia 200 mg
Subjects received 400 mg of CIMZIA at Weeks 0, 2, and 4, followed by 200 mg every other week. every other week
n (%)
N=350
| Placebo
n (%)
N=157
|
|---|
| Upper respiratory tract infections
Upper respiratory tract infection cluster includes upper respiratory tract infection, pharyngitis bacterial, pharyngitis streptococcal, upper respiratory tract infection bacterial, viral upper respiratory tract infection, viral pharyngitis, viral sinusitis, and nasopharyngitis. | 75 (21.9) | 68 (19.4) | 33 (21.0) |
| Headache
Headache includes headache and tension headache. | 13 (3.8) | 10 (2.9) | 4 (2.5) |
| Injection site reactions
Injection site reactions cluster includes injection site reaction, injection site erythema, injection site bruising, injection site discoloration, injection site pain, and injection site swelling. | 11 (3.2) | 6 (1.7) | 1 (0.6) |
| Cough | 11 (3.2) | 4 (1.1) | 3 (1.9) |
| Herpes infections
Herpes infections cluster includes oral herpes, herpes dermatitis, herpes zoster, and herpes simplex. | 5 (1.5) | 5 (1.4) | 2 (1.3) |
Elevated Liver Enzymes
Elevated liver enzymes were reported more frequently in the CIMZIA-treated subjects (4.3% in the 200 mg group and 2.3% in the 400 mg group) than in the placebo-treated subjects (2.5%). Of CIMZIA-treated subjects who had elevation of liver enzymes, two subjects were discontinued from the trial. In controlled Phase 3 studies of CIMZIA in adults with PsO with a controlled period duration ranging from 0 to 16 weeks, AST and/or ALT elevations ≥5 × ULN occurred in 0.9% of CIMZIA 200 mg or CIMZIA 400 mg arms and none in placebo arm.
Psoriasis-Related Adverse Events
In controlled clinical studies in psoriasis, change of plaque psoriasis into a different psoriasis sub-types (including erythrodermic, pustular and guttate), was observed in <1% of Cimzia treated subjects.
Adverse Reactions of Special Interest Across Indications
Infections
The incidence of infections in controlled studies in Crohn's disease was 38% for CIMZIA-treated patients and 30% for placebo-treated patients. The infections consisted primarily of upper respiratory infections (20% for CIMZIA, 13% for placebo). The incidence of serious infections during the controlled clinical studies was 3% per patient-year for CIMZIA-treated patients and 1% for placebo-treated patients. Serious infections observed included bacterial and viral infections, pneumonia, and pyelonephritis.
The incidence of new cases of infections in controlled clinical studies in rheumatoid arthritis was 0.91 per patient-year for all CIMZIA-treated patients and 0.72 per patient-year for placebo-treated patients. The infections consisted primarily of upper respiratory tract infections, herpes infections, urinary tract infections, and lower respiratory tract infections. In the controlled rheumatoid arthritis studies, there were more new cases of serious infection adverse reactions in the CIMZIA treatment groups, compared to the placebo groups (0.06 per patient-year for all CIMZIA doses vs. 0.02 per patient-year for placebo). Rates of serious infections in the 200 mg every other week dose group were 0.06 per patient-year and in the 400 mg every 4 weeks dose group were 0.04 per patient-year. Serious infections included tuberculosis, pneumonia, cellulitis, and pyelonephritis. In the placebo group, no serious infection occurred in more than one subject. There is no evidence of increased risk of infections with continued exposure over time
[see
Warnings and Precautions (5.1)]
.
In controlled clinical studies in psoriasis, the incidence rates of infections were similar in the CIMZIA and placebo groups. The infections consisted primarily of upper respiratory tract infections and viral infections (including herpes infections). Serious adverse events of infection occurred in CIMZIA-treated patients during the placebo-controlled periods of the pivotal studies (pneumonia, abdominal abscess, and hematoma infection) and Phase 2 study (urinary tract infection, gastroenteritis, and disseminated tuberculosis).
In an open-label clinical study of 193 pediatric patients with JIA with active polyarthritis, there were 26 serious infections; the most frequently reported serious infection was pneumonia.
Tuberculosis and Opportunistic Infections
In completed and ongoing global clinical studies in all indications including 5,118 CIMZIA-treated patients, the overall rate of tuberculosis is approximately 0.61 per 100 patient-years across all indications.
The majority of cases occurred in countries with high endemic rates of TB. Reports include cases of disseminated (miliary, lymphatic, and peritoneal) as well as pulmonary TB. The median time to onset of TB for all patients exposed to CIMZIA across all indications was 345 days. In the studies with CIMZIA in RA, there were 36 cases of TB among 2,367 exposed patients, including some fatal cases. Rare cases of opportunistic infections have also been reported in these clinical trials. In Phase 2 and Phase 3 studies with CIMZIA in plaque psoriasis, there were 2 cases of TB among 1112 exposed patients
[see
Warnings and Precautions (5.1)].
In an open-label clinical study of 193 pediatric patients with JIA with active polyarthritis, opportunistic infections consisted of tuberculosis, liver tuberculosis, varicella, pneumonia fungal, and esophageal candidiasis. Two cases of disseminated tuberculosis (liver TB and disseminated TB) were fatal.
Malignancies
In clinical studies of CIMZIA, the overall incidence rate of malignancies was similar for CIMZIA-treated and control patients. For some TNF blockers, more cases of malignancies have been observed among patients receiving those TNF blockers compared to control patients
[see
Warnings and Precautions (5.2)].
Heart Failure
In placebo-controlled and open-label studies, cases of new or worsening heart failure have been reported for CIMZIA-treated patients. The majority of these cases were mild to moderate and occurred during the first year of exposure
[see
Warnings and Precautions (5.3)].
Hypersensitivity Reactions
The following symptoms that could be compatible with hypersensitivity reactions have been reported rarely following CIMZIA administration to patients: angioedema, allergic dermatitis, dizziness (postural), dyspnea, hot flush, hypotension, injection site reactions, malaise, pyrexia, rash, serum sickness, and (vasovagal) syncope
[see
Warnings and Precautions (5.4)]
.
Autoantibodies
In clinical studies in Crohn's disease, 4% of patients treated with CIMZIA and 2% of patients treated with placebo that had negative baseline ANA titers developed positive titers during the studies. One of the 1,564 Crohn's disease patients treated with CIMZIA developed symptoms of a lupus-like syndrome.
In clinical trials of TNF blockers, including CIMZIA, in patients with RA, some patients have developed ANA. Four patients out of 2,367 patients treated with CIMZIA in RA clinical studies developed clinical signs suggestive of a lupus-like syndrome. The impact of long-term treatment with CIMZIA on the development of autoimmune diseases is unknown
[see
Warnings and Precautions (5.9)].
In a clinical study in pediatric patients with JIA with active polyarthritis, 17.1% of patients treated with CIMZIA that had negative baseline ANA titers developed positive titers during the study. 1.1% of the patients developed anti-dsDNA antibodies during the study; no patients developed symptoms of a lupus-like syndrome.
The observed incidence of anti-drug antibodies is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of anti-drug antibodies in the studies described below with the incidence of anti-drug antibodies in other studies, including those of certolizumab pegol or of other certolizumab products.
Patients with Crohn's disease were tested at multiple time points for antibodies to certolizumab pegol during Studies CD1 and CD2. In patients continuously exposed to CIMZIA, the overall percentage of patients who were antibody positive to CIMZIA on at least one occasion was 8%; approximately 6% were neutralizing
in vitro. No apparent correlation of antibody development to adverse events or efficacy was observed. Patients treated with concomitant immunosuppressants had a lower rate of antibody development than patients not taking immunosuppressants at baseline (3% and 11%, respectively). The following adverse events were reported in Crohn's disease patients who were antibody-positive (N = 100) at an incidence at least 3% higher compared to antibody-negative patients (N = 1,242): abdominal pain, arthralgia, edema peripheral, erythema nodosum, injection site erythema, injection site pain, pain in extremity, and upper respiratory tract infection.
In two long-term (up to 7 years of exposure), open-label Crohn's disease studies, overall 23% (207/903) of patients developed antibodies against certolizumab pegol on at least one occasion. Of the 207 patients who were antibody positive, 152 (73%) had a persistent reduction of drug plasma concentration, which represents 17% (152/903) of the study population. The data from these two studies do not suggest an association between the development of antibodies and adverse events.
The overall percentage of patients with antibodies to certolizumab pegol detectable on at least one occasion was 7% (105 of 1,509) in the rheumatoid arthritis placebo-controlled trials. Approximately one third (3%, 39 of 1,509) of these patients had antibodies with neutralizing activity
in vitro. Patients treated with concomitant immunosuppressants (MTX) had a lower rate of antibody development than patients not taking immunosuppressants at baseline. Patients treated with concomitant immunosuppressant therapy (MTX) in RA-I, RA-II, RA-III had a lower rate of neutralizing antibody formation overall than patients treated with CIMZIA monotherapy in RA-IV (2% vs. 8%). Both the loading dose of 400 mg every other week at Weeks 0, 2 and 4 and concomitant use of MTX were associated with reduced immunogenicity.
Antibody formation was associated with lowered drug plasma concentration and reduced efficacy. In patients receiving the recommended CIMZIA dosage of 200 mg every other week with concomitant MTX, the ACR20 response was lower among antibody positive patients than among antibody-negative patients (Study RA-I, 48% versus 60%; Study RA-II 35% versus 59%, respectively). In Study RA-III, too few patients developed antibodies to allow for meaningful analysis of ACR20 response by antibody status. In Study RA-IV (monotherapy), the ACR20 response was 33% versus 56%, antibody-positive versus antibody-negative status, respectively
[see
Clinical Pharmacology (12.3)].
No association was seen between antibody development and the development of adverse events.
Approximately 8 % (22/265) and 19% (54/281) of subjects with psoriasis who received CIMZIA 400 mg every 2 weeks and CIMZIA 200 mg every 2 weeks for 48 weeks, respectively, developed antibodies to certolizumab pegol. Of the subjects who developed antibodies to certolizumab pegol, 45% (27/60) had antibodies that were classified as neutralizing. Antibody formation was associated with lowered drug plasma concentration and reduced efficacy.
A more sensitive and drug tolerant electrochemiluminesence (ECL)-based bridging assay was used for the first time in the nr-axSpA-1 study, resulting in a greater proportion of samples having measurable antibodies to certolizumab pegol and thus a greater incidence of patients being classed as antibody positive. In the placebo-controlled trial in patients with non-radiographic axial spondyloarthritis, after up to 52 weeks of treatment, the overall incidence of patients who were antibody positive to certolizumab pegol was 97% (248/255 patients). Of these antibody positive patients, higher titers were associated with reduced certolizumab pegol plasma levels.
The data above reflect the percentage of patients whose test results were considered positive for antibodies to certolizumab pegol in an ELISA or ECL-based bridging assay, and are highly dependent on the sensitivity and specificity of the assay.
In a clinical study of pediatric patients with JIA with active polyarthritis, immunogenicity was evaluated using an ECL-based assay. For the patients receiving the recommended CIMZIA dose, the incidence of treatment emergent-anti-certolizumab pegol antibody positivity was 92.4% for the entire treatment period. Of these antibody positive patients, higher titers were associated with reduced certolizumab pegol plasma levels.
Pregnancy Exposure Registry
There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to CIMZIA during pregnancy. For more information, healthcare providers or patients can contact:
MotherToBaby Pregnancy Studies conducted by the Organization of Teratology Information Specialists (OTIS). The OTIS AutoImmune Diseases Study at 1-877-311-8972 or visit http://mothertobaby.org/pregnancy-studies/.
Risk Summary
Limited data from an ongoing pregnancy exposure registry on use of CIMZIA in pregnant women are not sufficient to inform a risk of major birth defects or other adverse pregnancy outcomes. However, certolizumab pegol plasma concentrations obtained from two studies of CIMZIA use during the third trimester of pregnancy demonstrated that placental transfer of certolizumab pegol was negligible in most infants at birth, and low in other infants at birth
(see
Data)
. There are risks to the mother and fetus associated with active rheumatoid arthritis or Crohn's disease. The theoretical risks of administration of live or live-attenuated vaccines to the infants exposed
in uteroto CIMZIA should be weighed against the benefits of vaccinations
(see
Clinical Considerations)
. No adverse developmental effects were observed in animal reproduction studies during which pregnant rats were administered intravenously a rodent anti-murine TNFα pegylated Fab' fragment (cTN3 PF) similar to certolizumab pegol during organogenesis at up to 2.4 times the recommended human dose of 400 mg every four weeks.
The background risk of major birth defects and miscarriage for the indicated population(s) are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies are 2 to 4% and 15 to 20%, respectively.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
Published data suggest that the risk of adverse pregnancy outcomes in women with rheumatoid arthritis or Crohn's disease is correlated with maternal disease activity and that active disease increases the risk of adverse pregnancy outcomes, including fetal loss, preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) and small for gestational age birth.
Fetal/Neonatal Adverse Reaction
Due to its inhibition of TNFα, CIMZIA administered during pregnancy could affect immune responses in the
in utero-exposed newborn and infant. The clinical significance of BLQ or low levels is unknown for
in utero-exposed infants. Additional data available from one exposed infant suggest that CIMZIA may be eliminated at a slower rate in infants than in adults
(see
Data).
The safety of administering live or live-attenuated vaccines in exposed infants is unknown.
Dosing During Pregnancy and the Postpartum Period
Based on a pharmacokinetic study in pregnant women with psoriasis or rheumatological diseases who were administered certolizumab pegol during pregnancy until at least 12 weeks postpartum, plasma certolizumab pegol concentrations throughout pregnancy were within the range observed in non-pregnant women with the same chronic inflammatory diseases. No dosage adjustment is required for pregnant women
[see
Clinical Pharmacology (12.3)].
Data
Human Data
A limited number of pregnancies have been reported in an ongoing pregnancy exposure registry. Due to the small number of CIMZIA-exposed pregnancies with known outcomes (n=217), no meaningful comparisons between the exposed group and control groups may be conducted to determine an association with CIMZIA and major birth defects or adverse pregnancy outcomes.
A multicenter clinical study was conducted in 16 women treated with CIMZIA at a maintenance dose of 200 mg every 2 weeks or 400 mg every 4 weeks during the third trimester of pregnancy for rheumatological diseases or Crohn's disease. The last dose of CIMZIA was given on average 11 days prior to delivery (range 1 to 27 days). Certolizumab pegol plasma concentrations were measured in samples from mothers and infants using an assay that can measure certolizumab pegol concentrations at or above 0.032 mcg/mL. Certolizumab pegol plasma concentrations measured in the mothers at delivery (range: 4.96 to 49.4 mcg/mL) were consistent with non-pregnant women's plasma concentrations in Study RA-I
[see
Clinical Studies (14.2)]
. Certolizumab pegol plasma concentrations were not measurable in 13 out of 15 infants at birth. The concentration of certolizumab pegol in one infant was 0.0422 mcg/mL at birth (infant/mother plasma ratio of 0.09%). In a second infant, delivered by emergency Caesarean section, the concentration was 0.485 mcg/mL (infant/mother plasma ratio of 4.49%). At Week 4 and Week 8, all 15 infants had no measurable concentrations. Among 16 exposed infants, one serious adverse reaction was reported in a neonate who was treated empirically with intravenous antibiotics due to an increased white blood cell count; blood cultures were negative. The certolizumab pegol plasma concentrations for this infant were not measurable at birth, Week 4, or Week 8.
In another clinical study conducted in 10 pregnant women with Crohn´s disease treated with CIMZIA (400 mg every 4 weeks for every mother), certolizumab pegol concentrations were measured in maternal blood as well as in cord and infant blood at the day of birth with an assay that can measure concentrations at or above 0.41 mcg/mL. The last dose of CIMZIA was given on average 19 days prior to delivery (range 5 to 42 days). Plasma certolizumab pegol concentrations ranged from not measurable to 1.66 mcg/mL in cord blood and 1.58 mcg/mL in infant blood; and ranged from 1.87 to 59.57 mcg/mL in maternal blood. Plasma certolizumab pegol concentrations were lower (by at least 75%) in the infants than in mothers suggesting low placental transfer of certolizumab pegol. In one infant, the plasma certolizumab pegol concentration declined from 1.02 to 0.84 mcg/mL over 4 weeks suggesting that certolizumab pegol may be eliminated at a slower rate in infants than adults.
Animal Data
Because certolizumab pegol does not cross-react with mouse or rat TNFα, reproduction studies were performed in rats using a rodent anti-murine TNFα pegylated Fab' fragment (cTN3 PF) similar to certolizumab pegol. Animal reproduction studies have been performed in rats during organogenesis at intravenous doses up to 100 mg/kg (about 2.4 times the recommended human dose of 400 mg, based on the surface area) and have revealed no evidence of harm to the fetus due to cTN3 PF.
Risk Summary
In a multicenter clinical study of 17 lactating women treated with CIMZIA at 200 mg every 2 weeks or 400 mg every 4 weeks, minimal certolizumab pegol concentrations were observed in breast milk. No serious adverse reactions were noted in the 17 infants in the study. There are no data on the effects on milk production. In a separate study, certolizumab pegol concentrations were not detected in the plasma of 9 breastfed infants at 4 weeks post-partum
(see
Data)
. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for CIMZIA and any potential adverse effects on the breastfed infant from CIMZIA or from the underlying maternal condition.
Data
A multicenter clinical study designed to evaluate breast milk was conducted in 17 lactating women who were at least 6 weeks post-partum and had received at least 3 consecutive doses of CIMZIA 200 mg every 2 weeks or 400 mg every 4 weeks for rheumatological disease or Crohn's disease. The effects of certolizumab pegol on milk production were not studied. The concentration of certolizumab pegol in breast milk was not measurable in 77 (56 %) of the 137 samples taken over the dosing periods using an assay that can measure certolizumab pegol concentrations at or above 0.032 mcg/mL. The median of the estimated average daily infant doses was 0.0035 mg/kg/day (range: 0 to 0.01 mg/kg/day). The percentage of the maternal dose (200 mg CIMZIA dosed once every 2 weeks), that reaches an infant ranged from 0.56% to 4.25% based on samples with measurable certolizumab pegol concentration. No serious adverse reactions were noted in the 17 breastfed infants in the study.
In a separate study, plasma certolizumab pegol concentrations were collected 4 weeks after birth in 9 breastfed infants whose mothers had been currently taking CIMZIA (regardless of being exclusively breastfed or not). Certolizumab pegol in infant plasma was not measurable i.e., below 0.032 mcg/mL.
Absorption
A total of 126 healthy subjects received doses of up to 800 mg certolizumab pegol subcutaneously (sc) and up to 10 mg/kg intravenously (IV) in four pharmacokinetic studies. Data from these studies demonstrate that single intravenous and subcutaneous doses of certolizumab pegol have predictable dose-related plasma concentrations with a linear relationship between the dose administered and the maximum plasma concentration (C
max), and the Area Under the certolizumab pegol plasma concentration versus time Curve (AUC). A mean C
maxof approximately 43 to 49 mcg/mL occurred at Week 5 during the initial loading dose period using the recommended dose regimen for the treatment of patients with rheumatoid arthritis (400 mg sc at Weeks 0, 2 and 4 followed by 200 mg every other week).
Certolizumab pegol plasma concentrations were broadly dose-proportional and pharmacokinetics observed in patients with rheumatoid arthritis, Crohn's disease, and plaque psoriasis were consistent with those seen in healthy subjects.
Following subcutaneous administration, peak plasma concentrations of certolizumab pegol were attained between 54 and 171 hours post-injection. Certolizumab pegol has bioavailability (F) of approximately 80% (ranging from 76% to 88%) following subcutaneous administration compared to intravenous administration.
In pediatric patients with JIA with active polyarthritis,
mean peak plasma concentrations, measured 1 week following loading dose and maintenance dose were 58.8 µg/ml and 41.8 µg/ml, respectively. Similar peak plasma concentrations were observed across the different body weight groups (10 kg to less than 20 kg, 20 kg to less than 40 kg, and greater than or equal to 40 kg).
Distribution
The steady state volume of distribution (Vss) was estimated as 4.7 to 8 L in the population pharmacokinetic analysis for adult patients with Crohn's disease, patients with rheumatoid arthritis, and adult patients with plaque psoriasis.
The volume of distribution in pediatric patients with JIA with active polyarthritis was dependent on body size.
Metabolism
The metabolism of certolizumab pegol has not been studied in human subjects. Data from animals indicate that once cleaved from the Fab' fragment the PEG moiety is mainly excreted in urine without further metabolism.
Elimination
PEGylation, the covalent attachment of PEG polymers to peptides, delays the metabolism and elimination of these entities from the circulation by a variety of mechanisms, including decreased renal clearance, proteolysis, and immunogenicity. Accordingly, certolizumab pegol is an antibody Fab' fragment conjugated with PEG in order to extend the terminal plasma elimination half-life (t
1/2) of the Fab'. The terminal elimination phase half-life (t
1/2) was approximately 14 days for all doses tested. The clearance following IV administration to healthy subjects ranged from 9.21 mL/h to 14.38 mL/h. The clearance following sc dosing was estimated 17 mL/h in the Crohn's disease population PK analysis with an inter-subject variability of 38% (CV) and an inter-occasion variability of 16%. Similarly, the clearance following sc dosing was estimated as 21.0 mL/h in the RA population PK analysis, with an inter-subject variability of 30.8% (%CV) and inter-occasion variability 22.0%. The clearance following subcutaneous dosing in patients with plaque psoriasis was 14 mL/h with an inter-subject variability of 22.2% (CV). The route of elimination of certolizumab pegol has not been studied in human subjects. Studies in animals indicate that the major route of elimination of the PEG component is via urinary excretion.
In pediatric patients with JIA with active polyarthritis, clearance
was body weight dependent, and t
1/2was similar to adult indications.
Specific Populations
Population pharmacokinetic analysis was conducted on data from adult patients with rheumatoid arthritis and adult patients with Crohn's disease, to evaluate the effect of age, race, sex, concomitant medication (NSAIDs, Cyclooxygenase-2 (COX-2) inhibitors, DMARDs including methotrexate), creatinine clearance and presence of anti-certolizumab antibodies on pharmacokinetics of certolizumab pegol. A population pharmacokinetic analysis was also conducted on data from patients with plaque psoriasis to evaluate the effect of age, sex, body weight, and presence of anti-certolizumab pegol antibodies. Only bodyweight and presence of anti-certolizumab antibodies significantly affected certolizumab pegol pharmacokinetics. Pharmacokinetic exposure was inversely related to body weight but pharmacodynamic exposure-response analysis showed that no additional therapeutic benefit would be expected from a weight-adjusted dose regimen. When assessed using the previous ELISA method, the presence of anti-certolizumab antibodies was associated with a ≥ 3 to 4 fold increase in clearance.
Geriatric Patients:Pharmacokinetics of certolizumab pegol was not different in elderly compared to young adults (≥18 years old).
Pregnant Patients
In a pharmacokinetic study, 21 women were treated with CIMZIA subcutaneously during pregnancy and through at least 12 weeks postpartum. Based on population pharmacokinetic analysis, median plasma pre-dose concentrations and C
maxof certolizumab pegol were lower (by up to 36% and 19%, respectively) during pregnancy compared to postpartum; however, the concentrations during pregnancy were within the range of observed concentrations in non-pregnant adult patients in clinical studies of rheumatoid arthritis, ankylosing spondylitis, non-radiographic axial spondyloarthritis, and plaque psoriasis.
Pediatric Patients:
In the JIA with active polyarthritis study (NCT01550003), the mean trough plasma concentrations at Week 12 (steady-state) were 31.8 µg/mL, 27.9 µg/mL, and 36.8 µg/mL for patients weighing 10 to <20 kg, 20 to <40 kg, and ≥40 kg, respectively. Population pharmacokinetic analyses showed that plasma concentrations in pediatric patients with JIA with active polyarthritis are in the same range as observed in adult patients with RA receiving a 200 mg Q2W maintenance dose.
Similar to the adult data, body weight and anti-certolizumab antibodies titers affected certolizumab pegol pharmacokinetics, where higher body weights and presence of anti-certolizumab antibodies was associated with lower exposures. There was no observed impact from the use of concomitant methotrexate on certolizumab pegol plasma concentrations.
Racial or Ethnic Groups:A specific clinical study showed no difference in pharmacokinetics between Caucasian and Japanese subjects.
Male and Female Patients:Pharmacokinetics of certolizumab pegol was similar in male and female subjects in both adult and pediatric patients.
Patients with Renal Impairment:Specific clinical studies have not been performed to assess the effect of renal impairment on the pharmacokinetics of CIMZIA. The pharmacokinetics of the PEG (polyethylene glycol) fraction of certolizumab pegol is expected to be dependent on renal function but has not been assessed in renal impairment. There are insufficient data to provide a dosing recommendation in moderate and severe renal impairment.
Drug Interaction Studies
Methotrexate pharmacokinetics is not altered by concomitant administration with CIMZIA in patients with rheumatoid arthritis. The effect of methotrexate on CIMZIA pharmacokinetics was not studied. However, methotrexate-treated patients have lower incidence of antibodies to CIMZIA. Thus, therapeutic plasma levels are more likely to be sustained when CIMZIA is administered with methotrexate in patients with rheumatoid arthritis.
Formal drug-drug interaction studies have not been conducted with CIMZIA upon concomitant administration with corticosteroids, nonsteroidal anti-inflammatory drugs, analgesics or immunosuppressants.
Study CD1
Study CD1 was a randomized placebo-controlled study in 662 patients with active Crohn's disease. CIMZIA or placebo was administered at Weeks 0, 2, and 4 and then every four weeks to Week 24. Assessments were done at Weeks 6 and 26. Clinical response was defined as at least a 100-point reduction in CDAI score compared to baseline, and clinical remission was defined as an absolute CDAI score of 150 points or lower.
The results for Study CD1 are provided in Table 3. At Week 6, the proportion of clinical responders was statistically significantly greater for CIMZIA-treated patients compared to controls. The difference in clinical remission rates was not statistically significant at Week 6. The difference in the proportion of patients who were in clinical response at both Weeks 6 and 26 was also statistically significant, demonstrating maintenance of clinical response.
Table 3: Study CD1 – Clinical Response and Remission, Overall Study Population| Timepoint | % Response or Remission (95% CI) |
|---|
Placebo
(N = 328)
| CIMZIA 400 mg
(N = 331)
|
|---|
| Week 6 |
| Clinical Response
Clinical response is defined as decrease in CDAI of at least 100 points, and clinical remission is defined as CDAI ≤ 150 points | 27%(22%, 32%)
| 35%(30%, 40%)
p-value < 0.05 logistic regression test |
| Clinical Remission
| 17%(13%, 22%)
| 22%(17%, 26%)
|
| Week 26 |
| Clinical Response | 27%(22%, 31%)
| 37%(32%, 42%)
|
| Clinical Remission | 18%(14%, 22%)
| 29%(25%, 34%)
|
| Both Weeks 6 & 26 |
| Clinical Response | 16%(12%, 20%)
| 23%(18%, 28%)
|
| Clinical Remission | 10%(7%, 13%)
| 14%(11%, 18%)
|
Study CD2
Study CD2 was a randomized treatment-withdrawal study in patients with active Crohn's disease. All patients who entered the study were dosed initially with CIMZIA 400 mg at Weeks 0, 2, and 4 and then assessed for clinical response at Week 6 (as defined by at least a 100-point reduction in CDAI score). At Week 6, a group of 428 clinical responders was randomized to receive either CIMZIA 400 mg or placebo, every four weeks starting at Week 8, as maintenance therapy through Week 24. Non-responders at Week 6 were withdrawn from the study. Final evaluation was based on the CDAI score at Week 26. Patients who withdrew or who received rescue therapy were considered not to be in clinical response. Three randomized responders received no study injections, and were excluded from the ITT analysis.
The results for clinical response and remission are shown in Table 4. At Week 26, a statistically significantly greater proportion of Week 6 responders were in clinical response and in clinical remission in the CIMZIA-treated group compared to the group treated with placebo.
Table 4: Study CD2 - Clinical Response and Clinical Remission| | % Response or Remission (95% CI) |
|---|
| | CIMZIA 400 mg ×3 + Placebo
N = 210
| CIMZIA
400 mg
N = 215
|
|---|
| Week 26 |
| Clinical Response
Clinical response is defined as decrease in CDAI of at least 100 points, and clinical remission is defined as CDAI ≤ 150 points | 36%(30%, 43%)
| 63%(56%, 69%)
p < 0.05 |
| Clinical Remission
| 29%(22%, 35%)
| 48%(41%, 55%)
|
Baseline use of immunosuppressants or corticosteroids had no impact on the clinical response to CIMZIA.
Clinical Response
The percent of CIMZIA-treated patients achieving ACR20, 50, and 70 responses in Studies RA-I and RA-IV are shown in Table 5. CIMZIA-treated patients had higher ACR20, 50 and 70 response rates at 6 months compared to placebo-treated patients. The results in study RA-II (619 patients) were similar to the results in RA-I at Week 24. The results in study RA-III (247 patients) were similar to those seen in study RA-IV. Over the one-year Study RA-I, 13% of CIMZIA-treated patients achieved a major clinical response, defined as achieving an ACR70 response over a continuous 6-month period, compared to 1% of placebo-treated patients.
Table 5: ACR Responses in Studies RA-I, and RA-IV (Percent of Patients) | Study RA-I
Methotrexate Combination
(24 and 52 weeks)
| Study RA-IV
Monotherapy
(24 weeks)
|
|---|
| Response | Placebo + MTX | CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 200 mg + MTX
q 2 weeks
| CIMZIA
200 mg + MTX - Placebo + MTX
| Placebo | CIMZIA
CIMZIA administered every 4 weeks not preceded by a loading dose regimen 400 mg
q 4 weeks
| CIMZIA
400 mg - Placebo
|
|---|
| N=199 | N=393 | (95% CI)
95% Confidence Intervals constructed using the large sample approximation to the Normal Distribution. | N=109 | N=111 | (95% CI)
|
|---|
| ACR20 | | | | | | |
| Week 24 | 14% | 59% | 45% (38%, 52%) | 9% | 46% | 36% (25%, 47%) |
| Week 52 | 13% | 53% | 40% (33%, 47%) | N/A | N/A | |
| ACR50 | | | | | | |
| Week 24 | 8% | 37% | 30% (24%, 36%) | 4% | 23% | 19% (10%, 28%) |
| Week 52 | 8% | 38% | 30% (24%, 37%) | N/A | N/A | |
| ACR70 | | | | | | |
| Week 24 | 3% | 21% | 18% (14%, 23%) | 0% | 6% | 6% (1%, 10%) |
| Week 52 | 4% | 21% | 18% (13%, 22%) | N/A | N/A | |
| Major Clinical Response
Major clinical response is defined as achieving ACR70 response over a continuous 6-month period | 1% | 13% | 12% (8%, 15%) | | | |
Table 6: Components of ACR Response in Studies RA-I and RA-IV | Study RA-I | Study RA-IV |
|---|
| Parameter
For Study RA-I, median is presented. For Study RA-IV, mean (SD) is presented except for CRP which presents geometric mean | Placebo +
MTX
N=199
| CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 200 mg + MTX q 2 weeks
N=393
| Placebo
N=109
| CIMZIA
CIMZIA administered every 4 weeks not preceded by a loading dose regimen 400 mg q 4 weeks
Monotherapy
N=111
|
|---|
| Baseline | Week 24 | Baseline | Week 24 | Baseline | Week 24 | Baseline | Week 24 |
|---|
| Number of tender joints (0-68) | 28 | 27 | 29 | 9 | 28 (12.5) | 24 (15.4) | 30 (13.7) | 16 (15.8) |
| Number of swollen joints (0-66) | 20 | 19 | 20 | 4 | 20 (9.3) | 16 (12.5) | 21 (10.1) | 12 (11.2) |
| Physician global assessment
Study RA-I - Visual Analog Scale: 0 = best, 100 = worst. Study RA-IV - Five Point Scale: 1 = best, 5 = worst | 66 | 56 | 65 | 25 | 4 (0.6) | 3 (1.0) | 4 (0.7) | 3 (1.1) |
| Patient global assessment
| 67 | 60 | 64 | 32 | 3 (0.8) | 3 (1.0) | 3 (0.8) | 3 (1.0) |
| Pain
Patient Assessment of Arthritis Pain
. Visual Analog Scale: 0 = best, 100 = worst
| 65 | 60 | 65 | 32 | 55 (20.8) | 60 (26.7) | 58 (21.9) | 39 (29.6) |
| Disability index (HAQ)
Health Assessment Questionnaire Disability Index; 0 = best, 3 = worst, measures the patient's ability to perform the following: dress/groom, arise, eat, walk, reach, grip, maintain hygiene, and maintain daily activity
All values are last observation carried forward.
| 1.75 | 1.63 | 1.75 | 1.00 | 1.55 (0.65) | 1.62 (0.68) | 1.43 (0.63) | 1.04 (0.74) |
CRP (mg/L)
| 16.0 | 14.0 | 16.0 | 4.0 | 11.3 | 13.5 | 11.6 | 6.4 |
The percent of patients achieving ACR20 responses by visit for Study RA-I is shown in Figure 1. Among patients receiving CIMZIA, clinical responses were seen in some patients within one to two weeks after initiation of therapy.
| Figure 1 Study RA-I ACR20 Response Over 52 Weeks
The same patients may not have responded at each time point |
|
Radiographic Response
In Study RA-I, inhibition of progression of structural damage was assessed radiographically and expressed as the change in modified Total Sharp Score (mTSS) and its components, the Erosion Score (ES) and Joint Space Narrowing (JSN) score, at Week 52, compared to baseline. CIMZIA inhibited the progression of structural damage compared to placebo plus MTX after 12 months of treatment as shown in Table 7. In the placebo group, 52% of patients experienced no radiographic progression (mTSS ≤0.0) at Week 52 compared to 69% in the CIMZIA 200 mg every other week treatment group. Study RA-II showed similar results at Week 24.
Table 7: Radiographic Changes at 6 and 12 months in Study RA-I | Placebo + MTX
N=199
Mean (SD)
| CIMZIA 200 mg + MTX
N=393
Mean (SD)
| CIMZIA 200 mg + MTX –
Placebo + MTX
Mean Difference
|
|---|
| An ANCOVA was fitted to the ranked change from baseline for each measure with region and treatment as factors and rank baseline as a covariate. |
| mTSS | | | |
| Baseline | 40 (45) | 38 (49) | -- |
| Week 24 | 1.3 (3.8) | 0.2 (3.2) | -1.1 |
| Week 52 | 2.8 (7.8) | 0.4 (5.7) | -2.4 |
| Erosion Score | | | |
| Baseline | 14 (21) | 15 (24) | -- |
| Week 24 | 0.7 (2.1) | 0.0 (1.5) | -0.7 |
| Week 52 | 1.5 (4.3) | 0.1 (2.5) | -1.4 |
| JSN Score | | | |
| Baseline | 25 (27) | 24 (28) | -- |
| Week 24 | 0.7 (2.4) | 0.2 (2.5) | -0.5 |
| Week 52 | 1.4 (5.0) | 0.4 (4.2) | -1.0 |
Physical Function Response
In studies RA-I, RA-II, RA-III, and RA-IV, CIMZIA-treated patients achieved greater improvements from baseline than placebo-treated patients in physical function as assessed by the Health Assessment Questionnaire – Disability Index (HAQ-DI) at Week 24 (RA-II, RA-III and RA-IV) and at Week 52 (RA-I).
Clinical Response
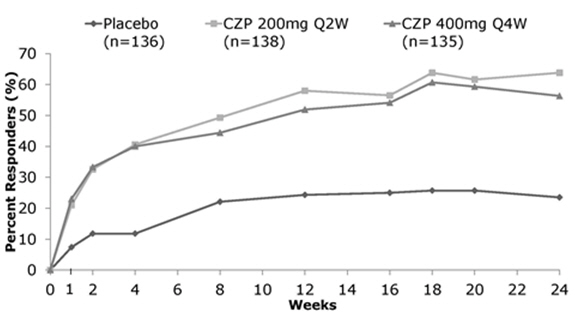
The percentage of CIMZIA-treated patients achieving ACR20, 50 and 70 responses in study PsA001 are shown in Table 8. ACR20 response rates at weeks 12 and 24 were higher for each CIMZIA dose group relative to placebo (95% confidence intervals for CIMZIA 200 mg minus placebo at weeks 12 and 24 of (23%, 45%) and (30%, 51%), respectively and 95% confidence intervals for CIMZIA 400 mg minus placebo at weeks 12 and 24 of (17%, 39%) and (22%, 44%), respectively). The results of the components of the ACR response criteria are shown in Table 9.
Patients with enthesitis at baseline were evaluated for mean improvement in Leeds Enthesitis Index (LEI). CIMZIA-treated patients receiving either 200 mg every 2 weeks or 400 mg every 4 weeks showed a reduction in enthesitis of 1.8 and 1.7, respectively as compared with a reduction in placebo-treated patients of 0.9 at week 12. Similar results were observed for this endpoint at week 24. Treatment with CIMZIA resulted in improvement in skin manifestations in patients with PsA.
Table 8: ACR Responses in Study PsA001 (Percent of Patients)| Response
Results are from the randomized set. Non-responder Imputation (NRI) is used for patients who escaped therapy or had missing data. | Placebo | CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 200 mg
Q2W
| CIMZIA
CIMZIA administered every 4 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 400 mg
Q4W
|
|---|
| N=136 | N=138 | N=135 |
|---|
| ACR20 | | | |
| Week 12 | 24% | 58% | 52% |
| Week 24 | 24% | 64% | 56% |
| ACR50 | | | |
| Week 12 | 11% | 36% | 33% |
| Week 24 | 13% | 44% | 40% |
| ACR70 | | | |
| Week 12 | 3% | 25% | 13% |
| Week 24 | 4% | 28% | 24% |
Table 9: Components of ACR Response in Study PsA001| Parameter | Placebo
Results are from the entire placebo group
N=136
| CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 200 mg Q2W
N=138
| CIMZIA
CIMZIA administered every 4 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 400 mg Q4W
N=135
|
|---|
| Baseline | Week 12 | Baseline | Week 12 | Baseline | Week 12 |
|---|
| All values presented represent the mean |
| Results are from the randomized set (either with imputation or observed case) |
| Number of tender joints (0-68)
Last Observation Carried Forward is used for missing data, early withdrawals or placebo escape | 20 | 17 | 22 | 11 | 20 | 11 |
| Number of swollen joints (0-66)
| 10 | 9 | 11 | 4 | 11 | 5 |
| Physician global assessment
, Patient and Physician Global Assessment of Disease Activity, VAS 0=best 100= worst | 59 | 44 | 57 | 25 | 58 | 29 |
| Patient global assessment
, | 57 | 50 | 60 | 33 | 60 | 40 |
| Pain
, The Patient Assessment of Arthritis Pain, VAS 0=no pain and 100= most severe pain | 60 | 50 | 60 | 33 | 61 | 39 |
| Disability index (HAQ)
, The HAQ-DI, 4 point scale 0=without difficulty and 3=unable to do | 1.30 | 1.15 | 1.33 | 0.87 | 1.29 | 0.90 |
| CRP (mg/L) | 18.56 | 14.75 | 15.36 | 5.67 | 13.71 | 6.34 |
The percent of patients achieving ACR20 responses by visit for PsA001 is shown in Figure 2.
| Randomized Set. Non-responder imputation used for patients with missing data or those who escaped therapy. |
| Figure 2: Study PsA001-ACR20 Response Over 24 Weeks
The same patients may not have responded at each time point. |
|
Radiographic Response
In study PsA001, inhibition of progression of structural damage was assessed radiographically and expressed as the change in modified total Sharp score (mTSS) and its components, the Erosion Score (ES) and Joint Space Narrowing score (JSN) at week 24, compared to baseline. The mTSS score was modified for psoriatic arthritis by addition of hand distal interphalangeal (DIP) joints.
Patients treated with CIMZIA 200 mg every other week demonstrated greater reduction in radiographic progression compared with placebo-treated patients at Week 24 as measured by change from baseline in total modified mTSS Score (estimated mean score was 0.18 in the placebo group compared with -0.02 in the CIMZIA 200 mg group; 95% CI for the difference was (-0.38, -0.04)). Patients treated with CIMZIA 400 mg every four weeks did not demonstrate greater inhibition of radiographic progression compared with placebo-treated patients at Week 24.
Physical Function Response
In Study PsA001, CIMZIA-treated patients showed improvement in physical function as assessed by the Health Assessment Questionnaire – Disability Index (HAQ-DI) at Week 24 as compared to placebo (estimated mean change from baseline was 0.19 in the placebo group compared with 0.54 in the CIMZIA 200 mg group; 95% CI for the difference was (-0.47, -0.22) and 0.46 in the CIMZIA 400 mg group; 95% CI for the difference was (-0.39, -0.14)).
Clinical Response
In study AS-1, at Week 12, a greater proportion of AS patients treated with CIMZIA 200 mg every 2 weeks or 400 mg every 4 weeks achieved ASAS 20 response compared to AS patients treated with placebo (Table 10). Responses were similar in patients receiving CIMZIA 200 mg every 2 weeks and CIMZIA 400 mg every 4 weeks. The results of the components of the ASAS response criteria and other measures of disease activity are shown in Table 11.
Table 10: ASAS Responses in AS patients at Weeks 12 and 24 in study AS-1| Parameters | Placebo
N=57
| CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 200 mg every 2 weeks
N=65
| CIMZIA
CIMZIA administered every 4 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 400 mg every 4 weeks
N=56
|
|---|
| All percents reflect the proportion of patients who responded in the full analysis set |
| ASAS20 | | | |
| Week 12 | 37% | 57% | 64% |
| Week 24 | 33% | 68% | 70% |
| ASAS40 | | | |
| Week 12 | 19% | 40% | 50% |
| Week 24 | 16% | 48% | 59% |
Table 11: Components of the ASAS response criteria and other measures of disease activity in AS patients at baseline and Week 12 in study AS-1 | Placebo
N=57
| CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 200 mg every 2 weeks
N=65
| CIMZIA
CIMZIA administered every 4 weeks preceded by a loading dose of 400 mg at Weeks 0, 2 and 4 400 mg every 4 weeks
N=56
|
|---|
| Baseline | Week 12 | Baseline | Week 12 | Baseline | Week 12 |
|---|
| All values presented represent the mean in the full analysis set |
| ASAS20 response criteria | | | | | | |
| -Patient Global Assessment (0-10) | 6.9 | 5.6 | 7.3 | 4.2 | 6.8 | 3.8 |
| -Total spinal pain (0-10) | 7.3 | 5.8 | 7.0 | 4.3 | 6.9 | 4.0 |
| -BASFI (0-10)
BASFI is Bath Ankylosing Spondylitis Functional Index | 6.0 | 5.2 | 5.6 | 3.8 | 5.7 | 3.8 |
| -Inflammation (0-10) | 6.7 | 5.5 | 6.7 | 3.8 | 6.4 | 3.4 |
| BASDAI (0-10)
BASDAI is Bath Ankylosing Spondylitis Disease Activity Index | 6.4 | 5.4 | 6.5 | 4.0 | 6.2 | 3.7 |
| BASMI
BASMI is Bath Ankylosing Spondylitis Metrology Index | 4.8 | 4.4 | 4.2 | 3.6 | 4.3 | 3.9 |
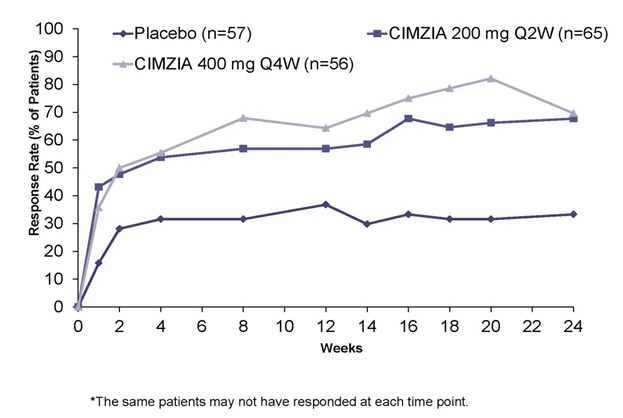
The percent of AS patients achieving ASAS20 responses by visit for Study AS001 is shown in Figure 3. Among patients receiving CIMZIA, clinical responses were seen in some AS patients within one to two weeks after initiation of therapy.
Figure 3: Study AS-1: ASAS20 response over 24 weeks in AS patients *
Clinical Response
In study nr-axSpA-1, at Week 52, a greater proportion of nr-axSpA patients treated with CIMZIA had ASDAS-MI response compared to patients treated with placebo. At both Weeks 12 and 52, ASAS40 responses were greater for patients treated with CIMZIA compared to patients treated with placebo (Table 12). The components of the ASDAS-MI and ASAS response criteria are shown in Table 13.
Table 12: Clinical Responses in nr-axSpA patients at Weeks 12 and 52 in study nr-axSpA-1| Parameters | Placebo | CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2, and 4 All percents reflect the proportion of patients who were responders and remained in the study and on randomized treatment in the full analysis set. Patients who initiated open-label CIMZIA, or discontinued randomized treatment and remained in the study, or were missing Week 52 visit data were imputed as non-responders. 200 mg every 2 weeks
| CIMZIA 200 mg versus Placebo Odds ratio
(95% CI)
|
|---|
| N=158 | N=159 |
|---|
| ASDAS-MI | | | |
| Week 52 | 7% | 47% | 15.2
(7.3 , 31.6)
|
| ASAS-40 | | | |
| Week 12 | 11% | 48% | 7.4
(4.1, 13.4)
|
| Week 52 | 16% | 57% | 7.4
(4.3, 12.6)
|
Table 13: Components of the ASDAS-MI and ASAS response criteria and other measures of disease activity in nr-axSpA patients at baseline, and at Week 12 in study nr-axSpA-1 | Placebo | CIMZIA
CIMZIA administered every 2 weeks preceded by a loading dose of 400 mg at Weeks 0, 2, and 4 200 mg every 2 weeks
|
|---|
| N=158 | N=159 |
|---|
| Baseline
(SD)
| Week 12
(SD)
| Baseline
(SD)
| Week 12
(SD)
|
|---|
| Mean and standard deviation in parenthesis were presented based on full analysis set. |
| Total Spinal Pain (0-10) | 6.9 (1.8) | 6.0 (2.3) | 7.0 (1.9) | 3.9 (2.6) |
| Patient Global Assessment of Disease Activity (0-10) | 6.7 (2.0) | 5.9 (2.4) | 6.8 (1.9) | 3.8 (2.6) |
| C-Reactive Protein (mg/L) | 15.8 (17.7) | 13.2 (17.2) | 15.8 (17.8) | 6.7 (15.1) |
| BASDAI (0-10)
(BASDAI is Bath Ankylosing Spondylitis Disease Activity Index | 6.8 (1.3) | 5.7 (2.1) | 6.9 (1.4) | 3.9 (2.2) |
| - Back Pain | 7.4 (1.3) | 6.2 (2.1) | 7.4 (1.4) | 4.1 (2.5) |
| - Peripheral pain and swelling (0-10) | 6.2 (2.2) | 5.3 (2.5) | 6.3 (2.3) | 3.7 (2.4) |
| - Inflammation
The average of BASDAI question 5 and 6 concerning morning stiffness intensity and duration. | 6.7 (1.8) | 5.5 (2.4) | 6.9 (1.8) | 3.6 (2.4) |
| BASFI (0-10)
BASFI is Bath Ankylosing Spondylitis Functional Index | 5.4 (2.2) | 4.9 (2.4) | 5.4 (2.1) | 3.2 (2.3) |
| BASMI
BASMI is Bath Ankylosing Spondylitis Metrology Index | 2.8 (1.4) | 2.7 (1.4) | 3.0 (1.3) | 2.6 (1.4) |
The percentage of nr-axSpA patients achieving ASDAS-MI response by visit for study nr-axSpA-1 is shown in Figure 4.
Figure 4: Study nr-axSpA-1: ASDAS-MI response over 12 weeks
The same patients may not have responded at each time point. |
|
In study AS-1, at Week 12, patients with nr-axSpA treated with CIMZIA 200 mg every 2 weeks and CIMZIA 400 mg every 4 weeks had an ASAS 20 response of 42% and 47%, respectively, compared to 20% of patients treated with placebo. The ASAS 40 response in patients treated with CIMZIA 200 mg every 2 weeks and 400 mg every 4 weeks was 30% and 37%, respectively, compared to 11% of patients treated with placebo at Week 12
(see
Section 14.4).
Other Health Related Outcomes
In study nr-axSpA-1, at Week 12, patients treated with CIMZIA achieved significantly greater improvement from baseline in the Ankylosing Spondylitis Quality of Life Questionnaire (ASQoL) score compared to patients treated with placebo.
Clinical Response
Table 15 presents the efficacy results of PS-1, PS-2, and PS-3 at Week 16.
Table 15: Efficacy Results at Week 16 in Adults with Plaque Psoriasis in PS-1, PS-2, and PS-3 [MI
Missing data was imputed using multiple imputation based on the MCMC method.
]
| Study PS-1 | Study PS-2 | Study PS-3
The primary endpoint in PS-3 was PASI 75 at Week 12. |
|---|
| Placebo
(N=51)
| CIMZIA 200mg
Subjects received 400 mg of CIMZIA at Weeks 0, 2, and 4, followed by 200 mg every other week.
Q2W
(N=95)
| CIMZIA 400mg
Q2W
(N=88)
| Placebo
(N=49)
| CIMZIA 200mg
Q2W
(N=91)
| CIMZIA 400mg
Q2W
(N=87)
| Placebo
(N=57)
| CIMZIA 200mg
Q2W
(N=165)
| CIMZIA 400mg
Q2W
(N=167)
|
|---|
| PGA of 0 or 1
The co-primary efficacy endpoints at Week 16 in PS-1 and PS-2. ,PGA score of 0 (clear) or 1 (almost clear). | 4% | 45% | 55% | 3% | 61% | 65% | 4% | 52% | 62% |
| PASI 75
| 7% | 65% | 75% | 13% | 81% | 82% | 4% | 69% | 75% |
| PASI 90 | 0% | 36% | 44% | 5% | 50% | 52% | 0% | 40% | 49% |
Examination of age, sex, prior use of biologics, and prior use of systemic therapies did not identify difference in response to CIMZIA among these subgroups.
Based on a post-hoc subgroup analysis in subjects with moderate-to-severe psoriasis, stratified by ≤90 kg or >90 kg, subjects with both lower body weight and lower disease severity may achieve an acceptable response with CIMZIA 200 mg.
Maintenance of Response
In PS-1 and PS-2, among subjects who were PASI 75 responders at Week 16 and received CIMZIA 400 mg every other week, the PASI 75 response rates at Week 48 were 94% and 81%, respectively. In subjects who were PASI 75 responders at Week 16 and received CIMZIA 200 mg every other week, the PASI 75 response rates at Week 48 were 81% and 74%, respectively.
In PS-1 and PS-2, among subjects who were PGA clear or almost clear responders at Week 16 and received CIMZIA 400 mg every other week, the PGA response rates at Week 48 were 79% and 73%, respectively. In subjects who were PGA clear or almost clear responders at Week 16 and received CIMZIA 200 mg every other week, the PGA response rates at Week 48 were 79% and 76%, respectively.
In PS-3 study, subjects who achieved a PASI 75 response at Week 16 were re-randomized to either continue treatment with CIMZIA or be withdrawn from therapy (i.e., receive placebo). At Week 48, 98% of subjects who continued on CIMZIA 400 mg every other week were PASI 75 responders as compared to 36% of subjects who were re-randomized to placebo. Among PASI 75 responders at Week 16 who received CIMZIA 200 mg every other week and were re-randomized to either CIMZIA 200 mg every other week or placebo, there was also a higher percentage of PASI 75 responders at Week 48 in the CIMZIA group as compared to placebo (80% and 46%, respectively).
How Supplied
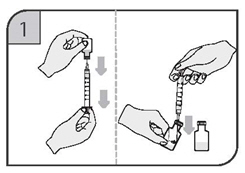
CIMZIA (certolizumab pegol) for injection is a sterile white, lyophilized powder for subcutaneous use after reconstitution in the following packaging configuration.
| Package size | NDC | Pack Contents |
|---|
| Carton of two 200 mg vials | NDC 50474-700-62 | Two 200 mg/vial glass vials with rubber stopper
Two 1 mL Sterile Water for Injection, USP glass vials
Two 3 mL plastic syringes
Four 20-gauge needles (1 inch)
Two 23-gauge needles (1 inch)
Eight alcohol swabs
|
CIMZIA (certolizumab pegol) injection is a sterile, clear to opalescent, colorless to yellow solution for subcutaneous use in the following packaging configurations.
| Package size | NDC | Pack Contents |
|---|
| Prefilled Syringe Starter Kit: each unit carton contains three cartons of two 200 mg/mL prefilled syringes per individual carton | NDC 50474-710-81 | Six 200 mg/mL prefilled syringes with a fixed 25 ½ gauge thin-wall needle
6 alcohol swabs
|
| Carton of two 200 mg/mL prefilled syringes | NDC 50474-710-79 | Two 200 mg/mL prefilled syringe with a fixed 25 ½ gauge thin-wall needle
Two alcohol swabs
|
| Carton of one 200 mg/mL prefilled syringe | NDC 50474-750-10 | One 200 mg/mL prefilled syringe with a fixed 25 ½ gauge thin-wall needle
One alcohol swab
|
The needle shield inside the removable cap of the CIMZIA prefilled syringe contains a derivative of natural rubber latex which may cause allergic reactions and should be handled with caution by latex-sensitive individuals
[see
Warnings and Precautions (5.4)].
When necessary, CIMZIA prefilled syringes may be stored at room temperature up to 77
°F (25
°C) in the original carton to protect from light for a single period of up to 7 days. Once stored at room temperature, do not place back in refrigerator. Write the date removed from the refrigerator in the space provided on the carton and discard if not used within the 7-day period.
Risk of Serious Infections
Inform patients that CIMZIA may lower the ability of the immune system to fight infections. Instruct patients of the importance of contacting their doctor if they develop any symptoms of infection, including tuberculosis and reactivation of hepatitis B virus infections.
Because caution should be exercised in prescribing CIMZIA to patients with clinically important active infections, advise patients of the importance of informing their health care providers about all aspects of their health
[see
Warnings and Precautions (5.1,
5.5)]
.
Malignancies
Counsel patients about the possible risk of lymphoma and other malignancies while receiving CIMZIA
[see
Warnings and Precautions (5.2)]
.
Other Medical Conditions
Advise patients to report any signs of new or worsening medical conditions such as heart disease, neurological disease, or autoimmune disorders
[see
Warnings and Precautions (5.3,
5.6,
5.9). Advise patients to report promptly any symptoms suggestive of a cytopenia such as bruising, bleeding, or persistent fever
[see
Warnings and Precautions (5.7)]
.
Hypersensitivity Reactions
Advise patients to seek immediate medical attention if they experience any symptoms of severe hypersensitivity reactions. Advise latex-sensitive patients that the needle shield inside the removable cap of the CIMZIA prefilled syringe contains a derivative of natural rubber latex
[see
Warnings and Precautions (5.4)]
.
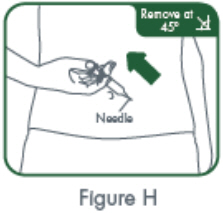
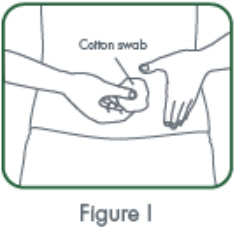
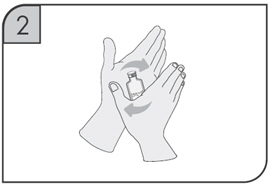
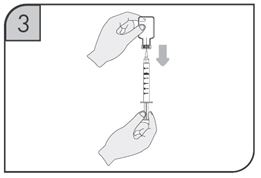
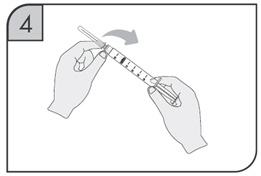
Preparation and Administration of CIMZIA Using the Prefilled Syringe
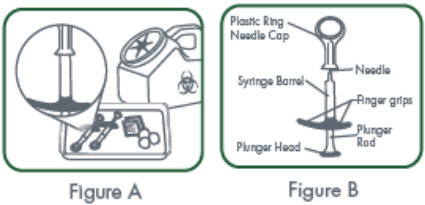
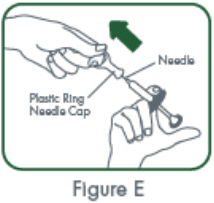
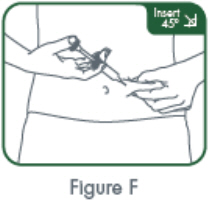
Instruct patients and caregivers on how to inject the Prefilled Syringe. Complete instructions are provided in the
Instructions for Usepackaged in each CIMZIA Prefilled Syringe kit.
- If refrigerated, remove the prefilled syringe from the carton and let it warm to room temperature.
- Inspect the liquid in the prefilled syringe. It should be clear to opalescent, and colorless to yellow and free from particulates. Discard the syringe if cloudy, discolored or contains particulates.
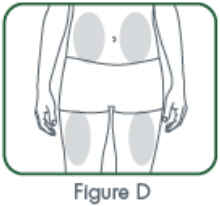
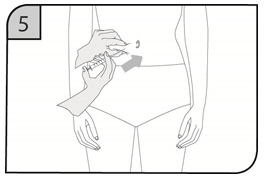
- Suitable sites for injection include the thigh or abdomen. Inject at least 1 inch from the previous site.
- Do not inject into areas where the skin is tender, bruised, red or hard, or where there are scars or stretch marks.
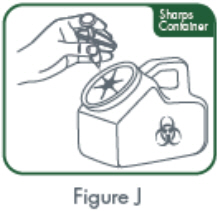
Instruct patients and caregivers in proper syringe and needle disposal technique.
- To avoid needle-stick injury, do not to place the needle cap back on the syringe or otherwise recap the needle.
- Properly dispose of needles and syringes in a puncture-proof container.
- Do not reuse the injection materials.
Manufactured by:
UCB, Inc.
1950 Lake Park Drive
Smyrna, GA 30080
US License No. 1736