Progesterone Insert
FDA Label NDC 50742-359

24 label sections · Submitted to the FDA by Ingenus Pharmaceuticals, Llc · Indications, Dosage, Usage, and Precautions

Structured Product Label

The following Structured Product Label (SPL) was submitted to the FDA by Ingenus Pharmaceuticals, Llc for the product Progesterone (NDC 50742-359). This document serves as the official prescribing information, containing essential scientific data and clinical materials required for healthcare providers and patients.

This specific version of the label includes detailed information regarding 1 indications and usage, other, 3 dosage forms and strengths, 4 contraindications, 5.1 cardiovascular or cerebrovascular disorders, 5.2 depression, 6.1 clinical studies experience, 7 drug interactions, and other regulatory disclosures. Use the navigation below to review specific sections of the FDA submission.

1 Indications And Usage

Progesterone vaginal insert is indicated, as part of an Assisted Reproductive Technology (ART) treatment program, to support embryo implantation in infertile women less than 35 years of age by supplementation of corpus luteal function and to maintain pregnancy after implantation up to 10 weeks.

Other

The recommendeddose of progesterone vaginal insert dose is 100 mg administered vaginally two or three times daily starting the day after oocyte retrieval and continuing for up to 10 weeks total duration.

Absorption

Progesterone serum concentrations increased following the administration of the progesterone vaginal insert in 12 healthy premenopausal females. After 5 days of dosing, steady-state progesterone concentrations were attained within approximately 1 day after initiation of progesterone vaginal insert treatment. Both progesterone vaginal insert dosing regimens provided average serum progesterone concentrations that exceeded 10 ng/mL on Day 5. The pharmacokinetic results are summarized in Table 2.

Table 2: Mean (±Standard Deviation) Serum Progesterone Pharmacokinetic Parameters after Progesterone Vaginal Insert Vaginal Administration
Pharmacokinetic Parameter (unit)Progesterone vaginal insert 100 mg
twice daily (N=6)
Progesterone vaginal insert 100 mg
three times daily (N=6)
Cmax Maximum progesterone serum concentration.
Tmax Time to maximum progesterone serum concentration.
Cavg Average progesterone serum concentration.
AUC0-24 Area under the drug concentration versus time curve from 0-24 hours post dose.
Cmin Minimum progesterone serum concentration.
One Day of Dosing
Cmax (ng/mL)17 ± 6.519.8 ± 7.2
Tmax (hr)24 ± 017.3 ± 7.4
AUC0-24
(ng∙hr/mL)
217 ± 113284 ± 143
Day 5 of Multiple Dosing
Cmax (ng/mL)18.5 ± 5.524.1 ± 5.6
Tmax (hr)18 ± 9.418 ± 9.4
Cmin (ng/mL)8.9 ± 4.510.9 ± 6.7
Cavg (ng/ml)14 ± 4.815.9 ± 4.3
AUC0-24
(ng∙hr/mL)
327 ± 127436 ± 106

Distribution

Progesterone is approximately 96% to 99% bound to serum proteins, primarily to serum albumin and corticosteroid binding globulin.

Elimination

Metabolism: Progesterone is metabolized primarily by the liver, largely to pregnanediols and pregnanolones. Pregnanediols and pregnanolones are conjugated in the liver to glucuronide and sulfate metabolites. Progesterone metabolites that are excreted in the bile may be deconjugated and may be further metabolized in the gut via reduction, dehydroxylation, and epimerization.

Excretion: Progesterone undergoes renal and biliary elimination. Following injection of labelled progesterone, 50-60% of the excretion of metabolites occurs via the kidney; approximately 10% occurs via the bile and feces. Overall recovery of the labelled material accounts for 70% of an administered dose. Only a small portion of unchanged progesterone is excreted in the bile.

A randomized, open-label, active-controlled study evaluated the efficacy of two different daily dosing regimens of progesterone vaginal insert (100 mg twice daily administered vaginally or 100 mg three times daily administered vaginally for 10 weeks) and a vaginally administered active comparator to support embryo implantation (as part of an Assisted Reproductive Technology (ART) treatment program) in infertile women less than 35 years of age by supplementation of corpus luteal function and to maintain pregnancy after implantation up to 10 weeks.
Efficacy of the two progesterone vaginal insert regimens was assessed by an endpoint of pregnancies, defined as the presence of at least one fetal heartbeat seen on ultrasound at 6 weeks post-embryo transfer. The study included 808 infertile women who were treated with one of the two progesterone vaginal insert dosing regimens (75% White; 10% Hispanic, 5% Black, 5% Asian, and 5% other races) between 19 and 42 years of age (mean age 33 years old) who had a body mass index <34 kg/m2 at screening.

The ongoing pregnancy rates for infertile women treated with both dosing regimens of progesterone vaginal insert were non-inferior (lower bounds of the 95% confidence interval of the difference between the two progesterone vaginal insert dosing regimens and the active comparator excluded a difference greater than 10%) to the pregnancy rate for infertile women treated with the active comparator. The results of progesterone vaginal insert treatment groups (but not the active comparator group) in this study are shown in Table 3.

Table 3: Pregnancy Rates

Pregnancy was defined as the presence of at least one fetal heartbeat seen on ultrasound at 6 weeks post-embryo transfer.

in Infertile Women Who Received Progesterone Vaginal Insert to Support Embryo Implantation by Supplementation of Corpus Luteal Function as Part of an ART Program
Progesterone Vaginal Insert
100 mg twice daily for 10 weeks
Progesterone Vaginal Insert
100 mg three times daily for 10 weeks
Number of subjects404404
Pregnancy: n (%)156 (39%)171 (42%)
95% Confidence Interval of pregnancy rate[33.8, 43.6][37.5, 47.3]
Pregnancy rate percentage difference between each progesterone vaginal insert treatment group and the active comparator-3.6%0.1%
95% Confidence Interval for difference vs active comparator[-10.3, 3.2][-6.7, 6.9]

Subjects participating in the study were stratified at randomization by age and ovarian reserve (as measured by serum FSH levels). The  pregnancy rates for these subgroups in the progesterone vaginal insert treatment groups (but not the active comparator group) are shown in Table 4. In subjects:

  • Under the age of 35 or with serum FSH levels less than 10 IU/L, results from both progesterone vaginal insert dosing regimens were non-inferior to the results from the active comparator with respect to pregnancy rates.
  • Age 35 and older and in subjects with serum FSH levels between 10 and 15 IU/L, the results with respect to ongoing pregnancy rates for both progesterone vaginal insert dosing regimens did not reach the criteria for non-inferiority.
  • Subjects who became pregnant received study medication for a total of 10 weeks. Patients over 34 kg/m2 were not studied; thus, the efficacy of progesterone vaginal insert in these patients is unknown..

    Table 4: Pregnancy Rates in Age- and Ovarian Reserve-Defined Subgroups Who Received Progesterone Vaginal Insert for Luteal Supplementation and Early Pregnancy While in an ART Program
    Progesterone Vaginal Insert
    100 mg twice daily
    Progesterone Vaginal Insert
    100 mg three times daily
    Subjects age < 35 years (N)247247
    Pregnancy: n (%)111 (45%)117 (47%)
    Pregnancy rate percentage difference between progesterone vaginal insert and the active comparator0.5%2.9%
    95% Confidence Interval for difference vs. active comparator[-8.3, 9.3][-5.9, 11.7]
    Subjects 35-42 years of age (N)157157
    Pregnancy: n (%)45 (28%)54 (34%)
    Pregnancy rate percentage difference between progesterone vaginal insert and the active comparator-10.1%-4.4%
    95% Confidence Interval for difference vs. active comparator[-20.3, 0.3][-14.9, 6.3]
    Subjects with FSH < 10 IU/L (N)350347
    Ongoing pregnancy: n (%)140 (40%)150 (43%)
    Pregnancy rate percentage difference between progesterone vaginal insert and ​the active comparator-2.0%1.2%
    95% Confidence Interval for difference vs. the active comparator[-9.3, 5.3][-6.1, 8.5]
    Subjects with FSH between 10 and 15 IU/L (N)4651
    Pregnancy: n (%)16 (35%)20 (39%)
    Pregnancy rate percentage difference between progesterone vaginal insert and the active comparator-12.2%-7.7%
    95% Confidence Interval for difference vs. active comparator[-31.0, 7.7][-26.6, 11.6]

3 Dosage Forms And Strengths

White to off-white oblong-shaped progesterone vaginal 100 mg insert, debossed with "G1" on one side and plain on the other side.

4 Contraindications

Progesterone vaginal insert is contraindicated in women with any of the following conditions:

  • Previous hypersensitivity reactions to progesterone or any of the ingredients of progesterone vaginal insert [see Description (11)]
  • Abnormal vaginal bleeding that has an undiagnosed etiology
  • Known missed abortion or ectopic pregnancy
  • Hepatic adenoma, hepatocellular carcinoma, acute hepatitis, or severe (decompensated) cirrhosis
  • Current diagnosis of, or history of, a hormone-sensitive malignancy (e.g., breast cancer)
  • Active arterial or venous thromboembolism or severe thrombophlebitis, or a history of these events

5.1 Cardiovascular Or Cerebrovascular Disorders

Life-threatening arterial or venous thromboembolic disorders may occur during hormone treatment, including treatment with progesterone vaginal insert.

The healthcare provider should be alert to earliest signs of myocardial infarction, cerebrovascular disorders, arterial or venous thromboembolism (venous thromboembolism or pulmonary embolism), thrombophlebitis, or retinal thrombosis. Progesterone vaginal insert should be discontinued if any of these are suspected.

5.2 Depression

Progesterone vaginal insert-treated women with a history of depression should be closely observed. Consider progesterone vaginal insert discontinuation if symptoms worsen.

6.1 Clinical Studies Experience

Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.

The safety data reflect exposure to progesterone vaginal insert in 808 infertile women in a single Assisted Reproductive Technology 10 week clinical study conducted in the U.S. [see Clinical Studies (14)]. Progesterone vaginal insert was studied at vaginally administered doses of 100 mg twice daily and 100 mg three times daily for 10 weeks and compared to a vaginally administered active comparator. The adverse reactions that occurred at a rate greater than or equal to 2% in either progesterone vaginal insert group are summarized in Table 1.

Other less common reported adverse reactions in progesterone vaginal insert-treated women included vaginal irritation, itching, burning, discomfort, urticaria, and peripheral edema.

Table 1: Number and Frequency of Reported Adverse Reactions in Infertile Women Treated with Progesterone Vaginal Insert in an Assisted Reproductive Technology Study

Progesterone Vaginal Insert

100 mg twice

daily

(N=404)

Progesterone Vaginal Insert

100 mg three

times daily

(N=404)

Post-oocyte retrieval pain

115 (28%)

102 (25%)

Abdominal pain

50 (12%)

50 (12%)

Nausea

32 (8%)

29 (7%)

Ovarian hyperstimulation syndrome

30 (7%)

27 (7%)

Abdominal distension

18 (4%)

17 (4%)

Headache

15 (4%)

13 (3%)

Uterine spasm

15 (4%)

11 (3%)

Vaginal bleeding

13 (3%)

14 (3%)

Vomiting

13 (3%)

9 (2%)

Urinary tract infection

9 (2%)

4 (1%)

Constipation

9 (2%)

14 (3%)

Fatigue

7 (2%)

12 (3%)

Adverse Reactions from Other Progesterone Products
Adverse reactions from other progesterone products included breast tenderness, bloating, mood swings, irritability, and drowsiness.

7 Drug Interactions

Drugs known to induce the hepatic cytochrome-P450-3A4 system may increase the elimination of progesterone, lower progesterone exposure in progesterone vaginal insert-treated women, and reduce the efficacy of progesterone vaginal insert.

The effect of concomitant vaginal products on the exposure of progesterone from progesterone vaginal insert has not been assessed. Progesterone vaginal insert is not recommended for use with other vaginal products (such as antifungal products) as this may alter progesterone release and absorption from the progesterone vaginal insert.

8.1 Pregnancy

Risk Summary
Progesterone vaginal insert is indicated, as part of an Assisted Reproductive Technology (ART) treatment program, to support embryo implantation in infertile women less than 35 years of age by supplementation of corpus luteal function and to maintain pregnancy after implantation up to 10 weeks.
Maternal risks of progesterone vaginal insert use during pregnancy are discussed throughout the labeling.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Human Data: In one clinical study [see Clinical Studies (14)], progesterone vaginal insert was vaginally administered to support embryo implantation during the first trimester of pregnancy and to maintain clinical pregnancy through week 10 of pregnancy when the placenta takes over production of progesterone. The live birth outcomes of these pregnancies were as follows:

  • Among the 404 women treated with progesterone vaginal insert twice daily, 143 (35%) women had live births consisting of 85 (59%) singletons, 56 (39%) twins, and 2 (1%) triplets. In this treatment group, 13 (3%) women had a spontaneous abortion, 1 (0.2%) woman had an ectopic pregnancy, and neonatal birth defects were reported in 7 infants (3% based on 203 live births).
  • Among the 404 women treated with progesterone vaginal insert three times daily, 155 (38%) women had live births consisting of 91 (59%) singletons, 60 (39%) twins, and 4 (3%) triplets. In this treatment group, 22 (5%) women had a spontaneous abortion, 4 (1%) women had an ectopic pregnancy, and neonatal birth defects were reported in 7 infants (3% based on 223 live births).
  • Birth defects reported in the progesterone vaginal insert:

    • Twice daily group included one neonate with a cleft palate and intrauterine growth retardation, one with spina bifida, three with congenital heart defects, one with an umbilical hernia, and one with an intestinal anomaly.
    • Three times daily group included one neonate with an esophageal fistula, one with hypospadias and an underdeveloped right ear, one with Down Syndrome and an atrial septal defect, one with congenital heart anomalies, one with DiGeorge’s syndrome, one fetus with a hand deformity, and one with cleft palate.
    • For additional information on the pharmacology of progesterone vaginal insert and pregnancy outcome information [ see Clinical Pharmacology (12) and Clinical Studies (14)].

8.2 Lactation

Risk Summary

Detectable amounts of progesterone have been identified in the milk of nursing mothers. The effect of this on the nursing infant has not been determined. A published study reported no adverse effects of progesterone on milk production or infant growth during the first postpartum year.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for progesterone vaginal insert and any potential adverse effects on the breastfed child from progesterone vaginal insert or from the underlying maternal condition.

8.4 Pediatric Use

The safety and effectiveness of progesterone vaginal insert in pediatric patients have not been established.

8.5 Geriatric Use

Clinical studies of progesterone vaginal insert did not include women 65 years of age and older. Progesterone vaginal insert is not indicated for use in this population.

8.6 Body Mass Index

The safety and efficacy of progesterone vaginal insert in women with a body mass index (BMI) >34 kg/m2 has not been studied.

8.7 Hepatic Impairment

Progesterone vaginal insert is contraindicated in women with hepatic adenoma, hepatocellular carcinoma, acute hepatitis, or severe (decompensated) cirrhosis.

10 Overdosage

Treatment of overdosage consists of discontinuation of progesterone vaginal insert together with institution of appropriate symptomatic and supportive care. If an overdose of progesterone vaginal insert occurs, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.

11 Description

Progesterone vaginal insert contains micronized progesterone. Progesterone vaginal insert is supplied with polyethylene vaginal applicators.

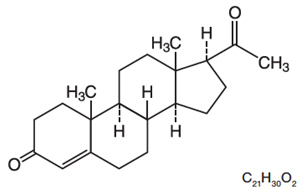
The active ingredient, progesterone, is present (100 mg) along with inactive ingredients. The chemical name for progesterone is pregn-4-ene-3,20-dione, its empirical formula is C21H30O2 , its molecular weight is 314.5. Progesterone exists in two polymorphic forms. The form used in progesterone vaginal insert, the alpha-form, has a melting point of 127-131°C.

The structural formula is:

Chemical Structure (Image 01)

Chemical Structure (Image 01)

Each progesterone vaginal insert delivers 100 mg of progesterone in a base containing lactose monohydrate, povidone, adipic acid, sodium bicarbonate, sodium lauryl sulfate, magnesium stearate, directly compressible starch, and colloidal silicon dioxide.

12.1 Mechanism Of Action

Progesterone is a naturally occurring steroid that is secreted by the ovary, placenta, and adrenal gland. In the presence of adequate estrogen, progesterone transforms a proliferative endometrium into a secretory endometrium. Progesterone is necessary to increase endometrial receptivity for implantation of an embryo. Once an embryo is implanted, progesterone acts to maintain a pregnancy.

12.2 Pharmacodynamics

The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of progesterone vaginal insert have not been fully characterized.

13.1 Carcinogenesis, Mutagenesis, Impairment Of Fertility

Nonclinical toxicity studies to determine the potential of progesterone vaginal insert to cause carcinogenicity or mutagenicity have not been performed. The effect of progesterone vaginal insert on fertility has not been evaluated in animals.

16 How Supplied/Storage And Handling

Each progesterone vaginal insert is a white to off-white oblong-shaped insert debossed with "G1" on one side and plain on the other side. Each vaginal insert, 100 mg, is packed individually in a sealed foil pouch. These pouches are available in cartons packed:

  • 21 vaginal inserts with 21 disposable vaginal applicators (NDC 50742-359-21)

17 Patient Counseling Information

Advise the patient to read the FDA-Approved patient labeling (Patient Information).

Vaginal Bleeding
Inform patients of the importance of reporting irregular vaginal bleeding to their health care provider as soon as possible.

Common Adverse Reactions with Progesterone
Inform patients of the possible adverse reactions of progesterone vaginal insert therapy such as headaches, breast tenderness, bloating, mood swings, irritability, and drowsiness.

Coadministration of Other Vaginal Products
Inform patients that progesterone vaginal insert is not recommended for use with other vaginal products.

Manufactured for:
Ingenus Pharmaceuticals, LLC
Orlando, FL 32811-7193
Made in China

Logo (Image 15)

Logo (Image 15)

I0209
Rev.B
Revised: 09/2026

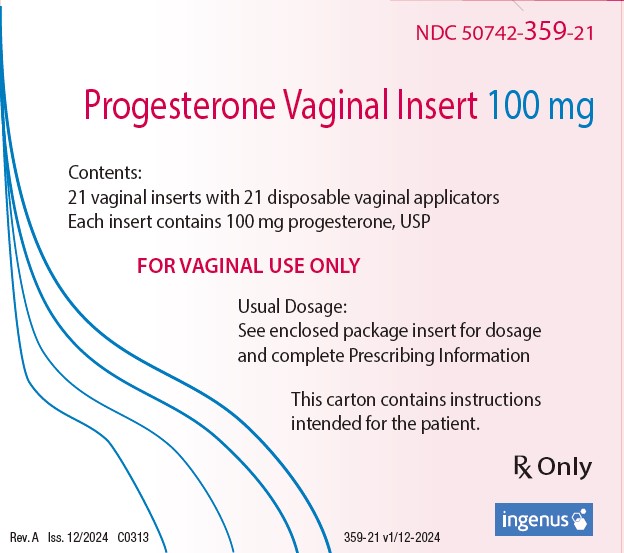
Principal Display Panel - 100 Mg Carton

NDC 50742-359-21
Progesterone Vaginal Insert 100mg

Contents:
21 vaginal inserts with 21 disposable vaginal applicators
Each insert contains 100 mg progesterone, USP

FOR VAGINAL USE ONLY

Usual Dosage:
See enclosed package insert for dosage and
complete Prescribing Information.

This carton contains instructions intended
for the patient.

Rx only

Ingenus Pharmaceuticals, LLC

Principal Display Panel (100 mg Carton)

Principal Display Panel (100 mg Carton)

* Please review the disclaimer below.