The dosage of TRIKAFTA should be reduced when used concomitantly with moderate CYP3A inhibitors [see Dosage and Administration (2.4) and Warnings and Precautions (5.6)]. Simulations indicated that concomitant use with moderate CYP3A inhibitors may increase elexacaftor and tezacaftor AUC by approximately 1.9- to 2.3-fold and 2.1-fold, respectively. Concomitant use of fluconazole increased ivacaftor AUC by 2.9-fold [see Clinical Pharmacology (12.3)].
- fluconazole
- erythromycin
Grapefruit
Concomitant use of TRIKAFTA with grapefruit juice, which contains one or more components that moderately inhibit CYP3A, may increase exposure of elexacaftor, tezacaftor and ivacaftor; therefore, food or drink containing grapefruit should be avoided during treatment with TRIKAFTA [see Dosage and Administration (2.4)].
CYP2C9 Substrates
Ivacaftor may inhibit CYP2C9; therefore, monitoring of the international normalized ratio (INR) during concomitant use of TRIKAFTA with warfarin is recommended. Other medicinal products for which exposure may be increased by TRIKAFTA include glimepiride and glipizide; these medicinal products should be used with caution [see Clinical Pharmacology (12.3)].
Transporters
Concomitant use of ivacaftor or tezacaftor/ivacaftor with digoxin, a sensitive P-gp substrate, increased digoxin AUC by 1.3-fold, consistent with weak inhibition of P-gp by ivacaftor. Administration of TRIKAFTA may increase systemic exposure of medicinal products that are sensitive substrates of P-gp, which may increase or prolong their therapeutic effect and adverse reactions. When used concomitantly with digoxin or other substrates of P-gp with a narrow therapeutic index such as cyclosporine, everolimus, sirolimus and tacrolimus, caution and appropriate monitoring should be used [see Clinical Pharmacology (12.3)].
Elexacaftor and M23-ELX inhibit uptake by OATP1B1 and OATP1B3 in vitro. Concomitant use of TRIKAFTA may increase exposures of medicinal products that are substrates of these transporters, such as statins, glyburide, nateglinide and repaglinide. When used concomitantly with substrates of OATP1B1 or OATP1B3, caution and appropriate monitoring should be used [see Clinical Pharmacology (12.3)]. Bilirubin is an OATP1B1 and OATP1B3 substrate.
Ciprofloxacin
Ciprofloxacin had no clinically relevant effect on the exposure of tezacaftor or ivacaftor and is not expected to affect the exposure of elexacaftor. Therefore, no dose adjustment is necessary during concomitant administration of TRIKAFTA with ciprofloxacin [see Clinical Pharmacology (12.3)].
Hormonal Contraceptives
TRIKAFTA has been studied with ethinyl estradiol/levonorgestrel and was found to have no clinically relevant effect on the exposures of the oral contraceptive. TRIKAFTA is not expected to have an impact on the efficacy of oral contraceptives.
Hormonal contraceptives may play a role in the occurrence of rash and cannot be excluded [see Adverse Reactions (6.1)]. For patients with CF taking hormonal contraceptives who develop rash, consider interrupting TRIKAFTA and hormonal contraceptives. Following the resolution of rash, consider resuming TRIKAFTA without the hormonal contraceptives. If rash does not recur, resumption of hormonal contraceptives can be considered.
Risk Summary
There are limited and incomplete human data from clinical trials on the use of TRIKAFTA or its individual components, elexacaftor, tezacaftor and ivacaftor, in pregnant women to inform a drug-associated risk. Although there are no animal reproduction studies with the concomitant administration of elexacaftor, tezacaftor and ivacaftor, separate reproductive and developmental studies were conducted with each active component of TRIKAFTA in pregnant rats and rabbits.
In animal embryo fetal development (EFD) studies oral administration of elexacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 2 times the exposure at the maximum recommended human dose (MRHD) in rats and 4 times the MRHD in rabbits [based on summed AUCs of elexacaftor and its metabolite (for rat) and AUC of elexacaftor (for rabbit)]. Oral administration of tezacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 3 times the exposure at the MRHD in rats and 0.2 times the MRHD in rabbits (based on summed AUCs of tezacaftor and M1-TEZ). Oral administration of ivacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 5 and 14 times the exposure at the MRHD, respectively [based on summed AUCs of ivacaftor and its metabolites (for rat) and AUC of ivacaftor (for rabbit)]. No adverse developmental effects were observed after oral administration of elexacaftor, tezacaftor or ivacaftor to pregnant rats from the period of organogenesis through lactation at doses that produced maternal exposures approximately 1 time, approximately 1 time and 3 times the exposures at the MRHD, respectively [based on summed AUCs of parent and metabolite(s)] (see Data).
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
Elexacaftor
In an EFD study, pregnant rats were administered oral doses of elexacaftor at 15, 25, and 40 mg/kg/day during the period of organogenesis from gestation Days 6-17. Elexacaftor did not cause adverse developmental outcomes at exposures up to 9 times the MRHD (based on summed AUCs for elexacaftor and its metabolite at maternal doses up to 40 mg/kg/day). Lower mean fetal body weights were observed at doses ≥25 mg/kg/day that produced maternal exposures ≥4 times the MRHD. Maternal toxicity was observed at 40 mg/kg/day (9 times the MRHD). In an EFD study, pregnant rabbits were administered oral doses of elexacaftor at 50, 100, or 125 mg/kg/day during the period of organogenesis from gestation Days 7-20. Elexacaftor was not teratogenic at exposures up to 4 times the MRHD (based on AUC of elexacaftor at maternal doses up to 125 mg/kg/day). Maternal toxicity was observed at 125 mg/kg/day (4 times the MRHD). In a pre- and postnatal development (PPND), pregnant rats were administered elexacaftor at oral doses of 5, 7.5, and 10 mg/kg/day from gestation Day 6 through lactation Day 18. Elexacaftor did not cause adverse developmental outcomes in pups at maternal doses up to 10 mg/kg/day (approximately 1 time the MRHD based on summed AUCs of elexacaftor and its metabolite). Placental transfer of elexacaftor was observed in pregnant rats.
Tezacaftor
In an EFD study, pregnant rats were administered tezacaftor at oral doses of 25, 50, or 100 mg/kg/day during the period of organogenesis from gestation Days 6-17. Tezacaftor did not cause adverse developmental effects at exposures up to 3 times the MRHD (based on summed AUCs of tezacaftor and M1-TEZ). Maternal toxicity in rats was observed at greater than or equal to 50 mg/kg/day (approximately greater than or equal to 1 time the MRHD). In an EFD study, pregnant rabbits were administered tezacaftor at oral doses of 10, 25, or 50 mg/kg/day during the period of organogenesis from gestation Days 7-20. Tezacaftor did not affect fetal developmental outcomes at exposures up to 0.2 times the MRHD (based on summed AUCs of tezacaftor and M1-TEZ). Lower fetal body weights were observed in rabbits at a maternally toxic dose that produced exposures approximately 1 time the MRHD (based on summed AUCs of tezacaftor and M1-TEZ at a maternal dose of 50 mg/kg/day). In a PPND study, pregnant rats were administered tezacaftor at oral doses of 25, 50, or 100 mg/kg/day from gestation Day 6 through lactation Day 18. Tezacaftor had no adverse developmental effects on pups at an exposure of approximately 1 time the MRHD (based on summed AUCs for tezacaftor and M1-TEZ at a maternal dose of 25 mg/kg/day). Decreased fetal body weights and early developmental delays in pinna detachment, eye opening, and righting reflex occurred at a maternally toxic dose (based on maternal weight loss) that produced exposures approximately 2 times the exposure at the MRHD (based on summed AUCs for tezacaftor and M1-TEZ). Placental transfer of tezacaftor was observed in pregnant rats.
Ivacaftor
In an EFD study, pregnant rats were administered ivacaftor at oral doses of 50, 100, or 200 mg/kg/day during the period of organogenesis from gestation Days 7-17. Ivacaftor did not affect fetal survival at exposures up to 5 times the MRHD (based on summed AUCs of ivacaftor and its metabolites at maternal oral doses up to 200 mg/kg/day). Maternal toxicity was observed at 100 and 200 mg/kg/day (3 and 5 times the exposure at the MRHD) and was associated with a decrease in fetal body weights at a maternal dose of 200 mg/kg/day (5 times the MRHD). In an EFD study, pregnant rabbits were administered ivacaftor at oral doses of 25, 50, or 100 mg/kg/day during the period of organogenesis from gestation Days 7-19. Ivacaftor did not affect fetal development or survival at exposures up to 14 times the MRHD (on an ivacaftor AUC basis at maternal oral doses up to 100 mg/kg/day). Maternal toxicity (i.e., death, decreased food consumption, decreased mean body weight and body weight gain, decreased clinical condition, abortions) was observed at doses greater than or equal to 50 mg/kg/day (approximately 5 times the MRHD). In a PPND study, pregnant rats were administered ivacaftor at oral doses of 50, 100, or 200 mg/kg/day from gestation Day 7 through lactation Day 20. Ivacaftor had no effects on delivery or growth and development of offspring at exposures up to 3 times the MRHD (based on summed AUCs for ivacaftor and its metabolites at maternal oral doses up to 100 mg/kg/day). Decreased fetal body weights were observed at a maternally toxic dose that produced exposures 5 times the MRHD (based on summed AUCs of ivacaftor and its metabolites). Placental transfer of ivacaftor was observed in pregnant rats and rabbits.
Risk Summary
There is no information regarding the presence of elexacaftor, tezacaftor, or ivacaftor in human milk, the effects on the breastfed infant, or the effects on milk production. Elexacaftor, tezacaftor, and ivacaftor are excreted into the milk of lactating rats (see Data). The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for TRIKAFTA and any potential adverse effects on the breastfed child from TRIKAFTA or from the underlying maternal condition.
Data
Elexacaftor: Lacteal excretion of elexacaftor in rats was demonstrated following a single oral dose (10 mg/kg) of 14C-elexacaftor administered 6 to 10 days postpartum to lactating dams. Exposure of 14C-elexacaftor in milk was approximately 0.4 times the value observed in plasma (based on AUC0-72h).
Tezacaftor: Lacteal excretion of tezacaftor in rats was demonstrated following a single oral dose (30 mg/kg) of 14C-tezacaftor administered 6 to 10 days postpartum to lactating dams. Exposure of 14C-tezacaftor in milk was approximately 3 times higher than in plasma (based on AUC0-72h).
Ivacaftor: Lacteal excretion of ivacaftor in rats was demonstrated following a single oral dose (100 mg/kg) of 14C-ivacaftor administered 9 to 10 days postpartum to lactating dams. Exposure of 14C-ivacaftor in milk was approximately 1.5 times higher than in plasma (based on AUC0-24h).
Juvenile Animal Toxicity Data
Findings of cataracts were observed in juvenile rats dosed from postnatal Day 7 through 35 with ivacaftor dose levels of 10 mg/kg/day and higher (0.21 times the MRHD based on systemic exposure of ivacaftor and its metabolites). This finding has not been observed in older animals [see Warnings and Precautions (5.7)].
Studies were conducted with tezacaftor in juvenile rats starting at postnatal day (PND) 21 and ranging up to PNDs 35 to 49. Findings of convulsions and death were observed in juvenile rats that received a tezacaftor dose level of 100 mg/kg/day (approximately equivalent to 1.9 times the MRHD based on summed AUCs of tezacaftor and its metabolite, M1-TEZ). A no-effect dose level was identified at 30 mg/kg/day (approximately equivalent to 0.8 times the MRHD based on summed AUCs of tezacaftor and its metabolite, M1-TEZ). Findings were dose related and generally more severe when dosing with tezacaftor was initiated earlier in the postnatal period (PND 7, which would be approximately equivalent to a human neonate). Tezacaftor and its metabolite, M1-TEZ, are substrates for P-glycoprotein. Lower brain levels of P-glycoprotein activity in younger rats resulted in higher brain levels of tezacaftor and M1-TEZ. These findings are not relevant for the indicated pediatric population, 2 years of age and older, for whom levels of P-glycoprotein activity are equivalent to levels observed in adults.
Elexacaftor
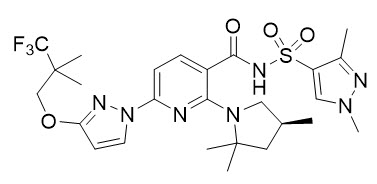
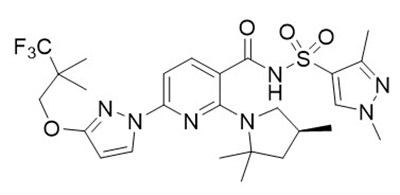
Elexacaftor is a white solid that is practically insoluble in water (<1 mg/mL). Its chemical name is N-(1,3-dimethyl-1H-pyrazole-4-sulfonyl)-6-[3-(3,3,3-trifluoro-2,2-dimethylpropoxy)-1H-pyrazol-1-yl]-2-[(4S)-2,2,4-trimethylpyrrolidin-1-yl]pyridine-3-carboxamide. Its molecular formula is C26H34N7O4SF3 and its molecular weight is 597.66. Elexacaftor has the following structural formula:
 Chemical Structure (Trikafta 01) |
Tezacaftor
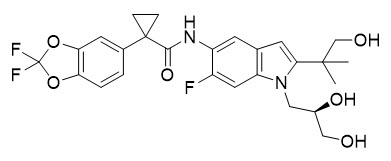
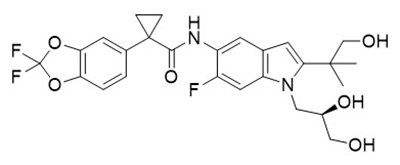
Tezacaftor is a white to off-white solid that is practically insoluble in water (<5 microgram/mL). Its chemical name is 1-(2,2-difluoro-2H-1,3-benzodioxol-5-yl)-N-{1-[(2R)-2,3-dihydroxypropyl]-6-fluoro-2-(1-hydroxy-2-methylpropan-2-yl)-1H-indol-5-yl}cyclopropane-1-carboxamide. Its molecular formula is C26H27N2F3O6 and its molecular weight is 520.50. Tezacaftor has the following structural formula:
 Chemical Structure (Trikafta 02) |
Ivacaftor
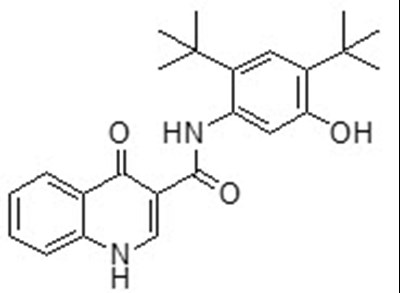
Ivacaftor is a white to off-white crystalline solid that is practically insoluble in water (<0.05 microgram/mL). Pharmacologically it is a CFTR potentiator. Its chemical name is N-(2,4-di-tert-butyl-5-hydroxyphenyl)-1,4-dihydro-4-oxoquinoline-3-carboxamide. Its molecular formula is C24H28N2O3 and its molecular weight is 392.49. Ivacaftor has the following structural formula:
 Chemical Structure (Trikafta 03) |
CFTR Chloride Transport Assay in Fischer Rat Thyroid Cells Expressing Mutant CFTR Protein
Effects of elexacaftor/tezacaftor/ivacaftor on chloride transport for mutant CFTR proteins was determined in Ussing chamber electrophysiology studies using a panel of Fischer Rat Thyroid (FRT) cell lines stably expressing individual mutant CFTR protein. Elexacaftor/tezacaftor/ivacaftor increased chloride transport in FRT cells expressing CFTR variants, as identified in Table 6.
The threshold that the treatment-induced increase in chloride transport must exceed for the mutant CFTR protein to be considered responsive is ≥10% of normal over baseline. This threshold was used because it is expected to predict clinical benefit. For individual variants, the magnitude of the net change over baseline in CFTR-mediated chloride transport in vitro is not correlated with the magnitude of clinical response.
CFTR Chloride Transport Assay in Human Bronchial Epithelial Cells Expressing Mutant CFTR Protein
Homozygous and heterozygous N1303K-Human Bronchial Epithelial (HBE) cells showed greater chloride transport in the presence of elexacaftor/tezacaftor/ivacaftor than F508del/F508del-HBE cells treated with tezacaftor/ivacaftor (which has shown clinical benefit in people homozygous for F508del).
Patient Selection
Select adult and pediatric patients 2 years of age and older for the treatment of CF with TRIKAFTA based on a clinical diagnosis of CF and the presence of at least one variant in the CFTR gene that is either responsive based on clinical and/or in vitro data or results in production of CFTR protein [see Indications and Usage (1)].
TRIKAFTA should only be used in patients with a clinical diagnosis of CF. The presence of eligible CFTR variant(s) should not be the sole determinant for using TRIKAFTA.
Table 6 lists CFTR variants responsive to TRIKAFTA based on clinical and/or in vitro data in FRT or HBE cells [see Clinical Studies (14)].
Table 6: List of CFTR Gene Variants Responsive to TRIKAFTA | The list of responsive CFTR variants is non-exhaustive. There may be protein-producing CFTR variants not listed that respond to treatment with TRIKAFTA. |
| Variants responsive to TRIKAFTA based on clinical data Clinical data obtained from Trials 1, 2, and 5. |
| 2789+5G→A | D1152H This variant is also predicted to be responsive by FRT assay. | L206W | R1066H | S945L |
| 3272-26A→G | F508del | L997F | R117C | T338I |
| 3849+10kbC→T | G85E | M1101K | R347H | V232D |
| A455E | L1077P | P5L | R347P | |
| Variants responsive to TRIKAFTA based on in vitro data The N1303K variant is predicted to be responsive by HBE assay. All other variants predicted to be responsive with in vitro data are supported by FRT assay. |
| 1140-1151dup | E264V | H620P | N396Y | S1251N |
| 1461insGAT | E282D | H620Q | N418S | S1255P |
| 1507_1515del9 | E292K | H939R | N900K | S13F |
| 2055del9 | E384K | H939R;H949L | P1013H | S13P |
| 2183A→G | E403D | H954P | P1013L | S158N |
| 2851A/G | E474K | I1023R | P1021L | S182R |
| 293A→G | E527G | I1027T | P1021T | S18I |
| 3007del6 | E56K | I105N | P111L | S18N |
| 3132T→G | E588V | I1139V | P1372T | S308P |
| 3141del9 | E60K | I1203V | P140S | S341P |
| 3143del9 | E822K | I1234L | P205S | S364P |
| 314del9 | E92K | I1234V del6aa | P439S | S434P |
| 3331del6 | F1016S | I125T | P499A | S492F |
| 3410T→C | F1052V | I1269N | P574H | S50P |
| 3523A→G | F1074L | I1366N | P67L | S519G |
| 3601A→C | F1078S | I1366T | P750L | S531P |
| 3761T→G | F1099L | I148L | P798S | S549I |
| 3791C/T | F1107L | I148N | P988R | S549N |
| 3850G→A | F191V | I148T | Q1012P | S549R |
| 3978G→C | F200I | I175V | Q1209P | S557F |
| 546insCTA | F311del | I331N | Q1291H | S589I |
| 548insTAC | F311L | I336K | Q1291R | S589N |
| A1006E | F312del | I336L | Q1313K | S624R |
| A1025D | F433L | I444S | Q1352H | S686Y |
| A1067P | F508C | I497S | Q151K | S737F |
| A1067T | F508C;S1251N | I502T | Q179K | S821G |
| A1067V | F508del;R1438W | I506L | Q237E | S898R |
| A107G | F575Y | I506V | Q237H | S912L |
| A1081V | F587I | I506V;D1168G | Q237P | S912L;G1244V |
| A1087P | F587L | I521S | Q30P | S912T |
| A120T | F693L(TTG) | I530N | Q359K/T360K | S955P |
| A1319E | F87L | I556V | Q359R | S977F |
| A1374D | F932S | I586V | Q372H | S977F;R1438W |
| A141D | G1047D | I601F | Q493L | T1036N |
| A1466S | G1047R | I618N | Q493R | T1053I |
| A155P | G1061R | I618T | Q552P | T1057R |
| A234D | G1069R | I807M | Q98P | T1086A |
| A234V | G1123R | I86M | Q98R | T1086I |
| A238V | G1173S | I980K | R1048G | T1246I |
| A309D | G1237V | K1060T | R1066G | T1299I |
| A349V | G1244E | K162E | R1070P | T1299K |
| A357T | G1244R | K464E | R1070Q | T351I |
| A455V | G1247R | K464N | R1070W | T351S |
| A457T | G1249E | K522E | R1162L | T351S;R851L |
| A462P | G1249R | K522Q | R1162Q | T388M |
| A46D | G1265V | K951E | R117C;G576A;R668C | T465I |
| A534E | G126D | L1011S | R117G | T501A |
| A554E | G1298V | L102R;F1016S | R117H | T582S |
| A566D | G1349D | L1065R | R117L | T908N |
| A62P | G149R;G576A;R668C | L1227S | R117L;L997F | T990I |
| A872E | G178E | L1324P | R117P | V1008D |
| c.1367_1369dupTTG | G178R | L1335P | R1239S | V1010D |
| C225R | G194R | L137P | R1283G | V1153E |
| C491R | G194V | L1388P | R1283M | V11I |
| C590Y | G213E | L1480P | R1283S | V1240G |
| C866Y | G213E;R668C | L159S | R1438W | V1293G |
| D110E | G213V | L15P | R170H | V1293I |
| D110H | G226R | L15P;L1253F | R248K | V1415F |
| D110N | G239R | L165S | R258G | V201M |
| D1152A | G253R | L167R | R297Q | V232A |
| D1270N | G27E | L210P | R31C | V317A |
| D1270Y | G27R | L293P | R31L | V322M |
| D1312G | G314E | L320V | R334L | V392G |
| D1377H | G314R | L327P | R334Q | V456A |
| D1445N | G424S | L32P | R347L | V456F |
| D192G | G437D | L333F | R352Q | V520I |
| D192N | G461R | L333H | R352W | V562I |
| D373N | G461V | L346P | R516S | V562I;A1006E |
| D426N | G463V | L441P | R553Q | V562L |
| D443Y | G480C | L453S | R555G | V591A |
| D443Y;G576A;R668C | G480D | L467F | R600S | V603F |
| D529G | G480S | L558F | R668C | V754M |
| D565G | G500D | L619S | R709Q | V920L |
| D567N | G545R | L633P | R74Q | V920M |
| D579G | G551A | L636P | R74Q;R297Q | V93D |
| D58H | G551D | L88S | R74Q;V201M;D1270N | W1098C |
| D58V | G551R | L927P | R74W | W1282G |
| D614G | G551S | L967F;L1096R | R74W;D1270N | W1282R |
| D651H | G576A | L967S | R74W;R1070W;D1270N | W202C |
| D651N | G576A;R668C | L973F | R74W;S945L | W361R |
| D806G | G576A;S1359Y | M1137R | R74W;V201M | W496R |
| D836Y | G622D | M1137V | R74W;V201M;D1270N | Y1014C |
| D924N | G622V | M1210K | R74W;V201M;L997F | Y1032C |
| D979A | G628A | M150K | R751L | Y1032N |
| D979V | G628R | M150R | R75L | Y1073C |
| D985H | G930E | M152L | R75Q | Y1092H |
| D985Y | G970D | M152V | R75Q;L1065P | Y109H |
| D993A | G970S | M265R | R75Q;N1088D | Y109N |
| D993G | G970V | M348K | R75Q;S549N | Y122C |
| D993Y | H1054D | M394L | R792G | Y1381H |
| E1104K | H1079P | M469V | R792Q | Y161C |
| E1104V | H1085P | M498I | R810G | Y161D |
| E1126K | H1085R | M952I | R851L | Y161S |
| E116K | H1375N | M952T | R933G | Y301C |
| E116Q | H1375P | M961L | S1045Y | Y563N |
| E1221V | H139L | N1088D | S108F | Y89C |
| E1228K | H139R | N1195T | S1118F | Y913S |
| E1409K | H146R | N1303I | S1159F | Y919C |
| E1433K | H199Q | N1303K | S1159P | |
| E193K | H199Y | N186K | S1188L | |
| E217G | H609L | N187K | S1235R | |
Sweat Chloride Evaluation
In Trial 1 (patients with an F508del variant on one allele and a variant on the second allele that results in either no CFTR protein or a CFTR protein that is not responsive ivacaftor and tezacaftor/ivacaftor), a reduction in sweat chloride was observed from baseline at Week 4 and sustained through the 24-week treatment period [see Clinical Studies (14.1)]. In Trial 2 (patients homozygous for the F508del variant), a reduction in sweat chloride was observed from baseline at Week 4 [see Clinical Studies (14.2)]. In Trial 3 (patients aged 6 to less than 12 years who are homozygous for the F508del variant or heterozygous for the F508del variant and a variant on the second allele that results in either no CFTR protein or a CFTR protein that is not responsive to ivacaftor and tezacaftor/ivacaftor), the mean absolute change in sweat chloride from baseline through Week 24 was -60.9 mmol/L (95% CI: -63.7, -58.2). In Trial 4 (patients aged 2 to less than 6 years who had at least one F508del variant or a variant known to be responsive to TRIKAFTA), the mean absolute change in sweat chloride from baseline through Week 24 was -57.9 mmol/L (95% CI: -61.3, -54.6). In Trial 5 (patients aged 6 years and older with at least one qualifying non-F508del elexacaftor/tezacaftor/ivacaftor-responsive CFTR variant), the mean absolute change in sweat chloride from baseline through Week 24 compared to placebo was -28.3 mmol/L (95% CI: -32.1, -24.5).
Cardiac Electrophysiology
At doses up to 2 times the maximum recommended dose of elexacaftor and 3 times the maximum recommended dose of tezacaftor and ivacaftor, the QT/QTc interval in healthy subjects was not prolonged to any clinically relevant extent.
Specific Populations
Pediatric Patients 2 to Less Than 12 Years of Age
Elexacaftor, tezacaftor and ivacaftor exposures observed in patients aged 2 to less than 12 years as determined using population PK analysis are presented by age group and dose administered in Table 8. Elexacaftor, tezacaftor and ivacaftor exposures in this patient population are within the range observed in patients aged 12 years and older.
Table 8: Mean (SD) Elexacaftor, Tezacaftor and Ivacaftor Exposures Observed at Steady State by Age Group and Dose Administered| Age Group | Dose | Elexacaftor AUC0-24h,ss
(µg∙h/mL) | Tezacaftor AUC0-24h,ss
(µg∙h/mL) | Ivacaftor AUC0-12h,ss
(µg∙h/mL) |
|---|
| SD: Standard Deviation; AUCss: area under the concentration versus time curve at steady state. |
Patients aged 2 to less than 6 years weighing less than 14 kg
(N = 16) | elexacaftor 80 mg qd/tezacaftor 40 mg qd/ivacaftor 60 mg qAM and ivacaftor 59.5 mg qPM | 128 (24.8) | 87.3 (17.3) | 11.9 (3.86) |
Patients aged 2 to less than 6 years weighing 14 kg or more
(N = 59) | elexacaftor 100 mg qd/tezacaftor 50 mg qd/ivacaftor 75 mg q12h | 138 (47.0) | 90.2 (27.9) | 13.0 (6.11) |
Patients aged 6 to less than 12 years weighing less than 30 kg
(N = 36) | elexacaftor 100 mg qd/tezacaftor 50 mg qd/ivacaftor 75 mg q12h | 116 (39.4) | 67.0 (22.3) | 9.78 (4.50) |
Patients aged 6 to less than 12 years weighing 30 kg or more
(N = 30) | elexacaftor 200 mg qd/ tezacaftor 100 mg qd/ ivacaftor 150 mg q12h | 195 (59.4) | 103 (23.7) | 17.5 (4.97) |
Pediatric Patients 12 to Less Than 18 Years of Age
The following conclusions about exposures between adults and the pediatric population are based on population pharmacokinetic (PK) analyses.
Following oral administration of TRIKAFTA to patients 12 to less than 18 years of age (elexacaftor 200 mg qd/tezacaftor 100 mg qd/ivacaftor 150 mg q12h), the mean (±SD) AUCss was 147 (36.8) mcg∙h/mL, 88.8 (21.8) mcg∙h/mL and 10.6 (3.35) mcg∙h/mL, respectively for elexacaftor, tezacaftor and ivacaftor, similar to the AUCss in adult patients.
Patients with Renal Impairment
Renal excretion of elexacaftor, tezacaftor and ivacaftor is minimal. Elexacaftor alone or in combination with tezacaftor and ivacaftor has not been studied in subjects with severe (eGFR <30 mL/min/1.73 m2) renal impairment or end-stage renal disease. Based on population PK analyses, the clearance of elexacaftor and tezacaftor was similar in subjects with mild (eGFR 60 to <90 mL/min/1.73 m2) or moderate (eGFR 30 to <60 mL/min/1.73 m2) renal impairment relative to patients with normal renal function [see Use in Specific Populations (8.6)].
Patients with Hepatic Impairment
Elexacaftor alone or in combination with tezacaftor and ivacaftor has not been studied in subjects with severe hepatic impairment (Child-Pugh Class C, score 10-15). In a clinical study, following multiple doses of elexacaftor, tezacaftor and ivacaftor for 10 days, subjects with moderately impaired hepatic function (Child-Pugh Class B, score 7-9) had 25% higher AUC and 12% higher Cmax for elexacaftor, 73% higher AUC and 70% higher Cmax for M23-ELX, 36% higher AUC and 24% higher Cmax for combined elexacaftor and M23-ELX, 20% higher AUC but similar Cmax for tezacaftor and 1.5-fold higher AUC and 10% higher Cmax for ivacaftor compared with healthy subjects matched for demographics [see Dosage and Administration (2.3), Warnings and Precautions (5.1), Adverse Reactions (6) and Use in Specific Populations (8.7)].
Tezacaftor and Ivacaftor
Following multiple doses of tezacaftor and ivacaftor for 10 days, subjects with moderately impaired hepatic function had an approximately 36% higher AUC and a 10% higher in Cmax for tezacaftor and a 1.5-fold higher AUC but similar Cmax for ivacaftor compared with healthy subjects matched for demographics.
Ivacaftor
In a study with ivacaftor alone, subjects with moderately impaired hepatic function had similar ivacaftor Cmax, but an approximately 2.0-fold higher ivacaftor AUC0-∞ compared with healthy subjects matched for demographics.
Male and Female Patients
Based on population PK analysis, the exposures of elexacaftor, tezacaftor and ivacaftor are similar in males and females.
Drug Interaction Studies
Drug interaction studies were performed with elexacaftor, tezacaftor and/or ivacaftor and other drugs likely to be co-administered or drugs commonly used as probes for pharmacokinetic interaction studies [see Drug Interactions (7)].
Potential for Elexacaftor, Tezacaftor and/or Ivacaftor to Affect Other Drugs
Based on in vitro results, elexacaftor and tezacaftor have a low potential to inhibit CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6 and CYP3A4, whereas ivacaftor has the potential to inhibit CYP2C8, CYP2C9 and CYP3A. However, clinical studies showed that the combination regimen of tezacaftor/ivacaftor is not an inhibitor of CYP3A and ivacaftor is not an inhibitor of CYP2C8 or CYP2D6.
Based on in vitro results, elexacaftor, tezacaftor and ivacaftor are not likely to induce CYP3A, CYP1A2 and CYP2B6.
Based on in vitro results, elexacaftor and tezacaftor have a low potential to inhibit the transporter P-gp, while ivacaftor has the potential to inhibit P-gp. Co-administration of tezacaftor/ivacaftor with digoxin, a sensitive P-gp substrate, increased digoxin exposure by 1.3-fold in a clinical study. Based on in vitro results, elexacaftor and M23-ELX may inhibit OATP1B1 and OATP1B3 uptake. Tezacaftor has a low potential to inhibit BCRP, OCT2, OAT1, or OAT3. Ivacaftor is not an inhibitor of the transporters OCT1, OCT2, OAT1, or OAT3.
The effects of elexacaftor, tezacaftor and/or ivacaftor on the exposure of co-administered drugs are shown in Table 9 [see Drug Interactions (7)].
Table 9: Impact of Elexacaftor, Tezacaftor and/or Ivacaftor on Other Drugs| Dose and Schedule | Effect on Other Drug PK | Geometric Mean Ratio (90% CI) of Other Drug
No Effect=1.0 |
|---|
| AUC | Cmax |
|---|
| ↑ = increase, ↓ = decrease, ↔ = no change. |
| AUC: area under the concentration versus time curve; CI: Confidence Interval; ELX: elexacaftor; Cmax: maximum observed concentration; TEZ: tezacaftor; IVA: ivacaftor; PK: Pharmacokinetics. |
Midazolam
2 mg single oral dose | TEZ 100 mg qd/IVA 150 mg q12h | ↔ Midazolam | 1.12
(1.01, 1.25) | 1.13
(1.01, 1.25) |
Digoxin
0.5 mg single dose | TEZ 100 mg qd/IVA 150 mg q12h | ↑ Digoxin | 1.30
(1.17, 1.45) | 1.32
(1.07, 1.64) |
Oral Contraceptive
Ethinyl estradiol 30 µg/Levonorgestrel 150 µg qd | ELX 200 mg qd/TEZ 100 mg qd/IVA 150 mg q12h | ↑ Ethinyl estradiol Effect is not clinically significant [see Drug Interactions (7.3)]. | 1.33
(1.20, 1.49) | 1.26
(1.14, 1.39) |
| ↑ Levonorgestrel | 1.23
(1.10, 1.37) | 1.10
(0.985, 1.23) |
Rosiglitazone
4 mg single oral dose | IVA 150 mg q12h | ↔ Rosiglitazone | 0.975
(0.897, 1.06) | 0.928
(0.858, 1.00) |
Desipramine
50 mg single dose | IVA 150 mg q12h | ↔ Desipramine | 1.04
(0.985, 1.10) | 1.00
(0.939, 1.07) |
Potential for Other Drugs to Affect Elexacaftor, Tezacaftor and/or Ivacaftor
In vitro studies showed that elexacaftor, tezacaftor and ivacaftor are all metabolized by CYP3A. Exposure to elexacaftor, tezacaftor and ivacaftor may be reduced by concomitant CYP3A inducers and increased by concomitant CYP3A inhibitors.
In vitro studies showed that elexacaftor and tezacaftor are substrates for the efflux transporter P-gp, but ivacaftor is not. Elexacaftor and ivacaftor are not substrates for OATP1B1 or OATP1B3; tezacaftor is a substrate for OATP1B1, but not OATP1B3. Tezacaftor is a substrate for BCRP.
The effects of co-administered drugs on the exposure of elexacaftor, tezacaftor and/or ivacaftor are shown in Table 10 [see Dosage and Administration (2.4) and Drug Interactions (7)].
Table 10: Impact of Other Drugs on Elexacaftor, Tezacaftor and/or Ivacaftor| Dose and Schedule | Effect on ELX, TEZ and/or IVA PK | Geometric Mean Ratio (90% CI) of Elexacaftor, Tezacaftor and Ivacaftor
No Effect = 1.0 |
|---|
| AUC | Cmax |
|---|
| ↑ = increase, ↓ = decrease, ↔ = no change. |
| AUC: area under the concentration versus time curve; CI: Confidence Interval; Cmax: maximum observed concentration; ELX: elexacaftor; TEZ: tezacaftor; IVA: ivacaftor; PK: Pharmacokinetics. |
Itraconazole
200 mg q12h on Day 1, followed by 200 mg qd | TEZ 25 mg qd + IVA 50 mg qd | ↑ Tezacaftor | 4.02
(3.71, 4.63) | 2.83
(2.62, 3.07) |
| ↑ Ivacaftor | 15.6
(13.4, 18.1) | 8.60
(7.41, 9.98) |
Itraconazole
200 mg qd | ELX 20 mg + TEZ 50 mg single dose | ↑ Elexacaftor | 2.83
(2.59, 3.10) | 1.05
(0.977, 1.13) |
| ↑ Tezacaftor | 4.51
(3.85, 5.29) | 1.48
(1.33, 1.65) |
Ketoconazole
400 mg qd | IVA 150 mg single dose | ↑ Ivacaftor | 8.45
(7.14, 10.0) | 2.65
(2.21, 3.18) |
Ciprofloxacin
750 mg q12h | TEZ 50 mg q12h + IVA 150 mg q12h | ↔ Tezacaftor | 1.08
(1.03, 1.13) | 1.05
(0.99, 1.11) |
| ↑ Ivacaftor Effect is not clinically significant [see Drug Interactions (7.3)]. | 1.17
(1.06, 1.30) | 1.18
(1.06, 1.31) |
Rifampin
600 mg qd | IVA 150 mg single dose | ↓ Ivacaftor | 0.114
(0.097, 0.136) | 0.200
(0.168, 0.239) |
Fluconazole
400 mg single dose on Day 1, followed by 200 mg qd | IVA 150 mg q12h | ↑ Ivacaftor | 2.95
(2.27, 3.82) | 2.47
(1.93, 3.17) |
Elexacaftor
A 6-month study in Tg.rasH2 transgenic mice showed no evidence of tumorigenicity at 50 mg/kg/day dose, the highest dose tested.
A two-year study was conducted in rats to assess the carcinogenic potential of elexacaftor. No evidence of tumorigenicity was observed in rats at elexacaftor oral doses up to 10 mg/kg/day (approximately 2 and 5 times the MRHD based on summed AUCs of elexacaftor and its metabolite in male and female rats, respectively).
Elexacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene variant, in vitro mammalian cell micronucleus assay in TK6 cells, and in vivo mouse micronucleus test.
Elexacaftor did not cause reproductive system toxicity in male rats at 55 mg/kg/day and female rats at 25 mg/kg/day, equivalent to approximately 6 times and 4 times the MRHD, respectively (based on summed AUCs of elexacaftor and its metabolite). Elexacaftor did not cause embryonic toxicity at 35 mg/kg/day which was the highest dose tested, equivalent to approximately 7 times the MRHD (based on summed AUCs of elexacaftor and its metabolite). Lower male and female fertility, male copulation and female conception indices were observed in males at 75 mg/kg/day and females at 35 mg/kg/day, equivalent to approximately 6 times and 7 times, respectively, the MRHD (based on summed AUCs of elexacaftor and its metabolite).
Tezacaftor
A two-year study in Sprague-Dawley rats and a 6-month study in Tg.rasH2 transgenic mice were conducted to assess the carcinogenic potential of tezacaftor. No evidence of tumorigenicity from tezacaftor was observed in male and female rats at oral doses up to 50 and 75 mg/kg/day (approximately 1 and 2 times the MRHD based on summed AUCs of tezacaftor and its metabolites in males and females, respectively). No evidence of tumorigenicity was observed in male and female Tg.rasH2 transgenic mice at tezacaftor doses up to 500 mg/kg/day.
Tezacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene variant, in vitro chromosomal aberration assay in Chinese hamster ovary cells and in vivo mouse micronucleus test.
There were no effects on male or female fertility and early embryonic development in rats at oral tezacaftor doses up to 100 mg/kg/day (approximately 3 times the MRHD based on summed AUC of tezacaftor and M1-TEZ).
Ivacaftor
Two-year studies were conducted in CD-1 mice and Sprague-Dawley rats to assess the carcinogenic potential of ivacaftor. No evidence of tumorigenicity from ivacaftor was observed in mice or rats at oral doses up to 200 mg/kg/day and 50 mg/kg/day, respectively (approximately equivalent to 2 and 7 times the MRHD, respectively, based on summed AUCs of ivacaftor and its metabolites).
Ivacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene variant, in vitro chromosomal aberration assay in Chinese hamster ovary cells and in vivo mouse micronucleus test.
Ivacaftor impaired fertility and reproductive performance indices in male and female rats at 200 mg/kg/day (approximately 7 and 5 times, respectively, the MRHD based on summed AUCs of ivacaftor and its metabolites). Increases in prolonged diestrus were observed in females at 200 mg/kg/day. Ivacaftor also increased the number of females with all nonviable embryos and decreased corpora lutea, implantations and viable embryos in rats at 200 mg/kg/day (approximately 5 times the MRHD based on summed AUCs of ivacaftor and its metabolites) when dams were dosed prior to and during early pregnancy. These impairments of fertility and reproductive performance in male and female rats at 200 mg/kg/day were attributed to severe toxicity.
Trial 1
Trial 1 evaluated 403 patients (200 TRIKAFTA, 203 placebo) with CF aged 12 years and older (mean age 26.2 years). The mean ppFEV1 at baseline was 61.4% (range: 32.3%, 97.1%). The primary endpoint assessed at the time of interim analysis was mean absolute change in ppFEV1 from baseline at Week 4. The final analysis tested all key secondary endpoints in the 403 patients who completed the 24-week study participation, including absolute change in ppFEV1 from baseline through Week 24; absolute change in sweat chloride from baseline at Week 4 and through Week 24; number of pulmonary exacerbations through Week 24; absolute change in BMI from baseline at Week 24, and absolute change in CFQ-R respiratory domain score (a measure of respiratory symptoms relevant to patients with CF, such as cough, sputum production and difficulty breathing) from baseline at Week 4 and through Week 24.
Of the 403 patients included in the interim analysis, the treatment difference between TRIKAFTA and placebo for the mean absolute change from baseline in ppFEV1 at Week 4 was 13.8 percentage points (95% CI: 12.1, 15.4; P<0.0001).
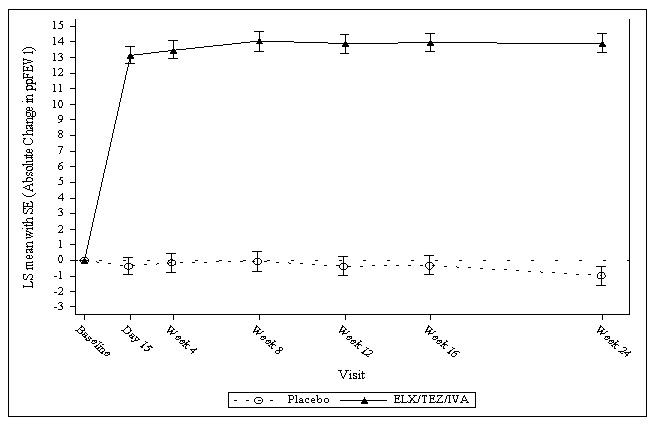
The treatment difference between TRIKAFTA and placebo for mean absolute change in ppFEV1 from baseline through Week 24 was 14.3 percentage points (95% CI: 12.7, 15.8; P<0.0001). Mean improvement in ppFEV1 was observed at the first assessment on Day 15 and sustained through the 24-week treatment period (see Figure 1). Improvements in ppFEV1 were observed regardless of age, baseline ppFEV1, sex and geographic region. See Table 11 for a summary of primary and key secondary outcomes in Trial 1.
Table 11: Primary and Key Secondary Efficacy Analyses (Trial 1)| Analysis | Statistic | Treatment Difference Treatment difference provided as the outcome measure for changes in ppFEV1, sweat chloride, CFQ-R and BMI; Rate ratio provided as the outcome measure for the number of pulmonary exacerbations. for TRIKAFTA (N=200) vs Placebo (N=203) |
|---|
| ppFEV1: percent predicted Forced Expiratory Volume in 1 second; CI: Confidence Interval; CFQ-R: Cystic Fibrosis Questionnaire-Revised; BMI: Body Mass Index. |
| Primary (Interim Full Analysis Set) Primary endpoint was based on interim analysis in 403 patients. |
| Absolute change in ppFEV1 from baseline at Week 4 (percentage points) | Treatment difference (95% CI)
P value | 13.8 (12.1, 15.4)
P<0.0001 |
| Key Secondary (Full Analysis Set) Key secondary endpoints were tested at the final analysis in 403 patients. |
| Absolute change in ppFEV1 from baseline through Week 24 (percentage points) | Treatment difference (95% CI)
P value | 14.3 (12.7, 15.8)
P<0.0001 |
| Number of pulmonary exacerbations from baseline through Week 24 A pulmonary exacerbation was defined as a change in antibiotic therapy (IV, inhaled, or oral) as a result of 4 or more of 12 pre-specified sino-pulmonary signs/symptoms. Number of pulmonary exacerbation events (event rate per year calculated based on 48 weeks per year) in the TRIKAFTA group were 41 (0.37) and 113 (0.98) in the placebo group. | Rate ratio (95% CI)
P value | 0.37 (0.25, 0.55)
P<0.0001 |
| Absolute change in sweat chloride from baseline through Week 24 (mmol/L) | Treatment difference (95% CI)
P value | -41.8 (-44.4, -39.3)
P<0.0001 |
| Absolute change in CFQ-R respiratory domain score from baseline through Week 24 (points) | Treatment difference (95% CI)
P value | 20.2 (17.5, 23.0)
P<0.0001 |
| Absolute change in BMI from baseline at Week 24 (kg/m2) | Treatment difference (95% CI)
P value | 1.04 (0.85, 1.23)
P<0.0001 |
| Absolute change in sweat chloride from baseline at Week 4 (mmol/L) | Treatment difference (95% CI)
P value | -41.2 (-44.0, -38.5)
P<0.0001 |
| Absolute change in CFQ-R respiratory domain score from baseline at Week 4 (points) | Treatment difference (95% CI)
P value | 20.1 (16.9, 23.2)
P<0.0001 |
Figure 1: Absolute Change from Baseline in Percent Predicted FEV1 at Each Visit in Trial 1
Trial 2
Trial 2 evaluated 107 patients with CF aged 12 years and older (mean age 28.4 years). The mean ppFEV1 at baseline, following the 4-week, open-label run-in period with tezacaftor/ivacaftor was 60.9% (range: 35.0%, 89.0%). The primary endpoint was mean absolute change in ppFEV1 from baseline at Week 4 of the double-blind treatment period. The key secondary efficacy endpoints were absolute change in sweat chloride and CFQ-R respiratory domain score from baseline at Week 4. Treatment with TRIKAFTA compared to tezacaftor/ivacaftor resulted in a statistically significant improvement in ppFEV1 of 10.0 percentage points (95% CI: 7.4, 12.6; P<0.0001). Mean improvement in ppFEV1 was observed at the first assessment on Day 15. Improvements in ppFEV1 were observed regardless of age, sex, baseline ppFEV1 and geographic region. See Table 12 for a summary of primary and key secondary outcomes.
Table 12: Primary and Key Secondary Efficacy Analyses, Full Analysis Set (Trial 2)| Analysis Baseline for primary and key secondary endpoints is defined as the end of the 4-week tezacaftor/ivacaftor run-in period. | Statistic | Treatment Difference for TRIKAFTA (N=55) vs Tezacaftor/Ivacaftor Regimen of tezacaftor 100 mg qd/ivacaftor 150 mg q12h. (N=52) |
|---|
| ppFEV1: percent predicted Forced Expiratory Volume in 1 second; CI: Confidence Interval; CFQ-R: Cystic Fibrosis Questionnaire-Revised. |
| Primary |
| Absolute change in ppFEV1 from baseline at Week 4 (percentage points) | Treatment difference (95% CI)
P value | 10.0 (7.4, 12.6)
P<0.0001 |
| Key Secondary |
| Absolute change in sweat chloride from baseline at Week 4 (mmol/L) | Treatment difference (95% CI)
P value | -45.1 (-50.1, -40.1)
P<0.0001 |
| Absolute change in CFQ-R respiratory domain score from baseline at Week 4 (points) | Treatment difference (95% CI)
P value | 17.4 (11.8, 23.0)
P<0.0001 |
Drug-Induced Liver Injury and Liver Failure
Inform patients that TRIKAFTA is associated with a serious risk for drug-induced liver injury and that liver injury resulting in liver failure leading to liver transplantation or death have occurred, including in patients without a history of liver disease.
Advise all patients that liver function tests (ALT, AST, alkaline phosphatase, and bilirubin) should be assessed prior to initiating TRIKAFTA and then assessed every month during the first 6 months of treatment, then every 3 months for the next 12 months, then at least annually thereafter. Inform patients with a history of liver disease or liver function test elevations at baseline that more frequent monitoring may be necessary. Instruct patients to interrupt treatment with TRIKAFTA if symptoms of liver injury occur (e.g., jaundice, right upper quadrant pain, nausea, vomiting, altered mental status, ascites) and to notify their healthcare provider immediately. [see Dosage and Administration (2.1) and Warnings and Precautions (5.1)].
Drug Interactions with CYP3A Inducers and Inhibitors
Ask patients to tell you all the medications they are taking including any herbal supplements or vitamins. Inform patients that concomitant use of TRIKAFTA with strong CYP3A inducers (e.g., rifampin, St. John's wort) is not recommended, as they may reduce the efficacy of TRIKAFTA. Dose reduction to two elexacaftor/tezacaftor/ivacaftor tablets or one elexacaftor/tezacaftor/ivacaftor oral granules packet twice a week, taken approximately 3 to 4 days apart is recommended when used concomitantly with strong CYP3A inhibitors, such as ketoconazole. Advise the patient not to take the evening dose of ivacaftor. Dose reduction to two elexacaftor/tezacaftor/ivacaftor tablets or one elexacaftor/tezacaftor/ivacaftor oral granules packet and one ivacaftor tablet or ivacaftor oral granules packet, taken on alternate days, is recommended when used concomitantly with moderate CYP3A inhibitors, such as fluconazole. Advise the patient not to take the evening dose of ivacaftor. Food or drink containing grapefruit should be avoided [see Dosage and Administration (2.4), Warnings and Precautions (5.5, 5.6), Drug Interactions (7.1) and Clinical Pharmacology (12.3)].
Hypersensitivity Reactions, Including Anaphylaxis
Hypersensitivity reactions including angioedema and anaphylaxis are possible with use of TRIKAFTA. Inform patients of the early signs of hypersensitivity reactions including rash, hives, itching, facial swelling, tightness of the chest and wheezing. Advise patients to discontinue use of TRIKAFTA immediately and contact their physician or go to the emergency department if these symptoms occur [see Warnings and Precautions (5.2)].
Intracranial Hypertension
Inform patients that intracranial hypertension has occurred with the use of TRIKAFTA. Instruct patients to notify their healthcare provider right away if they experience signs and symptoms of intracranial hypertension, including headache, blurred vision, diplopia, and vision loss [see Warnings and Precautions (5.3)].
Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors
Inform patients that neuropsychiatric symptoms, including anxiety, depression, suicidal thoughts and behaviors, and sleep disturbances (e.g., insomnia), have been reported with the use of TRIKAFTA or drugs containing the same or similar active ingredients as TRIKAFTA. The symptoms have been observed in patients with and without a history of similar symptoms and may occur within three months of TRIKAFTA initiation. Instruct patients to contact their healthcare provider immediately if changes in behavior or thinking that are not typical for the patient occur, or if the patient develops suicidal ideation or behavior [see Warnings and Precautions (5.4)].
Cataracts
Inform patients that abnormality of the eye lens (cataract) has been noted in some children and adolescents receiving ivacaftor-containing regimens. Baseline and follow-up ophthalmological examinations should be performed in pediatric patients initiating treatment with TRIKAFTA [see Warnings and Precautions (5.7) and Use in Specific Populations (8.4)].
Administration
Inform patients that TRIKAFTA is best absorbed by the body when taken with food that contains fat. A typical CF diet will satisfy this requirement. Examples include eggs, butter, peanut butter, whole-milk dairy products (such as whole milk, cheese and yogurt), etc. [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3)].
Patients should be informed about what to do in the event they miss a dose [see Dosage and Administration (2.5)] of TRIKAFTA:
- If 6 hours or less have passed since the missed morning or evening dose is usually taken, patients should be instructed to take the prescribed dose with fat-containing food as soon as possible.
- If more than 6 hours have passed since:
- the time the morning dose is usually taken, patients should be instructed to take the morning dose as soon as possible, and not take the evening dose. Patients should take the next scheduled morning dose at the usual time.
- the time the evening dose is usually taken, patients should be instructed to not take the missed evening dose. Patients should take the next scheduled morning dose at the usual time.
- Patients should be instructed to not take the morning and evening doses at the same time.
- Patients should be advised to contact their health care provider if they have questions.
Manufactured for
Vertex Pharmaceuticals Incorporated
50 Northern Avenue
Boston, MA 02210
TRIKAFTA, VERTEX and Vertex triangle logo are registered trademarks of Vertex Pharmaceuticals Incorporated.
All other trademarks referenced herein are the property of their respective owners.
©2026 Vertex Pharmaceuticals Incorporated
All Rights Reserved