Adverse Reactions in Placebo-Controlled Trials
In the two well-controlled studies demonstrating effectiveness, 1529 patients received dimethyl fumarate delayed-release capsules with an overall exposure of 2244 person-years
[see Clinical Studies (
14)]
.
The adverse reactions presented in the table below are based on safety information from 769 patients treated with dimethyl fumarate delayed-release capsules 240 mg twice a day and 771 placebo-treated patients.
The most common adverse reactions (incidence ≥10% and ≥2% more than placebo) for dimethyl fumarate delayed-release capsules were flushing, abdominal pain, diarrhea, and nausea.
Table 1: Adverse Reactions in Study 1 and 2 reported for Dimethyl Fumarate Delayed-Release Capsules 240 mg BID at ≥ 2% higher incidence than placebo | Dimethyl Fumarate Delayed-Release Capsules
N=769
% | Placebo
N=771
% |
| | |
| Flushing | 40 | 6 |
| Abdominal pain | 18 | 10 |
| Diarrhea | 14 | 11 |
| Nausea | 12 | 9 |
| Vomiting | 9 | 5 |
| Pruritus | 8 | 4 |
| Rash | 8 | 3 |
| Albumin urine present | 6 | 4 |
| Erythema | 5 | 1 |
| Dyspepsia | 5 | 3 |
| Aspartate aminotransferase increased | 4 | 2 |
| Lymphopenia | 2 | <1 |
Gastrointestinal
Dimethyl fumarate delayed-release capsules caused GI events (e.g., nausea, vomiting, diarrhea, abdominal pain, and dyspepsia). The incidence of GI events was higher early in the course of treatment (primarily in month 1) and usually decreased over time in patients treated with dimethyl fumarate delayed-release capsules compared with placebo. Four percent (4%) of patients treated with dimethyl fumarate delayed-release capsules and less than 1% of placebo patients discontinued due to gastrointestinal events. The incidence of serious GI events was 1% in clinical trial patients treated with dimethyl fumarate delayed-release capsules; these events, none of which were fatal, included vomiting (0.3%) and abdominal pain (0.3%).
Hepatic Transaminases
An increased incidence of elevations of hepatic transaminases in patients treated with dimethyl fumarate delayed-release capsules was seen primarily during the first six months of treatment, and most patients with elevations had levels < 3 times the upper limit of normal (ULN) during controlled trials. Elevations of alanine aminotransferase and aspartate aminotransferase to ≥ 3 times the ULN occurred in a small number of patients treated with both dimethyl fumarate delayed-release capsules and placebo and were balanced between groups. There were no elevations in transaminases ≥ 3 times the ULN with concomitant elevations in total bilirubin > 2 times the ULN. Discontinuations due to elevated hepatic transaminases were < 1% and were similar in patients treated with dimethyl fumarate delayed-release capsules or placebo.
Eosinophilia
A transient increase in mean eosinophil counts was seen during the first 2 months of therapy.
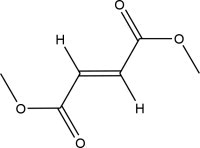
Dimethyl fumarate, USP is a white to off-white powder that is highly soluble in water with a molecular mass of 144.13.
Dimethyl fumarate delayed-release capsules, USP are provided as hard gelatin delayed-release capsules for oral administration, containing 120 mg or 240 mg of dimethyl fumarate consisting of the following inactive ingredients: silicified microcrystalline cellulose, microcrystalline cellulose, talc, croscarmellose sodium, colloidal silicon dioxide, magnesium stearate, methacrylic acid and methyl methacrylate copolymer, triethyl citrate, methacrylic acid copolymer dispersion, sodium lauryl sulphate, and polysorbate 80. The capsule shell, printed with black ink, contains the following inactive ingredients: gelatin, titanium dioxide, sodium lauryl sulfate, brilliant blue FCF, and tartrazine (Yellow No. 5). The black inks contain: shellac, isopropyl alcohol, butyl alcohol, propylene glycol, black iron oxide, and ammonium hydroxide or potassium hydroxide, dehydrated alcohol, and strong ammonia solution.
Absorption
The median Tmax of MMF is 2-2.5 hours. The peak plasma concentration (C
max) and overall exposure (AUC) increased approximately dose proportionally in the dose range studied (120 mg to 360 mg). Following administration of dimethyl fumarate delayed-release capsules 240 mg twice a day with food, the mean C
maxof MMF was 1.87 mg/L and AUC was 8.21 mg.hr/L in MS patients.
A high-fat, high-calorie meal did not affect the AUC of MMF but decreased its C
maxby 40%. The T
maxwas delayed from 2.0 hours to 5.5 hours. In this study, the incidence of flushing was reduced by approximately 25% in the fed state.
Distribution
The apparent volume of distribution of MMF varies between 53 and 73 L in healthy subjects. Human plasma protein binding of MMF is 27-45% and independent of concentration.
Metabolism
In humans, dimethyl fumarate is extensively metabolized by esterases, which are ubiquitous in the gastrointestinal tract, blood, and tissues, before it reaches the systemic circulation. Further metabolism of MMF occurs through the tricarboxylic acid (TCA) cycle, with no involvement of the cytochrome P450 (CYP) system. MMF, fumaric and citric acid, and glucose are the major metabolites in plasma.
Elimination
Exhalation of CO2 is the primary route of elimination, accounting for approximately 60% of the dimethyl fumarate delayed-release capsules dose. Renal and fecal elimination are minor routes of elimination, accounting for 16% and 1% of the dose respectively. Trace amounts of unchanged MMF were present in urine.
The terminal half-life of MMF is approximately 1 hour and no circulating MMF is present at 24 hours in the majority of individuals. Accumulation of MMF does not occur with multiple doses of dimethyl fumarate delayed-release capsules.
Specific Populations
Body weight, gender, and age do not require dosage adjustment.
No studies have been conducted in subjects with hepatic or renal impairment. However, neither condition would be expected to affect exposure to MMF and therefore no dosage adjustment is necessary.
Drug Interaction Studies
No potential drug interactions with dimethyl fumarate or MMF were identified in in vitro CYP inhibition and induction studies, or in P-glycoprotein studies. Single doses of interferon beta-1a or glatiramer acetate did not alter the pharmacokinetics of MMF. Aspirin, when administered approximately 30 minutes before dimethyl fumarate delayed-release capsules, did not alter the pharmacokinetics of MMF.
Oral Contraceptives
The coadministration of dimethyl fumarate with a combined oral contraceptive (norelgestromin and ethinyl estradiol) did not elicit any relevant effects in oral contraceptives exposure. No interaction studies have been performed with oral contraceptives containing other progestogens.
Vaccines
A randomized, open-label study examined the concomitant use of dimethyl fumarate delayed-release capsules and several non-live vaccines in adults 27-55 years of age with relapsing forms of MS (38 subjects undergoing treatment with dimethyl fumarate delayed-release capsules at the time of vaccination and 33 subjects undergoing treatment with non-pegylated interferon at the time of vaccination). Concomitant exposure to dimethyl fumarate delayed-release capsules did not attenuate antibody responses to tetanus toxoid-containing vaccine, pneumococcal polysaccharide, and meningococcal vaccines relative to antibody responses in interferon-treated patients. The impact of these findings on vaccine effectiveness in this patient population is unknown. The safety and effectiveness of live or live-attenuated vaccines administered concomitantly with dimethyl fumarate delayed-release capsules have not been assessed.
Mutagenesis
Dimethyl fumarate (DMF) and monomethyl fumarate (MMF) were not mutagenic in the
in vitrobacterial reverse mutation (Ames) assay. DMF and MMF were clastogenic in the
in vitro chromosomal aberration assay in human peripheral blood lymphocytes in the absence of metabolic activation. DMF was not clastogenic in the
in vivomicronucleus assay in the rat.
Impairment of Fertility
In male rats, oral administration of DMF (75, 250, and 375 mg/kg/day) prior to and throughout the mating period had no effect on fertility; however, increases in non-motile sperm were observed at the mid and high doses. The no-effect dose for adverse effects on sperm is similar to the recommended human dose (RHD) of 480 mg/day on a body surface area (mg/m
2) basis.
In female rats, oral administration of DMF (20, 100, and 250 mg/kg/day) prior to and during mating and continuing to gestation day 7 caused disruption of the estrous cycle and increases in embryolethality at the highest dose tested. The highest dose not associated with adverse effects (100 mg/kg/day) is twice the RHD on a mg/m
2basis.
Testicular toxicity (germinal epithelial degeneration, atrophy, hypospermia, and/or hyperplasia) was observed at clinically relevant doses in mice, rats, and dogs in subchronic and chronic oral toxicity studies of DMF, and in a chronic oral toxicity study evaluating a combination of four fumaric acid esters (including DMF) in rats.
Study 1: Placebo-Controlled Trial in RRMS
Study 1 was a 2-year randomized, double-blind, placebo-controlled study in 1234 patients with RRMS. The primary endpoint was the proportion of patients relapsed at 2 years. Additional endpoints at 2 years included the number of new or newly enlarging T2 hyperintense lesions, number of new T1 hypointense lesions, number of Gd+ lesions, annualized relapse rate (ARR), and time to confirmed disability progression. Confirmed disability progression was defined as at least a 1 point increase from baseline EDSS (1.5 point increase for patients with baseline EDSS of 0) sustained for 12 weeks.
Patients were randomized to receive dimethyl fumarate delayed-release capsules 240 mg twice a day (n=410), dimethyl fumarate delayed-release capsules 240 mg three times a day (n=416), or placebo (n=408) for up to 2 years. The median age was 39 years, median time since diagnosis was 4 years, and median EDSS score at baseline was 2. The median time on study drug for all treatment arms was 96 weeks. The percentages of patients who completed 96 weeks on study drug per treatment group were 69% for patients assigned to dimethyl fumarate delayed-release capsules 240 mg twice a day, 69% for patients assigned to dimethyl fumarate delayed-release capsules 240 mg three times a day and 65% for patients assigned to placebo groups.
Dimethyl fumarate delayed-release capsules had a statistically significant effect on all of the endpoints described above and the 240 mg three times daily dose showed no additional benefit over the dimethyl fumarate delayed-release capsules 240 mg twice daily dose. The results for this study (240 mg twice a day vs. placebo) are shown in Table 2 and Figure 1.
Table 2: Clinical and MRI Results of Study 1 | Dimethyl Fumarate
Delayed-Release Capsules240 mg BID | Placebo | P-value |
| Clinical Endpoints | N=410 | N=408 | |
Proportion relapsing (primary endpoint) Relative risk reduction | 27%
49%
| 46% | <0.0001 |
| | | |
| Annualized relapse rate | 0.172 | 0.364 | <0.0001 |
| Relative reduction | 53% | | |
| | | |
| Proportion with disability progression | 16% | 27% | 0.0050 |
| Relative risk reduction | 38% | | |
| | | |
| MRI Endpoints | N=152 | N=165 | |
| Mean number of new or newly enlarging | 2.6 | 17 | <0.0001 |
| T2 lesions over 2 years | | | |
| | | |
Percentage of subjects with no new or newly
enlarging lesions
| 45% | 27% | |
| | | |
| | | |
| Number of Gd+ lesions at 2 years | 0.1 (0) | 1.8 (0) | |
| Mean (median) | | | |
| | | |
| Percentage of subjects with | | | |
| 0 lesions | 93% | 62% | |
| 1 lesion | 5% | 10% | |
| 2 lesions | <1% | 8% | |
| 3 to 4 lesions | 0 | 9% | |
| 5 or more lesions | <1% | 11% | |
| | | |
| Relative odds reduction | 90% | | <0.0001 |
| (percentage) | | | |
| | | |
| Mean number of new T1 hypointense | 1.5 | 5.6 | <0.0001 |
| lesions over 2 years | | | |
Figure 1: Time to 12-Week Confirmed Progression of Disability (Study 1)

Image Description (Dtfclinical)
Study 2: Placebo-Controlled Trial in RRMS
Study 2 was a 2-year multicenter, randomized, double-blind, placebo-controlled study that also included an open-label comparator arm in patients with RRMS. The primary endpoint was the annualized relapse rate at 2 years. Additional endpoints at 2 years included the number of new or newly enlarging T2 hyperintense lesions, number of T1 hypointense lesions, number of Gd+ lesions, proportion of patients relapsed, and time to confirmed disability progression as defined in Study 1.
Patients were randomized to receive dimethyl fumarate delayed-release capsules 240 mg twice a day (n=359), dimethyl fumarate delayed-release capsules 240 mg three times a day (n=345), an open-label comparator (n=350), or placebo (n=363) for up to 2 years. The median age was 37 years, median time since diagnosis was 3 years, and median EDSS score at baseline was 2.5. The median time on study drug for all treatment arms was 96 weeks. The percentages of patients who completed 96 weeks on study drug per treatment group were 70% for patients assigned to dimethyl fumarate delayed-release capsules 240 mg twice a day, 72% for patients assigned to dimethyl fumarate delayed-release capsules 240 mg three times a day and 64% for patients assigned to placebo groups.
Dimethyl fumarate delayed-release capsules had a statistically significant effect on the relapse and MRI endpoints described above. There was no statistically significant effect on disability progression. The dimethyl fumarate delayed-release capsules 240 mg three times daily dose resulted in no additional benefit over the dimethyl fumarate delayed-release capsules 240 mg twice daily dose. The results for this study (240 mg twice a day vs. placebo) are shown in Table 3.
Table 3: Clinical and MRI Results of Study 2 | Dimethyl Fumarate
Delayed-Release Capsules 240 mg BID | Placebo | P-value |
| Clinical Endpoints | N=359 | N=363 | |
Annualized relapse rate
Relative reduction
| 0.224
44%
| 0.401
| <0.0001
|
| | | |
| Proportion relapsing | 29% | 41% | 0.0020 |
| Relative risk reduction | 34% | | |
| | | |
| Proportion with disability progression | 13% | 17% | 0.25 |
| Relative risk reduction | 21% | | |
| | | |
| MRI Endpoints | N=147 | N=144 | |
| Mean number of new or newly | 5.1 | 17.4 | <0.0001 |
| enlarging T2 lesions over 2 years | | | |
| | | |
Percentage of subjects with no new or
newly enlarging lesions
| 27% | 12% | |
| | | |
| | | |
| Number of Gd+ lesions at 2 years | | | |
| Mean (median) | 0.5 (0.0) | 2.0 (0.0) | |
| | | |
| Percentage of subjects with | | | |
| 0 lesions | 80% | 61% | |
| 1 lesion | 11% | 17% | |
| 2 lesions | 3% | 6% | |
| 3 to 4 lesions | 3% | 2% | |
| 5 or more lesions | 3% | 14% | |
| | | |
| Relative odds reduction | 74% | | <0.0001 |
| (percentage) | | | |
| | | |
| Mean number of new T1 hypointense | 3.0 | 7.0 | <0.0001 |
| lesions over 2 years | | | |
Dosage
Inform patients that they will be provided two strengths of dimethyl fumarate delayed-release capsules when starting treatment: 120 mg capsules for the 7 day starter dose and 240 mg capsules for the maintenance dose, both to be taken twice daily. Inform patients to swallow dimethyl fumarate delayed-release capsules whole and intact. Inform patients to not crush, chew, or sprinkle capsule contents on food. Inform patients that dimethyl fumarate delayed-release capsules can be taken with or without food
[see Dosage and Administration (
2.1)]
.
Anaphylaxis and Angioedema
Advise patients to discontinue dimethyl fumarate delayed-release capsules and seek medical care if they develop signs and symptoms of anaphylaxis or angioedema
[see Warnings and Precautions (
5.1)]
.
Progressive Multifocal Leukoencephalopathy
Inform patients that progressive multifocal leukoencephalopathy (PML) has occurred in patients who received dimethyl fumarate delayed-release capsules. Inform the patient that PML is characterized by a progression of deficits and usually leads to death or severe disability over weeks or months. Instruct the patient of the importance of contacting their doctor if they develop any symptoms suggestive of PML. Inform the patient that typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes
[see Warnings and Precautions (
5.2)]
.
Herpes Zoster and Other Serious Opportunistic Infections
Inform patients that herpes zoster and other serious opportunistic infections have occurred in patients who received dimethyl fumarate delayed-release capsules. Instruct the patient of the importance of contacting their doctor if they develop any signs or symptoms associated with herpes zoster or other serious opportunistic infections
[see Warnings and Precautions (
5.3)]
.
Lymphocyte Counts
Inform patients that dimethyl fumarate delayed-release capsules may decrease lymphocyte counts. A blood test should be obtained before they start therapy. Blood tests are also recommended after 6 months of treatment, every 6 to 12 months thereafter, and as clinically indicated
[see Warnings and Precautions (
5.4), Adverse Reactions (
6.1)]
.
Liver Injury
Inform patients that dimethyl fumarate delayed-release capsules may cause liver injury. Instruct patients treated with dimethyl fumarate delayed-release capsules to report promptly any symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine, or jaundice. A blood test should be obtained before patients start therapy and during treatment, as clinically indicated
[see Warnings and Precautions (
5.5)]
.
Flushing
Inform patients that flushing is one of the most common reactions, especially at the initiation of therapy, and may decrease over time. Advise patients to contact their healthcare provider if they experience persistent and/or severe flushing. Advise patients experiencing flushing that taking dimethyl fumarate delayed-release capsules with food or taking a non-enteric coated aspirin prior to taking dimethyl fumarate delayed-release capsules may help
[see Adverse Reactions (
6.1)]
.
Gastrointestinal (GI) Events
Inform patients that GI events (abdominal pain, diarrhea, and nausea) are some of the most common adverse reactions, especially at the initiation of therapy, and may decrease over time. Some patients may experience more severe GI events. Advise patients to immediately contact their healthcare provider and discontinue dimethyl fumarate delayed-release capsules if they experience gastrointestinal bleeding (e.g., rectal bleeding, bloody diarrhea, hematemesis) or other serious gastrointestinal adverse events (e.g., severe abdominal pain, severe vomiting and/or diarrhea)
[see Warnings and Precautions (
5.7)]
.
Distributed by
UPSHER-SMITH LABORATORIES, LLC
Maple Grove, MN 55369
Product of India
LA-3118-06 Revised: 11/2025
Marketed by:
GSMS, Inc.
Camarillo, CA 93012 USA