- Administer TRODELVY as an intravenous infusion.
- First infusion: Administer over 3 hours. Observe patients during the infusion and for at least 30 minutes following the initial dose, for signs or symptoms of infusion-related reactions [see Warning and Precautions (5.3)].
- Second and subsequent infusions: Administer over 1 to 2 hours if prior infusions were tolerated. Observe patients during the infusion and for at least 30 minutes after infusion.
- Protect infusion bag from light. The infusion bag should be covered during administration to the patient until dosing is complete. It is not necessary to cover the infusion tubing or to use light-protective tubing during the infusion.
- An infusion pump may be used.
- Do not mix TRODELVY, or administer in the same intravenous line, with other medicinal products.
- Upon completion of the infusion, flush the intravenous line with 20 mL 0.9% Sodium Chloride Injection, USP.
Locally Advanced or Metastatic Triple-Negative Breast Cancer (TNBC)
Single-Agent in Previously Untreated Unresectable Locally Advanced or Metastatic TNBC (ASCENT-03)
The safety of TRODELVY was evaluated in 275 patients with unresectable locally advanced or metastatic TNBC who had not received previous systemic therapy for advanced disease and who were not candidates for PD-1 or PD-L1 inhibitor therapy who had received at least one dose of TRODELVY 10 mg/kg in ASCENT-03. [see Clinical Studies (14.1)]. The median duration of treatment was 8.3 months (range: 0 to 29 months).
Serious adverse reactions occurred in 26% of patients receiving TRODELVY. Serious adverse reactions in > 2% of patients included diarrhea, febrile neutropenia, and neutropenia (3.6% each) and pneumonia (2.9%). Fatal adverse reactions occurred in 2.5% of patients who received TRODELVY including sepsis (1.1%) and acute respiratory failure , neutropenic colitis, pneumonia, and septic shock (0.4% each).
Permanent discontinuation of TRODELVY due to adverse reactions occurred in 3.6% of patients, of which interstitial lung disease accounted for 1.1%.
Dosage interruptions of TRODELVY occurred in 66% of patients. Adverse reactions which required dosage interruption in ≥ 5% of patients were decreased neutrophil count (43%), diarrhea (6%), decreased leukocyte count and COVID-19 (5% each).
Dose reductions of TRODELVY due to an adverse reaction occurred in 37% of patients. Adverse reaction which required dose reductions in >2% of patients included decreased neutrophil count (18%), diarrhea (6%), fatigue (4.7%), febrile neutropenia (2.5%), and weight decreased (2.2%).
The most common (≥25%) adverse reactions, including laboratory abnormalities, were decreased neutrophil count (84%), decreased leukocyte count (80%), decreased hemoglobin (78%), nausea (61%), diarrhea and alopecia (55% each), increased glucose (52%), decreased lymphocyte count and fatigue (47% each), increased alanine aminotransferase (39%), increased alkaline phosphatase and constipation (38% each), increased lactate dehydrogenase (35%), increased aspartate aminotransferase (31%), decreased potassium (28%) and vomiting (25%).
Tables 3 and 4 summarize the adverse reactions and laboratory abnormalities in ASCENT-03.
Table 3: Adverse Reactions in ≥ 10% of Patients with Metastatic TNBC in ASCENT-03 | TRODELVY
(n=275) | Treatment of Physician’s Choice Treatment of Physician’s Choice included gemcitabine/carboplatin (n=122), nab-paclitaxel (n=110), and paclitaxel (n=44)
(n=276) |
|---|
| Adverse Reaction Graded per NCI CTCAE v.5.0. | All Grades
(%) | Grade 3 - 4
(%) | All Grades
(%) | Grade 3 - 4
(%) |
|---|
| Gastrointestinal disorders |
| Nausea | 61 | 1.8 | 34 | 0.4 |
| Diarrhea Includes other related terms | 55 | 10 | 20 | 0.7 |
| Constipation | 38 | 0 | 25 | 0 |
| Vomiting | 25 | 1.8 | 13 | 1.4 |
| Abdominal Pain | 24 | 0.7 | 12 | 0 |
| Stomatitis | 19 | 1.1 | 9 | 0.4 |
| Skin and subcutaneous tissue disorders |
| Alopecia | 55 | 0 | 27 | 0 |
| Rash | 20 | 0.4 | 18 | 0.4 |
| Pruritus | 10 | 0 | 6 | 0 |
| General disorders and administration site conditions |
| Fatigue | 47 | 3.3 | 47 | 4.0 |
| Edema | 11 | 0.4 | 11 | 0 |
| Pyrexia | 11 | 1.1 | 10 | 0.7 |
| Respiratory, thoracic and mediastinal disorders |
| Cough | 18 | 0 | 13 | 0.4 |
| Metabolism and nutrition disorders |
| Decreased appetite | 17 | 0.7 | 10 | 0.4 |
| Nervous system disorders |
| Headache | 17 | 0.4 | 12 | 0 |
| Peripheral neuropathy | 12 | 0 | 31 | 0.4 |
| Infections and infestations |
| Upper respiratory tract infection | 16 | 0.4 | 9 | 0 |
| Urinary tract infection | 10 | 0.7 | 15 | 0.7 |
| Musculoskeletal and connective tissue disorders |
| Arthralgia | 15 | 0 | 17 | 0.4 |
| Back pain | 11 | 0.4 | 8 | 0.4 |
Table 4: Laboratory Abnormalities in > 10% of Patients with Metastatic TNBC in ASCENT-03| Laboratory Abnormality | TRODELVY
(n=275) | Treatment of Physician’s Choice
(n=276) |
|---|
| All Grades
(%) | Grade 3 - 4
(%) | All Grades
(%) | Grade 3 - 4
(%) |
|---|
| Hematology | |
| Decreased neutrophil count | 84 | 47 | 80 | 43 |
| Decreased leukocyte count | 80 | 29 | 80 | 33 |
| Decreased hemoglobin | 78 | 7 | 81 | 19 |
| Decreased lymphocyte count | 47 | 16 | 53 | 19 |
| Decreased platelet count | 18 | 6 | 40 | 17 |
| Chemistry | |
| Increased glucose | 52 | 0 | 44 | 0 |
| Increased alanine aminotransferase | 39 | 4.0 | 56 | 6 |
| Increased alkaline phosphatase | 38 | 1.1 | 35 | 0 |
| Increased lactate dehydrogenase | 35 | 0 | 35 | 0 |
| Increased aspartate aminotransferase | 31 | 2.2 | 47 | 2.5 |
| Decreased potassium | 28 | 5 | 18 | 2.5 |
| Decreased albumin | 23 | 2.5 | 14 | 0.4 |
| Decreased magnesium | 19 | 2.9 | 25 | 0.7 |
| Decreased sodium | 18 | 1.5 | 15 | 1.1 |
| Increased phosphate | 16 | 0 | 9 | 0 |
| Increased potassium | 16 | 0.7 | 18 | 0.7 |
| Increased magnesium | 14 | 5 | 11 | 1.8 |
| Hypoglycemia | 14 | 1.1 | 9 | 0 |
| Decreased phosphate | 12 | 0 | 10 | 0 |
| Increased urate | 12 | 0 | 4 | 0 |
In Combination with Pembrolizumab in Previously Untreated, Unresectable Locally Advanced or Metastatic TNBC whose tumors express PD-L1 (ASCENT-04)
The safety of TRODELVY in combination with pembrolizumab was evaluated in 221 patients with unresectable locally advanced or metastatic TNBC who have not received previous systemic therapy for advanced disease and whose tumors express PD-L1 who received at least one dose of TRODELVY 10 mg/kg in combination with pembrolizumab. [see Clinical Studies (14.1)]. The median duration of treatment of TRODELVY was 8.9 months (range: 0 to 27 months).
Serious adverse reactions occurred in 38% of patients receiving TRODELVY in combination with pembrolizumab. Serious adverse reactions in ≥ 2% of patients included febrile neutropenia (7%), neutropenia (6%), diarrhea (5%), fatigue and pneumonia (2.3% each). Fatal adverse reactions occurred in 3.2% of patients who received TRODELVY in combination with pembrolizumab including death (unknown cause) (0.9%) and completed suicide, neutropenic sepsis, sepsis, pneumonia, and pulmonary embolism (0.5% each).
Permanent discontinuation of TRODELVY due to an adverse reaction occurred in 7% of patients. Adverse reactions which resulted in permanent discontinuation of TRODELVY in ≥1% of patients included infusion related reaction (0.9%).
Dosage interruptions of TRODELVY due to an adverse reaction occurred in 75% of patients. Adverse reactions which required dosage interruption in ≥5% of patients included neutropenia (44%), upper respiratory tract infection (10%), diarrhea (8%), COVID-19 (6%), and anemia and fatigue (5% each).
Dose reduction of TRODELVY due to an adverse reaction occurred in 35% of patients. Adverse reactions which required dose reductions in ≥5% of patients included neutropenia (15%), diarrhea (8%), and fatigue (6%).
G-CSF was used in 63% of patients who received TRODELVY in combination with pembrolizumab.
The most common (≥25%) adverse reactions, including laboratory abnormalities, were decreased neutrophil count and decreased hemoglobin (86% each), decreased leukocyte count (84%), diarrhea (72%), nausea (68%), decreased lymphocyte count (61%), fatigue (58%), alopecia (52%), increased alkaline phosphatase and increased glucose (50% each), increased alanine aminotransferase (47%), constipation (41%), increased aspartate aminotransferase (40%), rash (37%), decreased potassium (35%), increased lactate dehydrogenase (34%), vomiting (29%), abdominal pain, headache and increased eosinophils (26% each), and decreased albumin (25%).
Tables 5 and 6 summarize the adverse reactions and laboratory abnormalities in ASCENT-04.
Table 5: Adverse Reactions in ≥ 10% of Patients Receiving TRODELVY in Combination with Intravenous Pembrolizumab with Metastatic TNBC in ASCENT-04 | TRODELVY
plus pembrolizumab
N=221 | Treatment of Physician’s Choice Treatment of Physician’s Choice included gemcitabine/carboplatin (n=107), nab-paclitaxel (n=68), and paclitaxel (n=45)
plus
pembrolizumab
N=220 |
|---|
| Adverse Reactions Graded per NCI CTCAE v. 5.0 | All Grades
(%) | Grade 3-4
(%) | All Grades
(%) | Grade 3-4
(%) |
|---|
| Gastrointestinal disorders |
| Diarrhea Includes other related terms | 72 | 12 | 30 | 2.7 |
| Nausea | 68 | 3.2 | 38 | 1.8 |
| Constipation | 41 | 0.5 | 35 | 0.5 |
| Vomiting | 29 | 0.9 | 14 | 1.8 |
| Abdominal Pain | 26 | 0.5 | 15 | 0 |
| Stomatitis | 18 | 0.5 | 16 | 0 |
| General disorders and administration site conditions |
| Fatigue | 58 | 8 | 56 | 3.2 |
| Edema | 16 | 0.5 | 17 | 0.5 |
| Pyrexia | 12 | 0.9 | 12 | 0.5 |
| Skin and subcutaneous tissue disorders |
| Alopecia | 52 | 0 | 32 | 0 |
| Rash | 37 | 1.4 | 33 | 1.8 |
| Pruritus | 14 | 0.5 | 12 | 0.9 |
| Nervous system disorders |
| Headache | 26 | 0.5 | 18 | 0 |
| Peripheral neuropathy | 13 | 0.9 | 39 | 4.5 |
| Dizziness | 12 | 0 | 10 | 0 |
| Musculoskeletal and connective tissue disorders |
| Arthralgia | 19 | 0.9 | 24 | 0.5 |
| Respiratory, thoracic and mediastinal disorders |
| Cough | 19 | 0.5 | 20 | 0 |
| Metabolism and nutrition disorders |
| Decreased appetite | 18 | 1.8 | 14 | 0 |
| Hypothyroidism | 11 | 0.5 | 18 | 0 |
| Infections and infestations |
| Upper respiratory tract infection | 18 | 0 | 13 | 0 |
| Urinary tract infection | 16 | 1.4 | 16 | 0.5 |
| COVID-19 | 10 | 0.5 | 7 | 0.5 |
| Reproductive system and breast disorders |
| Breast pain | 10 | 0 | 9 | 0 |
| Investigations |
| Weight decreased | 10 | 0 | 5 | 0.5 |
Table 6: Laboratory Abnormalities in > 10% of Patients Receiving TRODELVY in Combination with Intravenous Pembrolizumab with Metastatic TNBC in ASCENT-04| Laboratory Abnormality | TRODELVY plus
pembrolizumab
N=221 | TPC
plus pembrolizumab
N=220 |
|---|
| All Grades
(%) | Grade 3 - 4
(%) | All Grades
(%) | Grade 3 - 4
(%) |
|---|
| Hematology | |
| Decreased neutrophil count | 86 | 50 | 86 | 47 |
| Decreased hemoglobin | 86 | 10 | 88 | 18 |
| Decreased leukocytes count | 84 | 32 | 83 | 31 |
| Decreased lymphocyte count | 61 | 21 | 60 | 19 |
| Increased eosinophils | 26 | 0 | 17 | 0 |
| Decreased platelet count | 16 | 5 | 43 | 17 |
| Chemistry | |
| Increased alkaline phosphate | 50 | 0.9 | 33 | 1.8 |
| Increased glucose | 50 | 0 | 47 | 0 |
| Increased alanine aminotransferase | 47 | 4.1 | 55 | 8 |
| Increased aspartate aminotransferase | 40 | 3.7 | 51 | 4.1 |
| Decreased potassium | 35 | 4.6 | 24 | 2.3 |
| Increased lactate dehydrogenase | 34 | 0 | 37 | 0 |
| Decreased albumin | 25 | 0.9 | 14 | 0.9 |
| Decreased sodium | 20 | 1.4 | 20 | 3.2 |
| Increased Urate | 19 | 0 | 7 | 0 |
| Increased magnesium | 17 | 6 | 13 | 3.7 |
| Increased phosphate | 17 | 0 | 12 | 0 |
| Decreased magnesium | 16 | 1.4 | 21 | 0 |
| Increased thyroid stimulating hormone | 15 | 0 | 24 | 0 |
| Decreased phosphate | 14 | 0 | 9 | 0 |
| Increased blood bilirubin | 12 | 3.7 | 8 | 3.2 |
| Increased sodium | 12 | 0.5 | 2.3 | 0.5 |
| Decreased glucose | 11 | 0 | 15 | 1.4 |
| Increased potassium | 11 | 0.9 | 9 | 0.9 |
Previously Treated Locally Advanced or Metastatic TNBC (ASCENT)
The safety of TRODELVY was evaluated in 258 patients with metastatic TNBC who had previously received a taxane and at least two prior chemotherapies and who received at least one dose of TRODELVY 10 mg/kg in ASCENT. [see Clinical Studies (14.1)]. The median duration of treatment was 4.4 months (range: 0 to 23 months).
Serious adverse reactions occurred in 27% of patients receiving TRODELVY. Serious adverse reactions in > 1% of patients receiving TRODELVY included neutropenia (7%), diarrhea (4%), and pneumonia (3%). Fatal adverse reactions occurred in 1.2% of patients who received TRODELVY, including respiratory failure (0.8%) and pneumonia (0.4%).
Permanent discontinuation of TRODELVY due to an adverse reaction occurred in 5% of patients. Adverse reactions which resulted in permanent discontinuation of TRODELVY in ≥1% of patients included pneumonia and fatigue (1% each).
Dosage interruptions of TRODELVY due to an adverse reaction occurred in 63% of patients. Adverse reactions which required dosage interruption in ≥5% of patients included neutropenia (47%), diarrhea (5%), respiratory infection (5%), and leukopenia (5%).
Dose reductions of TRODELVY due to an adverse reaction occurred in 22% of patients. Adverse reactions which required a dose reduction in >4% of patients included neutropenia (11%) and diarrhea (5%).
Granulocyte-colony stimulating factor (G-CSF) was used in 44% of patients who received TRODELVY.
The most common (≥25%) adverse reactions, including laboratory abnormalities, were decreased hemoglobin (94%), decreased lymphocyte count (88%), decrease leukocyte count (86%), decreased neutrophil count (78%), fatigue (65%), diarrhea (59%), nausea (57%), increased glucose (49%), alopecia (47%), constipation (37%), decreased calcium (36%), vomiting, decreased magnesium, and decreased potassium (33% each), increased albumin (32%), abdominal pain (30%), decreased appetite (28%), increased aspartate aminotransferase (27%), increased alanine aminotransferase, increased alkaline phosphatase and decreased phosphate (26% each).
Tables 7 and 8 summarize adverse reactions and laboratory abnormalities, respectively, in ASCENT.
Table 7: Adverse Reactions in ≥ 10% of Patients with Metastatic TNBC in ASCENT | TRODELVY
(n=258) | Single Agent Chemotherapy Single agent chemotherapy included one of the following single-agents: eribulin (n=139), capecitabine (n=33), gemcitabine (n=38), or vinorelbine (except if patient had ≥ Grade 2 neuropathy, n=52).
(n=224) |
|---|
| Adverse Reaction | All Grades
% | Grade 3 - 4
% | All Grades
% | Grade 3 - 4
% |
|---|
| i. Graded per NCI CTCAE v.5.0. |
| General disorders and administration site conditions |
| Fatigue Includes other related terms | 65 | 6 | 50 | 9 |
| Pyrexia | 15 | 0.4 | 14 | 2.2 |
| Gastrointestinal disorders |
| Diarrhea | 59 | 11 | 17 | 0.9 |
| Nausea | 57 | 3.1 | 26 | 0.4 |
| Vomiting | 33 | 1.6 | 16 | 1.3 |
| Constipation | 37 | 0.4 | 23 | 0 |
| Abdominal Pain | 30 | 2.7 | 12 | 1.3 |
| Stomatitis | 17 | 1.6 | 13 | 1.3 |
| Skin and subcutaneous tissue disorders |
| Alopecia | 47 | 0 | 16 | 0 |
| Rash | 12 | 0.4 | 5 | 0.4 |
| Pruritus | 10 | 0 | 3.1 | 0 |
| Metabolism and nutrition disorders |
| Decreased appetite | 28 | 1.6 | 21 | 0.9 |
| Respiratory, thoracic and mediastinal disorders |
| Cough | 24 | 0 | 18 | 0.4 |
| Nervous system disorders |
| Headache | 18 | 0.8 | 13 | 0.4 |
| Dizziness | 10 | 0 | 7 | 0 |
| Musculoskeletal and connective tissue disorders |
| Back pain | 16 | 1.2 | 14 | 1.8 |
| Arthralgia | 12 | 0.4 | 7 | 0 |
| Infections and infestations |
| Urinary tract infection | 13 | 0.4 | 8 | 0.4 |
| Upper respiratory tract infection | 12 | 0 | 3.1 | 0 |
| Psychiatric disorders |
| Insomnia | 11 | 0 | 5 | 0 |
Table 8: Laboratory Abnormalities in > 10% of Patients with Metastatic TNBC in ASCENT | Laboratory Abnormality | TRODELVY
(n=258) | Single Agent Chemotherapy
(n=224) |
|---|
| All Grades
(%) | Grade 3 - 4
(%) | All Grades
(%) | Grade 3 - 4
(%) |
|---|
| Hematology | |
| Decreased hemoglobin | 94 | 9 | 57 | 6 |
| Decreased lymphocyte count | 88 | 31 | 40 | 24 |
| Decreased leukocyte count | 86 | 41 | 53 | 25 |
| Decreased neutrophil count | 78 | 49 | 48 | 36 |
| Decreased platelet count | 23 | 1.2 | 25 | 2.7 |
| Chemistry | |
| Increased glucose | 49 | 2.3 | 43 | 2.8 |
| Decreased calcium | 36 | 1.6 | 21 | 1.4 |
| Decreased magnesium | 33 | 0.4 | 20 | 0 |
| Decreased potassium | 33 | 4.3 | 28 | 0.9 |
| Increased albumin | 32 | 0.8 | 25 | 1.4 |
| Increased aspartate aminotransferase | 27 | 1.2 | 32 | 1.4 |
| Increased alanine aminotransferase | 26 | 1.2 | 26 | 1.8 |
| Increased alkaline phosphatase | 26 | 0 | 17 | 0.5 |
| Decreased phosphate | 26 | 7.8 | 20 | 3.3 |
| Decreased sodium | 22 | 0.4 | 17 | 0.5 |
| Increased lactate dehydrogenase | 18 | 0 | 22 | 0 |
| Decreased glucose | 10 | 0 | 3.2 | 0 |
Study IMMU-132-01
The safety of TRODELVY was evaluated in 108 patients with metastatic TNBC who had received at least two prior anticancer therapies for metastatic disease who received at least one dose of TRODELVY at doses up to 10 mg/kg. [see Clinical Studies (14.1)]. The median duration of treatment was 5.1 months (range: 0 to 51 months).
Serious adverse reactions occurred in 31% of patients receiving TRODELVY. Serious adverse reactions in > 1% of patients receiving TRODELVY included febrile neutropenia (6%) vomiting (5%), diarrhea (3.7%), nausea and dyspnea (2.8%), anemia, pleural effusion, neutropenia, pneumonia, dehydration (each 1.9%). A fatal adverse reaction of metastases to spine occurred in 1 patient (0.9%) who received TRODELVY.
Permanent discontinuation of TRODELVY due to an adverse reaction occurred in 2.8% of patients. Adverse reactions which resulted in permanent discontinuation of TRODELVY included anaphylaxis, decreased appetite, fatigue, and localized edema (each 0.9%).
Dosage interruptions of TRODELVY due to an adverse reaction occurred in 45% of patients. Adverse reactions which required dosage interruption in ≥2% of patients included neutropenia (33%), leukocytes decreased (6%), febrile neutropenia (3.7%), and anemia (2.8%).
Dose reductions of TRODELVY due to an adverse reaction occurred in 33% of patients. Adverse reactions which required dose reductions most commonly included neutropenia/febrile neutropenia.
The most common (≥25%) adverse reactions, including laboratory abnormalities, were decreased hemoglobin (93%), decreased leukocyte count (91%), decreased neutrophil count (82%), nausea (69%), diarrhea (63%), increased activated partial thromboplastin time (60%), fatigue and increased alkaline phosphatase (57% each), vomiting and decreased calcium (49% each), increased aspartate aminotransferase (45%), decreased albumin (39%), alopecia (38%), increased alanine aminotransferase (35%), constipation (34%), rash and increased glucose (31% each), decreased appetite and decreased platelet count (30% each), decreased phosphate (29%), decreased magnesium (27%), abdominal pain (26%), respiratory infection (26%), and decreased sodium (25%).
Tables 9 and 10 summarize adverse reactions and laboratory abnormalities occurring in ≥10% of patients with metastatic TNBC in Study IMMU-132-01.
Table 9: Adverse Reactions in ≥ 10% of Patients with Metastatic TNBC in IMMU-132-01| Adverse Reaction | TRODELVY
(n=108) |
|---|
All Grades
(%) | Grade 3-4
(%) |
|---|
| i. Graded per NCI CTCAE v. 4.0 |
| Any adverse reaction | 100 | 71 |
| Gastrointestinal disorders | 95 | 21 |
| Nausea | 69 | 6 |
| Diarrhea | 63 | 9 |
| Vomiting | 49 | 6 |
| Constipation | 34 | 0.9 |
| Abdominal pain Includes other related terms | 26 | 0.9 |
| Mucositis | 14 | 0.9 |
| General disorders and administration site conditions | 77 | 9 |
| Fatigue | 57 | 8 |
| Edema | 19 | 0 |
| Pyrexia | 14 | 0 |
| Metabolism and nutrition disorders | 68 | 22 |
| Decreased appetite | 30 | 0.9 |
| Dehydration | 13 | 5 |
| Skin and subcutaneous tissue disorders | 63 | 3.7 |
| Alopecia | 38 | 0 |
| Rash | 31 | 2.8 |
| Pruritus | 17 | 0 |
| Dry Skin | 15 | 0 |
| Nervous system disorders | 56 | 3.7 |
| Headache | 23 | 0.9 |
| Dizziness | 22 | 0 |
| Neuropathy | 24 | 0 |
| Dysgeusia | 11 | 0 |
| Infections and infestations | 55 | 12 |
| Respiratory Infection | 26 | 2.8 |
| Urinary Tract Infection | 21 | 2.8 |
| Musculoskeletal and connective tissue disorders | 54 | 0.9 |
| Back pain | 23 | 0 |
| Arthralgia | 17 | 0 |
| Pain in extremity | 11 | 0 |
| Respiratory, thoracic and mediastinal disorders | 54 | 5 |
| Cough | 22 | 0 |
| Dyspnea | 21 | 2.8 |
| Psychiatric disorders | 26 | 0.9 |
| Insomnia | 13 | 0 |
Table 10: Laboratory Abnormalities observed in > 10% of Patients with Metastatic TNBC in IMMU-132-01| Laboratory Abnormality | TRODELVY
(n=108) |
|---|
All Grades
(%) | Grade 3-4
(%) |
|---|
| Hematology |
| Decreased hemoglobin | 93 | 6 |
| Decreased leukocyte count | 91 | 26 |
| Decreased neutrophil count | 82 | 32 |
| Increased activated partial thromboplastin time | 60 | 12 |
| Decreased platelet count | 30 | 2.8 |
| Chemistry |
| Increased alkaline phosphatase | 57 | 1.9 |
| Decreased calcium | 49 | 2.8 |
| Increased aspartate aminotransferase | 45 | 2.8 |
| Decreased albumin | 39 | 0.9 |
| Increased alanine aminotransferase | 35 | 1.9 |
| Increased glucose | 31 | 2.8 |
| Decreased phosphate | 29 | 5 |
| Decreased magnesium | 27 | 1.9 |
| Decreased sodium | 25 | 4.7 |
| Decreased potassium | 24 | 3.7 |
| Decreased glucose | 19 | 1.9 |
Locally Advanced or Metastatic HR-Positive, HER2-Negative Breast Cancer
TROPiCS-02
The safety of TRODELVY was evaluated in 268 patients with unresectable locally advanced or metastatic HR-positive, HER2-negative breast cancer whose disease has progressed after the following in any setting: a CDK 4/6 inhibitor, endocrine therapy, and a taxane; patients received at least two prior chemotherapies in the metastatic setting (one of which could be in the neoadjuvant or adjuvant setting if progression occurred within 12 months) who had received at least one dose of TRODELVY 10 mg/kg in TROPiCS-02. [see Clinical Studies (14.2)]. The median duration of treatment was 4.1 months (range: 0 to 63 months).
Serious adverse reactions occurred in 28% of patients who received TRODELVY. Serious adverse reactions in >1% included diarrhea (5%), febrile neutropenia (4.1%), neutropenia (3.0%), abdominal pain (2.2%), neutropenic colitis , and vomiting (1.9 each%), and colitis and pneumonia 1.5% each). Fatal adverse reactions occurred in 2.2% of patients who received TRODELVY including arrhythmia, COVID-19 pneumonia, pneumonia, nervous system disorder, pulmonary embolism, and septic shock (0.4% each).
Permanent discontinuation of TRODELVY due to an adverse reaction occurred in 6% of patients. Adverse reactions which resulted in permanent discontinuation of TRODELVY in ≥ 0.5% of patients included asthenia, general physical health deterioration, and neutropenia (0.7% each).
Dosage interruptions of TRODELVY due to an adverse reaction occurred in 66% of patients. Adverse reactions which required dosage interruption in ≥ 5% of patients included neutropenia (50%).
Dose reductions of TRODELVY due to an adverse reaction occurred in 33% of patients. Adverse reactions which required dose reductions in >5% of patients included neutropenia (16%) and diarrhea (8%).
G-CSF was used in 54% of patients who received TRODELVY.
The most common (≥ 25%) adverse reactions, including laboratory abnormalities, were decreased leukocyte count (88%), decreased neutrophil count (83%), decreased hemoglobin (73%), decreased lymphocyte count (65%), diarrhea (62%), fatigue (60%), nausea (59%), alopecia (48%), increased glucose (37%), constipation (34%), and decreased albumin (32%).
Tables 11 and 12 summarize adverse reactions and laboratory abnormalities in TROPiCS-02.
Table 11: Adverse Reactions in ≥ 10% of Patients with Metastatic HR+/HER2- Breast Cancer in TROPiCS-02 | TRODELVY
(n=268) | Single Agent Chemotherapy Single agent chemotherapy included one of the following single-agents: eribulin (n=130), vinorelbine (n=63), gemcitabine (n=56), or capecitabine (n=22).
(n=249) |
|---|
| Adverse Reaction Graded per NCI CTCAE V 5.0 | All Grades
% | Grade 3 - 4
% | All Grades
% | Grade 3 - 4
% |
|---|
| Gastrointestinal disorders |
| Diarrhea | 62 | 10 | 23 | 1.2 |
| Nausea | 59 | 1.1 | 35 | 2.8 |
| Constipation | 34 | 0.4 | 25 | 0 |
| Vomiting | 23 | 1.1 | 16 | 1.6 |
| Abdominal Pain | 20 | 3.7 | 14 | 0.8 |
| Dyspepsia Includes other related terms | 11 | 0 | 6 | 0 |
| General disorders and administration site conditions |
| Fatigue | 60 | 8 | 51 | 4.4 |
| Skin and subcutaneous tissue disorders |
| Alopecia | 48 | 0 | 19 | 0 |
| Pruritus | 12 | 0.4 | 2.4 | 0 |
| Metabolism and nutrition disorders |
| Decreased appetite | 21 | 1.5 | 21 | 0.8 |
| Hypokalemia | 10 | 1.5 | 3.6 | 0.4 |
| Respiratory, thoracic and mediastinal disorders |
| Dyspnea | 20 | 0 | 17 | 0 |
| Cough | 12 | 0 | 7 | 0.4 |
| Musculoskeletal and connective tissue disorders |
| Arthralgia | 15 | 0.7 | 12 | 0.4 |
| Nervous system disorders |
| Headache | 16 | 0.4 | 15 | 0.4 |
Other clinically significant adverse reactions in TROPiCS-02 (≤ 10%) include: hypotension, pain, and rhinorrhea (4.9% each), hypocalcemia (3.0%), nasal congestion (2.6%), skin hyperpigmentation, (2.6%), colitis or neutropenic colitis (2.2%), pneumonia (1.9%), proteinuria (1.1%), enteritis (0.4%).
Table 12: Laboratory Abnormalities in > 10% of Patients with Metastatic HR+/HER2- Breast Cancer in TROPiCS-02| Laboratory Abnormality | TRODELVY
(n=268) | Single Agent Chemotherapy
(n=249) |
|---|
| All Grades
(%) | Grade 3 - 4
(%) | All Grades
(%) | Grade 3 - 4
(%) |
|---|
| Hematology |
| Decreased leukocyte count | 88 | 38 | 73 | 26 |
| Decreased neutrophil count | 83 | 53 | 67 | 40 |
| Decreased hemoglobin | 73 | 8 | 59 | 5 |
| Decreased lymphocyte count | 65 | 21 | 47 | 14 |
| Decreased platelet count | 21 | 1.1 | 30 | 3.7 |
| Eosinophilia | 13 | 0 | 4.1 | 0 |
| Chemistry | |
| Increased glucose | 37 | 0 | 31 | 0 |
| Decreased albumin | 32 | 0 | 27 | 0.4 |
| Decreased creatinine clearance | 24 | 2.3 | 19 | 1.3 |
| Increased alkaline phosphatase | 23 | 0 | 23 | 0.8 |
| Decreased potassium | 22 | 3.4 | 12 | 0.4 |
| Increased alanine aminotransferase | 21 | 1.1 | 31 | 2.1 |
| Decreased sodium | 19 | 0.8 | 17 | 0.4 |
| Decreased magnesium | 18 | 0 | 15 | 0 |
| Decreased phosphate | 17 | 0 | 10 | 0 |
| Increased phosphate | 16 | 0 | 16 | 0 |
| Increased lactate dehydrogenase | 16 | 0 | 28 | 0 |
| Increased aspartate aminotransferase | 15 | 1.5 | 25 | 1.3 |
| Increased potassium | 14 | 1.9 | 9 | 0 |
UGT1A1 Inhibitors
Avoid administering UGT1A1 inhibitors with TRODELVY.
SN-38 is a UGT1A1 substrate. Concomitant administration of TRODELVY with inhibitors of UGT1A1 may increase the incidence of adverse reactions due to potential increase in systemic exposure to SN-38 [see Warnings and Precaution (5.5) and Clinical Pharmacology (12.3, 12.5)].
UGT1A1 Inducers
Avoid administering UGT1A1 inducers with TRODELVY.
SN-38 is a UGT1A1 substrate. Concomitant administration of TRODELVY with inducers of UGT1A1may reduce exposure to SN-38 [see Warnings and Precaution (5.5) and Clinical Pharmacology (12.3, 12.5)].
Risk Summary
Based on its mechanism of action, TRODELVY can cause teratogenicity and/or embryo-fetal lethality when administered to a pregnant woman. There are no available data in pregnant women to inform the drug-associated risk. TRODELVY contains a genotoxic component, SN-38, and is toxic to rapidly dividing cells [see Clinical Pharmacology (12.1) and Nonclinical Toxicology (13.1)]. Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 – 4% and 15 – 20%, respectively.
Data
Animal data
There were no reproductive and developmental toxicology studies conducted with sacituzumab govitecan-hziy.
Risk Summary
There is no information regarding the presence of sacituzumab govitecan-hziy or SN-38 in human milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment and for 1 month after the last dose of TRODELVY.
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to the initiation of TRODELVY.
Contraception
Females
TRODELVY can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)]. Advise females of reproductive potential to use effective contraception during treatment with TRODELVY and for 6 months after the last dose.
Males
Because of the potential for genotoxicity, advise male patients with female partners of reproductive potential to use effective contraception during treatment with TRODELVY and for 3 months after the last dose.
Infertility
Females
Based on findings in animals, TRODELVY may impair fertility in females of reproductive potential [see Nonclinical Toxicology (13.1)].
Cardiac electrophysiology
At the recommended dose, the maximum mean change from baseline was 9.7 msec (the upper bound of the two-sided 90% confidence interval is 16.8 msec). The increase in QTc was concentration dependent based on SN-38 concentrations.
Distribution
Sacituzumab govitecan-hziy steady state volume of distribution is 4.6 L.
Elimination
The median elimination half-life (t1/2) of sacituzumab govitecan-hziy is 6.5 days and free SN-38 is 22 hours. The terminal half-life (t1/2) of sacituzumab govitecan-hziy is 6.7 days (23%) and the apparent half-life (t1/2) of free SN-38 is 24 hours (50%). The clearance of sacituzumab govitecan-hziy is 0.13 L/h (20%).
Renal elimination is known to contribute minimally to the excretion of SN-38, the small molecule moiety of sacituzumab govitecan-hziy.
Metabolism
No metabolism studies with sacituzumab govitecan-hziy were conducted. SN-38 (the small molecule moiety of sacituzumab govitecan-hziy) is metabolized via UGT1A1. The glucuronide metabolite of SN-38 (SN-38G) was detectable in the serum of patients.
Specific Populations
No clinically significant differences in the pharmacokinetics of sacituzumab govitecan-hziy were observed based on: age (27 to 88 years), race (75% White, 8% Asian, or 5% Black), or CLcr 30 to 89 mL/min. There are no data on the pharmacokinetics of sacituzumab govitecan-hziy in patients with CLcr 15 to 29 mL/min, or end-stage renal disease (CLcr < 15 mL/min).
Patients with Hepatic Impairment
The exposure of sacituzumab govitecan-hziy for patients with mild hepatic impairment (total bilirubin ≤ ULN with AST > ULN, or bilirubin > 1 to ≤ 1.5 ULN with any AST) is within range of that of patients with normal hepatic function (total bilirubin and AST < ULN).
Sacituzumab govitecan-hziy and free SN-38 exposures are unknown in patients with moderate (total bilirubin > 1.5 to 3 × ULN) or severe (total bilirubin > 3 × ULN) hepatic impairment.
Drug Interaction Studies
No drug-drug interaction studies were conducted with sacituzumab govitecan-hziy or its components. Inhibitors or inducers of UGT1A1 may increase or decrease SN-38 exposure, respectively.
Single Agent in Previously Untreated, Unresectable Locally Advanced or Metastatic TNBC
ASCENT-03
The efficacy of TRODELVY was evaluated in ASCENT-03 (NCT05382299), a multicenter, open-label, randomized study that enrolled 558 patients with unresectable locally advanced or metastatic triple-negative breast cancer (TNBC) who had not received previous systemic therapy for advanced disease and who were not candidates for PD-1 or PD-L1 inhibitor therapy. Patients were enrolled if:
- Their tumors were PD-L1 negative (defined as having a tumor CPS < 10 using the IHC 22C3 assay), or
- Their tumors were PD-L1 positive (defined as having a CPS ≥ 10 using the IHC 22C3 assay) and they had received a PD-1 or PD-L1 inhibitor in the (neo)adjuvant setting or if they had a comorbidity precluding treatment with a PD-1 or PD-L1 inhibitor.
Patients were excluded if they had received anticancer treatment or surgery within the previous 6 months, had active central nervous system (CNS) metastases and ECOG performance status (PS) >1.
Randomization was stratified by de novo metastatic disease vs recurrent disease within 6 to 12 months from completion of treatment in the curative setting versus recurrent disease > 12 months from completion of treatment in the curative setting, and by geographic region (United States/Canada/Western Europe vs. Rest of World).
Patients were randomized (1:1) to one of the following treatment arms; all study medications were administered via intravenous infusion:
- TRODELVY 10 mg/kg on Days 1 and 8 of a 21-day cycle (n=279)
- nab-paclitaxel 100mg/m3 on Days 1, 8, and 15 of a 28-day cycle (n=110), paclitaxel 90 mg/m2 on days 1, 8, and 15 of a 28-day cycle (n=45), or gemcitabine 1000 mg/m2 and carboplatin AUC2 on Days 1 and 8 of a 21-day cycle (n=124)
Assessment of tumor status was performed every 6 weeks for the first year followed by every 12 weeks thereafter. Crossover to TRODELVY monotherapy was allowed at the time of disease progression and study treatment discontinuation. The primary efficacy outcome was progression-free survival (PFS) as assessed by Blinded Independent Central Review (BICR) per Response Evaluation Criteria in Solid Tumors (RECIST v1.1). Additional efficacy outcomes measures included overall survival (OS) and objective response rate (ORR).
The median age was 55 years (range: 23-86 years), 26% age 65 or older; 99.5% female; 64% White, 23% Asian, 4.5% American Indian or Alaskan Native, 3.0% Black; and 5.2% not specified , 72% non-Hispanic/non-Latino, 27% Hispanic/Latino, and 0.9% not reported; and 66% ECOG PS of 0 and 34% ECOG PS of 1. Of patients enrolled 31% had de novo disease, 21% had recurrent disease with a disease-free interval (DFI) of 6 to 12 months and 48% had recurrent disease with a DFI of > 12 months. Seventy-six percent of patients had visceral metastasis at baseline; and 5% had previously treated brain metastases. The majority of patients (99.5%) had tumor CPS < 10, and 0.4% had tumor CPS ≥ 10.
The trial demonstrated a statistically significant improvement in PFS. The OS data were immature and a total of 283 (51%) patients had died across both study arms.
Table 14 and Figure 1 summarize the efficacy results for ASCENT-03.
Table 14: Efficacy Results from ASCENT-03 | TRODELVY
N=279 | TPC
N=279 |
|---|
| BICR = Blinded Independent Central Review; CI = Confidence Interval; TPC = Treatment of physician’s choice (gemcitabine and carboplatin, paclitaxel, or nab-paclitaxel) |
| Progression-Free Survival by BICR |
| Number of patients with events (%) | 161 (58) | 188 (67) |
| Median PFS in months (95% CI) | 9.7
(8.1, 11.1) | 6.9
(5.6, 8.2) |
| Hazard ratio (95% CI) Hazard ratio based on the stratified Cox proportional hazards model | 0.62 (0.50, 0.77) |
| p-value 2-sided p-value based on stratified log-rank test | <0.0001 |
| Objective Response Rate by BICR |
| Patients with Measurable Disease at Baseline, N | 266 | 264 |
| ORR (95% CI) | 50%
(44, 56) | 47%
(41, 53) |
| Complete response rate | 7% | 5% |
| Partial response rate | 43% | 42% |
Figure 1: Kaplan Meier Plot of Progression Free Survival (PFS) by BICR in ASCENT-03
In Combination with Pembrolizumab in Previously Untreated, Unresectable Locally Advanced or Metastatic TNBC whose tumors express PD-L1
ASCENT-04
The efficacy of TRODELVY in combination with intravenous pembrolizumab was evaluated in ASCENT-04 (NCT5382286) a multicenter, open-label, randomized study that enrolled 443 patients with locally advanced or metastatic TNBC who had not received previous systemic therapy for advanced disease and whose tumors express PD-L1 (CPS ≥ 10)] according to the PD-L1 IHC 22C3 pharmDx assay. Patients may have received chemotherapy with or without a PD-1 or PD-L1 inhibitor and/or radiotherapy in early-stage TNBC: however, at least 6 months must have elapsed between the completion of systemic breast cancer therapy or surgery, and first local or distant recurrence. Patients with active autoimmune disease that required systemic therapy within 2 years or treatment or a medical condition that required immunosuppression were ineligible.
Randomization was stratified by de novo metastatic disease versus disease recurrence within 6 to 12 months from completion of treatment in the curative setting versus disease recurrence > 12 months from completion of treatment in the curative setting, by geographic region (United States/ Canada/ Western Europe versus rest of world), and prior exposure to PD-1 or PD-L1 inhibitor (yes versus no).
Patients were randomized (1:1) to receive one of the following treatment arms; all study medications were administered via intravenous infusion:
- TRODELVY 10 mg/kg on Day 1 and 8 of 21-day cycles in combination with pembrolizumab 200 mg on Day 1 of 21-day cycles (n=221)
- nab-paclitaxel 100 mg/m2 on Days 1, 8 and 15 every 28 days (n=69), paclitaxel 90 mg/m2 on Days 1, 8, and 15 every 28 days (n=45), or gemcitabine 1000 mg/m2 and carboplatin AUC 2 mg/mL/min on Days 1 and 8 every 21 days in combination with pembrolizumab 200 mg on Day 1 of 21-day cycles (n=108)
Assessment of tumor status was performed every 8 weeks for the first 18 months followed by every 12 weeks thereafter. Treatment beyond BICR-verified PD per RECIST was permitted if the patient was clinically stable and there was evidence of clinical benefit per the investigator. Crossover to TRODELVY monotherapy was allowed following disease progression and study treatment discontinuation. The primary efficacy outcome was progression-free survival (PFS) by BICR per RECIST v1.1. Additional efficacy outcomes measures included overall survival (OS) and objective response rate (ORR).
The median age was 55 years (range: 23-88 years); 26% age 65 years or older; 100% female; 58% White, 24% Asian, 6% American Indian or Alaska Native, 5% Black, and 6.5% not specified ; 29% Hispanic/Latino, 69% non-Hispanic/non-Latino and 2.0% not reported; and 70% ECOG PS of 0, 30% ECOG PS of 1, and 0.2% ECOG PS of 2. Of the patients enrolled 34% had de novo metastatic disease, 18% had recurrent disease with a DFI of 6 to 12 months and 48% had recurrent DFI of > 12 months. Sixty-five percent of patients had visceral metastasis at baseline; and 3% of patients had previously treated brain metastasis.
The trial demonstrated a statistically significant improvement in PFS. The OS data were immature and a total of 203 (46%) patients had died across both study arms.
Table 15 and Figure 2 summarize the efficacy results for ASCENT-04.
Table 15: Efficacy Results from ASCENT-04 | TRODELVY plus
pembrolizumab
N=221 | TPC plus pembrolizumab
N=222 |
|---|
| BICR = Blinded Independent Central Review; CI = Confidence Interval; TPC=Treatment of Physicians choice (nab-paclitaxel, paclitaxel, or gemcitabine with carboplatin) |
| Progression-Free Survival by BICR |
| Number of patients with events (%) | 109 (49) | 140 (63) |
| Median PFS in months (95% CI) | 11.2 (9.3, 16.7) | 7.8 (7.3, 9.3) |
| Hazard ratio (95% CI) Hazard ratio based on the stratified Cox proportional hazards model | 0.65 (0.51, 0.84) |
| p-value 2-sided p-value based on stratified log-rank test | 0.0009 |
| Objective Response Rate by BICR |
| Patients with Measurable Disease at Baseline, N | 210 | 213 |
| ORR (95% CI) | 61%
(55, 68) | 55%
(48, 62) |
| Complete response rate | 12% | 8% |
| Partial response rate | 50% | 47% |
Figure 2: Kaplan Meier Plot of Progression Free Survival (PFS) by BICR in ASCENT-04
Previously Treated, Locally Advanced or Metastatic TNBC
ASCENT
The efficacy of TRODELVY was evaluated in ASCENT (NCT02574455), a multicenter, open-label, randomized study conducted in 529 patients with unresectable locally advanced or metastatic TNBC who were previously treated with at least two prior lines of chemotherapy, one of which could be in the neoadjuvant setting provided progression occurred within a 12-month period. Patients were required to have received treatment with a taxane (unless contraindicated or not tolerated) in the neoadjuvant, adjuvant, or advanced setting. Patients with brain metastases were eligible to enroll up to a pre-defined maximum of 15% of patients. Magnetic resonance imaging (MRI) to determine brain metastases was required prior to enrollment for patients with known or suspected brain metastases. Patients with known Gilbert’s disease or bone-only disease were excluded.
Randomization was stratified by the number of prior chemotherapies (2-3 vs > 3), geographic region (North America vs Europe), and presence of brain metastasis (yes vs no).
Patients were randomized (1:1) to one of the following treatment arms:
- TRODELVY 10 mg/kg via intravenous infusion on Days 1 and 8 of a 21-day cycle (n=267)
- eribulin 1.23 or 1.4 mg/m2 via intravenous infusion on Days 1 and 8 of a 21-day cycle (n=139), capecitabine 1000-1250 mg/m2 orally twice daily on days 1-14 of a 21-day cycle (n=33), gemcitabine 800-1200 mg/m2 via intravenous infusion on Days 1, 8, and 15 of a 28 day cycle (n=38), or vinorelbine 25 mg/m2 via intravenous infusion on Day 1 weekly (n=52).
Assessment of tumor status was performed every 6 weeks for 36 weeks, then every 9 weeks thereafter. The primary efficacy outcome was progression-free survival (PFS) in patients without brain metastases at baseline (BICR per RECIST v1.1). Additional efficacy outcome measures included PFS for the full population and overall survival (OS).
The median age was 54 years (range: 27 to 82 years); 19% age 65 or older; 99.6% female; 79% White, 12% Black, 4.2% Asian and 5% not specified; 43% ECOG PS 0 and 57% ECOG PS 1; and 8.1% with BRCA1/BRCA2 mutations. Forty-two percent of patients had hepatic metastases, and 12 had previously treated, stable brain metastases. Twenty-nine percent received prior PD-1/PD-L1 therapy and 13% in the TRODELVY arm received only 1 prior line of systemic therapy in the metastatic setting.
The study demonstrated a statistically significant PFS. Efficacy results for the subgroup of patients who had received only 1 prior line of systemic therapy in the metastatic setting (in addition to having disease recurrence or progression within 12 months of neoadjuvant/adjuvant systemic therapy) were consistent with those who had received at least two prior lines in the metastatic setting.
Table 16, Figure 3 and Figure 4 summarize the efficacy results for ASCENT.
Table 16: Efficacy Results from ASCENT | All Randomized Patients |
|---|
| TRODELVY
n=267 | Single Agent Chemotherapy
n=262 |
|---|
| CI = Confidence Interval |
| Progression-Free Survival PFS is defined as the time from the date of randomization to the date of the first radiological disease progression or death due to any cause, whichever comes first. per BICR |
| Disease Progression or Death (%) | 190 (71%) | 171 (65%) |
| Median PFS in months (95% CI) | 4.8
(4.1, 5.8) | 1.7
(1.5, 2.5) |
| Hazard ratio Stratified log-rank test adjusted for stratification factors: number of prior chemotherapies, presence of known brain metastases at study entry, and region. (95% CI) | 0.43 (0.35, 0.54) |
| p-value | <0.0001 |
| Overall Survival |
| Deaths (%) | 179 (67%) | 206 (79%) |
| Median OS in months (95% CI) | 11.8
(10.5, 13.8) | 6.9
(5.9, 7.6) |
| Hazard ratio (95% CI) | 0.51 (0.41, 0.62) |
| p-value | <0.0001 |
Figure 3: Kaplan-Meier Plot of PFS by BICR (All Randomized Patients) in ASCENT
Figure 4: Kaplan-Meier Plot of OS (All Randomized Patients) in ASCENT
An exploratory analysis of PFS in patients with previously treated, stable brain metastases showed a stratified HR of 0.65 (95% CI: 0.35, 1.22). The median PFS in the TRODELVY arm was 2.8 months (95% CI: 1.5, 3.9) and the median PFS with single agent chemotherapy was 1.6 months (95% CI: 1.3, 2.9). Exploratory OS analysis in the same population showed a stratified HR of 0.87 (95% CI: 0.47, 1.63). The median OS in the TRODELVY arm was 6.8 months (95% CI: 4.7, 14.1) and the median OS with single agent chemotherapy was 7.4 months (95% CI: 4.7, 11.1).
IMMU-132-01
The efficacy of TRODELVY was evaluated in IMMU-132-01 (NCT01631552) a multicenter, single-arm, study that enrolled 108 patients with metastatic TNBC who had received at least two prior anticancer therapies for metastatic disease. Patients with bulky disease, defined as a mass > 7 cm and patients with known Gilbert’s disease were ineligible. Patients with treated brain metastases not receiving high dose steroids (> 20 mg prednisone or equivalent) for at least four weeks were eligible.
Patients received TRODELVY 10 mg/kg via intravenous infusion on Days 1 and 8 of a 21-day cycle.
Assessment of tumor status was performed every 8 weeks, with confirmatory scans obtained 4-6 weeks after an initial partial or complete response. The primary efficacy outcome measure was overall response rate (ORR) per RECIST v1.1. Duration of response (DoR) per RECIST v 1.1 was an additional efficacy outcome.
The median age was 55 years (range: 31 to 80 years); 13% age 65 years or older; 99% female; 76% White, 7% Black, 2.8% Asian, and 0.9% American Indian or Alaska Native; 7% Hispanic/Latino and 93% non-Hispanic/non-Latino; 29% EGOC PS 0 and 71% ECOG PS 1; and 11% had Stage IV disease at the time of initial diagnosis. Seventy-six percent had visceral disease, 42% had hepatic metastases, 56% had lung/pleura metastases, and 2% had brain metastases. The median number of prior systemic therapies received in the metastatic setting was 3 (range: 2 to 10). Prior chemotherapies in the metastatic setting included carboplatin or cisplatin (69%), gemcitabine (55%), paclitaxel or docetaxel (53%), capecitabine (51%), eribulin (45%), doxorubicin (24%), vinorelbine (16%), cyclophosphamide (19%), and ixabepilone (8%). Ninety-eight percent had received prior taxanes and 86% had received prior anthracyclines either in the (neo)adjuvant or metastatic setting.
Table 17 summarizes the efficacy results.
Table 17: Efficacy results for patients with Metastatic TNBC in IMMU-132-01 | TRODELVY
(N=108) |
|---|
| CI: confidence interval |
| +: denotes ongoing |
| Overall Response Rate Investigator assessment | |
| ORR (95% CI) | 33.3% (24.6, 43.1) |
| Complete response | 2.8% |
| Partial response | 30.6% |
| Response duration | |
| Number of responders | 36 |
| Median, Months (95% CI) | 7.7 (4.9, 10.8) |
| Range, Months | 1.9+, 30.4+ |
| % with duration ≥6 months | 55.6% |
| % with duration ≥12 months | 16.7% |
TROPiCS-02 Study
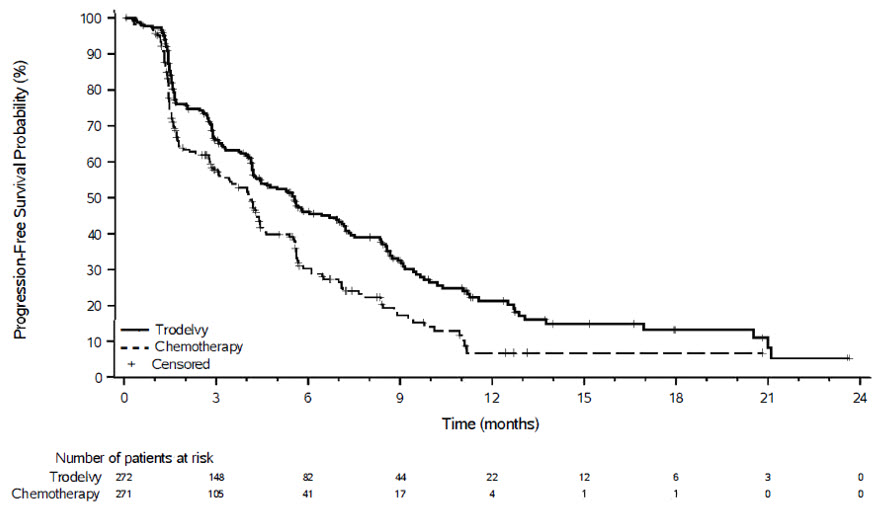
The efficacy of TRODELVY was evaluated in TROPiCS-02 (NCT 03901339), a multicenter, open label, randomized study conducted in 543 patients with unresectable locally advanced or metastatic HR-positive, HER2-negative (IHC 0, IHC 1+ or IHC 2+/ISH–) breast cancer whose disease has progressed after the following in any setting: a CDK 4/6 inhibitor, endocrine therapy, and a taxane. Patients must have received at least two prior chemotherapies in the metastatic setting (one of which could be in the neoadjuvant or adjuvant setting if recurrence occurred within 12 months).
Randomization was stratified by prior chemotherapy regimens for metastatic disease (2 vs. 3-4), visceral metastasis (Yes or No), and endocrine therapy in the metastatic setting for at least 6 months (Yes or No).
Patients were randomized (1:1) to receive one of the following treatment arms:
- TRODELVY 10 mg/kg via an intravenous infusion on Days 1 and 8 of a 21-day cycle (n=272)
- eribulin 1.23 or 1.4 mg/m2 via intravenous infusion on Days 1 and 8 of a 21-day cycle (n=130), vinorelbine 25 mg/m2 via intravenous infusion on day 1 of a weekly cycle (n=63), gemcitabine 800 to 1200 mg/m2 via intravenous infusion on Days 1, 8, and 15 of a 28-day cycle (n=56), or capecitabine 1000 to 1250 mg/m2 orally twice daily on days 1-14 of a 21-day cycle (n=22).
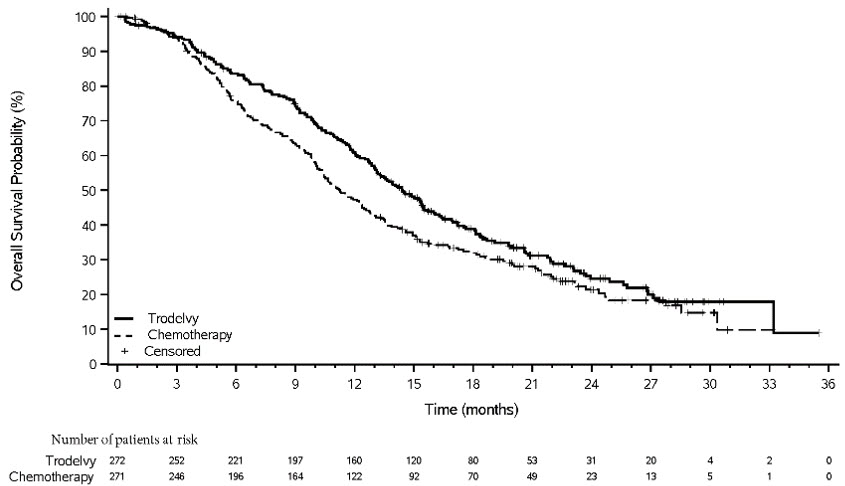
Assessment of tumor status was performed every 6 weeks for the first 54 weeks followed by every 12 weeks thereafter. Treatment beyond RECIST-defined disease progression was permitted if the patient was clinically stable and considered by the investigator to be deriving clinical benefit. The primary efficacy outcome measure was PFS by BICR per RECIST v1.1. Additional efficacy measures included OS, ORR by BICR, and DOR by BICR.
The median age was 56 years (range: 27–86 years); 26% of patients were 65 years or older; 99% female; 67% White, 3.9% Black, 2.9% Asian, and 26% unknown race; and 45% ECOG PS 0 and 55% ECOG PS 1. Ninety-five percent of patients had visceral metastases. Patients received a median of 7 (range: 3 to 17) prior systemic regimens in any setting and 3 (range: 0 to 8) prior systemic chemotherapy regimens in the metastatic setting. Approximately 42% of patients had 2 prior chemotherapy regimens for treatment of metastatic disease compared to 58% of patients who had 3 to 4 prior chemotherapy regimens. Eighty-six percent of patients received endocrine therapy in the metastatic setting for ³ 6 months.
The trial demonstrated a statistically significant improvement in PFS and OS.
Table 18, Figure 5 and Figure 6 summarize the results of TROPiCS-02.
Table 18: Efficacy Results from TROPiCS-02 | All Randomized Patients |
|---|
| TRODELVY
n=272 | Single Agent Chemotherapy
n=271 |
|---|
| Progression-Free Survival by BICR PFS is defined as the time from the date of randomization to the date of the first radiological disease progression or death due to any cause, whichever comes first. |
Median PFS in months
(95% CI) | 5.5
(4.2, 7.0) | 4.0
(3.1, 4.4) |
| Hazard ratio (95% CI) | 0.661 (0.529, 0.826) |
| p-value Stratified log-rank test adjusted for stratification factors: prior chemotherapy regimens for metastatic disease (2 vs. 3-4), visceral metastasis (Y/N), and endocrine therapy in the metastatic setting for at least 6 months (Yes or No).
BICR = Blinded Independent Central Review; CI = Confidence Interval | 0.0003 |
| Overall Survival Second interim OS analysis (conducted when 390 OS events were observed) |
Median OS in months
(95% CI) | 14.4
(13.0, 15.7) | 11.2
(10.1, 12.7) |
| Hazard ratio (95% CI) | 0.789 (0.646, 0.964) |
| p-value | 0.0200 |
| Objective Response Rate Objective Response Rate and Duration of response were based on the time of Second interim OS analysis by BICR |
| Response Rate, % (95% CI) | 21.0 (16.3, 26.3) | 14.0 (10.1, 18.7) |
| Odds ratio (95% CI) | 1.625 (1.034, 2.555) |
| p-value | 0.0348 |
| Duration of Response (DOR) by BICR |
Median DOR in months
(95% CI) | 8.1
(6.7, 9.1) | 5.6
(3.8, 7.9) |
Figure 5: Kaplan-Meier Plot of PFS by BICR in TROPiCS-02
Figure 6: Kaplan-Meier Plot of OS in TROPiCS-02
Neutropenia
Advise patients of the risk of neutropenia. Instruct patients to immediately contact their healthcare provider if they experience fever, chills, or other signs of infection [see Warnings and Precautions (5.1)].
Diarrhea
Advise patients of the risk of diarrhea. Instruct patients to immediately contact their healthcare provider if they experience diarrhea for the first time during treatment; black or bloody stools; symptoms of dehydration such as lightheadedness, dizziness, or faintness; inability to take fluids by mouth due to nausea or vomiting; or inability to get diarrhea under control within 24 hours [see Warnings and Precautions (5.2)].
Hypersensitivity and Infusion-Related Reactions
Inform patients of the risk of serious infusion reactions and anaphylaxis. Instruct patients to immediately contact their healthcare provider if they experience facial, lip, tongue, or throat swelling, urticaria, difficulty breathing, lightheadedness, dizziness, chills, rigors, wheezing, pruritus, flushing, rash, hypotension, or fever that occur during or at any time following the infusion [see Warnings and Precautions (5.3)].
Nausea/Vomiting
Advise patients of the risk of nausea and vomiting. Premedication according to established guidelines with a two or three drug regimen for prevention of chemotherapy-induced nausea and vomiting (CINV) is also recommended. Additional antiemetics, sedatives, and other supportive measures may also be employed as clinically indicated. All patients should receive take-home medications for preventing and treating delayed nausea and vomiting, with clear instructions. Instruct patients to immediately contact their healthcare provider if they experience uncontrolled nausea or vomiting [see Warnings and Precautions (5.4)].
Embryo-Fetal Toxicity
Advise female patients to contact their healthcare provider if they are pregnant or become pregnant. Inform female patients of the risk to a fetus and potential loss of the pregnancy [see Use in Specific Populations (8.1)].
Contraception
Advise female patients of reproductive potential to use effective contraception during treatment and for 6 months after the last dose of TRODELVY [see Use in Specific Populations (8.3)].
Advise male patients with female partners of reproductive potential to use effective contraception during treatment and for 3 months after the last dose of TRODELVY [see Use in Specific Populations (8.3)].
Lactation
Advise women not to breastfeed during treatment and for 1 month after the last dose of TRODELVY [see Use in Specific Populations (8.2)].
Infertility
Advise females of reproductive potential that TRODELVY may impair fertility [see Use in Specific Populations (8.3)].
Manufactured by:
Gilead Sciences, Inc.
333 Lakeside Dr.
Foster City, CA 94404, USA
U.S. License No. 2258