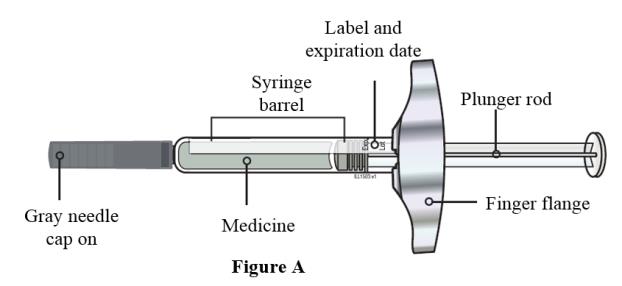
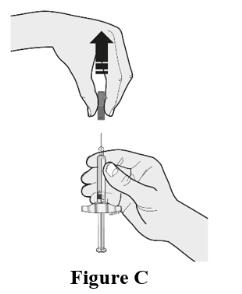
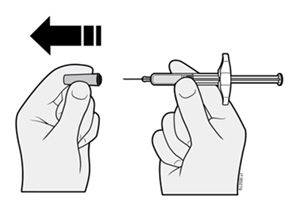
Choose the first syringe. Pull the gray needle cap straight off and away from your body when you are ready to inject. See Figure H.
- Do not put the gray needle cap back onto the syringe.
- Do not leave the cap off for more than 5 minutes as this can dry out the solution.
- The prefilled syringe may contain air bubbles. Do not try to push air bubbles out as it is normal to see air bubbles.
Step 3: Inject EVENITY
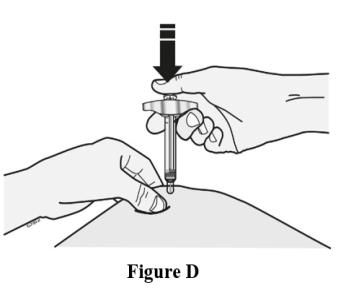
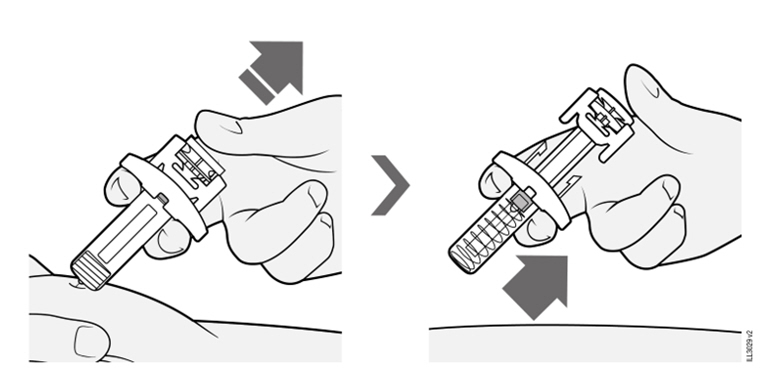
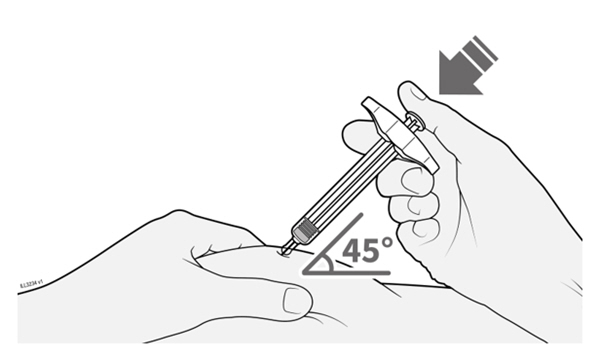
Pinch the skin around the injection site before injecting. Insert the needle into the pinched skin at or about a 45-degree angle. Insert needle and inject all the liquid subcutaneously. Do not administer into muscle or blood vessel. See Figure I.
When done, gently lift the syringe off of the skin.
Step 4: Syringe and Needle Cap Disposal
Immediately dispose of the syringe and needle cap in the nearest sharps container.
Important: Repeat all steps with the second syringe to inject the full dose.
Hypersensitivity Reactions
Across both trials, hypersensitivity reactions were reported in 364 (6.5%) women in the EVENITY group and 365 (6.5%) women in the control group. Reported reactions included angioedema (3 [< 0.1%] women in the EVENITY group vs. 3 [< 0.1%] women in the control group), erythema multiforme (1 [< 0.1%] woman in the EVENITY group vs. no woman in the control group), dermatitis (32 [0.6%] women in the EVENITY group vs. 42 [0.8%] women in the control group), rash (60 [1.1%] women in the EVENITY group vs. 53 [0.9%] women in the control group), and urticaria (23 [0.4%] women in the EVENITY group vs. 27 [0.5%] women in the control group). Although angioedema, dermatitis and urticaria were not reported at a higher incidence with EVENITY than control, there were cases of angioedema, dermatitis and urticaria that were determined to be related to EVENITY use [see Contraindications (4) and Warnings and Precautions (5.2)].
Hypocalcemia
Across both trials, adverse events of hypocalcemia occurred in 2 EVENITY-treated women and in 1 woman in the control group. Decreases in albumin-adjusted serum calcium to below the lower limit of the reference range (8.3 mg/dL) were reported in 14 (0.2%) women in the EVENITY group and 10 (0.2%) women in the control group. No patient receiving EVENITY developed serum calcium less than 7.5 mg/dL. The nadir in albumin-adjusted serum calcium occurred by month 1 after EVENITY dosing in patients with normal renal function [see Contraindications (4) and Warnings and Precautions (5.3)].
Injection Site Reactions
Across both trials, injection site reactions occurred in 278 (4.9%) women in the EVENITY group and 157 (2.8%) women in the control group. The most common injection site reactions were pain (94 [1.7%] women in the EVENITY group; 70 [1.3%] women in the control group) and erythema (80 [1.4%] women in the EVENITY group and 14 [0.3%] women in the control group). Injection site reactions resulted in discontinuation of treatment in 7 (0.1%) EVENITY-treated patients and 3 (< 0.1%) patients in the control group.
Osteonecrosis of the Jaw
Across both trials, osteonecrosis of the jaw occurred in one patient during treatment with EVENITY [see Warnings and Precautions (5.4)].
Atypical Subtrochanteric and Diaphyseal Fractures
Across both trials, atypical femoral fracture occurred in one patient during treatment with EVENITY [see Warnings and Precautions (5.5)].
Risk Summary
EVENITY is not indicated for use in women of reproductive potential. In animal reproduction studies, weekly administration of romosozumab-aqqg to pregnant rats during the period of organogenesis at exposures greater than 31 times the clinical exposure produced skeletal abnormalities in the offspring. Administration of romosozumab-aqqg to rats prior to mating and through to the end of lactation produced minimal to slight decreases in femoral bone mineral density and/or cortical circumferences in the offspring at 1.4 to 54 times the expected exposure in humans [see Data].
Data
Animal Data
Reproductive and developmental effects of romosozumab-aqqg were assessed in the rat in a preliminary and definitive embryo-fetal development study, a combined fertility and embryo-development study, and a pre and postnatal development study.
Skeletal malformations including syndactyly and polydactyly occurred in 1 out of 75 litters across all rat reproductive toxicity studies, in the litter of a dam given weekly subcutaneous romosozumab-aqqg doses of 300 mg/kg (equivalent to at least 31 times the clinical exposure observed in humans following a monthly subcutaneous dose of 210 mg, based on area under the concentration-time curve [AUC] comparison).
In the offspring of female rats given weekly romosozumab-aqqg doses from 6 weeks before cohabitation through mating and lactation, femoral periosteal and endocortical circumferences were slightly decreased at 10, 60, and 300 mg/kg (equivalent to 1.4, 18, and 54 times the clinical exposure following a monthly subcutaneous dose of 210 mg, based on AUC comparison). Cortical thickness was increased at 300 mg/kg (equivalent to 54 times expected clinical exposure). Femoral metaphyseal bone mineral density was slightly decreased at 60 and 300 mg/kg (equivalent to 18 and 54 times expected clinical exposure).
Risk Summary
EVENITY is not indicated for use in women of reproductive potential. In animal studies where pregnant rats were given weekly doses of romosozumab-aqqg from 6 weeks before cohabitation through mating and lactation at 10, 60, or 300 mg/kg (equivalent to 1.4, 18 or 54 times the clinical exposure following a monthly subcutaneous dose of 210 mg, based on AUC comparison), romosozumab-aqqg was dose-dependently present in the serum of offspring on postnatal day 21 at 0.01 to 2.4 times maternal exposure due to gestational and/or lactational exposure.
Absorption
The median time to maximum romosozumab-aqqg concentration (Tmax) is 5 days (range: 2 to 7 days).
Distribution
The estimated volume of distribution at steady-state is approximately 3.92 L.
Elimination
Romosozumab-aqqg exhibited nonlinear pharmacokinetics with the clearance of romosozumab-aqqg decreasing as the dose increased. The estimated mean systemic clearance (CL/F) of romosozumab-aqqg was 0.38 mL/hr/kg, following a single subcutaneous administration of 3 mg/kg (the approved recommended dosage for a 70 kg woman). The mean effective t1/2 was 12.8 days after 3 doses of 3 mg/kg (the approved recommended dosage for a 70 kg woman) every 4 weeks.
Metabolism
The metabolic pathway of romosozumab-aqqg has not been characterized. As a humanized IgG2 monoclonal antibody, romosozumab-aqqg is expected to be degraded into small peptides and amino acids via catabolic pathways in a manner similar to endogenous IgG.
Specific Populations
No clinically significant differences in the pharmacokinetics of romosozumab-aqqg were observed based on age (20-89 years), sex, race, disease state (low bone mass or osteoporosis), prior exposure to alendronate, or renal impairment including end-stage renal disease (ESRD) requiring dialysis. The effect of ESRD not requiring dialysis on the pharmacokinetics of romosozumab-aqqg is unknown.
Body Weight
The exposure of romosozumab-aqqg decreases with increasing body weight.
Anti-Product Antibody Formation Affecting Pharmacokinetics
Development of anti-romosozumab-aqqg antibodies was associated with reduced serum romosozumab-aqqg concentrations. The presence of anti-romosozumab-aqqg antibodies led to decreased mean romosozumab-aqqg concentrations up to 22%. The presence of neutralizing antibodies led to decreased mean romosozumab-aqqg concentrations up to 63%. These anti-romosozumab-aqqg antibody-associated pharmacokinetic changes were not identified to be clinically significant.
Carcinogenicity
In a rat carcinogenicity study, once-weekly romosozumab-aqqg doses of 3, 10 or 50 mg/kg were administered by subcutaneous injection to Sprague-Dawley rats from 8 weeks up to 98 weeks of age, resulting in systemic exposures that were up to 19 times the systemic exposure observed in humans following a monthly subcutaneous dose of 210 mg EVENITY (based on AUC comparison). Romosozumab-aqqg caused a dose-dependent increase in bone mass with trabecular and cortical bone thickening at all doses. There were no effects of romosozumab-aqqg on mortality and romosozumab-aqqg did not cause significant increases in tumor incidence in male or female rats.
Mutagenicity
Mutagenesis has not been evaluated, as monoclonal antibodies are not expected to alter DNA or chromosomes.
Impairment of Fertility
No effects on fertility were observed in male and female rats given subcutaneous romosozumab-aqqg doses up to 300 mg/kg (up to 54 times the systemic exposure observed in humans following a monthly subcutaneous dose of 210 mg EVENITY, based on AUC comparison). No effects were noted in reproductive organs in rats and cynomolgus monkeys dosed subcutaneously for 6 months with weekly doses up to 100 mg/kg (exposures up to 37 and 90 times, respectively, the systemic exposure observed in humans administered monthly subcutaneous doses of 210 mg based on AUC comparison).
Effect on Fractures
EVENITY significantly reduced the incidence of new vertebral fractures through month 12 compared to placebo. In addition, the significant reduction in fracture risk persisted through the second year in women who received EVENITY during the first year and transitioned to denosumab compared to those who transitioned from placebo to denosumab (see Table 2).
Table 2. Effect of EVENITY on the Incidence and Risk of Fractures in Study 1 | Proportion of Women with Fractures | Absolute Risk Reduction
(%)
(95% CI)Absolute and relative risk reduction are based on the Mantel-Haenszel method adjusting for age and prevalent vertebral fracture strata. | Relative Risk Reduction
(%)
(95% CI) | p-value P-value is based on logistic regression model adjusting for age and prevalent vertebral fracture strata. |
|---|
| At Month 12 | Placebo
(N = 3591) | EVENITY
(N = 3589) | | | |
|---|
| N = Number of subjects randomized |
| New vertebral fracture | 1.8% | 0.5% | 1.3
(0.8, 1.8) | 73
(53, 84) | < 0.001 |
| At Month 24 | Placebo Followed by Denosumab
(N = 3591) | EVENITY Followed by Denosumab
(N = 3589) | | | |
| New vertebral fracture | 2.5% | 0.6% | 1.9
(1.3, 2.5) | 75
(60, 84) | < 0.001 |
EVENITY significantly reduced the incidence of clinical fracture (a composite endpoint of symptomatic vertebral fracture and nonvertebral fracture) at 12 months. However, 88% of these clinical fractures were nonvertebral fractures and the incidence of nonvertebral fractures was not statistically significantly different when comparing EVENITY-treated women to placebo-treated women at month 12 or month 24.
Effect on Bone Mineral Density (BMD)
EVENITY significantly increased BMD at the lumbar spine, total hip, and femoral neck compared with placebo at month 12. The treatment differences in BMD were 12.7% at the lumbar spine, 5.8% at the total hip, and 5.2% at the femoral neck.
Following the transition from EVENITY to denosumab at month 12, BMD continued to increase through month 24. In patients who transitioned from placebo to denosumab, BMD also increased with denosumab use. The differences in BMD achieved at month 12 between EVENITY and placebo patients were overall maintained at month 24, when comparing patients who transitioned from EVENITY to denosumab to those who transitioned from placebo to denosumab. There was no evidence of differences in effects on BMD at the lumbar spine or total hip across subgroups defined by baseline age, baseline BMD, or geographic region.
After EVENITY discontinuation, BMD returns to approximately baseline levels within 12 months in the absence of follow-on anti-resorptive therapy [see Indications and Usage (1.2)].
Bone Histology and Histomorphometry
A total of 154 transiliac crest bone biopsy specimens were obtained from 139 postmenopausal women with osteoporosis at month 2, month 12, and/or month 24. All of these biopsies were adequate for qualitative histology and 138 (90%) were adequate for full quantitative histomorphometry assessment. Qualitative histology assessments from women treated with EVENITY showed normal bone architecture and quality at all time points. There was no evidence of woven bone, mineralization defects, or marrow fibrosis.
Histomorphometry assessments on biopsies at months 2 and 12 compared the effect of EVENITY with placebo (15 specimens at month 2 and 39 specimens at month 12 in the EVENITY group, 14 specimens at month 2 and 31 specimens at month 12 in the placebo group). At month 2 in women treated with EVENITY, histomorphometric indices of bone formation at trabecular and endocortical surfaces were increased. These effects on bone formation were accompanied by a decrease in indices of bone resorption. At month 12, both bone formation and resorption indices were decreased with EVENITY, while bone volume, and trabecular and cortical thickness were increased.
Study 2 (NCT01631214) was a randomized, double-blind, alendronate-controlled study of postmenopausal women aged 55 to 90 years (mean age of 74 years) with BMD T-score less than or equal to −2.5 at the total hip or femoral neck and either one moderate or severe vertebral fracture or two mild vertebral fractures, or BMD T-score less than or equal to -2.0 at the total hip or femoral neck and either two moderate or severe vertebral fractures or a history of a proximal femur fracture. Women were randomized (1:1) to receive either monthly subcutaneous injections of EVENITY (N = 2046) or oral alendronate 70 mg weekly (N = 2047) for 12 months, with 500 to 1000mg calcium and 600 to 800 international units vitamin D supplementation daily. After the 12-month treatment period, women in both arms transitioned to open-label alendronate 70 mg weekly while remaining blinded to their initial treatment.
This was an event-driven trial. The two primary efficacy endpoints were the incidence of morphometric vertebral fracture at 24 months and time to the first clinical fracture through the primary analysis period, which ended when at least 330 subjects had a clinical fracture and all subjects had completed the 24-month visit. Clinical fracture was a composite endpoint of nonvertebral fracture and symptomatic vertebral fracture.
Effect on Fractures
EVENITY significantly reduced the incidence of new vertebral fracture at 24 months (see Table 3).
Table 3. Effect of EVENITY on the Incidence of New Vertebral Fractures in Study 2 | Proportion of Women with Fracture (%) | Risk Reduction | p-value P-value is based on logistic regression model for new vertebral fracture) adjusting for age strata, baseline total hip BMD T-score, and presence of severe vertebral fracture at baseline. |
|---|
| Alendronate Alone
(N = 2047) | EVENITY Followed by Alendronate
(N = 2046) | Absolute Risk Reduction
(%)
(95% CI)Absolute and relative risk reductions are based on the Mantel-Haenszel method adjusting for age strata, baseline total hip BMD T-score (≤ -2.5, > -2.5), and presence of severe vertebral fracture at baseline. | Relative Risk Reduction (%)
(95% CI) | |
|---|
| N = Number of subjects randomized |
| New vertebral fracture through Month 24 | 8.0% | 4.1% | 4.0 (2.5, 5.6) | 50 (34, 62) | < 0.001 |
EVENITY significantly reduced the risk of clinical fracture through the end of the primary analysis period (see Table 4). This was an event-driven trial and the duration of follow-up varied across subjects. The median duration of subject follow-up for the primary analysis period was 33 months. Subjects with nonvertebral fracture comprised 83% of the subjects with clinical fracture during the primary analysis period.
Table 4. Effect of EVENITY on the Risk of Clinical Fractures in Study 2 | Proportion of Women with Fracture (%) % = number of subjects who had a clinical fracture through the primary analysis period/N*100%; the duration of follow-up varied across subjects. | Hazard Ratio
(95% CI)Hazard ratio and P-value are based on Cox proportional hazards model adjusting for age strata, baseline total hip BMD T-score, and presence of severe vertebral fracture at baseline. | p-value |
|---|
| Alendronate Alone
(N = 2047) | EVENITY Followed by Alendronate
(N = 2046) |
|---|
| N = Number of subjects randomized |
| Clinical fracture through primary analysis period Primary analysis period ended when clinical fracture events were confirmed for at least 330 subjects and all subjects completed the month 24 study visit. The median duration of follow-up for the primary analysis period was 33 months. | 13.0% | 9.7% | 0.73 (0.61, 0.88) | < 0.001 |
EVENITY followed by alendronate also significantly reduced the risk of nonvertebral fracture through the primary analysis period (with a median follow-up of 33 months), with a hazard ratio of 0.81 (95% CI: 0.66, 0.99; p = 0.04) compared to alendronate alone.
Effect on Bone Mineral Density (BMD)
EVENITY significantly increased BMD at the lumbar spine, total hip, and femoral neck compared with alendronate at month 12. The treatment differences in BMD were 8.7% at the lumbar spine, 3.3% at the total hip, and 3.2% at the femoral neck.
Twelve months of treatment with EVENITY followed by 12 months of treatment with alendronate significantly increased BMD compared with alendronate alone. The BMD increase with EVENITY over alendronate observed at month 12 was maintained at month 24. The treatment differences in BMD at month 24 were 8.1% at the lumbar spine, 3.8% at the total hip, and 3.8% at the femoral neck.
There was no evidence of differences in effects on BMD at the lumbar spine or total hip across subgroups defined by baseline age, baseline BMD, or geographic region.
Major Adverse Cardiac Events
Advise patients to seek immediate medical attention if they experience signs or symptoms of a myocardial infarction or stroke [see Boxed Warning, Warnings and Precautions (5.1) and Adverse Reactions (6.1)].
Hypersensitivity Reactions
Advise patients to seek immediate medical attention if they experience signs or symptoms of a hypersensitivity reaction including angioedema, erythema multiforme, dermatitis, rash, and urticaria [see Warnings and Precautions (5.2) and Adverse Reactions (6.1)].
Calcium and Vitamin D Supplements to Prevent Hypocalcemia
Advise patients to take calcium and vitamin D supplements daily to reduce the risk of hypocalcemia. Advise patients to seek immediate medical attention for symptoms of hypocalcemia [see Dosage and Administration (2.1), Warnings and Precautions (5.3) and Adverse Reactions (6.1)].
Osteonecrosis of the Jaw
Advise patients to practice good oral hygiene during treatment with EVENITY and tell their dentist that they are receiving EVENITY before having dental work. [see Warnings and Precautions (5.4) and Adverse Reactions (6.1)].
Atypical Femoral Fracture
Advise patients to report signs and symptoms that could be consistent with impending atypical femoral fracture including new or unusual thigh, hip, or groin pain [see Warnings and Precautions (5.5) and Adverse Reactions (6.1)].
EVENITY® (romosozumab-aqqg)
Manufactured by:
Amgen Inc.
One Amgen Center Drive
Thousand Oaks, California 91320-1799
U.S. License No. 1080
Patent: http://pat.amgen.com/EVENITY/
© 2019, 2020, 2024, 2026 Amgen Inc. All rights reserved.
1xxxxxx- v6