Other
SERIOUS INFECTIONS
Patients treated with SIMPONI are at increased risk for developing serious infections that may lead to hospitalization or death [see Warnings and Precautions (5.1)] . Most patients who developed these infections were taking concomitant immunosuppressants such as methotrexate or corticosteroids.
Discontinue SIMPONI if a patient develops a serious infection.
Reported infections with TNF blockers, of which SIMPONI is a member, include:
- Active tuberculosis, including reactivation of latent tuberculosis. Patients with tuberculosis have frequently presented with disseminated or extrapulmonary disease. Test patients for latent tuberculosis before SIMPONI use and during therapy. Initiate treatment for latent TB prior to SIMPONI use.
- Invasive fungal infections including histoplasmosis, coccidioidomycosis, candidiasis, aspergillosis, blastomycosis, and pneumocystosis. Patients with histoplasmosis or other invasive fungal infections may present with disseminated, rather than localized, disease. Antigen and antibody testing for histoplasmosis may be negative in some patients with active infection. Consider empiric antifungal therapy in patients at risk for invasive fungal infections who develop severe systemic illness.
- Bacterial, viral, and other infections due to opportunistic pathogens, including Legionella and Listeria.
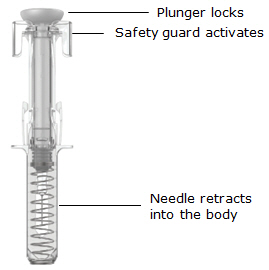
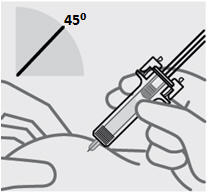
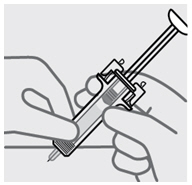
- Adult and pediatric patients 12 years of age and older may self-inject with SIMPONI prefilled syringe.
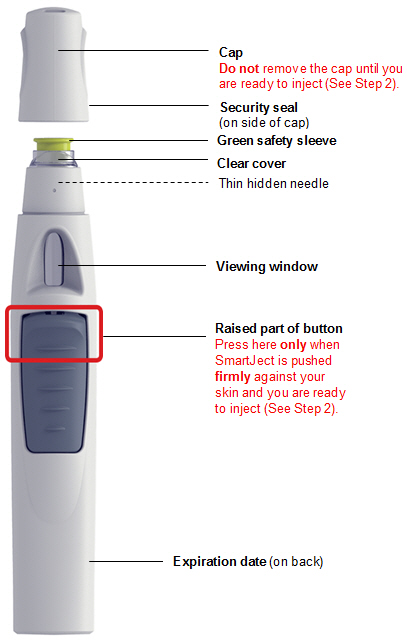
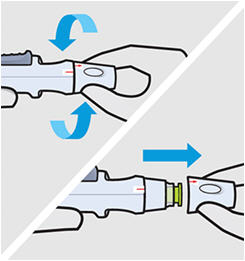
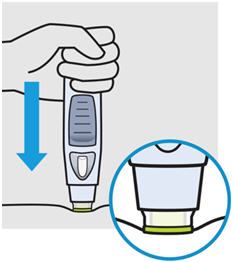
- Adult patients may self-inject with SIMPONI SmartJect® autoinjector.
- Use of the SmartJect® autoinjector for pediatric self-administration has not been evaluated.
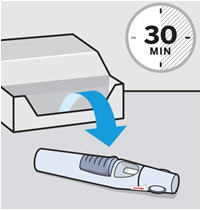
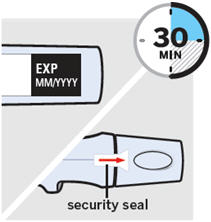
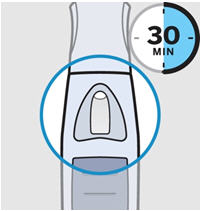
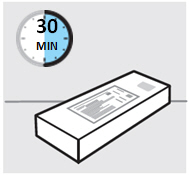
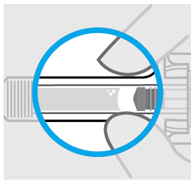
- Prior to use, remove the prefilled syringe or the prefilled SmartJect® autoinjector from the refrigerator and allow SIMPONI to sit at room temperature outside of the carton for at least 30 minutes and out of the reach of children.
- Do not warm SIMPONI in any other way. For example, do not warm SIMPONI in a microwave or in hot water.
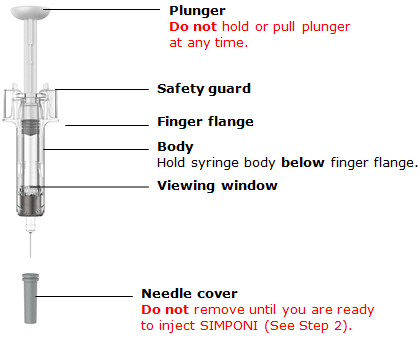
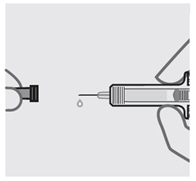
- Do not remove the prefilled syringe needle cover or SmartJect® autoinjector cap while allowing SIMPONI to reach room temperature. Remove these immediately before injection.
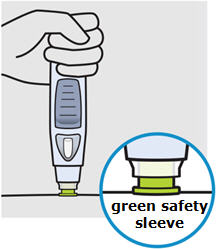
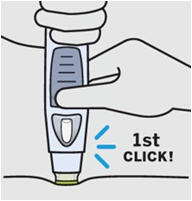
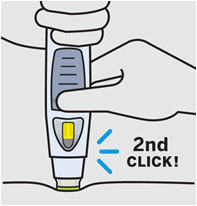
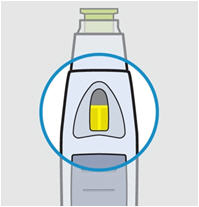
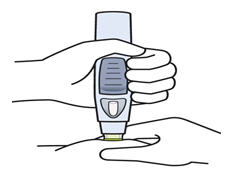
- Do not pull the autoinjector away from the skin until you hear a first "click" sound and then a second "click" sound (the injection is finished and the needle is pulled back). It usually takes about 3 to 6 seconds but may take up to 15 seconds for you to hear the second "click" after the first "click". If the autoinjector is pulled away from the skin before the injection is completed, a full dose of SIMPONI may not be administered.
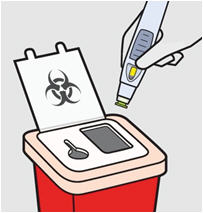
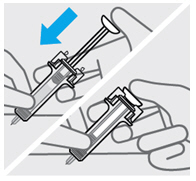
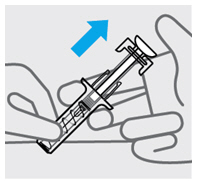
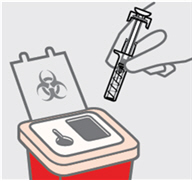
- A puncture-resistant container for disposal of needles and syringes should be used. Patients or caregivers should be instructed in the technique of proper syringe and needle disposal, and be advised not to reuse these items.
Consider the risks and benefits of treatment with SIMPONI prior to initiating therapy in patients with chronic or recurrent infection.
Monitor patients closely for the development of signs and symptoms of infection during and after treatment with SIMPONI, including the possible development of tuberculosis in patients who tested negative for latent tuberculosis infection prior to initiating therapy [see Warnings and Precautions (5.1)] .
MALIGNANCY
Lymphoma and other malignancies, some fatal, have been reported in children and adolescent patients treated with TNF blockers, of which SIMPONI is a member[seeWarnings and Precautions (5.2)] .
Monitoring
Closely monitor patients for the development of signs and symptoms of infection during and after treatment with SIMPONI. Discontinue SIMPONI if a patient develops a serious infection, an opportunistic infection, or sepsis. For a patient who develops a new infection during treatment with SIMPONI, perform a prompt and complete diagnostic workup appropriate for an immunocompromised patient, initiate appropriate antimicrobial therapy, and closely monitor them.
Serious Infection in Clinical Trials
In controlled Phase 3 trials through Week 16 in patients with RA, PsA, and AS, serious infections were observed in 1.4% of SIMPONI-treated patients and 1.3% of control-treated patients. In the controlled Phase 3 trials through Week 16 in patients with RA, PsA, and AS, the incidence of serious infections per 100 patient-years of follow-up was 5.7 (95% CI: 3.8, 8.2) for the SIMPONI group and 4.2 (95% CI: 1.8, 8.2) for the placebo group. In the controlled Phase 2/3 trial through Week 6 of SIMPONI induction in UC, the incidence of serious infections in SIMPONI 200/100 mg-treated patients was similar to the incidence of serious infections in placebo-treated patients. Through Week 60, the incidence of serious infections was similar in patients who received SIMPONI induction and 100 mg during maintenance compared with patients who received SIMPONI induction and placebo during the maintenance portion of the UC trial. Serious infections observed in SIMPONI-treated patients included sepsis, pneumonia, cellulitis, abscess, tuberculosis, invasive fungal infections, and hepatitis B infection.
Tuberculosis
Cases of reactivation of tuberculosis or new tuberculosis infections have been observed in patients receiving TNF blockers, including patients who have previously received treatment for latent or active tuberculosis. Evaluate patients for tuberculosis risk factors and test for latent infection prior to initiating SIMPONI and periodically during therapy.
Treatment of latent tuberculosis infection prior to therapy with TNF blockers has been shown to reduce the risk of tuberculosis reactivation during therapy. Prior to initiating SIMPONI, assess if treatment for latent tuberculosis is needed; an induration of 5 mm or greater is a positive tuberculin skin test, even for patients previously vaccinated with Bacille Calmette-Guerin (BCG).
Consider anti-tuberculosis therapy prior to initiation of SIMPONI in patients with a past history of latent or active tuberculosis in whom an adequate course of treatment cannot be confirmed, and for patients with a negative test for latent tuberculosis but having risk factors for tuberculosis infection. Consultation with a physician with expertise in the treatment of tuberculosis is recommended to aid in the decision whether initiating anti-tuberculosis therapy is appropriate for an individual patient.
Cases of active tuberculosis have occurred in patients treated with SIMPONI during and after treatment for latent tuberculosis. Monitor patients for the development of signs and symptoms of tuberculosis including patients who tested negative for latent tuberculosis infection prior to initiating therapy, patients who are on treatment for latent tuberculosis, or patients who were previously treated for tuberculosis infection.
Consider tuberculosis in the differential diagnosis in patients who develop a new infection during SIMPONI treatment, especially in patients who have previously or recently traveled to countries with a high prevalence of tuberculosis, or who have had close contact with a person with active tuberculosis.
In the controlled and uncontrolled portions of the Phase 2 RA and Phase 3 RA, PsA, and AS trials, the incidence of active TB was 0.23 and 0 per 100 patient-years in 2347 SIMPONI-treated patients and 674 placebo-treated patients, respectively. Cases of TB included pulmonary and extrapulmonary TB. The overwhelming majority of the TB cases occurred in countries with a high incidence rate of TB. In the controlled Phase 2/3 trial of SIMPONI induction through Week 6 in UC, no cases of TB were observed in SIMPONI 200/100 mg-treated patients or in placebo-treated patients. Through Week 60, the incidence per 100 patient-years of TB in patients who received SIMPONI induction and 100 mg during the maintenance portion of the UC trial was 0.52 (95% CI: 0.11, 1.53). One case of TB was observed in the placebo maintenance group in a patient who received SIMPONI intravenous (IV) induction.
Invasive Fungal Infections
If patients develop a serious systemic illness and they reside or travel in regions where mycoses are endemic, consider invasive fungal infection in the differential diagnosis. Consider appropriate empiric antifungal therapy, and take into account both the risk for severe fungal infection and the risks of antifungal therapy while a diagnostic workup is being performed. Antigen and antibody testing for histoplasmosis may be negative in some patients with active infection. To aid in the management of such patients, consider consultation with a physician with expertise in the diagnosis and treatment of invasive fungal infections.
Live Vaccines
Patients treated with SIMPONI may receive vaccinations, except for live vaccines. In patients receiving anti-TNF therapy, limited data are available on the response to live vaccination, or on the secondary transmission of infection by live vaccines. Use of live vaccines could result in clinical infections, including disseminated infections.
If possible, it is recommended that prior to initiating therapy with SIMPONI, pediatric patients be brought up to date with all immunizations in agreement with current immunization guidelines.
Therapeutic Infectious Agents
Other uses of therapeutic infectious agents such as live attenuated bacteria (e.g., BCG bladder instillation for the treatment of cancer) could result in clinical infections, including disseminated infections. It is recommended that therapeutic infectious agents not be given concurrently with SIMPONI.
Non-live Vaccines
In the Phase 3 PsA trial, after pneumococcal vaccination, a similar proportion of SIMPONI-treated and placebo-treated patients were able to mount an adequate immune response of at least a 2-fold increase in antibody titers to pneumococcal polysaccharide vaccine. In both SIMPONI-treated and placebo-treated patients, the proportions of patients with response to pneumococcal vaccine were lower among patients receiving MTX compared with patients not receiving MTX. The data suggest that SIMPONI does not suppress the humoral immune response to the pneumococcal vaccine.
Infections
In adult controlled Phase 3 trials through Week 16 in RA, PsA, and AS, infections were observed in 28% of SIMPONI-treated patients compared to 25% of control-treated patients. For serious infections, see the Warnings and Precautions section [see Warnings and Precautions (5.1)] . In Trial UC-1, the rates of infections were similar in SIMPONI 200/100 mg-treated patients and placebo-treated patients, or approximately 12%. Through Week 60, the incidence per patient year of infections was similar in patients who received SIMPONI induction and 100 mg during maintenance compared with patients who received SIMPONI induction and placebo during the maintenance period Trial UC-2.
Demyelinating Disorders
In Trial UC-1 of SIMPONI induction through Week 6, no cases of demyelination were observed in SIMPONI 200/100 mg-treated patients or placebo-treated patients. Through Week 60 in Trial UC-2, there were no cases of demyelination in the SIMPONI 100 mg group during maintenance. One case of CNS demyelination was observed in the placebo maintenance group in a patient who received SIMPONI 400/200 mg during induction.
Liver Enzyme Elevations
There have been reports of severe hepatic reactions including acute liver failure in patients receiving TNF blockers. In adult controlled Phase 3 trials of SIMPONI in patients with RA, PsA, and AS through Week 16, ALT elevations ≥ 5 × ULN occurred in 0.2% of control-treated patients and 0.7% of SIMPONI-treated patients and ALT elevations ≥ 3 × ULN occurred in 2% of control-treated patients and 2% of SIMPONI-treated patients. Since many of the patients in the Phase 3 trials for RA, PsA, and AS were also taking medications that cause liver enzyme elevations (e.g., NSAIDs, MTX), the relationship between SIMPONI and liver enzyme elevation is not clear.
In Trials UC-1, UC-2, and UC-3, the incidence of ALT elevations ≥ 5 × ULN was similar in SIMPONI-treated patients and placebo-treated patients, or approximately 1%, with an average duration of follow-up of 46 weeks and 18 weeks, respectively. ALT elevations ≥ 3 × ULN occurred in 2.0% of SIMPONI-treated patients compared with 1.5% of placebo-treated patients with an average duration of follow-up of 46 weeks and 18 weeks, respectively.
Autoimmune Disorders and Autoantibodies
In the adult controlled Phase 3 trials in patients with RA, PsA, and AS through Week 14, there was no association of SIMPONI treatment and the development of newly positive anti-dsDNA antibodies. In Phase 3 trials in RA, PsA, and AS through 1 year of follow-up, 4.0% of SIMPONI-treated patients and 2.6% of control patients were newly antinuclear antibody (ANA)-positive (at titers of 1:160 or greater). The frequency of anti-dsDNA antibodies at 1 year of follow-up was uncommon in patients who were anti-dsDNA negative at baseline. Through Week 60 of the UC trials (Trials UC-1, UC-2, and UC-3), 3.5% of patients who received SIMPONI induction and 100 mg during maintenance were newly ANA-positive (at titers of 1:160 or greater) compared with 3.5% of patients who received SIMPONI induction and placebo during the maintenance period in Trial UC-2. The frequency of anti-dsDNA antibodies at 1 year of follow-up in patients who were anti-dsDNA negative at baseline was 0.5% in patients receiving SIMPONI induction and 100 mg during maintenance compared with 0% in patients who received SIMPONI induction and placebo during maintenance [see Warnings and Precautions (5.6)].
Injection Site Reactions
In adult controlled Phase 3 trials through Week 16 in RA, PsA and AS, 6% of SIMPONI-treated patients had injection site reactions compared with 2% of control-treated patients. The majority of the injection site reactions were mild and the most frequent manifestation was injection site erythema.
In Trial UC-1, 3.4% of SIMPONI-treated patients had injection site reactions compared with 1.5% in control-treated patients. The majority of the injection site reactions were mild and moderate and the most frequent manifestation was injection site erythema.
In adult controlled Phase 2 and 3 trials in RA, PsA, AS, no patients treated with SIMPONI developed anaphylactic reactions.
Other Adverse Reactions
Table 2 summarizes the adverse drug reactions that occurred at a rate of at least 1% in the SIMPONI ± DMARD group and with a higher incidence than in the placebo ± DMARD group during the controlled period of the 5 pooled Phase 3 trials through Week 16 in adult patients with RA, PsA, and AS.
| SIMPONI ± DMARDs | Placebo ± DMARDs | |
|---|---|---|
| Patients treated | 1659 | 639 |
| Adverse Reaction | ||
| Infections and infestations | ||
| Upper respiratory tract infection (nasopharyngitis, pharyngitis, laryngitis, and rhinitis) | 16% | 13% |
| Viral infections (such as influenza and herpes) | 5% | 3% |
| Bronchitis | 2% | 1% |
| Superficial fungal infections | 2% | 1% |
| Sinusitis | 2% | 1% |
| General disorders and administration site conditions | ||
| Injection site reaction (injection site erythema, urticaria, induration, pain, bruising, pruritus, irritation, paresthesia) | 6% | 2% |
| Investigations | ||
| Alanine aminotransferase increased | 4% | 3% |
| Aspartate aminotransferase increased | 3% | 2% |
| Vascular disorders | ||
| Hypertension | 3% | 2% |
| Nervous system disorders | ||
| Dizziness | 2% | 1% |
| Paresthesia | 2% | 1% |
| Gastrointestinal disorders | ||
| Constipation | 1% | <1% |
Less Common Clinical Trial Adverse Drug Reactions
Adverse drug reactions that occurred <1% in adult SIMPONI-treated patients in the RA, PsA and AS clinical trials that do not appear in the Warnings and Precautions section included the following events listed by system organ class:
Infections and infestations:Septic shock, atypical mycobacterial infection, pyelonephritis, arthritis bacterial, bursitis infective
Neoplasms benign, malignant and unspecified:Leukemia
Skin and subcutaneous tissue disorders:Psoriasis (new onset or worsening, palmar/plantar and pustular), vasculitis (cutaneous)
Vascular disorders:Vasculitis (systemic)
Adults and Pediatric Patients Weighing at least 15 kg with Ulcerative Colitis
In general, adverse reactions reported in adult patients with UC in Trials UC-1, UC-2, and UC-3 were similar to those reported in clinical trials of patients with RA, PsA, and AS. Adverse reactions reported in the clinical trial of pediatric patients weighing at least 15 kg with UC were also similar to those reported in clinical trials of adults with UC and the other indicated populations. Additional adverse reactions reported in at least 10% of pediatric patients in the trial were headache (17%) and pyrexia (10%).
Risk Summary
Available data from postmarketing case reports with golimumab use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. An observational study of northern European births observed similar unadjusted rates of major birth defects in infants exposed in utero to golimumab compared to no treatment or non-biologic systemic therapy. However, this study had important limitations (see Data).
Monoclonal antibodies, such as golimumab, are transported across the placenta during the third trimester of pregnancy and may affect immune response in the in uteroexposed infant (see Clinical Considerations) . In an animal reproductive study, golimumab administered by the subcutaneous route to pregnant monkeys, during the period of organogenesis, at doses that produced exposures approximately 360 times the maximum recommended human dose (MRHD) had no adverse fetal effects (see Data) . In a pre- and post-natal development study with pregnant monkeys, subcutaneous administration of golimumab, during the later gestational and lactation periods, at doses producing maximal maternal blood concentrations approximately 460 times those found with the MRHD had no adverse developmental effects on infants (see Data). Data suggest that there are risks to the mother and the fetus associated with rheumatoid arthritis and ulcerative colitis in pregnancy (see Clinical Considerations).
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and of miscarriage is 15–20%, respectively.
Clinical Considerations
Disease-associated Maternal and/or Embryo/Fetal Risk
Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with rheumatoid arthritis or ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth.
Fetal/Neonatal Adverse Reactions
Golimumab crosses the placenta during pregnancy. Another TNF-blocking monoclonal antibody administered during pregnancy was detected for up to 6 months in the serum of infants. Consequently, these infants may be at increased risk of infection. Administration of live vaccines to infants exposed to SIMPONI in utero is not recommended for 6 months following the mother's last SIMPONI injection during pregnancy [see Warnings and Precautions (5.11) and Drug Interactions (7.3)] .
Data
Human Data
An observational, exposure-based, cohort study based on data from the Swedish, Danish, and Finnish Medical Birth Registers conducted between 2006–2020 (Sweden and Denmark) and 2006–2019 (Finland) compared the risk of major birth defects in 134 live-born infants exposed to golimumab (116 from women treated for rheumatic conditions, 18 from women treated for ulcerative colitis) to no treatment or non-biologic systemic therapy. The unadjusted rate of major birth defects in infants exposed in uterowas similar across all groups. However, this study had important limitations such as a small number of pregnant women exposed to golimumab, a wide exposure ascertainment window, and incomplete risk adjustment for potential confounders.
Animal Data
In an embryofetal developmental toxicology study in which pregnant cynomolgus monkeys were treated with golimumab during the period organogenesis from gestation days (GD) 20 to 51, exposures up to 360 times greater than the exposure at the MRHD (on an area under the curve (AUC) basis with maternal subcutaneous doses up to 50 mg/kg twice weekly) produced no evidence of fetal malformations or embryotoxicity. There was no evidence of maternal toxicity. Umbilical cord blood samples collected at the end of the second trimester showed that fetuses were exposed to golimumab during gestation.
In a pre- and post-natal developmental study in which pregnant cynomolgus monkeys were treated with golimumab from gestation day 50 to postpartum day 33, maximal drug concentrations approximately 460 times greater than that found with the MRHD (on a maximum blood concentration (C max) basis at steady state with maternal subcutaneous doses up to 50 mg/kg twice weekly) were not associated with any evidence of developmental defects in infants. There was no evidence of maternal toxicity. Golimumab was present in fetal serum at the end of the second trimester and in neonatal serum from the time of birth and for up to 6 months postpartum.
Risk Summary
There is no information regarding the presence of SIMPONI in human milk, the effects on breastfed infants, or the effects on milk production. Maternal IgG is known to be present in human milk. Golimumab is present in the milk of lactating cynomolgus monkeys (see Data) . If golimumab is transferred into human milk, the effects of local exposure in the gastrointestinal tract and potential limited systemic exposure in the infant to golimumab are unknown. The developmental and health benefits of breast-feeding should be considered along with the mother's clinical need for SIMPONI and any potential adverse effects on the breast-fed infants from SIMPONI, or from the underlying maternal condition.
Data
In the pre- and post-natal development study in cynomolgus monkeys in which golimumab was administered subcutaneously during pregnancy and lactation, golimumab was detected in the breast milk at concentrations that were approximately 400-fold lower than the maternal serum concentrations.
Ulcerative Colitis
The safety and effectiveness of SIMPONI for the treatment of moderately to severely active ulcerative colitis have been established in pediatric patients weighing at least 15 kg. Use of SIMPONI for this indication is supported by evidence from adequate and well-controlled studies in adults with additional safety and efficacy data from an open-label, study in 69 pediatric patients (4 to 17 years of age). The adverse reaction profile in these pediatric patients was similar to adults [see Adverse Reactions (6.1), Clinical Pharmacology (12.3), and Clinical Studies (14.5)]. Additionally, headache (17%) and pyrexia (10%) were reported in at least 10% of pediatric patients in the trial.
The safety and effectiveness of SIMPONI for the treatment of moderately to severely active ulcerative colitis have not been established in pediatric patients weighing less than 15 kg.
Polyarticular Juvenile Idiopathic Arthritis (pJIA)
The safety and efficacy of SIMPONI were evaluated in a multicenter, placebo-controlled, double-blind, randomized-withdrawal, parallel group study in 173 children (2 to 17 years of age) with active polyarticular juvenile idiopathic arthritis (pJIA) despite treatment with MTX for at least 3 months. Subjects were maintained on their stable dose of MTX at the same dose (mg/week) at study entry. Concurrent use of stable doses of oral corticosteroids (≤10 mg/day or 0.2 mg/kg/day prednisone or equivalent, whichever was less) and/or NSAIDs was permitted. In the 16 week open-label phase, all patients received MTX and SIMPONI 30 mg/m 2(maximum 50 mg) subcutaneously every 4 weeks. Patients who achieved an ACR Ped 30 response at Week 16 entered the randomized-withdrawal phase of the study and received MTX and either SIMPONI 30 mg/m 2(maximum 50 mg) or placebo every 4 weeks through Week 48.
The primary endpoint of the study was the proportion of patients who did not experience a flare between Week 16 and Week 48, among all subjects who entered the randomized withdrawal phase. The efficacy of SIMPONI in the treatment of pJIA was not demonstrated in this study because there was no statistical evidence of differences in flare rate between SIMPONI-treated patients and placebo patients between Weeks 16 and 48.
In this study, the frequency and type of the adverse reactions seen in children were generally similar to those observed in adults.
Absorption
Following subcutaneous administration of SIMPONI to healthy subjects and patients with active RA, the median time to reach maximum serum concentrations (T max) ranged from 2 to 6 days. A subcutaneous injection of 50 mg SIMPONI to healthy subjects produced a mean ± standard deviation maximum serum concentration (C max) of 3.2 ± 1.4 mcg/mL.
By cross-trial comparisons of mean AUC infvalues following an IV or subcutaneous administration of SIMPONI, the absolute bioavailability of subcutaneous SIMPONI was estimated to be approximately 53%.
Distribution
Following a single IV administration over the dose range of 0.1 to 10.0 mg/kg in patients with active RA, mean volume of distribution ranged from 58 to 126 mL/kg. The volume of distribution for golimumab indicates that golimumab is distributed primarily in the circulatory system with limited extravascular distribution.
Metabolism
The exact metabolic pathway of golimumab is unknown.
Elimination
Following a single IV administration over the dose range of 0.1 to 10.0 mg/kg in patients with active RA, mean systemic clearance of SIMPONI was estimated to be 4.9 to 6.7 mL/day/kg.
Median terminal half-life values were estimated to be approximately 2 weeks in healthy subjects and patients with active RA, PsA or AS.
Population PK analyses indicated that concomitant use of NSAIDs, oral corticosteroids, or sulfasalazine did not influence the apparent clearance of golimumab.
Patients who developed anti-golimumab antibodies generally had lower steady-state serum trough concentrations of golimumab.
Dose Linearity
Golimumab exhibited dose-proportional pharmacokinetics (PK) in patients with active RA over the dose range of 0.1 to 10 mg/kg following a single intravenous (IV) dose. Following a single SC dose in healthy subjects, dose proportional pharmacokinetics were also observed over a dose range of 50 mg to 400 mg.
Single Dose Versus Multiple Doses
When 50 mg SIMPONI was administered subcutaneous to patients with RA, PsA, or AS every 4 weeks, serum concentrations appeared to reach steady state by Week 12. With concomitant use of methotrexate (MTX), treatment with 50 mg SIMPONI subcutaneous every 4 weeks resulted in a mean steady-state trough serum concentration of approximately 0.4–0.6 mcg/mL in patients with active RA, approximately 0.5 mcg/mL in patients with active PsA, and approximately 0.8 mcg/mL in patients with active AS. Patients with RA, PsA, and AS treated with SIMPONI 50 mg and MTX had approximately 52%, 36% and 21% higher mean steady-state trough concentrations of golimumab, respectively compared with those treated with SIMPONI 50 mg without MTX. The presence of MTX also decreased anti-golimumab antibody incidence from 7% to 2% [see Adverse Reactions (6.1)] . For RA, SIMPONI should be used with MTX. In the PsA and AS trials, the presence or absence of concomitant MTX did not appear to influence clinical efficacy and safety parameters [see Drug Interactions (7.1) and Clinical Studies (14.1)] .
When induction doses of 200 mg and 100 mg SIMPONI at week 0 and 2, respectively, followed by maintenance doses of 100 mg SIMPONI every 4 weeks were administered subcutaneously in patients with UC, serum golimumab concentrations reached steady-state by week 8 after the first maintenance dose. Treatment with 100 mg SIMPONI subcutaneous every 4 weeks during maintenance resulted in a mean steady-state trough serum concentration of approximately 1.8 ± 1.1 mcg/mL.
Effect of Weight on Pharmacokinetics in Adults
Higher apparent clearance of golimumab was associated with increasing weight. Treatment with the recommended maintenance dose regimen of SIMPONI 100 mg in adult patients with UC did not result in meaningful differences in clinical efficacy among different weight groups. Across the PsA and AS populations, no meaningful differences in clinical efficacy were observed among the subgroups by weight quartile. The RA trial in MTX-experienced and TNF-blocker-naïve patients (Trial RA-2) did show evidence of a reduction in clinical efficacy with increasing body weight, but this effect was observed for both tested doses of SIMPONI (50 mg and 100 mg). There is no need to adjust the dosage of SIMPONI in adult patients based on body weight.
Specific Populations
In adults, population PK analyses suggested no PK differences between male and female patients after body-weight adjustment in the RA, PsA and UC trials. In the AS trial, female patients showed 13% higher apparent clearance than male patients after body-weight adjustment. Subgroup analysis based on gender showed that both female and male patients achieved clinically significant response at the proposed clinical dose. Dosage adjustment based on gender is not needed.
Population PK analyses indicated that PK parameters of golimumab were not influenced by age in adult patients. Patients with age ≥ 65 years had apparent clearance of golimumab similar to patients with age < 65 years. No ethnicity-related PK differences were observed between Caucasians and Asians, and there were too few patients of other races to assess for PK differences.
No formal trial of the effect of renal or hepatic impairment on the PK of golimumab was conducted.
Pediatric Patients Weighing at Least 15 kg with Ulcerative Colitis
The pharmacokinetics of golimumab were studied in pediatric patients with UC aged 4 to 17 years. The pharmacokinetics of golimumab are predicted to be similar between adult patients and pediatric patients with UC. There are no expected clinically significant differences in golimumab systemic exposure between adult patients and pediatric patients weighing 15 kg and above who receive the recommended dosage [see Dosage and Administration (2.3)].
Results from the EIA Method
Using an enzyme immunoassay (EIA method), antibodies to golimumab were detected in 57 (4%) of SIMPONI-treated adult patients across the Phase 3 RA, PsA and AS trials through Week 24. Similar rates were observed in each of the 3 indications. Patients who received SIMPONI with concomitant MTX had a lower proportion of antibodies to golimumab than patients who received SIMPONI without MTX (approximately 2% vs. 7%, respectively).
With the EIA method, the presence of serum concentrations of golimumab can interfere with the detection of antibodies to golimumab leading to inconclusive results. In adult UC trials, 34 (3%), 341 (28%) and 823 (69%) of SIMPONI-treated patients were positive, negative and inconclusive for antibodies to golimumab, respectively. Treatment with concomitant immunomodulators (AZA, 6-MP or MTX) resulted in a lower proportion of patients with antibodies to golimumab than patients receiving SIMPONI without immunomodulators (2% vs. 4%, respectively).
Of the adult patients with a positive antibody response to golimumab in the Phase 2 and 3 trials, most were determined to have neutralizing antibodies to golimumab as measured by a cell-based functional assay.
Results from the Drug-Tolerant EIA Method
A drug-tolerant enzyme immunoassay (drug-tolerant EIA) method for detecting antibodies to golimumab was developed and validated, which eliminated the inconclusive category as reported above. This method is approximately 16-fold more sensitive than the original EIA method with less interference from golimumab in serum.
Based on the drug-tolerant EIA method, 246 (23%) of SIMPONI-treated patients across the Phase 3 RA, PsA and AS trials in adults, antibodies to golimumab were detected in 59 (16%), 106 (28%), and 81 (24%) patients, respectively. Treatment with concomitant MTX resulted in a lower proportion of patients with antibodies to golimumab than in patients receiving SIMPONI without MTX in RA patients (7% vs. 35%), in PsA patients (18% vs. 38%) and in AS patients (6% vs. 29%). A trend of decreasing drug concentrations with increasing antibody titers was observed. While an overall decrease in clinical efficacy for ADA positive patients compared with ADA negative patients was not observed in patients with RA (ACR 20: 75% vs. 75%), PsA (ACR 20: 72% vs. 66%) and AS (ASAS 20: 57% vs. 65%), higher titer antibodies may be associated with diminished efficacy.
In UC trials in adults, 254 (21%) of SIMPONI-treated patients were positive for antibodies to golimumab through week 54 while the remaining 941 (79%) patients were negative. Treatment with concomitant immunomodulators (AZA, 6-MP or MTX) in the UC trials resulted in a lower proportion of patients with antibodies to golimumab than in patients receiving SIMPONI without immunomodulators (12% vs. 26%). There is a trend of decreasing drug concentrations with increasing antibody titers. Although the development of antibodies to golimumab did not preclude clinical response, a trend toward decreased efficacy in ADA positive patients was observed compared to ADA negative patients in the UC trials (clinical response 38% vs. 53%).
In the pediatric UC trial, 22% (15/69) of SIMPONI-treated patients developed ADA to golimumab through the final safety visit using the drug-tolerant EIA method. Of the 15 subjects who tested positive for ADA, 20% (3/15) tested positive for neutralizing antibodies. The incidence of antibodies to golimumab was comparable between pediatric and adult patients with UC. Pediatric UC patients who developed antibodies to golimumab generally had lower trough steady-state serum concentrations of golimumab. While there is insufficient data to assess whether the observed ADA-associated pharmacokinetic changes reduce effectiveness, a trend toward decreased efficacy in ADA positive patients was observed compared to ADA negative patients in the pediatric UC trial.
Clinical Response
In the 3 RA trials, a greater percentage of patients treated with the combination of SIMPONI and MTX achieved ACR responses at Week 14 (Trials RA-1 and RA-2) and Week 24 (Studies RA-1, RA-2, and RA-3) versus patients treated with the MTX alone. There was no clear evidence of improved ACR response with the higher SIMPONI dose group (100 mg) compared to the lower SIMPONI dose group (50 mg). In Trials RA-2 and RA-3, the SIMPONI monotherapy groups were not statistically different from the MTX monotherapy groups in ACR responses. Table 3 shows the proportion of patients with the ACR response for the SIMPONI 50 mg and control groups in Trials RA-1, RA-2, and RA-3. In the subset of patients who received SIMPONI in combination with MTX in Trial RA-1, the proportion of patients achieving ACR 20, 50 and 70 responses at Week 14 were 40%, 18%, and 12%, respectively, in the SIMPONI 50 mg + MTX group (N=101) compared with 17%, 6%, and 2%, respectively, in the placebo + MTX group (N=103). Table 4 shows the percent improvement in the components of the ACR response criteria for the SIMPONI 50 mg + MTX and MTX groups in Trial RA-2. The percentage of patients achieving ACR 20 responses by visit for Trial RA-2 is shown in Figure 1. ACR 20 responses were observed in 38% of patients in the SIMPONI 50 mg + MTX group at the first assessment (Week 4) after the initial SIMPONI administration.
| Trial RA-1
Active RA previously treated with one or more doses of TNF blockers | Trial RA-2
Active RA, despite MTX | Trial RA-3
Active RA, MTX Naïve | ||||
|---|---|---|---|---|---|---|
| Placebo ± DMARDs
DMARDs in Trial RA-1 included MTX, HCQ, and/or SSZ (about 68%, 8%, and 5% of patients received MTX, HCQ, and SSZ, respectively). | SIMPONI 50 mg ± DMARDs
| Background MTX | SIMPONI 50 mg + Background MTX | MTX | SIMPONI 50 mg + MTX | |
| N
N reflects randomized patients. | 150 | 147 | 133 | 89 | 160 | 159 |
| ACR 20 | ||||||
| Week 14 | 18% | 35% | 33% | 55% | NA
NA = Not applicable, as data was not collected at Week 14 in Trial RA-3. | NA
|
| Week 24 | 16% | 31% | 28% | 60% | 49% | 62% |
| ACR 50 | ||||||
| Week 14 | 7% | 15% | 10% | 35% | NA
| NA
|
| Week 24 | 4% | 16% | 14% | 37% | 29% | 40% |
| ACR 70 | ||||||
| Week 14 | 2% | 10% | 4% | 13% | NA
| NA
|
| Week 24 | 2% | 9% | 5% | 20% | 16% | 24%
Not significantly different from MTX monotherapy. |
| Background MTX | SIMPONI 50 mg + Background MTX | |
|---|---|---|
| Note: Baseline values are medians. | ||
| N
N reflects randomized patients; actual number of patients evaluable for each endpoint may vary. | 133 | 89 |
| Number of swollen joints (0–66) | ||
| Baseline | 12 | 13 |
| Week 14 | 38% | 62% |
| Number of tender joints (0–68) | ||
| Baseline | 21 | 26 |
| Week 14 | 30% | 60% |
| Patient's assessment of pain (0–10) | ||
| Baseline | 5.7 | 6.1 |
| Week 14 | 18% | 55% |
| Patient's global assessment of disease activity (0–10) | ||
| Baseline | 5.3 | 6.0 |
| Week 14 | 15% | 45% |
| Physician's global assessment of disease activity (0–10) | ||
| Baseline | 5.7 | 6.1 |
| Week 14 | 35% | 55% |
| HAQ score (0–3) | ||
| Baseline | 1.25 | 1.38 |
| Week 14 | 10% | 29% |
| CRP (mg/dL) | ||
| Baseline | 0.8 | 1.0 |
| Week 14 | 2% | 44% |
| Figure 1: Trial RA-2 – Percentage of Patients Achieving ACR 20 Response by Visit: Randomized Patients
The same patients may not have responded at each timepoint. |
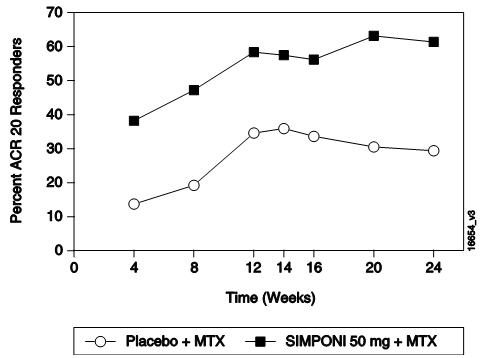 Figure 1 (Simponi 01) |
Physical Function Response in Patients with RA
In Trials RA-1 and RA-2, the SIMPONI 50 mg groups demonstrated a greater improvement compared to the control groups in the change in mean Health Assessment Questionnaire Disability Index (HAQ-DI) score from baseline to Week 24: 0.23 vs. 0.03 in RA-1, 0.47 vs. 0.13 in RA-2, respectively. Also in Trials RA-1 and RA-2, the SIMPONI 50 mg groups compared to the control groups had a greater proportion of HAQ responders (change from baseline > 0.22) at Week 24: 43% vs. 27%, 65% vs. 35%, respectively.
Clinical Response in Patients with PsA
SIMPONI ± MTX, compared with placebo ± MTX, resulted in significant improvement in signs and symptoms as demonstrated by the proportion of patients with an ACR 20 response at Week 14 in Trial PsA (see Table 5). There was no clear evidence of improved ACR response with the higher SIMPONI dose group (100 mg) compared to the lower SIMPONI dose group (50 mg). ACR responses observed in the SIMPONI-treated groups were similar in patients receiving and not receiving concomitant MTX. Similar ACR 20 responses at Week 14 were observed in patients with different PsA subtypes. However, the number of patients with arthritis mutilans was too small to allow meaningful assessment. SIMPONI 50 mg treatment also resulted in significantly greater improvement compared with placebo for each ACR component in Trial PsA (Table 6). Treatment with SIMPONI resulted in improvement in enthesitis and skin manifestations in patients with PsA. However, the safety and efficacy of SIMPONI in the treatment of patients with plaque psoriasis has not been established.
The percentage of patients achieving ACR 20 responses by visit for Trial PsA is shown in Figure 2. ACR 20 responses were observed in 31% of patients in the SIMPONI 50 mg + MTX group at the first assessment (Week 4) after the initial SIMPONI administration.
| Placebo ± MTX
In Trial PsA, about 48%, 16%, and 72% of the patients received stable doses of MTX (≤ 25 mg/week), low dose corticosteroids (equivalent to ≤ 10 mg of prednisone a day), and NSAIDs, respectively. | SIMPONI 50 mg ± MTX
| |
|---|---|---|
| Bold text indicates primary endpoint. | ||
| N
N reflects randomized patients. | 113 | 146 |
| ACR 20 | ||
| Week 14 | 9% | 51% |
| Week 24 | 12% | 52% |
| ACR 50 | ||
| Week 14 | 2% | 30% |
| Week 24 | 4% | 32% |
| ACR 70 | ||
| Week 14 | 1% | 12% |
| Week 24 | 1% | 19% |
| Placebo ± MTX
In Trial PsA, about 48%, 16%, and 78% of the patients received stable doses of MTX (≤ 25 mg/week), low dose corticosteroids (equivalent to ≤ 10 mg of prednisone a day), and NSAIDs, respectively. | SIMPONI 50 mg ± MTX
| |
|---|---|---|
| Note: Baseline are median values. | ||
| N
N reflects randomized patients; actual number of patients evaluable for each endpoint may vary by timepoint. | 113 | 146 |
| Number of swollen joints (0–66) | ||
| Baseline | 10.0 | 11.0 |
| Week 14 | 8% | 60% |
| Number of tender joints (0–68) | ||
| Baseline | 18.0 | 19.0 |
| Week 14 | 0% | 54% |
| Patient's assessment of pain (0–10) | ||
| Baseline | 5.4 | 5.8 |
| Week 14 | -1% | 48% |
| Patient's global assessment of disease activity (0–10) | ||
| Baseline | 5.2 | 5.2 |
| Week 14 | 2% | 49% |
| Physician's global assessment of disease activity (0–10) | ||
| Baseline | 5.2 | 5.4 |
| Week 14 | 7% | 59% |
| HAQ score (0–10) | ||
| Baseline | 1.0 | 1.0 |
| Week 14 | 0% | 28% |
| CRP (mg/dL) (0–10) | ||
| Baseline | 0.6 | 0.6 |
| Week 14 | 0% | 40% |
| Figure 2: Trial PsA – Percentage of ACR 20 PsA Responders by Visit: Randomized Patients
The same patients may not have responded at each timepoint. |
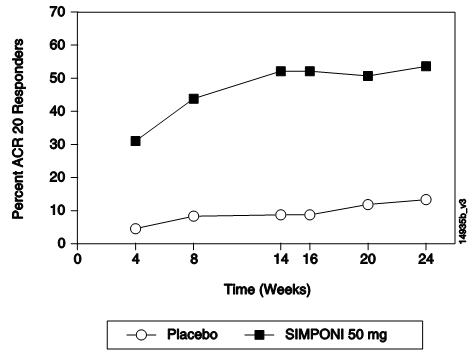 Figure 2 (Simponi 02) |
Physical Function Response in Patients with PsA
In Trial PsA, SIMPONI 50 mg demonstrated a greater improvement compared to placebo in the change in mean Health Assessment Questionnaire Disability Index (HAQ-DI) score from baseline to Week 24 (0.33 and -0.01, respectively). In addition, the SIMPONI 50 mg group compared to the placebo group had a greater proportion of HAQ responders (≥ 0.3 change from baseline) at Week 24: 43% vs. 22%, respectively.
Clinical Response in Patients with AS
In Trial AS, SIMPONI ± DMARDs treatment, compared with placebo ± DMARDs, resulted in a significant improvement in signs and symptoms as demonstrated by the proportion of patients with an ASAS 20 response at Week 14 (see Table 7). There was no clear evidence of improved ASAS response with the higher SIMPONI dose group (100 mg) compared to the lower SIMPONI dose group (50 mg). Table 8 shows the percent improvement in the components of the ASAS response criteria for the SIMPONI 50 mg ± DMARDs and placebo ± DMARDs groups in Trial AS.
The percentage of patients achieving ASAS 20 responses by visit for Trial AS is shown in Figure 3. ASAS 20 responses were observed in 48% of patients in the SIMPONI 50 mg + MTX group at the first assessment (Week 4) after the initial SIMPONI administration.
| Placebo ± DMARDs
During the trial, the concomitant use of stable doses of DMARDs was as follows: MTX (21%), SSZ (25%), and HCQ (1%). About 16% and 89% of patients received stable doses of low dose oral steroids and NSAIDs during the trial, respectively. | SIMPONI 50 mg ± DMARDs
| |
|---|---|---|
| Bold text indicates primary endpoint. | ||
| N
N reflects randomized patients. | 78 | 138 |
| Responders, % of patients | ||
| ASAS 20 | ||
| Week 14 | 22% | 59% |
| Week 24 | 23% | 56% |
| ASAS 40 | ||
| Week 14 | 15% | 45% |
| Week 24 | 15% | 44% |
| Placebo ± DMARDs
During the trial, the concomitant use of stable doses of DMARDs was as follows: MTX (21%), SSZ (25%), and HCQ (1%). About 16% and 89% of patients received stable doses of low dose oral steroids and NSAIDs during the trial, respectively. | SIMPONI 50 mg ± DMARDs
| |
|---|---|---|
| N
N reflects randomized patients. | 78 | 138 |
| ASAS components | ||
| Patient global assessment (0–10) | ||
| Baseline | 7.2 | 7.0 |
| Week 14 | 13% | 47% |
| Total back pain (0–10) | ||
| Baseline | 7.6 | 7.5 |
| Week 14 | 9% | 50% |
| BASFI (0–10)
BASFI is Bath Ankylosing Spondylitis Functional Index. | ||
| Baseline | 4.9 | 5.0 |
| Week 14 | -3% | 37% |
| Inflammation (0–10)
Inflammation is the mean of 2 patient-reported stiffness self-assessments in the Bath AS Disease Activity Index (BASDAI). | ||
| Baseline | 7.1 | 7.1 |
| Week 14 | 6% | 59% |
| Figure 3: Trial AS – Percentage of AS Patients Achieving ASAS 20 Response by Visit: Randomized Patients The same patients may not have responded at each timepoint. |
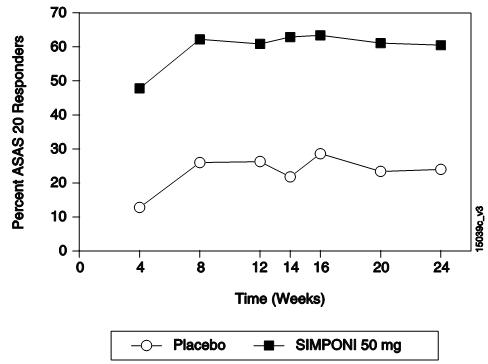 Figure 3 (Simponi 03) |
Clinical Response, Clinical Remission and Improvement of Endoscopic Appearance of the Mucosa
In Trial UC-1, a greater proportion of patients achieved clinical response, clinical remission and had improvement of endoscopic appearance of the mucosa at Week 6 in the SIMPONI 200/100 mg group compared with the placebo group. The SIMPONI 400/200 mg group did not demonstrate additional clinical benefit over the SIMPONI 200/100 mg group. Clinical response was defined as a decrease from baseline in the Mayo score of ≥ 30% and ≥ 3 points, accompanied by a decrease in the rectal bleeding subscore of ≥ 1 or a rectal bleeding subscore of 0 or 1. Clinical remission was defined as a Mayo score ≤ 2 points, with no individual subscore > 1. Improvement of endoscopic appearance of the mucosa was defined as a Mayo endoscopy subscore of 0 (normal or inactive disease) or 1 (erythema, decreased vascular pattern, mild friability).
In Trial UC-2, a greater proportion of patients maintained clinical response through Week 54 in the SIMPONI 100 mg group compared with the placebo group. In Trial UC-2, SIMPONI-treated patients in clinical response (which included the subset of patients in clinical remission) in Trial UC-1, were again assessed for clinical remission at Week 30 and Week 54. A greater proportion of patients had clinical remission at both Weeks 30 and 54 without demonstrating a loss of response at any time point through Week 54 in the SIMPONI 100 mg group compared with the placebo group.
These results are shown in Table 9 below.
| Trial UC-1 (6-Week Induction Trial) | |||
| Placebo
N=251 | SIMPONI
200/100 mg N=253 | Treatment difference
(95% CI) | |
| Clinical response
Patients who had a prohibited change in concomitant UC medication, an ostomy or colectomy, discontinued trial agent due to lack of therapeutic effect, or a dose adjustment in Trial UC-2 were considered not to be in clinical response, clinical remission or have an improvement in endoscopic appearance of the mucosa from the time of the event onward. at Week 6 | 30% | 51% | 21%
(12%, 29%) p<0.0001; |
| Clinical remission
| 6% | 18% | 11%
(6%, 17%) |
| Improvement of endoscopic appearance of the mucosa at Week 6
| 29% | 42% | 14%
(5%, 22%) p=0.0014; |
| Trial UC-2 (54-Week Maintenance Trial)
Results in Trial UC-2 are based on patients who were in clinical response to SIMPONI at trial entry. | |||
| Placebo
N=154 | SIMPONI
100 mg N=151 | Treatment difference
(95% CI) | |
| Clinical response
Patients were assessed for UC disease activity by partial Mayo score every 4 weeks (loss of response was confirmed by endoscopy). Therefore, a patient who maintained clinical response was in response at each evaluation through Week 54. | 31% | 50% | 19%
(8%, 29%) p<0.001; |
| Clinical remission
A patient had to be in remission at both Weeks 30 and 54 (without demonstrating a loss of response at any time point through Week 54) to achieve sustained remission. | 16% | 28% | 12%
(3%, 21%) p=0.004 |
Efficacy Endpoints Week 6
The results of the primary endpoint of clinical remission at Week 6 and secondary endpoint of clinical response at Week 6, both assessed by Mayo score are shown in Table 10.
| Endpoint | SIMPONI n (%) [90% CI] N=66 |
|---|---|
| Clinical remission at Week 6 Clinical remission is defined as a Mayo score ≤2 points, with no individual subscore >1. | 21 (32%) [22%, 41%] |
| Clinical response at Week 6 Clinical response is defined as a decrease from baseline in the Mayo score by ≥ 30% and ≥ 3 points, with either a decrease from baseline in the rectal bleeding subscore of ≥ 1 or a rectal bleeding subscore of 0 or 1. | 38 (58%) [48%, 68%] |
Additional Secondary Endpoints
Of the 38 pediatric subjects with clinical response at Week 6, 13 subjects (34%) were in clinical remission and 15 subjects (39%) had endoscopic improvement, defined as an endoscopy subscore of 0 or 1 based on local endoscopy, at Week 54. Of the 21 subjects in clinical remission at Week 6, 12 subjects (57%) maintained clinical remission at Week 54.
Infections
Inform patients that SIMPONI may lower the ability of their immune system to fight infections. Advise patients not to start taking SIMPONI if they have an active infection. Instruct patients to contact their healthcare provider if they develop any symptoms of infection, including tuberculosis, invasive fungal infections, and hepatitis B reactivation [see Warnings and Precautions (5.1, 5.5)].
Malignancies
Inform patients that SIMPONI may increase their risk of lymphoma and other malignancies while receiving SIMPONI [see Warnings and Precautions (5.2)].
Hypersensitivity Reactions
Advise patients to stop taking SIMPONI and contact their healthcare provider immediately if they experience any symptoms of hypersensitivity reactions while taking SIMPONI [see Warnings and Precautions (5.12)].
Advise latex-sensitive patients that the needle cover on the prefilled syringe as well as the prefilled syringe in the prefilled SmartJect® autoinjector contains dry natural rubber (a derivative of latex) [see How Supplied/Storage and Handling (16)].
Other Medical Conditions
Advise patients to report any signs of new or worsening medical conditions such as congestive heart failure, demyelinating disorders, autoimmune diseases, liver disease, or cytopenias [see Warnings and Precautions (5.3, 5.4, 5.5, 5.6, 5.10)].
Instructions for Safe Administration
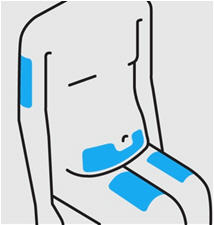
The first injection should be performed under the supervision of a qualified healthcare professional. Only the prefilled syringe is recommended for pediatric self-injection.
SIMPONI Prefilled Syringe
SIMPONI SmartJect® Autoinjector
If a patient or caregiver is to administer SIMPONI, he/she should be instructed in injection techniques and their ability to inject subcutaneously should be assessed to ensure the proper administration of SIMPONI.
Advise the patient to read the FDA-approved Instructions for Use and provide the following instructions to patients:
Manufactured by:
Janssen Biotech, Inc.
Horsham, PA 19044, USA
U.S. License No. 1864
For patent information: www.janssenpatents.com
© Johnson & Johnson and its affiliates 2025