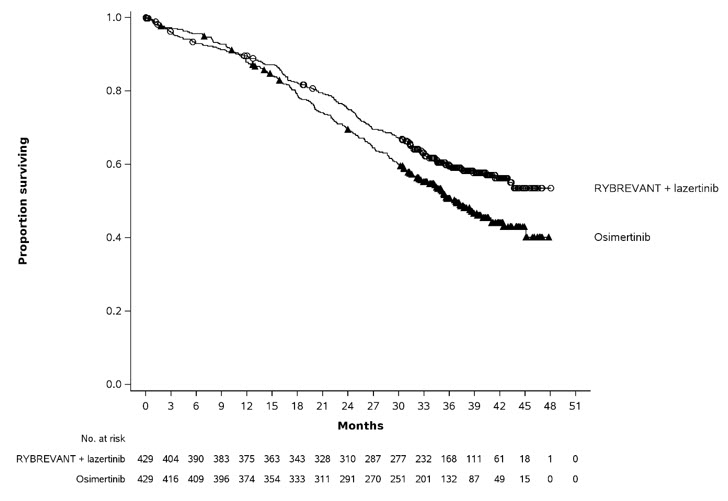
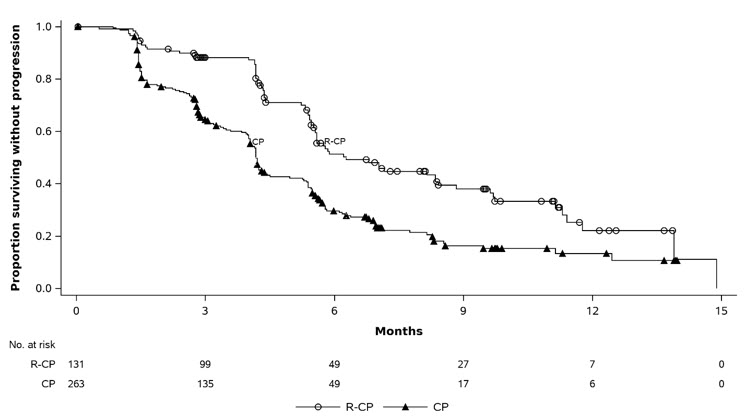
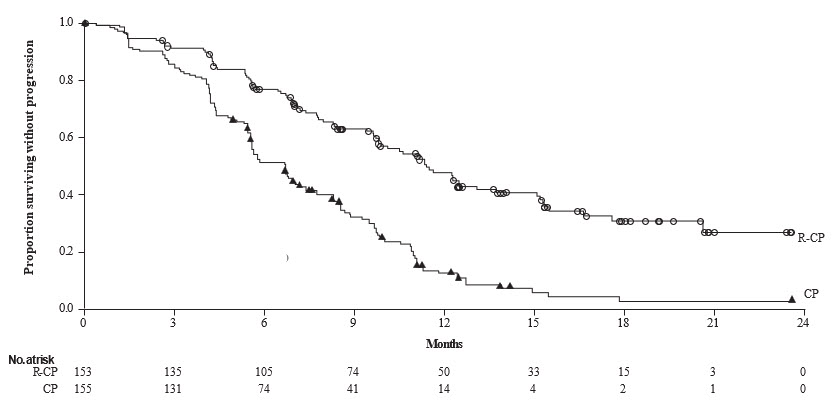
RYBREVANT in combination with lazertinib can cause infusion-related reactions. In MARIPOSA,
[see
Adverse Reactions (6.1)]
, IRRs occurred in 63% of patients treated with RYBREVANT in combination with lazertinib, including Grade 3 in 5% and Grade 4 in 1% of patients. The incidence of infusion modifications due to IRR was 54%, and IRRs leading to dose reduction of RYBREVANT occurred in 0.7% of patients. Infusion-related reactions leading to permanent discontinuation of RYBREVANT occurred in 4.5% of patients receiving RYBREVANT in combination with lazertinib.
Premedicate with antihistamines, antipyretics, and glucocorticoids and infuse RYBREVANT as recommended
[see
Dosage and Administration (2.5)]
. Administer RYBREVANT via a peripheral line on Week 1 and Week 2 to reduce the risk of infusion-related reactions
[see
Dosage and Administration (2.10)]
.
Monitor patients for new or worsening symptoms indicative of ILD/pneumonitis (e.g., dyspnea, cough, fever). Immediately withhold RYBREVANT in patients with suspected ILD/pneumonitis and permanently discontinue if ILD/pneumonitis is confirmed
[see
Dosage and Administration (2.8)]
.
Toxic epidermal necrolysis (TEN) occurred in one patient (0.3%) treated with RYBREVANT as a single agent.
Promptly refer patients with new or worsening eye symptoms to an ophthalmologist. Withhold, reduce the dose, or permanently discontinue RYBREVANT based on severity
[see
Dosage and Administration (2.8)]
.
The data described in the WARNINGS AND PRECAUTIONS reflect exposure to RYBREVANT in combination with lazertinib in the MARIPOSA study in 421 patients with previously untreated locally advanced or metastatic NSCLC whose tumors have EGFR exon 19 deletions or exon 21 L858R substitution mutations
[see
Clinical Studies (14.1)]
. Patients received RYBREVANT intravenously at 1,050 mg (for patients < 80 kg) or 1,400 mg (for patients ≥ 80 kg) once weekly for 4 weeks, then every 2 weeks thereafter starting at week 5 in combination with lazertinib, 240 mg orally once daily, until disease progression or unacceptable toxicity. Among 421 patients who received RYBREVANT in combination with lazertinib, 73% were exposed for 6 months or longer and 59% were exposed for greater than one year. The most common adverse reactions (≥ 20%) were rash, nail toxicity, infusion-related reaction, edema, musculoskeletal pain, stomatitis, VTE, paresthesia, fatigue, diarrhea, constipation, COVID-19, dry skin, hemorrhage, decreased appetite, pruritus, and nausea. The most common Grade 3 or 4 laboratory abnormalities (≥ 2%) were decreased albumin, increased ALT, decreased sodium, decreased hemoglobin, increased AST, increased GGT and increased magnesium.
The pooled safety population described in the WARNINGS AND PRECAUTIONS also reflect exposure to RYBREVANT in combination with carboplatin and pemetrexed in 281 patients in two studies:
- MARIPOSA-2
[see
Clinical Studies (14.2)]
in 130 patients with previously treated locally advanced or metastatic NSCLC with EGFR exon 19 deletions or exon 21 L858R substitution mutations whose disease has progressed on or after treatment with osimertinib.
- PAPILLON
[see
Clinical Studies (14.3)]
in 151 patients with previously untreated, locally advanced or metastatic NSCLC with EGFR exon 20 insertion mutations.
Patients received RYBREVANT intravenously at 1,400 mg (for patients < 80 kg) or 1,750 mg (for patients ≥ 80 kg) once weekly through 4 weeks, then every 3 weeks with a dose of 1,750 mg (for patients < 80 kg) or 2,100 mg (for patients ≥ 80 kg) starting at Week 7 until disease progression or unacceptable toxicity, in combination with carboplatin at area under the curve AUC 5 once every 3 weeks, for up to 12 weeks, and pemetrexed at 500 mg/m2 once every 3 weeks until disease progression or unacceptable toxicity. Among 281 patients who received RYBREVANT in combination with carboplatin and pemetrexed, 65% were exposed for 6 months or longer and 24% were exposed for greater than one year. In the safety population, the most common (≥ 20%) adverse reactions were rash, nail toxicity, infusion-related reaction, fatigue, nausea, stomatitis, constipation, edema, decreased appetite, musculoskeletal pain, vomiting, and COVID-19. The most common Grade 3 to 4 laboratory abnormalities (≥ 2%) were decreased neutrophils, decreased leukocytes, decreased platelets, decreased hemoglobin, decreased potassium, decreased sodium, increased alanine aminotransferase, increased gamma-glutamyl transferase, and decreased albumin.
RYBREVANT as a Single Agent
The data in the WARNINGS AND PRECAUTIONS also reflect exposure to RYBREVANT as a single agent in CHRYSALIS
[see
Clinical Studies (14.4)]
in 302 patients with locally advanced or metastatic NSCLC. Patients received RYBREVANT at 1,050 mg (for patient baseline body weight < 80 kg) or 1,400 mg (for patient baseline body weight ≥ 80 kg) once weekly for 4 weeks, then every 2 weeks thereafter until disease progression or unacceptable toxicity. Among 302 patients who received RYBREVANT as a single agent, 36% were exposed for 6 months or longer and 12% were exposed for greater than one year. In the safety population, the most common (≥ 20%) adverse reactions were rash, infusion-related reaction, paronychia, musculoskeletal pain, dyspnea, nausea, edema, cough, fatigue, stomatitis, constipation, vomiting and pruritus. The most common Grade 3 to 4 laboratory abnormalities (≥ 2%) were increased gamma glutamyl transference, decreased sodium, decreased potassium and increased alkaline phosphatase.
First-line Treatment of NSCLC with Exon 19 deletions or Exon 21 L858R substitution mutations
The safety data described below reflect exposure to RYBREVANT in combination with lazertinib in 421 previously untreated patients with locally advanced or metastatic NSCLC whose tumors have EGFR exon 19 deletions or exon 21 L858R substitution mutation in the MARIPOSA
[see
Clinical Studies (14.1)].
Patients received RYBREVANT intravenously at 1,050 mg (for patients < 80 kg) or 1,400 mg (for patients ≥ 80 kg) once weekly for 4 weeks, then every 2 weeks thereafter starting at week 5 in combination with lazertinib, 240 mg orally once daily. Among the 421 patients who received RYBREVANT in combination with lazertinib, 73% were exposed to RYBREVANT for ≥ 6 months and 59% were exposed to RYBREVANT for > 1 year.
The median age of patients who received RYBREVANT in combination with lazertinib was 64 years (range: 25 to 88); 64% were female; 59% were Asian, 38% were White, 1.7% were American Indian or Alaska Native, 0.7% were Black or African American, 1% were of unknown or other races; and 13% were Hispanic or Latino, 67% had Eastern Cooperative Oncology Group (ECOG) performance status (PS) of 1, 33% had ECOG PS of 0, 60% had EGFR exon 19 deletions, and 40% had EGFR exon 21 L858R substitution mutations.
Serious adverse reactions occurred in 49% of patients who received RYBREVANT in combination with lazertinib. Serious adverse reactions occurring in ≥ 2% of patients included VTE (11%), pneumonia (4%), rash, and ILD/pneumonitis (2.9% each), COVID-19 (2.4%), pleural effusion and infusion-related reaction (2.1% each). Fatal adverse reactions occurred in 7% of patients who received RYBREVANT in combination with lazertinib due to death not otherwise specified (1.2%); sepsis and respiratory failure (1% each); pneumonia, myocardial infarction and sudden death (0.7% each); cerebral infarction, pulmonary embolism (PE), and COVID-19 infection (0.5% each); and ILD/pneumonitis, acute respiratory distress syndrome (ARDS), and cardiopulmonary arrest (0.2% each).
Permanent discontinuation of RYBREVANT due to an adverse reaction occurred in 34% of patients. Adverse reactions which resulted in permanent discontinuation in ≥ 1% of patients included rash, infusion-related reactions, nail toxicity, VTE, ILD/pneumonitis, pneumonia, edema, hypoalbuminemia, fatigue, paresthesia and dyspnea.
Dosage interruption of RYBREVANT due to an adverse reaction occurred in 88% of patients. Adverse reactions which required dosage interruption in ≥ 5% of patients were infusion-related reactions, rash, nail toxicity, COVID-19, VTE, increased ALT, edema, and hypoalbuminemia.
Dose reductions of RYBREVANT due to an adverse reaction occurred in 46% of patients. Adverse reactions requiring dose reductions in ≥ 5% of patients were rash and nail toxicity.
The most common adverse reactions (≥ 20%) were rash, nail toxicity, infusion-related reaction, musculoskeletal pain, stomatitis, edema, VTE, paresthesia, fatigue, diarrhea, constipation, COVID-19, hemorrhage, dry skin, decreased appetite, pruritus, and nausea. The most common Grade 3 or 4 laboratory abnormalities (≥ 2%) were decreased albumin, decreased sodium, increased ALT, decreased potassium, decreased hemoglobin, increased AST, increased GGT, and increased magnesium.
Table 10 summarizes the adverse reactions (≥ 10%) in MARIPOSA.
Table 10: Adverse Reactions (≥ 10%) in Patients with NSCLC with Exon 19 Deletion or Exon 21 L858R Substitution Mutations in MARIPOSA| Adverse Reaction | RYBREVANT in combination with lazertinib
(N=421)
| Osimertinib
(N=428)
|
|---|
All Grades
(%)
| Grade 3 or 4
(%)
| All Grades
(%)
| Grade 3 or 4
(%)
|
|---|
| Skin and subcutaneous tissue disorders |
| Rash
Grouped terms | 86 | 26 | 48 | 1.2 |
| Nail toxicity
| 71 | 11 | 34 | 0.7 |
| Dry skin
| 25 | 1 | 18 | 0.2 |
| Pruritus | 24 | 0.5 | 17 | 0.2 |
| Injury, poisoning and procedural complications |
| Infusion-related reaction
Applicable for RYBREVANT only | 63 | 6 | 0 | 0 |
| Musculoskeletal and connective tissue disorders |
| Musculoskeletal pain
| 47 | 2.1 | 39 | 1.9 |
| Gastrointestinal disorders |
| Stomatitis
| 43 | 2.4 | 27 | 0.5 |
| Diarrhea
| 31 | 2.6 | 45 | 0.9 |
| Constipation | 29 | 0 | 13 | 0 |
| Nausea | 21 | 1.2 | 14 | 0.2 |
| Vomiting | 12 | 0.5 | 5 | 0 |
| Abdominal pain
| 11 | 0 | 10 | 0 |
| Hemorrhoids | 10 | 0.2 | 2.1 | 0.2 |
| General disorders and administration site conditions |
| Edema
| 43 | 2.6 | 8 | 0 |
| Fatigue
| 32 | 3.8 | 20 | 1.9 |
| Pyrexia | 12 | 0 | 9 | 0 |
| Vascular disorders |
| Venous thromboembolism
| 36 | 11 | 8 | 2.8 |
| Hemorrhage
| 25 | 1 | 13 | 1.2 |
| Nervous system disorders |
| Paresthesia
| 35 | 1.7 | 10 | 0.2 |
| Dizziness
| 14 | 0 | 10 | 0 |
| Headache
| 13 | 0.2 | 13 | 0 |
| Infections and infestations |
| COVID-19 | 26 | 1.7 | 24 | 1.4 |
| Conjunctivitis | 11 | 0.2 | 1.6 | 0 |
| Metabolism and nutrition disorders |
| Decreased appetite | 24 | 1 | 18 | 1.4 |
| Respiratory, thoracic and mediastinal disorders |
| Cough
| 19 | 0 | 23 | 0 |
| Dyspnea
| 14 | 1.7 | 17 | 3.5 |
| Eye disorders |
| Ocular toxicity
| 16 | 0.7 | 7 | 0 |
| Psychiatric disorders |
| Insomnia | 10 | 0 | 11 | 0 |
Clinically relevant adverse reactions in < 10% of patients who received RYBREVANT in combination with lazertinib included skin ulcer and ILD/pneumonitis.
Table 11 summarizes the laboratory abnormalities in MARIPOSA.
Table 11: Select Laboratory Abnormalities (≥ 20%) That Worsened from Baseline in Patients with NSCLC with EGFR Exon 19 Deletion or Exon 21 L858R Substitution Mutations in MARIPOSA
The denominator used to calculate the rate is the number of patients with a baseline value and at least one post-treatment value for the specific lab test.
| RYBREVANT in combination with lazertinib
(N=421)
| Osimertinib
(N=428)
|
|---|
| Laboratory Abnormality | All Grades
(%)
| Grade 3 or 4
(%)
| All Grades
(%)
| Grade 3 or 4
(%)
|
|---|
| Chemistry |
| Decreased albumin | 89 | 8 | 22 | 0.2 |
| Increased ALT | 65 | 7 | 29 | 2.6 |
| Increased AST | 52 | 3.8 | 36 | 1.9 |
| Increased alkaline phosphatase | 45 | 0.5 | 15 | 0.5 |
| Decreased calcium (corrected) | 41 | 1.4 | 27 | 0.7 |
| Increased GGT | 39 | 2.6 | 24 | 1.9 |
| Decreased sodium | 38 | 7 | 35 | 5 |
| Decreased potassium | 30 | 5 | 15 | 1.2 |
| Increased creatinine | 26 | 0.7 | 35 | 0.7 |
| Decreased magnesium | 25 | 0.7 | 10 | 0.2 |
| Increased magnesium | 12 | 2.6 | 20 | 4.8 |
| Hematology |
| Decreased platelet count | 52 | 0.7 | 57 | 1.4 |
| Decreased hemoglobin | 47 | 3.8 | 56 | 1.9 |
| Decreased white blood cell | 38 | 1 | 66 | 0.7 |
| Decreased neutrophils | 15 | 1.4 | 33 | 1.4 |
Previously Treated Non-Small Cell Lung Cancer (NSCLC) with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations
The safety data described below reflect exposure to RYBREVANT in combination with carboplatin and pemetrexed was evaluated in MARIPOSA-2
[see
Clinical Studies (14.2)].
Eligible patients had locally advanced or metastatic NSCLC with EGFR exon 19 deletions or exon 21 L858R substitution mutations with progressive disease on or after treatment with osimertinib
. Patients with asymptomatic or previously treated and stable intracranial metastases were eligible. Patients received RYBREVANT intravenously at 1,400 mg (for patients < 80 kg) or 1,750 mg (for patients ≥ 80 kg) once weekly through 4 weeks, then every 3 weeks with a dose of 1,750 mg (for patients < 80 kg) or 2,100 mg (for patients ≥ 80 kg) starting at Week 7 until disease progression or unacceptable toxicity, in combination with carboplatin at area under the curve AUC 5 once every 3 weeks, for up to 12 weeks, and pemetrexed at 500 mg/m2 once every 3 weeks until disease progression or unacceptable toxicity. Among patients who received RYBREVANT (n=130), 52% were exposed for 6 months or longer and 7% were exposed for greater than one year. The median treatment duration was 6.3 months (range: 0 to 14.7 months).
The median age was 62 years (range: 36 to 84 years); 62% were female; 48% were Asian, 46% were White, 2.3% Black or African American, 1.5% race not reported, 1.5% race unknown, 0.8% Alaska native; 7% were Hispanic or Latino; and 87% had baseline body weight < 80 kg.
Serious adverse reactions occurred in 32% of patients who received RYBREVANT in combination with carboplatin and pemetrexed. Serious adverse reactions in > 2% of patients included dyspnea (3.1%), thrombocytopenia (3.1%), sepsis (2.3%), and pulmonary embolism (2.3%). Fatal adverse reactions occurred in 2.3% of patients who received RYBREVANT in combination with carboplatin and pemetrexed; these included respiratory failure, sepsis, and ventricular fibrillation (0.8% each).
Permanent discontinuation of RYBREVANT due to adverse reactions occurred in 11% of patients. The most frequent adverse reactions leading to discontinuation of RYBREVANT in ≥ 5% of patients were infusion-related reactions.
Dose interruptions of RYBREVANT due to an adverse reaction occurred in 60% of patients. Infusion-related reactions (IRR) requiring infusion interruptions occurred in 52% of patients. Adverse reactions requiring dose interruption in ≥ 5% of patients included infusion-related reaction, rash and fatigue.
Dose reductions of RYBREVANT due to an adverse reaction occurred in 17% of patients. Adverse reactions requiring dose reductions in ≥ 2% of patients included rash.
The most common adverse reactions ≥ 20% were rash, infusion-related reactions, fatigue, nail toxicity, nausea, constipation, edema, stomatitis, decreased appetite, musculoskeletal pain, vomiting, and COVID-19.
Table 12 summarizes the adverse reactions in MARIPOSA-2.
Table 12: Adverse Reactions (≥ 10%) in Previously Treated Patients with NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations Treated with RYBREVANT in Combination with Carboplatin and Pemetrexed in MARIPOSA-2| Adverse Reaction | RYBREVANT + Carboplatin + Pemetrexed | Carboplatin + Pemetrexed |
|---|
| (N=130) | (N=243) |
|---|
| All Grades (%) | Grade 3 or 4
(%)
| All Grades
(%)
| Grade 3 or 4
(%)
|
|---|
| Skin and subcutaneous tissue disorders |
| Rash
Grouped term | 72 | 11 | 12 | 0 |
| Nail toxicity
| 45 | 2.3 | 0.4 | 0 |
| Pruritus | 15 | 0 | 7 | 0 |
| Dry skin
| 15 | 0 | 2.5 | 0 |
| General disorders and administration site conditions |
| Infusion-related reaction | 59 | 5.4 | 0.4 | 0 |
| Fatigue
| 51 | 3.8 | 35 | 3.7 |
| Edema
| 36 | 1.5 | 11 | 0.4 |
| Pyrexia | 12 | 0 | 10 | 0 |
| Gastrointestinal disorders |
| Nausea | 45 | 0.8 | 37 | 0.8 |
| Constipation | 39 | 0.8 | 30 | 0 |
| Stomatitis
| 35 | 2.3 | 11 | 0 |
| Vomiting | 25 | 0.8 | 17 | 0.4 |
| Diarrhea
| 15 | 1.5 | 7 | 0.8 |
| Metabolism and nutrition disorders |
| Decreased appetite | 31 | 0 | 21 | 1.2 |
| Musculoskeletal and connective tissue disorders |
| Musculoskeletal pain
| 30 | 3.1 | 19 | 0.8 |
| Infections and infestations |
| COVID-19 | 21 | 1.5 | 10 | 0 |
| Eye disorders |
| Ocular toxicity
| 17 | 0 | 3.7 | 0 |
| Vascular disorders |
| Hemorrhage
| 14 | 0.8 | 4.9 | 0 |
| Venous Thromboembolism
(VTE)
| 10 | 2.3 | 4.5 | 2.9 |
| Respiratory, thoracic and mediastinal disorders |
| Cough
| 14 | 0 | 16 | 0.4 |
| Dyspnea
| 13 | 1.5 | 8 | 1.2 |
Clinically relevant adverse reactions in < 10% of patients who received RYBREVANT in combination with carboplatin and pemetrexed include: abdominal pain, hemorrhoids, dizziness, visual impairment, trichomegaly, keratitis, interstitial lung disease, and skin ulcer.
Table 13 summarizes the laboratory abnormalities in MARIPOSA-2.
Table 13: Select Laboratory Abnormalities (≥ 20%) That Worsened from Baseline in Patients with NSCLC with EGFR Exon 19 Deletions or Exon 21 L858R Substitution Mutations Treated with RYBREVANT in Combination with Carboplatin and Pemetrexed in MARIPOSA-2 | RYBREVANT + Carboplatin + Pemetrexed
(N=130)
| Carboplatin + Pemetrexed
(N=243)
|
|---|
| Laboratory Abnormality | All Grades
(%)
| Grade 3 or 4
(%)
| All Grades
(%)
| Grade 3 or 4
(%)
|
|---|
| Hematology |
| Decreased white blood cells | 91 | 42 | 85 | 19 |
| Decreased neutrophils | 74 | 49 | 64 | 25 |
| Decreased platelets | 74 | 17 | 58 | 9 |
| Decreased hemoglobin | 71 | 12 | 77 | 9 |
| Decreased lymphocytes | 69 | 28 | 58 | 18 |
| Chemistry |
| Decreased albumin | 73 | 3.8 | 26 | 0.4 |
| Decreased sodium | 49 | 11 | 30 | 6 |
| Increased aspartate aminotransferase | 47 | 0.8 | 52 | 0.9 |
| Increased alkaline phosphatase | 42 | 0 | 29 | 0.4 |
| Increased alanine aminotransferase | 39 | 3.9 | 56 | 6 |
| Decreased magnesium | 38 | 0.8 | 17 | 0.4 |
| Decreased potassium | 37 | 11 | 12 | 3.4 |
| Increased gamma-glutamyl transferase | 30 | 3.1 | 41 | 1.3 |
| Decreased calcium (corrected) | 25 | 0 | 11 | 0.9 |
First-line Treatment of Non-Small Cell Lung Cancer (NSCLC) with Exon 20 Insertion Mutations
The safety data described below reflect exposure to RYBREVANT in combination with carboplatin and pemetrexed at the recommended dosage in the PAPILLON trial
[see
Clinical Studies (14.3)]
in 151 patients with locally advanced or metastatic NSCLC with EGFR exon 20 insertion mutations. Among patients who received RYBREVANT in combination with carboplatin and pemetrexed the median exposure was 9.7 months (range: 0.0 to 26.9 months). In patients that received carboplatin and pemetrexed alone, the median exposure was 6.7 months (range 0.0 to 25.3).
The median age was 61 years (range: 27 to 86 years); 56% were female; 64% were Asian, 32% were White, 1.3% were Black or African American, race was not reported in 1.3% of patients; 89% were not Hispanic or Latino; 86% had baseline body weight < 80 kg.
Serious adverse reactions occurred in 37% of patients who received RYBREVANT in combination with carboplatin and pemetrexed. Serious adverse reactions in ≥ 2% of patients included rash, pneumonia, interstitial lung disease (ILD), pulmonary embolism, vomiting, and COVID-19. Fatal adverse reactions occurred in 7 patients (4.6%) due to pneumonia, cerebrovascular accident, cardio-respiratory arrest, COVID-19, sepsis, and death not otherwise specified.
Permanent discontinuation of RYBREVANT due to an adverse reaction occurred in 11% of patients. Adverse reactions resulting in permanent discontinuation of RYBREVANT in ≥ 1% of patients were rash and ILD.
Dose interruptions of RYBREVANT due to an adverse reaction occurred in 64% of patients. Infusion-related reactions (IRR) requiring infusion interruptions occurred in 38% of patients. Adverse reactions requiring dose interruption in ≥ 5% of patients included rash and nail toxicity.
Dose reductions of RYBREVANT due to an adverse reaction occurred in 36% of patients. Adverse reactions requiring dose reductions in ≥ 5% of patients included rash and nail toxicity.
The most common adverse reactions (≥ 20%) were rash, nail toxicity, stomatitis, infusion-related reaction, fatigue, edema, constipation, decreased appetite, nausea, COVID-19, diarrhea, and vomiting. The most common Grade 3 to 4 laboratory abnormalities (≥ 2%) were decreased albumin, increased alanine aminotransferase, increased gamma-glutamyl transferase, decreased sodium, decreased potassium, decreased magnesium, and decreases in white blood cells, hemoglobin, neutrophils, platelets, and lymphocytes.
Table 14 summarizes the adverse reactions in PAPILLON.
Table 14: Adverse Reactions (≥ 10%) in Patients with Metastatic NSCLC with Exon 20 Insertion Mutations Who Received RYBREVANT in Combination with Carboplatin and Pemetrexed in PAPILLON | RYBREVANT in Combination with Carboplatin and Pemetrexed
(n=151)
| Carboplatin and Pemetrexed
(n=155)
|
|---|
| Adverse Reaction
Adverse reactions were graded using CTCAE version 5.0. | All Grades
(%)
| Grade 3 or 4
(%)
| All Grades
(%)
| Grade 3 or 4
(%)
|
|---|
| Skin and subcutaneous tissue disorders |
| Rash
Grouped Term | 90 | 19 | 19 | 0 |
| Nail toxicity
| 62 | 7 | 3 | 0 |
| Dry skin
| 17 | 0 | 6 | 0 |
| Gastrointestinal disorders |
| Stomatitis
| 43 | 4 | 11 | 0 |
| Constipation | 40 | 0 | 30 | 0.7 |
| Nausea | 36 | 0.7 | 42 | 0 |
| Vomiting | 21 | 3.3 | 19 | 0.7 |
| Diarrhea | 21 | 3 | 13 | 1.3 |
| Hemorrhoids | 12 | 1 | 1.3 | 0 |
| Abdominal pain
| 11 | 0.7 | 8 | 0 |
| General disorders and administration site conditions |
| Infusion-related reaction | 42 | 1.3 | 1.3 | 0 |
| Fatigue
| 42 | 6 | 45 | 3.9 |
| Edema
| 40 | 1.3 | 19 | 0 |
| Pyrexia
| 17 | 0 | 6 | 0 |
| Metabolism and nutrition disorders |
| Decreased appetite | 36 | 2.6 | 28 | 1.3 |
| Infections and infestations |
| COVID-19 | 24 | 2 | 14 | 0.6 |
| Pneumonia
| 13 | 5 | 6 | 1.9 |
| Vascular disorders |
| Hemorrhage
| 18 | 0.7 | 11 | 1.9 |
| Respiratory, thoracic, and mediastinal disorders |
| Cough
| 17 | 0 | 16 | 0 |
| Dyspnea
| 11 | 1.3 | 16 | 3.2 |
| Investigations |
| Weight decreased | 14 | 0.7 | 8 | 0 |
| Nervous system disorders |
| Dizziness
| 11 | 0 | 12 | 0 |
| Psychiatric disorders |
| Insomnia | 11 | 0 | 13 | 0 |
Clinically relevant adverse reactions in < 10% of patients who received RYBREVANT in combination with carboplatin and pemetrexed included pulmonary embolism, deep vein thrombosis, skin ulcer, conjunctivitis, and interstitial lung disease (ILD)/pneumonitis.
Table 15 summarizes the laboratory abnormalities in PAPILLON.
Table 15: Select Laboratory Abnormalities (≥ 20%) That Worsened from Baseline in Patients with Metastatic NSCLC with EGFR Exon 20 Insertion Mutations Who Received RYBREVANT in Combination with Carboplatin and Pemetrexed in PAPILLON | RYBREVANT in Combination with Carboplatin and Pemetrexed
The denominator used to calculate the rate varied from 113 to 150 based on the number of patients with a baseline value and at least one post-treatment value. | Carboplatin in Combination with Pemetrexed
The denominator used to calculate the rate varied from 119 to 154 based on the number of patients with a baseline value and at least one post-treatment value. |
|---|
| Laboratory Abnormality
Adverse reactions were graded using CTCAE version 5.0 | All Grades
(%)
| Grade 3 or 4
(%)
| All Grades
(%)
| Grade 3 or 4
(%)
|
|---|
| Hematology |
| Decreased white blood cells | 89 | 17 | 76 | 10 |
| Decreased hemoglobin | 79 | 11 | 85 | 13 |
| Decreased neutrophils | 76 | 36 | 61 | 23 |
| Decreased platelets | 70 | 10 | 54 | 12 |
| Decreased lymphocytes | 61 | 11 | 49 | 13 |
| Chemistry |
| Decreased albumin | 87 | 7 | 34 | 1 |
| Increased aspartate aminotransferase | 60 | 1 | 61 | 1 |
| Increased alanine aminotransferase | 57 | 4 | 54 | 1 |
| Decreased sodium | 55 | 7 | 39 | 4 |
| Increased alkaline phosphatase | 51 | 1 | 28 | 0 |
| Decreased potassium | 44 | 11 | 17 | 1 |
| Decreased magnesium | 39 | 2 | 30 | 1 |
| Increased gamma-glutamyl transferase | 38 | 4 | 43 | 4 |
| Decreased calcium (corrected) | 27 | 1 | 18 | 1 |
Previously Treated NSCLC Exon 20 Insertion Mutations
The safety data described below reflect exposure to RYBREVANT at the recommended dosage in 129 patients with locally advanced or metastatic NSCLC with EGFR exon 20 insertion mutations in the CHRYSALIS trial
[see
Clinical Studies (14.4)],
whose disease had progressed on or after platinum-based chemotherapy. Among patients who received RYBREVANT, 44% were exposed for 6 months or longer and 12% were exposed for greater than one year.
The median age was 62 years (range: 36 to 84 years); 61% were female; 55% were Asian, 35% were White, and 2.3% were Black; and 82% had baseline body weight < 80 kg.
Serious adverse reactions occurred in 30% of patients who received RYBREVANT. Serious adverse reactions in ≥ 2% of patients included pulmonary embolism, pneumonitis/ILD, dyspnea, musculoskeletal pain, pneumonia, and muscular weakness. Fatal adverse reactions occurred in 2 patients (1.5%) due to pneumonia and 1 patient (0.8%) due to sudden death.
Permanent discontinuation of RYBREVANT due to an adverse reaction occurred in 11% of patients. Adverse reactions resulting in permanent discontinuation of RYBREVANT in ≥ 1% of patients were pneumonia, IRR, pneumonitis/ILD, dyspnea, pleural effusion, and rash.
Dose interruptions of RYBREVANT due to an adverse reaction occurred in 78% of patients. Infusion-related reactions (IRR) requiring infusion interruptions occurred in 59% of patients. Adverse reactions requiring dose interruption in ≥ 5% of patients included dyspnea, nausea, rash, vomiting, fatigue, and diarrhea.
Dose reductions of RYBREVANT due to an adverse reaction occurred in 15% of patients. Adverse reactions requiring dose reductions in ≥ 2% of patients included rash and paronychia.
The most common adverse reactions (≥ 20%) were rash, IRR, paronychia, musculoskeletal pain, dyspnea, nausea, fatigue, edema, stomatitis, cough, constipation, and vomiting. The most common Grade 3 to 4 laboratory abnormalities (≥ 2%) were decreased lymphocytes, decreased albumin, decreased phosphate, decreased potassium, increased glucose, increased alkaline phosphatase, increased gamma-glutamyl transferase, and decreased sodium.
Table 16 summarizes the adverse reactions in CHRYSALIS.
Table 16: Adverse Reactions (≥ 10%) in Patients with NSCLC with Exon 20 Insertion Mutations Whose Disease Has Progressed on or after Platinum-based Chemotherapy and Received RYBREVANT in CHRYSALIS| Adverse Reactions | RYBREVANT
Adverse reactions were graded using CTCAE version 4.03
(N=129)
|
|---|
| All Grades (%) | Grades 3 or 4 (%) |
|---|
| Skin and subcutaneous tissue disorders |
| Rash
Grouped term | 84 | 3.9 |
| Pruritus | 18 | 0 |
| Dry skin | 14 | 0 |
| General disorders and administration site conditions |
| Infusion-related reaction | 64 | 3.1 |
| Fatigue
| 33 | 2.3 |
| Edema
| 27 | 0.8 |
| Pyrexia | 13 | 0 |
| Infections and infestations |
| Paronychia | 50 | 3.1 |
| Pneumonia
| 10 | 0.8 |
| Musculoskeletal and connective tissue disorders |
| Musculoskeletal pain
| 47 | 0 |
| Respiratory, thoracic, and mediastinal disorders |
| Dyspnea
| 37 | 2.3 |
| Cough
| 25 | 0 |
| Gastrointestinal disorders |
| Nausea | 36 | 0 |
| Stomatitis
| 26 | 0.8 |
| Constipation | 23 | 0 |
| Vomiting | 22 | 0 |
| Diarrhea | 16 | 3.1 |
| Abdominal Pain
| 11 | 0.8 |
| Vascular disorders |
| Hemorrhage
| 19 | 0 |
| Metabolism and nutrition disorders |
| Decreased appetite | 15 | 0 |
| Nervous system disorders |
| Peripheral neuropathy
| 13 | 0 |
| Dizziness | 12 | 0.8 |
| Headache
| 10 | 0.8 |
Clinically relevant adverse reactions in < 10% of patients who received RYBREVANT included ocular toxicity, ILD/pneumonitis, and toxic epidermal necrolysis (TEN).
Table 17 summarizes the laboratory abnormalities in CHRYSALIS.
Table 17: Select Laboratory Abnormalities (≥ 20%) That Worsened from Baseline in Patients With Metastatic NSCLC with EGFR Exon 20 Insertion Mutations Whose Disease Has Progressed on or After Platinum-based Chemotherapy and Who Received RYBREVANT in CHRYSALIS| Laboratory Abnormality | RYBREVANT
The denominator used to calculate the rate was 126 based on the number of patients with a baseline value and at least one post-treatment value.
(N=129)
|
|---|
All Grades
(%)
| Grades 3 or 4
(%)
|
|---|
| Chemistry | | |
| Decreased albumin | 79 | 8 |
| Increased glucose | 56 | 4 |
| Increased alkaline phosphatase | 53 | 4.8 |
| Increased creatinine | 46 | 0 |
| Increased alanine aminotransferase | 38 | 1.6 |
| Decreased phosphate | 33 | 8 |
| Increased aspartate aminotransferase | 33 | 0 |
| Decreased magnesium | 27 | 0 |
| Increased gamma-glutamyl transferase | 27 | 4 |
| Decreased sodium | 27 | 4 |
| Decreased potassium | 26 | 6 |
| Hematology | | |
| Decreased lymphocytes | 36 | 8 |
Risk Summary
Based on the mechanism of action and findings in animal models, RYBREVANT can cause fetal harm when administered to a pregnant woman. There are no available data on the use of RYBREVANT in pregnant women or animal data to assess the risk of RYBREVANT in pregnancy. Disruption or depletion of EGFR in animal models resulted in impairment of embryo-fetal development including effects on placental, lung, cardiac, skin, and neural development. The absence of EGFR or MET signaling has resulted in embryo lethality, malformations, and post-natal death in animals
(see
Data).
Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
No animal studies have been conducted to evaluate the effects of amivantamab-vmjw on reproduction and fetal development; however, based on its mechanism of action, RYBREVANT can cause fetal harm or developmental anomalies. In mice, EGFR is critically important in reproductive and developmental processes including blastocyst implantation, placental development, and embryo-fetal/postnatal survival and development. Reduction or elimination of embryo-fetal or maternal EGFR signaling can prevent implantation, can cause embryo-fetal loss during various stages of gestation (through effects on placental development) and can cause developmental anomalies and early death in surviving fetuses. Adverse developmental outcomes were observed in multiple organs in embryos/neonates of mice with disrupted EGFR signaling. Similarly, knock out of MET or its ligand HGF was embryonic lethal due to severe defects in placental development, and fetuses displayed defects in muscle development in multiple organs. Human IgG1 is known to cross the placenta; therefore, amivantamab-vmjw has the potential to be transmitted from the mother to the developing fetus.
Risk Summary
There are no data on the presence of amivantamab-vmjw in human milk, the effects on the breastfed child or on milk production. Because of the potential for serious adverse reactions from RYBREVANT in breast-fed children, advise women not to breastfeed during treatment with RYBREVANT and for 3 months after the last dose.
Pregnancy Testing
Verify pregnancy status of females of reproductive potential prior to initiating RYBREVANT.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment and for 3 months after the last dose of RYBREVANT.
Distribution
The amivantamab-vmjw mean (%CV) volume of distribution is 5 (24%) L.
Elimination
The mean (% CV) linear clearance (CL) is 0.26 L/day (30%) and mean terminal half-life is 14 days (33%).
Specific Populations
No clinically meaningful differences in the pharmacokinetics of amivantamab-vmjw were observed based on age (range: 21–88 years), body weight (31 to 140 kg), sex, race (White, Asian or Black or African American) and ethnicity (Hispanic/Latino or not Hispanic/Latino), mild or moderate renal impairment (eGFR 30 to 89 mL/min) or mild hepatic impairment [(total bilirubin ≤ ULN and AST > ULN) or (ULN < total bilirubin ≤ 1.5 times ULN)]. The effect of severe renal impairment (eGFR 15 to 29 mL/min), end-stage renal disease (eGFR < 15 mL/min) or moderate to severe hepatic impairment (total bilirubin > 1.5 times ULN and any AST) on amivantamab-vmjw pharmacokinetics has not been studied.
Body Weight
Increases in body weight increased the volume of distribution and clearance of amivantamab-vmjw. Amivantamab-vmjw exposures are 30 to 40% lower in patients who weighed ≥ 80 kg compared to patients with body weight < 80 kg at the same dose. Exposures of amivantamab-vmjw were comparable between patients who weighed < 80 kg and received 1,050 mg dose and patients who weighed ≥ 80 kg and received 1,400 mg dose.
How Supplied
RYBREVANT® (amivantamab-vmjw) injection is a sterile, preservative-free, colorless to pale yellow solution for intravenous infusion. Each single-dose vial contains 350 mg/7 mL (50 mg/mL) RYBREVANT. Each vial is individually packed in a single carton. (NDC 57894-501-01).
Infusion-Related Reactions
Advise patients that RYBREVANT can cause infusion-related reactions (IRR), including anaphylaxis. Instruct patients to take glucocorticoids 48 hours prior to the first RYBREVANT infusion to reduce the risk of IRR
[see
Dosage and Administration (2.5)].
The majority of infusion-related reactions occurred with the first infusion. Advise patients to alert their healthcare provider immediately for any signs or symptoms of infusion-related reactions
[see
Warnings and Precautions (5.1)]
.
Interstitial Lung Disease/Pneumonitis
Advise patients of the risks of interstitial lung disease (ILD)/pneumonitis. Advise patients to immediately contact their healthcare provider for new or worsening respiratory symptoms
[see
Warnings and Precautions (5.2)]
.
Venous Thromboembolic Events with Concomitant Use with Lazertinib
When RYBREVANT is used in combination with lazertinib, advise patients of the risks of serious and life threatening venous thromboembolic (VTE) events, including deep venous thrombosis and pulmonary embolism. Advise patients that prophylactic anticoagulants are recommended to be used for the first four months of treatment. Advise patients to immediately contact their healthcare provider for signs and symptoms of venous thromboembolism
[see
Warnings and Precautions (5.3)]
.
Dermatologic Adverse Reactions
Advise patients of the risk of dermatologic adverse reactions. Advise patients that prophylactic oral antibiotics are recommended starting on Day 1 for the first 12 weeks of treatment and, after completion of oral antibiotic treatment, topical antibiotic lotion to the scalp for the next 9 months of treatment. Advise patients to use a non-comedogenic skin moisturizer (ceramide-based or other formulations that provide long-lasting skin hydration and exclude drying components) on the face and whole body (except scalp) and 4% chlorhexidine solution to wash hands and feet, while on treatment. Advise patients to limit direct sun exposure during and for 2 months after treatment, to wear protective clothing, and to use broad-spectrum UVA/UVB sunscreen to reduce the risk and severity of dermatologic adverse reactions
[see
Warnings and Precautions (5.4)]
.
Ocular Toxicity
Advise patients of the risk of ocular toxicity. Advise patients to contact their ophthalmologist if they develop eye symptoms and advise discontinuation of contact lenses until symptoms are evaluated
[see
Warnings and Precautions (5.5)]
.
Paronychia/Nail Toxicity
Advise patients of the risk of paronychia. Advise patients to contact their healthcare provider for signs or symptoms of paronychia
[see
Adverse Reactions (6.1)].
Embryo-Fetal Toxicity
Advise females of reproductive potential of the potential risk to a fetus, to use effective contraception during treatment with RYBREVANT and for 3 months after the last dose, and to inform their healthcare provider of a known or suspected pregnancy
[see
Warnings and Precautions (5.6),
Use in Specific Populations (8.1,
8.3)].
Lactation
Advise women not to breastfeed during treatment with RYBREVANT and for 3 months after the last dose
[see
Use in Specific Populations (8.2)]
.
Product of Ireland
Manufactured by:
Janssen Biotech, Inc.
Horsham, PA 19044, USA
U.S. License Number 1864
For patent information: www.janssenpatents.com
© Johnson & Johnson and its affiliates 2021-2025