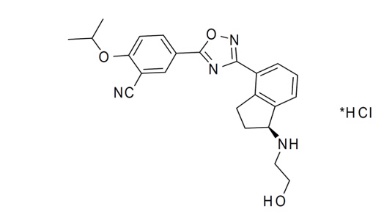
Patients without a healthcare professional-confirmed history of chickenpox or without documentation of a full course of vaccination against varicella zoster virus (VZV) should be tested for antibodies to VZV before initiating ZEPOSIA; VZV vaccination of antibody-negative patients is recommended prior to commencing treatment with ZEPOSIA
[see
Warnings and Precautions (5.1) and
Drug Interactions (7)].
ZEPOSIA causes a mean reduction in peripheral blood lymphocyte count to approximately 45% of baseline values because of reversible sequestration of lymphocytes in lymphoid tissues
[see
Clinical Pharmacology (12.2)].
ZEPOSIA may therefore increase the susceptibility to infections, some serious in nature
.Life-threatening and rare fatal infections have occurred in patients receiving ZEPOSIA.
Obtain a recent (i.e., within 6 months or after discontinuation of prior MS or UC therapy) complete blood count (CBC) including lymphocyte count before initiation of ZEPOSIA
.
Delay initiation of ZEPOSIA in patients with an active infection until the infection is resolved.
In MS Study 1 and Study 2, the overall rate of infections and rate of serious infections in patients treated with ZEPOSIA were similar to that in patients who received interferon (IFN) beta-1a (35% vs. 34% and 1% vs. 0.8%, respectively). In UC Study 1 and Study 3, the overall rate of infections and rate of serious infections in patients treated with ZEPOSIA were similar to that in patients who received placebo (9.9% vs. 10.7% and 0.8% vs. 0.4%, respectively). In UC Study 2, the overall rate of infections in patients treated with ZEPOSIA was higher than in patients treated with placebo (23% vs. 12%) and the rate of serious infections was similar (0.9% vs. 1.8%).
ZEPOSIA increased the risk of viral upper respiratory tract infections, urinary tract infections, and herpes infections
[see
Adverse Reactions (6.1)].
The proportion of patients treated with ZEPOSIA who experienced lymphocyte counts less than 0.2 × 10
9/L was 3.3% in MS Study 1 and Study 2. The proportion of patients treated with ZEPOSIA with lymphocyte counts less than 0.2 × 10
9/L was 2% in UC Study 1 and Study 3 and 2.3% in UC Study 2. These values generally returned to greater than 0.2 × 10
9/L while patients remained on treatment with ZEPOSIA. After discontinuing ZEPOSIA 0.92 mg, the median time for peripheral blood lymphocytes to return to the normal range was approximately 30 days, with approximately 80% to 90% of patients in the normal range within 3 months
[see
Clinical Pharmacology (12.2)].
Consider interruption of treatment with ZEPOSIA if a patient develops a serious infection.
Because the elimination of ZEPOSIA after discontinuation may take up to 3 months, continue monitoring for infections throughout this period.
Cases of localized herpes virus infection (e.g., herpes zoster and herpes simplex) were seen in clinical trials of ZEPOSIA.
In MS Study 1 and Study 2, herpes zoster was reported as an adverse reaction in 0.6% of patients treated with ZEPOSIA 0.92 mg and in 0.2% of patients who received IFN beta-1a.
In UC Study 1 and Study 3, herpes zoster was reported in 0.4% of patients who received ZEPOSIA and none in patients who received placebo. In UC Study 2, herpes zoster was reported in 2.2% of patients who received ZEPOSIA and 0.4% of patients who received placebo. None were serious or disseminated.
Herpes simplex encephalitis and varicella zoster meningitis have been reported with sphingosine 1-phosphate (S1P) receptor modulators. Patients without a healthcare professional-confirmed history of varicella (chickenpox), or without documentation of a full course of vaccination against varicella zoster virus (VZV), should be tested for antibodies to VZV before initiating ZEPOSIA
(see Vaccinations below).
Cases of fatal cryptococcal meningitis (CM) and disseminated cryptococcal infections have been reported with S1P receptor modulators. Physicians should be vigilant for clinical symptoms or signs of CM. Patients with symptoms or signs consistent with a cryptococcal infection should undergo prompt diagnostic evaluation and treatment. ZEPOSIA treatment should be suspended until a cryptococcal infection has been excluded. If CM is diagnosed, appropriate treatment should be initiated.
In the MS and UC clinical studies, patients who received ZEPOSIA were not to receive concomitant treatment with anti-neoplastic, non-corticosteroid immunosuppressive, or immune-modulating therapies used for the treatment of MS and UC. Concomitant use of ZEPOSIA with any of these therapies would be expected to increase the risk of immunosuppression. In UC studies, concomitant use of corticosteroids was allowed and did not appear to influence the safety or efficacy of ZEPOSIA
[see
Clinical Studies (14.2)].
Anti-neoplastic, immune-modulating, or immunosuppressive therapies (including corticosteroids) should be co-administered with caution because of the risk of additive immune system effects during such therapy. When switching to ZEPOSIA from immunosuppressive medications, consider the duration of their effects and their mode of action to avoid unintended additive immunosuppressive effects.
Patients without a healthcare professional-confirmed history of chickenpox or without documentation of a full course of vaccination against VZV should be tested for antibodies to VZV before initiating ZEPOSIA. A full course of vaccination for antibody-negative patients with varicella vaccine is recommended prior to commencing treatment with ZEPOSIA, following which initiation of treatment with ZEPOSIA should be postponed for 4 weeks to allow the full effect of vaccination to occur.
No clinical data are available on the efficacy and safety of vaccinations in patients taking ZEPOSIA. Vaccinations may be less effective if administered during ZEPOSIA treatment.
Initiation of ZEPOSIA may result in a transient decrease in heart rate. After the initial dose of ZEPOSIA 0.23 mg, the greatest mean decrease from baseline in heart rate occurred at Hour 5 on Day 1 (decrease of 1.2 bpm in MS Study 1 and Study 2, and 0.7 bpm in UC Study 1 and Study 3), returning to near baseline at Hour 6. With continued up-titration, the maximal heart rate effect of ozanimod occurred on Day 8. The utility of performing first-dose cardiac monitoring when initiating ZEPOSIA in patients with characteristics similar to those studied in the clinical trials of ZEPOSIA is unclear. Heart rates below 40 bpm were not observed. Initiation of ZEPOSIA without titration may result in greater decreases in heart rate
[see
Dosage and Administration (2.2)].
In MS Study 1 and Study 2, bradycardia was reported on the day of treatment initiation in 0.6% of patients treated with ZEPOSIA compared to no patients who received IFN beta-1a. After Day 1, the incidence of bradycardia was 0.8% in patients treated with ZEPOSIA compared to 0.7% of patients who received IFN beta-1a. In UC Study 1 and Study 3, bradycardia was reported on the day of treatment initiation in 1 patient (0.2%) treated with ZEPOSIA compared to none in patients who received placebo. After Day 1, bradycardia was reported in 1 patient (0.2%) treated with ZEPOSIA. In UC Study 2, bradycardia was not reported.
Initiation of ZEPOSIA may result in transient atrioventricular conduction delays. At ZEPOSIA exposures higher than the recommended dosage without dose titration, first- and second-degree type 1 atrioventricular blocks were observed in healthy volunteers; however, in MS Study 1 and Study 2 and UC Study 1 and Study 3 with dose titration, Mobitz type 2 second- or third-degree atrioventricular blocks were not reported in patients treated with ZEPOSIA.
If treatment with ZEPOSIA is considered, advice from a cardiologist should be sought for those individuals:
- With significant QT prolongation (QTcF > 450 msec in males, > 470 msec in females)
- With arrhythmias requiring treatment with Class Ia or Class III anti-arrhythmic drugs
- With ischemic heart disease, heart failure, history of cardiac arrest or myocardial infarction, cerebrovascular disease, and uncontrolled hypertension
- With a history of with second-degree Mobitz type II or higher AV block, sick-sinus syndrome, or sinoatrial heart block
[see
Contraindications (4)]
Macular Edema in Patients with a History of Uveitis or Diabetes Mellitus
Patients with a history of uveitis and patients with a history of diabetes mellitus are at increased risk of macular edema during ZEPOSIA therapy.
Common Adverse Reactions
Multiple Sclerosis
The safety of ZEPOSIA was evaluated in two randomized, double-blind, active comparator-controlled clinical studies (MS Study 1 and MS Study 2) in which 882 patients received ZEPOSIA 0.92 mg
[see
Clinical Studies (14.1)].
Table 2 lists adverse reactions that occurred in at least 2% of ZEPOSIA-treated patients and greater than comparator. The most common adverse reactions that occurred in at least 4% of ZEPOSIA-treated patients and greater than in patients who received IFN beta-1a were upper respiratory infection, hepatic transaminase elevation, orthostatic hypotension, urinary tract infection, back pain, and hypertension.
Table 2: Adverse Reactions with an Incidence of at Least 2% in ZEPOSIA-Treated Patients and at Least 1% Greater than IFN beta-1a in Patients with Multiple Sclerosis (Pooled MS Study 1 and Study 2)
aaData are not an adequate basis for comparison of rates between ZEPOSIA and the active control.
bIncludes the following terms: nasopharyngitis, upper respiratory tract infection, pharyngitis, respiratory tract infection, bronchitis, rhinitis, viral respiratory tract infection, viral upper respiratory tract infection, rhinorrhea, tracheitis, and laryngitis.
cIncludes the following terms: alanine aminotransferase increased, gamma-glutamyl transferase increased, aspartate aminotransferase increased, hepatic enzyme increased, abnormal liver function test, and increased transaminases.
dIncludes hypertension, essential hypertension, and orthostatic hypertension.
eZEPOSIA was initiated with a 7-day titration
[see
Dosage and Administration (2.2)].
|
Adverse Reactions | MS Studies 1 and 2 |
ZEPOSIA
0.92 mg Once Daily
e
(n=882)
% | IFN beta-1a
30 mcg Intramuscularly Once Weekly
(n=885)
% |
Upper respiratory infection
b | 26 | 23 |
Hepatic transaminase elevation
c | 10 | 5 |
Orthostatic hypotension | 4 | 3 |
Urinary tract infection | 4 | 3 |
Back pain | 4 | 3 |
Hypertension
d | 4 | 2 |
Upper abdominal pain | 2 | 1 |
Ulcerative Colitis
The safety of ZEPOSIA was evaluated in two randomized, double-blind, placebo-controlled clinical studies [UC Study 1 (induction), n=429; and UC Study 2 (maintenance), n=230] in adult patients with moderately to severely active ulcerative colitis
[see
Clinical Studies (14.2)]
. Additional data from the induction period of a randomized, double-blind, placebo-controlled study (UC Study 3, NCT01647516) included 67 patients who received ZEPOSIA 0.92 mg once daily.
Common adverse reactions in UC Study 1 and Study 3 and in UC Study 2 are listed in Tables 3 and 4, respectively. The most common adverse reactions that occurred in at least 4% of ZEPOSIA-treated patients and greater than in patients who received placebo were liver test increased, upper respiratory infection, and headache.
Table 3: Adverse Reactions with an Incidence of at Least 2% in ZEPOSIA-Treated Patients and at Least 1% Greater than Placebo in Patients with Ulcerative Colitis (Pooled UC Study 1 and Study 3)aIncludes the following terms: streptococcal pharyngitis, pharyngotonsillitis, bacterial pharyngitis, nasopharyngitis, upper respiratory tract infection, pharyngitis, sinusitis, tonsillitis, viral upper respiratory tract infection, laryngitis, acute sinusitis, catarrh, chronic sinusitis, upper respiratory tract inflammation, chronic tonsillitis, viral pharyngitis, viral sinusitis, bacterial sinusitis, bacterial upper respiratory tract infection, viral labyrinthitis, laryngeal inflammation, and pharyngeal inflammation.
bIncludes the following terms: gamma-glutamyl transferase increased, alanine aminotransferase increased, aspartate aminotransferase increased, hepatic enzyme increased, hyperbilirubinemia, liver function test increased, blood alkaline phosphatase increased, and increased transaminases.
cZEPOSIA was initiated with a 7-day titration
[see
Dosage and Administration (2.2)].
dPercentages were calculated as the sum of each individual study percentage multiplied by its Cochran-Mantel-Haenszel weight.
|
Adverse Reactions | Induction Periods (UC Study 1 and Study 3) |
ZEPOSIA
0.92 mg Once Daily
(n=496)
c,d
% | Placebo
(n=281)
%
d |
Upper respiratory infection
a | 5 | 4 |
Liver test increased
b | 5 | 0 |
Headache | 4 | 3 |
Pyrexia | 3 | 2 |
Nausea | 3 | 2 |
Arthralgia | 3 | 1 |
Table 4: Adverse Reactions with an Incidence of at Least 4% in ZEPOSIA-Treated Patients and at Least 1% Greater than Placebo in Patients with Ulcerative Colitis (UC Study 2)| aIncludes the following terms: gamma-glutamyl transferase increased, alanine aminotransferase increased, aspartate aminotransferase increased, hepatic enzyme increased, hyperbilirubinemia, blood bilirubin increased, liver function test increased, and blood alkaline phosphatase increased.
|
Adverse Reactions | Maintenance Period (UC Study 2) |
ZEPOSIA
0.92 mg Once Daily
(n=230)
% | Placebo
(n=227)
% |
Liver test increased
a | 11 | 2 |
Headache | 5 | <1 |
Other Adverse Reactions
Reduction in Heart Rate
Initiation of ZEPOSIA may result in transient decrease in heart rate in MS and UC patients
[see
Warnings and Precautions (5.3)].
Respiratory Effects
Dose-dependent reductions in absolute FEV
1and FVC were observed in MS and UC patients treated with ZEPOSIA
[seeWarnings and Precautions (5.7)].
Malignancies
Malignancies, such as melanoma, basal cell carcinoma, breast cancer, seminoma, cervical carcinoma, and adenocarcinomas, including rectal adenocarcinoma, were reported with ZEPOSIA in controlled trials of MS and UC. An increased risk of cutaneous malignancies has been reported with S1P receptor modulators
[see
Warnings and Precautions (5.9)].
Hypersensitivity
Hypersensitivity, including rash and urticaria, has been reported with ZEPOSIA in active-controlled MS clinical trials.
Peripheral Edema
Peripheral edema was observed in 3% of ZEPOSIA-treated patients and in 0.4% of patients who received placebo in UC Study 2.
Risk Summary
There are no adequate data on the developmental risk associated with the use of ZEPOSIA in pregnant women
.In animal studies, administration of ozanimod during pregnancy produced adverse effects on development, including embryolethality, an increase in fetal malformations, and neurobehavioral changes, in the absence of maternal toxicity. In rabbits, fetal blood vessel malformations occurred at clinically relevant maternal ozanimod and metabolite exposures
(see Data). The receptor affected by ozanimod (sphingosine1-phosphate) has been demonstrated to have an important role in embryogenesis, including vascular and neural development.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Data
Animal Data
Oral administration of ozanimod (0, 0.2, 1, or 5 mg/kg/day) to female rats during organogenesis resulted in a marked increase in embryofetal mortality, increased fetal malformations and skeletal variations (abnormal/delayed ossification), and reduced fetal body weight at the highest dose tested. No maternal toxicity was observed. At the no-effect dose (1 mg/kg/day) for adverse effects on embryofetal development, plasma ozanimod exposure (AUC) for ozanimod was approximately 60 times that in humans at the maximum recommended human dose (MRHD) of 0.92 mg/day. Plasma AUCs for major human metabolites, CC112273 and CC1084037, were similar to and less than, respectively, those in humans at the MRHD.
Oral administration of ozanimod (0, 0.2, 0.6, or 2.0 mg/kg/day) to female rabbits during organogenesis resulted in a marked increase in embryofetal mortality at the highest dose tested and increased fetal malformations (malformed blood vessels) and skeletal variations at the mid and high doses. Maternal toxicity was not observed. At the no-effect dose (0.2 mg/kg/day) for adverse effects on embryofetal development in rabbit, plasma ozanimod exposure (AUC) was approximately 2 times that in humans at the MRHD; plasma AUCs for major human metabolites, CC112273 and CC1084037, were less than those in humans at the MRHD.
Oral administration of ozanimod (0, 0.2, 0.7, or 2 mg/kg/day) to female rats throughout gestation and lactation resulted in persistent body weight reductions and long-term effects on reproductive (prolonged estrus cycle) and neurobehavioral (increased motor activity) function in offspring at the highest dose tested, which was not associated with maternal toxicity. At the no-effect dose (0.7 mg/kg/day) for adverse effects on pre- and postnatal development, plasma ozanimod exposure (AUC) was 30 times that in humans at the MRHD; plasma AUCs for major human metabolites, CC112273 and CC1084037, were less than those in humans at the MRHD.
Risk Summary
There are no data on the presence of ozanimod in human milk, the effects on the breastfed infant, or the effects of the drug on milk production. Following oral administration of ozanimod, ozanimod and/or metabolites were detected in the milk of lactating rat at levels higher than those in maternal plasma.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for ZEPOSIA and any potential adverse effects on the breastfed infant from ZEPOSIA or from the underlying maternal condition.
Contraception
Before initiation of ZEPOSIA treatment, women of childbearing potential should be counseled on the potential for a serious risk to the fetus and the need for contraception during treatment with ZEPOSIA
[see
Use in Specific Populations (8.1)]
. Because of the time it takes to eliminate the drug from the body after stopping treatment, the potential risk to the fetus may persist and women of childbearing age should also use effective contraception for 3 months after stopping ZEPOSIA.
Reduction in Blood Lymphocyte Counts
In active-controlled MS and controlled UC clinical trials, mean lymphocyte counts decreased to approximately 45% of baseline at 3 months (approximate mean blood lymphocyte counts 0.8 × 10
9/L), and low lymphocyte counts were maintained during treatment with ZEPOSIA
[see
Warnings and Precautions (5.1)].
After discontinuing ZEPOSIA 0.92 mg, the median time for peripheral blood lymphocytes to return to the normal range was 30 days, with approximately 90% of patients in the normal range within 3 months.
Reduction in Heart Rate
ZEPOSIA may cause a transient decrease in heart rate on initiation of dosing
[see
Warnings and Precautions (5.3)].
An up-titration schedule of ZEPOSIA 0.23 mg followed by doses of 0.46 mg, and 0.92 mg attenuates the magnitude of heart rate reductions
[see
Dosage and Administration (2.2)].
Tyramine Challenge Test
No clinically significant effect in tyramine induced pressor response was observed when steady state ZEPOSIA 0.92 mg (recommended dose) or 1.84 mg was co-administered with increasing doses of oral tyramine (a monoamine oxidase substrate).
Drug Interaction Studies
Sympathomimetic Agents
No clinically significant differences in heart rate or blood pressure was observed when ZEPOSIA 1.84 mg daily (two times the recommended dosage) for 28 days was co-administered with a single dose of 60 mg pseudoephedrine (a sympathomimetic agent) compared to pseudoephedrine alone.
Beta Blocker or Calcium Channel Blocker
The effect of co-administration of the maintenance dosage of ZEPOSIA, propranolol, or diltiazem, or administration with both a beta blocker and a calcium channel blocker taken together has not been studied
[see
Drug Interactions (7)]
.
Pulmonary Function
Dose-dependent reductions in FEV
1and FVC were observed in patients treated with ZEPOSIA
[seeWarnings and Precautions (5.7)].
Cardiac Electrophysiology
Following a 14-day titration regimen of once daily doses of ozanimod 0.23 mg for 4 days, 0.46 mg for 3 days, 0.92 mg for 3 days, and 1.84 mg (2 times the maximum approved recommended dose) for 4 days in healthy subjects, ZEPOSIA did not prolong the QTc interval to any clinically relevant extent
[see
Warnings and Precautions (5.3)].
Absorption
The T
maxof ozanimod is approximately 6 to 8 hours.
Effect of Food
No clinically significant differences in the C
maxand AUC of ozanimod were observed following administration of ZEPOSIA with either a high-fat, high-calorie meal (1000 calories, 50% fat) or a low-fat, low-calorie meal (300 calories, 10% fat) compared to fasted conditions
[see
Dosage and Administration (2.2)]
.
Distribution
The mean (CV%) apparent volume of distribution of ozanimod (Vz/F) is 5590 L (27%). Human plasma proteins binding of ozanimod, CC112273 and CC1084037 is approximately 98.2%, 99.8%, and 99.3%, respectively.
Elimination
The mean (CV%) plasma half-life (t1/2) of ozanimod is approximately 21 hours (15%). The mean (CV%) effective half-life (t1/2) of CC112273 and its direct interconverting metabolite CC1084037 was approximately 11 days (104%) in relapsing MS patients. The mean (CV%) apparent oral clearance for ozanimod was approximately 192 L/h (37%).
Metabolism
Ozanimod is metabolized by multiple enzymes to form circulating major active metabolites (e.g., CC112273 and CC1084037) and minor active metabolites (e.g., RP101988, RP101075, and RP112509) with similar activity and selectivity for S1P
1and S1P
5. Ozanimod is metabolized by ALDH/ADH to form carboxylate metabolite RP101988 and by CYP3A4 to form RP101075. RP101075 is then metabolized either by NAT-2 to form a minor active metabolite RP101442 or by MAO-B to form CC112273. CC112273 is then metabolized by CYP2C8 to form RP112509 or reduced to form CC1084037. CC1084037 is metabolized by AKR 1C1/1C2 and/or 3β- and 11β-HSD to form CC112273. The interconversion between CC112273 and CC1084037 favors CC112273. Approximately 94% of circulating total active drug exposure is represented by ozanimod (6%), CC112273 (73%), and CC1084037 (15%), in humans.
Excretion
Following a single oral dose of radiolabeled ozanimod 0.92 mg, approximately 26% of the radioactivity was recovered in urine and 37% in feces, primarily composed of inactive metabolites.
Specific Populations
Geriatric Patients
Population pharmacokinetic analyses showed that steady state exposure (AUC) of CC112273 in UC patients over 65 years of age was approximately 3% to 4% greater than patients 45 to 65 years of age and 27% greater than adult patients under 45 years of age. There is no meaningful difference in the pharmacokinetics in elderly patients with UC
[see
Use in Specific Populations (8.5)]
.
Male and Female Patients
No clinically significant differences in the pharmacokinetics of ozanimod and CC112273 were observed based on sex or weight.
Racial or Ethnic Groups
In a dedicated Japanese PK bridging study, following repeated dosing of 0.96 mg ZEPOSIA, ozanimod exposures (C
maxand AUC
tau) were unchanged and CC112273 exposures (C
maxand AUC
tau) were approximately 28% and 43% higher, respectively, in Japanese subjects (N=10) compared to Caucasian subjects (N=12). These differences are not considered clinically meaningful.
Patients with Renal Impairment
In a dedicated renal impairment trial, following a single oral dose of 0.23 mg ZEPOSIA, exposures (AUC
last) for ozanimod and CC112273 were approximately 27% higher and 23% lower, respectively, in subjects with end stage renal disease (N=8) compared to subjects with normal renal function (N=8). Based on this trial, renal impairment has no clinically important effects on pharmacokinetics of ozanimod or CC112273.
Patients with Hepatic Impairment
In a hepatic impairment study, following an 8-day titration regimen of once daily doses of ZEPOSIA 0.23 mg on days 1 to 4, 0.46 mg on days 5 to 7, and 0.92 mg on day 8, in subjects with mild hepatic impairment (Child-Pugh class A, N=8), mean exposures (AUC
last) of ozanimod and active metabolites CC112273 and CC1084037 on day 8 increased by 60%, 98%, and 107%, respectively, compared to healthy controls (N=8). In subjects with moderate hepatic impairment (Child-Pugh class B, N=8) mean exposures (AUC
last) of ozanimod and active metabolites CC112273 and CC1084037 on day 8 increased by 17%, 38%, and 61%, respectively, compared to healthy controls.
The pharmacokinetics of ozanimod or its active metabolites were not evaluated in patients with severe hepatic impairment (Child-Pugh class C)
[see
Use in Specific Populations (8.6)]
.
Smokers
Population PK analyses showed that CC112273 steady-state exposure (AUC) was approximately 50% lower in smokers than in nonsmokers, although for smokers this reduction in exposure did not result in meaningful differences in absolute lymphocyte count (ALC) reduction or an apparent impact on clinical efficacy.
Drug Interaction Studies
Clinical/In Vivo Studies
Strong CYP3A and P-gp Inhibitors
No clinically significant differences in the pharmacokinetics of ozanimod and its major active metabolites CC112273 and CC1084037 were observed when co-administered with itraconazole (P-gp and strong CYP3A inhibitor).
Strong CYP2C8 Inhibitors
Co-administration of ozanimod with gemfibrozil (a strong CYP2C8 inhibitor) increased exposure (AUC) of active metabolites CC112273 and CC1084037 by approximately 47% and 69%, respectively, with no change in the AUC of ozanimod
[see
Drug Interactions (7)].
BCRP Inhibitors
Co-administration of ozanimod with cyclosporine (BCRP inhibitor) had no effect on the exposure of ozanimod or the major active metabolites CC112273 and CC1084037.
Strong CYP2C8 Inducers
Co-administration of rifampin (a strong inducer of CYP3A and P-gp, and a moderate inducer of CYP2C8) 600 mg once daily at steady state and a single dose of ZEPOSIA 0.92 mg reduced the exposure (AUC) for ozanimod, CC112273, and CC1084037 by approximately 24%, 60%, and 55%, respectively. The effect on CC112273 and CC1084037 is primarily caused by induction of CYP2C8
[see
Drug Interactions (7)].
Prednisone and Prednisolone
Population pharmacokinetic analyses showed that concomitant administration of prednisone or prednisolone in patients with UC did not alter the apparent clearance of the predominant active metabolite CC112273. The impact of prednisone or prednisolone on the pharmacokinetics of CC1084037 is unknown.
Monoamine Oxidase Inhibitors
No clinical studies evaluating the drug interaction potential of ozanimod with MAO inhibitors have been conducted
[seeDrug Interactions (7)].
Monoamine Oxidase Substrates
Co-administration of steady state 0.92 mg or 1.84 mg ozanimod had no effect on the plasma concentrations of oral tyramine, an MAO substrate.
Oral Contraceptives
No clinically significant differences in the pharmacokinetic of oral contraceptive containing ethinyl estradiol and norethindrone were observed when co-administered with ozanimod.
In Vitro Studies
Cytochrome P450 (CYP) Enzymes
Ozanimod, CC112273, CC1084037, and other metabolites do not inhibit CYPs 1A2, 2B6, 2C19, 2C8, 2C9, 2D6, and 3A, and do not induce CYPs 1A2, 2B6, and 3A.
In vitro, CC112273 and CC1084037 inhibited MAO-B (IC
50values of 5.72 nM and 58 nM, respectively) with more than 1000-fold selectivity over monoamine oxidase A (MAO-A)
[see
Drug Interactions (7)]
.
Transporter Systems
Ozanimod, CC112273, CC1084037, and other metabolites do not inhibit P-gp, OATP1B1, OATP1B3, OAT1, OAT3, MATE1, or MATE2-K. CC112273 and CC1084037 do not inhibit BCRP at clinically relevant concentrations.
Carcinogenesis
Oral administration of ozanimod (0, 8, 25, or 80 mg/kg/day) to Tg.rasH2 mice for 26-weeks resulted in an increase in hemangioma and hemangiosarcoma (combined) in males and females at the mid and high doses tested.
Oral administration of ozanimod (0, 0.2, 0.7, or 2 mg/kg/day) to rats for 2 years resulted in no increase in tumors. At the highest dose tested (2 mg/kg/day), plasma exposure (AUC) for ozanimod was approximately 100 times that in humans at the maximum recommended human dose (MRHD) of 0.92 mg/day. Plasma AUCs for major human metabolites, CC112273 and CC1084037, were similar to and less than, respectively, those in humans at the MRHD.
Mutagenesis
Ozanimod was negative in a battery of in vitro (Ames, mouse lymphoma tk) and in vivo (rat micronucleus) assays. Metabolite CC112273 was negative in in vitro (Ames, chromosomal aberration in mammalian cell) assays. Metabolite CC1084037 was negative in an Ames assay, and positive in an in vitro chromosomal aberration assay in human (TK6) cells but negative in an in vivo rat micronucleus/comet assay.
Impairment of Fertility
Oral administration of ozanimod (0, 0.2, 2, or 30 mg/kg/day) to male and female rats prior to and during mating and continuing through gestation day 7 resulted in no adverse effects on fertility. At the highest dose tested (30 mg/kg/day), plasma ozanimod exposure (AUC) was approximately 1600 times that in humans at the maximum recommended human dose (MRHD) (0.92 mg/day); plasma AUCs for metabolites, CC112273 and CC1084037, at 30 mg/kg/day were 13 and 3 times, respectively, those in humans at the MRHD.
UC Study 1
In UC Study 1, a total of 645 patients were randomized 2:1 to either ZEPOSIA 0.92 mg given orally once daily or placebo for 10 weeks, beginning with a dosage titration
[see
Dosage and Administration (2.2)]
. The trial included adult patients with moderately to severely active UC who had an inadequate response or were intolerant to any of the following: oral aminosalicylates, corticosteroids, immunomodulators (e.g., 6-mercaptopurine and azathioprine), or a biologic (e.g., TNF blocker and/or vedolizumab). Patients were required to be on stable doses of oral aminosalicylates and/or corticosteroids (prednisone daily dose up to 20 mg equivalent or budesonide extended-release tablets) prior to enrollment. Seventy-one percent of patients were receiving mesalamine, 13% sulfasalazine, and 33% oral corticosteroids. A total of 30% of patients had previously failed or were intolerant to TNF blockers. Of these patients, 63% received at least two biologics including TNF blockers.
The disease activity was assessed by the Mayo score (0 to 12) which consists of four subscores (0 to 3 for each subscore): stool frequency, rectal bleeding, findings on centrally-read endoscopy, and physician global assessment. An endoscopy subscore of 2 was defined by marked erythema, lack of vascular pattern, friability, and erosions; an endoscopy subscore of 3 was defined by spontaneous bleeding and ulceration. Enrolled patients had Mayo scores between 6 to 12; at baseline, patients had a median Mayo score of 9, with 86% of patients having moderate disease (Mayo score 6-10), and 14% having severe disease (Mayo score 11-12).
Concomitant immunomodulators or biologic therapies were not permitted.
The primary endpoint was clinical remission at Week 10, defined using a 3-component Mayo score without the physician global assessment: rectal bleeding subscore = 0, stool frequency subscore = 0 or 1 (and a decrease of ≥ 1 point from the baseline stool frequency subscore), and endoscopy subscore = 0 or 1 (an endoscopy subscore of 0 defined as normal or inactive disease, and an endoscopy subscore of 1 defined as presence of erythema, decreased vascular pattern and no friability).
The secondary endpoints were clinical response, endoscopic improvement, and endoscopic-histologic mucosal improvement. Clinical response (reduction from baseline in the 3-component Mayo score of ≥ 2 points and ≥ 35%, and a reduction from baseline in the rectal bleeding subscore of ≥ 1 point or an absolute rectal bleeding subscore of 0 or 1), endoscopic improvement (Mayo endoscopy subscore of 0 or 1), and endoscopic-histologic mucosal improvement [combined endoscopic improvement and histologic improvement of colonic tissue (no neutrophils in the epithelial crypts or lamina propria and no increase in eosinophils, no crypt destruction, and no erosions, ulcerations, or granulation tissue, i.e., Geboes < 2.0)].
A significantly greater proportion of patients treated with ZEPOSIA achieved clinical remission, clinical response, endoscopic improvement, and endoscopic-histologic mucosal improvement compared to placebo at Week 10 (see Table 9).
Table 9: Proportion of Patients Meeting Efficacy Endpoints in the Induction Period at Week 10 in UC Study 1CI = confidence interval; TNF = tumor necrosis factor.
aZEPOSIA was initiated with a 7-day titration
[see
Dosage and Administration (2.2)]
.
bTreatment difference (adjusted for stratification factors of prior anti-TNF exposure and corticosteroid use at baseline).
cClinical remission is defined as: rectal bleeding subscore = 0, stool frequency subscore = 0 or 1 (and a decrease from baseline in the stool frequency subscore of ≥ 1 point), and endoscopy subscore = 0 or 1 without friability.
dClinical response is defined as a reduction from baseline in the 3-component Mayo score of ≥ 2 points and ≥ 35%, and a reduction from baseline in the rectal bleeding subscore of ≥ 1 point or an absolute rectal bleeding subscore of 0 or 1.
eEndoscopic improvement is defined as a Mayo endoscopy subscore of 0 or 1 without friability.
fEndoscopic-histologic mucosal improvement is defined as both Mayo endoscopic subscore of 0 or 1 without friability and histologic improvement of colonic tissue (defined as no neutrophils in the epithelial crypts or lamina propria and no increase in eosinophils, no crypt destruction, and no erosions, ulcerations, or granulation tissue, i.e., Geboes < 2.0).
gp<0.0001.
hp<0.001.
|
Endpoint | ZEPOSIA 0.92 mg Once Daily
a
(N=429) | Placebo
(N=216) | Treatment Difference
b
(95% CI) |
n | % | n | % |
Clinical remission
c | 79 | 18% | 13 | 6% | 12%
(8%, 17%)
g |
Without prior TNF blocker exposure | 66/299 | 22% | 10/151 | 7% | |
Prior TNF blocker exposure | 13/130 | 10% | 3/65 | 5% |
Clinical response
d | 205 | 48% | 56 | 26% | 22%
(14%, 29%)
g |
Without prior TNF blocker exposure | 157/299 | 53% | 44/151 | 29% | |
Prior TNF blocker exposure | 48/130 | 37% | 12/65 | 19% |
Endoscopic improvement
e | 117 | 27% | 25 | 12% | 16%
(10%, 22%)
g |
Without prior TNF blocker exposure | 97/299 | 32% | 18/151 | 12% | |
Prior TNF blocker exposure | 20/130 | 15% | 7/65 | 11% |
Endoscopic-histologic mucosal improvement
f | 54 | 13% | 8 | 4% | 9%
(5%, 13%)
h |
Without prior TNF blocker exposure | 47/299 | 16% | 6/151 | 4% | |
Prior TNF blocker exposure | 7/130 | 5% | 2/65 | 3% |
The relationship of endoscopic-histologic mucosal improvement, as defined in UC Study 1, at Week 10 to disease progression and long term outcomes was not evaluated during UC Study 1.
Rectal Bleeding Subscore and Stool Frequency Subscores
Decreases in rectal bleeding and stool frequency subscores were observed as early as Week 2 (i.e., 1 week after completing the required 7-day dosage titration) in patients treated with ZEPOSIA.
UC Study 2
In UC Study 2, a total of 457 patients who received ZEPOSIA in either UC Study 1 or in an open-label arm and achieved clinical response at Week 10 were re-randomized 1:1 and were treated with either ZEPOSIA 0.92 mg (n=230) or placebo (n=227) for 42 weeks (UC Study 2), for a total of 52 weeks of treatment.
Patients were permitted to be on stable doses of oral aminosalicylates. Corticosteroid tapering was required upon entering this study for patients who were receiving corticosteroids during the induction period. Concomitant oral immunomodulators or biologic therapies were not permitted. At study entry, 35% of patients were in clinical remission; 29% of patients were on corticosteroids; and 31% of patients had an inadequate response, loss of response, or intolerance to TNF blockers.
The primary endpoint was the proportion of patients in clinical remission at Week 52. The secondary endpoints at Week 52 were the proportion of patients with clinical response, endoscopic improvement, endoscopic-histologic mucosal improvement, corticosteroid-free clinical remission, and maintenance of clinical remission at Week 52 among patients who achieved clinical remission at Week 10 in UC Study 1.
The results of the efficacy endpoints in the maintenance period are shown in Table 10.
Table 10: Proportion of Patients Meeting Efficacy Endpoints in the Maintenance Period at Week 52 in UC Study 2CI = confidence interval; TNF = tumor necrosis factor.
aZEPOSIA was initiated with a 7-day titration
[see
Dosage and Administration (2.2)]
.
bTreatment difference (adjusted for stratification factors of clinical remission and concomitant corticosteroid use at Week 10).
cClinical remission is defined as: rectal bleeding subscore = 0, stool frequency subscore = 0 or 1 (and a decrease from baseline in the stool frequency subscore of ≥ 1 point), and endoscopy subscore = 0 or 1 without friability.
dClinical response is defined as a reduction from baseline in the 3-component Mayo score of ≥ 2 points and ≥ 35%, and a reduction from baseline in the rectal bleeding subscore of ≥ 1 point or an absolute rectal bleeding subscore of 0 or 1.
eEndoscopic improvement is defined as a Mayo endoscopy subscore of 0 or 1 without friability.
fMaintenance of remission is defined as clinical remission at Week 52 in the subset of patients in clinical remission at Week 10.
gCorticosteroid-free remission is defined as clinical remission at Week 52 while off corticosteroids for ≥ 12 weeks.
hEndoscopic-histologic mucosal improvement is defined as both Mayo endoscopic score of 0 or 1 without friability and histologic improvement of colonic tissue (defined as no neutrophils in the epithelial crypts or lamina propria and no increase in eosinophils, no crypt destruction, and no erosions, ulcerations, or granulation tissue, i.e., Geboes <2.0).
ip<0.0001.
jp<0.001.
kp=0.0025.
|
Endpoint | ZEPOSIA 0.92 mg Once Daily
a
(N=230) | Placebo
(N=227) | Treatment Difference
b
(95% CI) |
n | % | n | % |
Clinical remission
c | 85 | 37% | 42 | 19% | 19%
(11%, 26%)
i |
Without prior TNF blocker exposure | 63/154 | 41% | 35/158 | 22% | |
Prior TNF blocker exposure | 22/76 | 29% | 7/69 | 10% |
Clinical response
d | 138 | 60% | 93 | 41% | 19%
(10%, 28%)
i |
Without prior TNF blocker exposure | 96/154 | 62% | 76/158 | 48% | |
Prior TNF blocker exposure | 42/76 | 55% | 17/69 | 25% |
Endoscopic improvement
e | 105 | 46% | 60 | 26% | 19%
(11%, 28%)
j |
Without prior TNF blocker exposure | 77/154 | 50% | 48/158 | 30% | |
Prior TNF blocker exposure | 28/76 | 37% | 12/69 | 17% |
Maintenance of clinical remission at Week 52 in the subset of patients in remission at Week 10
f | 41/79 | 52% | 22/75 | 29% | 24%
(9%, 39%)
k |
Without prior TNF blocker exposure | 37/64 | 58% | 19/58 | 33% | |
Prior TNF blocker exposure | 4/15 | 27% | 3/17 | 18% |
Corticosteroid-free clinical remission
g | 73 | 32% | 38 | 17% | 15%
(8%, 23%)
j |
Without prior TNF blocker exposure | 55/154 | 36% | 31/158 | 20% | |
Prior TNF blocker exposure | 18/76 | 24% | 7/69 | 10% |
Endoscopic-histologic mucosal improvement
h | 68 | 30% | 32 | 14% | 16%
(8%, 23%)
j |
Without prior TNF blocker exposure | 51/154 | 33% | 28/158 | 18% | |
Prior TNF blocker exposure | 17/76 | 22% | 4/69 | 6% |
The relationship of endoscopic-histologic mucosal improvement, as defined in UC Study 2, at Week 52 to disease progression and long term outcomes was not evaluated during UC Study 2.
Risk of Infections
Inform patients that they may be more likely to get infections, some of which could be life-threatening, when taking ZEPOSIA and for 3 months after stopping it, and that they should contact their healthcare provider if they develop symptoms of infection
[see
Warnings and Precautions (5.1)].
Inform patients that prior or concomitant use of drugs that suppress the immune system may increase the risk of infection. Advise patients that some vaccines containing live virus (live attenuated vaccines) should be avoided during treatment with ZEPOSIA. Advise patients that if immunizations are planned, they should be administered at least 1 month prior to initiation of ZEPOSIA. Inform patients that the use of live
attenuatedvaccines should be avoided during and for 3 months after treatment with ZEPOSIA.
Progressive Multifocal Leukoencephalopathy
Inform patients that cases of progressive multifocal leukoencephalopathy (PML) have occurred in patients who received ZEPOSIA and other S1P receptor modulators. Inform the patient that PML is characterized by a progression of deficits and usually leads to death or severe disability over weeks or months. Instruct the patient of the importance of contacting their healthcare provider if they develop any symptoms suggestive of PML. Inform the patient that typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes
[see
Warnings and Precautions (5.2)]
.
Cardiac Effects
Advise patients that initiation of ZEPOSIA treatment may result in a transient decrease in heart rate
.Inform patients that to reduce this effect, dose titration is required. Advise patients that the dose titration is also required if a dose is missed for 1 day or more during the first 14 days of treatment
[see
Dosage and Administration (2.2,
2.4)and
Warnings and Precautions (5.3)].
Liver Injury
Inform patients that ZEPOSIA may cause liver injury. Advise patients that they should contact their healthcare provider if they have any unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, or jaundice and/or dark urine
[seeWarnings and Precautions (5.4)].
Pregnancy and Fetal Risk
Inform patients that, based on animal studies, ZEPOSIA may cause fetal harm
.Discuss with women of childbearing age whether they are pregnant, might be pregnant, or are trying to become pregnant. Advise women of childbearing potential of the need for effective contraception during treatment with ZEPOSIA and for 3 months after stopping ZEPOSIA. Advise a female patient to immediately inform her healthcare provider if she is pregnant or planning to become pregnant
[seeWarnings and Precautions (5.5)and
Use in Specific Populations (8.3)].
Pregnancy Registry
Encourage multiple sclerosis patients to enroll in the ZEPOSIA Pregnancy Registry if they become pregnant while taking ZEPOSIA
[see
Use in Specific Populations (8.1)]
.
Respiratory Effects
Advise patients that they should contact their healthcare provider if they experience new onset or worsening dyspnea
[seeWarnings and Precautions (5.7)].
Macular Edema
Advise patients that ZEPOSIA may cause macular edema, and that they should obtain an eye exam near the start of treatment with ZEPOSIA, have their eyes monitored periodically by an eye care professional while receiving therapy, and contact their healthcare provider if they experience any changes in their vision while taking ZEPOSIA. Inform patients with diabetes mellitus or a history of uveitis that their risk of macular edema may be increased
[seeWarnings and Precautions (5.8)].
Cutaneous Malignancies
Inform patients that the risk of basal cell carcinoma, squamous cell carcinoma, and melanoma is increased in patients treated with S1P receptor modulators. Advise patients that any suspicious skin lesions should be promptly evaluated. Advise patients to limit exposure to sunlight and ultraviolet light by wearing protective clothing and using a sunscreen with high protection factor
[see
Warnings and Precautions (5.9)].
Posterior Reversible Encephalopathy Syndrome
Advise patients to immediately report to their healthcare provide any symptoms involving sudden onset of severe headache, altered mental status, visual disturbances, or seizure. Inform patients that delayed treatment could lead to permanent neurological consequences
[seeWarnings and Precautions (5.10)].
Severe Increase in Multiple Sclerosis Disability after Stopping ZEPOSIA
Inform patients with multiple sclerosis that severe increase in disability has been reported after discontinuation of a S1P receptor modulator like ZEPOSIA. Advise patients to contact their physician if they develop worsening symptoms of MS following discontinuation of ZEPOSIA
[seeWarnings and Precautions (5.12)].
Immune System Effects after Stopping ZEPOSIA
Advise patients that ZEPOSIA continues to have effects, such as lowering effects on peripheral lymphocyte count, for up to 3 months after the last dose
[seeWarnings and Precautions (5.13)].
Marketed by:
Bristol-Myers Squibb Company
Princeton, NJ 08543 USA
ZEPOSIA
®is a trademark of Celgene Corporation, a Bristol-Myers Squibb company.
ZEPPI.012/ZEPMG.009