Most Commonly Observed Adverse Reactions during 1 Year of Treatment
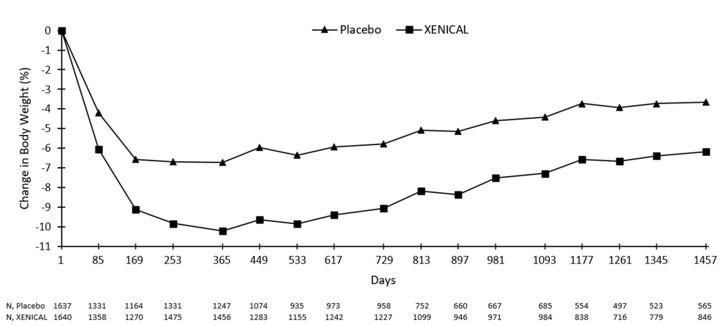
XENICAL was evaluated for safety in adults with obesity or overweight with at least one comorbid condition in seven multicenter, double-blind, placebo-controlled clinical trials of 1- to 2-years duration, and in a 4-year trial. The seven trials included 1,466 patients treated with placebo, 1,913 patients treated with XENICAL 120 mg orally three times a day, and 809 patients treated with unapproved dosages of XENICAL. Age of the patients ranged from 17 to 78 years; 80% were female, 91% White, 6% Black or African American, 2% were of Hispanic or Latino ethnicity, and 1% of other races. Six of the trials enrolled patients without type 2 diabetes mellitus (Trials 1-6) and one of the trials enrolled a population of patients with type 2 diabetes mellitus (Trial 7). The 4-year trial (Trial 8) included 3,304 patients, age range 30-58 years; 55% were female; 99% were White and 1% other races. This trial included a subset of patients with abnormal glucose at baseline [see Clinical Studies (14.1)].
In placebo-controlled clinical trials, 9% of patients treated with XENICAL discontinued treatment due to adverse reactions, compared with 5% of placebo-treated patients. The most common adverse reactions that led to discontinuation of XENICAL treatment were gastrointestinal in nature. Gastrointestinal symptoms, as shown in Table 1, were the most commonly observed adverse reactions associated with the use of XENICAL in the first year of seven placebo-controlled clinical trials. In general, the first occurrence of these events was within 3 months of starting therapy.
Table 1 Adverse Reactions (5% and an incidence at least twice that of placebo) in XENICAL-Treated Adults with Obesity or Overweight for Chronic Weight Management During 1 Year of Treatment
AdverseEvent | Placebo %Patients (N=1,466) | XENICAL %Patients (N=1,913) |
Oily Spottinga | 1 | 27 |
Flatus with Discharge | 1 | 24 |
Fecal Urgency | 7 | 22 |
Fatty/Oily Stoola | 3 | 20 |
Oily Evacuationa | 1 | 12 |
Increased Defecation | 4 | 11 |
Fecal Incontinence | 1 | 8 |
a Oily discharge may be clear or have a coloration such as orange or brown.
Table 2 lists other adverse reactions from the seven placebo-controlled clinical trials that occurred at a frequency of ≥3% among patients treated with XENICAL and with an incidence that was greater than placebo during year 1.
Table 2 Adverse Reactions (incidence ≥3% and greater than placebo) from Seven Placebo-Controlled Clinical Trials During 1 Year of Treatment
AdverseEvent | Placebo %Patients (N=1,466) | XENICAL %Patients (N=1,913) |
Influenza | 36 | 40 |
Upper Respiratory Infection | 33 | 38 |
Headache | 28 | 31 |
Abdominal Pain/Discomfort | 21 | 26 |
Back Pain | 12 | 14 |
Menstrual Irregularity | 8 | 10 |
Lower Respiratory Infection | 7 | 8 |
Nausea | 7 | 8 |
Urinary Tract Infection | 7 | 8 |
Fatigue | 6 | 7 |
Arthritis | 5 | 5 |
Dizziness | 5 | 5 |
Anxiety | 3 | 5 |
Infectious Diarrhea | 4 | 5 |
Rectal Pain/Discomfort | 4 | 5 |
Vaginitis | 4 | 4 |
Rash | 4 | 4 |
Vomiting | 4 | 4 |
Otitis | 3 | 4 |
Sleep Disorders | 3 | 4 |
Myalgia | 3 | 4 |
Tooth Disorder | 3 | 4 |
Gingival Disorder | 3 | 4 |
Other Adverse Reactions
Low Vitamin Levels
Table 3 illustrates the percentage of adult patients on XENICAL and placebo who developed a low blood vitamin level on two or more consecutive visits in studies up to 2 years in which patients were not previously receiving vitamin supplementation.
Table 3 Incidence of Low Blood Vitamin Values on Two or More Consecutive Visits (Adult Patients with Normal Nonsupplemented Baseline Values)
| Placebo % Patients | XENICAL % Patients |
Vitamin D | 7 | 12 |
Beta-carotene | 2 | 6 |
Vitamin E | 1 | 6 |
Vitamin A | 1 | 2 |
Adverse Reactions in Patients with Type 2 Diabetes Mellitus
Hypoglycemia and abdominal distension were also reported in clinical trials in patients with type 2 diabetes mellitus and overweight or obesity.
Adverse Reactions in Pediatric Patients Aged 12 Years and Older with Obesity
In clinical trials with XENICAL in pediatric patients aged 12 years and older with obesity, adverse reactions were similar to those reported in adults [see Clinical Studies (14.2)].
Table 4 describes the clinically significant drug and dietary supplement interactions with XENICAL.
Table 4 Clinically Significant Drug and Dietary Supplement Interactions with XENICAL
Cyclosporine |
Clinical Impact | Coadministration of XENICAL and cyclosporine reduces cyclosporine plasma levels [see Clinical Pharmacology (12.3)]. |
Intervention | Avoid simultaneous coadministration of XENICAL and cyclosporine. Administer cyclosporine 3 hours after the administration of XENICAL. In those patients whose cyclosporine levels are being measured, monitor more frequently [see Warnings and Precautions (5.1)]. |
Fat-soluble Vitamin Supplements and Analogues |
Clinical Impact | The absorption of beta-carotene supplements is reduced when concomitantly administered with XENICAL. XENICAL also inhibited absorption of a vitamin E acetate supplement. The effect of XENICAL on the absorption of supplemental vitamin D, vitamin A, and nutritionally-derived vitamin K is not known [see Clinical Pharmacology (12.3) and Warnings and Precautions (5.1)]. |
Intervention | Administer a multivitamin supplement at least 2 hours before or 2 hours after the administration of XENICAL, or at bedtime [see Dosage and Administration (2)]. |
Levothyroxine |
Clinical Impact | Hypothyroidism has been reported in patients treated concomitantly with XENICAL and levothyroxine postmarketing. |
Intervention | Avoid simultaneous coadministration of XENICAL and levothyroxine. Administer levothyroxine and XENICAL at least 4 hours apart [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3)]. Monitor patients treated concomitantly with XENICAL and levothyroxine for changes in thyroid function. |
AnticoagulantsincludingWarfarin |
Clinical Impact | Vitamin K absorption may be decreased with XENICAL. Reports of decreased prothrombin, increased INR and unbalanced anticoagulant treatment resulting in change of hemostatic parameters have been reported in patients treated concomitantly with XENICAL and anticoagulants. |
Intervention | Monitor patients on warfarin or other anticoagulants who are prescribed XENICAL for changes in coagulation parameters [see Clinical Pharmacology (12.3)]. |
Amiodarone |
Clinical Impact | Coadministration of XENICAL and amiodarone reduces exposure to amiodarone and its metabolite, desethylamiodarone [see Clinical Pharmacology (12.3)]. A reduced therapeutic effect of amiodarone is possible. The effect of commencing orlistat treatment in patients on stable amiodarone therapy has not been studied. |
Intervention | Monitor patients as clinically indicated. |
AntiepilepticDrugs |
Clinical Impact | XENICAL may decrease the effect of antiepileptic drugs. Convulsions have been reported in patients treated concomitantly with orlistat and antiepileptic drugs. |
Intervention | Monitor patients for changes in seizure frequency. |
Antiretroviral Drugs |
Clinical Impact | Loss of virological control has been reported in HIV-infected patients taking orlistat concomitantly with antiretroviral drugs such as atazanavir, ritonavir, tenofovir disoproxil fumarate, emtricitabine, and with the combinations lopinavir/ritonavir and emtricitabine/efavirenz/tenofovir disoproxil fumarate. The exact mechanism for this is unclear, but may include a drug-drug interaction that inhibits systemic absorption of the antiretroviral drug. |
Intervention | HIV RNA levels should be frequently monitored in patients who take XENICAL while being treated for HIV infection. Discontinue XENICAL if there is a confirmed increase in HIV viral load. |
Absorption
Systemic exposure to orlistat is minimal. Following oral dosing with 360 mg 14C-orlistat, plasma radioactivity peaked at approximately 8 hours; plasma concentrations of intact orlistat were near the limits of detection (<5 ng/mL). In therapeutic studies involving monitoring of plasma samples, detection of intact orlistat in plasma was sporadic and concentrations were low (<10 ng/mL or 0.02 µM), without evidence of accumulation, and consistent with minimal absorption.
Distribution
In vitro orlistat was >99% bound to plasma proteins (lipoproteins and albumin were major binding proteins). Orlistat minimally partitioned into erythrocytes.
Elimination
Metabolism
Based on an oral 14C-orlistat mass balance study in patients with obesity, two metabolites, M1 (the hydrolyzed ß-lactone ring product of orlistat) and M3 (sequential metabolite after M1’s cleavage of the N-formyl leucine side-chain), accounted for approximately 42% of total radioactivity in plasma. M1 and M3 have an open ß-lactone ring and extremely weak lipase inhibitory activity (1000- and 2500-fold less than orlistat, respectively). In view of this low inhibitory activity and the low plasma levels at the therapeutic dose (average of 26 ng/mL and 108 ng/mL for M1 and M3, respectively, 2 to 4 hours after a dose), these metabolites are considered pharmacologically inconsequential. The primary metabolite M1 had a short half-life (approximately 3 hours) whereas the secondary metabolite M3 eliminated at a slower rate (half-life approximately 13.5 hours).
Plasma concentrations of orlistat and its metabolites M1 and M3 were similar in pediatric patients to those found in adults at the same dose level.
Excretion
Following a single oral dose of 360 mg 14C-orlistat in subjects with normal weight and with obesity, fecal excretion of the unabsorbed drug was found to be the major route of elimination. Orlistat and its M1 and M3 metabolites were also subject to biliary excretion. Approximately 97% of the administered radioactivity was excreted in feces; 83% of that was found to be unchanged orlistat. The cumulative renal excretion of total radioactivity was <2% of the given dose of 360 mg 14C-orlistat. The time to reach complete excretion (fecal plus urinary) was 3 to 5 days. The disposition of orlistat appeared to be similar between subjects with normal weight and subjects with obesity. Based on limited data, the half-life of the absorbed orlistat is in the range of 1 to 2 hours.
Specific Populations
No pharmacokinetic study was conducted for specific populations such as geriatric patients, patients of different races, and patients with renal or hepatic impairment.
Drug Interaction Studies
Alcohol
In a multiple-dose study in 30 normal-weight subjects, coadministration of orlistat and 40 grams of alcohol (e.g., approximately 3 glasses of wine) did not result in alteration of alcohol pharmacokinetics, orlistat pharmacodynamics (fecal fat excretion), or systemic exposure to orlistat.
Amiodarone
In a pharmacokinetic study conducted in healthy volunteers who received 120 mg orlistat three times daily for 13 days and a single dose of 120 mg orlistat on the morning of Day 14 co-administered with a single dose of 1,200 mg amiodarone on Day 4, a 23 to 27% reduction in the systemic exposure to amiodarone and desethylamiodarone was observed [see Drug Interactions (7)]. The effect of commencing orlistat treatment in patients on stable amiodarone therapy has not been studied.
Cyclosporine
In a multiple-dose study, coadministration of 50 mg cyclosporine twice daily with 120 mg orlistat three times daily decreased cyclosporine AUC and Cmax by 31% and 25%, respectively. In the same study, administration of 50 mg cyclosporine twice daily three hours after the administration of 120 mg orlistat three times daily decreased cyclosporine AUC and Cmax by 17% and 4%, respectively.
Digoxin
In 12 normal-weight subjects receiving orlistat 120 mg three times a day for 6 days, orlistat did not alter the pharmacokinetics of a single dose of digoxin.
Fat-soluble Vitamin Supplements and Analogues
A pharmacokinetic interaction study showed a 30% reduction in beta-carotene supplement absorption when concomitantly administered with orlistat. Orlistat inhibited absorption of a vitamin E acetate supplement by approximately 60%. The effect of orlistat on the absorption of supplemental vitamin D, vitamin A, and nutritionally-derived vitamin K is not known.
Glyburide
In 12 normal-weight subjects receiving orlistat 80 mg three times a day for 5 days, orlistat did not alter the pharmacokinetics or pharmacodynamics (blood glucose-lowering) of glyburide.
Nifedipine(extended-releasetablets)
In 17 normal-weight subjects receiving orlistat 120 mg three times a day for 6 days, orlistat did not alter the bioavailability of nifedipine (extended-release tablets).
Oral Contraceptives
In 20 normal-weight female subjects, the treatment of orlistat 120 mg three times a day for 23 days resulted in no changes in the ovulation-suppressing action of oral contraceptives.
Phenytoin
In 12 normal-weight subjects receiving orlistat 120 mg three times a day for 7 days, orlistat did not alter the pharmacokinetics of a single 300-mg dose of phenytoin.
Pravastatin
In a 2-way crossover study of 24 normal-weight, mildly hypercholesterolemic patients receiving orlistat 120 mg three times a day for 6 days, orlistat did not affect the pharmacokinetics of pravastatin.
Warfarin
In 12 normal-weight subjects, administration of orlistat 120 mg three times a day for 16 days did not result in any change in either warfarin pharmacokinetics (both R- and S-enantiomers) or pharmacodynamics (prothrombin time and serum Factor VII). Although undercarboxylated osteocalcin, a marker of vitamin K nutritional status, was unaltered with orlistat administration, vitamin K levels tended to decline in subjects taking orlistat [see Drug Interactions (7)].
XENICAL® is a registered trademark of CHEPLAPHARM Arzneimittel GmbH.
Licensed by:
CHEPLAPHARM Arzneimittel GmbH
Ziegelhof 24
17489 Greifswald, Germany
Distributed by:
H2-Pharma, LLC
611 Industrial Park Blvd
Montgomery, AL 36117, USA
© 2026 CHEPLAPHARM Arzneimittel GmbH. All rights reserved.
Representative sample of labeling (see the HOW SUPPLIED section for complete listing):