Adverse Reactions in Adults with Hypercholesterolemia
The data in Table 1 are derived from 9 primary hypercholesterolemia placebo-controlled trials that included 2,476 adult patients treated with PRALUENT 75 mg and/or 150 mg every 2 weeks, including 2,135 exposed for 6 months and 1,999 exposed for more than 1 year (median treatment duration of 65 weeks). The mean age of the population was 59 years, 40% of the population were female, 90% were White, 4% were Black or African American, 3% were Asian, and 3% other races; 6% identified as Hispanic or Latino ethnicity.
Adverse reactions reported in at least 2% of PRALUENT-treated patients, and more frequently than in placebo-treated patients, are shown in Table 1.
Table 1: Adverse Reactions Occurring in >2% of PRALUENT-Treated Adult Patients and ≥1% More Frequently Than with Placebo| Adverse Reactions | Placebo
(N=1,276)
% | PRALUENT 75 mg every 2 weeks and 150 mg every 2 weeks combined
(N=2,476)
% |
|---|
| Injection site reactions Includes erythema/redness, itching, swelling, pain/tenderness | 5 | 7 |
| Influenza | 5 | 6 |
| Diarrhea | 4 | 5 |
| Myalgia | 3 | 4 |
| Muscle spasms | 2 | 3 |
| Contusion | 1 | 2 |
Adverse reactions led to discontinuation of treatment in 5.3% of patients treated with PRALUENT and 5.1% of patients treated with placebo. The most common adverse reactions leading to treatment discontinuation in patients treated with PRALUENT were allergic reactions (0.6% versus 0.2% for PRALUENT and placebo, respectively) and elevated liver enzymes (0.3% versus <0.1%).
In an analysis of ezetimibe-controlled trials in which 864 patients were exposed to PRALUENT for a median of 27 weeks and 618 patients were exposed to ezetimibe for a median of 24 weeks, the types and frequencies of common adverse reactions were similar to those listed above.
Adverse Reactions in a Cardiovascular Outcomes Trial in Adults
In a CV outcomes trial in which 9,451 patients were exposed to PRALUENT for a median of 31 months and 9,443 patients were exposed to placebo for a median of 32 months, common adverse reactions (greater than 5% of patients treated with PRALUENT and occurring more frequently than placebo) included myalgia (6% PRALUENT, 5% placebo).
Adverse Reactions in Pediatric Patients with HeFH
In a 24-week placebo-controlled clinical trial in which 101 pediatric patients aged 8 to 17 years with HeFH were exposed to PRALUENT and 52 pediatric patients with HeFH were exposed to placebo [see Clinical Studies (14.3)], the safety profile of PRALUENT observed in this population was consistent with the safety profile observed in adults with HeFH.
Other Adverse Reactions
Local Injection Site Reactions
In a pool of placebo-controlled trials evaluating PRALUENT 75 mg and/or 150 mg administered every 2 weeks in adults, local injection site reactions including erythema/redness, itching, swelling, and pain/tenderness were reported more frequently in patients treated with PRALUENT (7.2% versus 5.1% for PRALUENT and placebo, respectively). Few patients discontinued treatment because of these reactions (0.2% versus 0.4% for PRALUENT and placebo, respectively), but patients receiving PRALUENT had a greater number of injection site reactions, had more reports of associated symptoms, and had reactions of longer average duration than patients receiving placebo.
In a 48-week placebo-controlled trial evaluating PRALUENT 300 mg every 4 weeks and 75 mg every 2 weeks in adults, in which all patients received an injection of drug or placebo every 2 weeks, local injection site reactions were reported more frequently in patients treated with PRALUENT 300 mg every 4 weeks as compared to those receiving PRALUENT 75 mg every 2 weeks or placebo (16.6%, 9.6%, and 7.9%, respectively). Three patients (0.7%) treated with PRALUENT 300 mg every 4 weeks discontinued treatment due to local injection site reactions versus no patients (0%) in the other 2 treatment groups.
In a CV outcomes trial in adults, local injection site reactions were reported in 3.8% of patients treated with PRALUENT versus 2.1% patients treated with placebo, and led to permanent discontinuation in 26 patients (0.3%) versus 3 patients (<0.1%), respectively.
In the trial of pediatric patients with HeFH, local injection site reactions were reported in 5% of patients treated with PRALUENT versus 0% patients treated with placebo; no patients discontinued treatment due to injection site reactions.
Hypersensitivity Reactions in Adults
Hypersensitivity reactions were reported more frequently in adult patients treated with PRALUENT than in those treated with placebo (8.6% versus 7.8%). The most common hypersensitivity reaction was pruritus (1.1% versus 0.4% for PRALUENT and placebo, respectively). The proportion of patients who discontinued treatment due to allergic reactions was higher among those treated with PRALUENT (0.6% versus 0.2%).
Serious allergic reactions, such as hypersensitivity, nummular eczema, and hypersensitivity vasculitis were reported in patients using PRALUENT in controlled clinical trials.
Liver Enzyme Abnormalities in Adults
In the hypercholesterolemia trials in adults, liver-related disorders (primarily related to abnormalities in liver enzymes) were reported in 2.5% of patients treated with PRALUENT and 1.8% of patients treated with placebo, leading to treatment discontinuation in 0.4% and 0.2% of patients, respectively. Increases in serum transaminases to greater than 3 times the upper limit of normal occurred in 1.7% of patients treated with PRALUENT and 1.4% of patients treated with placebo.
Risk Summary
Available data from clinical trials and postmarketing reports on PRALUENT use in pregnant women are insufficient to evaluate for a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes. In animal reproduction studies, there were no effects on embryo-fetal development when rats were subcutaneously administered alirocumab during organogenesis at dose exposures up to 12-fold the exposure at the maximum recommended human dose of 150 mg every two weeks. In monkeys, suppression of the humoral immune response was observed in infant monkeys when alirocumab was dosed during organogenesis to parturition at dose exposures 13-fold the exposure at the maximum recommended human dose of 150 mg every two weeks. No additional effects on pregnancy or neonatal/infant development were observed at dose exposures up to 81-fold the maximum recommended human dose of 150 mg every two weeks. Measurable alirocumab serum concentrations were observed in the infant monkeys at birth at comparable levels to maternal serum, indicating that alirocumab, like other IgG antibodies, crosses the placental barrier. Monoclonal antibodies are transported across the placenta in increasing amounts especially near term; therefore, alirocumab has the potential to be transmitted from the mother to the developing fetus.
The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively.
There is a pregnancy safety study for PRALUENT. If PRALUENT is administered during pregnancy, healthcare providers should report PRALUENT exposure by contacting Regeneron at 1-844-734-6643.
Data
Animal data
In Sprague Dawley rats, no effects on embryo-fetal development were observed when alirocumab was dosed at up to 75 mg/kg/dose by the subcutaneous route on gestation days 6 and 12 at exposures 12-fold the maximum recommended human dose of 150 mg every two weeks, based on serum AUC.
In cynomolgus monkeys, suppression of the humoral immune response to keyhole limpet hemocyanin (KLH) antigen was observed in infant monkeys at 4 to 6 months of age when alirocumab was dosed during organogenesis to parturition at 15 mg/kg/week and 75 mg/kg/week by the subcutaneous route, corresponding to 13-fold and 81-fold the human exposure at the maximum recommended human dose of 150 mg every two weeks, based on serum AUC. The lowest dose tested in the monkey resulted in humoral immune suppression; therefore, it is unknown if this effect would be observed at clinical exposure. No study designed to challenge the immune system of infant monkeys was conducted. No additional embryo-fetal, prenatal or postnatal effects were observed in infant monkeys, and no maternal effects were observed, when alirocumab was dosed at up to 75 mg/kg/week by the subcutaneous route, corresponding to maternal exposure of 81-fold the exposure at the maximum recommended human dose of 150 mg every two weeks, based on serum AUC.
Risk Summary
There is no information regarding the presence of alirocumab in human milk, the effects on the breastfed infant, or the effects on milk production. The development and health benefits of breastfeeding should be considered along with the mother's clinical need for PRALUENT and any potential adverse effects on the breastfed infant from PRALUENT or from the underlying maternal condition. Human IgG is present in human milk, but published data suggest that breast milk IgG antibodies do not enter the neonatal and infant circulation in substantial amounts.
Absorption
After subcutaneous administration of 75 mg to 300 mg alirocumab, median times to maximum serum concentrations (tmax) were 3-7 days. The pharmacokinetics of alirocumab after single subcutaneous administration of 75 mg into the abdomen, upper arm, or thigh were similar. The absolute bioavailability of alirocumab after subcutaneous administration was about 85% as determined by population pharmacokinetics analysis. A slightly greater than dose proportional increase was observed, with a 2.1-fold to 2.7-fold increase in total alirocumab concentrations for a 2-fold increase in dose from 75 mg every 2 weeks to 150 mg every 2 weeks. Monthly dose normalized exposure with 300 mg every 4 weeks treatment was similar to that of 150 mg every 2 weeks. Steady state was reached after 2 to 3 doses with an accumulation ratio up to a maximum of about 2-fold.
Distribution
Following intravenous administration, the volume of distribution was about 0.04 to 0.05 L/kg indicating that alirocumab is distributed primarily in the circulatory system.
Elimination
Specific metabolism studies were not conducted, because alirocumab is a protein. Alirocumab is expected to degrade to small peptides and individual amino acids. In clinical studies where alirocumab was administered in combination with atorvastatin or rosuvastatin, no relevant changes in statin concentrations were observed in the presence of repeated administration of alirocumab, indicating that cytochrome P450 enzymes (mainly CYP3A4 and CYP2C9) and transporter proteins such as P-gp and OATP were not affected by alirocumab.
Two elimination phases were observed for alirocumab. At low concentrations, the elimination is predominately through saturable binding to target (PCSK9), while at higher concentrations the elimination of alirocumab is largely through a non-saturable proteolytic pathway.
Based on a population pharmacokinetic analysis, the median apparent half-life of alirocumab at steady state was 17 to 20 days in patients receiving alirocumab at subcutaneous doses of 75 mg every 2 weeks or 150 mg every 2 weeks.
Specific Populations
A population pharmacokinetic analysis was conducted on data from 2799 patients. Age, body weight, gender, race, and creatinine clearance were found not to significantly influence alirocumab pharmacokinetics.
Pediatric Patients
The pharmacokinetics of alirocumab were evaluated in 140 pediatric patients aged 8 to 17 years with HeFH. Steady-state concentrations were reached at or before week 8 (first PK sampling during repeated dosing) with recommended dosing regimen [see Dosage and Administration (2.2)].
Renal Impairment
Since monoclonal antibodies are not known to be eliminated via renal pathways, renal function is not expected to impact the pharmacokinetics of alirocumab.
No data are available in patients with severe renal impairment.
Hepatic Impairment
Following administration of a single 75 mg SC dose, alirocumab pharmacokinetic profiles in patients with mild and moderate hepatic impairment were similar to those in patients with normal hepatic function.
No data are available in patients with severe hepatic impairment.
Drug-Drug Interactions
The median apparent half-life of alirocumab is reduced to 12 days when administered with a statin; however, this difference is not clinically meaningful.
Baseline Disease and Demographic Characteristics
The mean age at baseline was 59 years (range 39-92), with 25% female, and 27% at least 65 years old. The trial population was 79% White, 3% Black or African American and 13% Asian; 17% identified as Hispanic or Latino ethnicity. The index ACS event was a myocardial infarction in 83% of patients and unstable angina in 17% of patients. Prior to the index ACS event, 19% had prior myocardial infarction and 23% had coronary revascularization procedures (CABG/PCI). Selected additional baseline risk factors included hypertension (65%), diabetes mellitus (25%), New York Heart Association class I or II congestive heart failure (15%), and eGFR <60 mL/min/1.73 m2 (13%). Most patients (89%) were receiving statin-intensive therapy with or without other LMT at randomization. The mean LDL-C value at baseline was 92.4 mg/dL.
Endpoint Results
PRALUENT significantly reduced the risk for the primary composite endpoint (time to first occurrence of coronary heart disease death, non-fatal myocardial infarction, fatal and non-fatal ischemic stroke, or unstable angina requiring hospitalization: p=0.0003). The results are presented in Table 2.
Table 2: Cardiovascular Outcomes in Adult Patients with Established Cardiovascular Disease| Endpoint | PRALUENT
N=9,462 | Placebo
N=9,462 | Hazard Ratio
(95% CI)Cox-proportional hazards model with treatment as a factor and stratified by geographic region |
|---|
| n (%) | Incidence Rate per 100 Patient Years
(95% CI) | n (%) | Incidence Rate per 100 Patient Years
(95% CI) |
|---|
| Primary composite endpoint Primary composite endpoint defined as: time to first occurrence of coronary heart disease death, non-fatal myocardial infarction, fatal and non-fatal ischemic stroke, or unstable angina requiring hospitalization | 903
(9.5%) | 3.5
(3.3 to 3.8) | 1052
(11.1%) | 4.2
(3.9 to 4.4) | 0.85
(0.78, 0.93) |
| Components of the Primary Composite Endpoint First occurrence of specified event at any time; patients may have experienced more than one adjudicated event |
| CHD death | 205
(2.2%) | 0.8
(0.7 to 0.9) | 222
(2.3%) | 0.8
(0.7 to 0.9) | 0.92
(0.76, 1.11) |
| Non-fatal MI Statistical testing performed outside hierarchy; therefore not considered statistically significant | 626
(6.6%) | 2.4
(2.2 to 2.6) | 722
(7.6%) | 2.8
(2.6 to 3.0) | 0.86
(0.77, 0.96) |
| Fatal or non-fatal ischemic stroke | 111
(1.2%) | 0.4
(0.3 to 0.5) | 152
(1.6%) | 0.6
(0.5 to 0.7) | 0.73
(0.57, 0.93) |
| Unstable angina requiring hospitalization | 37
(0.4%) | 0.1
(0.1 to 0.2) | 60
(0.6%) | 0.2
(0.2 to 0.3) | 0.61
(0.41, 0.92) |
| Mortality Endpoint (not statistically significant per pre-specified method to control for type I error) |
| All-cause mortality | 334
(3.5%) | 1.2
(1.1 to 1.4) | 392
(4.1%) | 1.5
(1.3 to 1.6) | 0.85
(0.73, 0.98) |
The Kaplan-Meier estimates of the cumulative incidence of the primary endpoint over time is presented in Figure 1.
Figure 1: Primary Composite Endpoint Cumulative Incidence over 4 Years in ODYSSEY OUTCOMES
Primary Hypercholesterolemia
Trial 2 (ODYSSEY LONG TERM, NCT01507831) was a multicenter, double-blind, placebo-controlled trial that randomly assigned 1,553 adult patients to PRALUENT 150 mg every 2 weeks and 788 adult patients to placebo. All patients were taking maximally tolerated doses of statins with or without other lipid-modifying therapy and required additional LDL-C reduction.
Baseline Disease and Demographic Characteristics
The mean age was 61 years (range 18-89), 38% were female, 93% were White, 3% were Black or African American, and 5% identified as Hispanic or Latino ethnicity. The average LDL-C at baseline was 122 mg/dL.
Endpoint Results
At week 24, the treatment difference between PRALUENT and placebo in mean LDL-C percent change was -58% (95% CI: -61%, -56%; p-value: ˂0.0001).
The proportion of patients who prematurely discontinued trial drug prior to the 24-week primary endpoint was 8% among those treated with PRALUENT and 8% among those treated with placebo.
For additional results see Table 3 and Figure 2.
Table 3: Mean Percent Change from Baseline and DifferenceDifference is PRALUENT minus Placebo
from Placebo in Lipid Parameters at Week 24 in ODYSSEY LONG TERMA pattern-mixture model approach was used with multiple imputation of missing post-treatment values based on a patient's own baseline value and multiple imputation of missing on-treatment values based on a model including available on-treatment values
| Treatment Group | LDL-C | Total-C | Non-HDL-C | Apo B |
|---|
| Week 24 (Mean Percent Change from Baseline) |
| Placebo (n=788) | 1 | 0 | 1 | 1 |
| PRALUENT 150 mg (n=1,553) | -58 | -36 | -49 | -50 |
Difference from placebo (LS Mean)
(95% CI) | -58
(-61, -56) | -36
(-37, -34) | -50
(-52, -47) | -51
(-53, -48) |
| a The means were estimated based on all randomized patients, with multiple imputation of missing data taking into account treatment adherence |
| b Number of patients with observed data |
| Figure 2: Mean Percent Change from Baseline in LDL-C Over 52 Weeks in Adult Patients on Maximally Tolerated Statin Treated with PRALUENT 150 mg Every 2 Weeks and Placebo Every 2 Weeks (ODYSSEY LONG TERM)a |
|
Trial 3 (ODYSSEY COMBO I, NCT01644175) was a multicenter, double-blind, placebo-controlled trial that randomly assigned 209 adult patients to PRALUENT and 107 adult patients to placebo. Patients were taking maximally tolerated doses of statins with or without other lipid-modifying therapy and required additional LDL-C reduction.
Baseline Disease and Demographic Characteristics
The mean age was 63 years (range 39-87), 34% were female, 82% were White, 16% were Black or African American, and 11% were Hispanic or Latino. Mean baseline LDL-C was 102 mg/dL.
Endpoint Results
At week 12, the mean percent change from baseline in LDL-C was -45% with PRALUENT compared to 1% with placebo, and the treatment difference between PRALUENT 75 mg every 2 weeks and placebo in mean LDL-C percent change was -46% (95% CI: -53%, -39%).
At week 12, if additional LDL-C lowering was required based on pre-specified LDL-C criteria, PRALUENT was up-titrated to 150 mg every 2 weeks for the remainder of the trial. The dose was up-titrated to 150 mg every 2 weeks in 32 (17%) of 191 patients treated with PRALUENT for at least 12 weeks. At week 24, the mean percent change from baseline in LDL-C was -44% with PRALUENT and -2% with placebo, and the treatment difference between PRALUENT and placebo in mean LDL-C percent change was -43% (95% CI: -50%, -35%; p-value: ˂0.0001).
The proportion of patients who prematurely discontinued trial drug prior to the 24-week primary endpoint was 11% among those treated with PRALUENT and 12% among those treated with placebo.
Trials 4 (ODYSSEY FH I, NCT01623115) and 5 (ODYSSEY FH II, NCT01709500) were multicenter, double-blind, placebo-controlled trials that, combined, randomly assigned 490 adult patients to PRALUENT and 245 adult patients to placebo. The trials were similar with regard to both design and eligibility criteria. All patients had HeFH, were taking a maximally tolerated dose of statin with or without other lipid-modifying therapy, and required additional LDL-C reduction. The diagnosis of HeFH was made either by genotyping or clinical criteria ("definite FH" using either the Simon Broome or WHO/Dutch Lipid Network criteria).
Baseline Disease and Demographic Characteristics
The mean age was 52 years (range 20-87), 45% were female, 94% were White, 1% were Black or African American, and 3% identified as Hispanic or Latino ethnicity. The average LDL-C at baseline was 141 mg/dL.
Endpoint Results
At week 12, the treatment difference between PRALUENT 75 mg every 2 weeks and placebo in mean LDL-C percent change was -48% (95% CI: -52%, -44%).
At week 12, if additional LDL-C lowering was required based on pre-specified LDL-C criteria, PRALUENT was up-titrated to 150 mg every 2 weeks for the remainder of the trials. The dose was up-titrated to 150 mg every 2 weeks in 196 (42%) of 469 patients treated with PRALUENT for at least 12 weeks. At week 24, the mean treatment difference between PRALUENT and placebo in mean LDL-C percent change from baseline was -54% (95% CI: -59%, -50%; p-value: ˂0.0001). The LDL-C-lowering effect was sustained to week 52.
Considering both trials together, the proportion of patients who prematurely discontinued trial drug prior to the 24-week primary endpoint was 6% among those treated with PRALUENT and 4% among those treated with placebo.
For additional results see Table 4 and Figure 3.
Table 4: Mean Percent Change from Baseline and DifferenceDifference is PRALUENT minus Placebo
from Placebo in Lipid Parameters at Week 12 and Week 24 in Adult Patients with HeFH (ODYSSEY FH I and FH II Pooled)A pattern-mixture model approach was used with multiple imputation of missing post-treatment values based on a patient's own baseline value and multiple imputation of missing on-treatment values based on a model including available on-treatment values
| Treatment Group | LDL-C | Total-C | Non-HDL-C | Apo B |
|---|
| Week 12 (Mean Percent Change from Baseline) |
| Placebo (n=245) | 5 | 4 | 5 | 2 |
| PRALUENT 75 mg (n=490) | -43 | -27 | -38 | -34 |
Difference from placebo (LS Mean)
(95% CI) | -48
(-52, -44) | -31
(-34, -28) | -42
(-46, -39) | -36
(-39, -33) |
| Week 24 (Mean Percent Change from Baseline) |
| Placebo (n=245) | 7 | 5 | 7 | 2 |
| PRALUENT 75 mg/150 mg Dose was up-titrated to 150 mg every 2 weeks in 196 (42%) patients treated for at least 12 weeks (n=490) | -47 | -30 | -42 | -40 |
Difference from placebo (LS Mean)
(95% CI) | -54
(-59, -50) | -36
(-39, -33) | -49
(-53, -45) | -42
(-45, -39) |
| a The means were estimated based on all randomized patients, with multiple imputation of missing data taking into account treatment adherence |
| b Number of patients with observed data |
| Figure 3: Mean Percent Change from Baseline in LDL-C Over 52 Weeks in Adult Patients with HeFH on Maximally Tolerated Statin Treated with PRALUENT 75/150 mg Every 2 Weeks and Placebo every 2 weeks (ODYSSEY FH I and FH II Pooled)a |
|
Trial 6 (ODYSSEY HIGH FH, NCT01617655) was a multicenter, double-blind, placebo-controlled trial that randomly assigned 72 adult patients to PRALUENT 150 mg every 2 weeks and 35 adult patients to placebo. Patients had HeFH with a baseline LDL-C ≥160 mg/dL while taking a maximally tolerated dose of statin with or without other lipid-modifying therapy.
Baseline Disease and Demographic Characteristics
The mean age was 51 years (range 18-80), 47% were female, 88% were White, 2% were Black or African American, and 6% identified as Hispanic or Latino ethnicity. The average LDL-C at baseline was 198 mg/dL.
Endpoint Results
At week 24, the mean percent change from baseline in LDL-C was -43% with PRALUENT and -7% with placebo, and the treatment difference between PRALUENT and placebo in mean LDL-C percent change was -36% (95% CI: -49%, -24%; p-value: <0.0001).
The proportion of patients who discontinued trial drug prior to the 24-week primary endpoint was 10% among those treated with PRALUENT and 0% among those treated with placebo.
Trial 7 (ODYSSEY CHOICE I, NCT01926782) was a multicenter, double-blind, placebo-controlled trial that randomly assigned 458 adult patients with hypercholesterolemia to PRALUENT 300 mg every 4 weeks, 115 adult patients to PRALUENT 75 mg every 2 weeks, and 230 adult patients to placebo. Patients were stratified based on whether or not they were treated concomitantly with statin.
Baseline Disease and Demographic Characteristics
The mean age was 61 years (range 21-88), 42% were female, 87% were White, 11% were Black or African American, and 3% identified as Hispanic or Latino ethnicity.
Endpoint Results
In the cohort of patients on background statin, the mean LDL-C at baseline was 113 mg/dL. At week 12, the treatment difference between PRALUENT 300 mg every 4 weeks and placebo in mean percent change in LDL-C from baseline was -54% (97.5% CI: -61%, -48%), and the treatment difference between PRALUENT 75 mg every 2 weeks and placebo in mean percent change in LDL-C was -44% (97.5% CI: -53%, -35%) (Figure 4).
| Figure 4: Mean Percent Change from Baseline in LDL-C up to Week 12 in Adult Patients on Concomitant Statin Treated with PRALUENT 75 mg Every 2 Weeks, PRALUENT 300 mg Every 4 Weeks or Placebo The means were estimated based on all randomized patients, with multiple imputation of missing data taking into account treatment adherence |
 Figure 4 (S Praluent 03a) |
At week 12, if additional LDL-C lowering was required based on pre-specified LDL-C criteria, PRALUENT was adjusted to 150 mg every 2 weeks for the remainder of the trial. The dose was adjusted to 150 mg every 2 weeks in approximately 20% of patients treated with PRALUENT 75 mg every 2 weeks or 300 mg every 4 weeks for at least 12 weeks.
At week 24, the treatment difference between initial assignment to PRALUENT 300 mg every 4 weeks and placebo in mean percent change in LDL-C from baseline was -56% (97.5% CI: -62%, -49%; p-value: <0.0001), and the treatment difference between initial assignment to PRALUENT 75 mg every 2 weeks and placebo in mean percent change in LDL-C from baseline was -48% (97.5% CI: -57%, -39%).
In the cohort of patients not treated with a concomitant statin, the mean LDL-C at baseline was 142 mg/dL. The treatment difference between PRALUENT and placebo were similar to the cohort of patients treated with a concomitant statin.
The proportion of patients who discontinued trial drug prior to the 24-week primary endpoint was 12% among those treated with PRALUENT 300 mg every 4 weeks, 14% among those treated with PRALUENT 75 mg every 2 weeks, and 15% among those treated with placebo.
Trial 8 (ODYSSEY ESCAPE, NCT02326220) was a multicenter, double-blind, placebo-controlled trial that randomly assigned adult patients with HeFH who were undergoing LDL apheresis to PRALUENT 150 mg every 2 weeks (N=41) or placebo (N=21). Patients were treated in combination with their usual LDL apheresis schedule for 6 weeks.
Baseline Disease and Demographic Characteristics
The mean age was 59 years (range 27-79), 42% were female, 97% were White, 3% were Black or African American, and 0% identified as Hispanic or Latino ethnicity. The mean LDL-C at baseline, measured before the apheresis procedure, was 181 mg/dL.
Endpoint Results
At week 6, the mean percent change from baseline in pre-apheresis LDL-C was -53% in patients in the PRALUENT group compared to 1% in patients who received placebo.
The proportion of patients who discontinued study drug prior to the 6-week endpoint was 2% among those treated with PRALUENT 150 mg every 2 weeks and 5% among those treated with placebo.
Trial 9 (ODYSSEY COMBO II, NCT01644188) was a multicenter, double-blind, ezetimibe-controlled trial that randomly assigned 479 adult patients to PRALUENT 75 mg every 2 weeks/150 mg every 2 weeks and 241 adult patients to ezetimibe 10 mg/day. Patients were taking a maximally tolerated dose of a statin and required additional LDL-C reduction.
Baseline Disease and Demographic Characteristics
The mean age was 62 years (range 29-88), 26% were female, 85% were White, 4% were Black or African American, and 3% identified as Hispanic or Latino ethnicity. Mean baseline LDL-C was 107 mg/dL.
Endpoint Results
At week 12, the mean percent change from baseline in LDL-C was -50% with PRALUENT compared to -22% with ezetimibe, and the treatment difference between PRALUENT and ezetimibe in mean LDL-C percent change was -28% (95% CI: -32%, -23%).
At week 12, if additional LDL-C lowering was required based on pre-specified LDL-C criteria, PRALUENT was up-titrated to 150 mg every 2 weeks for the remainder of the trial. The dose was up-titrated to 150 mg every 2 weeks in 82 (18%) of 446 patients treated with PRALUENT for at least 12 weeks. At week 24, the mean percent change from baseline in LDL-C was -48% with PRALUENT and -20% with ezetimibe, and the treatment difference between PRALUENT and ezetimibe in mean LDL-C percent change was -28% (95% CI: -33%, -23%; p-value: <0.0001).
The proportion of patients who prematurely discontinued trial drug prior to the 24-week primary endpoint was 9% among those treated with PRALUENT and 10% among those treated with ezetimibe.
Trial 10 (ODYSSEY MONO, NCT01644474) was a multicenter, double-blind, ezetimibe-controlled trial in adult patients with a moderate CV risk, not taking statins or other lipid-modifying therapies, and a baseline LDL-C between 100 mg/dL to 190 mg/dL that randomly assigned 52 patients to PRALUENT 75 mg every 2 weeks and 51 patients to ezetimibe 10 mg/day.
Baseline Disease and Demographic Characteristics
The mean age was 60 years (range 45-72), 47% were female, 90% were White and 10% were Black or African American, and 1% identified as Hispanic or Latino ethnicity. Mean baseline LDL-C was 140 mg/dL.
Endpoint Results
At week 12, the mean percent change from baseline in LDL-C was -48% with PRALUENT compared to -19% with ezetimibe, and the treatment difference between PRALUENT 75 mg every 2 weeks and ezetimibe in mean LDL-C percent change was -29% (95% CI: -37%, -22%). At week 12, if additional LDL-C lowering was required based on pre-specified LDL-C criteria, PRALUENT was up-titrated to 150 mg every 2 weeks for the remainder of the trial. The dose was up-titrated to 150 mg every 2 weeks in 14 (30%) of 46 patients treated with PRALUENT for at least 12 weeks. At week 24, the mean percent change from baseline in LDL-C was -45% with PRALUENT and -14% with ezetimibe, and the treatment difference between PRALUENT and ezetimibe in mean LDL-C percent change was -31% (95% CI: -40%, -22%; p-value: <0.0001).
The proportion of patients who prematurely discontinued trial drug prior to the 24-week endpoint was 15% among those treated with PRALUENT and 14% among those treated with ezetimibe.
Adult Patients with HoFH
Trial 11 (ODYSSEY HoFH, NCT03156621) was a multicenter, double-blind, placebo-controlled trial that randomly assigned 45 adult patients to PRALUENT 150 mg every 2 weeks and 24 adult patients to placebo. Patients were taking maximally tolerated doses of statins with or without other lipid-lowering therapy and required additional LDL-C reduction.
Randomization was stratified by LDL apheresis treatment status. The diagnosis of HoFH was made by either clinical diagnosis, which included a history of an untreated total cholesterol concentration >500 mg/dL together with either xanthoma before 10 years of age or with a history of total cholesterol >250 mg in both parents, or by genetic testing.
Baseline Disease and Demographic Characteristics
The mean age was 43 years (range 19-81), 51% were female, 78% were White, 3% were Black or African American, 17% were Asian, and 3% identified as Hispanic or Latino ethnicity. Mean baseline LDL-C was 283 mg/dL with 97% on statins, 72% on ezetimibe, and 14% on lomitapide.
Endpoint Results
At week 12, the treatment difference between PRALUENT and placebo in mean LDL-C percent change from baseline was -36% (95% CI: -51% to -20%; p <0.0001) (see Figure 5). For the effect of PRALUENT on lipid parameters as compared to placebo, see Table 5. No patient discontinued from the trial prior to the 12-week primary endpoint.
Patients with two LDL-receptor negative alleles (little to no residual function) had a minimal to absent response to PRALUENT.
Figure 5: LS Mean Percent Change from Baseline in LDL-C Over 12 Weeks in Adult Patients with HoFH (ODYSSEY HoFH)

Figure 5 (S Praluent 03b)
Table 5: Effect of PRALUENT on Lipid Parameters in Adult Patients with HoFH (LS Mean Percent Change from Baseline to Week 12 in ODYSSEY HoFH)| Treatment Group | LDL-C | Apo B | Non-HDL-C | Total Cholesterol |
|---|
| Placebo (n=24) | 9 | 7 | 8 | 7 |
| PRALUENT 150 mg every 2 weeks (n=45) | -27 | -23 | -25 | -20 |
| Difference from placebo (LS Mean) (95% CI) | -36
(-51, -20) | -30
(-42, -17) | -33
(-48, -18) | -27
(-39, -14) |
Baseline Disease and Demographic Characteristics
The diagnosis of HeFH was made based on criteria from Simon Broome Register Group (1991) or by genetic testing. The mean age was 13 years (range: 8 to 17 years); 57% female; 82% White, 2% Black or African American, 10% American Indian or Alaska Native, and <1% not reported; 18% Hispanic/Latino ethnicity. Mean body weight was 53kg. The mean LDL-C at baseline was 174mg/dL; Of the patients receiving PRALUENT once every 2 weeks with an optional up-titration, 99% were on statins and 7% were on ezetimibe at baseline. Of the patients receiving PRALUENT once every 4 weeks with an optional up-titration, 91% were on statins and 20% were on ezetimibe at baseline.
Endpoint Results
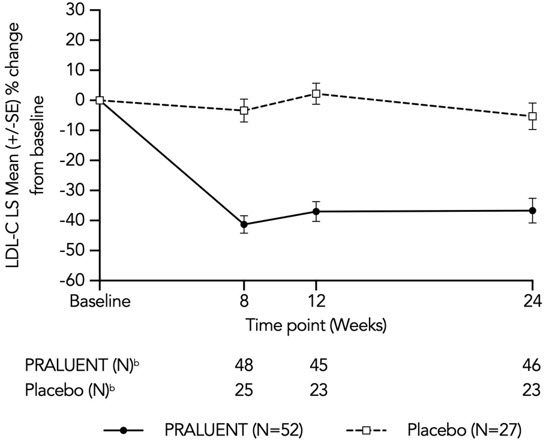
At week 24 in the group receiving treatment every 4 weeks, the treatment difference between the PRALUENT and placebo groups in LS mean LDL-C percent change from baseline was -31.4% (97.5% CI: -45.0 to -17.9; p<0.0001) (see Table 6 and Figure 6). For the effect of PRALUENT on lipid parameters as compared to placebo see Table 6.
| b Number of patients with observed data |
| Figure 6: LDL-C LS Mean Percent Change from Baseline Over Time Through Week 24 in Pediatric Patients (aged 8 to 17 years) with HeFH Treated with PRALUENT Every 4 Weeks or Placebo A pattern-mixture approach was used with multiple imputation of missing post-treatment values based on a patient's own baseline value and multiple imputation of missing on-treatment values based on a model including available on-treatment values |
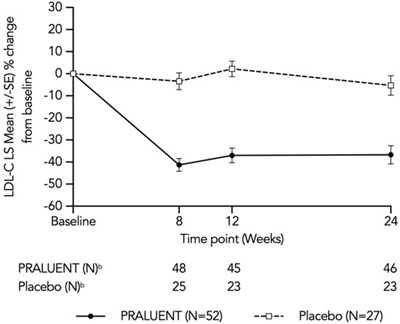 Figure 6 (S Praluent 03c) |
Table 6: Mean Percent Change from Baseline and Difference from Placebo in Lipid Parameters at Week 24 in Pediatric Patients (aged 8 to 17 years)| Treatment Group | LDL-C | Apo B | Non-HDL-C | Total Cholesterol |
|---|
| PRALUENT once every 4 weeks (150 mg for body weight less than 50 kg or 300 mg for body weight 50 kg or more) In the PRALUENT group 52 patients received a dose of 150 mg every 4 weeks (body weight less than 50 kg) or 300 mg every 4 weeks (body weight 50 kg or more). At week 12, a total of 15 (28.8%) patients had an automatic blinded dose adjustment to 75 mg every 2 weeks (body weight less than 50 kg) or 150 mg every 2 weeks (body weight 50 kg or more). |
| LS Mean: Placebo (n=27) | -5.2 | -3.3 | -4.1 | -4.4 |
| LS Mean: PRALUENT (n=52) | -36.6 | -33.0 | -34.2 | -26.7 |
| LS Mean Difference from Placebo (97.5% CI) | -31.4
(-45.0, -17.9) | -29.7
(-41.1, -18.2) | -30.1
(-43.0, -17.2) | -22.3
(-33.0, -11.6) |
| PRALUENT once every 2 weeks (40 mg for body weight less than 50 kg or 75 mg for body weight 50 kg or more) In the PRALUENT group dosed every 2 weeks, 49 patients received a dose of 40 mg for body weight less than 50 kg or 75 mg for body weight 50 kg or more. At week 12, a total of 22 (44.9%) patients had an automatic blinded dose adjustment to 75 mg every 2 weeks (body weight less than 50 kg) or 150 mg every 2 weeks (body weight 50 kg or more). ,The 40 mg dosage every 2 weeks is not approved |
| LS Mean: Placebo (n=25) | 9.7 | 10.4 | 9.7 | 7.4 |
| LS Mean: PRALUENT (n=49) | -31.9 | -25.7 | -29.5 | -22.4 |
| LS Mean Difference from Placebo (97.5% CI) | -41.7
(-54.2, -29.1) | -36.2
(-45.8, -26.5) | -39.2
(-50.6, -27.8) | -29.8
(-38.7, -21.0) |
Hypersensitivity Reactions
Inform patients that serious hypersensitivity reactions (e.g., angioedema) have been reported in patients treated with PRALUENT. Advise patients on the symptoms of hypersensitivity reactions and instruct them to discontinue PRALUENT and seek medical attention promptly, if such symptoms occur [see Warnings and Precautions (5.1)].
Administration
Provide guidance to patients and caregivers on proper subcutaneous injection technique and how to use the pre-filled pen. Inform patients that it may take up to 20 seconds to inject PRALUENT. Inform patients the pre-filled pen should be allowed to warm to room temperature for 30 to 40 minutes prior to use if refrigerated.
Pregnancy
Advise women who are exposed to PRALUENT during pregnancy that there is a pregnancy safety study that monitors pregnancy outcomes. Encourage these patients to report their pregnancy to Regeneron at 1 844-734-6643 [see Use in Specific Populations (8.1)].
Manufactured by:
Regeneron Pharmaceuticals, Inc.
Tarrytown, NY 10591
U.S. License # 1760
PRALUENT is a registered trademark of Regeneron Pharmaceuticals, Inc.
© 2025 Regeneron Pharmaceuticals, Inc. All rights reserved.