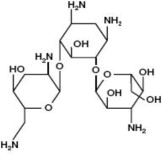
Other
Nephrotoxicity
Tobramycin for Injection can result in acute kidney injury, including acute renal failure. Risk factors that may contribute to nephrotoxicity include tobramycin accumulation (increasing serum trough levels), high peak concentrations (above 12 mcg/mL), total cumulative dose, advanced age, volume depletion and concurrent or sequential use of other nephrotoxic drugs. Avoid concurrent or sequential use of other potentially nephrotoxic drugs. Monitor serum tobramycin levels and renal function in all patients during drug treatment. Reduce the dose or discontinue the Tobramycin for Injection if renal impairment occurs [see Warnings and Precautions (5.1)].
Ototoxicity
Tobramycin for Injection can cause irreversible auditory and vestibular toxicity that may continue to develop after the drug has been discontinued. Risk factors include high serum concentrations, prolonged therapy, renal impairment, concurrent and sequential use of other nephrotoxic or ototoxic drugs (e.g. aminoglycosides), and extremes of age. Avoid concurrent or sequential use with other potentially ototoxic drugs. Monitor for signs and symptoms of auditory and vestibular toxicity. Reduce the dose or discontinue the Tobramycin for Injection if renal impairment occurs. Discontinue the Tobramycin for Injection if ototoxicity occurs. [see Warnings and Precautions (5.2)].
Neuromuscular Blockade
Aminoglycosides have been associated with neuromuscular blockade. During therapy with Tobramycin for Injection, monitor for adverse reactions associated with neuromuscular blockade, particularly in high-risk patients, such as patients with underlying neuromuscular disorders (including myasthenia gravis) or in patients concomitantly receiving neuromuscular blocking agents [see Warnings and Precautions (5.5)].
Embryo-Fetal Toxicity
Tobramycin and other aminoglycosides can cause fetal harm when administered to a pregnant woman. If Tobramycin for Injection is used during pregnancy or if the patient becomes pregnant while taking tobramycin, apprise the patient of the potential hazard to the fetus [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1)].
Pharmacy Bulk Package-Not for Direct Infusion
Tobramycin for Injection Pharmacy Bulk Package is intended for dispensing of single doses to many patients in a hospital pharmacy admixture service. It should only be prepared in an aseptic work area, such as a laminar flow hood. Tobramycin for Injection Pharmacy Bulk Package vial must be reconstituted and diluted prior to intravenous administration [see Dosage and Administration (2.8)]. After reconstitution, the closure may be penetrated only one time using a suitable sterile transfer device or dispensing set, which allows measured dispensing of the contents. Use of a syringe and needle is not recommended as it may cause leakage. After penetration, the entire contents of the bulk vial must be dispensed within 24 hours. Do not administer Tobramycin for Injection as a direct, undiluted intravenous injection.
Adult Patients
Adults with Serious Infections
3 mg/kg/day administered in 3 equal doses of 1 mg/kg every 8 hours.
Adults with Life-Threatening Infections
Up to 5 mg/kg/day may be administered in 3 or 4 equal doses (see Table 1). The dosage should be reduced to 3 mg/kg/day as soon as clinically indicated. To prevent increased toxicity due to excessive serum concentrations, dosage should not exceed 5 mg/kg/day unless serum concentrations are monitored [see Boxed Warning, Warnings and Precautions (5.2)].
| For Patient Weighing | Usual Dose for Serious Infections 1 mg/kg Every 8 hours (h) | ||
| kg | lb | (Total, 3 mg/kg/day) | |
| mg/dose | mL/dose* | ||
| q8h | |||
| 120 | 264 | 120 mg | 3 mL |
| 115 | 253 | 115 mg | 2.9 mL |
| 110 | 242 | 110 mg | 2.75 mL |
| 105 | 231 | 105 mg | 2.6 mL |
| 100 | 220 | 100 mg | 2.5 mL |
| 95 | 209 | 95 mg | 2.4 mL |
| 90 | 198 | 90 mg | 2.25 mL |
| 85 | 187 | 85 mg | 2.1 mL |
| 80 | 176 | 80 mg | 2 mL |
| 75 | 165 | 75 mg | 1.9 mL |
| 70 | 154 | 70 mg | 1.75 mL |
| 65 | 143 | 65 mg | 1.6 mL |
| 60 | 132 | 60 mg | 1.5 mL |
| 55 | 121 | 55 mg | 1.4 mL |
| 50 | 110 | 50 mg | 1.25 mL |
| 45 | 99 | 45 mg | 1.1 mL |
| 40 | 88 | 40 mg | 1 mL |
*Applicable to all product forms except the Tobramycin Injection, USP, (Pediatric). | |||||
| For Patient Weighing | Maximum Dose for Life- Threatening Infections (Reduce as soon as possible) 1.66 mg/kg Every 8 hours | ||||
| kg | lb | (Total, 5 mg/kg/day) | |||
| mg/dose | mL/dose* | ||||
| Every 8h | |||||
| 120 | 264 | 200 mg | 5 mL | ||
| 115 | 253 | 191 mg | 4.75 mL | ||
| 110 | 242 | 183 mg | 4.5 mL | ||
| 105 | 231 | 175 mg | 4.4 mL | ||
| 100 | 220 | 166 mg | 4.2 mL | ||
| 95 | 209 | 158 mg | 4 mL | ||
| 90 | 198 | 150 mg | 3.75 mL | ||
| 85 | 187 | 141 mg | 3.5 mL | ||
| 80 | 176 | 133 mg | 3.3 mL | ||
| 75 | 165 | 125 mg | 3.1 mL | ||
| 70 | 154 | 116 mg | 2.9 mL | ||
| 65 | 143 | 108 mg | 2.7 mL | ||
| 60 | 132 | 100 mg | 2.5 mL | ||
| 55 | 121 | 91 mg | 2.25 mL | ||
| 50 | 110 | 83 mg | 2.1 mL | ||
| 45 | 99 | 75 mg | 1.9 mL | ||
| 40 | 88 | 66 mg | 1.6 mL | ||
Pediatric Patients (Greater than 1 Week of Age):
6 to 7.5 mg/kg/day administered in 3 or 4 equally divided doses (2 to 2.5 mg/kg every 8 hours or 1.5 to 1.9 mg/kg every 6 hours).
Premature or Full-Term Neonates (1 Week of Age or Less):
Up to 4 mg/kg/day may be administered in 2 equal doses every 12 hours.
Reduced dosage at 8-hour intervals
When the creatinine clearance rate is less than or equal to 70 mL per minute or when the serum creatinine value is known, the amount of the reduced dose can be determined by multiplying the normal dose in adult patients from Table 1 by the percent of the normal dosage from the accompanying nomogram in Figure 1 below.
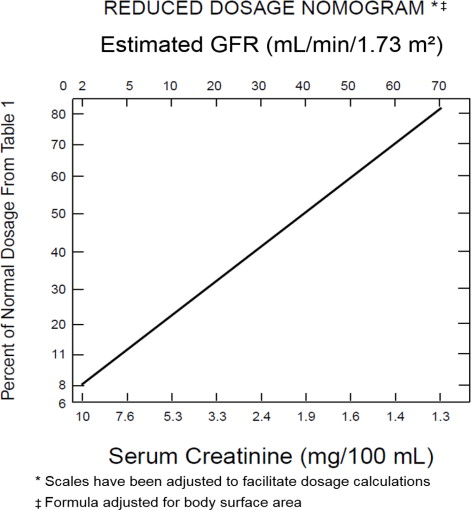
Figure 1: Nomogram (Tob0c 0000 01)
Normal dosage at prolonged intervals
If the creatinine clearance rate is not available and the patient's condition is stable, a dosage frequency in hours for the recommended adult dose can be determined by multiplying the patient's serum creatinine by 6.
Ototoxicity with use of Tobramycin for Injection
Tobramycin for Injection can cause both auditory and vestibular eighth nerve damage. The auditory changes are irreversible, are usually bilateral, and may be partial or total. Symptoms of ototoxicity can include dizziness, vertigo, tinnitus, roaring in the ears and hearing loss. Ototoxicity symptoms may manifest during therapy or after tobramycin has been discontinued. The risk of ototoxicity increases with higher peak and trough serum tobramycin concentrations, in patients who receive high doses or prolonged or prior treatment with tobramycin or other aminoglycosides, in patients with renal impairment, patients receiving with other nephrotoxic or ototoxic drugs and in the extremes of age. To decrease the risk of ototoxicity, use as short a duration of therapy as clinically appropriate, adequately hydrate patients, limit the use of other ototoxic drugs, and closely monitor tobramycin concentrations during therapy [see Dosage and Administration (2.9)]. Monitor patients for signs and symptoms of auditory or vestibular toxicity and consider serial audiograms in high-risk patients. Discontinue tobramycin in patients with evidence of auditory or vestibular toxicity.
Risk of Ototoxicity Due to Mitochondrial DNA Variants
Cases of ototoxicity with aminoglycosides have been observed in patients with certain variants in the mitochondrially encoded 12S rRNA gene (MT-RNR1), particularly the m.1555A>G variant. Ototoxicity occurred in some patients even when their aminoglycoside serum levels were within the recommended range. Mitochondrial DNA variants are present in less than 1% of the general US population, and the proportion of the variant carriers who may develop ototoxicity as well as the severity of ototoxicity is unknown. In case of known maternal history of ototoxicity due to aminoglycoside use or a known mitochondrial DNA variant in the patient, consider alternative treatments other than aminoglycosides unless the increased risk of permanent hearing loss is outweighed by the severity of infection and lack of safe and effective alternative therapies.
Risk Summary
Aminoglycosides, including Tobramycin for Injection, can cause fetal harm when administered to a pregnant woman. Published literature reports that use of streptomycin, an aminoglycoside, can cause total, irreversible, bilateral congenital deafness when administered to a pregnant woman [see Warnings and Precautions (5.3)]. In animal reproduction studies with subcutaneous administration of tobramycin in pregnant rats and rabbits during organogenesis, there were no adverse developmental outcomes at doses up to 3.2 times and 1.3 times the maximum recommended clinical dose based on body surface area; however, ototoxicity was not evaluated in the offspring from these studies (see Data). Advise pregnant women of the potential risk to a fetus.
The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively.
Data
Animal Data
Subcutaneous administration of tobramycin at doses of up to 100 mg/kg/day (rat) or 20 mg/kg/day (rabbit) during organogenesis was not associated with adverse developmental outcomes. These doses are 3.2 and 1.3 times the maximum recommended clinical daily dose of 5 mg/kg based on body surface area. Doses of tobramycin ≥40 mg/kg/day were maternally toxic to rabbits and precluded the evaluation of adverse developmental outcomes. Ototoxicity was not evaluated in offspring during nonclinical reproductive toxicity studies with tobramycin.
Risk Summary
Limited published data with Tobramycin for Injection in lactating women indicate that tobramycin is present in human milk. There are no data on the effects of Tobramycin for Injection on milk production. Tobramycin may cause alteration in the intestinal flora of the breastfeeding infant. Advise a woman to monitor the breastfed infant for loose or bloody stools and candidiasis (thrush, diaper rash).
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for Tobramycin for Injection and any potential adverse effects on the breastfed infant from Tobramycin for Injection or from the underlying maternal condition.
Absorption
Following intramuscular administration, peak serum concentrations of tobramycin occur between 30 and 90 minutes. Following an intramuscular dose of 1 mg/kg of body weight, maximum serum concentrations reach about 4 mcg/mL, and measurable concentrations persist for as long as 8 hours. Therapeutic serum concentrations are generally considered to range from 4 to 6 mcg/mL. When Tobramycin for Injection is administered by intravenous infusion over a 1-hour period, the serum concentrations are similar to those obtained by intramuscular administration. Tobramycin is poorly absorbed from the gastrointestinal tract.
Distribution
Based on ultrafiltration studies, practically no serum protein binding of tobramycin occurs.
Tobramycin can be detected in tissues and body fluids after parenteral administration. Concentrations of tobramycin in bile and stools ordinarily have been low, which suggests minimal biliary excretion. The concentration of tobramycin in cerebrospinal fluid following parenteral administration is low, and concentrations are dependent on dose, rate of penetration, and degree of meningeal inflammation. Tobramycin has also been detected in sputum, peritoneal fluid, synovial fluid, and abscess fluids, and it crosses the placental membranes. Concentrations in the renal cortex are several times higher than serum concentrations.
Metabolism
Following parenteral administration, minimal, metabolic transformation occurs, and tobramycin is eliminated almost exclusively by glomerular filtration.
Excretion
Peak urine concentrations ranging from 75 to 100 mcg/mL have been observed following the intramuscular injection of a single dose of 1 mg/kg. After several days of treatment, the amount of tobramycin excreted in the urine approaches the daily dose administered. Renal clearance is similar to that of endogenous creatinine. In patients with normal renal function, up to 84% of the dose is recoverable from the urine in 8 hours and up to 93% in 24 hours. When renal function is impaired, excretion of tobramycin is slowed, and accumulation of the drug may cause toxic blood concentrations.
Drug Interactions
Probenecid does not affect the renal tubular transport of tobramycin.
Mechanism of Action
Tobramycin is an aminoglycoside that inhibits protein synthesis by binding to the aminoacyl site (A) of the 16S RNA within the bacterial 30S ribosomal subunit. Tobramycin is bactericidal against susceptible bacteria.
Resistance
Resistance to aminoglycosides includes production of aminoglycoside modifying enzymes (AMEs), alteration of the ribosomal target through production of 16S rRNA methyltransferases, up-regulation of efflux pumps and reduced permeability into bacterial cell due to loss of outer membrane porins. Aminoglycosides are generally not active against most gram-positive organisms, including Streptococcus pyogenes, Streptococcus pneumoniae, and enterococci. Cross-resistance between aminoglycosides may occur.
Interaction with Other Antimicrobials
In vitro studies have shown that an aminoglycoside combined with an antibacterial that interferes with cell-wall synthesis, such as penicillin, results in a synergistic bactericidal effect in some isolates of Enterococcus faecalis. This combination is not synergistic against other closely related organisms, e.g., Enterococcus faecium. Species-level identification of enterococci alone cannot be used to predict susceptibility. Susceptibility testing and tests for antibacterial synergism must be performed.
Antimicrobial Activity
Tobramycin has been shown to be active against most isolates of the following bacteria both in vitro and in clinical infections [see Indications and Usage (1)]:
Gram-positive bacteria
Staphylococcus aureus
Gram-negative bacteria
Citrobacter species
Enterobacter species
Escherichia coli
Klebsiella species
Morganella morganii
Pseudomonas aeruginosa
Proteus mirabilis
Proteus vulgaris
Providencia species
Serratia species
Susceptibility Testing
For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
Carcinogenesis
Carcinogenicity studies in animals have not been conducted with Tobramycin for Injection.
Mutagenesis
Tobramycin has been evaluated for genotoxicity in a battery of in vitro and in vivo tests. The Ames bacterial reversion test, conducted with 5 tester strains, failed to show a significant increase in revertants with or without metabolic activation in all strains. Tobramycin was negative in the mouse lymphoma forward mutation assay, did not induce chromosomal aberrations in Chinese hamster ovary cells, and was negative in the mouse micronucleus test.
Impairment of Fertility
Subcutaneous administration of up to 100 mg/kg of tobramycin (3.2 times the maximum recommended clinical dose of 5 mg/kg/day based on body surface area) did not affect mating behavior or cause impairment of fertility in male or female rats.
Serious Allergic Reactions
Advise patients that serious allergic reactions could occur with Tobramycin for Injection. Advise patients to report fever, swelling, difficulty breathing, wheezing, decrease blood pressure or dizziness, or skin rash. If an allergic reaction occurs, discontinue the drug and institute appropriate therapy immediately.
Impairment of Kidney Function
Advise patients that Tobramycin for Injection may cause impairment in kidney function and that periodic blood draws are required to monitor kidney function and tobramycin drug levels.
Hearing Loss and Impaired Balance
Advise patients that Tobramycin for Injection may cause serious and irreversible hearing loss and impaired balance. Advise patients to report hearing loss, ringing or roaring in the ears, dizziness or imbalance.
Antibacterial Resistance
Counsel patients that antibacterial drugs, including Tobramycin for Injection should be used to treat bacterial infections only. They do not treat viral infections (e.g., the common cold). When Tobramycin for Injection is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be administered exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by Tobramycin for Injection or other antibacterial drugs in the future.
Diarrhea
Counsel patients that diarrhea is a common problem caused by antibacterials, and it usually ends when the antibacterial is discontinued. Sometimes after starting treatment with antibacterials, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as 2 or more months after having taken their last dose of the antibacterial. If this occurs, patients should contact their physician as soon as possible.
Embryofetal Toxicity
Advise pregnant women that aminoglycosides, including Tobramycin for Injection, can cause irreversible congenital deafness when administered to a pregnant woman [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1)].
Lactation
Advise a woman to monitor their breastfed infants for diarrhea and/or bloody stools [see Use in Specific Populations (8.2)].
Novaplus is a registered trademark of Vizient, Inc.
Manufactured by:
Fresenius Kabi
Lake Zurich, IL 60047
www.fresenius-kabi.com/us
451027D

Novaplus Logo (Tob0c 0000 03)