Complete Atrioventricular Block
Patients who receive Octreotide Acetate Injection intravenously may be at increased risk for higher degree atrioventricular blocks. In postmarketing reports, complete atrioventricular block was reported in patients receiving IV Octreotide Acetate Injection during surgical procedures. In the majority of patients, Octreotide Acetate Injection was given at higher than recommended doses and/or as a continuous IV infusion. The safety of continuous IV infusion has not been established in patients receiving Octreotide Acetate Injection for the approved indications.
Consider cardiac monitoring in patients receiving Octreotide Acetate Injection intravenously.
Other Cardiac Conduction Abnormalities
Other cardiac conduction abnormalities have occurred during treatment with Octreotide Acetate Injection. In acromegalic patients, bradycardia (< 50 bpm) developed in 25%; conduction abnormalities occurred in 10% and arrhythmias occurred in 9% of patients during Octreotide Acetate Injection therapy [see Adverse Reactions (6)]. Other electrocardiogram (ECG) changes observed included QT prolongation, axis shifts, early repolarization, low voltage, R/S transition, and early R-wave progression. These ECG changes are not uncommon in acromegalic patients. Dose adjustments in drugs such as beta-blockers that have bradycardia effects may be necessary. In one acromegalic patient with severe congestive heart failure (CHF), initiation of Octreotide Acetate Injection therapy resulted in worsening of CHF with improvement when drug was discontinued. Confirmation of a drug effect was obtained with a positive rechallenge.
Gallbladder Abnormalities
Gallbladder abnormalities, especially stones and/or biliary sludge, frequently develop in patients on chronic Octreotide Acetate Injection therapy [see Warnings and Precautions (5.1)]. In clinical trials (primarily patients with acromegaly or psoriasis), the incidence of biliary tract abnormalities was 63% (27% gallstones, 24% sludge without stones, 12% biliary duct dilatation). The incidence of stones or sludge in patients who received Octreotide Acetate Injection for 12 months or longer was 52%. Less than 2% of patients treated with Octreotide Acetate Injection for 1 month or less developed gallstones.
Cardiac
In acromegalics, sinus bradycardia (< 50 bpm) developed in 25%; conduction abnormalities occurred in 10% and arrhythmias developed in 9% of patients during Octreotide Acetate Injection therapy [see Warnings and Precautions (5.1)].
Gastrointestinal
Diarrhea, loose stools, nausea, and abdominal discomfort were each seen in 34% to 61% of acromegalic patients in U.S. studies. 2.6% of the patients discontinued therapy due to these symptoms. These symptoms were seen in 5% to 10% of patients with carcinoid tumors and VIPomas.
The frequency of these symptoms was not dose related, but diarrhea and abdominal discomfort generally resolved more quickly in patients treated with 300 mcg/day than in those treated with 750 mcg/day. Vomiting, flatulence, abnormal stools, abdominal distention, and constipation were each seen in less than 10% of patients.
In rare instances, gastrointestinal side effects may resemble acute intestinal obstruction, with progressive abdominal distension, severe epigastric pain, abdominal tenderness, and guarding.
Hypo/Hyperglycemia
Hypoglycemia and hyperglycemia occurred in 3% and 16% of acromegalic patients, respectively, but only in about 1.5% of other patients. Symptoms of hypoglycemia were noted in approximately 2% of patients.
Hypothyroidism
In acromegalics, biochemical hypothyroidism alone occurred in 12% while goiter occurred in 8% and 4% required initiation of thyroid replacement therapy during Octreotide Acetate Injection therapy [see Warnings and Precautions (5.4)]. In patients without acromegaly, hypothyroidism has only been reported in several isolated patients and goiter has not been reported.
Other Adverse Events
Pain on injection was reported in 7.7%, headache in 6%, and dizziness in 5%. Pancreatitis was also observed [see Warnings and Precautions (5.2)].
Other Adverse Events 1% to 4%
Other events, each observed in 1% to 4% of patients, included fatigue, weakness, pruritus, joint pain, backache, urinary tract infection, cold symptoms, flu symptoms, injection site hematoma, bruise, edema, flushing, blurred vision, pollakiuria, fat malabsorption, hair loss, visual disturbance, and depression.
Anaphylactoid reactions, including anaphylactic shock, have been reported in several patients receiving Octreotide Acetate Injection.
Risk Summary
The limited data with Octreotide Acetate Injection in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, no adverse developmental-effects were observed with IV administration of octreotide to pregnant rats and rabbits during organogenesis at doses 7- and 13-times, respectively the maximum recommended human dose (MRHD) of 1.5 mg/day based on body surface area (BSA). Transient growth retardation, with no impact on postnatal development, was observed in rat offspring from a pre- and post-natal study of octreotide at IV doses below the MRHD based on BSA (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Human Data
In postmarketing data, a limited number of exposed pregnancies have been reported in patients with acromegaly. Most women were exposed to octreotide during the first trimester of pregnancy at doses ranging from 100 to 300 mcg/day of Octreotide Acetate Injection or 20 mg to 30 mg once a month of octreotide acetate for injectable suspension, however some women elected to continue octreotide therapy throughout pregnancy. In cases with a known outcome, no congenital malformations were reported.
Animal Data
In embryo-fetal development studies in rats and rabbits, pregnant animals received IV doses of octreotide up to 1 mg/kg/day during the period of organogenesis. A slight reduction in body weight gain was noted in pregnant rats at 0.1 and 1 mg/kg/day. There were no maternal effects in rabbits or embryo-fetal effects in either species up to the maximum dose tested. At 1 mg/kg/day in rats and rabbits, the dose multiple was approximately 7- and 13-times, respectively, at the highest recommended human dose of 1.5 mg/day based on BSA.
In a pre- and post-natal development rat study at IV doses of 0.02-1 mg/kg/day, a transient growth retardation of the offspring was observed at all doses which was possibly a consequence of GH inhibition by octreotide. The doses attributed to the delayed growth are below the human dose of 1.5 mg/day, based on BSA.
Risk Summary
There is no information available on the presence of Octreotide Acetate Injection in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production. Studies show that octreotide administered subcutaneously passes into the milk of lactating rats; however, due to species-specific differences in lactation physiology, animal data may not reliably predict drug levels in human milk (see Data). The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for Octreotide Acetate Injection, and any potential adverse effects on the breastfed child from Octreotide Acetate Injection or from the underlying maternal condition.
Data
Following a subcutaneous dose (1 mg/kg) of octreotide to lactating rats, transfer of octreotide into milk was observed at a low concentration compared to plasma (milk/plasma ratio of 0.009).
Absorption
After subcutaneous injection, octreotide is absorbed rapidly and completely from the injection site. Peak concentrations of 5.2 ng/mL (100-mcg dose) were reached 0.4 hours after dosing. Using a specific radioimmunoassay, IV and subcutaneous doses were found to be bioequivalent. Peak concentrations and area under the curve (AUC) values were dose proportional after IV single doses up to 200 mcg and subcutaneous single doses up to 500 mcg and after subcutaneous multiple doses up to 500 mcg 3 times a day (1,500 mcg/day). In patients with acromegaly, a mean peak concentration of 2.8 ng/mL (100-mcg dose) was reached in 0.7 hours after subcutaneous dosing.
Distribution
In healthy volunteers, the distribution of octreotide from plasma was rapid (tα½ = 0.2 h), the volume of distribution (Vdss) was estimated to be 13.6 L, and the total body clearance ranged from 7 L/hr to 10 L/hr. In blood, the distribution into the erythrocytes was found to be negligible and about 65% was bound in the plasma in a concentration-independent manner. Binding was mainly to lipoprotein and, to a lesser extent, to albumin. In patients with acromegaly, the volume of distribution (Vdss) was estimated to be 21.6 ± 8.5 L, and the total body clearance was increased to 18 L/h. The mean percent of the drug bound was 41.2%.
Elimination
The elimination of octreotide from plasma had an apparent half-life of 1.7 to 1.9 hours compared with 1 to 3 minutes with the natural hormone. The duration of action of Octreotide Acetate Injection is variable but extends up to 12 hours depending upon the type of tumor. About 32% of the dose is excreted unchanged into the urine. In an elderly population, dose adjustments may be necessary due to a significant increase in the half-life (46%) and a significant decrease in the clearance (26%) of the drug.
In patients with acromegaly, the disposition and elimination half-lives were similar to normal subjects.
Specific Populations
Renal Impairment
In patients with mild renal impairment (CLCR 40 to 60 mL/min), octreotide t1/2 was 2.4 hours and total body clearance was 8.8 L/hr, in moderate impairment (CLCR 10 to 39 mL/min) t1/2 was 3.0 hours and total body clearance 7.3 L/hr. In patients with severe renal impairment not requiring dialysis (CLCR < 10 mL/min), octreotide t1/2 was 3.1 hours and total body clearance was 7.6 L/hr. In patients with severe renal failure requiring dialysis, total body clearance was reduced to about half that found in healthy subjects (from approximately 10 L/hr to 4.5 L/hr).
Hepatic Impairment
Patients with liver cirrhosis showed prolonged elimination of drug, with octreotide t1/2 increasing to 3.7 hr and total body clearance decreasing to 5.9 L/hr, whereas patients with fatty liver disease showed t1/2 increased to 3.4 hr and total body clearance of 8.2 L/hr.
How Supplied
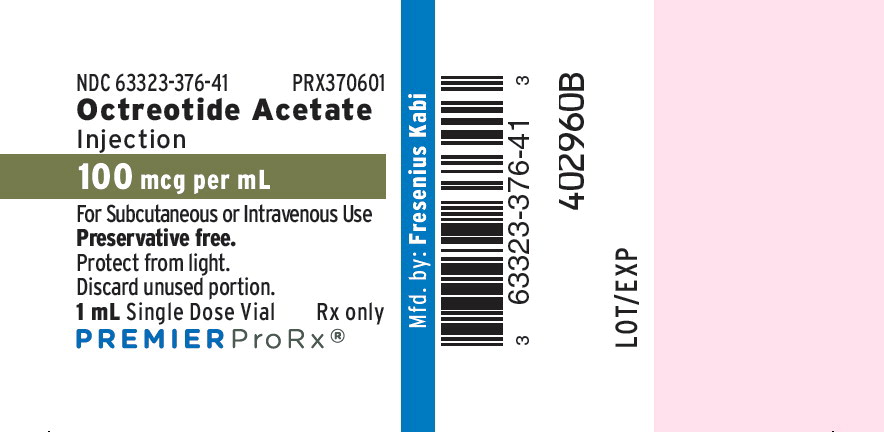
Octreotide Acetate Injection is available as follows:
Preservative Free Single Dose Vials:
| Product Code | Unit of Sale | Strength | Each |
| PRX370601
| NDC 63323-376-04
Unit of 10
| 100 mcg per mL,
1 mL fill in a 2
mL vial
| NDC 63323-376-41
1 mL Single Dose Vial
|
| PRX370701
| NDC 63323-377-04
Unit of 10
| 500 mcg per mL,
1 mL fill in a 2
mL vial
| NDC 63323-377-41
1 mL Single Dose Vial
|
Sterile Subcutaneous Injection Technique
Careful instruction in sterile subcutaneous injection technique should be given to the patients and to other persons who may administer Octreotide Acetate Injection.
Cholelithiasis and Complications of Cholelithiasis
Advise patients to contact their healthcare provider if they experience signs or symptoms of gallstones (cholelithiasis) or complications of cholelithiasis (e.g., cholecystitis, cholangitis, and pancreatitis) [see Warnings and Precautions (5.2)].
Pregnancy
Inform female patients that treatment with Octreotide Acetate Injection may result in unintended pregnancy [see Use in Specific Populations (8.3)].
PREMIERProRx® is a registered trademark of Premier Healthcare Alliance, L.P., used under license.
Manufactured by:
Fresenius Kabi
Lake Zurich, IL 60047
www.fresenius-kabi.com/us
451396C
Revised: April 2024

Premierprorx Logo (Oct04 0002 02)