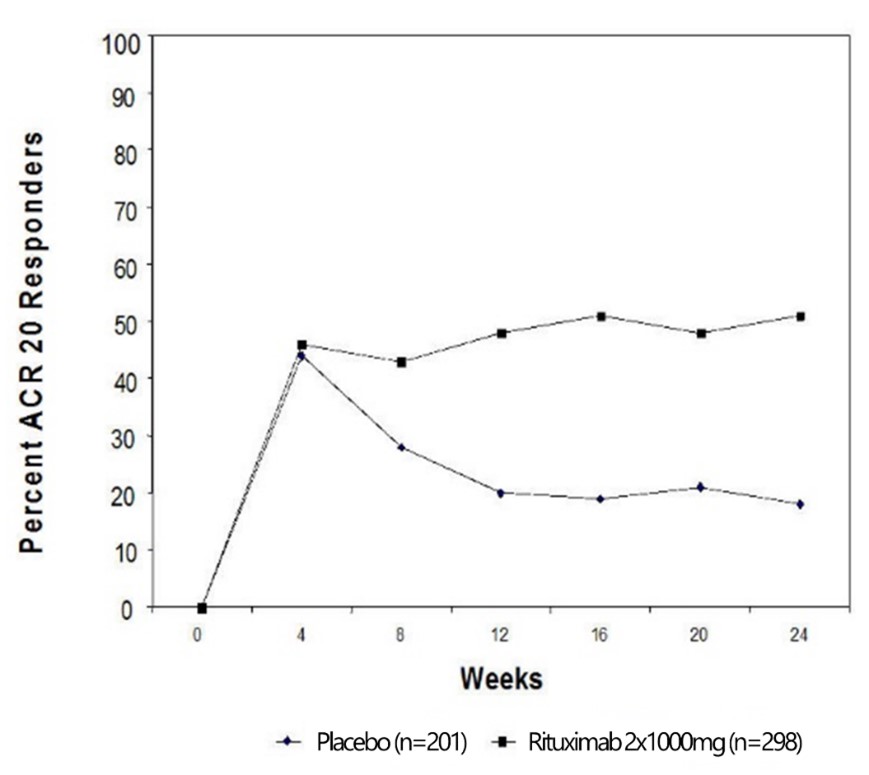
Other
Infusion-Related Reactions
Administration of rituximab products, including TRUXIMA, can result in serious, including fatal, infusion-related reactions. Deaths within 24 hours of rituximab infusion have occurred. Approximately 80% of fatal infusion-related reactions occurred in association with the first infusion. Monitor patients closely. Discontinue TRUXIMA infusion for severe reactions and provide medical treatment for Grade 3 or 4 infusion-related reactions [see Warnings and Precautions (5.1), Adverse Reactions (6.1)].
Severe Mucocutaneous Reactions
Severe, including fatal, mucocutaneous reactions can occur in patients receiving rituximab products [see Warnings and Precautions (5.2)].
Hepatitis B Virus (HBV) Reactivation
HBV reactivation can occur in patients treated with rituximab products, in some cases resulting in fulminant hepatitis, hepatic failure, and death. Screen all patients for HBV infection before treatment initiation, and monitor patients during and after treatment with TRUXIMA. Discontinue TRUXIMA and concomitant medications in the event of HBV reactivation [see Warnings and Precautions (5.3)].
Progressive Multifocal Leukoencephalopathy (PML), including fatal PML, can occur in patients receiving rituximab products [see Warnings and Precautions (5.4) and Adverse Reactions (6.1)].
Prior to First Infusion: Screen all patients for HBV infection by measuring HBsAg and anti-HBc before initiating treatment with TRUXIMA [see Warnings and Precautions (5.3)]. Obtain complete blood counts (CBC) including platelets prior to the first dose.
During TRUXIMA Therapy: In patients with lymphoid malignancies, during treatment with TRUXIMA monotherapy, obtain complete blood counts (CBC) with differential and platelet counts prior to each TRUXIMA course. During treatment with TRUXIMA and chemotherapy, obtain CBC with differential and platelet counts at weekly to monthly intervals and more frequently in patients who develop cytopenias [see Adverse Reactions (6.1)]. In patients with RA, GPA or MPA, obtain CBC with differential and platelet counts at two to four month intervals during TRUXIMA therapy. Continue to monitor for cytopenias after final dose and until resolution.
- First Infusion:
Initiate infusion at a rate of 50 mg/hr. In the absence of infusion toxicity, increase infusion rate by 50 mg/hr increments every 30 minutes, to a maximum of 400 mg/hr. - Subsequent Infusions:
Standard Infusion: Initiate infusion at a rate of 100 mg/hr. In the absence of infusion toxicity, increase rate by 100 mg/hr increments at 30-minute intervals, to a maximum of 400 mg/hr. - Interrupt the infusion or slow the infusion rate for infusion-related reactions [see Boxed Warning, Warnings and Precautions (5.1)]. Continue the infusion at one-half the previous rate upon improvement of symptoms.
For previously untreated follicular NHL and DLBCL patients:
If patients did not experience a Grade 3 or 4 infusion related adverse event during Cycle 1, a 90-minute infusion can be administered in Cycle 2 with a glucocorticoid-containing chemotherapy regimen.
Initiate at a rate of 20% of the total dose given in the first 30 minutes and the remaining 80% of the total dose given over the next 60 minutes. If the 90-minute infusion is tolerated in Cycle 2, the same rate can be used when administering the remainder of the treatment regimen (through Cycle 6 or 8).
Patients who have clinically significant cardiovascular disease or who have a circulating lymphocyte count ≥5000/mm3 before Cycle 2 should not be administered the 90-minute infusion [see Clinical Studies (14.4)].
Infusion-Related Reactions
In the majority of patients with NHL, infusion-related reactions consisting of fever, chills/rigors, nausea, pruritus, angioedema, hypotension, headache, bronchospasm, urticaria, rash, vomiting, myalgia, dizziness, or hypertension occurred during the first rituximab infusion. Infusion-related reactions typically occurred within 30 to 120 minutes of beginning the first infusion and resolved with slowing or interruption of the rituximab infusion and with supportive care (diphenhydramine, acetaminophen, and intravenous saline). The incidence of infusion-related reactions was highest during the first infusion (77%) and decreased with each subsequent infusion. [see Warnings and Precautions (5.1)]. In patients with previously untreated follicular NHL or previously untreated DLBCL, who did not experience a Grade 3 or 4 infusion-related reaction in Cycle 1 and received a 90-minute infusion of rituximab at Cycle 2, the incidence of Grade 3-4 infusion-related reactions on the day of, or day after the infusion was 1.1% (95% CI [0.3%, 2.8%]). For Cycles 2-8, the incidence of Grade 3-4 infusion-related reactions on the day of or day after the 90-minute infusion, was 2.8% (95% CI [1.3%, 5.0%]) [see Warnings and Precautions (5.1), Clinical Studies (14.4)].
Infections
Serious infections (NCI CTCAE Grade 3 or 4), including sepsis, occurred in less than 5% of patients with NHL in the single-arm studies. The overall incidence of infections was 31% (bacterial 19%, viral 10%, unknown 6%, and fungal 1%) [see Warnings and Precautions (5.6)].
In randomized, controlled studies where rituximab was administered following chemotherapy for the treatment of follicular or low-grade NHL, the rate of infection was higher among patients who received rituximab. In diffuse large B-cell lymphoma patients, viral infections occurred more frequently in those who received rituximab.
Cytopenias and hypogammaglobulinemia
In patients with NHL receiving rituximab monotherapy, NCI-CTC Grade 3 and 4 cytopenias were reported in 48% of patients. These included lymphopenia (40%), neutropenia (6%), leukopenia (4%), anemia (3%), and thrombocytopenia (2%). The median duration of lymphopenia was 14 days (range, 1-588 days) and of neutropenia was 13 days (range, 2-116 days). A single occurrence of transient aplastic anemia (pure red cell aplasia) and two occurrences of hemolytic anemia following rituximab therapy occurred during the single-arm studies.
In studies of monotherapy, rituximab -induced B-cell depletion occurred in 70% to 80% of patients with NHL. Decreased IgM and IgG serum levels occurred in 14% of these patients.
In CLL trials, the frequency of prolonged neutropenia and late-onset neutropenia was higher in patients treated with R-FC compared to patients treated with FC. Prolonged neutropenia is defined as Grade 3-4 neutropenia that has not resolved between 24 and 42 days after the last dose of study treatment. Late-onset neutropenia is defined as Grade 3-4 neutropenia starting at least 42 days after the last treatment dose.
In patients with previously untreated CLL, the frequency of prolonged neutropenia was 8.5% for patients who received R-FC (n=402) and 5.8% for patients who received FC (n=398). In patients who did not have prolonged neutropenia, the frequency of late-onset neutropenia was 14.8% of 209 patients who received R-FC and 4.3% of 230 patients who received FC.
For patients with previously treated CLL, the frequency of prolonged neutropenia was 24.8% for patients who received R-FC (n=274) and 19.1% for patients who received FC (n=274). In patients who did not have prolonged neutropenia, the frequency of late-onset neutropenia was 38.7% in 160 patients who received R-FC and 13.6% of 147 patients who received FC.
Relapsed or Refractory, Low-Grade NHL
Adverse reactions presented in Table 1 occurred in 356 patients with relapsed or refractory, low-grade or follicular, CD20-positive, B-cell NHL treated in single-arm studies of rituximab administered as a single agent [see Clinical Studies (14.1)]. Most patients received rituximab 375 mg/m2 weekly for 4 doses.
| All Grades (%) | Grade 3 and 4 (%) | |
|---|---|---|
| Any Adverse Reactions | 99 | 57 |
| Body as a Whole | 86 | 10 |
| Fever | 53 | 1 |
| Chills | 33 | 3 |
| Infection | 31 | 4 |
| Asthenia | 26 | 1 |
| Headache | 19 | 1 |
| Abdominal Pain | 14 | 1 |
| Pain | 12 | 1 |
| Back Pain | 10 | 1 |
| Throat Irritation | 9 | 0 |
| Flushing | 5 | 0 |
| Heme and Lymphatic System | 67 | 48 |
| Lymphopenia | 48 | 40 |
| Leukopenia | 14 | 4 |
| Neutropenia | 14 | 6 |
| Thrombocytopenia | 12 | 2 |
| Anemia | 8 | 3 |
| Skin and Appendages | 44 | 2 |
| Night Sweats | 15 | 1 |
| Rash | 15 | 1 |
| Pruritus | 14 | 1 |
| Urticaria | 8 | 1 |
| Respiratory System | 38 | 4 |
| Increased Cough | 13 | 1 |
| Rhinitis | 12 | 1 |
| Bronchospasm | 8 | 1 |
| Dyspnea | 7 | 1 |
| Sinusitis | 6 | 0 |
| Metabolic and Nutritional Disorders | 38 | 3 |
| Angioedema | 11 | 1 |
| Hyperglycemia | 9 | 1 |
| Peripheral Edema | 8 | 0 |
| LDH Increase | 7 | 0 |
| Digestive System | 37 | 2 |
| Nausea | 23 | 1 |
| Diarrhea | 10 | 1 |
| Vomiting | 10 | 1 |
| Nervous System | 32 | 1 |
| Dizziness | 10 | 1 |
| Anxiety | 5 | 1 |
| Musculoskeletal System | 26 | 3 |
| Myalgia | 10 | 1 |
| Arthralgia | 10 | 1 |
| Cardiovascular System | 25 | 3 |
| Hypotension | 10 | 1 |
| Hypertension | 6 | 1 |
In these single-arm rituximab studies, bronchiolitis obliterans occurred during and up to 6 months after rituximab infusion.
Previously Untreated, Low-Grade or Follicular, NHL
In NHL Study 4, patients in the R-CVP arm experienced a higher incidence of infusional toxicity and neutropenia compared to patients in the CVP arm. The following adverse reactions occurred more frequently ( ≥5%) in patients receiving R-CVP compared to CVP alone: rash (17% vs. 5%), cough (15% vs. 6%), flushing (14% vs. 3%), rigors (10% vs. 2%), pruritus (10% vs. 1%), neutropenia (8% vs. 3%), and chest tightness (7% vs. 1%) [see Clinical Studies (14.2)].
In NHL Study 5, detailed safety data collection was limited to serious adverse reactions, Grade ≥ 2 infections, and Grade ≥ 3 adverse reactions. In patients receiving rituximab as single-agent maintenance therapy following rituximab plus chemotherapy, infections were reported more frequently compared to the observation arm (37% vs. 22%). Grade 3-4 adverse reactions occurring at a higher incidence (≥ 2%) in the rituximab group were infections (4% vs. 1%) and neutropenia (4% vs. <1%).
In NHL Study 6, the following adverse reactions were reported more frequently (≥5%) in patients receiving rituximab following CVP compared to patients who received no further therapy: fatigue (39% vs. 14%), anemia (35% vs. 20%), peripheral sensory neuropathy (30% vs. 18%), infections (19% vs. 9%), pulmonary toxicity (18% vs. 10%), hepato-biliary toxicity (17% vs. 7%), rash and/or pruritus (17% vs. 5%), arthralgia (12% vs. 3%), and weight gain (11% vs. 4%). Neutropenia was the only Grade 3 or 4 adverse reaction that occurred more frequently (≥2%) in the rituximab arm compared with those who received no further therapy (4% vs. 1%) [see Clinical Studies (14.3)].
DLBCL
In NHL Studies 7 (NCT00003150) and 8, [see Clinical Studies (14.3)], the following adverse reactions, regardless of severity, were reported more frequently (≥5%) in patients age ≥60 years receiving R-CHOP as compared to CHOP alone: pyrexia (56% vs. 46%), lung disorder (31% vs. 24%), cardiac disorder (29% vs. 21%), and chills (13% vs. 4%). Detailed safety data collection in these studies was primarily limited to Grade 3 and 4 adverse reactions and serious adverse reactions.
In NHL Study 8, a review of cardiac toxicity determined that supraventricular arrhythmias or tachycardia accounted for most of the difference in cardiac disorders (4.5% for R-CHOP vs. 1.0% for CHOP).
The following Grade 3 or 4 adverse reactions occurred more frequently among patients in the R-CHOP arm compared with those in the CHOP arm: thrombocytopenia (9% vs. 7%) and lung disorder (6% vs. 3%). Other Grade 3 or 4 adverse reactions occurring more frequently among patients receiving R-CHOP were viral infection (NHL Study 8), neutropenia (NHL Studies 8 and 9 (NCT00064116)), and anemia (NHL Study 9).
CLL
The data below reflect exposure to rituximab in combination with fludarabine and cyclophosphamide in 676 patients with CLL in CLL Study 1 (NCT00281918) or CLL Study 2 (NCT00090051) [) or CLL Study 2 (NCT00090051) [see Clinical Studies (14.5)]. The age range was 30-83 years and 71% were men. Detailed safety data collection in CLL Study 1 was limited to Grade 3 and 4 adverse reactions and serious adverse reactions.
Infusion-related adverse reactions were defined by any of the following adverse events occurring during or within 24 hours of the start of infusion: nausea, pyrexia, chills, hypotension, vomiting, and dyspnea.
In CLL Study 1, the following Grade 3 and 4 adverse reactions occurred more frequently in R-FC-treated patients compared to FC-treated patients: infusion-related reactions (9% in R-FC arm), neutropenia (30% vs. 19%), febrile neutropenia (9% vs. 6%), leukopenia (23% vs. 12%), and pancytopenia (3% vs. 1%).
In CLL Study 2, the following Grade 3 or 4 adverse reactions occurred more frequently in R-FC-treated patients compared to FC-treated patients: infusion-related reactions (7% in R-FC arm), neutropenia (49% vs. 44%), febrile neutropenia (15% vs. 12%), thrombocytopenia (11% vs. 9%), hypotension (2% vs. 0%), and hepatitis B (2% vs. <1%). Fifty-nine percent of R-FC-treated patients experienced an infusion-related reaction of any severity.
Infusion-Related Reactions
In the rituximab RA pooled placebo-controlled studies, 32% of rituximab-treated patients experienced an adverse reaction during or within 24 hours following their first infusion, compared to 23% of placebo-treated patients receiving their first infusion. The incidence of adverse reactions during the 24-hour period following the second infusion, rituximab or placebo, decreased to 11% and 13%, respectively. Acute infusion-related reactions (manifested by fever, chills, rigors, pruritus, urticaria/rash, angioedema, sneezing, throat irritation, cough, and/or bronchospasm, with or without associated hypotension or hypertension) were experienced by 27% of rituximab-treated patients following their first infusion, compared to 19% of placebo-treated patients receiving their first placebo infusion. The incidence of these acute infusion-related reactions following the second infusion of rituximab or placebo decreased to 9% and 11%, respectively. Serious acute infusion-related reactions were experienced by <1% of patients in either treatment group. Acute infusion-related reactions required dose modification (stopping, slowing, or interruption of the infusion) in 10% and 2% of patients receiving rituximab or placebo, respectively, after the first course. The proportion of patients experiencing acute infusion-related reactions decreased with subsequent courses of rituximab. The administration of intravenous glucocorticoids prior to rituximab infusions reduced the incidence and severity of such reactions, however, there was no clear benefit from the administration of oral glucocorticoids for the prevention of acute infusion-related reactions. Patients in clinical studies also received antihistamines and acetaminophen prior to rituximab infusions.
Infections
In the pooled, placebo-controlled studies, 39% of patients in the rituximab group experienced an infection of any type compared to 34% of patients in the placebo group. The most common infections were nasopharyngitis, upper respiratory tract infections, urinary tract infections, bronchitis, and sinusitis.
The incidence of serious infections was 2% in the rituximab-treated patients and 1% in the placebo group.
In the experience with rituximab in 2578 RA patients, the rate of serious infections was 4.31 per 100 patient years. The most common serious infections (≥0.5%) were pneumonia or lower respiratory tract infections, cellulitis and urinary tract infections. Fatal serious infections included pneumonia, sepsis and colitis. Rates of serious infection remained stable in patients receiving subsequent courses. In 185 rituximab-treated RA patients with active disease, subsequent treatment with a biologic DMARD, the majority of which were TNF antagonists, did not appear to increase the rate of serious infection. Thirteen serious infections were observed in 186.1 patient years (6.99 per 100 patient years) prior to exposure and 10 were observed in 182.3 patient years (5.49 per 100 patient years) after exposure.
Cardiovascular Adverse Reactions
In the pooled, placebo-controlled studies, the proportion of patients with serious cardiovascular reactions was 1.7% and 1.3% in the rituximab and placebo treatment groups, respectively. Three cardiovascular deaths occurred during the double-blind period of the RA studies including all rituximab regimens (3/769 = 0.4%) as compared to none in the placebo treatment group (0/389).
In the experience with rituximab in 2578 RA patients, the rate of serious cardiac reactions was 1.93 per 100 patient years. The rate of myocardial infarction (MI) was 0.56 per 100 patient years (28 events in 26 patients), which is consistent with MI rates in the general RA population. These rates did not increase over three courses of rituximab.
Since patients with RA are at increased risk for cardiovascular events compared with the general population, patients with RA should be monitored throughout the infusion and TRUXIMA should be discontinued in the event of a serious or life-threatening cardiac event.
Hypophosphatemia and hyperuricemia
In the pooled, placebo-controlled studies, newly-occurring hypophosphatemia (<2.0 mg/dl) was observed in 12% (67/540) of patients on rituximab versus 10% (39/398) of patients on placebo. Hypophosphatemia was more common in patients who received corticosteroids. Newly-occurring hyperuricemia (>10 mg/dl) was observed in 1.5% (8/540) of patients on rituximab versus 0.3% (1/398) of patients on placebo.
In the experience with rituximab in RA patients, newly-occurring hypophosphatemia was observed in 21% (528/2570) of patients and newly-occurring hyperuricemia was observed in 2% (56/2570) of patients. The majority of the observed hypophosphatemia occurred at the time of the infusions and was transient.
Retreatment in Patients with RA
In the experience with rituximab in RA patients, 2578 patients have been exposed to rituximab and have received up to 10 courses of rituximab in RA clinical trials, with 1890, 1043, and 425 patients having received at least two, three, and four courses, respectively. Most of the patients who received additional courses did so 24 weeks or more after the previous course and none were retreated sooner than 16 weeks. The rates and types of adverse reactions reported for subsequent courses of rituximab were similar to rates and types seen for a single course of rituximab.
In RA Study 2, where all patients initially received rituximab, the safety profile of patients who were retreated with rituximab was similar to those who were retreated with placebo [see Clinical Studies (14.6), and Dosage and Administration (2.5)].
Induction Treatment of Adult Patients with Active GPA/MPA (GPA/MPA Study 1)
The data presented below from GPA/MPA Study 1 (NCT00104299) reflect the experience in 197 adult patients with active GPA and MPA treated with rituximab or cyclophosphamide in a single controlled study, which was conducted in two phases: a 6 month randomized, double-blind, double-dummy, active-controlled remission induction phase and an additional 12 month remission maintenance phase [see Clinical Studies (14.7)]. In the 6-month remission induction phase, 197 patients with GPA and MPA were randomized to either rituximab 375 mg/m2 once weekly for 4 weeks plus glucocorticoids, or oral cyclophosphamide 2 mg/kg daily (adjusted for renal function, white blood cell count, and other factors) plus glucocorticoids to induce remission. Once remission was achieved or at the end of the 6 month remission induction period, the cyclophosphamide group received azathioprine to maintain remission. The rituximab group did not receive additional therapy to maintain remission. The primary analysis was at the end of the 6 month remission induction period and the safety results for this period are described below.
Adverse reactions presented below in Table 3 were adverse events which occurred at a rate of greater than or equal to 10% in the rituximab group. This table reflects experience in 99 GPA and MPA patients treated with rituximab, with a total of 47.6 patient-years of observation and 98 GPA and MPA patients treated with cyclophosphamide, with a total of 47.0 patient-years of observation. Infection was the most common category of adverse events reported (47-62%) and is discussed below.
| Adverse Reaction | Rituximab N=99 n (%) | Cyclophosphamide N=98 n (%) |
|---|---|---|
| Nausea | 18 (18%) | 20 (20%) |
| Diarrhea | 17 (17%) | 12 (12%) |
| Headache | 17 (17%) | 19 (19%) |
| Muscle spasms | 17 (17%) | 15 (15%) |
| Anemia | 16 (16%) | 20 (20%) |
| Peripheral edema | 16 (16%) | 6 (6%) |
| Insomnia | 14 (14%) | 12 (12%) |
| Arthralgia | 13 (13%) | 9 (9%) |
| Cough | 13 (13%) | 11 (11%) |
| Fatigue | 13 (13%) | 21 (21%) |
| Increased ALT | 13 (13%) | 15 (15%) |
| Hypertension | 12 (12%) | 5 (5%) |
| Epistaxis | 11 (11%) | 6 (6%) |
| Dyspnea | 10 (10%) | 11 (11%) |
| Leukopenia | 10 (10%) | 26 (27%) |
| Rash | 10 (10%) | 17 (17%) |
Infusion-Related Reactions
Infusion-related reactions in GPA/MPA Study 1 were defined as any adverse event occurring within 24 hours of an infusion and considered to be infusion-related by investigators. Among the 99 patients treated with rituximab, 12% experienced at least one infusion-related reaction, compared with 11% of the 98 patients in the cyclophosphamide group.
Infusion-related reactions included cytokine release syndrome, flushing, throat irritation, and tremor. In the rituximab group, the proportion of patients experiencing an infusion-related reaction was 12%, 5%, 4%, and 1% following the first, second, third, and fourth infusions, respectively. Patients were pre-medicated with antihistamine and acetaminophen before each rituximab infusion and were on background oral corticosteroids which may have mitigated or masked an infusion-related reaction; however, there is insufficient evidence to determine whether premedication diminishes the frequency or severity of infusion-related reactions.
Infections
In GPA/MPA Study 1, 62% (61/99) of patients in the rituximab group experienced an infection of any type compared to 47% (46/98) patients in the cyclophosphamide group by Month 6. The most common infections in the rituximab group were upper respiratory tract infections, urinary tract infections, and herpes zoster.
The incidence of serious infections was 11% in the rituximab-treated patients and 10% in the cyclophosphamide treated patients, with rates of approximately 25 and 28 per 100 patient-years, respectively. The most common serious infection was pneumonia.
Hypogammaglobulinemia
Hypogammaglobulinemia (IgA, IgG or IgM below the lower limit of normal) has been observed in patients with GPA and MPA treated with rituximab in GPA/MPA Study 1. At 6 months, in the rituximab group, 27%, 58% and 51% of patients with normal immunoglobulin levels at baseline, had low IgA, IgG and IgM levels, respectively compared to 25%, 50% and 46% in the cyclophosphamide group.
Follow up Treatment of Adult Patients with GPA/MPA who have Achieved Disease Control with Induction Treatment (GPA/MPA Study 2)
In GPA/MPA Study 2 (NCT00748644), an open-label, controlled, clinical study [see Clinical Studies (14.7)], evaluating the efficacy and safety of non-U.S.-licensed rituximab versus azathioprine as follow up treatment in adult patients with GPA, MPA or renal-limited ANCA-associated vasculitis who had achieved disease control after induction treatment with cyclophosphamide, a total of 57 GPA and MPA patients in disease remission received follow up treatment with two 500 mg intravenous infusions of non-U.S.-licensed rituximab, separated by two weeks on Day 1 and Day 15, followed by a 500 mg intravenous infusion every 6 months for 18 months.
The safety profile was consistent with the safety profile for rituximab in RA and GPA and MPA.
Infusion-Related Reactions
In GPA/MPA Study 2, 7/57 (12%) patients in the non-U.S.-licensed rituximab arm reported infusion-related reactions. The incidence of IRR symptoms was highest during or after the first infusion (9%) and decreased with subsequent infusions (<4%). One patient had two serious IRRs, two IRRs led to a dose modification, and no IRRs were severe, fatal, or led to withdrawal from the study.
Infections
In GPA/MPA Study 2, 30/57 (53%) patients in the non-U.S.-licensed rituximab arm and 33/58 (57%) in the azathioprine arm reported infections. The incidence of all grade infections was similar between the arms. The incidence of serious infections was similar in both arms (12%). The most commonly reported serious infection in the group was mild or moderate bronchitis.
Long-term, Observational Study with Rituximab in Patients with GPA/MPA (GPA/MPA Study 3)
In a long-term observational safety study (NCT01613599), 97 patients with GPA or MPA received treatment with rituximab (mean of 8 infusions [range 1-28]) for up to 4 years, according to physician standard practice and discretion. Majority of patients received doses ranging from 500 mg to 1000 mg, approximately every 6 months. The safety profile was consistent with the safety profile for rituximab in RA and GPA and MPA.
Infusion-Related Reactions
Infusion-related reactions were the most commonly reported adverse drug reactions (58%, 22 patients). All infusion-related reactions were mild to moderate (Grade 1 or 2) except one Grade 3 serious infusion-related reaction (arthralgia) associated with the Month 12 maintenance infusion. The proportion of patients experiencing an infusion-related reaction was 29% (11 patients), 40% (15 patients), 13% (5 patients), and 10% (4 patients) following the first, second, third, and fourth infusions, respectively. No patients were withdrawn from treatment due to infusion-related reactions. Symptoms of infusion-related reactions were similar in type and severity to those seen in RA and GPA and MPA patients [see Adverse Reactions (6.1)].
Infections
Fourteen patients (37%) in the group treated with non-U.S.-licensed rituximab experienced treatment-related infections compared to 15 patients (42%) in the prednisone group. The most common infections in the group treated with non-U.S.-licensed rituximab were herpes simplex, herpes zoster, bronchitis, urinary tract infection, fungal infection, and conjunctivitis. Three patients (8%) in the group treated with non-U.S.-licensed rituximab experienced a total of 5 serious infections (Pneumocystis jirovecii pneumonia, infective thrombosis, intervertebral discitis, lung infection, Staphylococcal sepsis) and 1 patient (3%) in the prednisone group experienced 1 serious infection (Pneumocystis jirovecii pneumonia).
PV Study 2
In PV Study 2 (NCT02383589), a randomized, double-blind, double-dummy, active-comparator, multicenter study evaluating the efficacy and safety of rituximab compared to mycophenolate mofetil (MMF) in patients with moderate-to-severe PV requiring oral corticosteroids, 67 PV patients received treatment with rituximab (initial 1,000 mg IV on Study Day 1 and a second 1,000 mg IV on Study Day 15 repeated at Weeks 24 and 26) for up to 52 weeks [see Clinical Studies (14.8)].
In PV Study 2, ADR defined as adverse events occurring in greater than or equal to 5% of patients in the rituximab arms and assessed as related are shown in Table 5.
Adverse Reactions | Rituximab (N=67) |
Infusion-related reactions* | 15 (22%)* |
Upper respiratory tract infection/Nasopharyngitis | 11 (16%) |
Headache | 10 (15%) |
Asthenia/Fatigue | 9 (13%) |
Oral candidiasis | 6 (9%) |
Arthralgia | 6 (9%) |
Back pain | 6 (9%) |
Urinary tract infection | 5 (8%) |
Dizziness | 4 (6%) |
*The most common infusion-related reaction symptoms/Preferred Terms for PV Study 2 in the rituximab arm were dyspnoea, erythema, hyperhidrosis, flushing/hot flush, hypotension/low blood pressure and rash/rash pruritic | |
Infusion-Related Reactions
In PV Study 2, IRRs occurred primarily at the first infusion and the frequency of IRRs decreased with subsequent infusions: 17.9%, 4.7%, 3.5% and 3.5% of patients experienced IRRs at the first, second, third, and fourth infusions, respectively. In 11/15 patients who experienced at least one IRR, the IRRs were Grade 1 or 2. In 4/15 patients, Grade greater than or equal to 3 IRRs were reported and led to discontinuation of rituximab treatment; three of the four patients experienced serious [life-threatening] IRRs. Serious IRRs occurred at the first (2 patients) or second (1 patient) infusion and resolved with symptomatic treatment.
Infections
In PV Study 2, 42/67 patients (62.7%) in the rituximab arm experienced infections. The most common infections in the rituximab arm were upper respiratory tract infection, nasopharyngitis, oral candidiasis and urinary tract infection. Six patients (9%) in the rituximab arm experienced serious infections.
Laboratory Abnormalities
In PV Study 2, in the rituximab arm, transient decreases in T-cell lymphocytes and phosphorus level were very commonly observed post-infusion. In some cases, treatment of hypophosphatemia was required.
Hypogammaglobulinemia (IgG or IgM below the lower limit of normal), including prolonged hypogammaglobulinemia (defined as Ig levels below lower limit of normal for at least 4 months) was observed in PV Study 2. Based on levels less than LLN measured at Week 16, Week 24, Week 40, and Week 52, 16.4% (11/67) of patients with normal baseline immunoglobulins had prolonged hypogammaglobulinemia (10 patients – IgM, 1 patient – both IgG and IgM) after treatment with rituximab.
Risk Summary
Based on human data, rituximab products can cause adverse developmental outcomes including B-cell lymphocytopenia in infants exposed to in-utero [see Clinical Considerations]. In animal reproduction studies, intravenous administration of rituximab to pregnant cynomolgus monkeys during the period of organogenesis caused lymphoid B-cell depletion in the newborn offspring at doses resulting in 80% of the exposure (based on AUC) of those achieved following a dose of 2 grams in humans. Advise pregnant women of the risk to a fetus.
Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications. The background risk of major birth defects and miscarriage for the indicated populations is unknown. The estimated background risk in the U.S. general population of major birth defects is 2%-4% and of miscarriage is 15%-20% of clinically recognized pregnancies.
Clinical Considerations
Fetal/Neonatal Adverse Reactions
Observe newborns and infants for signs of infection and manage accordingly.
Data
Human data
Postmarketing data indicate that B-cell lymphocytopenia generally lasting less than six months can occur in infants exposed to rituximab in-utero. Rituximab was detected postnatally in the serum of infants exposed in-utero.
Animal Data
An embryo-fetal developmental toxicity study was performed on pregnant cynomolgus monkeys. Pregnant animals received rituximab via the intravenous route during early gestation (organogenesis period; post coitum days 20 through 50). Rituximab was administered as loading doses on post coitum (PC) Days 20, 21 and 22, at 15, 37.5 or 75 mg/kg/day, and then weekly on PC Days 29, 36, 43 and 50, at 20, 50 or 100 mg/kg/week. The 100 mg/kg/week dose resulted in 80% of the exposure (based on AUC) of those achieved following a dose of 2 grams in humans. Rituximab crosses the monkey placenta. Exposed offspring did not exhibit any teratogenic effects but did have decreased lymphoid tissue B cells.
A subsequent pre-and postnatal reproductive toxicity study in cynomolgus monkeys was completed to assess developmental effects including the recovery of B cells and immune function in infants exposed to rituximab in utero. Animals were treated with a loading dose of 0, 15, or 75 mg/kg every day for 3 days, followed by weekly dosing with 0, 20, or 100 mg/kg dose. Subsets of pregnant females were treated from PC Day 20 through postpartum Day 78, PC Day 76 through PC Day 134, and from PC Day 132 through delivery and postpartum Day 28. Regardless of the timing of treatment, decreased B cells and immunosuppression were noted in the offspring of rituximab-treated pregnant animals. The B-cell counts returned to normal levels, and immunologic function was restored within 6 months postpartum.
Diffuse Large B-Cell NHL
Among patients with DLBCL evaluated in three randomized, active-controlled trials, 927 patients received rituximab in combination with chemotherapy. Of these, 396 (43%) were age 65 or greater and 123 (13%) were age 75 or greater. No overall differences in effectiveness were observed between these patients and younger patients. Cardiac adverse reactions, mostly supraventricular arrhythmias, occurred more frequently among elderly patients. Serious pulmonary adverse reactions were also more common among the elderly, including pneumonia and pneumonitis.
Low-Grade or Follicular Non-Hodgkin's Lymphoma
Patients with previously untreated follicular NHL evaluated in NHL Study 5 were randomized to rituximab as single-agent maintenance therapy (n=505) or observation (n=513) after achieving a response to rituximab in combination with chemotherapy. Of these, 123 (24%) patients in the rituximab arm were age 65 or older. No overall differences in safety or effectiveness were observed between these patients and younger patients. Other clinical studies of rituximab in low-grade or follicular, CD20-positive, B-cell NHL did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger subjects.
Chronic Lymphocytic Leukemia
Among patients with CLL evaluated in two randomized active-controlled trials, 243 of 676 rituximab-treated patients (36%) were 65 years of age or older; of these, 100 rituximab-treated patients (15%) were 70 years of age or older.
In exploratory analyses defined by age, there was no observed benefit from the addition of rituximab to fludarabine and cyclophosphamide among patients 70 years of age or older in CLL Study 1 or in CLL Study 2; there was also no observed benefit from the addition of rituximab to fludarabine and cyclophosphamide among patients 65 years of age or older in Study 2 [see Clinical Studies (14.5)]. Patients 70 years or older received lower dose intensity of fludarabine and cyclophosphamide compared to younger patients, regardless of the addition of rituximab. In CLL Study 1, the dose intensity of rituximab was similar in older and younger patients, however in CLL Study 2 older patients received a lower dose intensity of rituximab.
The incidence of Grade 3 and 4 adverse reactions was higher among patients receiving R-FC who were 70 years or older compared to younger patients for neutropenia [44% vs. 31% (CLL Study 1); 56% vs. 39% (CLL Study 2)], febrile neutropenia [16% vs. 6% (NHL Study 10 (NCT00719472))], anemia [5% vs. 2% (CLL Study 1); 21% vs. 10% (CLL Study 2)], thrombocytopenia [19% vs. 8% (CLL Study 2)], pancytopenia [7% vs. 2% (CLL Study 1); 7% vs. 2% (CLL Study 2)] and infections [30% vs. 14% (CLL Study 2)].
Rheumatoid Arthritis
Among the 2578 patients in global RA studies completed to date, 12% were 65-75 years old and 2% were 75 years old and older. The incidences of adverse reactions were similar between older and younger patients. The rates of serious adverse reactions, including serious infections, malignancies, and cardiovascular events were higher in older patients.
Granulomatosis with Polyangiitis (GPA) (Wegener’s Granulomatosis) and Microscopic Polyangiitis
Of the 99 rituximab-treated GPA and MPA patients in GPA/MPA Study 1, 36 (36%) were 65 years old and over, while 8 (8%) were 75 years and over. No overall differences in efficacy were observed between patients that were 65 years old and over and younger patients. The overall incidence and rate of all serious adverse events was higher in patients 65 years old and over. The clinical study did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger subjects.
In GPA/MPA Study 2, 30 (26%) of the enrolled patients were at least 65 years old, of which 12 patients were exposed to non-U.S.-licensed rituximab and 18 were exposed to azathioprine. The clinical study did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger subjects.
Pemphigus Vulgaris
Of the 46 patients treated with non-U.S.-licensed rituximab, 15 (33%) patients were 65 years of age and older. The clinical study did not include sufficient numbers of patients aged 65 and older to determine whether they respond differently from younger patients.
Non-Hodgkin's Lymphoma (NHL)
In NHL patients, administration of rituximab resulted in depletion of circulating and tissue-based B cells. Among 166 patients in NHL Study 1 (NCT000168740), circulating CD19-positive B cells were depleted within the first three weeks with sustained depletion for up to 6 to 9 months post treatment in 83% of patients.
B-cell recovery began at approximately 6 months and median B-cell levels returned to normal by 12 months following completion of treatment.
There were sustained and statistically significant reductions in both IgM and IgG serum levels observed from 5 through 11 months following rituximab administration; 14% of patients had IgM and/or IgG serum levels below the normal range.
Rheumatoid Arthritis
In RA patients, treatment with rituximab induced depletion of peripheral B lymphocytes, with the majority of patients demonstrating near complete depletion (CD19 counts below the lower limit of quantification, 20 cells/ml) within 2 weeks after receiving the first dose of rituximab. The majority of patients showed peripheral B-cell depletion for at least 6 months. A small proportion of patients (~4%) had prolonged peripheral B-cell depletion lasting more than 3 years after a single course of treatment.
Total serum immunoglobulin levels, IgM, IgG, and IgA were reduced at 6 months with the greatest change observed in IgM. At Week 24 of the first course of rituximab treatment, small proportions of patients experienced decreases in IgM (10%), IgG (2.8%), and IgA (0.8%) levels below the lower limit of normal (LLN). In the experience with rituximab in RA patients during repeated rituximab treatment, 23.3%, 5.5%, and 0.5% of patients experienced decreases in IgM, IgG, and IgA concentrations below LLN at any time after receiving rituximab, respectively. The clinical consequences of decreases in immunoglobulin levels in RA patients treated with rituximab are unclear.
Treatment with rituximab in patients with RA was associated with reduction of certain biologic markers of inflammation such as interleukin-6 (IL-6), C-reactive protein (CRP), serum amyloid protein (SAA), S100 A8/S100 A9 heterodimer complex (S100 A8/9), anti-citrullinated peptide (anti-CCP), and RF.
Granulomatosis with Polyangiitis (GPA) (Wegener’s Granulomatosis) and Microscopic Polyangiitis
In GPA and MPA patients in GPA/MPA Study 1, peripheral blood CD19 B-cells depleted to less than 10 cells/μl following the first two infusions of rituximab, and remained at that level in most (84%) patients through Month 6. By Month 12, the majority of patients (81%) showed signs of B-cell return with counts >10 cells/μL. By Month 18, most patients (87%) had counts >10 cells/μL.
In GPA/MPA Study 2 where patients received non-U.S.-licensed rituximab as two 500 mg intravenous infusions separated by two weeks, followed by a 500 mg intravenous infusion at Month 6, 12, and 18, 70% (30 out of 43) of the rituximab-treated patients with CD19+ peripheral B cells evaluated post-baseline had undetectable CD19+ peripheral B cells at Month 24. At Month 24, all 37 patients with evaluable baseline CD19+ peripheral B cells and Month 24 measurements had lower CD19+ B cells relative to baseline.
Non-Hodgkin’s Lymphoma (NHL)
Pharmacokinetics were characterized in 203 NHL patients receiving 375 mg/m2 rituximab weekly by intravenous infusion for 4 doses. Rituximab was detectable in the serum of patients 3 to 6 months after completion of treatment.
The pharmacokinetic profile of rituximab when administered as 6 infusions of 375 mg/m2 in combination with 6 cycles of CHOP chemotherapy was similar to that seen with rituximab alone.
Based on a population pharmacokinetic analysis of data from 298 NHL patients who received rituximab once weekly or once every three weeks, the estimated median terminal elimination half-life was 22 days (range, 6.1 to 52 days). Patients with higher CD19-positive cell counts or larger measurable tumor lesions at pretreatment had a higher clearance. However, dose adjustment for pretreatment CD19 count or size of tumor lesion is not necessary. Age and gender had no effect on the pharmacokinetics of rituximab.
Pharmacokinetics were characterized in 21 patients with CLL receiving rituximab according to the recommended dose and schedule. The estimated median terminal half-life of rituximab was 32 days (range, 14 to 62 days).
Rheumatoid Arthritis
Following administration of 2 doses of rituximab in patients with RA, the mean (± S.D.; % CV) concentrations after the first infusion (Cmax first) and second infusion (Cmax second) were 157 (± 46; 29%) and 183 (± 55; 30%) mcg/mL, and 318 (± 86; 27%) and 381 (± 98; 26%) mcg/mL for the 2 x 500 mg and 2 x 1000 mg doses, respectively.
Based on a population pharmacokinetic analysis of data from 2005 RA patients who received rituximab, the estimated clearance of rituximab was 0.335 L/day; volume of distribution was 3.1 L and mean terminal elimination half-life was 18.0 days (range, 5.17 to 77.5 days). Age, weight and gender had no effect on the pharmacokinetics of rituximab in RA patients.
Granulomatosis with Polyangiitis (GPA) (Wegener’s Granulomatosis) and Microscopic Polyangiitis
The PK parameters in adult patients with GPA/MPA receiving 375 mg/m2 intravenous rituximab once weekly for four doses are summarized in Table 6.
| Parameter | Statistic | Adult GPA/MPA (GPA/MPA Study 1) |
|---|---|---|
| N | Number of Patients | 97 |
| Terminal Half-life (days) | Median (Range) | 25 (11 to 52) |
| AUC0-180d (µg/mL*day) | Median (Range) | 10302 (3653 to 21874) |
| Clearance (L/day) | Median (Range) | 0.279 (0.113 to 0.653) |
| Volume of Distribution (L) | Median (Range) | 3.12 (2.42 to 3.91) |
The population PK analysis in adults with GPA and MPA showed that male patients and patients with higher BSA or positive anti-rituximab antibody levels have higher clearance. However, further dose adjustment based on gender or antidrug antibody status is not necessary.
Pemphigus Vulgaris
The PK parameters in adult PV patients receiving 1,000 mg IV infusion of rituximab at Days 1, 15, 168, and 182 are summarized in Table 7.
Parameter | Infusion Cycle | |
1st cycle of 1,000 mg Day 1 and Day 15 N=67 | 2nd cycle of 1,000 mg Day 168 and Day 182 N=67 | |
Terminal Half-life (days) | ||
Median | 21.1 | 26.2 |
(Range) | (9.3 to 36.2) | (16.4 to 42.8) |
Clearance (L/day) | ||
Median | 0.30 | 0.24 |
(Range) | (0.16 to 1.51) | (0.13 to 0.45) |
Central Volume of Distribution (L) | ||
Median | 3.49 | 3.49 |
(Range) | (2.48 to 5.22) | (2.48 to 5.22) |
Drug Interaction Studies
Formal drug interaction studies have not been performed with rituximab products.
Drug Interaction Studies
Formal drug interaction studies have not been performed with rituximab products.
NHL Study 1
A multicenter, open-label, single-arm study was conducted in 166 patients with relapsed or refractory, low-grade or follicular, B-cell NHL who received 375 mg/m2 of rituximab given as an intravenous infusion weekly for 4 doses. Patients with tumor masses > 10 cm or with > 5000 lymphocytes/µL in the peripheral blood were excluded from the study.
Results are summarized in Table 5. The median time to onset of response was 50 days. Disease-related signs and symptoms (including B-symptoms) resolved in 64% (25/39) of those patients with such symptoms at study entry.
NHL Study 2
In a multicenter, single-arm study, 37 patients with relapsed or refractory, low-grade NHL received 375 mg/m2 of rituximab weekly for 8 doses. Results are summarized in Table 5.
NHL Study 3
In a multicenter, single-arm study, 60 patients received 375 mg/m2 of rituximab weekly for 4 doses. All patients had relapsed or refractory, low-grade or follicular, B-cell NHL and had achieved an objective clinical response to rituximab administered 3.8–35.6 months (median 14.5 months) prior to retreatment with rituximab. Of these 60 patients, 5 received more than one additional course of rituximab. Results are summarized in Table 8.
Bulky Disease
In pooled data from studies 1 and 3, 39 patients with bulky (single lesion > 10 cm in diameter) and relapsed or refractory, low-grade NHL received rituximab 375 mg/m2 weekly for 4 doses. Results are summarized in Table 8.
| NHL Study 1 Weekly × 4 N=166 | NHL Study 2 Weekly × 8 N=37 | NHL Study 1 and NHL Study 3 Bulky disease, Weekly × 4 N=39 Six of these patients are included in the first column. Thus, data from 296 intent-to-treat patients are provided in this table. | NHL Study 3 Retreatment, Weekly × 4 N=60 | |
|---|---|---|---|---|
| Overall Response Rate | 48% | 57% | 36% | 38% |
| Complete Response Rate | 6% | 14% | 3% | 10% |
| Median Duration of Response | 11.2 | 13.4 | 6.9 | 15.0 |
| (Months) [Range] Kaplan-Meier projected with observed range. ,+ indicates an ongoing response. ,Duration of response: interval from the onset of response to disease progression. | [1.9 to 42.1+] | [2.5 to 36.5+] | [2.8 to 25.0+] | [3.0 to 25.1+] |
NHL Study 4
A total of 322 patients with previously untreated follicular NHL were randomized (1:1) to receive up to eight 3-week cycles of CVP chemotherapy alone (CVP) or in combination with rituximab 375 mg/m2 on Day 1 of each cycle (R-CVP) in an open-label, multicenter study. The main outcome measure of the study was progression-free survival (PFS) defined as the time from randomization to the first of progression, relapse, or death.
Twenty-six percent of the study population was >60 years of age, 99% had Stage III or IV disease, and 50% had an International Prognostic Index (IPI) score 2. The results for PFS as determined by a blinded, independent assessment of progression are presented in Table 9. The point estimates may be influenced by the presence of informative censoring. The PFS results based on investigator assessment of progression were similar to those obtained by the independent review assessment.
| Study Arm | ||
|---|---|---|
| R-CVP N=162 | CVP N=160 | |
| Median PFS (years) p<0.0001, two-sided stratified log-rank test. | 2.4 | 1.4 |
| Hazard ratio (95% CI) Estimates of Cox regression stratified by center. | 0.44 (0.29, 0.65) | |
NHL Study 5
An open-label, multicenter, randomized (1:1) study was conducted in 1,018 patients with previously untreated follicular NHL who achieved a response (CR or PR) to rituximab in combination with chemotherapy. Patients were randomized to rituximab as single-agent maintenance therapy, 375 mg/m2 every 8 weeks for up to 12 doses or to observation. Rituximab was initiated at 8 weeks following completion of chemotherapy. The main outcome measure of the study was progression-free survival (PFS), defined as the time from randomization in the maintenance/observation phase to progression, relapse, or death, as determined by independent review.
Of the randomized patients, 40% were 60 years of age, 70% had Stage IV disease, 96% had ECOG performance status (PS) 01, and 42% had FLIPI scores of 35. Prior to randomization to maintenance therapy, patients had received R-CHOP (75%), R-CVP (22%), or R-FCM (3%); 71% had a complete or unconfirmed complete response and 28% had a partial response.
PFS was longer in patients randomized to rituximab as single agent maintenance therapy (HR: 0.54, 95% CI: 0.42, 0.70). The PFS results based on investigator assessment of progression were similar to those obtained by the independent review assessment.
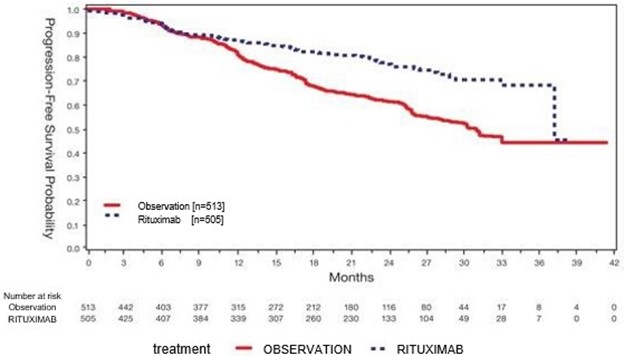 Figure 1 (Figure1) |
NHL Study 6
A total of 322 patients with previously untreated low-grade, B-cell NHL who did not progress after 6 or 8 cycles of CVP chemotherapy were enrolled in an open-label, multicenter, randomized trial. Patients were randomized (1:1) to receive rituximab, 375 mg/m2 intravenous infusion, once weekly for 4 doses every 6 months for up to 16 doses or no further therapeutic intervention. The main outcome measure of the study was progression-free survival defined as the time from randomization to progression, relapse, or death. Thirty-seven percent of the study population was >60 years of age, 99% had Stage III or IV disease, and 63% had an IPI score ≥2.
There was a reduction in the risk of progression, relapse, or death (hazard ratio estimate in the range of 0.36 to 0.49) for patients randomized to rituximab as compared to those who received no additional treatment.
NHL Study 7
A total of 632 patients age ≥60 years with DLBCL (including primary mediastinal B-cell lymphoma) were randomized in a 1:1 ratio to treatment with CHOP or R-CHOP. Patients received 6 or 8 cycles of CHOP, each cycle lasting 21 days. All patients in the R-CHOP arm received 4 doses of rituximab 375 mg/m2 on Days -7 and -3 (prior to Cycle 1) and 48-72 hours prior to Cycles 3 and 5. Patients who received 8 cycles of CHOP also received rituximab prior to Cycle 7. The main outcome measure of the study was progression-free survival, defined as the time from randomization to the first of progression, relapse, or death. Responding patients underwent a second randomization to receive rituximab or no further therapy.
Among all enrolled patients, 62% had centrally confirmed DLBCL histology, 73% had Stage III-IV disease, 56% had IPI scores ≥2, 86% had ECOG performance status of <2, 57% had elevated LDH levels, and 30% had two or more extranodal disease sites involved. Efficacy results are presented in Table 7. These results reflect a statistical approach which allows for an evaluation of rituximab administered in the induction setting that excludes any potential impact of rituximab given after the second randomization.
Analysis of results after the second randomization in NHL Study 7 demonstrates that for patients randomized to R-CHOP, additional rituximab exposure beyond induction was not associated with further improvements in progression-free survival or overall survival.
NHL Study 8
A total of 399 patients with DLBCL, age ≥60 years, were randomized in a 1:1 ratio to receive CHOP or R-CHOP. All patients received up to eight 3-week cycles of CHOP induction; patients in the R-CHOP arm received rituximab 375 mg/m2 on Day 1 of each cycle. The main outcome measure of the study was event-free survival, defined as the time from randomization to relapse, progression, change in therapy, or death from any cause. Among all enrolled patients, 80% had Stage III or IV disease, 60% of patients had an age-adjusted IPI ≥2, 80% had ECOG performance status scores <2, 66% had elevated LDH levels, and 52% had extranodal involvement in at least two sites. Efficacy results are presented in Table 7.
NHL Study 9
A total of 823 patients with DLBCL, aged 18-60 years, were randomized in a 1:1 ratio to receive an anthracycline-containing chemotherapy regimen alone or in combination with rituximab. The main outcome measure of the study was time to treatment failure, defined as time from randomization to the earliest of progressive disease, failure to achieve a complete response, relapse, or death. Among all enrolled patients, 28% had Stage III-IV disease, 100% had IPI scores of 1, 99% had ECOG performance status of <2, 29% had elevated LDH levels, 49% had bulky disease, and 34% had extranodal involvement. Efficacy results are presented in Table 10.
| NHL Study 7 (n = 632) | NHL Study 8 (n = 399) | NHL Study 9 (n = 823) | ||||||
|---|---|---|---|---|---|---|---|---|
| R-CHOP | CHOP | R-CHOP | CHOP | R-Chemo | Chemo | |||
| Main outcome | Progression-free survival (years) | Event-free survival (years) | Time to treatment failure (years) | |||||
| Median of main outcome measure | 3.1 | 1.6 | 2.9 | 1.1 | NE NE=Not reliably estimable. | NE | ||
| Hazard ratio R-CHOP vs. CHOP. | 0.69 Significant at p <0.05, 2-sided. | 0.60 | 0.45 | |||||
| Overall survival at 2 years Kaplan-Meier estimates. | 74% | 63% | 69% | 58% | 95% | 86% | ||
| Hazard ratio | 0.72 | 0.68 | 0.40 | |||||
In NHL Study 8, overall survival estimates at 5 years were 58% vs. 46% for R-CHOP and CHOP, respectively.
Induction Treatment of Adult Patients with Active Disease (GPA/MPA Study 1)
A total of 197 adult patients with active, severe GPA and MPA (two forms of ANCA Associated Vasculitides) were treated in a randomized, double-blind, active-controlled, multicenter, non-inferiority study, conducted in two phases a 6 month remission induction phase and a 12 month remission maintenance phase. Patients were 15 years of age or older, diagnosed with GPA (75% of patients) or MPA (24% of patients) according to the Chapel Hill Consensus conference criteria (1% of the patients had unknown vasculitis type). All patients had active disease, with a Birmingham Vasculitis Activity Score for Granulomatosis with Polyangiitis (BVAS/GPA) 3, and their disease was severe, with at least one major item on the BVAS/GPA. Ninety-six (49%) of patients had new disease and 101 (51%) of patients had relapsing disease.
Patients in both arms received 1000 mg of pulse intravenous methylprednisolone per day for 1 to 3 days within 14 days prior to initial infusion. Patients were randomized in a 1:1 ratio to receive either rituximab 375 mg/m2 once weekly for 4 weeks or oral cyclophosphamide 2 mg/kg daily for 3 to 6 months in the remission induction phase. Patients were pre-medicated with antihistamine and acetaminophen prior to rituximab infusion. Following intravenous corticosteroid administration, all patients received oral prednisone (1 mg/kg/day, not exceeding 80 mg/day) with pre-specified tapering. Once remission was achieved or at the end of the 6 month remission induction period, the cyclophosphamide group received azathioprine to maintain remission. The rituximab group did not receive additional therapy to maintain remission. The main outcome measure for both GPA and MPA patients was achievement of complete remission at 6 months defined as a BVAS/GPA of 0, and off glucocorticoid therapy. The pre-specified non-inferiority margin was a treatment difference of 20%. As shown in Table 17, the study demonstrated non-inferiority of rituximab to cyclophosphamide for complete remission at 6 months.
| Rituximab (n = 99) | Cyclophosphamide (n = 98) | Treatment Difference (Rituximab Cyclophosphamide) | |
|---|---|---|---|
| Rate | 64% | 53% | 11% |
| 95.1% The 95.1% confidence level reflects an additional 0.001 alpha to account for an interim efficacy analysis. CI | (54%, 73%) | (43%, 63%) | (-3%, 24%) non-inferiority was demonstrated because the lower bound was higher than the prespecified non-inferiority margin (-3% > -20%). |
Complete Remission (CR) at 12 and 18 months
In the rituximab group, 44% of patients achieved CR at 6 and 12 months, and 38% of patients achieved CR at 6, 12, and 18 months. In patients treated with cyclophosphamide (followed by azathioprine for maintenance of CR), 38% of patients achieved CR at 6 and 12 months, and 31% of patients achieved CR at 6, 12, and 18 months.
Retreatment of Flares with Rituximab
Based upon investigator judgment, 15 patients received a second course of rituximab therapy for treatment of relapse of disease activity which occurred between 8 and 17 months after the induction treatment course of rituximab.
Follow up Treatment of Adult Patients with GPA/MPA who have achieved disease control with other Immunosuppressant (GPA/MPA Study 2)
A total of 115 patients (86 with GPA, 24 with MPA, and 5 with renal-limited ANCA-associated vasculitis) in disease remission were randomized to receive azathioprine (58 patients) or non-U.S.-licensed rituximab (57 patients) in this open-label, prospective, multi-center, randomized, active-controlled study. Eligible patients were 21 years and older and had either newly diagnosed (80%) or relapsing disease (20%). A majority of the patients were ANCA-positive. Remission of active disease was achieved using a combination of glucocorticoids and cyclophosphamide. Within a maximum of 1 month after the last cyclophosphamide dose, eligible patients (based on BVAS of 0), were randomized in a 1:1 ratio to receive either non-U.S.-licensed rituximab or azathioprine.
The non-U.S.-licensed rituximab was administered as two 500 mg intravenous infusions separated by two weeks (on Day 1 and Day 15) followed by a 500 mg intravenous infusion every 6 months for 18 months. Azathioprine was administered orally at a dose of 2 mg/kg/day for 12 months, then 1.5 mg/kg/day for 6 months, and finally 1 mg/kg/day for 4 months; treatment was discontinued after 22 months. Prednisone treatment was tapered and then kept at a low dose (approximately 5 mg per day) for at least 18 months after randomization. Prednisone dose tapering and the decision to stop prednisone treatment after month 18 were left at the investigators discretion.
Planned follow-up was until month 28 (10 or 6 months, respectively, after the last non-U.S.-licensed rituximab infusion or azathioprine dose). The primary endpoint was the occurrence of major relapse (defined by the reappearance of clinical and/or laboratory signs of vasculitis activity that could lead to organ failure or damage, or could be life threatening) through month 28.
By month 28, major relapse occurred in 3 patients (5%) in the non-U.S.-licensed rituximab group and 17 patients (29%) in the azathioprine group.
The observed cumulative incidence rate of first major relapse during the 28 months was lower in patients on non-U.S.-licensed rituximab relative to azathioprine (Figure 3).
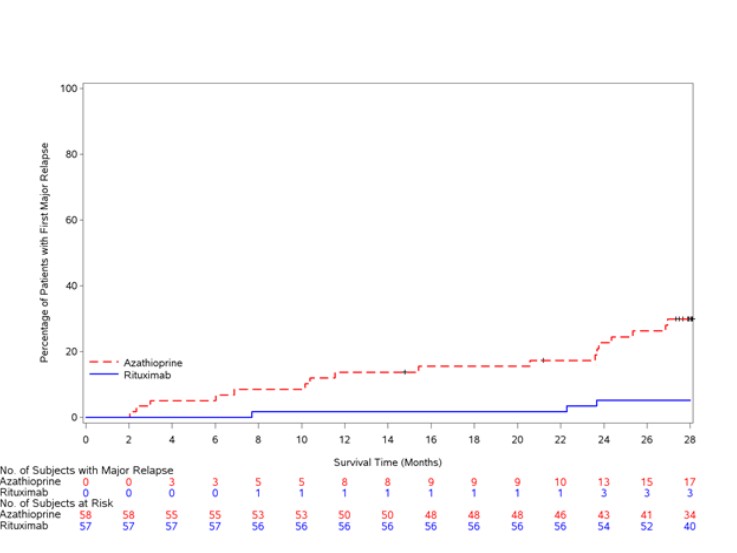 Figure 3 (Figure3) |
| Patients were censored at the last follow-up dates if they had no event |
PV Study 1 (NCT00784589)
Non-U.S.-licensed rituximab in combination with short-term prednisone was compared to prednisone monotherapy as first-line treatment in 90 newly diagnosed adult patients with moderate to severe pemphigus (74 Pemphigus Vulgaris [PV] and 16 Pemphigus Foliaceus [PF]) in this randomized, open-label, controlled, multicenter study (PV Study 1). Patients were between 19 and 79 years of age and had not received prior therapies for pemphigus. In the PV population, 5 (13%) patients in the group treated with non-U.S.-licensed rituximab and 3 (8%) patients in the prednisone group had moderate disease and 33 (87%) patients in the group treated with non-U.S.-licensed rituximab and 33 (92%) patients in the prednisone group had severe disease according to disease severity defined by Harman’s criteria.
Patients were stratified by baseline disease severity (moderate or severe) and randomized 1:1 to receive either the non-U.S.-licensed rituximab and short-term prednisone or long-term prednisone monotherapy. Patients were pre-medicated with antihistamine, acetaminophen and methylprednisolone prior to infusion of the non-U.S.-licensed rituximab. Patients randomized to the group treated with non-U.S.-licensed rituximab received an initial intravenous infusion of 1,000 mg non-U.S.-licensed rituximab on Study Day 1 in combination with a short-term regimen of 0.5 mg/kg/day oral prednisone tapered off over 3 months if they had moderate disease or 1 mg/kg/day oral prednisone tapered off over 6 months if they had severe disease. All patients received a second intravenous infusion of 1,000 mg non-U.S.-licensed rituximab on Study Day 15. Maintenance infusions of 500 mg non-U.S.-licensed rituximab were administered at Months 12 and 18. Patients randomized to the prednisone monotherapy group received an initial 1 mg/kg/day oral prednisone tapered off over 12 months if they had moderate disease or 1.5 mg/kg/day oral prednisone tapered off over 18 months if they had severe disease. Patients in the group treated with non-U.S.-licensed rituximab who relapsed could receive an additional infusion of 1,000 mg non-U.S.-licensed rituximab in combination with reintroduced or escalated prednisone dose. Maintenance and relapse infusions were administered no sooner than 16 weeks following the previous infusion.
The primary endpoint for the study was complete remission (complete epithelialization and absence of new and/or established lesions) at Month 24 without the use of prednisone therapy for 2 months or more (CRoff for greater than or equal to 2 months).
The results of the trial are presented in Table 18.
Non-U.S. licensed rituximab + short-term prednisone N=46 | Prednisone N=44 | |
Number of responders (response rate [%] | 41 (89%) | 15 (34%) |
PV Patients | 34/38 (90%) | 10/36 (28%) |
PF Patients | 7/8 (88%) | 5/8 (63%) |
PV Study 2 (NCT02383589)
In a randomized, double-blind, double-dummy, active-comparator, multicenter study, the efficacy and safety of rituximab compared to mycophenolate mofetil (MMF) were evaluated in patients with moderate-to-severe PV receiving 60 to 120 mg/day oral prednisone or equivalent (1.0 to 1.5 mg/kg/day) at study entry and tapered to reach a dose of 60 or 80 mg/day by Day 1. Patients had a confirmed diagnosis of PV within the previous 24 months and evidence of moderate-to-severe disease defined as a total Pemphigus Disease Area Index (PDAI) activity score of greater than or equal to 15. The study consisted of a screening period of up to 28 days, a 52-week double-blind treatment period, and a 48-week safety follow up period.
One hundred and thirty-five patients were randomized to treatment with rituximab 1,000 mg administered on Day 1, Day 15, Week 24 and Week 26 or oral MMF 2 g/day (starting at 1 g/day on Day 1 and titrated to achieve a goal of 2 g/day by Week 2) for 52 weeks in combination with an initial dose of 60 or 80 mg oral prednisone with the aim of tapering to 0 mg/day by Week 24. Randomization was stratified by duration of PV (within the 1 year prior to screening or greater than 1 year) and geographical region. A dual-assessor approach was used during the study for efficacy and safety evaluations to prevent potential unblinding.
One hundred and twenty-five patients (excluding exploratory data from ten telemedicine patients) were analyzed for efficacy (Modified Intent-to-Treat Population). The primary efficacy endpoint for this study was the proportion of subjects achieving sustained complete remission defined as achieving healing of lesions with no new active lesions (i.e., PDAI activity score of 0) while on 0 mg/day prednisone or equivalent, and maintaining this response for at least 16 consecutive weeks, during the 52-week treatment period.
Secondary endpoints included cumulative oral corticosteroid dose and the total number of disease flares.
The results of the trial are presented in Table 19
Rituximab (N= 62) | MMF (N = 63) | Difference (95% CI) | |
Numbers of responders (response rate [%] | 25 (40.3%) | 6 (9.5%) | 30.80% (14.70%, 45.15%) |
MMF = Mycophenolate mofetil. CI = Confidence Interval | |||
Glucocorticoid exposure
The median (min, max) cumulative oral prednisone dose at Week 52 was 2,775 mg (450, 22,180) in the rituximab group compared to 4,005 mg (900, 19,920) in the MMF group. Topical corticosteroid use and pre-infusion IV methylprednisolone were not included in this analysis. Prior to each infusion, the rituximab group received IV methylprednisolone 100 mg and the MMF group received IV saline solution.
Disease flare
Disease flare was defined as an appearance of 3 or more new lesions a month that do not heal spontaneously within 1 week or by the extension of established lesions in a patient who has achieved disease control. The total number of disease flares was lower in patients treated with rituximab compared to MMF (6 vs. 44).
Infusion-Related Reactions
Inform patients about the signs and symptoms of infusion-related reactions. Advise patients to contact their healthcare provider immediately to report symptoms of infusion-related reactions including urticaria, hypotension, angioedema, sudden cough, breathing problems, weakness, dizziness, palpitations, or chest pain [see Warnings and Precautions (5.1)].
Severe Mucocutaneous Reactions
Advise patients to contact their healthcare provider immediately for symptoms of severe mucocutaneous reactions, including painful sores or ulcers on the mouth, blisters, peeling skin, rash, and pustules [see Warnings and Precautions (5.2)].
Hepatitis B Virus Reactivation
Advise patients to contact their healthcare provider immediately for symptoms of hepatitis including worsening fatigue or yellow discoloration of skin or eyes [see Warnings and Precautions (5.3)].
Progressive Multifocal Leukoencephalopathy (PML)
Advise patients to contact their healthcare provider immediately for signs and symptoms of PML, including new or changes in neurological symptoms such as confusion, dizziness or loss of balance, difficulty talking or walking, decreased strength or weakness on one side of the body, or vision problems [see Warnings and Precautions (5.4)].
Tumor Lysis Syndrome (TLS)
Advise patients to contact their healthcare provider immediately for signs and symptoms of tumor lysis syndrome such as nausea, vomiting, diarrhea, and lethargy [see Warnings and Precautions (5.5)].
Infections
Advise patients to contact their healthcare provider immediately for signs and symptoms of infections including fever, cold symptoms (e.g., rhinorrhea or laryngitis), flu symptoms (e.g., cough, fatigue, body aches), earache or headache, dysuria, oral herpes simplex infection, and painful wounds with erythema and advise patients of the increased risk of infections during and after treatment with TRUXIMA [see Warnings and Precautions (5.6)].
Cardiovascular Adverse Reactions
Advise patients of the risk of cardiovascular adverse reactions, including ventricular fibrillation, myocardial infarction, and cardiogenic shock. Advise patients to contact their healthcare provider immediately to report chest pain and irregular heartbeats [see Warnings and Precautions (5.7)].
Renal Toxicity
Advise patients of the risk of renal toxicity. Inform patients of the need for healthcare providers to monitor kidney function [see Warnings and Precautions (5.8)].
Bowel Obstruction and Perforation
Advise patients to contact their healthcare provider immediately for signs and symptoms of bowel obstruction and perforation, including severe abdominal pain or repeated vomiting [see Warnings and Precautions (5.9)].
Embryo-Fetal Toxicity
Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions(5.11) and Use in Specific Populations(8.1)].
Advise females of reproductive potential to use effective contraception during treatment with TRUXIMA and for at least 12 months after the last dose [seeUse in Specific Populations (8.3)].
Lactation
Advise women not to breastfeed during treatment with TRUXIMA and for at least 6 months after the last dose [see Use in Specific Populations (8.2)].
TRUXIMA® [rituximab-abbs]
TRUXIMA® is a registered trademark of CELLTRION, Inc
Manufactured by:
CELLTRION, Inc.
20, Academy-ro 51 beon-gil,
Yeonsu-gu, Incheon
22014, Republic of Korea
US License No. 1996
Marketed by:
Teva Pharmaceuticals USA, Inc.
North Wales, PA 19454