Other
SERIOUS INFECTIONS
Patients treated with XELJANZ (tablets and oral solution) or XELJANZ XR (extended-release tablets) are at increased risk for developing serious bacterial, fungal, viral, and opportunistic infections, including tuberculosis (TB), that may lead to hospitalization or death [see Warnings and Precautions (5.1) and Adverse Reactions (6.1)]. Most patients who developed these infections were taking concomitant immunosuppressants such as methotrexate or corticosteroids. Reported infections included:
- Active TB, which may present with pulmonary or extrapulmonary disease. Patients should be tested for latent TB before XELJANZ/XELJANZ XR use and during therapy. Treatment for latent infection should be initiated prior to XELJANZ/XELJANZ XR use.
- Invasive fungal infections, including cryptococcosis and pneumocystosis. Patients with invasive fungal infections may present with disseminated, rather than localized, disease.
- Bacterial, viral, including herpes zoster, and other infections due to opportunistic pathogens.
- 5 mg twice daily may be switched to XELJANZ XR extended-release tablets 11 mg once daily the day following the last dose of XELJANZ tablets 5 mg.
- 10 mg twice daily may be switched to XELJANZ XR extended-release tablets 22 mg once daily the day following the last dose of XELJANZ tablets 10 mg.
o 5 mg of tofacitinib: White, round, immediate-release film-coated tablets, debossed with “Pfizer” on one side, and “JKI 5” on the other side.o 10 mg of tofacitinib: Blue, round, immediate-release film-coated tablets, debossed with “Pfizer” on one side, and “JKI 10” on the other side.o 11 mg of tofacitinib: Pink, oval, extended-release film-coated tablets with a drilled hole at one end of the tablet band and “JKI 11” printed on one side of the tablet.o 22 mg of tofacitinib: Beige, oval, extended-release film-coated tablets with a drilled hole at one end of the tablet band and “JKI 22” printed on one side of the tablet.- Monitor lymphocyte counts at baseline and every 3 months thereafter.
- Avoid initiation of XELJANZ/XELJANZ XR treatment in patients with a low lymphocyte count (i.e., less than 500 cells/mm3). In patients who develop a confirmed absolute lymphocyte count less than 500 cells/mm3, treatment with XELJANZ/XELJANZ XR is not recommended.
- Monitor neutrophil counts at baseline and after 4-8 weeks of treatment and every 3 months thereafter.
- Avoid initiation of XELJANZ/XELJANZ XR treatment in patients with a low neutrophil count (i.e., ANC less than 1000 cells/mm3). For patients who develop a persistent ANC of 500 to 1000 cells/mm3, interrupt dosing until ANC is greater than or equal to 1000 cells/mm3. In patients who develop an ANC less than 500 cells/mm3, treatment with XELJANZ/XELJANZ XR is not recommended.
- Monitor hemoglobin at baseline and after 4-8 weeks of treatment and every 3 months thereafter.
- Avoid initiation of XELJANZ/XELJANZ XR treatment in patients with a low hemoglobin level (i.e., less than 9 g/dL). Interrupt treatment with XELJANZ/XELJANZ XR in patients who develop hemoglobin levels less than 8 g/dL or whose hemoglobin level drops greater than 2 g/dL on treatment until hemoglobin values have normalized.
- Routine monitoring of liver tests and prompt investigation of the causes of liver enzyme elevations is recommended to identify potential cases of drug-induced liver injury.
- If drug-induced liver injury is suspected, interrupt the administration of XELJANZ/XELJANZ XR until this diagnosis has been excluded.
- Perform assessment of lipid parameters approximately 4-8 weeks following initiation of XELJANZ/XELJANZ XR therapy.
- Manage patients according to clinical guidelines [e.g., National Cholesterol Educational Program (NCEP)] for the management of hyperlipidemia.
- XELJANZ (monotherapy) 5 mg twice daily (292 patients) or 10 mg twice daily (306 patients),
- In combination with DMARDs (including methotrexate), XELJANZ 5 mg twice daily (1044 patients) or 10 mg twice daily (1043 patients) and
- Placebo (809 patients).
- Mean LDL cholesterol increased by 15% in the XELJANZ 5 mg twice daily arm and 19% in the XELJANZ 10 mg twice daily arm.
- Mean HDL cholesterol increased by 10% in the XELJANZ 5 mg twice daily arm and 12% in the XELJANZ 10 mg twice daily arm.
- Mean LDL/HDL ratios were essentially unchanged in XELJANZ-treated patients.
- Study PsA-I (NCT01877668) had a duration of 12 months and enrolled adults who had an inadequate response to a nonbiologic DMARD and who were naïve to treatment with a TNF blocker. Study PsA-I included a 3-month placebo-controlled period and also included adalimumab 40 mg subcutaneously once every 2 weeks for 12 months.
- Study PsA-II (NCT01882439) had a duration of 6 months and enrolled adults who had an inadequate response to at least one approved TNF blocker. This clinical trial included a 3-month placebo-controlled period.
- 3 malignancies (excluding NMSC) in 474 patients who received XELJANZ plus non-biologic DMARD (6 to 12 months exposure)
- 0 malignancies in 236 patients who received placebo plus non-biologic DMARD group (3 months exposure) and
- 0 malignancies in 106 patients in patients who received adalimumab plus non-biologic DMARD group (12 months exposure).
- Study AS-I (NCT03502616) had a duration of 48 weeks and enrolled adults who had an inadequate response to at least 2 NSAIDs. Study AS-I included a 16-week double-blind period in which patients received XELJANZ 5 mg or placebo twice daily and a 32-week open-label treatment period in which all patients received XELJANZ 5 mg twice daily.
- Study AS-II (NCT01786668) had a duration of 16 weeks and enrolled adults who had an inadequate response to at least 2 NSAIDs. This clinical trial included a 12-week treatment period in which patients received either XELJANZ 2 mg (40% of the recommended dose), 5 mg, 10 mg, or placebo twice daily. A dosage of XELJANZ 10 mg twice daily is not recommended for the treatment of AS. For the treatment of adults with active AS [see Indications and Usage (1.3)], the recommended dosage of XELJANZ is 5 mg twice daily and the recommended dosage for XELJANZ XR is 11 mg once daily [see Dosage and Administration (2.3)].
- Patient Global Assessment of Disease Activity (0–10)Measured on a numerical rating scale with 0 = not active or no pain, 10 = very active or most severe pain.
,type I error-controlled.
- Total spinal pain (0–10), - BASFI (0–10)Bath Ankylosing Spondylitis Functional Index measured on a numerical rating scale with 0 = easy and 10 = impossible.
,- Inflammation (0–10)Inflammation is the mean of two patient-reported stiffness self-assessments in BASDAI.
,- 179 (30%) patients were in remission
- 289 (49%) patients were receiving oral corticosteroids
- 265 (45%), 445 (75%), and 413 (70%) patients had previously failed or were intolerant to TNF blocker therapy, corticosteroids, and immunosuppressants, respectively. XELJANZ and XELJANZ XR are indicated only for use in patients who have had inadequate response or intolerance to one or more TNF blockers [see Indications and Usage (1.5)].
The risks and benefits of XELJANZ/XELJANZ XR treatment should be carefully considered prior to initiating therapy in patients with chronic or recurrent infection.
Patients should be closely monitored for the development of signs and symptoms of infection during and after XELJANZ/XELJANZ XR treatment, including the possible development of TB in patients who tested negative for latent TB infection prior to initiating therapy. If a serious infection develops, interrupt XELJANZ/XELJANZ XR until the infection is controlled [see Warnings and Precautions (5.1)].
MORTALITY
In a large, randomized, postmarketing safety study in rheumatoid arthritis (RA) patients 50 years of age and older with at least one cardiovascular (CV) risk factor comparing XELJANZ tablets 5 mg or 10 mg twice a day to tumor necrosis factor (TNF) blockers, a higher rate of all-cause mortality, including sudden CV death, was observed with XELJANZ tablets 5 mg or 10 mg twice a day [see Warnings and Precautions (5.2)]. XELJANZ 10 mg twice daily and XELJANZ XR 22 mg once daily dosages are not recommended for the treatment of RA, psoriatic arthritis (PsA), ankylosing spondylitis (AS), or polyarticular course juvenile idiopathic arthritis (pcJIA) [see Dosage and Administration (2.3, 2.4)].
MALIGNANCIES
Malignancies, including lymphomas and solid tumors, have occurred in patients treated with XELJANZ and other Janus kinase inhibitors used to treat inflammatory conditions. In RA patients, a higher rate of malignancies (excluding non-melanoma skin cancer (NMSC)) was observed in patients treated with XELJANZ tablets 5 mg or 10 mg twice a day compared with TNF blockers [see Warnings and Precautions (5.3)].
Lymphomas and lung cancers were observed at a higher rate in patients treated with XELJANZ tablets 5 mg or 10 mg twice a day in RA patients compared to those treated with TNF blockers. Patients who are current or past smokers are at additional increased risk.
MAJOR ADVERSE CARDIOVASCULAR EVENTS
RA patients 50 years of age and older with at least one cardiovascular risk factor, treated with XELJANZ tablets 5 mg or 10 mg twice daily, had a higher rate of major adverse cardiovascular events (MACE) (defined as cardiovascular death, myocardial infarction, and stroke), compared to those treated with TNF blockers. Patients who are current or past smokers are at additional increased risk. Discontinue XELJANZ/XELJANZ XR in patients that have experienced a myocardial infarction or stroke [see Warnings and Precautions (5.4)].
THROMBOSIS
Thrombosis, including pulmonary embolism, deep venous thrombosis, and arterial thrombosis have occurred in patients treated with XELJANZ and other Janus kinase inhibitors used to treat inflammatory conditions. Many of these events were serious and some resulted in death. RA patients 50 years of age and older with at least one cardiovascular risk factor treated with XELJANZ tablets 5 mg or 10 mg twice daily compared to TNF blockers had an observed increase in incidence of these events. Avoid XELJANZ/XELJANZ XR in patients at risk. Discontinue XELJANZ/XELJANZ XR and promptly evaluate patients with symptoms of thrombosis [see Warnings and Precautions (5.5)].
Switching from XELJANZ Tablets to XELJANZ XR Extended-Release Tablets
Patients treated with XELJANZ tablets 5 mg twice daily may be switched to XELJANZ XR extended-release tablets 11 mg once daily the day following the last dose of XELJANZ tablets 5 mg.
Switching from XELJANZ Tablets to XELJANZ XR Extended-Release Tablets
Patients treated with XELJANZ tablets:
XELJANZ tablets:
XELJANZ XR extended-release tablets:
XELJANZ oral solution:
1 mg/mL of tofacitinib: Clear, colorless oral solution.
Tuberculosis
Evaluate and test patients for latent or active tuberculosis (TB) infection prior to and per applicable guidelines during administration of XELJANZ/XELJANZ XR.
Consider anti-TB therapy prior to administration of XELJANZ/XELJANZ XR in patients with a past history of latent or active TB in whom an adequate course of treatment cannot be confirmed, and for patients with a negative test for latent TB but who have risk factors for TB infection. Consultation with a physician with expertise in the treatment of TB is recommended to aid in the decision about whether initiating anti-TB therapy is appropriate for an individual patient.
Monitor patients closely for the development of signs and symptoms of TB, including patients who tested negative for latent TB infection prior to initiating therapy.
Treat patients with latent TB with standard antimycobacterial therapy before administering XELJANZ/XELJANZ XR.
Viral Reactivation
Viral reactivation, including cases of herpes virus reactivation (e.g., herpes zoster), were observed in clinical studies with XELJANZ. Postmarketing cases of hepatitis B reactivation have been reported in patients treated with XELJANZ. The impact of XELJANZ/XELJANZ XR on chronic viral hepatitis reactivation is unknown. Patients who screened positive for hepatitis B or C were excluded from clinical trials. Perform screening for viral hepatitis in accordance with clinical guidelines before starting therapy with XELJANZ/XELJANZ XR. The risk of herpes zoster is increased in patients treated with XELJANZ/XELJANZ XR and appears to be higher in patients treated with XELJANZ in Japan and Korea.
Progressive Multifocal Leukoencephalopathy (PML)
Postmarketing cases of PML have been reported during treatment with XELJANZ/XELJANZ XR; in some of these patients, immune reconstitution inflammatory syndrome (IRIS) occurred within several weeks after discontinuation of XELJANZ/XELJANZ XR. Consider PML in any patient presenting with new onset or worsening neurological symptoms. If PML is suspected, stop XELJANZ/XELJANZ XR/XELJANZ oral solution and evaluate; if PML is confirmed, discontinue treatment and manage patients appropriately.
Non-Melanoma Skin Cancer
Non-melanoma skin cancers (NMSCs) have been reported in patients treated with XELJANZ tablets. Periodic skin examination is recommended for patients who are at increased risk for skin cancer. In the UC population, treatment with XELJANZ tablets 10 mg twice daily was associated with greater risk of NMSC than treatment with placebo.
Lymphocyte Abnormalities
Treatment with XELJANZ tablets was associated with initial lymphocytosis at one month of XELJANZ tablets treatment followed by a gradual decrease in mean absolute lymphocyte counts below the baseline of approximately 10% during 12 months of therapy. Lymphocyte counts less than 500 cells/mm3 in these patients were associated with an increased incidence of treated and serious infections.
Neutropenia
Treatment with XELJANZ tablets was associated with an increased incidence of neutropenia (less than 2000 cells/mm3) compared to treatment with placebo.
Anemia
Liver Enzyme Elevations
Treatment with XELJANZ tablets was associated with an increased incidence of liver enzyme elevation compared to treatment with placebo. Most of these abnormalities occurred in studies with background DMARD therapy (primarily methotrexate).
Lipid Elevations
Treatment with XELJANZ tablets was associated with dose-dependent increases in lipid parameters including total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol. Maximum changes in these lipid parameters were generally observed within 6 weeks. There were no clinically relevant changes in LDL/HDL cholesterol ratios. The effect of these lipid parameter elevations on cardiovascular morbidity and mortality has not been determined.
Adverse Reactions in Adults with Rheumatoid Arthritis
In RA Safety Study 1, 1,455 adults were treated with XELJANZ 5 mg twice daily, 1,456 adults were treated with 10 mg twice daily, and 1,451 adults were treated with a TNF blocker for a median of 4 years [see Clinical Studies (14.6)]. A dosage of XELJANZ 10 mg twice daily is not recommended for the treatment of RA because of increased risks [see Dosage and Administration (2.3) and Warnings and Precautions (5)]. For the treatment of adults with moderately to severely active RA [see Indications and Usage (1.1)], the recommended dosage of XELJANZ is 5 mg twice daily and the recommended dosage for XELJANZ XR is 11 mg once daily.
The safety of XELJANZ was also evaluated in two Phase 2 and five Phase 3 double-blind, placebo-controlled, multicenter trials in patients with RA. In these trials, adults were randomized to receive:
All seven trials included provisions for patients taking placebo to receive treatment with XELJANZ at Month 3 or Month 6 either by patient response (based on uncontrolled disease activity) or by design, so that adverse events cannot always be unambiguously attributed to a given treatment. Therefore, some analyses that follow include patients who changed treatment by design or by patient response from placebo to XELJANZ in both the placebo and XELJANZ group of a given interval. Comparisons between placebo and XELJANZ groups were based on the first 3 months of exposure, and comparisons between XELJANZ 5 mg twice daily and XELJANZ 10 mg twice daily were based on the first 12 months of exposure.
The long-term safety population includes all adults with RA who participated in a double-blind, placebo-controlled trial (including earlier development phase studies) and then participated in one of two long-term safety studies. The design of the long-term safety studies allowed for modification of XELJANZ doses according to clinical judgment. This limits the interpretation of the long-term safety data with respect to dose.
The most common serious adverse reactions were serious infections [see Warnings and Precautions (5.1)].
The proportion of patients who discontinued treatment due to any adverse reaction during the 0 to 3 months exposure in the double-blind, placebo-controlled trials was 4% for XELJANZ-treated patients and 3% for placebo-treated patients.
Overall Infections
In the seven placebo-controlled trials in patients with RA, during the 0 to 3 months exposure, the overall frequency of infections was 20% and 22% in the XELJANZ 5 mg twice daily and XELJANZ 10 mg twice daily groups, respectively, and 18% in the placebo group.
The most commonly reported infections with XELJANZ were upper respiratory tract infections, nasopharyngitis, and urinary tract infections (4%, 3%, and 2% of patients, respectively).
Serious Infections: In the seven placebo-controlled trials in patients with RA, during the 0 to 3 months exposure, serious infections were reported in 1 patient (0.5 events per 100 patient-years) who received placebo and 11 patients (1.7 events per 100 patient-years) who received XELJANZ 5 mg or 10 mg twice daily. The rate difference between treatment groups (and the corresponding 95% confidence interval) was 1.1 (-0.4, 2.5) events per 100 patient-years for the combined XELJANZ 5 mg twice daily and 10 mg twice daily group minus placebo.
In the seven placebo-controlled trials, during the 0 to 12 months exposure, serious infections were reported in 34 patients (2.7 events per 100 patient-years) who received XELJANZ 5 mg twice daily and 33 patients (2.7 events per 100 patient-years) who received XELJANZ 10 mg twice daily. The rate difference between XELJANZ doses (and the corresponding 95% confidence interval) was -0.1 (-1.3, 1.2) events per 100 patient-years for XELJANZ 10 mg twice daily minus XELJANZ 5 mg twice daily.
The most common serious infections included pneumonia, cellulitis, herpes zoster, and urinary tract infection [see Warnings and Precautions (5.1)].
Tuberculosis: In the seven placebo-controlled trials in patients with RA, during the 0 to 3 months exposure, tuberculosis (TB) was not reported in patients who received placebo, XELJANZ 5 mg twice daily, or XELJANZ 10 mg twice daily.
In the seven placebo-controlled trials, during the 0 to 12 months exposure, TB was reported in 0 patients who received XELJANZ 5 mg twice daily and 6 patients (0.5 events per 100 patient-years) who received XELJANZ 10 mg twice daily. The rate difference between XELJANZ doses (and the corresponding 95% confidence interval) was 0.5 (0.1, 0.9) events per 100 patient-years for XELJANZ 10 mg twice daily minus XELJANZ 5 mg twice daily.
Cases of disseminated TB were also reported. The median XELJANZ exposure prior to diagnosis of TB was 10 months (range from 152 to 960 days) [see Warnings and Precautions (5.1)].
Opportunistic Infections (excluding tuberculosis): In the seven placebo-controlled trials in patients with RA, during the 0 to 3 months exposure, opportunistic infections were not reported in patients who received placebo, XELJANZ 5 mg twice daily, or XELJANZ 10 mg twice daily.
In the seven placebo-controlled trials, during the 0 to 12 months exposure, opportunistic infections were reported in 4 patients (0.3 events per 100 patient-years) who received XELJANZ 5 mg twice daily and 4 patients (0.3 events per 100 patient-years) who received XELJANZ 10 mg twice daily. The rate difference between XELJANZ doses (and the corresponding 95% confidence interval) was 0 (-0.5, 0.5) events per 100 patient-years for XELJANZ 10 mg twice daily minus XELJANZ 5 mg twice daily.
The median XELJANZ exposure prior to diagnosis of an opportunistic infection was 8 months (range from 41 to 698 days) [see Warnings and Precautions (5.1)].
Malignancies
In the seven placebo-controlled trials in patients with RA, during the 0 to 3 months exposure, malignancies excluding NMSC were reported in 0 patients who received placebo and 2 patients (0.3 events per 100 patient-years) who received either XELJANZ 5 mg or 10 mg twice daily. The rate difference between treatment groups (and the corresponding 95% confidence interval) was 0.3 (-0.1, 0.7) events per 100 patient-years for the combined XELJANZ 5 mg and 10 mg twice daily group minus placebo.
In the seven placebo-controlled trials, during the 0 to 12 months exposure, malignancies excluding NMSC were reported in 5 patients (0.4 events per 100 patient-years) who received XELJANZ 5 mg twice daily and 7 patients (0.6 events per 100 patient-years) who received XELJANZ 10 mg twice daily. The rate difference between XELJANZ doses (and the corresponding 95% confidence interval) was 0.2 (-0.4, 0.7) events per 100 patient-years for XELJANZ 10 mg twice daily minus XELJANZ 5 mg twice daily. One of these malignancies was a case of lymphoma that occurred during the 0-to-12-month period in a patient treated with XELJANZ 10 mg twice daily.
The most common types of malignancy, including malignancies observed during the long-term extension in XELJANZ-treated patients, were lung and breast cancer, followed by gastric, colorectal, renal cell, prostate cancer, lymphoma, and malignant melanoma [see Warnings and Precautions (5.3)].
Laboratory Abnormalities
Lymphopenia: In the placebo-controlled clinical trials in patients with RA, confirmed decreases in absolute lymphocyte counts below 500 cells/mm3 occurred in 0.04% of patients for the XELJANZ 5 mg twice daily and 10 mg twice daily groups combined during the first 3 months of exposure.
Confirmed lymphocyte counts less than 500 cells/mm3 were associated with an increased incidence of treated and serious infections [see Warnings and Precautions (5.9)].
Neutropenia: In the placebo-controlled clinical trials in patients with RA, confirmed decreases in ANC below 1,000 cells/mm3 occurred in 0.07% of patients for the XELJANZ 5 mg twice daily and 10 mg twice daily groups combined during the first 3 months of exposure.
There were no confirmed decreases in ANC below 500 cells/mm3 observed in any treatment group. There was no clear relationship between neutropenia and the occurrence of serious infections.
In the long-term safety population, the pattern and incidence of confirmed decreases in ANC remained consistent with what was seen in the placebo-controlled clinical trials [see Warnings and Precautions (5.9)].
Liver Enzyme Elevations: Confirmed increases in liver enzymes greater than 3 times the upper limit of normal (3 × ULN) were observed in patients with RA treated with XELJANZ. In patients experiencing liver enzyme elevation, modification of treatment regimen, such as reduction in the dose of concomitant DMARD, interruption of XELJANZ, or reduction in XELJANZ dosage, resulted in decrease or normalization of liver enzymes.
In the placebo-controlled monotherapy trials (0–3 months), no differences in the incidence of ALT or AST elevations were observed between the placebo, and XELJANZ 5 mg, and 10 mg twice daily groups.
In the placebo-controlled background DMARD trials (0–3 months), ALT elevations greater than 3 × ULN were observed in 1.0%, 1.3% and 1.2% of patients who received placebo, XELJANZ 5 mg, and 10 mg twice daily, respectively. In these trials, AST elevations greater than 3 × ULN were observed in 0.6%, 0.5% and 0.4% of patients who received placebo, XELJANZ 5 mg, and 10 mg twice daily, respectively.
One case of drug-induced liver injury was reported in a patient treated with XELJANZ 10 mg twice daily for approximately 2.5 months. The patient developed symptomatic elevations of AST and ALT greater than 3 × ULN and bilirubin elevations greater than 2 × ULN, which required hospitalizations and a liver biopsy.
Lipid Elevations: In the placebo-controlled clinical trials in patients with RA, dose-related elevations in lipid parameters (total cholesterol, LDL cholesterol, HDL cholesterol, triglycerides) were observed at one month of exposure and remained stable thereafter. Changes in lipid parameters during the first 3 months of exposure in the placebo-controlled clinical trials are summarized below:
In a placebo-controlled clinical trial, elevations in LDL cholesterol and ApoB decreased to pretreatment levels in response to statin therapy.
In the long-term safety population, elevations in lipid parameters remained consistent with what was seen in the placebo-controlled clinical trials.
Serum Creatinine Elevations: In the placebo-controlled clinical trials in patients with RA, dose-related elevations in serum creatinine were observed with XELJANZ treatment. The mean increase in serum creatinine was <0.1 mg/dL in the 12-month pooled safety analysis; however, with increasing duration of exposure in the long-term extensions, up to 2% of patients were discontinued from XELJANZ treatment due to the protocol-specified discontinuation criterion of an increase in creatinine by more than 50% of baseline. The clinical significance of the observed serum creatinine elevations is unknown.
Common Adverse Reactions
Table 5 displays adverse reactions that occurred in 2% or more of patients on XELJANZ 5 mg or 10 mg twice daily and at least 1% greater than in XELJANZ-treated patients that observed in placebo-treated patients with or without DMARD in the RA trials.
| Preferred Term | Placebo | XELJANZ 5 mg Twice Daily | XELJANZ 10 mg Twice Daily The recommended dose of XELJANZ for the treatment of RA is 5 mg twice daily [see Dosage and Administration (2)]. |
|---|---|---|---|
| N = 809 (%) | N = 1336 (%) | N = 1349 (%) | |
| N reflects randomized and treated patients from the seven placebo-controlled clinical trials. | |||
Upper respiratory tract infection | 3 | 4 | 4 |
Nasopharyngitis | 3 | 4 | 3 |
Diarrhea | 2 | 4 | 3 |
Headache | 2 | 4 | 3 |
Hypertension | 1 | 2 | 2 |
Other adverse reactions that occurred in placebo-controlled and open-label extension studies in patients with RA included:
Blood and lymphatic system disorders: Anemia
Infections and infestations: Diverticulitis
Metabolism and nutrition disorders: Dehydration
Psychiatric disorders: Insomnia
Nervous system disorders: Paresthesia
Respiratory, thoracic and mediastinal disorders: Dyspnea, cough, sinus congestion, interstitial lung disease (cases were limited to patients with RA and some were fatal)
Gastrointestinal disorders: Abdominal pain, dyspepsia, vomiting, gastritis, nausea
Hepatobiliary disorders: Hepatic steatosis
Skin and subcutaneous tissue disorders: Rash, erythema, pruritus
Musculoskeletal, connective tissue and bone disorders: Musculoskeletal pain, arthralgia, tendonitis, joint swelling
Neoplasms benign, malignant and unspecified (including cysts and polyps): Non-melanoma skin cancers
General disorders and administration site conditions: Pyrexia, fatigue, peripheral edema
Clinical Experience in Methotrexate-Naïve Patients
Study RA-VI was an active-controlled clinical trial in methotrexate-naïve patients [see Clinical Studies (14)]. The safety experience in these patients was consistent with Studies RA-I through V.
Adverse Reactions in Adults with Psoriatic Arthritis
The safety of XELJANZ was evaluated in 2 double-blind Phase 3 clinical trials in adults with active psoriatic arthritis (PsA):
In these combined Phase 3 clinical trials, 238 patients were randomized and treated with XELJANZ 5 mg twice daily and 236 patients were randomized and treated with XELJANZ 10 mg twice daily. A dosage of XELJANZ 10 mg twice daily is not recommended for the treatment of PsA. For the treatment of adults with active PsA [see Indications and Usage (1.2)], the recommended dosage of XELJANZ is 5 mg twice daily and the recommended dosage for XELJANZ XR is 11 mg once daily [see Dosage and Administration (2.3)].
All patients in the clinical trials in patients with PsA were required to receive treatment with a stable dose of a nonbiologic DMARD [the majority (79%) received methotrexate]. The study population randomized and treated with XELJANZ (474 patients) included 45 (10%) patients aged 65 years or older and 66 (14%) patients with diabetes at baseline.
During the 2 PsA controlled clinical trials, there were:
No lymphomas were reported. Malignancies have also been observed in the long-term extension study in patients with PsA treated with XELJANZ.
The safety profile observed in adults with active PsA treated with XELJANZ was consistent with the safety profile observed in adults with RA.
Adverse Reactions in Adults with Ankylosing Spondylitis
The safety of XELJANZ was evaluated in adults with active ankylosing spondylitis (AS) in a double-blind placebo-controlled Phase 3 clinical trial (Study AS-I) and in a dose-ranging Phase 2 clinical trial (Study AS-II).
In the combined Phase 2 and Phase 3 clinical trials, a total of 420 patients were treated with either XELJANZ 2 mg, 5 mg, or 10 mg twice daily. Of these, 316 patients were treated with XELJANZ 5 mg twice daily for up to 48 weeks. In the combined double-blind period, 185 patients were randomized to and treated with XELJANZ 5 mg twice daily and 187 to placebo for up to 16 weeks. Concomitant treatment with stable doses of nonbiologic DMARDs, NSAIDs, or corticosteroids (≤10 mg/day) was permitted. The study population randomized and treated with XELJANZ included 13 (3%) patients aged 65 years or older and 18 (4%) patients with diabetes at baseline.
The safety profile observed in adults with AS treated with XELJANZ was consistent with the safety profile observed in adults with RA and PsA.
Adverse Reactions in Pediatric Patients 2 Years of Age and Older with Polyarticular Course Juvenile Idiopathic Arthritis
XELJANZ tablets and XELJANZ oral solution 5 mg twice daily or weight-based equivalent twice daily was studied in 225 pediatric patients from 2 years to 17 years of age in Study pcJIA-I [see Clinical Studies (14.4)] and one open-label extension study (Study A3921145). The total patient exposure (defined as patients who received at least one dose of XELJANZ tablets or XELJANZ oral solution) was 105.6 patient-years in Study pcJIA-I and 777.5 patient-years in Study A3921145.
In general, the types of adverse reactions in pediatric patients 2 years of age and older with pcJIA, were consistent with those seen in adults with RA and PsA (see Adverse Reactions in Adults with Rheumatoid Arthritis and Adverse Reactions in Adults with Psoriatic Arthritis).
Adverse Reactions in Adults with Ulcerative Colitis
The safety of XELJANZ has been evaluated in adults with moderately to severely active UC in 4 randomized, double-blind, placebo-controlled trials (UC-I, UC-II, UC-III, and dose-ranging UC-V) and an open-label long-term extension study (UC-IV) [see Clinical Studies (14.5)].
Adverse reactions reported in ≥5% of patients treated with either XELJANZ 5 mg or 10 mg twice daily and ≥1% greater than reported in patients receiving placebo in either the induction or maintenance clinical trials of patients with UC were: nasopharyngitis, elevated cholesterol levels, headache, upper respiratory tract infection, increased blood creatine phosphokinase, rash, diarrhea, and herpes zoster.
Induction Trials in Adults with UC
Common adverse reactions reported in ≥2% of patients treated with XELJANZ 10 mg twice daily and ≥1% greater in XELJANZ-treated patients than placebo-treated patients in the 3 induction trials of patients with UC (Studies UC-I, UC-II, and UC-V) were: headache, nasopharyngitis, elevated cholesterol levels, acne, increased blood creatine phosphokinase, and pyrexia.
Maintenance Trial in Adults with UC
Common adverse reactions reported in ≥4% of patients treated with either dosage of XELJANZ and ≥1% greater than reported in patients treated with placebo in the maintenance trial of patients with UC (Study UC-III) are shown in Table 6.
Preferred Term | Placebo | XELJANZ 5 mg Twice Daily | XELJANZ 10 mg Twice Daily |
N = 198 (%) | N = 198 (%) | N = 196 (%) | |
Nasopharyngitis | 6 | 10 | 14 |
Elevated cholesterol levels Includes hypercholesterolemia, hyperlipidemia, blood cholesterol increased, dyslipidemia, blood triglycerides increased, low-density lipoprotein increased, low-density lipoprotein abnormal, or lipids increased. | 1 | 5 | 9 |
Headache | 6 | 9 | 3 |
Upper respiratory tract infection | 4 | 7 | 6 |
Increased blood creatine phosphokinase | 2 | 3 | 7 |
Rash | 4 | 3 | 6 |
Diarrhea | 3 | 2 | 5 |
Herpes zoster | 1 | 1 | 5 |
Gastroenteritis | 3 | 3 | 4 |
Anemia | 2 | 4 | 2 |
Nausea | 3 | 1 | 4 |
Dose-dependent adverse reactions seen in patients treated with XELJANZ 10 mg twice daily, in comparison to 5 mg twice daily, include the following: herpes zoster infections, serious infections, and NMSC [see Warnings and Precautions (5.1, 5.3)].
During the UC controlled clinical studies (8-week induction and 52-week maintenance studies), which included 1,220 patients, 0 cases of solid cancer or lymphoma were observed in XELJANZ-treated patients.
In the long-term extension study, malignancies (including solid cancers, lymphomas and NMSC) were observed in patients treated with XELJANZ 5 mg and 10 mg twice daily [see Warnings and Precautions (5.3)]. Five cases of pulmonary embolism were reported in patients taking XELJANZ 10 mg twice daily, including one fatality in a patient with advanced cancer [see Warnings and Precautions (5.5)].
Risk Summary
The available data with XELJANZ (tablets and oral solution) and XELJANZ XR (extended-release tablets) from a pregnancy exposure registry that enrolled 11 exposed pregnant females, pharmacovigilance, and published literature are insufficient to draw conclusions about a drug‑associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. There are risks to the mother and the fetus associated with RA and UC in pregnancy (see Clinical Considerations). In animal reproduction studies, fetocidal and teratogenic effects were noted when pregnant rats and rabbits received tofacitinib during the period of organogenesis at exposures multiples of 73-times and 6.3-times the maximum recommended dose of 10 mg twice daily, respectively. Further, in a peri- and post-natal study in rats, tofacitinib resulted in reductions in live litter size, postnatal survival, and pup body weights at exposure multiples of approximately 73-times the recommended dosage of 5 mg twice daily and approximately 36 times the maximum recommended dosage of 10 mg twice daily, respectively (see Data).
The background risks of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risks in the U.S. general population of major birth defects and miscarriages are 2 to 4% and 15 to 20% of clinically recognized pregnancies, respectively.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk: Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with RA or UC. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 grams) infants, and small for gestational age at birth.
Data
Animal Data: In a rat embryofetal developmental study, in which pregnant rats received tofacitinib during organogenesis, tofacitinib was teratogenic at exposure levels approximately 146 times the recommended dose of 5 mg twice daily, and approximately 73 times the maximum recommended dose of 10 mg twice daily (on an AUC basis at oral doses of 100 mg/kg/day in rats). Teratogenic effects consisted of external and soft tissue malformations of anasarca and membranous ventricular septal defects, respectively; and skeletal malformations or variations (absent cervical arch; bent femur, fibula, humerus, radius, scapula, tibia, and ulna; sternoschisis; absent rib; misshapen femur; branched rib; fused rib; fused sternebra; and hemicentric thoracic centrum). In addition, there was an increase in post-implantation loss, consisting of early and late resorptions, resulting in a reduced number of viable fetuses. Mean fetal body weight was reduced. No developmental toxicity was observed in rats at exposure levels approximately 58 times the recommended dose of 5 mg twice daily, and approximately 29 times the maximum recommended dose of 10 mg twice daily (on an AUC basis at oral doses of 30 mg/kg/day in pregnant rats).
In a rabbit embryofetal developmental study in which pregnant rabbits received tofacitinib during the period of organogenesis, tofacitinib was teratogenic at exposure levels approximately 13 times the recommended dose of 5 mg twice daily, and approximately 6.3 times the maximum recommended dose of 10 mg twice daily (on an AUC basis at oral doses of 30 mg/kg/day in rabbits) in the absence of signs of maternal toxicity. Teratogenic effects included thoracogastroschisis, omphalocele, membranous ventricular septal defects, and cranial/skeletal malformations (microstomia, microphthalmia), mid-line and tail defects. In addition, there was an increase in post-implantation loss associated with late resorptions. No developmental toxicity was observed in rabbits at exposure levels approximately 3 times the recommended dose of 5 mg twice daily, and approximately 1.5 times the maximum recommended dose of 10 mg twice daily (on an AUC basis at oral doses of 10 mg/kg/day in pregnant rabbits).
In a peri- and postnatal development study in pregnant rats that received tofacitinib from gestation day 6 through day 20 of lactation, there were reductions in live litter size, postnatal survival, and pup body weights at exposure levels approximately 73 times the recommended dose of 5 mg twice daily, and approximately 36 times the maximum recommended dose of 10 mg twice daily (on an AUC basis at oral doses of 50 mg/kg/day in rats). There was no effect on behavioral and learning assessments, sexual maturation or the ability of the F1 generation rats to mate and produce viable F2 generation fetuses in rats at exposure levels approximately 17 times the recommended dose of 5 mg twice daily, and approximately 8.3 times the maximum recommended dose of 10 mg twice daily (on an AUC basis at oral doses of 10 mg/kg/day in rats).
Risk Summary
Based on published data, tofacitinib is present in human milk. Data on the effects of tofacitinib on the breastfed infant is limited to a small number of cases with no reported adverse effects. There are no data on the effects on milk production. Given the serious adverse reactions seen in patients treated with XELJANZ (tablets and oral solution) and XELJANZ XR (extended-release tablets), such as increased risk of serious infections, advise patients that breastfeeding is not recommended during treatment and for at least 18 hours after the last dose of XELJANZ or 36 hours after the last dose of XELJANZ XR (approximately 6 elimination half-lives).
Data
Following administration of tofacitinib to lactating rats, concentrations of tofacitinib in milk over time paralleled those in serum and were approximately 2 times higher in milk relative to maternal serum at all time points measured.
Contraception
Females
In an animal reproduction study, tofacitinib at AUC multiples of 13 times the recommended dosage of 5 mg twice daily and 6.3 times the maximum recommended dosage of 10 mg twice daily demonstrated adverse embryo-fetal findings [see Use in Specific Populations (8.1)]. However, there is uncertainty as to how these animal findings relate to females of reproductive potential treated with the recommended clinical dosage. Consider pregnancy planning and prevention for females of reproductive potential.
Infertility
Females
Based on findings in rats, treatment with XELJANZ (tablets and oral solution) and XELJANZ XR (extended-release tablets) may result in reduced fertility in females of reproductive potential. It is not known if this effect is reversible [see Nonclinical Toxicology (13.1)].
Severe Hepatic Impairment
XELJANZ (tablets and oral solution) and XELJANZ XR (extended-release tablets) has not been studied in patients with severe hepatic impairment (HI) (Child-Pugh C); therefore, use of XELJANZ/XELJANZ XR in patients with severe HI is not recommended.
Moderate Hepatic Impairment
XELJANZ-treated patients with moderate hepatic impairment (Child-Pugh B) had greater tofacitinib blood concentration than XELJANZ-treated patients with normal hepatic function [see Clinical Pharmacology (12.3)]. Higher blood concentrations may increase the risk of some adverse reactions. The recommended XELJANZ (tablets and oral solution) and XELJANZ XR (extended-release tablets) dosage in patients with moderate HI is lower than the recommended dosage in patients with normal hepatic function [see Dosage and Administration (2.3, 2.4, 2.5)].
Mild Hepatic Impairment
The recommended dosage of XELJANZ/XELJANZ XR in patients with mild hepatic impairment (Child-Pugh A) is the same as patients with normal hepatic function.
Hepatitis B or C Serology
The safety and efficacy of XELJANZ/XELJANZ XR have not been studied in patients with positive hepatitis B virus or hepatitis C virus serology.
Following oral administration of XELJANZ (tablets and oral solution), peak plasma concentrations were reached within 0.5 hour - 1 hour, elimination half-life was about 3 hours and a dose-proportional increase in systemic exposure was observed in the therapeutic dosage range. Steady state concentrations were achieved in 24-48 hours with negligible accumulation after twice daily administration.
Following oral administration of XELJANZ XR (extended-release tablets), peak plasma concentrations were reached at 4 hours and half-life was about 6 to 8 hours. Steady state concentrations were achieved within 48 hours with negligible accumulation after once daily administration.
Table 8 describes the pharmacokinetic parameters of XELJANZ and XELJANZ XR.
| PK Parameters Values represent the geometric mean, except Tmax, for which the median (range) is shown. (CV%) | XELJANZ | XELJANZ XR | ||
|---|---|---|---|---|
| Dosing Regimen | 5 mg Twice Daily | 10 mg Twice Daily | 11 mg Once Daily | 22 mg Once Daily |
| Abbreviations: AUC24 = area under the concentration time profile from time 0 to 24 hours; Cmax = maximum plasma concentration; Cmin = minimum plasma concentration; Tmax = time to Cmax; CV = Coefficient of variation. | ||||
AUC24 (ng.hr/mL) | 263.4 (15) | 539.6 (22) | 269.0 (18) | 596.6 (19) |
Cmax (ng/mL) | 42.7 (26) | 84.7 (18) | 38.2 (15) | 83.8 (25) |
Cmin (ng/mL) | 1.41 (40) | 3.10 (54) | 1.07 (69) | 3.11 (43) |
Tmax (hours) | 1.0 Values beyond 12 hours were after the evening dose which was administered 12 hours after the morning dose of twice-daily XELJANZ. ) | 0.8 | 4.0 | 4.0 |
Absorption
XELJANZ
The absolute oral bioavailability of XELJANZ is 74%. Coadministration of XELJANZ with a high-fat meal resulted in no changes in AUC while Cmax was reduced by 32%. In clinical trials, XELJANZ was administered without regard to meals [see Dosage and Administration (2.2)].
XELJANZ XR
Coadministration of XELJANZ XR 11 and 22 mg with a high-fat meal resulted in no changes in AUC while Cmax was increased by 27% and 19% respectively. Tmax was extended by approximately 1 hour for both XELJANZ XR 11 and 22 mg.
Distribution
After intravenous administration, the volume of distribution was 87 L. The protein binding of tofacitinib is approximately 40%. Tofacitinib binds predominantly to albumin and does not appear to bind to α1-acid glycoprotein. Tofacitinib distributes equally between red blood cells and plasma.
Metabolism and Excretion
Clearance mechanisms for tofacitinib are approximately 70% hepatic metabolism and 30% renal excretion of the parent drug. The metabolism of tofacitinib is primarily mediated by CYP3A4 with minor contribution from CYP2C19. In a human radiolabeled study, more than 65% of the total circulating radioactivity was accounted for by unchanged tofacitinib, with the remaining 35% attributed to 8 metabolites, each accounting for less than 8% of total radioactivity. The pharmacologic activity of tofacitinib is attributed to the parent molecule.
Pharmacokinetics in Patients with RA, PsA, AS, and UC
Population pharmacokinetic (PK) analyses indicated that PK characteristics were similar between patients with RA, PsA, ankylosing spondylitis, and UC. The coefficient of variation (%) in AUC of tofacitinib were generally similar across different disease patients, ranging from 22% to 34% (Table 9).
| Pharmacokinetic Parameters Pharmacokinetic parameters estimated based on population pharmacokinetic analysis. Geometric Mean(CV%) | XELJANZ 5 mg Twice Daily | XELJANZ 10 mg Twice Daily | |||
|---|---|---|---|---|---|
| Rheumatoid Arthritis | Psoriatic Arthritis | Ankylosing Spondylitis | Ulcerative Colitis | Ulcerative Colitis | |
| Abbreviations: AUC0–24,ss = area under the plasma concentration-time curve over 24 hours at steady state; CV = coefficient of variation. | |||||
AUC0–24,ss | 504 | 419 | 381 | 423 | 807 |
Specific Populations
Covariate evaluation as part of population PK analyses in adult patient populations indicated no clinically relevant change in tofacitinib exposure, after accounting for differences in renal function (i.e., creatinine clearance) between patients, based on age, weight, biological sex and race (Figure 1). An approximately linear relationship between body weight and volume of distribution was observed, resulting in higher peak (Cmax) and lower trough (Cmin) concentrations in lighter patients. However, this difference is not considered to be clinically relevant.
Covariate evaluation as part of population PK analyses in pediatric patients with pcJIA, including PsA, identified body weight significantly impacting tofacitinib exposure, which supports weight-based dosing in this population. There were no identified clinically significant differences in tofacitinib exposure with different age, biological sex, racial, or pcJIA or PsA disease severity groups.
The effect of renal and hepatic impairment and other intrinsic factors on the PK of tofacitinib is shown in Figure 1.
 Figure 1 (Xeljanz 02) |
Note: Reference values for weight, age, biological sex, and race comparisons are 70 kg, 55 years, male, and white, respectively; reference groups for renal and hepatic impairment data are patients with normal renal and hepatic function. Renal function was estimated using creatinine clearance by Cockcroft-Gault method and hepatic function was estimated using Child-Pugh scoring method.
In patients with end-stage renal disease maintained on hemodialysis, mean AUC was approximately 40% higher compared with historical healthy subject data, consistent with approximately 30% contribution of renal clearance to the total clearance of tofacitinib [see Dosage and Administration (2.3, 2.4, 2.5) and Use in Specific Populations (8.6)].
Drug Interaction Studies
Potential for XELJANZ/XELJANZ XR to Influence the PK of Other Drugs
In vitro studies indicate that tofacitinib does not significantly inhibit or induce the activity of the major human drug-metabolizing CYPs (CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP3A4) at concentrations corresponding to the steady state Cmax of a 10 mg twice daily dose. These in vitro results were confirmed by a human drug interaction study showing no changes in the pharmacokinetics of midazolam, a highly sensitive CYP3A4 substrate, when concomitantly administered with XELJANZ.
In vitro studies indicate that tofacitinib does not significantly inhibit the activity of the major human drug-metabolizing uridine 5'-diphospho-glucuronosyltransferases (UGTs) [UGT1A1, UGT1A4, UGT1A6, UGT1A9, and UGT2B7] at concentrations exceeding 250 times the steady state Cmax of a 10 mg twice daily dose.
In patients with RA, the oral clearance of tofacitinib does not vary with time, indicating that tofacitinib does not normalize CYP enzyme activity in patients with RA. Therefore, concomitant use with XELJANZ/XELJANZ XR is not expected to result in clinically relevant increases in the metabolism of CYP substrates in patients with RA.
In vitro data indicate that the potential for tofacitinib to inhibit transporters such as P-glycoprotein, organic anionic or cationic transporters at therapeutic concentrations is low.
The impact of tofacitinib on the PK of other drugs for the concomitant drugs are shown in Figure 2.
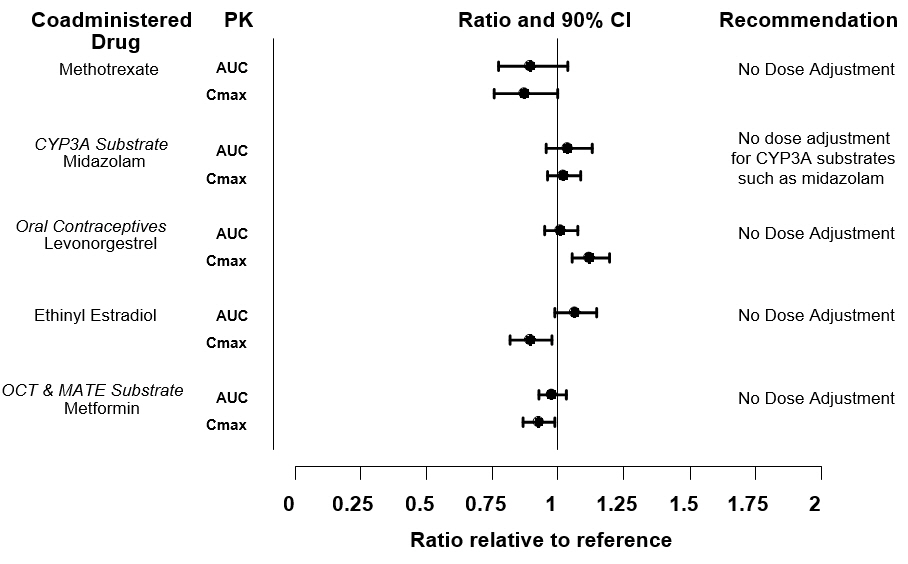 Figure 2 (Xeljanz 03) |
Note: Reference group is administration of concomitant medication alone; OCT = Organic Cationic Transporter; MATE = Multidrug and Toxic Compound Extrusion.
Potential for Other Drugs to Influence the Pharmacokinetics of Tofacitinib
Since tofacitinib is metabolized by CYP3A4, interaction with drugs that inhibit or induce CYP3A4 is likely. Inhibitors of CYP2C19 alone or P-glycoprotein are unlikely to substantially alter the pharmacokinetics of tofacitinib (see Figure 3).
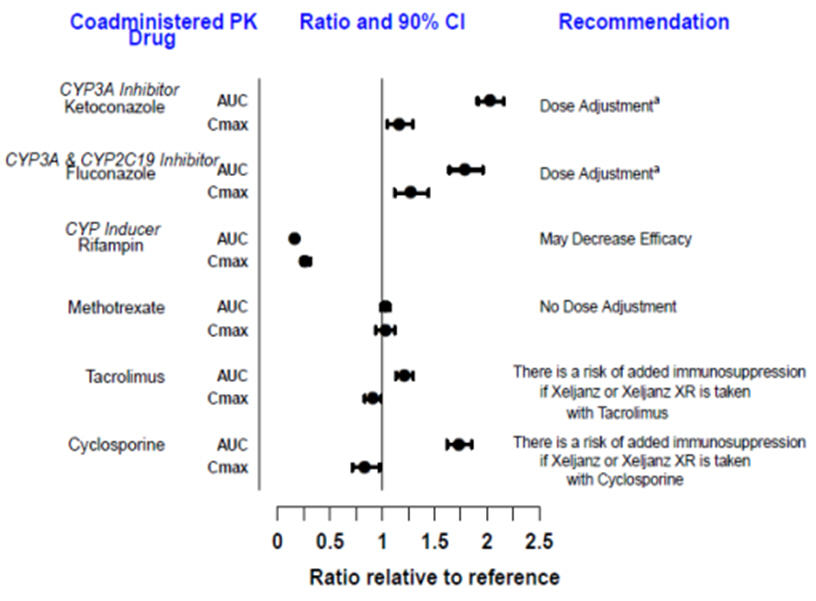 Figure 3 (Xeljanz 04) |
Note: Reference group is administration of XELJANZ alone.
Radiographic Response
Two studies were conducted to evaluate the effect of XELJANZ on structural joint damage. In Study RA-IV and Study RA-VI, progression of structural joint damage was assessed radiographically and expressed as change from baseline in mTSS and its components, the erosion score and joint space narrowing score, at Months 6 and 12. The proportion of patients with no radiographic progression (mTSS change less than or equal to 0) was also assessed.
In Study RA-IV, XELJANZ 5 mg twice daily reduced the mean progression of structural damage (not statistically significant) as shown in Table 13. Analyses of erosion and joint space narrowing scores were consistent with the overall results.
In the placebo plus MTX group, 74% of patients experienced no radiographic progression at Month 6 compared to 84% of patients treated with XELJANZ plus MTX 5 mg twice daily.
In Study RA-VI, XELJANZ monotherapy inhibited the progression of structural damage compared to MTX at Months 6 and 12 as shown in Table 13. Analyses of erosion and joint space narrowing scores were consistent with the overall results.
In the MTX group, 55% of patients experienced no radiographic progression at Month 6 compared to 73% of patients treated with XELJANZ 5 mg twice daily.
Study RA-IV | |||
Placebo SD = Standard Deviation | XELJANZ 5 mg Twice Daily | XELJANZ 5 mg Twice Daily Difference between least squares means XELJANZ minus placebo or MTX (95% CI = 95% confidence interval) (CI) | |
mTSS Month 6 and Month 12 data are mean change from baseline. | |||
Baseline | 33 (42) | 31 (48) | - |
Month 6 | 0.5 (2.0) | 0.1 (1.7) | -0.3 (-0.7, 0.0) |
Study RA-VI | |||
MTX | XELJANZ 5 mg Twice Daily | XELJANZ 5 mg Twice Daily | |
mTSS | |||
Baseline | 17 (29) | 20 (40) | - |
Month 6 | 0.8 (2.7) | 0.2 (2.3) | -0.7 (-1.0, -0.3) |
Month 12 | 1.3 (3.7) | 0.4 (3.0) | -0.9 (-1.4, -0.4) |
Physical Function Response
Improvement in physical functioning was measured by the HAQ-DI. Patients who received XELJANZ 5 mg twice daily demonstrated greater improvement from baseline in physical functioning compared to patients who received placebo at Month 3.
The mean (95% CI) difference from placebo in HAQ-DI improvement from baseline at Month 3 in Study RA-III was -0.22 (-0.35, -0.10) in patients who received 5 mg XELJANZ twice daily. Similar results were obtained in Studies RA-I, II, IV and V. In the 12-month trials, HAQ-DI results in XELJANZ-treated patients were consistent at 6 and 12 months.
Other Health-Related Outcomes
General health status was assessed by the Short Form health survey (SF-36). In Studies RA-I, IV, and V, patients who received XELJANZ 5 mg twice daily demonstrated greater improvement from baseline compared to placebo in physical component summary (PCS), mental component summary (MCS) scores and in all 8 domains of the SF-36 at Month 3.
Clinical Response
At Month 3, patients treated with XELJANZ 5 mg twice daily had higher (p≤0.05) response rates versus placebo for ACR20, ACR50, and ACR70 in Study PsA-I and for ACR20 and ACR50 in Study PsA-II; ACR70 response rates were also higher for XELJANZ 5 mg twice daily versus placebo in Study PsA-II, although the differences versus placebo were not statistically significant (p>0.05) (Tables 14 and 15).
| Treatment Group | Placebo | XELJANZ 5 mg Twice Daily + Background Nonbiologic DMARD | |
|---|---|---|---|
| Patients with missing data were treated as non-responders. | |||
N N is number of randomized and treated patients. | 105 | 107 | |
Response Rate | Response Rate | Difference (%) | |
Month 3 | |||
ACR20 | 33% | 50% | 17.1 (4.1, 30.2) |
ACR50 | 10% | 28% | 18.5 (8.3, 28.7) |
ACR70 | 5% | 17% | 12.1 (3.9, 20.2) |
| Treatment Group | Placebo | XELJANZ 5 mg Twice Daily | |
|---|---|---|---|
| Patients with missing data were treated as non-responders. | |||
N N is number of randomized and treated patients. | 131 | 131 | |
Response Rate | Response Rate | Difference (%) | |
Month 3 | |||
ACR20 | 24% | 50% | 26.0 (14.7, 37.2) |
ACR50 | 15% | 30% | 15.3 (5.4, 25.2) |
ACR70 | 10% | 17% | 6.9 (-1.3, 15.1) |
Improvements from baseline in the ACR response criteria components for both studies are shown in Table 16.
| Nonbiologic DMARD Inadequate Responders (TNF Blocker-Naïve) | TNF Blocker Inadequate Responders | |||
|---|---|---|---|---|
| Study PsA-I Patients received one concomitant nonbiologic DMARD. ,XELJANZ and XELJANZ XR are not approved for use in TNF blocker-naïve patients [see Indications and Usage (1.2)]. | Study PsA-II | |||
Treatment Group | Placebo | XELJANZ | Placebo | XELJANZ |
N at Baseline | 105 | 107 | 131 | 131 |
ACR Component Data shown are mean value at baseline and at Month 3. | ||||
Number of tender/painful joints (0–68) | ||||
Baseline | 20.6 | 20.5 | 19.8 | 20.5 |
Month 3 | 14.6 | 12.2 | 15.1 | 11.5 |
Number of swollen joints (0–66) | ||||
Baseline | 11.5 | 12.9 | 10.5 | 12.1 |
Month 3 | 7.1 | 6.3 | 7.7 | 4.8 |
Patient assessment of arthritis pain Visual analog scale (VAS): 0 = best, 100 = worst. | ||||
Baseline | 53.2 | 55.7 | 54.9 | 56.4 |
Month 3 | 44.7 | 34.7 | 48.0 | 36.1 |
Patient global assessment of arthritis | ||||
Baseline | 53.9 | 54.7 | 55.8 | 57.4 |
Month 3 | 44.4 | 35.5 | 49.2 | 36.9 |
HAQ-DI HAQ-DI = Health Assessment Questionnaire – Disability Index: 0 = best, 3 = worst; 20 questions; categories: dressing and grooming, arising, eating, walking, hygiene, reach, grip, and activities. | ||||
Baseline | 1.11 | 1.16 | 1.25 | 1.26 |
Month 3 | 0.95 | 0.81 | 1.09 | 0.88 |
Physician's Global Assessment of Arthritis | ||||
Baseline | 53.8 | 54.6 | 53.7 | 53.5 |
Month 3 | 35.4 | 29.5 | 36.4 | 27.0 |
CRP (mg/L) | ||||
Baseline | 10.4 | 10.5 | 12.1 | 13.8 |
Month 3 | 8.6 | 4.0 | 11.4 | 7.7 |
The percentage of ACR20 responders by visit for Study PsA-I is shown in Figure 5. Similar responses were observed in Study PsA-II. In both studies, improvement in ACR20 response on XELJANZ was observed at the first visit after baseline (Week 2).
| BID = twice daily; SE = standard error. |
| Patients with missing data were treated as non-responders. |
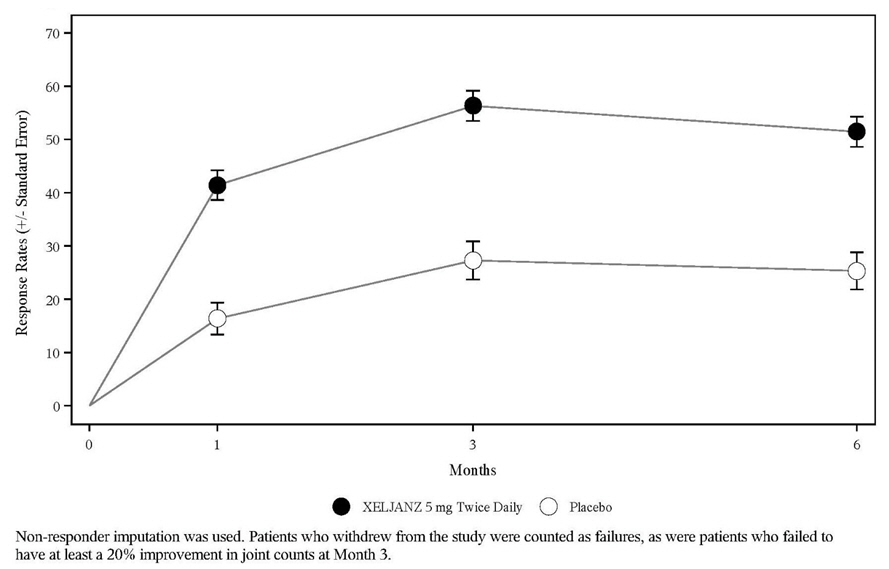 Figure 5 (Xeljanz 06) |
In patients with active PsA evidence of benefit in enthesitis and dactylitis was observed with XELJANZ treatment.
Physical Function
Improvement in physical functioning was measured by the HAQ-DI. Patients receiving XELJANZ 5 mg twice daily demonstrated significantly greater improvement (p ≤0.05) from baseline in physical functioning compared to placebo at Month 3 (Table 17).
| Least Squares Mean Change from Baseline In HAQ-DI at Month 3 | ||||
|---|---|---|---|---|
| Nonbiologic DMARD Inadequate Responders Inadequate response to at least one nonbiologic DMARD due to lack of efficacy and/or intolerability. (TNF Blocker-Naïve) | TNF Blocker Inadequate Responders Inadequate response to at least one TNF blocker due to lack of efficacy and/or intolerability. | |||
| Study PsA-I Patients received one concomitant nonbiologic DMARD. ,XELJANZ and XELJANZ XR are not approved for use in TNF blocker-naïve patients [see Indications and Usage (1.2)]. | Study PsA-II | |||
Treatment Group | Placebo | XELJANZ 5 mg | Placebo | XELJANZ 5 mg |
N N is the total number of patients in the statistical analysis. | 104 | 107 | 131 | 129 |
LSM Change from Baseline | -0.18 | -0.35 | -0.14 | -0.39 |
Difference from Placebo (95% CI) | - | -0.17 | - | -0.25 |
In Study PsA-I, the HAQ-DI responder rate (response defined as having improvement from baseline of ≥0.35) at Month 3 was 53% in patients receiving XELJANZ 5 mg twice daily and 31% in patients receiving placebo. Similar responses were observed in Study PsA-II.
Other Health-Related Outcomes
General health status was assessed by the Short Form health survey (SF-36). In Studies PsA-I and PsA-II, patients receiving XELJANZ 5 mg twice daily had greater improvement from baseline compared to placebo in Physical Component Summary (PCS) score, but not in Mental Component Summary (MCS) score at Month 3. Patients receiving XELJANZ 5 mg twice daily reported consistently greater improvement relative to placebo in the domains of Physical Functioning, Bodily Pain, Vitality, and Social Functioning, but not in Role-Physical, General Health, Role-Emotional, or Mental Health.
Radiographic Response
Treatment effect on inhibition of radiographic progression in PsA could not be established from the results of Study PsA-I.
Trial Design
Study AS-I was a randomized, double-blind, placebo-controlled, 48-week clinical trial in 269 adult patients who had an inadequate response (inadequate clinical response or intolerance) to at least 2 NSAIDs. Although Study AS-I included some patients who are TNF blocker-naïve, XELJANZ and XELJANZ XR are not approved for use in TNF blocker-naïve patients [see Indications and Usage (1.3)]. Patients were randomized and treated with XELJANZ 5 mg twice daily or placebo for 16 weeks of blinded treatment and then all received treatment of XELJANZ 5 mg twice daily for additional 32 weeks. The primary endpoint was to evaluate the proportion of patients who achieved an ASAS20 response at Week 16.
Approximately 7% and 21% of patients used concomitant methotrexate or sulfasalazine, respectively from baseline to Week 16. Twenty-two percent of patients had an inadequate response to 1 or 2 TNF blockers.
Clinical Response
Patients treated with XELJANZ 5 mg twice daily achieved greater improvements in ASAS20 and ASAS40 responses compared to patients treated with placebo at Week 16 (Table 18). Consistent results were observed in the subgroup of patients who had an inadequate response to TNF blockers for both the ASAS20 (primary endpoint) and ASAS40 (secondary endpoint) at Week 16 (Table 18).
| Placebo | XELJANZ 5 mg Twice Daily | Difference from Placebo (95% CI) | |
|---|---|---|---|
| Abbreviations: CI = confidence interval; TNFi-IR = tumor necrosis factor inhibitor inadequate response. | |||
All patients (N) | N=136 | N=133 | |
ASAS20 response type I error-controlled. , % | 29 | 56 | 27 (16, 38) p-value <0.0001. |
ASAS40 response | 13 | 41 | 28 (18, 38) |
TNFi-IR patients (N) | N=30 | N=29 | |
ASAS20 response, % | 17 | 41 | 25 (2, 47) |
ASAS40 response, % | 7 | 28 | 21 (2, 39) |
The improvements in the components of the ASAS response and other measures of disease activity were greater in the XELJANZ 5 mg twice daily group compared to the placebo group as shown in Table 19.
| Placebo (N=136) | XELJANZ 5 mg Twice Daily (N=133) | ||||
|---|---|---|---|---|---|
| Baseline (mean) | Week 16 (LSM change from Baseline) Estimates are generated based on a mixed model for repeated measures using both on-treatment and off-treatment data. | Baseline (mean) | Week 16 (LSM change from Baseline) | Difference from Placebo (95% CI) | |
| LSM = least squares mean. | |||||
ASAS Components | |||||
7.0 | -1.0 | 6.9 | -2.5 | -1.5 p <0.0001. | |
6.9 | -1.1 | 6.9 | -2.6 | -1.5 | |
5.9 | -0.8 | 5.8 | -2.0 | -1.2 | |
6.8 | -1.1 | 6.6 | -2.8 | -1.7 | |
BASDAI Score BASDAI total score. | 6.5 | -1.2 | 6.4 | -2.6 | -1.4 |
BASMI Bath Ankylosing Spondylitis Metrology Index. , | 4.4 | -0.1 | 4.5 | -0.6 | -0.5 |
hsCRP High sensitivity C-reactive protein. , | 1.8 | -0.1 | 1.6 | -1.1 | -0.9 |
The percentage of patients with active AS who achieved ASAS20 response by visit is shown in Figure 6.
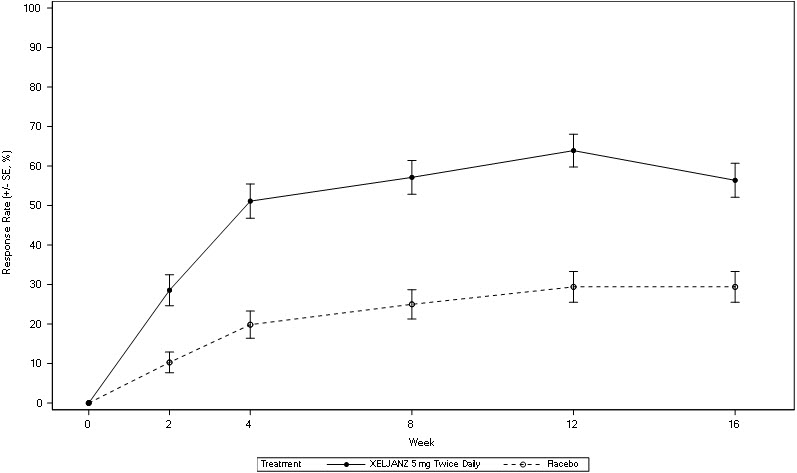 Figure 6 (Xeljanz 06a) |
SE = standard error.
Patients with missing data were treated as non-responders.
Other Health-Related Outcomes
Patients treated with XELJANZ 5 mg twice daily achieved greater improvements from baseline in Ankylosing Spondylitis Quality of Life (ASQoL) (-4.0 vs -2.0) compared to patients treated with placebo at Week 16.
The efficacy of XELJANZ tablets (referred to as “XELJANZ” in this subsection of labeling) was evaluated in two 12-week induction studies (UC-I and UC-II), a 52-week maintenance study (UC-III), and a long-term extension study (UC-IV).
Induction Trials (Study UC-I [NCT01465763] and Study UC-II [NCT01458951])
In two identical induction trials (UC-I and UC-II), 1139 adult patients were randomized (598 and 541 patients, respectively) to XELJANZ 10 mg twice daily or placebo with a 4:1 treatment allocation ratio. These trials included adult patients with moderately to severely active UC (total Mayo score of 6 to 12, with an endoscopy subscore of at least 2, and rectal bleeding subscore of at least 1) and who had failed or were intolerant to at least 1 of the following treatments: oral or intravenous corticosteroids, azathioprine, 6-MP or TNF blocker. XELJANZ and XELJANZ XR are indicated only for use in patients who have had inadequate response or intolerance to one or more TNF blockers [see Indications and Usage (1.5)].
The disease activity was assessed by Mayo scoring index (0 to 12) which consists of four subscores (0 to 3 for each subscore): stool frequency, rectal bleeding, findings on endoscopy, and physician global assessment. An endoscopy subscore of 2 was defined by marked erythema, absent vascular pattern, any friability, and erosions; an endoscopy subscore of 3 was defined by spontaneous bleeding and ulceration.
Patients were permitted to use stable doses of oral aminosalicylates and corticosteroids (prednisone daily dose up to 25 mg equivalent). Concomitant immunosuppressants (oral immunomodulators or biologic therapies) were not permitted for UC patients during these studies.
A total of 52%, 73% and 72% of patients had previously failed or were intolerant to TNF blockers (51% in Study UC-1 and 52% in Study UC-II), corticosteroids (75% in Study UC-I and 71% in Study UC-II), and/or immunosuppressants (74% in Study UC-I and 70% in Study UC-II), respectively.
Oral corticosteroids were received as concomitant treatment for UC by 47% of patients (45% in Study UC-I and 48% in Study UC-II) and 71% received concomitant aminosalicylates as treatment for UC (71% in Study UC-I, and 72% in Study UC-II). The baseline clinical characteristics were generally similar between the XELJANZ-treated patients and placebo-treated patients.
The primary endpoint of Study UC-I and Study UC-II was the proportion of patients in remission at Week 8, and the key secondary endpoint was the proportion of patients with improvement of endoscopic appearance of the mucosa at Week 8.
The efficacy results of Study UC-I and Study UC-II based on the centrally read endoscopy results are shown in Table 20.
| CI = Confidence interval; N = number of patients in the analysis set; TNF = tumor necrosis factor | |||
Study UC‑I | |||
Endpoint | Placebo | XELJANZ 10 mg Twice Daily | Treatment Difference versus Placebo (95% CI) |
Remission at Week 8 Remission was defined as clinical remission (a Mayo score ≤2 with no individual subscore >1) and rectal bleeding subscore of 0. | |||
Total Population | N=122 8% | N=476 18% | 10% p-value <0.01. (4.3, 16.3) |
With Prior TNF Blocker Failure Prior TNF blocker failure was defined in this program as inadequate response, loss of response, or intolerance to TNF blocker therapy. | N=64 2% | N=243 11% | |
Without Prior TNF Blocker Failure Patients in this group had failed one or more conventional therapies (corticosteroid, azathioprine, 6-mercaptopurine) but did not have history of prior failure of TNF blocker therapy. ,XELJANZ and XELJANZ XR are indicated only for use in patients who have had inadequate response or intolerance to one or more TNF blockers [see Indications and Usage (1.5)]. | N=58 16% | N=233 26% | |
Improvement of Endoscopic Appearance of the Mucosa at Week 8 Improvement of endoscopic appearance of the mucosa was defined as Mayo endoscopy subscore of 0 (normal or inactive disease) or 1 (erythema, decreased vascular pattern). | |||
Total Population | N=122 16% | N=476 31% | 16% p-value <0.001. (8.1, 23.4) |
With Prior TNF Blocker Failure | N=64 6% | N=243 23% | |
Without Prior TNF Blocker Failure | N=58 26% | N=233 40% | |
Study UC-II | |||
Endpoint | Placebo | XELJANZ 10 mg Twice Daily | Treatment Difference (95% CI) |
Remission at Week 8 | |||
Total Population | N=112 4% | N=429 17% | 13% (8.1, 17.9) |
With Prior TNF Blocker Failure | N=60 0% | N=222 12% | |
Without Prior TNF Blocker Failure | N=52 8% | N=207 22% | |
Improvement of Endoscopic Appearance of the Mucosa at Week 8 | |||
Total Population | N=112 12% | N=429 28% | 17% (9.5, 24.1) |
With Prior TNF Blocker Failure | N=60 7% | N=222 22% | |
Without Prior TNF Blocker Failure | N=52 17% | N=207 36% | |
Clinical Response at Week 8
Clinical response was defined as a decrease from baseline in Mayo score of ≥3 points and ≥30%, with an accompanying decrease in the subscore for rectal bleeding of ≥1 point or absolute subscore for rectal bleeding of 0 or 1.
Clinical response was observed in 60% of patients treated with XELJANZ 10 mg twice daily compared to 33% of patients treated with placebo in Study UC-I and 55% compared to 29% in Study UC-II.
Normalization of the Endoscopic Appearance of the Mucosa at Week 8
Normalization of endoscopic appearance of the mucosa was defined as a Mayo endoscopic subscore of 0 and was observed in 7% of patients treated with XELJANZ 10 mg twice daily compared to 2% of treated with placebo in both Studies UC-I and UC-II.
Rectal Bleeding and Stool Frequency
Decreases in rectal bleeding and stool frequency subscores were observed as early as Week 2 in patients treated with XELJANZ.
Maintenance Trial (Study UC-III [NCT01458574])
A total of 593 adult patients who completed the induction trials (UC-I or UC-II) and achieved clinical response were re-randomized with 1:1:1 treatment allocation ratio to XELJANZ 5 mg twice daily, XELJANZ 10 mg twice daily, or placebo for 52 weeks in Study UC-III. XELJANZ 5 mg twice daily is the recommended dosage for maintenance therapy; limit use of XELJANZ 10 mg twice daily beyond induction to those with loss of response and should be used for the shortest duration [see Dosage and Administration (2.5)]. As in the induction trials, patients were permitted to use stable doses of oral aminosalicylates; however, corticosteroid tapering was required upon entrance into this study for patients who were receiving corticosteroids at baseline. Concomitant immunosuppressants (oral immunomodulators or biologic therapies) were not permitted.
At baseline of Study UC-III:
In Study UC-III, the primary endpoint was the proportion of patients in remission at Week 52. There were two key secondary endpoints: the proportion of patients with improvement of endoscopic appearance at Week 52, and the proportion of patients with sustained corticosteroid-free remission at both Week 24 and Week 52 among patients in remission at baseline of Study UC-III.
The efficacy results of Study UC-III based on the centrally read endoscopy results are summarized in Table 21.
| Treatment Difference versus Placebo (95% CI) | |||||
|---|---|---|---|---|---|
| Endpoint | Placebo | XELJANZ 5 mg Twice Daily | XELJANZ 10 mg Twice Daily | XELJANZ 5 mg Twice Daily | XELJANZ 10 mg Twice Daily |
| CI = Confidence interval; N = number of patients in the analysis set; TNF = tumor necrosis factor. | |||||
Remission at Week 52 Remission was defined as clinical remission (a Mayo score ≤2 with no individual subscore >1) and rectal bleeding subscore of 0. | |||||
Total Population | N=198 | N=198 | N=197 | 23% p-value <0.0001. (15.3, 31.2) | 30% |
11% | 34% | 41% | |||
With Prior TNF Blocker Failure Prior TNF blocker failure was defined in this program as inadequate response, loss of response, or intolerance to TNF blocker therapy. | N=89 | N=83 | N=93 | ||
11% | 24% | 37% | |||
Without Prior TNF Blocker Failure Patients in this group had failed one or more conventional therapies (corticosteroid, azathioprine, 6-mercaptopurine) but did not have history of prior failure of TNF blocker therapy. XELJANZ and XELJANZ XR are indicated only for use in patients who have had inadequate response or intolerance to one or more TNF blockers [see Indications and Usage (1.5)]. | N=109 | N=115 | N=104 | ||
11% | 42% | 44% | |||
Improvement of endoscopic appearance of the mucosa at Week 52 Improvement of endoscopic appearance of the mucosa was defined as Mayo endoscopy subscore of 0 (normal or inactive disease) or 1 (erythema, decreased vascular pattern). | |||||
Total Population | N=198 | N=198 | N=197 | 24% | 33% |
13% | 37% | 46% | |||
With Prior TNF Blocker Failure | N=89 | N=83 | N=93 | ||
12% | 30% | 40% | |||
Without Prior TNF Blocker Failure | N=109 | N=115 | N=104 | ||
14% | 43% | 51% | |||
Sustained corticosteroid-free remission at both Week 24 and Week 52 among patients in remission at baseline Sustained corticosteroid-free remission was defined as being in remission and not taking corticosteroids for at least 4 weeks prior to the visit at both Week 24 and Week 52. | |||||
Total Population | N=59 | N=65 | N=55 | 30% | 42% |
5% | 35% | 47% | |||
With Prior TNF Blocker Failure | N=21 | N=18 | N=18 | ||
5% | 22% | 39% | |||
Without Prior TNF Blocker Failure | N=38 | N=47 | N=37 | ||
5% | 40% | 51% | |||
Maintenance of Clinical Response
Maintenance of clinical response was defined as the proportion of patients who met the definition of clinical response (defined as a decrease from the induction study (UC-I, UC-II) baseline Mayo score of ≥3 points and ≥30%, with an accompanying decrease in the rectal bleeding subscore of ≥1 point or rectal bleeding subscore of 0 or 1) at both Baseline and Week 52 of Study UC-III.
Maintenance of clinical response was observed in 20% in the placebo group, 52% in the XELJANZ 5 mg twice daily group, and 62% in the XELJANZ 10 mg twice daily group.
Maintenance of Remission (Among Patients in Remission at Baseline)
In the 179 patients who were in remission at baseline of Study UC-III (N = 59 for placebo, N = 65 for XELJANZ 5 mg twice daily, N = 55 for XELJANZ 10 mg twice daily), 10% in the placebo group, 46% in the XELJANZ 5 mg twice daily group and 56% in the XELJANZ 10 mg twice daily group maintained remission at Week 52.
Normalization of the Endoscopic Appearance of the Mucosa
Normalization of endoscopic appearance of the mucosa was defined as a Mayo endoscopic subscore of 0 and was observed at Week 52 in 15% of patients in the XELJANZ 5 mg twice daily group and 17% of patients in the XELJANZ 10 mg twice daily group compared to 4% of placebo patients.
Open-label Extension Study (Study UC-IV [NCT01470612])
In Study UC-IV, 914 patients were treated of which 156 received XELJANZ 5 mg twice daily and 758 received XELJANZ 10 mg twice daily.
Of the 905 patients who were assigned to XELJANZ 10 mg twice daily in the 8-week induction studies (Study UC-I or Study UC-II), 322 patients completed the induction studies but did not achieve clinical response. Of these 322 patients, 291 continued to receive XELJANZ 10 mg twice daily (unblinded) and had available data after an additional 8 weeks in Study UC-IV. After 8 additional weeks (a total of 16 weeks treatment), 148 patients achieved clinical response, and 25 patients achieved remission (based on central endoscopy read). Among those 143 patients who achieved clinical response by 16 weeks and had available data at Week 52, 66 patients achieved remission (based on local endoscopy read) after continued treatment with XELJANZ 10 mg twice daily for 52 weeks.
Serious Infections
Inform patients that XELJANZ (tablets and oral solution) and XELJANZ XR (extended-release tablets) may lower the ability of their immune system to fight infections. Advise patients not to start taking XELJANZ/XELJANZ XR if they have an active infection. Instruct patients to contact their healthcare provider immediately during treatment if symptoms suggesting infection appear to ensure rapid evaluation and appropriate treatment. Instruct patients to contact their healthcare provider immediately during treatment if they, their partner, or caregiver notice new onset or worsening of neurological symptoms including general muscle weakness, disturbance of vision, changes in thinking, memory and orientation leading to confusion and personality changes as these may be symptoms of a very rare, serious brain infection called progressive multifocal leukoencephalopathy (PML) [see Warnings and Precautions (5.1)].
Advise patients that the risk of herpes zoster, some cases of which can be serious, is increased in patients treated with XELJANZ/XELJANZ XR [see Warnings and Precautions (5.1)].
Malignancies and Lymphoproliferative Disorders
Inform patients that XELJANZ/XELJANZ XR may increase their risk of certain cancers, and that lymphoma and other cancers have been observed in patients taking XELJANZ. Instruct patients to inform their healthcare provider if they have ever had any type of cancer [see Warnings and Precautions (5.3)].
Major Adverse Cardiovascular Events
Inform patients that XELJANZ/XELJANZ XR may increase their risk of major adverse cardiovascular events (MACE) defined as myocardial infarction, stroke, and cardiovascular death. Instruct all patients, especially current or past smokers or patients with other cardiovascular risk factors, to be alert for the development of signs and symptoms of cardiovascular events [see Warnings and Precautions (5.4)].
Thrombosis
Advise patients to stop taking XELJANZ/XELJANZ XR and to call their healthcare provider right away if they experience any symptoms of thrombosis (sudden shortness of breath, chest pain worsened with breathing, swelling of leg or arm, leg pain or tenderness, red or discolored skin in the affected leg or arm) [see Warnings and Precautions (5.5)].
Hypersensitivity
Advise patients to stop taking XELJANZ/XELJANZ XR and to call their healthcare provider right away if they experience any symptoms of allergic reactions while taking XELJANZ/XELJANZ XR [see Warnings and Precautions (5.7)].
Hypoglycemia in Patients with Diabetes
Consider advising patients with diabetes to increase monitoring of blood glucose since hypoglycemia, including severe hypoglycemia, has been reported after starting XELJANZ/XELJANZ XR. Advise patients with diabetes to notify their healthcare provider if they develop signs or symptoms of hypoglycemia [see Warnings and Precautions (5.8)].
Important Information on Laboratory Abnormalities
Inform patients that XELJANZ/XELJANZ XR may affect certain lab test results, and that blood tests are required before and during XELJANZ/XELJANZ XR treatment [see Warnings and Precautions (5.9)].
Pregnancy
Advise pregnant females and females of reproductive potential of the potential risk to a fetus. Advise females to inform their prescriber of a known or suspected pregnancy [see Use in Specific Populations (8.1)].
Lactation
Advise women not to breastfeed during treatment with XELJANZ/XELJANZ XR and for at least 18 hours after the last dose of XELJANZ or 36 hours after the last dose of XELJANZ XR [see Use in Specific Populations (8.2)].
Infertility
Advise females of reproductive potential that XELJANZ/XELJANZ XR may impair fertility [see Use in Specific Populations (8.3), Nonclinical Toxicology (13.1)]. It is not known if this effect is reversible.
Residual Tablet Shell
Patients receiving XELJANZ XR may notice an inert tablet shell passing in the stool or via colostomy. Patients should be informed that the active medication has already been absorbed by the time the patient sees the inert tablet shell.

Logo (Xeljanz 08)
This product’s labeling may have been updated. For the most recent prescribing information, please visit www.pfizer.com.
LAB-0445-32.0