For example, an 80 kg patient with a baseline of INR of 5.0, the dose would be 2,800 Factor IX units of KCENTRA, calculated as follows based on INR range of 4–6, see Table 1:
35 units of Factor IX/kg × 80 kg = 2,800 units of Factor IX required
For a vial with an actual potency of 30 units/mL Factor IX, 93 mL would be given (2,800 U/30 U per mL = 93 mL).
Monitor INR and clinical response during and after treatment. In clinical trials, KCENTRA decreased the INR to ≤ 1.3 within 30 minutes in most subjects. The relationship between this or other INR values and clinical hemostasis in patients has not been established [see Clinical Studies (14)].
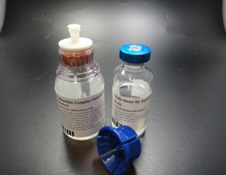
- Ensure that the KCENTRA vial and diluent vial are at room temperature.
- Remove flip caps from the KCENTRA and diluent vials.
- Wipe the stoppers with the alcohol swab provided and allow to dry prior to opening the Mix2Vial package.
- Open the Mix2Vial package by peeling off the lid (Fig. 1). Do not remove the Mix2Vial from the blister package.
Fig. 1 - Place the diluent vial on an even, clean surface and hold the vial tight. Take the Mix2Vial together with the blister package and push the spike of the blue adapter end straight down through the diluent vial stopper (Fig. 2).
Fig. 2 - Carefully remove the blister package from the Mix2Vial set by holding at the rim, and pulling vertically upwards. Make sure that you only pull away the blister package and not the Mix2Vial set (Fig. 3).
Fig. 3 - Place the KCENTRA vial on an even and firm surface. Invert the diluent vial with the Mix2Vial set attached and push the spike of the transparent adapter end straight down through the KCENTRA vial stopper (Fig. 4). The diluent will automatically flow into the KCENTRA vial.
Fig. 4
Note: If the vacuum in the KCENTRA vial is accidentally lost during reconstitution with the Mix2Vial device, the transfer with the Mix2Vial will not work.
In this case, separate the set into two pieces as illustrated in Fig. 6 below; do not discard the diluent vial. Place the KCENTRA vial aside on a flat surface. Remove the blue adapter end from the diluent vial of the Mix2Vial set (Fig. 5) by lifting and bending the blue adapter to the side until it disconnects from the diluent vial.
For reconstitution:- Using a separate sterile needle and syringe, withdraw the remaining diluent. Remove the needle from the syringe.
- Attach the syringe to the transparent adapter of the KCENTRA vial as illustrated in Fig. 8 below, and transfer the entire diluent volume into the KCENTRA vial. Remove syringe.
- Gently swirl the KCENTRA vial to ensure the product is fully dissolved. Do not shake.
- Proceed to step 10.
Fig. 5
- With one hand, grasp the KCENTRA-side of the Mix2Vial set and with the other hand grasp the diluent-side and unscrew the set carefully counterclockwise into two pieces (Fig. 6). Discard the diluent vial with the blue Mix2Vial adapter attached.
Fig. 6 - Gently swirl the KCENTRA vial with the transparent adapter attached until the substance is fully dissolved (Fig. 7). Do not shake.
Fig. 7 - Draw air into an empty, sterile syringe. While the KCENTRA vial is upright, connect the syringe to the Mix2Vial's Luer Lock fitting by screwing clockwise. Inject air into the KCENTRA vial (Fig. 8).
Fig. 8 - While keeping the syringe plunger pressed, turn the system upside down and draw the solution into the syringe by pulling the plunger back slowly (Fig. 9).
Fig. 9 - Now that the solution has been transferred into the syringe, firmly hold on to the barrel of the syringe (keeping the syringe plunger facing down) and disconnect the transparent Mix2Vial adapter from the syringe by unscrewing counterclockwise (Fig. 10). Attach the syringe to a suitable intravenous administration set.
Fig. 10 - After reconstitution, administration should begin promptly or within 4 hours.
- If the same patient is to receive more than one vial, you may pool the contents of multiple vials. Use a separate unused Mix2Vial transfer set for each product vial.
Randomized, Plasma-Controlled Trial in Acute Major Bleeding
In a prospective, randomized, open-label, active-controlled multicenter non-inferiority trial, 212 subjects who required urgent reversal of VKA therapy due to acute major bleeding were enrolled and randomized to treatment; 103 were treated with KCENTRA and 109 with plasma. Subjects with a history of a thrombotic event, myocardial infarction, cerebral vascular accident, transient ischemic attack, unstable angina pectoris, severe peripheral vascular disease, or disseminated intravascular coagulation, within the previous 3 months were excluded from participating. Subjects ranged in age from 26 years to 96 years.
Randomized, Plasma-Controlled Trial in Urgent Surgery/Invasive Procedures
In a prospective, randomized, open-label, active-controlled, multicenter non-inferiority trial, 176 subjects who required urgent reversal of VKA therapy due to the need for an urgent surgical or urgent invasive procedure were enrolled; 88 were treated with KCENTRA and 88 with plasma. Subjects ranged in age from 27 years to 94 years.
Adverse reactions are summarized for KCENTRA and plasma in the Acute Major Bleeding and Urgent Surgery/Invasive Procedures RCTs (see Table 2).
Adverse Reactions are defined as adverse events that began during or within 72 hours of test product infusion plus adverse events considered possibly/probably related or related to study treatment according to the investigator, sponsor, or the blinded safety adjudication board (SAB), and with at least a 1.3‐fold difference between treatments.
Table 2: Adverse Reactions Reported in more than 5 Subjects (≥2.8%) Following KCENTRA or Plasma Administration in RCTs | No. (%) of subjects |
|---|
KCENTRA
(N = 191) | Plasma
(N = 197) |
|---|
| Nervous system disorders | | |
| Headache | 14 (7.3%) | 7 (3.6%) |
| Respiratory, thoracic, and mediastinal disorders | | |
| Pleural effusion | 8 (4.2%) | 3 (1.5%) |
| Respiratory distress/dyspnea/hypoxia | 7 (3.7%) | 10 (5.1%) |
| Pulmonary edema | 3 (1.6%) | 10 (5.1%) |
| Gastrointestinal disorders | | |
| Nausea/vomiting | 12 (6.3%) | 8 (4.1%) |
| Diarrhea | 4 (2.1%) | 7 (3.6%) |
| Cardiac disorders | | |
| Tachycardia | 9 (4.7%) | 2 (1.0%) |
| Atrial fibrillation | 8 (4.2%) | 6 (3.0%) |
| Metabolism and nutrition disorders | | |
| Fluid overload Includes fluid overload and cardiac failure congestive | 5 (2.6%) | 16 (8.1%) |
| Hypokalemia | 9 (4.7%) | 14 (7.1%) |
| Psychiatric disorders | | |
| Insomnia | 9 (4.7%) | 6 (3.0%) |
| Vascular disorders | | |
| Hypotension Includes orthostatic hypotension, hypotension, and hemorrhagic shock | 14 (7.3%) | 10 (5.1%) |
| Injury, poisoning, and procedural complications | | |
| Skin laceration/contusion/subcutaneous hematoma | 8 (4.2%) | 5 (2.5%) |
| Blood and lymphatic disorders | | |
| Anemia Includes anemia, hemoglobin decreased, and hematocrit decreased | 11 (5.8%) | 16 (8.1%) |
Serious adverse reactions in subjects receiving KCENTRA in both RCTs included ischemic cerebrovascular accident (stroke), DVT, thrombosis, and venous insufficiency. Serious adverse reactions in both RCTs for plasma included myocardial ischemia, myocardial infarction, fluid overload, embolic cerebral infarction, pulmonary edema, respiratory failure, and DVT.
There were a total of 10 subjects (9.7%) who died in the KCENTRA group (1 additional death occurred on day 46 just after completion of the study reporting period) and 5 (4.6%) who died in the plasma group in the plasma-controlled RCT in acute major bleeding. The 95% confidence interval for the KCENTRA minus plasma between-group difference in deaths ranged from -2.7% to 13.5%. From the plasma-controlled RCT in urgent surgery/invasive procedures, there were a total of 3 subjects (3.4%) who died in the KCENTRA group (1 additional death occurred on day 48 after completion of the study reporting period) and 8 (9.1%) who died in the plasma group. The 95% confidence interval for the KCENTRA minus plasma between-group difference in deaths in this trial ranged from -14.6% to 2.7%. One death in the KCENTRA group in the RCT in Acute Major Bleeding and one death in the plasma group in the RCT in urgent surgery/invasive procedures were considered possibly related to study treatment according to an assessment of masked data by an independent safety adjudication board. No factors common to all deaths were identified, except for the frequent findings of a high comorbidity burden, advanced age, and death after being placed on comfort care. Although, a greater proportion of subjects in the RCT in acute major bleeding than in the RCT in surgery/invasive procedure received the highest two recommended doses of KCENTRA because more subjects in the trial in acute major bleeding had a baseline INR in the ranges of 4–6 and > 6.0, an analysis of deaths and factor levels in subjects with major bleeding revealed that subjects who died had similar median factor levels to subjects that did not die. Additionally, outliers with supraphysiologic factor levels did not have a mortality rate out of proportion to the overall population.
Fluid Overload
There were 9 subjects (4.7%, all non-related by investigator assessment) in the KCENTRA group who experienced fluid overload in the plasma-controlled RCTs in acute major bleeding and urgent surgery/invasive procedures and 25 (12.7%, 13 events related by investigator assessment) who had fluid overload in the plasma group. The 95% confidence interval for the KCENTRA minus Plasma between-group difference in fluid overload event incidence ranged from -14.1% to -2.0%.
Subgroup analyses of the RCTs in acute major bleeding and urgent surgery/invasive procedures according to whether subjects with fluid overload events had a prior history of congestive heart failure are presented in Table 3.
Table 3: Subjects with Fluid Overload Events by Prior History of Congestive Heart Failure in RCTs| Subgroup | Acute Major Bleeding Study | Urgent Surgery/Invasive Procedures Study |
|---|
| KCENTRA | Plasma | KCENTRA | Plasma |
|---|
| N | Fluid Overload
N (%) | N | Fluid Overload
N (%) | N | Fluid Overload
N (%) | N | Fluid Overload
N (%) |
|---|
| All subjects | 103 | 6 (5.8) | 109 | 14 (12.8) | 88 | 3 (3.4) | 88 | 11 (12.5) |
| With history of CHF | 46 | 4 (8.7) | 44 | 11 (25.0) | 24 | 1 (4.2) | 36 | 6 (16.7) |
| Without history of CHF | 57 | 2 (3.5) | 65 | 3 (4.6) | 64 | 2 (3.1) | 52 | 5 (9.6) |
Thromboembolic Events
In RCTs, there were 13 subjects (6.8%) in the KCENTRA group who experienced possible thromboembolic events (TEEs) and 14 (7.1%) who had TEEs in the plasma group. The incidence of thromboembolic (TE) adverse reactions assessed as at least possibly related to study treatment by the Investigator or, in the case of serious thromboembolic events, the blinded safety adjudication board (SAB) was 9 (4.7%) in the KCENTRA group and 7 (3.6%) in the plasma group. When also considering the events which began during or within 72 hours of test product infusion, the incidence was 9 (4.7%) in the KCENTRA group and 8 (4.1%) in the plasma group.
TE events observed in the acute major bleeding and the urgent surgery/invasive procedures RCTs are shown in Table 4.
Table 4: Adverse Reactions (TEEs only) Following KCENTRA or Plasma Administration in RCTs | No. (%) of subjects |
|---|
| System Organ Class | Acute Major Bleeding Study | Urgent Surgery/Invasive Procedures Study |
|---|
| KCENTRA
(N = 103) | Plasma
(N = 109) | KCENTRA
(N = 88) | Plasma
(N = 88) |
|---|
| Any possible TEE The tabulation of possible TEEs includes subjects with confirmed TEEs as well as 3 subjects in the Acute Major Bleeding RCT KCENTRA group that died of unknown causes on days 7, 31, and 38 and 1 subject in the Urgent Surgery/Invasive Procedures RCT plasma group that died of unknown causes on day 18. The death on day 7 was considered possibly related to study product by the SAB and is tabulated as an adverse reaction. | 9 (8.7%) | 6 (5.5%) | 4 (4.5) | 8 (9.1) |
| TEE Adverse reactions | 6 (5.5%) | 4 (3.7%) | 4 (4.5) | 4 (4.5) |
| Cardiac disorders |
| Myocardial infarction | 0 | 1 (0.9%) | 0 | 2 (2.3) |
| Myocardial ischemia | 0 | 2 (1.8%) | 0 | 0 |
| Nervous system disorders |
| Ischemic cerebrovascular accident (stroke) | 2 (1.9%) | 0 | 1 (1.1) | 0 |
| Embolic cerebral infarction | 0 | 0 | 0 | 1 (1.1) |
| Cerebrovascular disorder | 0 | 1 (0.9%) | 0 | 0 |
| Vascular disorders |
| Venous thrombosis calf | 1 (1.0%) | 0 | 0 | 0 |
| Venous thrombosis radial vein | 0 | 0 | 1 (1.1) | 0 |
| Thrombosis (microthrombosis of toes) | 0 | 0 | 1 (1.1) | 0 |
| Deep vein thrombosis (DVT) | 1 (1.0%) | 0 | 1 (1.1) | 1 (1.1) |
| Fistula Clot | 1 (1.0%) | 0 | 0 | 0 |
| Unknown Cause of Death (not confirmed TEE) |
| Sudden death | 1 (1.0%) | 0 | 0 | 0 |
Subgroup analyses of the RCTs according to whether subjects with thromboembolic events had a prior history of a thromboembolic event are presented in Table 5.
Table 5: Subjects with Thromboembolic Events by Prior History of TE Event in RCTs | Acute Major Bleeding Study | Urgent Surgery/Invasive Procedures Study |
|---|
| KCENTRA | Plasma | KCENTRA | Plasma |
|---|
| N | TE Events
N (%) | N | TE Events
N (%) | N | TE Events
N (%) | N | TE Events
N (%) |
|---|
| All subjects | 103 | 9 (8.7) | 109 | 6 (5.5) | 88 | 4 (4.5) | 88 | 8 (9.1) |
| With history of TE event History of prior TE event greater than 3 months from study entry (TE event within 3 months not studied). | 69 | 8 (11.6) | 79 | 3 (3.8) | 55 | 3 (5.5) | 62 | 5 (8.1) |
| Without history of TE event | 34 | 1 (2.9) | 30 | 3 (10.0) | 33 | 1 (3.0) | 26 | 3 (11.5) |
The European Bleeding and Surgical Study
In a prospective, open label, single-arm, multicenter safety and efficacy trial, 17 subjects who required urgent reversal of VKA due to acute bleeding were enrolled and 26 subjects who required urgent reversal of Vitamin K antagonist due to the need for an urgent surgical/invasive procedure were enrolled, all were treated with KCENTRA. Subjects ranged in age from 22 years to 85 years. Serious adverse reactions considered possibly related to KCENTRA included a suspected pulmonary embolism which occurred in one subject following a second dose of KCENTRA. A single non-fatal TE event occurred in another KCENTRA-treated subject in that trial.
Risk Summary
There are no data with KCENTRA use in pregnancy to inform on drug-associated risk. Animal reproduction studies have not been conducted with KCENTRA. It is not known whether KCENTRA can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. KCENTRA should be prescribed for a pregnant woman only if clearly needed.
In the U.S. general population, the estimated background risk of major birth defect and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Risk Summary
There is no information regarding the excretion of KCENTRA in human milk, the effect on the breastfed infant, or the effects on milk production. Because many drugs are excreted in human milk, use KCENTRA only if clearly needed when treating a nursing woman.
Coagulation Factor II
Factor II (prothrombin) is converted to thrombin by activated FX (FXa) in the presence of Ca2+, FV, and phospholipids.
Coagulation Factor VII
Factor VII (proconvertin) is converted to the activated form (FVIIa) by splitting of an internal peptide link. The FVIIa-TF complex activates Factor IX and initiates the primary coagulation pathway by activating FX in the presence of phospholipids and calcium ions.
Coagulation Factor IX
Factor IX (antihemophilic globulin B, or Christmas factor) is activated by the FVIIa-TF complex and by FXIa. Factor IXa in the presence of FVIIIa activates FX to FXa.
Coagulation Factor X
Factor X (Stuart-Prower factor) activation involves the cleavage of a peptide bond by the FVIIIa-Factor IXa complex or the TF-FVIIa complex. Factor Xa forms a complex with activated FV (FVa) that converts prothrombin to thrombin in the presence of phospholipids and calcium ions.
Protein C
Protein C, when activated by thrombin, exerts an antithrombotic effect by inhibiting FVa and FVIIIa leading to a decrease in thrombin formation, and has indirect profibrinolytic activity by inhibiting plasminogen activator inhibitor-1.
Protein S
Protein S exists in a free form (40%) and in a complex with C4b-binding protein (60%). Protein S (free form) functions as a cofactor for activated Protein C in the inactivation of FVa and FVIIIa, leading to antithrombotic activity.
International Normalized Ratio (INR)
In the plasma-controlled RCT in acute major bleeding, the INR was determined at varying time points after the start or end of infusion, depending upon study design. The median INR was above 3.0 prior to the infusion and dropped to a median value of 1.20 by the 30 minute time point after start of KCENTRA infusion. By contrast, the median value for plasma was 2.4 at 30 minutes after the start of infusion. The INR differences between KCENTRA and plasma were statistically significant in randomized plasma-controlled trial in bleeding up to 12 hours after start of infusion [see Table 8].
The relationship between these or other INR values and clinical hemostasis in patients has not been established [see Clinical Studies (14)].
Table 8: Median INR (Min-Max) after Start of Infusion in RCTs| Study | Treatment | Baseline | 30 min | 1 hr | 2-3 hr | 6-8 hr | 12 hr | 24 hr |
|---|
| INR = international normalized ratio; NC = not collected. |
| Acute Major Bleeding Study | KCENTRA
(N = 98) | 3.90
(1.8–20.0) | 1.20
(0.9–6.7) | 1.30
(0.9–5.4) | 1.30
(0.9–2.5) | 1.30
(0.9–2.1) | 1.20
(0.9–2.2) | 1.20
(0.9–3.8) |
Plasma
(N = 104) | 3.60
(1.9–38.9) | 2.4
(1.4–11.4) | 2.1
(1.0–11.4) | 1.7
(1.1–4.1) | 1.5
(1.0–3.0) | 1.4
(1.0–3.0) | 1.3
(1.0–2.9) |
| Urgent Surgery/ Invasive Procedures Study | KCENTRA
(N = 87) | 2.90
(2.0–17.0) | 1.30
(0.9–7.0) | 1.20
(0.9–2.5) | 1.30
(0.9–39.2) | 1.30
(1.0–10.3) | NC | 1.20
(0.9–2.7) |
Plasma
(N = 81) | 2.90
(2.0–26.7) | 2.15
(1.4–5.4) | 1.90
(1.3–5.7) | 1.70
(1.1–3.7) | 1.60
(1.0–5.8) | NC | 1.30
(1.0–2.7) |
Acute Major Bleeding RCT
The efficacy of KCENTRA has been evaluated in a prospective, open-label, (blinded assessor), active-controlled, non-inferiority, multicenter RCT in subjects who had been treated with VKA therapy and who required urgent replacement of their Vitamin K-dependent clotting factors to treat acute major bleeding. A total of 216 subjects with acquired coagulation factor deficiency due to oral Vitamin K antagonist therapy were randomized to a single dose of KCENTRA or plasma. Two hundred twelve (212) subjects received KCENTRA or plasma for acute major bleeding in the setting of a baseline INR ≥ 2.0 and recent use of a VKA anticoagulant. The doses of KCENTRA (25 units/kg, 35 units/kg, or 50 units/kg) based on nominal Factor IX content and plasma (10 mL/kg, 12 mL/kg, or 15 mL/kg) were calculated according to the subject's baseline INR (2–< 4, 4–6, > 6, respectively). The observation period lasted for 90 days after the infusion of KCENTRA or plasma. The modified efficacy (ITT-E) population for KCENTRA included 98 subjects and for plasma included 104 subjects. Additionally, intravenous Vitamin K was administered.
The efficacy endpoint was hemostatic efficacy for the time period from the start of infusion of KCENTRA or plasma until 24 hours. Efficacy was adjudicated as "effective" or "not effective" by a blinded, independent Endpoint Adjudication Board for all subjects who received study product. Criteria for effective hemostasis were based upon standard clinical assessments including vital signs, hemoglobin measurements, and CT assessments at pre-defined time points, as relevant to the type of bleeding (i.e., gastrointestinal, intracranial hemorrhage, visible, musculoskeletal, etc.). The proportion of subjects with effective hemostasis was 72.4% in the KCENTRA group and 65.4% in the plasma group. The lower limit of the 95% confidence interval (CI) for the difference in proportions of KCENTRA minus plasma was -5.8%, which exceeded -10% and thereby demonstrated the non-inferiority of KCENTRA versus plasma (the study's primary objective) [see Table 11]. Because the lower limit of the CI was not greater than zero, the prospectively defined criterion for superiority of KCENTRA for hemostatic efficacy (a secondary objective) was not met.
Table 11: Rating of Hemostatic Efficacy in Subjects with Acute Major Bleeding| Rating | No. (%) of subjects [95% CI] | Difference KCENTRA – Plasma (%)
[95% CI]KCENTRA non-inferior to plasma if lower limit of 95% CI > –10%; KCENTRA superior to plasma if lower limit of 95% CI > 0. |
|---|
KCENTRA
(N = 98) | Plasma
(N = 104) |
|---|
| CI = confidence interval; N = number of subjects |
| "Effective" hemostasis | 71 (72.4%)
[62.3; 82.6] | 68 (65.4%)
[54.9; 75.8] | (7.1%)
[-5.8; 19.9] |
Results of a post-hoc analysis of hemostatic efficacy stratified by actual dose of KCENTRA or plasma administered in the acute major bleeding RCT are presented in Table 12.
Table 12: Rating of Hemostatic Efficacy Stratified by Actual Dose of KCENTRA or Plasma (Number and % of Subjects rated "Effective") in Acute Major Bleeding RCT | Low Dose | Mid Dose | High Dose |
|---|
| N = 49 (K) | N = 22 (K) | N = 26 (K) |
|---|
| N = 55 (P) | N = 18 (P) | N = 31 (P) |
|---|
| KCENTRA | 36 (74.5%) | 16 (72.7%) | 18 (69.2%) |
| Plasma | 38 (69.1%) | 11 (61.1%) | 19 (61.3%) |
| Difference KCENTRA minus Plasma | (4.4%) | (11.6%) | (7.9%) |
| 95% CI K–P | -13.2–21.9 | -17.4–40.6 | -17.0–32.9 |
An additional endpoint was the reduction of INR to ≤ 1.3 at 30 minutes after the end of infusion of KCENTRA or plasma for all subjects that received study product. The proportion of subjects with this decrease in INR was 62.2% in the KCENTRA group and 9.6% in the plasma group. The 95% confidence interval for the difference in proportions of KCENTRA minus plasma was 39.4% to 65.9%. The lower limit of the 95% CI of 39.4% demonstrated superiority of KCENTRA versus plasma for this endpoint [see Table 13].
Table 13: Decrease of INR (1.3 or Less at 30 Minutes after End of Infusion) in Acute Major Bleeding RCT| Rating | No. (%) of subjects [95% CI] | Difference KCENTRA – Plasma (%)
[95% CI]KCENTRA non-inferior to plasma if lower limit of 95% CI > –10%; KCENTRA superior to plasma if lower limit of 95% CI > 0. |
|---|
KCENTRA
(N = 98) | Plasma
(N = 104) |
|---|
| CI = confidence interval; INR = international normalized ratio; N = total subjects |
| Decrease of INR to ≤ 1.3 at 30 min | 61 (62.2%)
[52.6; 71.8] | 10 (9.6%)
[3.9; 15.3] | (52.6%)
[39.4; 65.9] |
Urgent Surgery/Invasive Procedure RCT
The efficacy of KCENTRA has been evaluated in a prospective, open-label, active-controlled, non-inferiority, multicenter RCT in subjects who had been treated with VKA therapy and who required urgent replacement of their Vitamin K-dependent clotting factors because of their need for an urgent surgery/invasive procedure. A total of 181 subjects with acquired coagulation factor deficiency due to oral Vitamin K antagonist therapy were randomized to a single dose of KCENTRA or plasma. One hundred seventy-six (176) subjects received KCENTRA or plasma because of their need for an urgent surgery/invasive procedure in the setting of a baseline INR ≥ 2.0 and recent use of a VKA anticoagulant. The doses of KCENTRA (25 units/kg, 35 units/kg, or 50 units/kg) based on nominal Factor IX content and plasma (10 mL/kg, 12 mL/kg, or 15 mL/kg) were calculated according to the subject's baseline INR (2–< 4, 4–6, > 6, respectively). The observation period lasted for 90 days after the infusion of KCENTRA or plasma. The modified efficacy (ITT-E) population for KCENTRA included 87 subjects and for plasma included 81 subjects. Additionally, oral or intravenous Vitamin K was administered.
The efficacy endpoint was hemostatic efficacy for the time period from the start of infusion of KCENTRA or plasma until the end of the urgent surgery/invasive procedure. Criteria for effective hemostasis were based upon the difference between predicted and actual blood losses, subjective hemostasis rating, and the need for additional blood products containing coagulation factors. The proportion of subjects with effective hemostasis was 89.7% in the KCENTRA group and 75.3% in the plasma group. The lower limit of the 95% confidence interval (CI) for the difference in proportions of KCENTRA minus plasma was 2.8%, which exceeded -10% and thereby demonstrated the non-inferiority of KCENTRA versus plasma (the study's primary objective) [see Table 14]. Because the lower limit of the CI was greater than 0, the prospectively defined criterion for superiority of KCENTRA for hemostatic efficacy (a secondary objective) was also met.
Table 14: Rating of Hemostatic Efficacy in Urgent Surgery/Invasive Procedure RCT| Rating | No. (%) of subjects [95% CI] | Difference KCENTRA – Plasma (%)
[95% CI]KCENTRA non-inferior to plasma if lower limit of 95% CI > –10%; KCENTRA superior to plasma if lower limit of 95% CI > 0. |
|---|
KCENTRA
(N = 87) | Plasma
(N = 81) |
|---|
| CI = confidence interval; N = number of subjects |
| "Effective" hemostasis | 78 (89.7%)
[83.3; 96.1] | 61 (75.3%)
[65.9; 84.7] | (14.3%)
[2.8; 25.8] |
Results of a post-hoc analysis of hemostatic efficacy stratified by actual dose of KCENTRA or plasma administered in the urgent surgery/invasive procedure RCT are presented in Table 15.
Table 15: Rating of Hemostatic Efficacy Stratified by Actual Dose of KCENTRA or Plasma (Number and % of Subjects rated "Effective") in Urgent Surgery/Invasive Procedure RCT | Low Dose | Mid Dose | High Dose |
|---|
| N = 69 (K) | N = 10 (K) | N = 8 (K) |
|---|
| N = 62 (P) | N = 10 (P) | N = 9 (P) |
|---|
| KCENTRA | 63 (91.3%) | 8 (80.0%) | 7 (87.5%) |
| Plasma | 48 (77.4%) | 7 (70.0%) | 6 (66.7%) |
| Difference KCENTRA minus Plasma | (13.9%) | (10.0%) | (20.8%) |
| 95% CI K–P | 1.4–26.6 | -26.5–43.5 | -19.8–53.7 |
An additional endpoint was the reduction of INR to ≤ 1.3 at 30 minutes after the end of infusion of KCENTRA or plasma for all subjects that received study product. The proportion of subjects with this decrease in INR was 55.2% in the KCENTRA group and 9.9% in the plasma group. The 95% confidence interval for the difference in proportions of KCENTRA minus plasma was 31.9% to 56.4%. The lower limit of the 95% CI of 31.9% demonstrated superiority of KCENTRA versus plasma for this endpoint [see Table 16]. The relationship between a decrease in INR to less than or equal to 1.3 and clinical hemostatic efficacy has not been established.
Table 16: Decrease of INR (1.3 or Less at 30 Minutes after End of Infusion) in Urgent Surgery/Invasive Procedure RCT| Rating | No. (%) of subjects [95% CI] | Difference KCENTRA – Plasma (%)
[95% CI]KCENTRA non-inferior to plasma if lower limit of 95% CI > -10%; KCENTRA superior to plasma if lower limit of 95% CI > 0. |
|---|
KCENTRA
(N = 87) | Plasma
(N = 81) |
|---|
| CI = confidence interval; INR = international normalized ratio; N = total subjects |
| Decrease of INR to ≤ 1.3 at 30 min | 48 (55.2%)
[44.7; 65.6] | 8 (9.9%)
[3.4; 16.4] | (45.3%)
[31.9; 56.4] |
The European Bleeding and Surgical Study was an open-label, single-arm, multicenter study.1 Forty-three (43) subjects who were receiving VKA were treated with KCENTRA, because they either (1) required a surgical or an invasive diagnostic intervention (26 subjects), or (2) experienced an acute bleeding event (17 subjects). The dose of KCENTRA (25 units/kg, 35 units/kg, or 50 units/kg) based on nominal Factor IX content was calculated according to the subject's baseline INR value (2–< 4, 4–6, > 6). The endpoint was the decrease of the INR to ≤ 1.3 within 30 minutes after end of KCENTRA infusion in subjects who received any portion of study product.
Of the 17 evaluable subjects receiving KCENTRA for acute bleeding, 16 subjects (94%) experienced a decrease in INR to ≤ 1.3 within 30 minutes after the end of the KCENTRA infusion.
In RCTs, levels of Coagulation Factors II, VII, IX, X, and Antithrombotic Proteins C and S were measured after the infusion of KCENTRA or plasma and the results were similar for subjects with acute major bleeding or subjects requiring an urgent surgery or invasive procedure. In the plasma-controlled RCT in acute major bleeding, the mean duration of KCENTRA infusion was 24 minutes (± 32 minutes) and the mean duration of infusion for plasma was 169 minutes (± 143 minutes). The mean infusion volume of KCENTRA was 105 mL ± 37 mL and the mean infusion volume of plasma was 865 mL ± 269 mL. In the plasma-controlled RCT for patients needing urgent surgery/invasive procedures, the mean duration of KCENTRA infusion was 21 minutes (± 14 minutes) and the mean duration of infusion for plasma was 141 minutes (± 113 minutes). The mean infusion volume of KCENTRA was 90 mL ± 32 mL and the mean infusion volume of plasma was 819 mL ± 231 mL.
The increase in mean factor levels over time following KCENTRA and plasma administration in the plasma-controlled RCT in acute major bleeding is shown in Figure 9 below (the mean factor levels over time following KCENTRA and plasma administration in the plasma-controlled RCT for patients needing urgent surgery/invasive procedures are not shown, but showed similar profiles). Levels of some factors continued to increase at later time points, consistent with the effect of concomitant Vitamin K treatment. Formal pharmacokinetic parameters were not derived because of the effect of Vitamin K on factor levels at time points required for pharmacokinetic profiling.
Figure 9: Mean Factor Levels (Factors II, VII, IX, X, Proteins C & S) over 24 hours in Acute Major Bleeding RCT
Time axis is scheduled measuring time: hours after start of infusion (P=pre-infusion)
Prior to Reconstitution
- KCENTRA is for single-dose only. Contains no preservatives.
- Store KCENTRA between 2–25°C (36–77°F), this includes room temperature, not to exceed 25°C (77°F). Do not freeze.
- KCENTRA is stable for 36 months from the date of manufacture, up to the expiration date on the carton and vial labels.
- Do not use KCENTRA beyond the expiration date on the vial label and carton.
- Store the vial in the original carton to protect it from light.
After Reconstitution
KCENTRA must be used within 4 hours following reconstitution. Reconstituted KCENTRA can be stored at 2–25°C. If cooled, the solution should be warmed to 20–25°C prior to administration. Do not freeze. Discard partially used vials.
Manufactured by:
CSL Behring GmbH
35041 Marburg Germany
US License No. 1765
Distributed by:
CSL Behring LLC
Kankakee, IL 60901 USA
Mix2Vial® is a registered trademark of West Pharma. Services IL, Ltd., a subsidiary of West Pharmaceuticals Services, Inc.