The safety of EXPAREL was evaluated in a multicenter, randomized, double-blind, active-controlled trial in 119 patients undergoing foot and ankle procedures (Study 9) [see Clinical Studies (14.3)]. Patients were administered a dose of either 266 mg EXPAREL, 266 mg EXPAREL admixed with 50 mg bupivacaine HCl, or 100 mg bupivacaine HCl. The following adverse reactions were observed following administration of EXPAREL or EXPAREL admixed with bupivacaine in Study 9 that either were not observed in Studies 4 and 5, or were observed at a higher frequency than was observed in Studies 4 and 5. These include:
- The most common adverse reactions (incidence greater than 10%) observed in Study 9 at higher frequencies than Studies 4 and 5: hypoesthesia (21% vs. 1% and 0%, respectively), paresthesia (10% vs. 1% and 0%, respectively).
- The common adverse reactions (incidence greater than or equal to 2% to less than 10%) observed in Study 9 but not in Studies 4 and 5: epistaxis, motor dysfunction, pain in extremity, skin abrasion, infusion site pain, muscular weakness.
Bupivacaine
Bupivacaine HCl administered together with EXPAREL may impact the pharmacokinetic and/or physicochemical properties of EXPAREL, and this effect is concentration dependent. Therefore, bupivacaine HCl and EXPAREL may be administered simultaneously in the same syringe, and bupivacaine HCl may be injected immediately before EXPAREL as long as the ratio of the milligram dose of bupivacaine HCl solution to EXPAREL does not exceed 1:2.
Non-Bupivacaine Local Anesthetics
EXPAREL should not be admixed with local anesthetics other than bupivacaine. Non-bupivacaine based local anesthetics, including lidocaine, may cause an immediate release of bupivacaine from EXPAREL if administered together locally. The administration of EXPAREL may follow the administration of lidocaine after a delay of 20 minutes or more. There are no data to support administration of other local anesthetics prior to administration of EXPAREL.
Other than bupivacaine as noted above, EXPAREL should not be admixed with other drugs prior to administration.
Water and Hypotonic Agents
Do not dilute EXPAREL with water or other hypotonic agents, as it will result in disruption of the liposomal particles.
Risk Summary
There are no studies conducted with EXPAREL in pregnant women. In animal reproduction studies, embryo-fetal deaths were observed with subcutaneous administration of bupivacaine to rabbits during organogenesis at a dose equivalent to 1.6 times the maximum recommended human dose (MRHD) of 266 mg. Subcutaneous administration of bupivacaine to rats from implantation through weaning produced decreased pup survival at a dose equivalent to 1.5 times the MRHD [see Data]. Based on animal data, advise pregnant women of the potential risks to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. However, the background risk in the U.S. general population of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies.
Clinical Considerations
Labor or Delivery
Bupivacaine is contraindicated for obstetrical paracervical block anesthesia. While EXPAREL has not been studied with this technique, the use of bupivacaine for obstetrical paracervical block anesthesia has resulted in fetal bradycardia and death.
Bupivacaine can rapidly cross the placenta, and when used for epidural, caudal, or pudendal block anesthesia, can cause varying degrees of maternal, fetal, and neonatal toxicity [See Clinical Pharmacology (12.3)]. The incidence and degree of toxicity depend upon the procedure performed, the type, and amount of drug used, and the technique of drug administration. Adverse reactions in the parturient, fetus, and neonate involve alterations of the central nervous system, peripheral vascular tone, and cardiac function.
Data
Animal Data
Bupivacaine hydrochloride was administered subcutaneously to rats and rabbits during the period of organogenesis (implantation to closure of the hard plate). Rat doses were 4.4, 13.3, and 40 mg/kg/day (equivalent to 0.2, 0.5 and 1.5 times the MRHD, respectively, based on the BSA comparisons and a 60 kg human weight) and rabbit doses were 1.3, 5.8, and 22.2 mg/kg/day (equivalent to 0.1, 0.4 and 1.6 times the MRHD, respectively, based on the BSA comparisons and a 60 kg human weight). No embryo-fetal effects were observed in rats at the doses tested with the high dose causing increased maternal lethality. An increase in embryo-fetal deaths was observed in rabbits at the high dose in the absence of maternal toxicity.
Decreased pup survival was noted at 1.5 times the MRHD in a rat pre- and post-natal development study when pregnant animals were administered subcutaneous doses of 4.4, 13.3, and 40 mg/kg/day bupivacaine hydrochloride (equivalent to 0.2, 0.5 and 1.5 times the MRHD, respectively, based on the BSA comparisons and a 60 kg human weight) from implantation through weaning (during pregnancy and lactation).
Risk Summary
Limited published literature reports that bupivacaine and its metabolite, pipecoloxylidide, are present in human milk at low levels. There is no available information on effects of the drug in the breastfed infant or effects of the drug on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for EXPAREL and any potential adverse effects on the breastfed infant from EXPAREL or from the underlying maternal condition.
Clinical Presentation
Acute emergencies from local anesthetics are generally related to high plasma concentrations encountered during therapeutic use of local anesthetics or to unintended intravascular injection of local anesthetic solution [See Warnings and Precautions (5) and Adverse Reactions (6)].
Signs and symptoms of overdose include CNS symptoms (perioral paresthesia, dizziness, dysarthria, confusion, mental obtundation, sensory and visual disturbances, and eventually convulsions) and cardiovascular effects (that range from hypertension and tachycardia to myocardial depression, hypotension, bradycardia, and asystole).
Plasma levels of bupivacaine associated with toxicity can vary. Although concentrations of 2,500 to 4,000 ng/mL have been reported to elicit early subjective CNS symptoms of bupivacaine toxicity, symptoms of toxicity have been reported at levels as low as 800 ng/mL.
Management of Local Anesthetic Overdose
At the first sign of change, oxygen should be administered.
The first step in the management of convulsions, as well as underventilation or apnea, consists of immediate attention to the maintenance of a patent airway and assisted or controlled ventilation with oxygen and a delivery system capable of permitting immediate positive airway pressure by mask. Immediately after the institution of these ventilatory measures, the adequacy of the circulation should be evaluated, keeping in mind that drugs used to treat convulsions sometimes depress the circulation when administered intravenously. Should convulsions persist despite adequate respiratory support, and if the status of the circulation permits, small increments of an ultra-short acting barbiturate (such as thiopental or thiamylal) or a benzodiazepine (such as diazepam) may be administered intravenously. The clinician should be familiar, prior to the use of anesthetics, with these anticonvulsant drugs. Supportive treatment of circulatory depression may require administration of intravenous fluids and, when appropriate, a vasopressor dictated by the clinical situation (such as ephedrine to enhance myocardial contractile force).
If not treated immediately, both convulsions and cardiovascular depression can result in hypoxia, acidosis, bradycardia, arrhythmias, and cardiac arrest. If cardiac arrest should occur, standard cardiopulmonary resuscitative measures should be instituted.
Endotracheal intubation, employing drugs and techniques familiar to the clinician, may be indicated, after initial administration of oxygen by mask, if difficulty is encountered in the maintenance of a patent airway or if prolonged ventilatory support (assisted or controlled) is indicated.
Active Ingredient
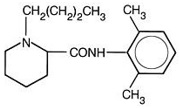
Bupivacaine is related chemically and pharmacologically to the amide-type local anesthetics. It is a homologue of mepivacaine and is related chemically to lidocaine. All three of these anesthetics contain an amide linkage between the aromatic nucleus and the amino, or piperidine group. They differ in this respect from the procaine-type local anesthetics, which have an ester linkage. Chemically, bupivacaine is 1-butyl-N-(2,6-dimethylphenyl)-2-piperidinecarboxamide with a molecular weight of 288.4. Bupivacaine has the following structural formula:

Chemical Structure (Exparel 01)
EXPAREL
The median diameter of the liposome particles in EXPAREL ranges from 24 to 31 μm. The liposomes are suspended in a 0.9% Sodium Chloride Injection. Each vial contains bupivacaine at a nominal concentration of 13.3 mg/mL. Inactive ingredients and their nominal concentrations are: cholesterol, 4.7 mg/mL; 1, 2-dipalmitoyl-sn-glycero-3 phospho-rac-(1-glycerol) sodium salt (DPPG), 0.9 mg/mL; tricaprylin, 2.0 mg/mL; 1, 2-dierucoylphosphatidylcholine (DEPC), 8.2 mg/mL; phosphoric acid to adjust pH; and sodium chloride to adjust tonicity. The pH of EXPAREL is in the range of 5.8 to 7.4.
Bupivacaine in EXPAREL has different functional properties relative to those of the unencapsulated or nonlipid-associated bupivacaine products. Bupivacaine that is released from EXPAREL has a different pharmacokinetic and systemic profile relative to other bupivacaine products. In addition, the nominal weight percent concentration of bupivacaine in EXPAREL is based on bupivacaine free base rather than bupivacaine HCl (100 mg of bupivacaine HCl contains 88.6 mg of bupivacaine free base) [see Dosage and Administration (2.1)].
Absorption
The rate of systemic absorption of bupivacaine is dependent upon the total dose of EXPAREL administered, the route of administration, and the vascularity of the administration site.
Pharmacokinetic parameters of EXPAREL after local infiltration, and following an interscalene brachial plexus nerve block, sciatic nerve block in the popliteal fossa, and adductor canal block were evaluated following surgical procedures. Descriptive statistics of pharmacokinetic parameters of representative EXPAREL doses in each study are provided in Table 5 for adult patients after administration of single doses of EXPAREL via local infiltration; Table 6 for adult patients after administration of single doses of EXPAREL via nerve block; and in Table 7 for pediatric patients aged 6 to less than 17 years old after administration of single doses of EXPAREL via local infiltration.
Table 5: Summary of Pharmacokinetic Parameters for Bupivacaine after Administration of Single Doses of EXPAREL via Local Infiltration in Adult Patients | Parameters Arithmetic mean (standard deviation) except Tmax where it is median (minimum, maximum). | Bunionectomy Patients undergoing bunionectomy (Study 1)
106 mg
(8 mL) | Hemorrhoidectomy Patients undergoing hemorrhoidectomy (Study 2)
266 mg
(20 mL) | Spine Surgery Patients undergoing open posterior spinal fusion or reconstructive surgery
266 mg
(20 mL) | Cardiothoracic Surgery Patients undergoing posterolateral thoracotomy
266 mg
(20 mL) |
|---|
| (N=26) | (N=25) | (N=11) | (N=5) |
|---|
| NE: Not evaluated |
| Cmax (ng/mL) | 166 (93) | 867 (353) | 513 (268) | 445 (120) |
| Tmax (h) | 2 (0.5, 24) | 0.5 (0.25, 36) | 0.6 (0.2, 37) | 0.6 (0.6, 36) |
AUC0-40h
(h × ng/mL) | NE | NE | 13035 (8782) | 9867 (1332) |
AUC(0-last)
(h × ng/mL) | 5864 (2038) AUC0-last, 0-72h; | 16867 (7868) | 17214 (11621) AUC0-last, 0-96h | 14277 (3449) |
AUC(inf)
(h × ng/mL) | 7105 (2283) | 18289 (7569) | 17917 (12187) | 15768 (4530) |
| t½ (h) | 34 (17) | 24 (39) | 9 (2) | 14 (6) |
Table 6: Summary of Pharmacokinetic Parameters for Bupivacaine after Administration of Single Doses of EXPAREL via Nerve Block in Adult Patients (Studies 3, 4 and 5)| Parameters Arithmetic mean (standard deviation) except Tmax where it is median (minimum, maximum). | Interscalene Brachial Plexus Nerve Block Patients undergoing total shoulder arthroplasty (Study 3) | Sciatic Nerve Block in the Popliteal Fossa Patients undergoing bunionectomy (Study 4) | Adductor Canal Block Patients undergoing total knee arthroplasty (Study 5) |
|---|
EXPAREL
133 mg (10 mL) | EXPAREL
133 mg (10 mL) + BUP as Mayo field block (100 mg100 mg bupivacaine HCl contains 88.6 mg of bupivacaine free base. )
(Total dose: 221.6 mg bupivacaine) | EXPAREL
133 mg (10 mL) + BUP 50 mg + BUP as IPACK (37.5 mg) + BUP (up to 15 mg) as spinal anesthesia
(Total dose: 224 mg bupivacaine) |
|---|
| (N = 12) | (N = 21) | (N = 24) |
|---|
BUP: Bupivacaine HCl.
IPACK: Infiltration between the popliteal artery and capsule of the knee
NE: Not evaluated |
| Cmax (ng/mL) | 207 (137) | 382 (241) | 495 (165) |
| Tmax (h) | 48 (3, 74) | 8.1 (1.7, 12) | 0.7 (0.4, 72) |
| AUC(0-last) (h × ng/mL) | 11484 (8615) AUC0-last, 0-120h ; | 16005 (6740) AUC0-last, 0-168h | 25039 (11921) |
| AUC(inf) (h × ng/mL) | 11590 (8603) | 17004 (7206) | 25109 (11918) |
| t½ (h) | 11 (5) | 28 (14) | 11 (3) |
Table 7: Summary of Pharmacokinetic Parameters for Bupivacaine after Administration of Single Doses of EXPAREL via Local Infiltration in Pediatric Patients Aged 6 to Less Than 17 Years Old (Studies Peds-1 and Peds-2)| Parameters Arithmetic mean (standard deviation) except Tmax where it is median (minimum, maximum). | Spine Surgery | Cardiac Surgery |
|---|
EXPAREL
4 mg/kg
(Maximum 266 mg) | EXPAREL
4 mg/kg
(Maximum 266 mg) |
|---|
6 to <17 years
(N = 17) | 6 to <12 years
(N = 21) |
|---|
NR1 = Not reported, since the last sampling time point varies among different patients.
NR2= Not reported, since the terminal elimination phase was not adequately characterized in sufficient number of patients. |
| Cmax (ng/mL) | 353 (125) | 447 (243) |
| Tmax (h) | 1.2 (0.3-26) | 23 (0.2, 55) |
| AUC(0- 40 h) (h × ng/mL) | 8782 (2834) | 11286 (4791) |
| AUC(0-last) (h × ng/mL) | NR1 | 16776 (7936) AUC0-last, 0-72h |
| AUC(inf) (h × ng/mL) | NR2 | NR2 |
| t½ (h) | NR2 | NR2 |
Distribution
After bupivacaine has been released from EXPAREL and is absorbed systemically, bupivacaine distribution is expected to be the same as for any bupivacaine HCl solution formulation.
Local anesthetics including bupivacaine are distributed to some extent to all body tissues, with high concentrations found in highly perfused organs such as the liver, lungs, heart, and brain.
Local anesthetics including bupivacaine appear to cross the placenta by passive diffusion. The rate and degree of diffusion is governed by (1) the degree of plasma protein binding, (2) the degree of ionization, and (3) the degree of lipid solubility. Fetal/maternal ratios of local anesthetics appear to be inversely related to the degree of plasma protein binding, because only the free, unbound drug is available for placental transfer. Bupivacaine with a high protein binding capacity (95%) has a low fetal/maternal ratio (0.2 to 0.4). The extent of placental transfer is also determined by the degree of ionization and lipid solubility of the drug. Lipid soluble, non-ionized drugs such as bupivacaine readily enter the fetal blood from the maternal circulation.
Elimination
Metabolism
Amide-type local anesthetics, such as bupivacaine, are metabolized primarily in the liver via conjugation with glucuronic acid. Pipecoloxylidide (PPX) is the major metabolite of bupivacaine; approximately 5% of bupivacaine is converted to PPX. Elimination of drug depends largely upon the availability of plasma protein binding sites in the circulation to carry it to the liver where it is metabolized.
Various pharmacokinetic parameters of the local anesthetics can be significantly altered by the presence of hepatic disease. Patients with hepatic disease, especially those with severe hepatic disease, may be more susceptible to the potential toxicities of the amide-type local anesthetics.
Excretion
After bupivacaine has been released from EXPAREL and is absorbed systemically, bupivacaine excretion is expected to be the same as for other bupivacaine formulations.
The kidney is the main excretory organ for most local anesthetics and their metabolites. Only 6% of bupivacaine is excreted unchanged in the urine.
Urinary excretion is affected by urinary perfusion and factors affecting urinary pH. Acidifying the urine hastens the renal elimination of local anesthetics. Various pharmacokinetic parameters of the local anesthetics can be significantly altered by the presence of renal disease, factors affecting urinary pH, and renal blood flow.
Specific Populations
Hepatic Impairment
Because amide-type local anesthetics, such as bupivacaine, are metabolized by the liver, the effects of decreased hepatic function on bupivacaine pharmacokinetics following administration of EXPAREL were studied in patients with moderate hepatic impairment. Consistent with the hepatic clearance of bupivacaine, mean plasma concentrations were higher in patients with moderate hepatic impairment than in the healthy control volunteers with approximately 1.5- and 1.6-fold increases in the mean values for Cmax and the area under the curve (AUC), respectively. [see Warnings and Precautions (5.1) and Use in Specific Populations (8.6)].
Carcinogenesis
Long-term studies in animals to evaluate the carcinogenic potential of bupivacaine have not been conducted.
Mutagenesis
The mutagenic potential of bupivacaine has not been determined.
Impairment of Fertility
The effect of bupivacaine on fertility has not been determined.
Study 1: Infiltration for Bunionectomy in Adults
A multicenter, randomized, double-blind, placebo-controlled, parallel-group clinical trial (NCT00890682) (Study 1) evaluated the safety and efficacy of 106 mg (8 mL) EXPAREL in 193 adult patients undergoing bunionectomy. The mean age was 43 years (range 18 to 72).
Study medication was administered directly into the site at the conclusion of the surgery, prior to closure. There was an infiltration of placebo or 7 mL of EXPAREL into the tissues surrounding the osteotomy and 1 mL into the subcutaneous tissue.
Pain intensity was rated by the patients on a 0 to 10 numeric rating scale (NRS) out to 72 hours. Postoperatively, patients were allowed rescue medication (5 mg oxycodone/325 mg acetaminophen orally every 4 to 6 hours as needed) or, if that was insufficient within the first 24 hours, ketorolac (15 to 30 mg IV). The primary outcome measure was the area under the curve (AUC) of the NRS pain intensity scores (cumulative pain scores) collected over the first 24-hour period. There was a significant treatment effect for EXPAREL compared to placebo. EXPAREL demonstrated a significant reduction in pain intensity compared to placebo for up to 24 hours. There was no significant difference in the amount of morphine equivalents used through 72 hours post-surgery, 43 mg versus 42 mg for placebo and EXPAREL, respectively. In addition, there was not a significant difference in the percentage of patients that used ketorolac, 43% versus 31% for placebo and EXPAREL, respectively.
Study 2: Infiltration for Hemorrhoidectomy in Adults
A multicenter, randomized, double-blind, placebo-controlled, parallel-group clinical trial (NCT00890721) (Study 2) evaluated the safety and efficacy of 266 mg (20 mL) EXPAREL in 189 adult patients undergoing hemorrhoidectomy. The mean age was 48 years (range 18 to 86).
EXPAREL or placebo were administered directly into the site (greater than or equal to 3 cm) at the conclusion of the surgery. Dilution of 20 mL of EXPAREL with 10 mL of saline, for a total of 30 mL, was divided into six 5-mL aliquots. A field block was performed by visualizing the anal sphincter as a clock face and slowly infiltrating one aliquot to each of the even numbers.
Pain intensity was rated by the patients on a 0 to 10 NRS at multiple time points up to 72 hours. Postoperatively, patients were allowed rescue medication (morphine sulfate 10 mg intramuscular every 4 hours as needed).
The primary outcome measure was the AUC of the NRS pain intensity scores (cumulative pain scores) collected over the first 72-hour period.
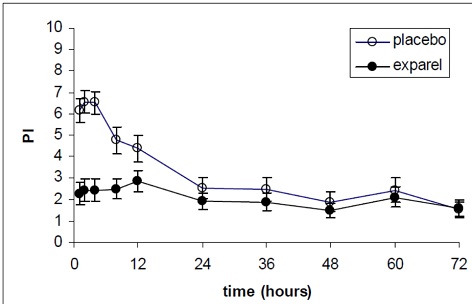
There was a significant treatment effect for EXPAREL compared to placebo. See Figure 1 for the mean pain intensity over time for the EXPAREL and placebo treatment groups for the 72-hour efficacy period.
There were statistically significant, but small differences in the amount of opioid rescue analgesia used across the treatment groups, the clinical benefit of which has not been established. The median time to rescue analgesic use was 15 hours for patients treated with EXPAREL and one hour for patients treated with placebo. Twenty-eight percent of patients treated with EXPAREL required no rescue medication at 72 hours compared to 10% treated with placebo. For those patients who did require rescue medication, the mean amount of morphine sulfate intramuscular injections used over 72 hours was 22 mg for patients treated with EXPAREL and 29 mg for patients treated with placebo.
Study 3: Interscalene Brachial Plexus Nerve Block for Total Shoulder Arthroplasty or Rotator Cuff Repair in Adults
A multicenter, randomized, double-blind, placebo-controlled study (NCT02713230) (Study 3) was conducted in 156 adult patients undergoing primary unilateral total shoulder arthroplasty or rotator cuff repair with general anesthesia. The mean age was 61 years (range 33 to 80). Prior to the surgical procedure, patients received 133 mg (10 mL) of EXPAREL expanded with normal saline to 20 mL or placebo as a brachial plexus nerve block (perineural use) via interscalene or supraclavicular approach with ultrasound guidance. Only two patients received nerve block with EXPAREL by supraclavicular approach. Postsurgically, patients were administered acetaminophen/paracetamol up to 1,000 mg orally or intravenously every 8 hours unless contraindicated. Patients were allowed opioid rescue medication administered initially as oral immediate-release oxycodone (initiating at 5-10 mg every 4 hours or as needed). If a patient could not tolerate oral medication, intravenous morphine (2.5-5 mg) or hydromorphone (0.5-1 mg) could be administered every 4 hours or as needed.
In Study 3, there was a statistically significant treatment effect for EXPAREL compared to placebo in cumulative pain scores through 48 hours as measured by the AUC of the visual analog scale (VAS) pain intensity scores. There were statistically significant, but small differences in the amount of opioid consumption through 48 hours, the clinical benefit of which has not been demonstrated. For those patients who required rescue medication, the mean amount of morphine-equivalent opioid rescue used over 48 hours was 12 mg for EXPAREL-treated patients and 54 mg for placebo-treated patients and 23 mg with EXPAREL-treated patients vs. 70 mg for placebo-treated patients over 72 hours.
Although at 48 hours, 9 patients (13%) in the EXPAREL group remained opioid-free compared to 1 patient (1%) in the placebo group, a difference which was statistically significant, at 72 hours, there were 4 (6%) patients in the EXPAREL group who remained opioid-free compared to 1 (1%) patient in the placebo group, a difference that is not statistically significant.
Study 4: Sciatic Nerve Block in the Popliteal Fossa for Bunionectomy in Adults
A multicenter, randomized, double-blind, active controlled study (NCT05157841) (Study 4) was conducted in 185 adult patients undergoing bunionectomy. The mean age was 49 years (range 18 to 76).
Prior to the surgical procedure, patients received 133 mg of EXPAREL mixed with 20 mL saline OR 50 mg (20 mL) of 0.25% bupivacaine HCl mixed with 10 mL saline via sciatic nerve block (perineural use) in the popliteal fossa. All patients received 100 mg (20 mL) of 0.5% immediate-release bupivacaine HCl as a Mayo field block after study drug administration (i.e., in the operating room immediately prior to surgical incision). All patients also received a dose of 1,000 mg of intravenous (IV) acetaminophen at the time of surgical incision. IV fentanyl was allowed for intraoperative pain control (not exceeding 1 mcg/kg unless deemed medically necessary).
Postsurgically, all patients received one post-operative dose of 1,000 mg IV acetaminophen, administered approximately 8 hours after the first dose (approximately 8 hours after incision). Patients were administered pain medications on an as needed basis; opioids were not given on a pre-determined schedule. Patients were allowed opioid rescue medication administered initially as oral immediate-release oxycodone (initiating at 5 mg and increasing the dose to 10 mg if initial opioid dose was insufficient). If a patient could not tolerate oral medication or the oral oxycodone pain relief was insufficient, IV morphine (initiated at 2 mg) or hydromorphone (initiated at 0.2 mg) could be administered. No NSAIDs or other opioids including tramadol were allowed for the breakthrough pain management and no acetaminophen (other than the scheduled IV acetaminophen) was used for breakthrough pain.
In Study 4, there was a statistically significant treatment effect for EXPAREL (with 0.5% immediate-release bupivacaine HCl as a Mayo field block) compared to bupivacaine HCl (with 0.5% immediate-release bupivacaine HCl as a Mayo field block) in cumulative pain scores through 96 hours as measured by AUC of the NRS pain intensity scores. There were statistically significant differences in the total amount of postsurgical opioid medication used through 96 hours, the clinical benefit of which has not been demonstrated. For those patients who required postsurgical opioid medication, the mean amount of morphine-equivalent opioid rescue used over 96 hours was 18 mg for patients treated with EXPAREL + Mayo field block and 45 mg for patients treated with bupivacaine HCl + Mayo field block. There was also a statistically significant difference in the percentage of opioid-free patients through 96 hours compared with bupivacaine HCl (24% in the EXPAREL + Mayo field block vs. 6% in the bupivacaine HCl + Mayo field block).
See Figure 2 for the LS mean pain intensity scores after administration of either 133 mg of EXPAREL or 50 mg of 0.25% bupivacaine HCl.
Figure 2. NRS Pain Intensity After Administration of Study Drug by Sciatic Nerve Block in the Popliteal Fossa.
Study 5: Adductor Canal Block for Total Knee Arthroplasty in Adults
A multicenter, randomized, double-blind, active controlled study (NCT05139030) (Study 5) was conducted in 166 adult patients undergoing primary unilateral total knee arthroplasty. The mean age was 62 years (range 37 to 83).
Prior to the surgical procedure, patients received (via adductor canal block) (perineural use):
- 133 mg (10 mL) of 1.3% EXPAREL admixed with 50 mg (10 mL) of 0.5% bupivacaine HCl or
- 50 mg (10 mL) of 0.5% bupivacaine HCl mixed with 10 mL normal saline.
All patients also received 37.5 mg (15 mL) of 0.25% immediate-release bupivacaine HCl as an infiltration between the popliteal artery and capsule of the knee (IPACK) block immediately following study drug administration. All patients received spinal anesthesia immediately prior to surgery with 0.5% bupivacaine HCl (up to 15 mg). All patients also received a dose of 1,000 mg of intravenous (IV) acetaminophen at the time of surgical incision. IV fentanyl was allowed for intraoperative pain control (not exceeding 1 ug/kg unless deemed medically necessary).
Postsurgically, all patients received one post-operative dose of 1,000 mg IV acetaminophen, administered approximately 8 hours after the first dose (approximately 8 hours after incision). Patients were administered pain medications on an as needed basis for breakthrough pain; opioids were not given on a pre-determined schedule. Patients were allowed opioid rescue medication administered initially as oral immediate-release oxycodone (initiating at 5 mg and increasing the dose to 10 mg if initial opioid dose was insufficient). If a patient could not tolerate oral medication or the oral oxycodone pain relief was insufficient, IV morphine (initiated at 2 mg) or hydromorphone (initiated at 0.2 mg) could be administered. No NSAIDs or other opioids including tramadol were allowed for the breakthrough pain management and no acetaminophen (other than the scheduled IV acetaminophen) was used for breakthrough pain.
In Study 5, there was a statistically significant treatment effect for EXPAREL + IPACK block compared to bupivacaine HCl + IPACK in cumulative pain scores through 96 hours as measured by AUC of the NRS pain intensity scores. There were statistically significant differences in the total amount of postsurgical opioid medication used through 96 hours, the clinical benefit of which has not been demonstrated. For those patients who required postsurgical opioid medication, the mean amount of morphine-equivalent opioid rescue used over 96 hours was 102 mg for patients treated with EXPAREL + IPACK and 133 mg for patients treated with bupivacaine HCl+ IPACK. The median time to first postsurgical use was 4.2 hours for patients treated with EXPAREL + IPACK and 3.6 hours for patients treated with bupivacaine HCl + IPACK.
See Figure 3 for LS mean pain intensity scores after administration of either 133 mg of 1.3% EXPAREL admixed with 50 mg) of 0.5% bupivacaine HCl or 50 mg of 0.5% bupivacaine HCl.
Figure 3. NRS Pain Intensity After Administration of Study Drug by Adductor Canal Block
Studies 6 and 7: Inadequate Demonstration of Efficacy and Safety in Femoral Nerve Block in Total Knee Arthroplasty
EXPAREL was administered via a femoral nerve block in two placebo-controlled studies in adults (Studies 6 and 7). The results of these studies did not support a femoral nerve block indication due to inadequate safety data (Study 6) and/or due to inadequate efficacy findings (Study 7). In addition, patient falls were reported only in the EXPAREL treatment groups, and none was reported in placebo groups.
Study 6
Study 6, a multicenter, randomized, double-blind, parallel-group, placebo-controlled study (NCT01683071), was conducted in 196 adult patients undergoing primary unilateral total knee arthroplasty (TKA) under general or spinal anesthesia. The mean age was 65 years (range 42 to 88). Prior to the surgical procedure, 266 mg (20 mL) of EXPAREL or placebo was administered as a femoral nerve block with ultrasound guidance. Postsurgically, patients were allowed opioid rescue medication administered initially by intravenous injection of hydromorphone and subsequently by a patient-controlled analgesia (PCA) pump containing morphine or hydromorphone only. Once patients were tolerating oral medication, oral immediate-release oxycodone was administered on an as-needed basis (but not more than 10 mg every 4 hours) or, if that was insufficient, a third rescue of 1.25 mg/mL of 0.125% bupivacaine HCl was administered at a rate of 8 mL per hour via the previously placed femoral nerve catheter.
In this study, there was a statistically significant treatment effect for EXPAREL compared to placebo in cumulative pain scores through 72 hours as measured by the AUC of the NRS pain (at rest) intensity scores.
There was a statistically significant, although small decrease in opioid consumption for the EXPAREL treatment group compared to the placebo group, the clinical benefit of which has not been established. All patients in both the EXPAREL and placebo treatment groups required opioid rescue medication during the first 72 hours. The mean amount of opioid rescue used over 72 hours was 76 mg for patients treated with EXPAREL and 103 mg for patients treated with placebo.
The study was inadequate to fully characterize the safety of EXPAREL when used for femoral nerve block due to patient falls, which occurred only in the EXPAREL-treated patients and not in the placebo-treated patients.
Study 7
Study 7, a multicenter, randomized, double-blind, parallel-group, placebo-controlled study (NCT02713178), was conducted in 230 adult patients undergoing primary unilateral total knee arthroplasty (TKA) under general or spinal anesthesia. The mean age was 65 years (range 39 to 89). Prior to the surgical procedure, either 266 mg (20 mL) of EXPAREL or 133 mg (10 mL) of EXPAREL plus 10 mL of normal saline or placebo was administered as a femoral nerve block with ultrasound guidance. In addition to study drug, 8 mL of 0.5% bupivacaine HCl diluted with 8 mL of normal saline was administered by the surgeon as a periarticular infiltration to the posterior capsule (8 mL each behind the medial and lateral condyles) before placement of the prosthesis. Postsurgically, patients were allowed opioid rescue medication consisting of oral immediate-release oxycodone (initiated at 5 to 10 mg every 4 hours or as needed). If a patient could not tolerate oral medication, IV morphine (2.5 to 5 mg) or hydromorphone (0.5 to 1 mg) was permitted every 4 hours or as needed. Patient-controlled analgesia was not permitted. No other analgesic agents, including NSAIDs, were permitted through 108 hours. However, to reflect the current standard of care of postsurgical multimodal therapy, all patients received cyclobenzaprine (a single dose of 10 mg orally or as needed) and acetaminophen/paracetamol (up to 1,000 mg orally or IV every 8 hours for a maximum total daily dose of 3000 mg) postsurgically.
In this study there were no statistically significant treatment effects for the EXPAREL group compared to the placebo group in cumulative pain intensity scores or total opioid consumption. All patients in the EXPAREL and placebo treatment groups required opioid rescue medication over 72 hours. The median Tmax of bupivacaine observed in this study was 72 hours with a range of 2.5 to 108 hours. Similar to Study 6, patient falls only occurred in the EXPAREL-treated patients and not the placebo-treated patients.
Study 8: Lack of Efficacy in Intercostal Nerve Block for Posterolateral Thoracotomy
A multicenter, randomized, double-blind, placebo-controlled study was conducted in 191 adult patients undergoing posterolateral thoracotomy under general anesthesia (NCT01802411) (Study 8). The mean age was 58 years (range 18 to 82).
After the surgical procedure was completed but prior to the surgical site closure, 266 mg (20 mL) of EXPAREL was administered by the surgeon as an intercostal nerve block divided into three equal doses in three syringes of approximately 88 mg in 6.6 mL volume per nerve, and administered to each of three nerve segments (index nerve, nerve above, and nerve below). Postsurgically, patients were allowed opioid rescue medication administered initially by intravenous fentanyl 100 mcg, which was to be administered once via bolus only. For the US sites, the second rescue medication was to be PCA-administered morphine or hydromorphone. For the European sites, the second rescue medication was to be intramuscular administered morphine up to 10 mg every 4 hours. At all sites, once a patient was tolerating oral medication, oral immediate-release oxycodone was administered (but not more than 10 mg every 4 hours). Patients who did not achieve adequate pain relief with this regimen were to be withdrawn from the study and followed for safety only.
In this study there were no statistically significant treatment effects for EXPAREL 266 mg compared to placebo in cumulative pain intensity scores or total opioid consumption. Four percent of patients treated with EXPAREL required no rescue medication at 72 hours compared to 1% treated with placebo. For those patients who did require rescue medication, the mean amount of opioid rescue used over 72 hours was 71 mg for patients treated with EXPAREL and 71 mg for patients treated with placebo. The median Tmax of bupivacaine observed in this study was 1 hour with a range of 0.5 hours to 50 hours.
Study 9: Lack of Efficacy in Combined Sciatic (in popliteal fossa) and Saphenous (in adductor canal) Nerve Block Study in Lower Extremity Surgeries
A multicenter, randomized, double-blind, active-controlled trial (NCT04518462) (Study 9) was conducted in 119 adult patients who underwent foot and ankle procedures (bunionectomy, first metatarsophalangeal fusion, forefoot & hindfoot fusion, total ankle arthroplasty). The mean age was 48 years (range 20 to 72). Prior to the surgical procedure, patients received one of the following three treatments under ultrasound guidance as a sciatic nerve block in the popliteal fossa and a saphenous nerve block in the adductor canal:
- 266 mg of EXPAREL (20 mL) admixed with 20 mL of 0.9% Sodium Chloride Injection (referred to as normal saline (NS)),
- 266 mg of EXPAREL (20 mL) admixed with 50 mg of 0.25% bupivacaine HCl (20 mL), or
- 100 mg of 0.25% bupivacaine (40 mL).
The total volume (40 mL) was divided evenly between the two blocks. All patients received general anesthesia or nonopioid sedation (except fentanyl); were allowed medication for intraoperative nausea/vomiting prevention; and were allowed medication for breakthrough pain postsurgery which followed a step-wise approach starting with acetaminophen or a nonsteroidal anti-inflammatory drug (not exceeding the maximum dose), and, if needed escalating to an initial 5 mg dose of oxycodone, then to a 10 mg dose of oxycodone, and finally to intravenous morphine (initiated at 2 mg) or intravenous hydromorphone (initiated at 0.2 mg).
In Study 9 there was no significant difference in the primary endpoint [least square mean (LSM) area under the curve (AUC) numerical rating scale (NRS) pain score from 0 to 96 hours after surgery] between EXPAREL + NS and the 0.25% bupivacaine HCl treatment groups. Cumulative opioid consumption differences between groups were nonsignificant 0-96 hours after surgery. The LSM amount of opioids received over 96 hours was 21 mg in EXPAREL group and 20 mg in bupivacaine HCl group.
Manufactured for Pacira Pharmaceuticals, Inc., a wholly owned subsidiary of Pacira BioSciences, Inc.
San Diego, CA 92121 USA
Trademark of Pacira Pharmaceuticals, Inc.
©2023 Pacira Pharmaceuticals, Inc. All rights reserved.
For additional information call 1-855-RX-EXPAREL (1-855-793-9727) or visit www.EXPAREL.com