Risk Summary
Olmesartan medoxomil and hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue olmesartan medoxomil and hydrochlorothiazide as soon as possible. Use alternative antihypertensive therapy during pregnancy.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations
Disease-associated maternal and/or embryo/fetal risk
Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/Neonatal Adverse Reactions
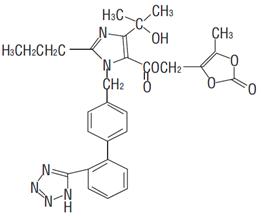
Olmesartan
Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to olmesartan medoxomil and hydrochlorothiazide for hypotension, oliguria, and hyperkalemia. If oliguria or hypotension occur, utilize measures to maintain adequate blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and supporting renal function [see Use in Specific Populations (8.4)].
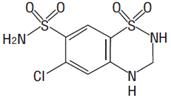
Hydrochlorothiazide
Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion. It accumulates in the amniotic fluid, with reported concentrations up to 19 times that in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of preeclampsia, these drugs should not be used to treat hypertension in pregnant women. The use of hydrochlorothiazide for other indications (e.g., heart disease) in pregnancy should be avoided.
Data
Animal Data
Olmesartan
No teratogenic effects were observed when olmesartan medoxomil was administered to pregnant rats at oral doses up to 1000 mg/kg/day (240 times the maximum recommended human dose [MRHD] on a mg/m2 basis) or pregnant rabbits at oral doses up to 1 mg/kg/day (half the MRHD on a mg/m2 basis; higher doses could not be evaluated for effects on fetal development as they were lethal to the does). In rats, significant decreases in pup birth weight and weight gain were observed at doses ≥1.6 mg/kg/day, and delays in developmental milestones (delayed separation of ear auricula, eruption of lower incisors, appearance of abdominal hair, descent of testes, and separation of eyelids) and dose-dependent increases in the incidence of dilation of the renal pelvis were observed at doses ≥ 8 mg/kg/day. The no observed effect dose for developmental toxicity in rats is 0.3 mg/kg/day, about one-tenth the MRHD of 40 mg/day.
Olmesartan medoxomil and Hydrochlorothiazide.
No teratogenic effects were observed when 1.6:1 combinations of olmesartan medoxomil and hydrochlorothiazide were administered to pregnant mice at oral doses up to 1625 mg/kg/day (122 times the maximum recommended human dose MRHD on a mg/m2 basis) or pregnant rats at oral doses up to 1625 mg/kg/day (243 times the MRHD on a mg/m2 basis). In rats, however, fetal body weights at 1625 mg/kg/day (a toxic, sometimes lethal dose in the dams) were significantly lower than control. The no observed effect dose for developmental toxicity in rats, 162.5 mg/kg/day, is about 24 times, on a mg/m2 basis, the MRHD of 40 mg olmesartan medoxomil /25 mg hydrochlorothiazide/day (calculations based on a 60 kg patient).
Hydrochlorothiazide
No teratogenic effects were observed when hydrochlorothiazide was administered to mice and rats via gavage at doses up to 3000 and 1000 mg/kg/day, respectively (about 600 and 400 times the MRHD), on gestation days 6 through 15.