Other
Adult Patients
UPTRAVI is indicated for the treatment of pulmonary arterial hypertension in adults (PAH, WHO Group I) to delay disease progression and reduce the risk of hospitalization for PAH.
Effectiveness of UPTRAVI tablets was established in a long-term study in adult PAH patients with WHO Functional Class II–III symptoms.
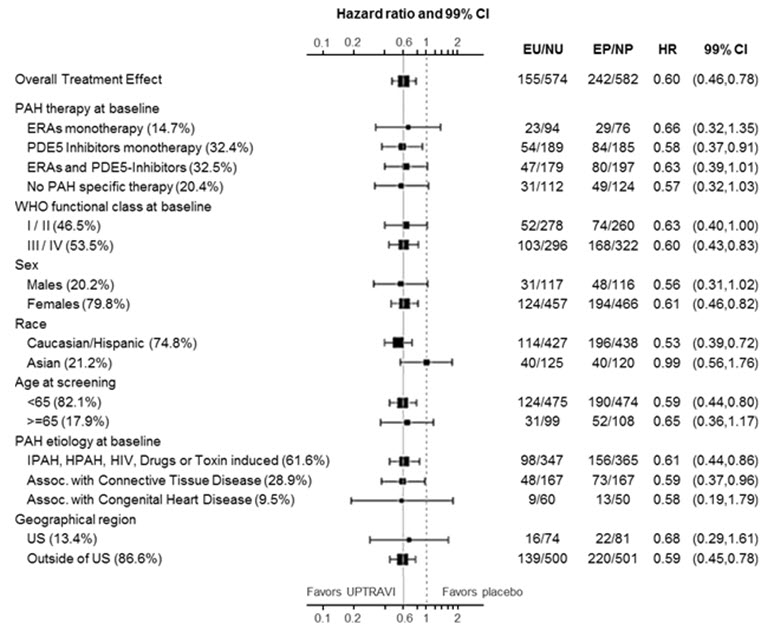
Patients had idiopathic and heritable PAH (58%), PAH associated with connective tissue disease (29%), PAH associated with congenital heart disease with repaired shunts (10%) [see Clinical Studies (14.1)].
Pediatric Patients
UPTRAVI is indicated for the treatment of PAH (WHO Group I) in pediatric patients aged two years and older. UPTRAVI reduces NT-proBNP and is expected to delay disease progression and reduce the risk of hospitalization for PAH.
Adult Patients
The recommended starting dosage of UPTRAVI tablets is 200 mcg given orally twice daily. Tolerability may be improved when taken with food [see Clinical Pharmacology (12.3)].
Increase the dose in increments of 200 mcg orally twice daily, usually at weekly intervals, to the highest tolerated dose up to 1,600 mcg orally twice daily. If a patient reaches a dose that cannot be tolerated, the dose should be reduced to the previous tolerated dose.
Swallow the UPTRAVI tablets whole. Do not split or crush the tablets.
Pediatric Patients Two Years and Older
The recommended starting dose of UPTRAVI is determined based on the patient's body weight and is given orally twice daily. The recommended UPTRAVI starting doses, titration increments, and maximum allowed doses based on body weight categories in pediatric patients are shown in Table 1.
| Body weight (kg) | Recommended starting dose | Recommended titration increments | Maximum dose allowed |
|---|---|---|---|
| 9 kg to less than 25 kg | 100 mcg orally twice daily | 100 mcg orally twice daily | 800 mcg orally twice daily |
| 25 kg to less than 40 kg | 150 mcg orally twice daily | 150 mcg orally twice daily | 1,200 mcg orally twice daily |
| 40 kg to less than 50 kg | 150 mcg orally twice daily | 150 mcg orally twice daily | 1,600 mcg orally twice daily For pediatric patients with a body weight ≥40 kg to <50 kg multiple tablet dose strengths may be needed to reach the doses up to 1,600 mcg twice daily. |
| 50 kg and greater | 200 mcg orally twice daily | 200 mcg orally twice daily | 1,600 mcg orally twice daily |
Increase the dose in increments equivalent to the starting dose (i.e., 100 mcg, 150 mcg or 200 mcg given orally twice daily), at weekly intervals, to the highest tolerated dose up to the maximum dose allowed for the patient's body weight (see Table 1). If a patient reaches a dose that cannot be tolerated or medically managed, the dose should be reduced to the previous tolerated dose.
Re-evaluate further dose titration based on changes in body weight category over time.
Tolerability may be improved when taken with food [see Clinical Pharmacology (12.3)].
Swallow the UPTRAVI tablets whole. Do not split or crush the tablets.
Alternate Methods of Administration of 100 mcg and 150 mcg UPTRAVI Film-coated Tablets
For patients who cannot swallow the tablets whole, 100 mcg or 150 mcg UPTRAVI tablets can be dispersed and administered in apple or orange juice. Do not disperse the tablet(s) in water or milk. Do not crush or split the tablet(s). At least 1 mL of juice per tablet is recommended. Add the juice to the required number of tablet(s) per dosing schedule (see Table 1). Wait for 5 min and then stir until the tablets are dispersed. Administer the mixture immediately after dispersion. Do not store tablets that are mixed with juice for later use.
Alternatively, 100 mcg and 150 mcg UPTRAVI tablets can also be administered with soft foods such as yogurt, applesauce, or mashed banana. Cover the required number of tablets with soft food. Administer the mixture immediately. To ensure no tablet residue is left, add more soft food and administer the contents immediately. Do not store tablets that are mixed with soft food for later use.
Reconstitution
- Remove the carton of UPTRAVI for injection from the refrigerator and allow to stand for approximately 30 to 60 minutes to reach room temperature (20 °C to 25 °C [68 °F to 77 °F]).
- The vial needs to be protected from light at all times. Ensure the protective wrap around label is covering the entire vial.
- Peel back light protective wrap on vial to inspect the contents in the vial. It should appear white to almost white broken cake or powdered material. Immediately close the light protective wrap on the vial.

Image (Uptravi 01)

Image (Uptravi 02)
- Reconstitute UPTRAVI for injection using a polypropylene syringe with 8.6 mL of 0.9% Sodium Chloride Injection, USP and slowly inject into the UPTRAVI vial with the stream directed toward the inside wall of the vial to obtain a concentration of 225 mcg/mL of selexipag.
- Document date and time of first puncture. Complete infusion within 4 hours of first puncture.
- Gently invert the vial and repeat until powder is completely dissolved. Do not shake.
- Inspect the vial by peeling back the light protective wrap around label for discoloration. The reconstituted solution should appear clear, colorless and free from foreign material. Do not use if the reconstituted solution is discolored, cloudy, or contains visible particles.
- UPTRAVI for injection must be diluted in glass containers only.
- Withdraw 100 mL of 0.9% Sodium Chloride Injection, USP and transfer into an empty sterile glass container.
- Withdraw the required volume of reconstituted solution (see Table 2 for reconstituted transfer volume) from the UPTRAVI vial using a single, appropriately sized polypropylene syringe and dilute into the glass container containing 100 mL 0.9% Sodium Chloride Injection, USP to obtain the desired final dose.
- Mix the diluted UPTRAVI infusion solution by gentle inversion of the glass container 5 times. Do not shake.
- Protect diluted UPTRAVI infusion solution from light at all times. Assign a 4-hour expiry from the time of first vial puncture and wrap the glass container completely with light protective cover.
- The UPTRAVI infusion solution should be kept at room temperature (20 °C to 25 °C [68 °F to 77 °F]) and must be infused within 4 hours from the first puncture of the vial stopper (including infusion time).
- Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration. The diluted UPTRAVI infusion solution should be clear and colorless. Discard if particulate matter is observed.
- To take a missed dose as soon as possible, unless the next dose is within the next 6 hours.
- Not to split or crush tablets.
- To follow the instructions for alternate methods of administration for patients who cannot swallow tablets whole [see Dosage and Administration (2.1)].
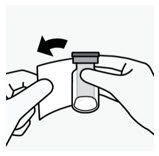
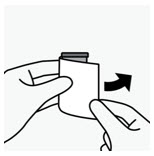
Dilution
UPTRAVI for injection vials are single-dose, for single administration. All remaining reconstituted product must be discarded.
| UPTRAVI tablets dose (mcg) for twice daily dosing | Corresponding intravenous UPTRAVI dose (mcg) for twice daily dosing | Reconstituted transfer volume (mL) for dilution |
|---|---|---|
| 200 | 225 | 1 |
| 400 | 450 | 2 |
| 600 | 675 | 3 |
| 800 | 900 | 4 |
| 1,000 | 1,125 | 5 |
| 1,200 | 1,350 | 6 |
| 1,400 | 1,575 | 7 |
| 1,600 | 1,800 | 8 |
UPTRAVI Tablets
Adult Patients
The safety of UPTRAVI tablets has been evaluated in a long-term, placebo-controlled study enrolling 1,156 adult patients with symptomatic PAH (GRIPHON study) [see Clinical Studies (14.1)]. The exposure to UPTRAVI in this trial was up to 4.2 years with median duration of exposure of 1.4 years.
Table 3 presents adverse reactions more frequent on UPTRAVI tablets than on placebo by ≥3%.
| UPTRAVI | Placebo | |
|---|---|---|
| Adverse Reaction | N=575 | N=577 |
| Headache | 65% | 32% |
| Diarrhea | 42% | 18% |
| Jaw pain | 26% | 6% |
| Nausea | 33% | 18% |
| Myalgia | 16% | 6% |
| Vomiting | 18% | 9% |
| Pain in extremity | 17% | 8% |
| Flushing | 12% | 5% |
| Arthralgia | 11% | 8% |
| Anemia | 8% | 5% |
| Decreased appetite | 6% | 3% |
| Rash | 11% | 8% |
These adverse reactions are more frequent during the dose titration phase.
Hyperthyroidism was observed in 1% (n=8) of patients on UPTRAVI tablets and in none of the patients on placebo.
Pediatric Patients Two Years and Older
The safety of UPTRAVI tablets has been evaluated in a long-term, Phase 3, double-blind, placebo-controlled study (SALTO), where a total of 138 pediatric patients with symptomatic PAH ≥2 to <18 years of age were randomized 1:1 to receive either UPTRAVI or placebo [see Clinical Studies (14.2)]. The exposure to UPTRAVI in this study was up to 4.1 years with a median duration of exposure of 1.5 years.
The safety profile in pediatric patients was consistent with that observed in adults with PAH. Compared to adults, a higher frequency of vomiting was observed (39% on UPTRAVI versus 19% on placebo). In addition, abdominal pain was observed in 15% of pediatric patients on UPTRAVI and in 6% on placebo.
UPTRAVI-treated pediatric patients experienced a smaller mean increase in body weight and height compared to the placebo group. The mean change in weight Z-score from baseline at 48 weeks in UPTRAVI-treated pediatric patients (n=54) was –0.31 compared to –0.09 in the placebo group (n=61); and at 96 weeks in UPTRAVI-treated pediatric patients (n=32) was –0.46 compared to –0.12 in the placebo group (n=35). The mean change in height Z-score from baseline at 48 weeks in UPTRAVI-treated pediatric patients (n=54) was –0.16 compared to –0.04 in the placebo group (n=61); and at 96 weeks in the UPTRAVI-treated pediatric patients (n=32) was –0.30 compared to –0.05 in the placebo group (n=35). When treating pediatric patients with UPTRAVI, monitor growth.
UPTRAVI for Injection
Infusion-site reactions (infusion site erythema/redness, pain and swelling) were reported with UPTRAVI for Injection in adult patients.
Laboratory Test Abnormalities
Hemoglobin
In a Phase 3 placebo-controlled study in adult patients with PAH, mean absolute changes in hemoglobin at regular visits compared to baseline ranged from −0.34 to −0.02 g/dL in the UPTRAVI group compared to −0.05 to 0.25 g/dL in the placebo group. A decrease in hemoglobin concentration to below 10 g/dL was reported in 8.6% of patients treated with UPTRAVI tablets and 5.0% of placebo-treated patients.
Thyroid Function Tests
In a Phase 3 placebo-controlled study in adult patients with PAH, a reduction (up to −0.3 MU/L from a baseline median of 2.5 MU/L) in median thyroid-stimulating hormone (TSH) was observed at most visits in the UPTRAVI group. In the placebo group, little change in median values was apparent. There were no mean changes in triiodothyronine or thyroxine in either group.
Risk Summary
There are no adequate and well-controlled studies with UPTRAVI in pregnant women. Animal reproduction studies performed with selexipag showed no clinically relevant effects on embryofetal development and survival. A slight reduction in maternal as well as in fetal body weight was observed when pregnant rats were administered selexipag during organogenesis at a dose producing an exposure to the active metabolite approximately 47 times that in humans at the maximum recommended human dose. No adverse developmental outcomes were observed with oral administration of selexipag to pregnant rabbits during organogenesis at exposures to the active metabolite up to 50 times the human exposure at the maximum recommended human dose.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively.
Clinical Considerations
Disease-associated maternal and/or embryo/fetal risk
In patients with pulmonary arterial hypertension, pregnancy is associated with an increased rate of maternal and fetal morbidity and mortality, including heart failure, stroke, spontaneous abortion, intrauterine growth restriction, premature labor, and preterm birth.
Data
Animal Data
Pregnant rats were treated with selexipag using oral doses of 2, 6, and 20 mg/kg/day (up to 47 times the exposure to the active metabolite at the maximum recommended human oral dose of 1,600 mcg twice daily on an area under the curve [AUC] basis) during the period of organogenesis (gestation days 7 to 17). Selexipag did not cause adverse developmental effects to the fetus in this study. A slight reduction in fetal body weight was observed in parallel with a slight reduction in maternal body weight at the high dose.
Pregnant rabbits were treated with selexipag using oral doses of 3, 10, and 30 mg/kg (up to 50 times the exposure to the active metabolite at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis) during the period of organogenesis (gestation days 6 to 18). Selexipag did not cause adverse developmental effects to the fetus in this study.
In a pre- and post-natal development study, pregnant rats were treated with selexipag from gestation day 7 through lactation day 20 at oral doses of 2, 6, and 20 mg/kg/day (up to 35 times the exposure to the active metabolite at the maximum recommended human dose of 1,600 mcg twice daily on an AUC basis). Treatment with selexipag did not cause adverse developmental effects in this study at any dose.
Juvenile Animal Toxicity Data
In juvenile dogs, intussusception due to prostacyclin-related effects on intestinal motility was observed sporadically. Safety margins adapted for prostacyclin receptor potency for the active metabolite were 2-fold (based on total exposure) in relation to human therapeutic exposure. The finding did not occur in mouse or rat toxicity studies.
Cardiac Electrophysiology
At the maximum tolerated dose of 1,600 mcg UPTRAVI tablets twice daily, UPTRAVI does not prolong the QT interval to any clinically relevant extent.
Platelet Aggregation
Both selexipag and its active metabolite caused concentration-dependent inhibition of platelet aggregation in vitro with an IC50 of 5.5 µM and 0.21 µM, respectively. However, at clinically relevant concentrations, there was no effect on platelet aggregation test parameters as seen following multiple-dose administrations of UPTRAVI tablets in healthy subjects from 400 to 1,800 mcg twice daily.
Pulmonary Hemodynamics
A Phase 2 clinical study NS-304/-02 assessed hemodynamic variables after 17 weeks of oral treatment in adult patients with PAH WHO Functional Class II–III and concomitantly receiving endothelin receptor antagonists (ERAs) and/or phosphodiesterase type 5 (PDE-5) inhibitors. Patients titrating UPTRAVI tablets to an individually tolerated dose (200 mcg twice daily increments up to 800 mcg twice daily) (N=33) achieved a statistically-significant mean reduction in pulmonary vascular resistance of 30.3% (95% confidence interval [CI] −44.7%, −12.2%) and an increase in cardiac index (median treatment effect) of 0.41 L/min/m2 (95% CI 0.10, 0.71) compared to placebo (N=10).
A Phase 2 clinical study NS304P-P2-1 assessed hemodynamic variables in 6 Japanese pediatric patients with PAH WHO Functional Class II–III. The mean age was 9.2 years (range 3–13 years). Five patients had idiopathic PAH, and 1 patient had postoperative congenital heart disease. Three patients were treatment-naïve, while 3 patients received background combination therapy. UPTRAVI was titrated and dosed the same as in the SALTO study [see Clinical Studies (14.2)]. A mean reduction of 5.55 Wood units∙m2 (95% CI −12.76, 1.67) in pulmonary vascular resistance index at week 16 was achieved.
Drug Interaction
In a study in healthy adult subjects, UPTRAVI tablets (400 mcg twice a day) did not influence the pharmacodynamic effect of warfarin on the international normalized ratio.
Absorption
The absolute bioavailability of orally administered selexipag is approximately 49%. Upon oral administration, maximum observed plasma concentrations of selexipag and its active metabolite are reached within about 1–3 hours and 3–4 hours, respectively.
Similar exposures were observed in pediatric study patients after taking whole tablets with water, taking with soft food, and dispersing in apple or orange juice.
Effect of Food
In the presence of food, the absorption of selexipag was prolonged resulting in a delayed time to peak concentration (Tmax) and ~30% lower peak plasma concentration (Cmax). The exposure to selexipag and the active metabolite (AUC) did not significantly change in the presence of food.
Distribution
The volume of distribution of selexipag at steady-state is 11.7 L.
Selexipag and its active metabolite are highly bound to plasma proteins (approximately 99% in total and to the same extent to albumin and alpha1-acid glycoprotein).
Metabolism
Selexipag is hydrolyzed to its active metabolite, (free carboxylic acid) in the liver and intestine by carboxylesterases. Oxidative metabolism, catalyzed mainly by CYP2C8 and to a smaller extent by CYP3A4, leads to the formation of hydroxylated and dealkylated products. UGT1A3 and UGT2B7 are involved in the glucuronidation of the active metabolite. Except for the active metabolite, none of the circulating metabolites in human plasma exceeds 3% of the total drug-related material.
Elimination
Elimination of selexipag is predominately via metabolism with a mean terminal half-life of 0.8–2.5 hours. The terminal half-life of the active metabolite is 6.2–13.5 hours. Selexipag does not accumulate following twice daily repeat administration. There is minimal accumulation of the active metabolite upon twice daily repeat administration suggesting that the effective half-life is in the range of 3–4 hours. The total body clearance of selexipag is 17.9 L/hour.
Excretion
In a study in healthy subjects with radiolabeled selexipag, approximately 93% of radioactive drug material was eliminated in feces and only 12% in urine. Neither selexipag nor its active metabolite were found in urine.
Specific Populations
No clinically relevant effects of sex, race, age or body weight on the pharmacokinetics of selexipag and its active metabolite have been observed in healthy subjects or PAH patients.
Pediatric Patients
In pediatric patients aged 2 to 17 years with PAH, the applied body weight adjusted dosing regimen in clinical studies resulted in a combined exposure of selexipag and its active metabolite comparable to that observed in adult PAH patients [see Dosage and Administration (2.1) and Clinical Studies (14.2)].
Geriatric Patients
The pharmacokinetic variables (Cmax and AUC) were similar in adult and elderly subjects up to 75 years of age. There was no effect of age on the pharmacokinetics of selexipag and the active metabolite in PAH patients.
Hepatic Impairment
In subjects with mild (Child-Pugh class A) or moderate (Child-Pugh class B) hepatic impairment, exposure to selexipag was 2- and 4-fold that seen in healthy subjects. Exposure to the active metabolite of selexipag remained almost unchanged in subjects with mild hepatic impairment and was doubled in subjects with moderate hepatic impairment [see Use in Specific Populations (8.6)].
Based on pharmacokinetic modeling of data from a study in subjects with hepatic impairment, the exposure to the active metabolite at steady-state in subjects with moderate hepatic impairment (Child-Pugh class B) after a once daily regimen is expected to be similar to that in healthy subjects receiving a twice daily regimen. The exposure to selexipag at steady-state in these patients during a once daily regimen is predicted to be approximately 2-fold that seen in healthy subjects receiving a twice-daily regimen.
Renal Impairment
A 40–70% increase in exposure (maximum plasma concentration and area under the plasma concentration-time curve) to selexipag and its active metabolite was observed in subjects with severe renal impairment (estimated glomerular filtration rate ≥15 mL/min and <30 mL/min) [see Use in Specific Populations (8.7)].
Drug Interaction Studies
Drug interaction studies have been performed in adult subjects using UPTRAVI tablets.
In Vitro Studies
Selexipag is hydrolyzed to its active metabolite by carboxylesterases. Selexipag and its active metabolite both undergo oxidative metabolism mainly by CYP2C8 and to a smaller extent by CYP3A4. The glucuronidation of the active metabolite is catalyzed by UGT1A3 and UGT2B7. Selexipag and its active metabolite are substrates of OATP1B1 and OATP1B3. Selexipag is a substrate of P-gp, and the active metabolite is a substrate of the transporter of breast cancer resistance protein (BCRP).
Selexipag and its active metabolite do not inhibit or induce cytochrome P450 enzymes and transport proteins at clinically relevant concentrations.
The results of in vivo drug interaction studies are presented in Figures 1 and 2.
Figure 1 Effect of Other Drugs on Selexipag and its Active Metabolite
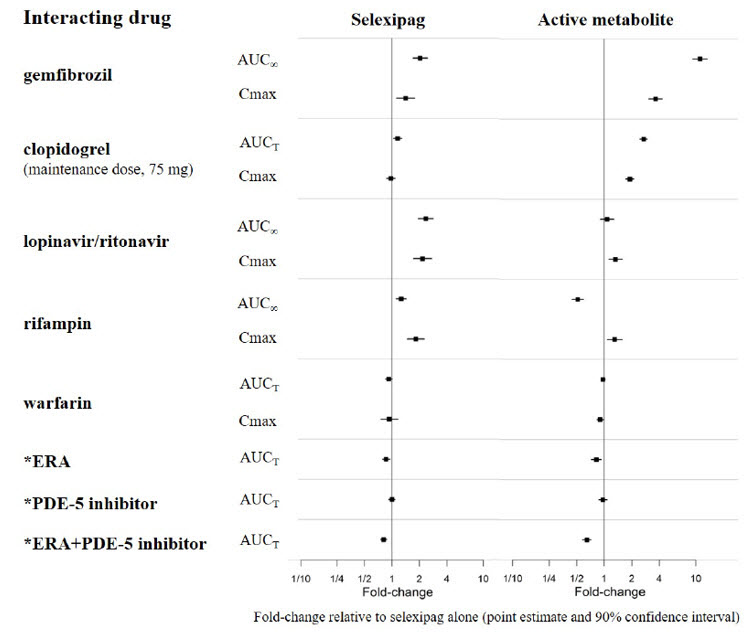
Figure 1 (Uptravi 04)
* ERA and PDE-5 inhibitor data from GRIPHON.
Figure 2 Effect of UPTRAVI on Other Drugs
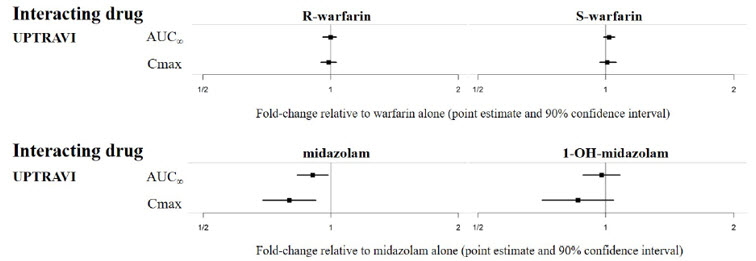
Figure 2 (Uptravi 05)
Carcinogenesis: In the 2-year carcinogenicity studies, chronic oral administration of selexipag revealed no evidence of carcinogenic potential in rats at 100 mg/kg/day and mice at 500 mg/kg/day which resulted in the exposures to the active metabolite more than 25 times the human exposure at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis.
Mutagenesis: Selexipag and the active metabolite are not genotoxic on the basis of the overall evidence of conducted genotoxicity studies.
Fertility: In rats administered with selexipag orally, the no effect dose for effects on fertility was 60 mg/kg/day which resulted in the exposure to the active metabolite approximately 175 times the human exposure at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis.
6-Minute Walk Distance (6MWD)
Exercise capacity was evaluated as a secondary endpoint. Median absolute change from baseline to week 26 in 6MWD measured at trough (i.e., at approximately 12 hours post-dose) was +4 meters with UPTRAVI and -9 meters in the placebo group. This resulted in a placebo-corrected median treatment effect of 12 meters (99% CI: 1, 24 meters; two-sided p = 0.005).
Long-Term Treatment of PAH
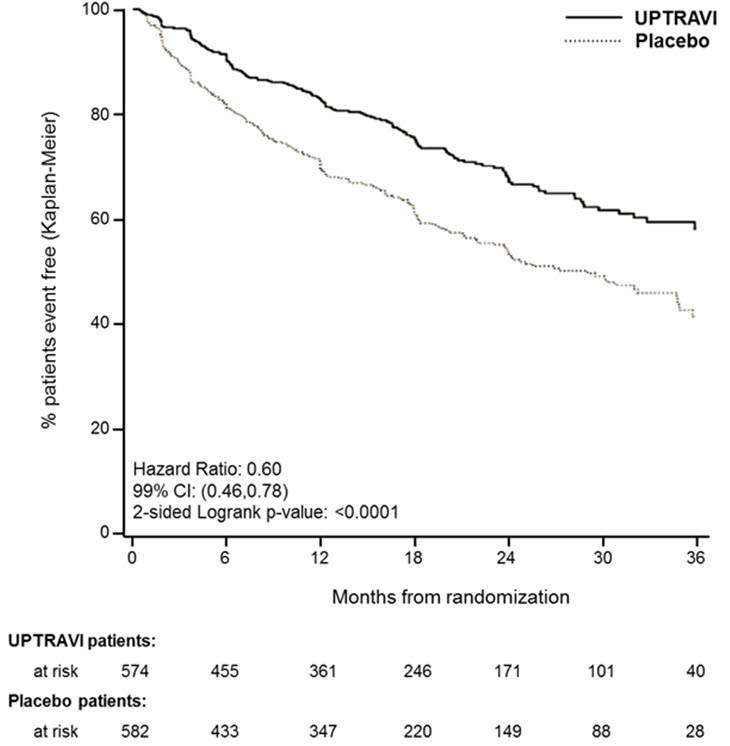
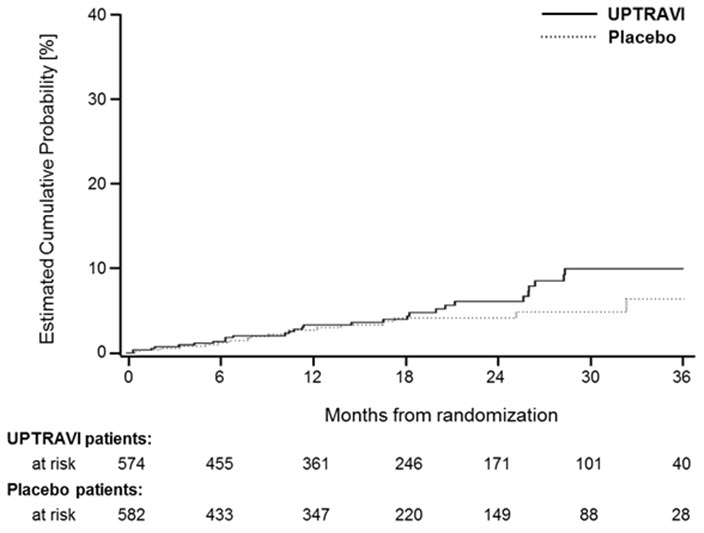
In long-term follow-up of patients who were treated with UPTRAVI in the pivotal study and the open-label extension (N=574), Kaplan-Meier estimates of survival of these patients across the GRIPHON study and the long-term extension study at 1, 2, 5 and 7 years were 92%, 85%, 71%, and 63%, respectively. The median exposure to UPTRAVI was 3 years. These uncontrolled observations do not allow comparison with a control group not given UPTRAVI and cannot be used to determine the long-term effect of UPTRAVI on mortality.
NT-proBNP
UPTRAVI improved outcomes and reduced NT-proBNP in adults in GRIPHON. Therefore, the effect on NT-proBNP was used to infer a delay in PAH disease progression and reduce the risk of hospitalizations in pediatric patients aged 2 years and older.
In pediatric patients aged ≥2 to <18 years (SALTO), NT-proBNP change from baseline to week 24 was evaluated. The median NT-proBNP concentration at baseline was 231 ng/L in the UPTRAVI group and 168 ng/L in the placebo group. The placebo-adjusted reduction in NT-proBNP for the study population was 7% (geometric mean ratio of 0.93 [95% CI: 0.71, 1.21]). Among patients with baseline levels ≥300 ng/L (n=51), treatment with UPTRAVI resulted in a placebo-adjusted reduction in NT-proBNP of 26% (geometric mean ratio of 0.74 [95% CI: 0.46, 1.21]). Among patients with baseline levels <300 ng/L (n=86) treatment with UPTRAVI resulted in a placebo‑adjusted increase in NT‑proBNP of 5% (geometric mean ratio of 1.05 [95% CI: 0.80, 1.37]).
Inform Patients
Manufactured for:
Actelion Pharmaceuticals US, Inc.
Titusville, NJ 08560, USA
For patent information: www.janssenpatents.com
© Johnson & Johnson and its affiliates, 2015 – 2021, 2026.