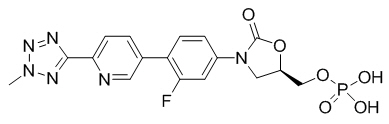
- Reconstitute the SIVEXTRO vial with 4 mL of Sterile Water for Injection to provide a concentration of 50 mg/mL in each vial.
- Gently swirl the contents and let the vial stand until the cake has completely dissolved and any foam disperses.
- Inspect the vial to ensure the solution contains no particulate matter and no cake or powder remains attached to the sides of the vial. If necessary, invert the vial to dissolve any remaining powder and swirl gently to prevent foaming. The reconstituted solution is clear and colorless to pale-yellow in color; the total time from reconstitution to the end of administration should not exceed 24 hours at either room temperature or under refrigeration at 2°C to 8°C (36°F to 46°F).
Prepare a stock solution (100 mL of 0.8 mg/mL tedizolid phosphate): Tilt the upright vial and insert a syringe with appropriately sized needle into the bottom corner of the vial and remove 1.6 mL of the reconstituted solution and add it to an infusion bag containing 98.4 mL of 0.9% Sodium Chloride Injection, USP or 5% Dextrose Injection, USP. Do not invert the vial during extraction. - Prepare the required volume of stock solution for infusion: Refer to Table 4 to convert the dose in mg to the appropriate volume of stock solution to be administered. Transfer this volume of stock solution to an adequately sized infusion bag or infusion syringe. It may be necessary to round to the nearest graduation mark of an appropriately sized syringe for smaller volumes. The total time from reconstitution to the end of administration should not exceed 24 hours at either room temperature or under refrigeration at 2°C to 8°C (36°F to 46°F).
Table 4: Preparation of SIVEXTRO for Injection for Pediatric Patients Weighing 1 kg to Less than 35 kg from the 100 mL Stock Solution of 0.8 mg/mL Tedizolid Phosphate| Body Weight (kg) | Amount of SIVEXTRO per dose
(given twice daily) | Volume of stock solution (0.8 mg/mL) to be transferred to an adequately sized infusion bag or infusion syringe |
|---|
| Pediatric Patients Weighing Less than 2 kg |
| 1 to less than 2 | 3 mg/kg | Volume (mL) = Weight (kg) x 3.75 mL/kg |
| Pediatric Patients Weighing at Least 2 kg |
| 2 to less than 3 | 6 mg | 7.5 mL |
| 3 to less than 6 | 12 mg | 15 mL |
| 6 to less than 10 | 20 mg | 25 mL |
| 10 to less than 14 | 30 mg | 37.5 mL |
| 14 to less than 20 | 40 mg | 50 mL |
| 20 to less than 35 | 60 mg | 75 mL |
Administration of SIVEXTRO for Injection
Administer SIVEXTRO for Injection as an intravenous infusion only.
Do not administer as an intravenous push or bolus. Do not mix SIVEXTRO for Injection with other drugs when administering. It is not intended for intra-arterial, intramuscular, intrathecal, intraperitoneal, or subcutaneous administration.
The intravenous bag containing the reconstituted and diluted intravenous solution should be inspected visually for particulate matter prior to administration. Discard if visible particles are observed. The resulting solution is clear and colorless to pale-yellow in color.
After reconstitution and dilution, SIVEXTRO for Injection is to be administered via intravenous infusion using a total time of 1 hour.
The total time from reconstitution to the end of administration of SIVEXTRO for Injection should not exceed 24 hours at either room temperature or under refrigeration at 2°C to 8°C (36°F to 46°F).
Discard unused portion.
Serious Adverse Reactions and Adverse Reactions Leading to Discontinuation in Adults
Serious adverse reactions occurred in 37/1425 (2.6%) of adult patients treated with SIVEXTRO and in 25/1000 (2.5%) of adult patients treated with the comparator. SIVEXTRO was discontinued due to an adverse reaction in 14/1425 (1%) of adult patients and the comparator was discontinued due to an adverse reaction in 13/1000 (1.3%) of adult patients.
Most Common Adverse Reactions in Adults
The most common adverse reactions in adult patients treated with SIVEXTRO were nausea (7.1%), headache (4.5%), diarrhea (3.6%), vomiting (2.7%), and dizziness (1.6%). The median time of onset of adverse reactions was 5 days for both SIVEXTRO and linezolid with 12% occurring on the second day of treatment in both treatment groups.
Table 5 lists selected adverse reactions occurring in at least 2% of adult patients treated with SIVEXTRO in clinical trials.
Table 5: Selected Adverse Reactions Occurring in ≥2% of Adult Patients Receiving SIVEXTRO in the Pooled Phase 3 ABSSSI Clinical Trials| Adverse Reactions | Pooled Phase 3 ABSSSI Clinical Trials |
|---|
SIVEXTRO
(200 mg oral/intravenous once daily for 6 days)
(N=1037) | Linezolid
(600 mg oral/intravenous twice daily for 10 days)
(N=1000) |
|---|
| Gastrointestinal Disorders |
| Nausea | 7% | 10% |
| Diarrhea | 4% | 5% |
| Vomiting | 3% | 5% |
| Nervous System Disorder |
| Headache | 5% | 5% |
| Dizziness | 2% | 2% |
| Infusion- or Injection-Related Adverse Reactions Includes adverse reactions in the following body system or organ classes: General disorders and administration site conditions, infections and infestations, injury, poisoning and procedural complications, and vascular disorders, including but not limited to, phlebitis, injection- or infusion-site pain, injection- or infusion-site swelling, injection-site reaction, injection-site erythema, injection-site induration, and infusion-related reaction. |
| 4% | 2% |
The following selected adverse reactions were reported in SIVEXTRO-treated adult patients at a rate of less than 2% in these clinical trials:
Blood and Lymphatic System Disorders: anemia
Cardiovascular: palpitations, tachycardia
Eye Disorders: asthenopia, vision blurred, visual impairment, vitreous floaters
Immune System Disorders: drug hypersensitivity
Infections and Infestations: Clostridioides difficile colitis, oral candidiasis, vulvovaginal mycotic infection
Investigations: hepatic transaminases increased (ALT increased, AST increased), gamma-glutamyltransferase (GGT) increased, white blood cell count decreased
Nervous System Disorders: hypoesthesia, paresthesia, VIIth nerve paralysis
Psychiatric Disorders: insomnia
Skin and Subcutaneous Tissue Disorders: pruritus, urticaria, dermatitis
Vascular Disorders: flushing, hypertension
Laboratory Parameters
Hematology laboratory abnormalities that were determined to be potentially clinically significant in the pooled Phase 3 ABSSSI clinical trials are provided in Table 6.
Table 6: Potentially Clinically Significant Lowest Laboratory Values in the Pooled Phase 3 ABSSSI Clinical Trials in Adults| Laboratory Assay | Potentially Clinically Significant Values <75% (<50% for absolute neutrophil count) of lower limit of normal (LLN) for post-baseline measurements ,Represents laboratory values within two days after the last dose of active drug |
|---|
SIVEXTRO
(200 mg oral/intravenous once daily for 6 days)
(N)Number of subjects with at least one post-baseline test result that are within two days after the last dose of active drug | Linezolid
(600 mg oral/intravenous twice daily for 10 days)
(N) |
|---|
| M = male; F = female |
Hemoglobin
(<10.1 g/dL [M])
(<9 g/dL [F]) | (994)
3.4% | (957)
3.4% |
Platelet count
(<112 × 103/mm3) | (989)
2.1% | (950)
3.8% |
Absolute neutrophil count
(<0.8 × 10³/mm3) | (980)
0.4% | (941)
0.6% |
Myelosuppression
Phase 1 studies conducted in healthy adults exposed to SIVEXTRO for 21 days showed a possible dose and duration effect on hematologic parameters beyond 6 days of treatment. In the Phase 3 trials, clinically significant changes in these parameters were generally similar for both treatment arms (see Table 6). In postmarketing experience, thrombocytopenia has been reported in patients treated with SIVEXTRO. In one postmarketing report, patients who experienced thrombocytopenia were treated with tedizolid for a median duration of 26.5 days. A duration of treatment beyond 6 days is not approved.
Peripheral and Optic Neuropathy
Peripheral and optic neuropathy have been described in patients treated with another member of the oxazolidinone class for longer than 28 days. In Phase 3 trials in adults, reported adverse reactions for peripheral neuropathy and optic nerve disorders were similar between both treatment arms (peripheral neuropathy 1.2% vs. 0.7% for tedizolid phosphate and linezolid, respectively; optic nerve disorders 0.3% vs. 0.1%, respectively).
Clinical Trials Experience in Pediatric Patients
SIVEXTRO was evaluated in 166 pediatric patients with ABSSSI in two randomized, active-controlled clinical trials, including one in patients aged 12 years to less than 18 years and one in patients aged 4 months to less than 12 years (Pediatric Trial 1 and Pediatric Trial 2, respectively). Additionally, SIVEXTRO was evaluated in 47 pediatric patients less than 2 years of age with a suspected or confirmed gram-positive bacterial infection in an open-label clinical trial (pediatric Trial 3).
Pediatric Trial 1
Adverse Reactions
Pediatric Trial 1 was a randomized, active-controlled, single-blind clinical trial that enrolled pediatric patients aged 12 to less than 18 years with ABSSSI. A total of 91 pediatric patients were treated with IV and/or oral SIVEXTRO 200 mg for 6 days and 29 patients were treated with a comparator agent for 10 days. The majority of pediatric patients treated with SIVEXTRO were male (64%) and white (88%).
Serious adverse reactions occurred in 1/91 (1%) of pediatric patients treated with SIVEXTRO and in none of the 29 patients treated with the comparator. Adverse reactions leading to discontinuation occurred in 1 (1%) pediatric patient in the SIVEXTRO arm and in none in the comparator arm.
The most common adverse reactions occurring in those receiving SIVEXTRO in Pediatric Trial 1 were phlebitis (3%), increased hepatic transaminases (alanine aminotransferase, aspartate aminotransferase) (3%), anemia (1%), and vomiting (1%).
Laboratory Parameters
Table 7: Potentially Clinically Significant Lowest Laboratory Values in the ABSSSI Clinical Trial in Pediatric Patients (12 to <18 years)| Laboratory Assay | Potentially Clinically Significant Values <75% (<50% for absolute neutrophil count) of lower limit of normal (LLN) for post-baseline measurements ,Represents laboratory values within two days after the last dose of active drug |
|---|
SIVEXTRO
(200 mg oral/intravenous
once daily for 6 days)
(N)Number of subjects with at least one post-baseline test result that are within two days after the last dose of active drug | Comparators 5 IV and 4 oral comparators selected per local standard of care
(for 10 days)
(N) |
|---|
| M = male; F = female |
Hemoglobin
(<10.1 g/dL [M])
(<9 g/dL [F]) | (85)
2.4% | (26)
0.0% |
Platelet count
(<112 × 103/mm3) | (82)
1.2% | (26)
0.0% |
Absolute neutrophil count
(<0.8 × 10³/mm3) | (85)
0.0% | (26)
0.0% |
Pediatric Trial 2
Pediatric Trial 2 was a randomized, active-controlled, single-blind clinical trial that enrolled pediatric patients aged 4 months to less than 12 years with ABSSSI. A total of 75 patients were treated with IV and/or oral SIVEXTRO for 6 to 10 days and 25 were treated with a comparator agent for 10 to 14 days. The oral suspension formulation (currently not an approved formulation) was used in the clinical trial for those receiving oral therapy [see Clinical Studies (14.1)]. The majority of patients treated with SIVEXTRO were male (53%) and white (77%), with a median age of 7 years and range of 0.3 to 11 years. The most common adverse reactions occurring in >2% of patients receiving SIVEXTRO in Pediatric Trial 2 were infusion- or injection-related adverse reactions (including catheter site pain, catheter occlusion, infusion site extravasation, phlebitis; 5%), and vomiting (4%).
Potentially clinically significant laboratory abnormalities in Pediatric Trial 2 included one patient treated with SIVEXTRO who developed thrombocytopenia with platelet count less than 100 × 103/mm3.
Pediatric Trial 3
Pediatric Trial 3 was an open-label, pharmacokinetic and safety trial enrolling 47 pediatric patients less than 2 years of age as follows: ages 28 days to less than 2 years (N=14), term neonates from birth to less than 28 days (N=16), and pre-term neonates (gestational age ≥ 26 weeks) from birth to less than 28 days (N=17). In this single-arm trial, 39 patients aged less than 2 years with a suspected or confirmed gram-positive bacterial infection received a single-dose of IV or oral SIVEXTRO and 8 patients aged less than 28 days with a suspected or confirmed gram-positive bacterial infection received multiple doses of IV SIVEXTRO for 3 days. The majority of patients were male (62%) and white (55%), with a median age of 16 days (range 1 day to 608 days).
The safety profile observed in this pediatric population was similar to that observed in Pediatric Trials 1 and 2.
Risk Summary
Based on animal reproduction studies, SIVEXTRO may cause fetal harm when administered to pregnant women. The available data on the use of SIVEXTRO in pregnant women are insufficient to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Advise pregnant women of the potential risks to a fetus. Fetal developmental toxicities were observed in mice and rats treated with SIVEXTRO. In embryo-fetal studies in mice and rats, tedizolid phosphate was shown to produce fetal developmental toxicities in mice and maternal toxicity and fetal developmental toxicities in rats. Tedizolid phosphate administered orally during organogenesis to pregnant animals was associated with reduced fetal weights and an increased incidence of costal cartilage anomalies in the absence of maternal toxicity in mice; and maternal toxicity, decreased fetal weights, and increased skeletal variations in rats at plasma exposures approximately 4 and 6 times respectively, the human plasma exposure at the maximum recommended human dose (MRHD) of 200 mg/day. In female rats administered tedizolid phosphate during organogenesis through lactation, there was no evidence of fetal toxicity, developmental delays, or impaired reproduction in the offspring at plasma exposures approximately equivalent to the human plasma exposure at the MRHD. (see Data)
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data
Animal Data
In an embryo-fetal development study, tedizolid phosphate administered orally to pregnant mice at doses of 1, 5, and 25 mg/kg/day during organogenesis (Gestational Day [GD] 6 to GD15) was associated with fetal developmental effects occurring in the absence of maternal toxicity, including reduced fetal weights and an increased incidence of costal cartilage anomalies at the high dose (approximately 4-times the human plasma exposure at the MRHD based on plasma AUC comparison). Tedizolid phosphate administered orally at doses of 2.5, 5, and 15 mg/kg/day to pregnant rats during organogenesis (GD6 through GD17) was associated with maternal toxicity (reduced maternal body weights), decreased fetal weights, and increased skeletal variations including reduced ossification of the sternebrae, vertebrae, and skull at the high dose of 15 mg/kg/day (approximately 6-times the human plasma exposure at the MRHD based on plasma AUC comparison). The doses not associated with fetal toxicity in mice and maternal and fetal toxicity in rats were 5 and 2.5 mg/kg/day respectively (for both species approximately equivalent to the human plasma exposure at the MRHD based on plasma AUC comparison).
In a pre-postnatal study, oral tedizolid phosphate administered to female rats at doses of 1.25, 2.5, and 3.75 mg/kg/day during gestation and lactation (GD6 through Lactational Day 20) was not associated with maternal toxicity, fetal toxicity, developmental delays, or impaired reproduction at doses up to the high dose of 3.75 mg/kg/day (approximately equivalent to the human plasma exposure at the MRHD based on plasma AUC comparison).
Risk Summary
There is no information on the presence of tedizolid in human milk. Tedizolid is present in rat milk. When a drug is present in animal milk, it is likely that the drug will be present in human milk. There are no data on the effects of SIVEXTRO on the breastfed child or on milk production.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for SIVEXTRO and any potential adverse effects on the breastfed child from SIVEXTRO or from the underlying maternal condition.
Cardiac Electrophysiology
In a randomized, positive- and placebo-controlled crossover thorough QTc study, 48 enrolled subjects were administered a single oral dose of SIVEXTRO at a therapeutic dose of 200 mg, SIVEXTRO at a supratherapeutic dose of 1200 mg, placebo, and a positive control; no significant effects of SIVEXTRO on heart rate, electrocardiogram morphology, PR, QRS, or QT interval were detected. Therefore, SIVEXTRO does not affect cardiac repolarization.
Absorption
Peak plasma tedizolid concentrations are achieved within approximately 3 hours following oral administration of the oral tablet under fasting conditions or at the end of the 1 hour intravenous infusion of tedizolid phosphate. The absolute bioavailability of the oral tablet is approximately 91% and no dosage adjustment is necessary between intravenous and oral administration.
Tedizolid phosphate (oral tablet) may be administered with or without food as total systemic exposure (AUC0-∞) is unchanged between fasted and fed (high-fat, high-calorie) conditions.
Distribution
Protein binding of tedizolid to human plasma proteins is approximately 70 to 90%. The mean steady state volume of distribution of tedizolid in healthy adults following a single intravenous dose of tedizolid phosphate 200 mg ranged from 67 to 80 L (approximately twice total body water). Tedizolid penetrates into the interstitial space fluid of adipose and skeletal muscle tissue with exposure similar to free drug exposure in plasma.
Elimination
Metabolism
Other than tedizolid, which accounts for approximately 95% of the total radiocarbon AUC in plasma, there are no other significant circulating metabolites in humans.
There was no degradation of tedizolid in human liver microsomes indicating tedizolid is unlikely to be a substrate for hepatic CYP450 enzymes.
In vitro studies showed that conjugation of tedizolid is mediated via multiple sulfotransferase (SULT) isoforms (SULT1A1, SULT1A2, and SULT2A1).
Excretion
Following single oral administration of 14C-labeled tedizolid phosphate under fasted conditions in adult healthy volunteers, the majority of elimination occurred via the liver, with 82% of the radioactive dose recovered in feces and 18% in urine, primarily as a non-circulating and microbiologically inactive sulfate conjugate. Most of the elimination of tedizolid (>85%) occurs within 96 hours. Less than 3% of the tedizolid phosphate-administered dose is excreted in feces and urine as unchanged tedizolid.
Specific Populations
Based on the population pharmacokinetic analysis, there are no clinically relevant demographic or clinical patient factors (including age, gender, race, ethnicity, weight, body mass index, and measures of renal or liver function) that impact the pharmacokinetics of tedizolid.
Patients with Hepatic Impairment
Following administration of a single 200 mg oral dose of SIVEXTRO, no clinically meaningful changes in mean tedizolid Cmax and AUC0-∞ were observed in adult patients with moderate (n=8) or severe (n=8) hepatic impairment (Child-Pugh Class B and C) compared to 8 matched healthy control subjects. No dose adjustment is necessary for patients with hepatic impairment.
Patients with Renal Impairment
Following administration of a single 200 mg intravenous dose of SIVEXTRO to 8 adult subjects with severe renal impairment defined as eGFR <30 mL/min/1.73 m2, the Cmax was essentially unchanged and AUC0-∞ was decreased by less than 10% compared to 8 matched healthy control adult subjects. Hemodialysis does not result in meaningful removal of tedizolid from systemic circulation, as assessed in subjects with end-stage renal disease (eGFR <15 mL/min/1.73 m2). No dosage adjustment is necessary in patients with renal impairment or patients on hemodialysis.
Geriatric Patients
The pharmacokinetics of tedizolid were evaluated in a Phase 1 study conducted in elderly healthy volunteers (age 65 years and older, with at least 5 subjects at least 75 years old; n=14) compared to younger control subjects (25 to 45 years old; n=14) following administration of a single oral dose of SIVEXTRO 200 mg. There were no clinically meaningful differences in tedizolid Cmax and AUC0-∞ between elderly subjects and younger control subjects. No dosage adjustment of SIVEXTRO is necessary in elderly patients.
Male and Female Patients
The impact of gender on the pharmacokinetics of SIVEXTRO was evaluated in clinical trials of adult healthy males and females and in a population pharmacokinetics analysis. The pharmacokinetics of tedizolid were similar in males and females. No dosage adjustment of SIVEXTRO is necessary based on gender.
Pediatric Patients
The pharmacokinetics of tedizolid was evaluated in clinical studies in pediatric patients from birth (includes neonates who are at least 26 weeks gestational age and weighing at least 1 kg) to less than 18 years of age (N=249).
Compared to adult patients, tedizolid exposures are higher in pediatric patients (12 to <18 years of age, mean weight: 59.7 kg, weight range: 28 kg to 126 kg in Pediatric Trial 1) following multiple dose administration of a once daily dose of 200 mg IV or oral SIVEXTRO (geometric mean Cmax 3.1 vs. 2.0 mcg/mL, AUC24h 28.6 vs. 21.0 mcg*h/mL); however, this increase in exposure is not considered clinically significant.
The predicted steady state mean pharmacokinetic parameters of tedizolid by the pediatric weight-based dosage in Table 2 and Table 3 are shown in Table 9.
Table 9: Geometric Mean (% CV) Predicted Steady-State Exposures Following Multiple Dose Administration of IV or Oral Tedizolid Phosphate Based Upon the Weight-Banded Dosage in Pediatric Patients BirthPediatric patients from birth (includes neonates at least 26 weeks gestational age).
to Less than 18 Years| Weight (kg) | Dosage Regimen | Total Daily Dose | Route | Steady-State AUC24h (mcg·hr/mL) AUC0-24 = 2 X AUC0-12 for twice daily dosing. | Steady-State Cmax (mcg/mL) |
|---|
| AUC, area under the concentration-time curve; Cmax, maximum concentration; %CV, coefficient of variation. |
| 1 to less than 2 | 3 mg/kg
Twice daily | 6 mg to less than12 mg | IV | 33.1 (29.8) | 2.3 (17.2) |
| 2 to less than 3 | 6 mg
Twice daily | 12 mg | IV | 20.8 (25.6) | 1.8 (15.9) |
| 3 to less than 6 | 12 mg
Twice daily | 24 mg | IV | 26.4 (34.4) | 2.4 (20.7) |
| 6 to less than 10 | 20 mg
Twice daily | 40 mg | IV | 22.5 (43.9) | 2.2 (20.4) |
| 10 to less than 14 | 30 mg
Twice daily | 60 mg | IV | 27.6 (32.1) | 2.7 (19.6) |
| 14 to less than 20 | 40 mg
Twice daily | 80 mg | IV | 28.4 (22.1) | 2.7 (13.0) |
| 20 to less than 35 | 60 mg
Twice daily | 120 mg | IV | 31.4 (29.9) | 2.6 (21.6) |
| At least 35 | 200 mg
Once daily | 200 mg | IV | 30.6 (29.7) | 3.8 (23.9) |
| Oral (tablet) | 29.3 (29.7) | 2.5 (24.4) |
Drug Interaction Studies
Drug Metabolizing Enzymes
Transformation via Phase 1 hepatic oxidative metabolism is not a significant pathway for elimination of SIVEXTRO.
Neither SIVEXTRO nor tedizolid detectably inhibited or induced the metabolism of selected CYP enzyme substrates, suggesting that drug-drug interactions based on oxidative metabolism are unlikely.
Membrane Transporters
Coadministration of multiple oral doses of SIVEXTRO (200 mg once daily) increased the Cmax and AUC of rosuvastatin (10 mg single oral dose), a known BCRP substrate, by approximately 55% and 70%, respectively, in healthy adult subjects [see Drug Interactions (7)].
No clinically relevant interactions are expected to occur with drug efflux transporter P-gp and drug uptake transporters OAT1, OAT3, OATP1B1, OATP1B3, OCT1, and OCT2 based on in vitro studies.
Monoamine Oxidase Inhibition
Tedizolid is a reversible inhibitor of monoamine oxidase (MAO) in vitro. The interaction with MAO inhibitors could not be evaluated in Phase 2 and 3 trials, as subjects taking such medications were excluded from the trials.
Adrenergic Agents
Two placebo-controlled crossover studies were conducted to assess the potential of 200 mg oral SIVEXTRO at steady state to enhance pressor responses to pseudoephedrine and tyramine in healthy adults. No meaningful changes in blood pressure or heart rate were seen with pseudoephedrine. The median tyramine dose required to cause an increase in systolic blood pressure of ≥30 mmHg from pre-dose baseline was 325 mg with SIVEXTRO compared to 425 mg with placebo. Palpitations were reported in 21/29 (72.4%) adult subjects exposed to SIVEXTRO compared to 13/28 (46.4%) exposed to placebo in the tyramine challenge study.
Serotonergic Agents
In Phase 3 trials, subjects taking serotonergic agents including antidepressants such as selective serotonin reuptake inhibitors (SSRIs), tricyclic antidepressants, and serotonin 5-hydroxytryptamine (5-HT1) receptor agonists (triptans), meperidine, or buspirone were excluded [see Drug Interactions (7) and Warnings and Precautions (5.1)].
Mechanism of Action
The antibacterial activity of tedizolid is mediated by binding to the 50S subunit of the bacterial ribosome resulting in inhibition of protein synthesis. Tedizolid inhibits bacterial protein synthesis through a mechanism of action different from that of other non-oxazolidinone class antibacterial drugs; therefore, cross-resistance between tedizolid and other classes of antibacterial drugs is unlikely. The results of in vitro time-kill studies show that tedizolid is bacteriostatic against enterococci, staphylococci, and streptococci.
Resistance
Organisms resistant to oxazolidinones via mutations in chromosomal genes encoding 23S rRNA or ribosomal proteins (L3 and L4) are generally cross-resistant to tedizolid. In the limited number of Staphylococcus aureus strains tested, the presence of the chloramphenicol-florfenicol resistance (cfr) gene did not result in resistance to tedizolid in the absence of chromosomal mutations. Mutations in 23SrRNA (G2576T mutation) have been associated with tedizolid resistance in S. aureus isolates.
Spontaneous mutations conferring reduced susceptibility to tedizolid occur in vitro at a frequency rate of approximately 10-10.
Interaction with Other Antimicrobial Drugs
In vitro drug combination studies with tedizolid and aztreonam, ceftriaxone, ceftazidime, imipenem, rifampin, trimethoprim/sulfamethoxazole, minocycline, clindamycin, ciprofloxacin, daptomycin, vancomycin, gentamicin, amphotericin B, ketoconazole, and terbinafine demonstrate neither synergy nor antagonism.
Antimicrobial Activity
Tedizolid has been shown to be active against most isolates of the following bacteria, both in vitro and in clinical infections, as described in Indications and Usage (1).
Aerobic bacteria
Gram-positive bacteria
- Staphylococcus aureus (including methicillin-resistant [MRSA] and methicillin-susceptible [MSSA] isolates)
- Streptococcus pyogenes
- Streptococcus agalactiae
- Streptococcus anginosus Group (including S. anginosus, S. intermedius, and S. constellatus)
- Enterococcus faecalis
The following in vitro data are available, but their clinical significance is unknown. At least 90% of the following bacteria exhibit an in vitro minimum inhibitory concentration (MIC) less than or equal to the susceptible breakpoint for tedizolid against isolates of similar genus or organism group. However, the efficacy of SIVEXTRO in treating clinical infections caused by these bacteria has not been established in adequate and well-controlled clinical trials.
Aerobic bacteria
Gram-positive bacteria
- Staphylococcus epidermidis (including methicillin-susceptible and methicillin-resistant isolates)
- Staphylococcus haemolyticus
- Staphylococcus lugdunensis
- Enterococcus faecium
Susceptibility Testing
For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC
Carcinogenicity
Long-term carcinogenicity studies have not been conducted with tedizolid phosphate.
Mutagenesis
Tedizolid phosphate was negative for genotoxicity in all in vitro assays (bacterial reverse mutation (Ames), Chinese hamster lung (CHL) cell chromosomal aberration) and in all in vivo tests (mouse bone marrow micronucleus, rat liver unscheduled DNA synthesis). Tedizolid, generated from tedizolid phosphate after metabolic activation (in vitro and in vivo), was also tested for genotoxicity. Tedizolid was positive in an in vitro CHL cell chromosomal aberration assay, but negative for genotoxicity in other in vitro assays (Ames, mouse lymphoma mutagenicity) and in vivo in a mouse bone marrow micronucleus assay.
Impairment of Fertility
In a fertility study, oral tedizolid phosphate administered in doses of 5, 15, and 50 mg/kg/day for 28 days before mating and during mating to male rats had no adverse effects on the fertility or reproductive performance, including spermatogenesis, at the maximum tested dose (50 mg/kg/day) with a plasma tedizolid AUC approximately 5-fold greater than the plasma AUC value in humans at the maximum recommended human dose (MRHD). Tedizolid phosphate administered in doses of 2.5, 5, and 15 mg/kg/day for 14 days before mating, during mating, and until Gestation Day (GD)7 to female rats also had no adverse effects on the fertility or reproductive performance at doses up to the maximum tested dose of 15 mg/kg/day (approximately 4-fold higher than exposures in humans at the MRHD based on plasma AUC comparison).
Serotonin Syndrome
Advise patients to inform their healthcare provider if they are taking serotonergic agents and of the increased risk of serotonin syndrome when SIVEXTRO is used concomitantly with serotonergic agents [see Warnings and Precautions (5.1)].
Potentially Serious Adverse Reactions
Advise patients that diarrhea is a common problem caused by antibacterial drugs including SIVEXTRO and usually resolves when the drug is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop frequent watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug and may be a sign of a more serious intestinal infection [see Warnings and Precautions (5.2) and Adverse Reactions (6.1)]. If this occurs, patients should contact their healthcare provider as soon as possible.
Antibacterial Resistance
Patients should be counseled that antibacterial drugs including SIVEXTRO should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When SIVEXTRO is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by SIVEXTRO or other antibacterial drugs in the future [see Warnings and Precautions (5.4)].
Administration with Food
Inform patients that SIVEXTRO Tablets may be taken with or without food and without any dietary restrictions [see Dosage and Administration (2.2, 2.3) and Clinical Pharmacology (12.3)].
Missed Doses
Inform patients that if they miss a SIVEXTRO oral dose, they should take the dose as soon as possible anytime up to 8 hours prior to their next scheduled dose. If less than 8 hours remains before the next dose, then they should wait until their next scheduled dose. Patients should take the prescribed number of doses [see Dosage and Administration (2.2, 2.3)].
Embryo-Fetal Toxicity
Based on animal data, advise pregnant women and females of reproductive potential of the potential risk of SIVEXTRO to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Use in Specific Populations (8.1)].
Manuf. for: Merck Sharp & Dohme LLC
Rahway, NJ 07065, USA
SIVEXTRO Tablets
Manufactured by: Patheon Inc.
Whitby, Ontario, L1N 5Z5 Canada
SIVEXTRO for Injection
Manufactured by: Patheon Italia S.p.A.
03013, Ferentino, FR Italy
For patent information: www.msd.com/research/patent
Copyright © 2015-2026 Merck & Co., Inc., Rahway, NJ, USA, and its affiliates.
All rights reserved.
uspi-mk1986-mf-2602r013