1.1 Treatment Of Invasive Aspergillosis
Posaconazole injection is indicated for the treatment of invasive aspergillosis in adults and pediatric patients 2 years of age and older who weigh 10 kg or greater.
The following Structured Product Label (SPL) was submitted to the FDA by Gland Pharma Limited for the product Posaconazole (NDC 68083-577). This document serves as the official prescribing information, containing essential scientific data and clinical materials required for healthcare providers and patients.
This specific version of the label includes detailed information regarding 1.1 treatment of invasive aspergillosis, 1.2 prophylaxis of invasive aspergillus and candida infections, 2.1 important administration instructions, 2.2 recommended dosage of posaconazole injection in adult patients, 2.3 recommended dosage of posaconazole injection for the treatment of invasive aspergillosis and prophylaxis of invasive aspergillus and candida infections in pediatric patients 2 years of age and older, 2.5 preparation of posaconazole injection, 2.6 administration of diluted posaconazole infusion solution, 2.11 dosage modifications in patients with renal impairment, and other regulatory disclosures. Use the navigation below to review specific sections of the FDA submission.
Posaconazole injection is indicated for the treatment of invasive aspergillosis in adults and pediatric patients 2 years of age and older who weigh 10 kg or greater.
Posaconazole injection is indicated for the prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised, such as hematopoietic stem cell transplant (HSCT) recipients with graft-versus-host disease (GVHD) or those with hematologic malignancies with prolonged neutropenia from chemotherapy as follows:
Posaconazole injection
The recommended dosage of posaconazole injection in adult patients for the treatment of invasive aspergillosis, prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised is shown in Table 1 [see Dosage and Administration (2.5, 2.6) and Clinical Pharmacology (12.3)].
Table 1: Recommended Dosage of Posaconazole Injection in Adult Patients
| Dosage | Duration of Therapy |
| Treatment of Invasive Aspergillosis* | |
| Posaconazole Injection: Loading dose: 300 mg posaconazole injection intravenously twice a day on the first day. Maintenance dose: 300 mg posaconazole injection intravenously once a day, starting on the second day. | Loading dose: 1 day Maintenance dose: Recommended total duration of therapy is 6 to 12 weeks. |
| Prophylaxis of Invasive Aspergillus and Candida Infections | |
| Posaconazole Injection: Loading dose: 300 mg posaconazole injection intravenously twice a day on the first day. Maintenance dose: 300 mg posaconazole injection intravenously once a day thereafter. | Loading dose: 1 day Maintenance dose: Duration of therapy is based on recovery from neutropenia or immunosuppression. |
| * Switching between the posaconazole injection and delayed-release tablets is acceptable. A loading dose is not required when switching between dosage forms. | |
The recommended dosage of posaconazole injection in pediatric patients 2 years of age and older who weigh 10 kg or greater for the treatment of invasive aspergillosis and prophylaxis of invasive Aspergillus and Candida infections is shown in Table 2 [see Dosage and Administration (2.5, 2.6) and Clinical Pharmacology (12.3)].
Table 2: Recommended Dosage of Posaconazole Injection for the Treatment of Invasive Aspergillosis* and Prophylaxis of Invasive Aspergillus and Candida Infections in Pediatric Patients (2 Years of Age and Older)
| Recommended Pediatric Dosage | Duration of Therapy |
| Posaconazole Injection (patients weighing 10 kg or greater): Loading dose: 6 mg/kg up to a maximum of 300 mg twice daily on the first day Maintenance dose: 6 mg/kg up to a maximum of 300 mg once daily, starting on the second day. | Treatment of invasive aspergillosis: Recommended total duration of therapy is 6 to 12 weeks. Prophylaxis of invasive Aspergillus and Candida infections: Duration of therapy is based on recovery from neutropenia or immunosuppression. |
| * Switching between the intravenous and delayed-release tablets is acceptable. A loading dose is not required when switching between formulations. | |
Preparation of Posaconazole Injection:
• Remove the vial of posaconazole injection from the refrigerator and allow to equilibrate to room temperature prior to use.
• To prepare the required dose, aseptically transfer one vial of posaconazole injection (containing 300 mg of posaconazole in 16.7 mL of solution) to an intravenous bag or bottle of one of the following compatible diluents to achieve a final posaconazole concentration between 1 mg/mL and 2 mg/mL:
o 0.45% Sodium Chloride Injection
o 0.9% Sodium Chloride Injection
o 5% Dextrose Injection
o 5% Dextrose and 0.45% Sodium Chloride Injection
o 5% Dextrose and 0.9% Sodium Chloride Injection
o 5% Dextrose and 20 mEq Potassium Chloride Injection
Use of other diluents is not recommended because they may result in particulate formation.
• Discard any unused posaconazole injection from the vial.
• Parenteral drug products should be inspected visually for particulate matter prior to administration, whenever solution and container permit. Once admixed, the diluted posaconazole infusion solution ranges from colorless to yellow (variations of color within this range do not affect the quality of the product).
• Immediately use the diluted posaconazole infusion solution, once admixed. If not used immediately, refrigerate (2 to 8°C (36 to 46°F)) the diluted posaconazole infusion solution up to 24 hours. Discard any unused portion.
Incompatible Diluents
Co-administration of drug products besides the infusion solutions or products stated above are not recommended because this may result in particulate formation. The following diluents were determined to be incompatible with posaconazole injection; thus, do not dilute posaconazole injection with them:
• Lactated Ringer’s Injection
• Lactated Ringer’s and 5% Dextrose Injection
• 4.2% Sodium Bicarbonate Injection
See Dosage and Administration (2.5) for the preparation instructions for the diluted Posaconazole Solution.
Important Administration Instructions for the Diluted Posaconazole Infusion Solution
• Must administer diluted posaconazole infusion solution through a 0.22-micron polyethersulfone (PES) or polyvinylidene difluoride (PVDF) filter.
• Administer diluted posaconazole infusion solution via a central venous line, including a central venous catheter (CVC) or peripherally inserted central catheter (PICC), by slow intravenous infusion over approximately 90 minutes [see Adverse Reactions (6.1)]
• If a CVC or PICC are not available, may administer diluted posaconazole solution once through a peripheral venous catheter by intravenous infusion over approximately 30 minutes to bridge the period during which a CVC or PICC are replaced, inserted, or unavailable for use (e.g., the CVC is being used for intravenous treatment with another product). However, do not administer diluted posaconazole infusion solution more than once via peripheral venous catheter because in clinical trials, multiple peripheral infusions given through the same vein resulted in infusion site reactions [see Adverse Reactions (6.1)].
• When multiple dosing is required, the infusion should be done via a central venous line.
Additional Administration Instructions for the Diluted Posaconazole Infusion Solution
• Administer diluted posaconazole infusion solution intravenously through the same intravenous line (or cannula) with the following compatible infusion solutions:
o 0.45% Sodium Chloride Injection
o 0.9% Sodium Chloride Injection
o 5% Dextrose Injection
o 5% Dextrose and 0.45% Sodium Chloride Injection
o 5% Dextrose and 0.9% Sodium Chloride Injection
o 5% Dextrose and 20 mEq potassium chloride Injection
• Administer diluted posaconazole infusion solution intravenously at the same time through the same intravenous line (or cannula) with the following intravenous drug products prepared in 5% Dextrose Injection or 0.9% Sodium Chloride Injection:
o Amikacin Sulfate Injection
o Caspofungin Acetate for Injection
o Ciprofloxacin Injection
o Daptomycin for Injection
o Dobutamine Injection
o Famotidine Injection
o Filgrastim Injection
o Gentamicin Injection
o Hydromorphone Hydrochloride Injection
o Levofloxacin Injection
o Lorazepam Injection
o Meropenem for Injection
o Micafungin for Injection
o Morphine Sulfate Injection
o Norepinephrine Bitartrate Injection
o Potassium Chloride Injection
o Vancomycin Hydrochloride for Injection
Avoid the use of posaconazole injection in patients with eGFR less than 50 mL/minute/1.73 m2, unless an assessment of the benefit/risk to the patient justifies its use. If the decision is made to use posaconazole injection in patients with eGFR less than 50 mL/minute/1.73 m2, closely monitor serum creatinine levels, and, if increases occur, consider changing to oral posaconazole therapy. The recommended dosage of posaconazole injection in patients with eGFR 50 to 90 mL/minute/1.73 m2 is the same as those with normal renal function.
Posaconazole injection
300 mg/16.7 mL (18 mg/mL) of posaconazole: Clear, colorless to yellow sterile liquid in a single-dose vial.
Posaconazole is contraindicated in persons with known hypersensitivity to posaconazole or other azole antifungal agents.
Posaconazole is contraindicated with CYP3A4 substrates that prolong the QT interval. Concomitant administration of posaconazole with the CYP3A4 substrates, pimozide and quinidine may result in increased plasma concentrations of these drugs, leading to QTc prolongation and cases of torsades de pointes [see Warnings and Precautions (5.2) and Drug Interactions (7.2)].
Coadministration with the HMG-CoA reductase inhibitors that are primarily metabolized through CYP3A4 (e.g., atorvastatin, lovastatin, and simvastatin) is contraindicated since increased plasma concentration of these drugs can lead to rhabdomyolysis [see Drug Interactions (7.2) and Clinical Pharmacology (12.3)].
Posaconazole may increase the plasma concentrations of ergot alkaloids (ergotamine and dihydroergotamine) which may lead to ergotism [see Drug Interactions (7.2)].
Coadministration of posaconazole with venetoclax at initiation and during the ramp-up phase is contraindicated in patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL) due to the potential for increased risk of tumor lysis syndrome [see Warnings and Precautions (5.11) and Drug Interactions (7.2)].
Concomitant administration of posaconazole with cyclosporine or tacrolimus increases the whole blood trough concentrations of these calcineurin-inhibitors [see Drug Interactions (7.2) and Clinical Pharmacology (12.3)]. Nephrotoxicity and leukoencephalopathy (including deaths) have been reported in clinical efficacy studies in patients with elevated cyclosporine or tacrolimus concentrations. Frequent monitoring of tacrolimus or cyclosporine whole blood trough concentrations should be performed during and at discontinuation of posaconazole treatment and the tacrolimus or cyclosporine dose adjusted accordingly.
Some azoles, including posaconazole, have been associated with prolongation of the QT interval on the electrocardiogram. In addition, cases of torsades de pointes have been reported in patients taking posaconazole.
Results from a multiple time-matched ECG analysis in healthy volunteers did not show any increase in the mean of the QTc interval. Multiple, time-matched ECGs collected over a 12-hour period were recorded at baseline and steady-state from 173 healthy male and female volunteers (18 to 85 years of age) administered Noxafil® (posaconazole) oral suspension 400 mg twice daily with a high-fat meal. In this pooled analysis, the mean QTc (Fridericia) interval change from baseline was –5 msec following administration of the recommended clinical dose. A decrease in the QTc(F) interval (–3 msec) was also observed in a small number of subjects (n=16) administered placebo. The placebo-adjusted mean maximum QTc(F) interval change from baseline was <0 msec (–8 msec). No healthy subject administered posaconazole had a QTc(F) interval ≥500 msec or an increase ≥60 msec in their QTc(F) interval from baseline.
Posaconazole should be administered with caution to patients with potentially proarrhythmic conditions. Do not administer with drugs that are known to prolong the QTc interval and are metabolized through CYP3A4 [see Contraindications (4.3) and Drug Interactions (7.2)].
Electrolyte disturbances, especially those involving potassium, magnesium or calcium levels, should be monitored and corrected as necessary before and during posaconazole therapy.
Pseudoaldosteronism, manifested by the onset of hypertension or worsening of hypertension, and abnormal laboratory findings (hypokalemia, low serum renin and aldosterone, and elevated 11-deoxycortisol), has been reported with posaconazole use in the postmarket setting. Monitor blood pressure and potassium levels and manage as necessary. Management of pseudoaldosteronism may include discontinuation of posaconazole, substitution with an appropriate antifungal drug that is not associated with pseudoaldosteronism, or use of aldosterone receptor antagonists.
Hepatic reactions (e.g., mild to moderate elevations in alanine aminotransferase (ALT), aspartate aminotransferase (AST), alkaline phosphatase, total bilirubin, and/or clinical hepatitis) have been reported in clinical trials. The elevations in liver tests were generally reversible on discontinuation of therapy, and in some instances these tests normalized without drug interruption. Cases of more severe hepatic reactions including cholestasis or hepatic failure including deaths have been reported in patients with serious underlying medical conditions (e.g., hematologic malignancy) during treatment with posaconazole. These severe hepatic reactions were seen primarily in subjects receiving the Noxafil® (posaconazole) oral suspension 800 mg daily (400 mg twice daily or 200 mg four times a day) in clinical trials.
Liver tests should be evaluated at the start of and during the course of posaconazole therapy. Patients who develop abnormal liver tests during posaconazole therapy should be monitored for the development of more severe hepatic injury. Patient management should include laboratory evaluation of hepatic function (particularly liver tests and bilirubin). Discontinuation of posaconazole must be considered if clinical signs and symptoms consistent with liver disease develop that may be attributable to posaconazole.
Posaconazole injection should be avoided in patients with moderate or severe renal impairment (eGFR <50 mL/min/1.73 m2), unless an assessment of the benefit/risk to the patient justifies the use of posaconazole injection. In patients with moderate or severe renal impairment (eGFR <50 mL/min/1.73 m2), receiving the posaconazole injection, accumulation of the intravenous vehicle, SBECD, is expected to occur. Serum creatinine levels should be closely monitored in these patients, and, if increases occur, consideration should be given to changing to oral posaconazole therapy [see Dosage and Administration (2.11) and Use in Specific Populations (8.6)].
Concomitant administration of posaconazole with midazolam increases the midazolam plasma concentrations by approximately 5-fold. Increased plasma midazolam concentrations could potentiate and prolong hypnotic and sedative effects. Patients must be monitored closely for adverse effects associated with high plasma concentrations of midazolam and benzodiazepine receptor antagonists must be available to reverse these effects [see Drug Interactions (7.2) and Clinical Pharmacology (12.3)].
Concomitant administration of azole antifungals, including posaconazole, with vincristine has been associated with neurotoxicity and other serious adverse reactions, including seizures, peripheral neuropathy, syndrome of inappropriate antidiuretic hormone secretion, and paralytic ileus. Reserve azole antifungals, including Posaconazole, for patients receiving a vinca alkaloid, including vincristine, who have no alternative antifungal treatment options [see Drug Interactions (7.2)].
Concomitant administration of posaconazole, a strong CYP3A4 inhibitor, with venetoclax may increase venetoclax toxicities, including the risk of tumor lysis syndrome (TLS), neutropenia, and serious infections. In patients with CLL/SLL, administration of posaconazole during initiation and the ramp-up phase of venetoclax is contraindicated [see Contraindications (4.6)]. Refer to the venetoclax labeling for safety monitoring and dose reduction in the steady daily dosing phase in CLL/SLL patients.
For patients with acute myeloid leukemia (AML), dose reduction and safety monitoring are recommended across all dosing phases when coadministering posaconazole with venetoclax [see Drug Interactions (7.2)]. Refer to the venetoclax prescribing information for dosing instructions.
The following serious and otherwise important adverse reactions are discussed in detail in another section of the labeling:
• Arrhythmias and QT Prolongation [see Warnings and Precautions (5.2)]
• Electrolyte Disturbances [see Warnings and Precautions (5.3)]
• Pseudoaldosteronism [see Warnings and Precautions (5.4)]
• Hepatic Toxicity [see Warnings and Precautions (5.5)]
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of posaconazole cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Treatment of Invasive Aspergillosis in Adults and Adolescents (Posaconazole Injection and Noxafil® (posaconazole) Delayed-Release Tablets)
The safety of posaconazole injection and Noxafil® (posaconazole) delayed-release tablets was assessed in a randomized, double-blind, active-controlled clinical study of posaconazole injection and Noxafil® (posaconazole) delayed-release tablets versus voriconazole for treatment of invasive aspergillosis (Aspergillosis Treatment Study). A total of 575 adult and pediatric patients 14 years of age and older (288 in the posaconazole group, 287 in voriconazole group (voriconazole for injection or voriconazole tablets)) with proven, probable or possible invasive aspergillosis were included. The median duration of treatment was 67 days for posaconazole injection or Noxafil® (posaconazole) delayed-release tablets and 64 days for voriconazole. In this study, 55% to 60% of patients started intravenous treatment with posaconazole injection or voriconazole (voriconazole for injection). The median duration of the first instance of intravenous treatment (before switching to oral treatment or discontinuing or completing study treatment) was 9 days for both groups. Table 7 presents adverse reactions reported at an incidence of ≥10% in either one of the treatment groups in the Aspergillosis Treatment Study.
Adverse reactions leading to treatment discontinuation were reported for 34% of patients. The most commonly reported adverse reactions (>2% of patients) leading to treatment discontinuation were septic shock, respiratory failure, and bronchopulmonary aspergillosis in the posaconazole group, and septic shock and acute myeloid leukemia in the voriconazole group. The most frequently reported adverse reactions in the posaconazole-treated group were pyrexia (28%), hypokalemia (28%), and nausea (23%).
Table 7: Adverse Reactions in at least 10% of Adults and Adolescents Receiving Posaconazole Injection or Noxafil® (posaconazole) Delayed-Release Tablets for the Treatment of Invasive Aspergillosis
Adverse Reactions | Posaconazole injection or Noxafil® (posaconazole) delayed-release tablets n = 288 (%) | Voriconazole for injection or Voriconazole tablets n = 287 (%) |
| Percentage of Patients Reporting any Adverse Reaction | 97.6 | 97.6 |
| Hypokalemia | 28.5 | 17.1 |
| Pyrexia | 28.1 | 25.1 |
| Nausea | 22.6 | 17.8 |
| Diarrhea | 18.1 | 18.1 |
| Vomiting | 18.1 | 13.6 |
| Alanine aminotransferase increased | 14.6 | 12.9 |
| Febrile neutropenia | 14.6 | 13.2 |
| Aspartate aminotransferase increased | 13.2 | 12.5 |
| Pneumonia | 12.5 | 9.1 |
| Headache | 12.2 | 8.7 |
| Constipation | 11.1 | 8.0 |
| Edema peripheral | 11.1 | 8.4 |
| Epistaxis | 11.1 | 5.9 |
| Cough | 10.4 | 8.4 |
| Abdominal pain | 10.1 | 8.4 |
| Hypomagnesemia | 10.1 | 6.3 |
Clinical Trial Experience with Posaconazole Injection for Prophylaxis of Invasive Aspergillus and Candida Infections
Administration of multiple doses of posaconazole injection via a peripheral venous catheter were associated with thrombophlebitis (60% incidence). Therefore, in subsequent studies, posaconazole injection was administered via central venous catheter [see Dosage and Administration (2.6)].
The safety of posaconazole injection has been assessed in 268 patients in a clinical trial. Patients were enrolled in a non-comparative pharmacokinetic and safety trial of posaconazole injection when given as antifungal prophylaxis (Posaconazole Injection Study). Patients were immunocompromised with underlying conditions including hematological malignancy, neutropenia post-chemotherapy, GVHD, and post HSCT. This patient population was 55% male, had a mean age of 51 years (range 18 to 82 years, 19% of patients were ≥65 years of age), and were 95% White and 8% Hispanic. In this study, 10 patients received a single dose of 200 mg posaconazole injection, 21 patients received 200 mg daily dosage for a median of 14 days, and 237 patients received 300 mg daily dosage for a median of 9 days (the 200 mg dosage is not a recommended dosage for prophylaxis of invasive Aspergillus and Candida infections in adults [see Dosage and Administration (2.2)]. In the 300 mg daily dosage group each patient received a loading intravenous dose of posaconazole injection 300 mg twice on Day 1, then intravenous posaconazole injection therapy, and finally Noxafil® (posaconazole) oral suspension to complete 28 days of total posaconazole therapy.
Table 8 presents adverse reactions observed in patients treated with the posaconazole injection 300 mg daily dosage group in the Posaconazole Injection Study.
The most frequently reported adverse reactions with an onset during the intravenous posaconazole injection phase of dosing with 300 mg once daily were diarrhea (32%), hypokalemia (22%), pyrexia (21%), and nausea (19%). These adverse reactions were consistent with those seen in studies with Noxafil® (posaconazole) oral suspension.
Table 8: Adverse Reactions in at least 10% of Adults Receiving Posaconazole Injection for the Prophylaxis of Invasive Aspergillus and Candida infections
Adverse Reactions | Posaconazole Injection Treatment Phase n=237* (%) | Posaconazole Injection Treatment Phase or Subsequent Noxafil® (posaconazole) Oral Suspension Treatment Phase n=237† (%) |
| Percentage of Patients Reporting any Adverse Reaction | 93 | 99 |
| Diarrhea | 32 | 39 |
| Hypokalemia | 22 | 28 |
| Pyrexia | 21 | 31 |
| Nausea | 19 | 30 |
| Rash | 15 | 24 |
| Headache | 14 | 21 |
| Epistaxis | 14 | 17 |
| Abdominal Pain | 13 | 17 |
| Chills | 12 | 16 |
| Edema Peripheral | 12 | 15 |
| Vomiting | 12 | 19 |
| Hypomagnesemia | 11 | 13 |
| Decreased appetite | 10 | 12 |
| Cough | 9 | 13 |
| Constipation | 8 | 13 |
| Fatigue | 8 | 10 |
| Hypertension | 8 | 11 |
| Petechiae | 8 | 10 |
| Anemia | 7 | 10 |
| Dyspnea | 7 | 10 |
| Thrombocytopenia | 7 | 11 |
| Abdominal Pain Upper | 6 | 11 |
| * Adverse reactions reported in patients with an onset during the posaconazole intravenous dosing phase of the study. † Adverse reactions reported with an onset at any time during the study in patients who were treated for up to 28 days of posaconazole therapy. | ||
Liver Test Abnormalities in the Clinical Trials with Noxafil® (posaconazole) Oral Suspension for the Treatment of Invasive Aspergillosis
The number and percentage of patients treated for invasive aspergillosis with clinically significant liver test abnormalities at any time during the Aspergillosis Treatment Study is provided in Table 14. Liver test abnormalities present prior to the initiation of study drug included: ALT (22% of the patients), AST (13% of the patients), and bilirubin (13% of the patients).
Table 14: Changes in Liver Test Results from CTC Grade 0, 1, or 2 at Baseline to Grade 3 or 4 (Aspergillosis Treatment Study)
Number (%) of Patients with Change* | ||
Laboratory Parameter | Posaconazole n/N (%) | Voriconazole n/N (%) |
| AST | 22/281 (8) | 21/285 (7) |
| ALT | 29/281(10) | 23/282 (8) |
| Bilirubin | 26/280 (9) | 25/284 (9) |
| Alkaline Phosphatase | 12/282 (4) | 20/284 (7) |
| *Change from Grade 0 to 2 at baseline to Grade 3 or 4 during the study. These data are presented in the form n/N, where n represents the number of patients who met the criterion as indicated, and N represents the number of patients who had a baseline observation and at least one post-baseline observation. N=Number of patients for a given laboratory test with a baseline value of CTC Grade 0, 1, or 2 and at least one post-baseline value. CTC = Common Toxicity Criteria; AST= Aspartate Aminotransferase; ALT = Alanine Aminotransferase. | ||
In healthy volunteers and patients, elevation of liver test values did not appear to be associated with higher plasma posaconazole concentrations.
Clinical Trials in Pediatric Patients 2 Years of Age and Older
The safety of Posaconazole injection and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension for prophylaxis of invasive fungal infections was evaluated in an open -label uncontrolled dose-ranging pharmacokinetic and safety study of posaconazole injection and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension (Pediatric Study 1, NCT02452034). In this study, 115 immunocompromised pediatric patients 2 to less than 18 years of age with known or expected neutropenia initially received posaconazole injection (up to 6 mg/kg twice daily for the first day and then up to 6 mg/kg for at least 7 days), and then 63 patients were transitioned to Noxafil® PowderMix (posaconazole) for delayed-release oral suspension (up to 6 mg/kg once daily). The mean overall treatment duration was 21 days including a mean duration of 14 days (range: 1 to 28 days) on posaconazole injection and a mean duration of 12 days (range: 2 to 18 days) on Noxafil® PowderMix (posaconazole) for delayed-release oral suspension [see Clinical Pharmacology (12.3)]. In this study, the reported adverse reaction profile of posaconazole injection and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension in pediatric patients was consistent with the safety profile of posaconazole in adults. The most common adverse reactions that occurred in greater than 20% of pediatric patients who received posaconazole injection and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension were pyrexia, febrile neutropenia, vomiting, mucosal inflammation, pruritus, hypertension, hypokalemia, and stomatitis.
The safety of posaconazole injection, Noxafil® (posaconazole) delayed-release tablets, and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension for the treatment of invasive aspergillosis was evaluated in an open-label, non-comparative clinical study in 31 pediatric patients 2 to less than 18 years of age with a diagnosis of possible, probable, or proven invasive aspergillosis (Pediatric Study 2, NCT04218851). In this study, all 31 pediatric patients initially received posaconazole injection (6 mg/kg twice daily on the first day and then 6 mg/kg once daily) for the treatment of invasive aspergillosis; 12 patients were transitioned to Noxafil® (posaconazole) delayed-release tablets (300 mg once daily) if they weighed ≥40 kg, and 10 patients were transitioned to Noxafil® PowderMix (posaconazole) for delayed-release oral suspension (based on weight) if they weighed 10 to 40 kg [see Dosage and Administration (2.3)]. The mean overall treatment duration was 50 days including 15 days (range 2 to 78 days) on posaconazole injection, 54 days (range: 6 to 80 days) on Noxafil® (posaconazole) delayed-release tablets, and 44 days (range 7 to 76 days) on Noxafil® PowderMix (posaconazole) for delayed-release oral suspension. The reported adverse reaction profile of posaconazole injection, Noxafil® (posaconazole) delayed-release tablets, and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension in pediatric patients was consistent with the known safety profile of posaconazole in adults. The most common adverse reactions that occurred in greater than 20% of pediatric patients who received any of the three formulations of posaconazole were vomiting, pyrexia, abdominal pain, liver test abnormalities, and hypertension.
The following adverse reaction has been identified during the post-approval use of posaconazole. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Endocrine Disorders: Pseudoaldosteronism
Table 15 and Table 17 include drugs with clinically important drug interactions when administered concomitantly with posaconazole and instructions for preventing or managing them.
These recommendations are based on either drug interaction studies or predicted interactions due to the expected magnitude of interaction and potential for serious adverse reactions or loss of efficacy [see Clinical Pharmacology (12.3)].
The following information was derived from data with Noxafil® (posaconazole) oral suspension or another posaconazole tablet formulation unless otherwise noted. All clinically important drug interactions with Noxafil® (posaconazole) oral suspension, except for those that affect the absorption of posaconazole (via gastric pH and motility), are considered relevant to clinically important drug interactions with posaconazole injection [Clinical Pharmacology (12.3)].
Consult the labeling of concomitantly used drugs to obtain further information about interactions with posaconazole.
Posaconazole is primarily metabolized via UDP-glucuronosyltransferase and is a substrate of p-glycoprotein (P-gp) efflux. Therefore, inhibitors or inducers of these clearance pathways may affect posaconazole plasma concentrations. Concomitant use of posaconazole with drugs that can decrease the plasma posaconazole concentrations should generally be avoided unless the benefit outweighs the risk. If such drugs are necessary, patients should be monitored closely for breakthrough fungal infections.
Table 15: Drug Interactions Affecting Posaconazole Injection When Administered Concomitantly with Other Drugs
| UDP-Glucuronidase Inducers | ||
| Mechanism and Clinical Effect(s) | Posaconazole is a UDP-glucuronosyltransferase substrate. Concomitant use of posaconazole with UDP-glucuronidase inducers may decrease posaconazole exposure [see Clinical Pharmacology (12.3)], which may reduce the effectiveness of posaconazole. | |
| Prevention or Management | Efavirenz | Avoid concomitant use of posaconazole with efavirenz, unless the benefit outweighs the risks. |
| Rifabutin | Avoid concomitant use of posaconazole with rifabutin unless the benefit to the patient outweighs the risk. If concomitant use is needed, monitor closely for breakthrough fungal infections. See Table 17 for rifabutin monitoring considerations when posaconazole affects rifabutin via CYP3A4 inhibition. | |
| Phenytoin | Avoid concomitant use of posaconazole with phenytoin unless the benefit to the patient outweighs the risk. If concomitant use is needed, monitor for breakthrough fungal infections. See Table 17 for phenytoin monitoring considerations when posaconazole affects phenytoin via CYP3A4 inhibition. | |
| Fosamprenavir | ||
| Mechanism and Clinical Effect(s) | Concomitant use of posaconazole with fosamprenavir may lead to decreased posaconazole plasma concentrations [see Clinical Pharmacology (12.3)], which may reduce effectiveness of posaconazole. | |
| Prevention or Management | If concomitant use of posaconazole with fosamprenavir is needed, monitor closely for breakthrough fungal infections. | |
Posaconazole is a strong CYP3A4 inhibitor. Therefore, concomitant use of posaconazole may increase plasma concentrations of drugs that are CYP3A4 substrates [see Clinical Pharmacology (12.3)].
Table 17: Drug Interactions Affecting Drugs Administered Concomitantly with Posaconazole Injection
| Digoxin | ||
| Clinical Effect(s) | Increased digoxin plasma concentrations have been reported in patients who received concomitant posaconazole and digoxin. | |
| Prevention or Management | Monitor digoxin plasma concentrations during concomitant use of posaconazole. | |
| Glipizide | ||
| Clinical Effect(s) | No dosage modification of glipizide is needed when used concomitantly with posaconazole. However, glucose concentrations decrease in some patients concomitantly administered posaconazole and glipizide. | |
| Prevention or Management | Increase monitoring of glucose concentrations when used concomitantly. | |
| CYP3A Substrates | ||
| Immunosuppressants that are CYP3A4 Substrates | ||
| Mechanism and Clinical Effect(s) | Posaconazole is a strong CYP3A4 inhibitor. Therefore, plasma concentrations of CYP3A4 substrates may be increased by posaconazole use [see Clinical Pharmacology (12.3)]. | |
| Prevention or Management | Sirolimus | Posaconazole is contraindicated with sirolimus [see Clinical Pharmacology (12.3)]. |
| Tacrolimus | • At initiation of posaconazole treatment, reduce the tacrolimus dosage to approximately one-third of the original tacrolimus dosage. • Frequent monitoring of tacrolimus whole blood trough concentrations should be performed during and at discontinuation of posaconazole treatment and the tacrolimus dosage should be modified accordingly [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3)]. | |
| Cyclosporine | • At initiation of posaconazole treatment reduce the cyclosporine dosage to approximately three-fourths of the original dosage. • Frequent monitoring of cyclosporine whole blood trough concentrations should be performed during and at discontinuation of posaconazole treatment and the cyclosporine dosage should be modified accordingly [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3)]. | |
| CYP3A4 Substrates that Prolong QTc Interval | ||
| Mechanism and Clinical Effect(s) | Concomitant use of posaconazole with CYP3A4 substrates such as pimozide and quinidine may result in increased plasma concentrations of the CYP3A4 substrates leading to QTc interval prolongation and torsades de pointes [see Warnings and Precautions (5.2)]. | |
| Prevention or Management | Pimozide | Concomitant use with posaconazole is contraindicated. |
| Quinidine | ||
| HMG-CoA Reductase Inhibitors (Statins) that are CYP3A4 Substrates | ||
| Mechanism and Clinical Effect(s) | Concomitant use of posaconazole with simvastatin increased simvastatin plasma concentrations which can lead to rhabdomyolysis [see Clinical Pharmacology (12.3)]. | |
| Prevention or Management | Atorvastatin, Lovastatin, Simvastatin | Concomitant use with posaconazole is contraindicated. |
| Benzodiazepines that are CYP3A4 Substrates | ||
| Mechanism and Clinical Effect(s) | Concomitant use of posaconazole with midazolam increased midazolam plasma concentrations which could potentiate and prolong hypnotic and sedative effects [see Clinical Pharmacology (12.3)]. | |
| Prevention or Management | Midazolam, Alprazolam, Triazolam | Closely monitor for adverse reactions associated with high plasma concentrations of benzodiazepines that are CYP3A4 substrates during concomitant use, and a benzodiazepine receptor antagonist should be available to reverse effects [see Warnings and Precautions (5.7)]. |
| Calcium Channel Blockers that are CYP3A4 Substrates | ||
| Mechanism and Clinical Effect(s) | Posaconazole may increase the plasma concentrations of calcium channel blockers that are substrates of CYP3A4. | |
| Prevention or Management | Verapamil, Diltiazem, Nifedipine, Nicardipine, Felodipine | Monitor frequently for adverse reactions and toxicity with concomitant use of posaconazole with calcium channel blockers that are CYP3A4 substrates. Dosage reduction of the calcium channel blocker may be needed. |
| Anti-HIV Drugs that are CYP3A4 Substrates | ||
| Mechanism and Clinical Effect(s) | Ritonavir and atazanavir are CYP3A4 substrates and posaconazole increased plasma concentrations of these drugs [see Clinical Pharmacology (12.3)]. | |
| Prevention or Management | Ritonavir and Atazanavir | Monitor frequently for adverse reactions and toxicity of ritonavir and atazanavir during concomitant use. |
| Antineoplastic Drugs that are CYP3A4 Substrates | ||
| Mechanism and Clinical Effect(s) | Posaconazole may increase plasma concentrations of oncology drugs that are CYP3A4 substrates, which may increase the risk of serious adverse reactions. | |
| Prevention or Management | Venetoclax | CLL/SLL patients: Concomitant use of posaconazole with venetoclax during initiation and ramp-up phase is contraindicated. AML patients: With concomitant use, venetoclax dosage reduction and safety monitoring is recommended across all dosing phases [see Warnings and Precautions (5.11)]. |
| Vinca alkaloids (e.g., vincristine, vinblastine) | Reserve concomitant use for patients with no alternative antifungal treatment options [see Warnings and Precautions (5.8)]. | |
| Ergot Alkaloids | ||
| Mechanism and Clinical Effect(s) | Most of the ergot alkaloids are CYP3A4 substrates. Posaconazole may increase the plasma concentrations of ergot alkaloids (ergotamine and dihydroergotamine) which may lead to ergotism. | |
| Prevention or Management | Ergotamine, Dihydroergotamine | Concomitant use with posaconazole is contraindicated. |
| Phenytoin | ||
| Mechanism and Clinical Effect(s) | Phenytoin is a CYP3A4 substrate. Concomitant use of posaconazole with phenytoin increased phenytoin plasma concentrations [see Clinical Pharmacology (12.3)]. | |
| Prevention or Management | Avoid concomitant use of posaconazole with phenytoin unless the benefit outweighs the risk. frequently monitor phenytoin concentrations and consider a dosage reduction of phenytoin. See Table 15 for additional monitoring considerations when phenytoin affects posaconazole via UDP-glucuronosyltransferase inhibition. | |
| Rifabutin | ||
| Mechanism and Clinical Effect(s) | Rifabutin is a CYP3A4 substrate. Concomitant use of posaconazole with rifabutin increased rifabutin plasma concentrations [see Clinical Pharmacology (12.3)]. | |
| Prevention or Management | Avoid concomitant use of posaconazole with rifabutin unless the benefit outweighs the risk. Frequent monitoring of full blood counts and adverse reactions due to increased rifabutin plasma concentrations (e.g., uveitis, leukopenia) during concomitant use are recommended. See Table 15 for additional monitoring considerations when rifabutin affects posaconazole via UDP-glucuronosyltransferase inhibition. | |
Additional clinical studies demonstrated that no clinically important effects on zidovudine, lamivudine, indinavir, or caffeine were observed when administered with posaconazole 200 mg once daily; therefore, no dose adjustments are required for these drugs when coadministered with posaconazole 200 mg once daily.
No clinically relevant effects on the pharmacokinetics of Noxafil® (posaconazole) delayed-release tablets were observed during concomitant use with antacids, H2-receptor antagonists and proton pump inhibitors, and metoclopramide [see Clinical Pharmacology (12.3)]. No dosage adjustment of Noxafil® (posaconazole) delayed-release tablets or Noxafil® PowderMix (posaconazole) for delayed-release oral suspension is required during concomitant use with these drugs.
No clinically relevant effects on the pharmacokinetics of Noxafil® (posaconazole) oral suspension were observed during concomitant use with antacids, H2-receptor antagonists (other than cimetidine), and loperamide [see Clinical Pharmacology (12.3)]. No dosage adjustment of Noxafil® (posaconazole) oral suspension is required during concomitant use with these drugs (other than cimetidine).
Risk Summary
Based on findings from animal data, posaconazole may cause fetal harm when administered to pregnant women. Available data for use of posaconazole in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, skeletal malformations were observed when posaconazole was dosed orally to pregnant rats during organogenesis at doses ≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of posaconazole in healthy volunteers. In pregnant rabbits dosed orally during organogenesis, doses of ≥ 3 times the clinical exposure caused an increase in resorptions (see Data). Based on animal data, advise pregnant women of the potential risk to a fetus.
The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data
Animal Data: Posaconazole resulted in maternal toxicity (reduced food consumption and reduced body weight gain) and skeletal malformations (cranial malformations and missing ribs) when given orally to pregnant rats during organogenesis (Gestational Days 6 through 15) at doses ≥27 mg/kg (≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of drug in healthy volunteers). The no-effect dose for malformations and maternal toxicity in rats was 9 mg/kg, which is 0.7 times the exposure achieved with the 400 mg twice daily oral suspension regimen. No malformations were seen in rabbits dosed during organogenesis (Gestational Days 7 through 19) at doses up to 80 mg/kg (5 times the exposure achieved with the 400 mg twice daily oral suspension regimen). In the rabbit, the no-effect dose was 20 mg/kg, while high doses of 40 mg/kg and 80 mg/kg (3 or 5 times the clinical exposure) caused an increase in resorptions. In rabbits dosed at 80 mg/kg, a reduction in body weight gain of females and a reduction in litter size were seen.
Risk Summary
There are no data on the presence of posaconazole in human milk, the effects on the breastfed infant, or the effects on milk production. Posaconazole is excreted in the milk of lactating rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for posaconazole and any potential adverse effects on the breastfed child from posaconazole or from the underlying maternal condition.
Treatment of Invasive Aspergillosis
The safety and effectiveness of posaconazole injection have been established for the treatment of invasive aspergillosis in pediatric patients 2 years of age and older.
Use of posaconazole for these pediatric indications is supported by evidence from adequate and well-controlled studies of posaconazole in adults and safety and pharmacokinetic (PK) data from two pediatric studies [see Adverse Reactions (6.1) and Clinical Pharmacology (12.3)]. The safety of posaconazole in pediatric patients for these pediatric indications was consistent with the known safety profile of posaconazole in adults [see Adverse Reactions (6.1)].
The safety and effectiveness of posaconazole have not been established in pediatric patients less than 2 years of age.
Prophylaxis of Invasive Aspergillus and Candida Infections
The safety and effectiveness of posaconazole injection have been established for the prophylaxis of invasive Aspergillus and Candida infections in pediatric patients 2 years of age and older who are at high risk of developing these infections due to being severely immunocompromised.
Use of posaconazole for these pediatric indications is supported by adequate and well controlled studies of posaconazole in adults and pediatric patients aged 13 years of age and older and additional PK and safety data in pediatric patients 2 years of age and older [see Clinical Pharmacology (12.3) and Clinical studies (14)].
The safety and effectiveness of posaconazole have not been established in pediatric patients less than 2 years of age.
No overall differences in the safety or effectiveness of posaconazole injection have been observed between geriatric patients and younger adult patients in the clinical trials; therefore, the recommended dosage in geriatric patients is the same as that for younger adult patients. No clinically meaningful differences in posaconazole pharmacokinetics were observed in posaconazole-treated geriatric patients compared to posaconazole-treated younger adult patients during clinical trials [see Clinical Pharmacology (12.3)].
• Of the 279 patients treated with posaconazole injection in the Posaconazole Injection Study (prophylaxis of invasive Aspergillus and Candida infections in those at high risk of developing these infections due to being severely immunocompromised), 52 (19%) patients were >65 years of age.
• Of the 230 patients treated with Noxafil® (posaconazole) delayed-release tablets, 38 (17%) patients were >65 years of age.
• Of the 605 patients treated with Noxafil® (posaconazole) oral suspension in Noxafil Oral Suspension Study 1 and Study 2 (prophylaxis of invasive Aspergillus and Candida infections in those at high risk of developing these infections due to being severely immunocompromised), 63 (10%) patients were ≥65 years of age.
• Of the 288 patients treated with Posaconazole injection or Noxafil® (posaconazole) delayed-release tablets in the Aspergillosis Treatment Study, 85 (29%) patients were ≥65 years of age.
Posaconazole Injection
Avoid use of posaconazole injection in patients with eGFR less than 50 mL/minute/1.73 m2 unless the benefit/risk to the patient justifies its use. The inactive ingredient in posaconazole injection, Betadex Sulfobutyl Ether Sodium (SBECD) is expected to accumulate in patients with reduced renal function. Safety and effectiveness of posaconazole injection have not been established in patients with less than 50 mL/minute/1.73 m2.
If treatment with posaconazole injection is unavoidable in patients with eGFR less than 50 mL/minute/1.73 m2, monitor serum creatinine levels. If serum creatinine increases, consider changing to oral posaconazole therapy.
No dosage adjustment is recommended for posaconazole injection in patients with mild, moderate, or severe hepatic impairment (Child-Pugh Class A, B, or C, respectively) [see Clinical Pharmacology (12.3)].
However, a specific hepatic impairment study has not been conducted with the posaconazole injection.
No adjustment in the dosage of posaconazole is necessary based on sex.
No adjustment in the dosage of posaconazole is necessary based on race.
Pharmacokinetic modeling suggests that patients who weigh greater than 120 kg may have lower posaconazole plasma drug exposure. Therefore, consider closely monitoring for breakthrough fungal infections [see Clinical Pharmacology (12.3)].
There is no experience with overdosage of posaconazole injection.
During the clinical trials, some patients received Noxafil® (posaconazole) oral suspension up to 1,600 mg/day with no adverse reactions noted that were different from the lower doses. In addition, accidental overdose was noted in one patient who took 1200 mg twice daily Noxafil® (posaconazole) oral suspension for 3 days. No related adverse reactions were noted by the investigator.
Posaconazole is not removed by hemodialysis.
Posaconazole injection contains posaconazole, an azole antifungal agent.
Posaconazole is designated chemically as 4-[4-[4-[4-[[ (3R,5R)-5-(2,4-difluorophenyl)tetrahydro-5-(1H-1,2,4-triazol-1-ylmethyl)-3-furanyl]methoxy]phenyl]-1-piperazinyl]phenyl]-2-[(1S,2S)-1-ethyl-2-hydroxypropyl]-2,4-dihydro-3H-1,2,4-triazol-3-one with an empirical formula of C37H42F2N8O4 and a molecular weight of 700.8. The chemical structure is:
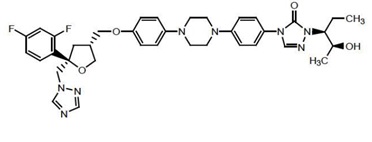
Posaconazole-spl-structure (Posaconazole Spl Structure)
Posaconazole is a white powder with a low aqueous solubility.
Posaconazole Injection
Posaconazole injection, for intravenous use, is a clear colorless to yellow, without preservatives sterile liquid essentially free of foreign matter. Each vial contains 300 mg of posaconazole and the following inactive ingredients: 6.68 g Betadex Sulfobutyl Ether Sodium (SBECD), 0.0033 g edetate disodium dihydrate, hydrochloric acid and sodium hydroxide to adjust the pH to 2.6, and water for injection.
Posaconazole is an azole antifungal agent [see Clinical Pharmacology (12.4)].
Exposure Response Relationship: Prophylaxis of invasive Aspergillus and Candida Infections in Adults Who Are at High Risk of Developing These Infections Due to Being Severely Immunocompromised
In clinical studies of neutropenic patients who were receiving cytotoxic chemotherapy for acute myelogenous leukemia (AML) or myelodysplastic syndromes (MDS) or hematopoietic stem cell transplant (HSCT) recipients with Graft versus Host Disease (GVHD), a wide range of plasma posaconazole exposures was noted following administration of Noxafil® (posaconazole) oral suspension. A pharmacokinetic-pharmacodynamic analysis of patient data revealed an apparent association between average posaconazole concentrations (Cavg) and prophylactic efficacy (Table 18). A lower Cavg may be associated with an increased risk of treatment failure, defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections.
Table 18: Noxafil® (posaconazole) Oral Suspension Exposure Analysis (Cavg) in Prophylaxis Trials
Prophylaxis in AML/MDS* | Prophylaxis in GVHD† | |||
Cavg Range (ng/mL) | Treatment Failure‡ (%) | Cavg Range (ng/mL) | Treatment Failure‡ (%) | |
Quartile 1 | 90-322 | 54.7 | 22-557 | 44.4 |
Quartile 2 | 322-490 | 37.0 | 557-915 | 20.6 |
Quartile 3 | 490-734 | 46.8 | 915-1563 | 17.5 |
Quartile 4 | 734-2200 | 27.8 | 1563-3650 | 17.5 |
| Cavg = the average posaconazole concentration when measured at steady state *Neutropenic patients who were receiving cytotoxic chemotherapy for AML or MDS † HSCT recipients with GVHD ‡ Defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections | ||||
Exposure Response Relationship: Treatment of Invasive Aspergillosis in Adult and Adolescent Patients:
Across a range of posaconazole plasma minimum concentrations (Cmin, range: 244 to 5663 ng/mL) following administration of posaconazole injection and Noxafil® (posaconazole) delayed-release tablets in adult and pediatric patients aged 14 years and older treated for invasive aspergillosis in Aspergillosis Treatment Study, there was no association between posaconazole Cmin and treatment efficacy [see Clinical Pharmacology (12.3) and Clinical Studies (14.1)]. Similarly, across a range of population pharmacokinetic model-predicted steady-state plasma average concentrations (Cavg, range: 589 to 6315 ng/mL), there was no association between posaconazole Cavg and treatment efficacy.
General Pharmacokinetic Characteristics
General Pharmacokinetic Characteristics of Posaconazole Injection
Posaconazole injection exhibits dose proportional pharmacokinetics after single doses between 200 and 300 mg in healthy volunteers and patients. The mean pharmacokinetic parameters after single doses with posaconazole injection in healthy volunteers and patients are shown in Table 19.
Table 19: Summary of Mean Pharmacokinetic Parameters (%CV) in Healthy Volunteers (30 minute infusion via peripheral venous line) and Patients (90 minute infusion via central venous line) after Dosing with Posaconazole Injection on Day 1
| Dose (mg) | n | AUC0-∞ (ng·hr/mL) | AUC0-12 (ng·hr/mL) | Cmax (ng/mL) | t1/2 (hr) | CL (L/hr) | |
| Healthy Volunteers | 200 | 9 | 35400 (50) | 8840 (20) | 2250 (29) | 23.6 (23) | 6.5 (32) |
| 300 | 9 | 46400 (26) | 13000 (13) | 2840 (30) | 24.6 (20) | 6.9 (27) | |
| Patients | 200 | 30 | N/D | 5570 (32) | 954 (44) | N/D | N/D |
| 300 | 22 | N/D | 8240 (26) | 1590 (62) | N/D | N/D | |
| AUC0-∞ = Area under the plasma concentration-time curve from time zero to infinity; AUC0-12 = Area under the plasma concentration-time curve from time zero to 12 hr after the first dose on Day 1; Cmax = maximum observed concentration; t½ = terminal phase half-life; CL = total body clearance; N/D = Not Determined | |||||||
Table 20 displays the pharmacokinetic parameters of posaconazole in patients following administration of posaconazole injection 300 mg taken once a day for 10 or 14 days following twice daily dosing on Day 1.
Table 20: Arithmetic Mean (%CV) of PK Parameters in Serial PK-Evaluable Patients Following Dosing of Posaconazole Injection (300 mg)*
| Day | N | Cmax (ng/mL) | Tmax† (hr) | AUC0-24 (ng*hr/mL) | Cav (ng/mL) | Cmin (ng/mL) |
| 10/14 | 49 | 3280 (74) | 1.5 (0.98-4.0) | 36100 (35) | 1500 (35) | 1090 (44) |
| AUC0-24 = area under the concentration-time curve over the dosing interval (i.e. 24 hours); Cav= time-averaged concentrations (i.e., AUC0-24h/24hr); Cmin = POS trough level immediately before a subject received the dose of POS on the day specified in the protocol; Cmax = observed maximum plasma concentration; CV = coefficient of variation, expressed as a percent (%); Day = study day on treatment; Tmax = time of observed maximum plasma concentration. * 300 mg dose administered over 90 minutes once a day following twice daily dosing on Day 1 † Median (minimum-maximum) | ||||||
Distribution:
The mean volume of distribution of posaconazole after intravenous solution administration was 261 L and ranged from 226 to 295 L between studies and dose levels.
Posaconazole is highly bound to human plasma proteins (>98%), predominantly to albumin.
Metabolism:
Posaconazole primarily circulates as the parent compound in plasma. Of the circulating metabolites, the majority are glucuronide conjugates formed via UDP glucuronidation (phase 2 enzymes). Posaconazole does not have any major circulating oxidative (CYP450 mediated) metabolites. The excreted metabolites in urine and feces account for ~17% of the administered radiolabeled dose.
Posaconazole is a substrate for p-glycoprotein (P-gp) efflux.
In vitro studies with human hepatic microsomes and clinical studies indicate that posaconazole is an inhibitor primarily of CYP3A4.
Excretion:
Following administration of Noxafil® (posaconazole) oral suspension, posaconazole is predominantly eliminated in the feces (71% of the radiolabeled dose up to 120 hours) with the major component eliminated as parent drug (66% of the radiolabeled dose). Renal clearance is a minor elimination pathway, with 13% of the radiolabeled dose excreted in urine up to 120 hours (<0.2% of the radiolabeled dose is parent drug).
Posaconazole injection is eliminated with a mean terminal half-life (t½) of 27 hours and a total body clearance (CL) of 7.3 L/h.
Specific Populations:
No clinically significant differences in the pharmacokinetics of posaconazole were observed based on age, sex, renal impairment, and indication (prophylaxis or treatment).
Race/Ethnicity:
In a population pharmacokinetic analysis of posaconazole, AUC was found to be 25% higher in Chinese patients relative to patients from other races/ethnicities. This higher exposure is not expected to be clinically relevant given the expected variability in posaconazole exposure [see Use in Specific Populations (8.9)].
Patients Weighing More Than 120 kg:
Weight has a clinically significant effect on posaconazole clearance. Relative to 70 kg patients, the Cavg is decreased by 25% in patients greater than 120 kg. Patients administered posaconazole weighing more than 120 kg may be at higher risk for lower posaconazole plasma concentrations compared to lower weight patients [see Use in Specific Populations (8.10)].
Pediatric Patients:
Prophylaxis of invasive Aspergillus and Candida infections in pediatric patients 2 years of age and older: A total of 12 patients 13 to 17 years of age received 600 mg/day (200 mg three times a day) of Noxafil® (posaconazole) oral suspension for prophylaxis of invasive fungal infections. Based on pharmacokinetic data in 10 of these pediatric patients, the mean steady-state Cav was similar between these patients and adults (≥18 years of age). In a study of 136 neutropenic pediatric patients 11 months to less than 18 years treated with Noxafil® (posaconazole) oral suspension, the exposure target of steady-state posaconazole Cavg between 500 ng/mL and less than 2500 ng/mL was attained in approximately 50% of patients instead of the prespecified 90% of patients.
The mean pharmacokinetic parameters after multiple-dose administration of Posaconazole injection and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension in neutropenic pediatric patients 2 to less than 18 years of age (Pediatric Study 1) are shown in Table 26. Patients were enrolled into 2 age groups and received posaconazole injection and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension doses at 6 mg/kg (0.6 to 1 times the recommended dose) with a maximum 300 mg dose once daily (twice daily on Day 1) [see Adverse Reactions (6.1)].
Table 26: Summary of Steady-State Geometric Mean Pharmacokinetic Parameters (% Geometric CV) After Multiple Dosing with Posaconazole Injection and Noxafil® PowderMix (posaconazole) for Delayed-Release Oral Suspension 6 mg/kg* in Pediatric Patients with Neutropenia or Expected Neutropenia
| Age Group | Dose Type | N | AUC0-24 hr (ng·hr/mL) | Cav† (ng/mL) | Cmax (ng/mL) | Cmin (ng/mL) | Tmax‡ (hr) | CL/F§ (L/hr) |
| 2 to <7 years | IV | 17 | 31100 (48.9) | 1300 (48.9) | 3060 (54.1) | 626 (104.8) | 1.75 (1.57-1.83) | 3.27 (49.3) |
| PFS | 7 | 23000 (47.3) | 960 (47.3) | 1510 (43.4) | 542 (68.8) | 4.00 (2.17-7.92) | 4.60 (35.2) | |
| 7 to 17 years | IV | 24 | 44200 (41.5) | 1840 (41.5) | 3340 (39.4) | 1160 (60.4) | 1.77 (1.33-6.00) | 4.76 (55.7) |
| PFS | 12 | 25000 (184.3) | 1040 (184.3) | 1370 (178.5) | 713 (300.6) | 2.78 (0.00-4.00) | 8.39 (190.3) | |
| IV= Posaconazole injection; PFS= Noxafil® PowderMix (posaconazole) for delayed-release oral suspension; AUC0-24 = Area under the plasma concentration-time curve from time zero to 24 hr; Cmax = maximum observed concentration; Cmin = minimum observed plasma concentration; Tmax = time of maximum observed concentration; CL/F = apparent total body clearance * 0.6 to 1 times the recommended dose † Cav = time-averaged concentrations (i.e., AUC0-24 hr/24 hr) ‡ Median (minimum-maximum) § Clearance (CL for IV and CL/F for PFS) | ||||||||
Based on a population pharmacokinetic model evaluating posaconazole pharmacokinetics and predicting exposures in pediatric patients, the exposure of steady-state posaconazole average concentration greater than or equal to 700 ng/mL in approximately 90% of patients is attained with the recommended dose of Posaconazole injection and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension.
The population pharmacokinetic analysis of posaconazole in pediatric patients from Pediatric Study 1 suggests that age, sex, renal impairment and ethnicity have no clinically meaningful effect on the pharmacokinetics of posaconazole.
Treatment of invasive aspergillosis in pediatric patients 2 years of age and older: A total of 31 patients 2 to less than 18 years of age (body weight of ≥12 kg) received pediatric dosing based on body weight of Noxafil® (posaconazole) delayed-release tablets, posaconazole Injection, and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension [see Dosage and Administration (2.3].
The mean population pharmacokinetic model parameters after multiple dose administration of Noxafil® (posaconazole) delayed-release tablets, posaconazole Injection, and Noxafil® PowderMix (posaconazole) for delayed-release oral suspension in pediatric patients 2 to less than 18 years of age for the treatment of invasive aspergillosis (Pediatric Study 2) are shown in Table 27[see Adverse Reactions (6.1)].
Table 27: Summary of Steady-State Geometric Mean Pharmacokinetic Parameters* (% Geometric CV) After Multiple Dosing with Posaconazole Injection, Noxafil® PowderMix (posaconazole) for Delayed-Release Oral Suspension, and Noxafil® (posaconazole) Delayed-Release Tablets in Pediatric Patients being Treated for Invasive Aspergillosis
| Age Group | Dose Type | N† | AUC0-24 hours (ng·hr/mL) | Cav‡ (ng/mL) | Cmax (ng/mL) | Cmin (ng/mL) | Tmax§ (hr) | CL/F¶ (L/hr) |
| 2 to <12 years | IV | 9 | 61900 (49.8) | 2580 (49.8) | 3630 (30.8) | 1710 (82.2) | 1.50 (1.25-1.77) | 2.56 (47.8) |
| PFS | 6 | 45200 (30.2) | 1880 (30.2) | 2220 (26.5) | 1370 (41.8) | 7.00 (6.40-7.20) | 3.25 (34.6) | |
| 12 to <18 years | IV | 13 | 60800 (35.6) | 2530 (35.6) | 3510 (26.8) | 1740 (48.5) | 1.50 (1.30-1.63) | 4.41 (41.8) |
| Tablet | 10 | 47800 (52.7) | 1990 (52.7) | 2250 (48.3) | 1580 (62.6) | 7.15 (6.70-7.30) | 6.27 (52.7) | |
| IV= Posaconazole injection; PFS= Noxafil® PowderMix (posaconazole) for delayed-release oral suspension, Tablet= Noxafil® (posaconazole) delayed-release tablets; AUC0-24 hours = Area under the plasma concentration-time curve from time zero to 24 hr; Cmax = maximum observed concentration; Cmin = minimum observed plasma concentration; Tmax = time of maximum observed concentration; CL/F = apparent total body clearance * Parameter estimates reported only for N>2 (excludes a single patient ≥2 to <12 receiving tablet and 2 patients ≥12 to <18 years receiving PFS) † Some patients had 2 values (1 for IV dosing and 1 for oral dosing) ‡ Cav = time-averaged concentrations (i.e., AUC0-24 hours/24hr) § Median (minimum-maximum) ¶ Clearance (CL for IV and CL/F for PFS or Tablet) | ||||||||
The population pharmacokinetic analysis of posaconazole in pediatric patients, including Pediatric Study 2, suggests that age, sex, ethnicity, and disease status have no clinically meaningful effect on the pharmacokinetics of posaconazole
Drug Interaction Studies:
Posaconazole is primarily metabolized via UDP glucuronidation (phase 2 enzymes) and is a substrate for p-glycoprotein (P-gp) efflux. Therefore, inhibitors or inducers of these clearance pathways may affect posaconazole plasma concentrations. A summary of drugs studied clinically with the oral suspension or another tablet formulation, which affect posaconazole concentrations, is provided in Table 28.
A clinical study in healthy volunteers also indicates that posaconazole is a strong CYP3A4 inhibitor as evidenced by a >5-fold increase in midazolam AUC. Therefore, plasma concentrations of drugs predominantly metabolized by CYP3A4 may be increased by posaconazole. A summary of the drugs studied clinically, for which plasma concentrations were affected by posaconazole, is provided in Table 31[see Contraindications (4) and Drug Interactions (7.2) including recommendations].
Effects of Other Drugs on Posaconazole and Noxafil® PowderMix (posaconazole) for Delayed-Release Oral Suspension:
Table 28: Summary of the Effects of Coadministered Drugs on Posaconazole in Healthy Volunteers
| Coadministered Drug (Postulated Mechanism of Interaction) | Coadministered Drug Dose/Schedule | Posaconazole Dose/Schedule | Effect on Bioavailability of Posaconazole | |
| Change in Mean Cmax (ratio estimate*; 90% CI of the ratio estimate) | Change in Mean AUC (ratio estimate*; 90% CI of the ratio estimate) | |||
| Efavirenz (UDP-G Induction) | 400 mg once daily × 10 and 20 days | 400 mg (oral suspension) twice daily × 10 and 20 days | ↓45% (0.55; 0.47-0.66) | ↓ 50% (0.50; 0.43-0.60) |
| Fosamprenavir (unknown mechanism) | 700 mg twice daily x 10 days | 200 mg once daily on the 1st day, 200 mg twice daily on the 2nd day, then 400 mg twice daily x 8 Days | ↓21% 0.79 (0.71-0.89) | ↓23% 0.77 (0.68-0.87) |
| Rifabutin (UDP-G Induction) | 300 mg once daily x 17 days | 200 mg (tablets) once daily × 10 days† | ↓ 43% (0.57; 0.43-0.75) | ↓ 49% (0.51; 0.37-0.71) |
| Phenytoin (UDP-G Induction) | 200 mg once daily x 10 days | 200 mg (tablets) once daily × 10 days† | ↓ 41% (0.59; 0.44-0.79) | ↓ 50% (0.50; 0.36-0.71) |
| * Ratio Estimate is the ratio of coadministered drug plus Posaconazole to Posaconazole alone for Cmax or AUC. † The tablet refers to a non-commercial tablet formulation without polymer. | ||||
Effects of Posaconazole on Other Drugs:
Table 31: Summary of the Effects of Posaconazole on Coadministered Drugs in Healthy Adult Volunteers and Patients
| Coadministered Drug (Postulated Mechanism of Interaction is Inhibition of CYP3A4 by posaconazole) | Coadministered Drug Dose/Schedule | Posaconazole Dose/ Schedule | Effect on Bioavailability of Coadministered Drugs | |
| Change in Mean Cmax (ratio estimate*; 90% CI of the ratio estimate) | Change in Mean AUC (ratio estimate*; 90% CI of the ratio estimate) | |||
| Sirolimus | 2-mg single oral dose | 400 mg (oral suspension) twice daily x 16 days | ↑ 572% (6.72; 5.62-8.03) | ↑ 788% (8.88; 7.26-10.9) |
| Cyclosporine | Stable maintenance dose in heart transplant recipients | 200 mg (tablets) once daily x 10 days† | ↑ Cyclosporine whole blood trough concentrations Cyclosporine dose reductions of up to 29% were required | |
| Tacrolimus | 0.05-mg/kg single oral dose | 400 mg (oral suspension) twice daily × 7 days | ↑ 121% (2.21; 2.01-2.42) | ↑ 358% (4.58; 4.03-5.19) |
| Simvastatin | 40-mg single oral dose | 100 mg (oral suspension) once daily x 13 days 200 mg (oral suspension) once daily x 13 days | Simvastatin ↑ 841% (9.41, 7.13-12.44) Simvastatin Acid ↑ 817% (9.17, 7.36-11.43) Simvastatin ↑ 1041% (11.41, 7.99-16.29) Simvastatin Acid ↑851% (9.51, 8.15-11.10) | Simvastatin ↑ 931% (10.31, 8.40-12.67) Simvastatin Acid ↑634% (7.34, 5.82-9.25) Simvastatin ↑ 960% (10.60, 8.63-13.02) Simvastatin Acid ↑ 748% (8.48, 7.04-10.23) |
| Midazolam | 0.4-mg single intravenous dose‡ 0.4-mg single intravenous dose‡ 2-mg single oral dose‡ 2-mg single oral dose‡ | 200 mg (oral suspension) twice daily x 7 days 400 mg (oral suspension) twice daily x 7 days 200 mg (oral suspension) once daily x 7 days 400 mg (oral suspension) twice daily x 7 days | ↑ 30% (1.3; 1.13-1.48) ↑62% (1.62; 1.41-1.86) ↑ 169% (2.69; 2.46-2.93) ↑ 138% (2.38; 2.13-2.66) | ↑ 362% (4.62; 4.02-5.3) ↑524% (6.24; 5.43-7.16) ↑ 470% (5.70; 4.82-6.74) ↑ 397% (4.97; 4.46-5.54) |
| Rifabutin | 300 mg once daily x 17 days | 200 mg (tablets) once daily × 10 days† | ↑ 31% (1.31; 1.10-1.57) | ↑ 72% (1.72;1.51-1.95) |
| Phenytoin | 200 mg once daily PO x 10 days | 200 mg (tablets) once daily x 10 days† | ↑ 16% (1.16; 0.85-1.57) | ↑ 16% (1.16; 0.84-1.59) |
| Ritonavir | 100 mg once daily x 14 days | 400 mg (oral suspension) twice daily x 7 days | ↑ 49% (1.49; 1.04-2.15) | ↑ 80% (1.8;1.39-2.31) |
| Atazanavir | Atazanavir/ ritonavir boosted regimen 300 mg once daily x 14 days 300 mg/100 mg once daily x 14 days | 400 mg (oral suspension) twice daily x 7 days 400 mg (oral suspension) twice daily x 7 days | ↑ 155% (2.55; 1.89-3.45) ↑ 53% (1.53; 1.13-2.07) | ↑ 268% (3.68; 2.89-4.70) ↑ 146% (2.46; 1.93-3.13) |
| * Ratio Estimate is the ratio of coadministered drug plus posaconazole to coadministered drug alone for Cmax or AUC. † The tablet refers to a non-commercial tablet formulation without polymer. ‡ The mean terminal half-life of midazolam was increased from 3 hours to 7 to 11 hours during coadministration with posaconazole. | ||||
Mechanism of Action
Posaconazole blocks the synthesis of ergosterol, a key component of the fungal cell membrane, through the inhibition of cytochrome P-450 dependent enzyme lanosterol 14α-demethylase responsible for the conversion of lanosterol to ergosterol in the fungal cell membrane. This results in an accumulation of methylated sterol precursors and a depletion of ergosterol within the cell membrane thus weakening the structure and function of the fungal cell membrane. This may be responsible for the antifungal activity of posaconazole.
Resistance
Clinical isolates of Candida albicans and Candida glabrata with decreased susceptibility to posaconazole were observed in oral swish samples taken during prophylaxis with posaconazole and fluconazole, suggesting a potential for development of resistance. These isolates also showed reduced susceptibility to other azoles, suggesting cross-resistance between azoles. The clinical significance of this finding is not known.
Antimicrobial Activity
Posaconazole has been shown to be active against most isolates of the following microorganisms, both in vitro and in clinical infections [see Indications and Usage (1)].
Microorganisms
Aspergillus spp. and Candida spp.
Susceptibility Testing
For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
Carcinogenesis
No drug-related neoplasms were recorded in rats or mice treated with posaconazole for 2 years at doses higher than the clinical dose. In a 2 year carcinogenicity study, rats were given posaconazole orally at doses up to 20 mg/kg (females), or 30 mg/kg (males). These doses are equivalent to 3.9- or 3.5 times the exposure achieved with a 400 mg twice daily oral suspension regimen, respectively, based on steady-state AUC in healthy volunteers administered a high-fat meal (400 mg twice daily oral suspension regimen). In the mouse study, mice were treated at oral doses up to 60 mg/kg/day or 4.8 times the exposure achieved with a 400 mg twice daily oral suspension regimen.
Mutagenesis
Posaconazole was not genotoxic or clastogenic when evaluated in bacterial mutagenicity (Ames), a chromosome aberration study in human peripheral blood lymphocytes, a Chinese hamster ovary cell mutagenicity study, and a mouse bone marrow micronucleus study.
Impairment of Fertility
Posaconazole had no effect on fertility of male rats at a dose up to 180 mg/kg (1.7 x the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations in healthy volunteers) or female rats at a dose up to 45 mg/kg (2.2 x the 400 mg twice daily oral suspension regimen).
Aspergillosis Treatment Study (NCT01782131) was a randomized, double-blind, controlled trial which evaluated the safety and efficacy of posaconazole injection and Noxafil® (posaconazole) delayed-release tablets versus voriconazole for primary treatment of invasive fungal disease caused by Aspergillus species. Eligible patients had proven, probable, or possible invasive fungal infections per the European Organization for Research and Treatment of Cancer/Mycoses Study Group, EORTC/MSG criteria. Patients were stratified by risk for mortality or poor outcome where high risk included a history of allogeneic bone marrow transplant, liver transplant, or relapsed leukemia undergoing salvage chemotherapy. The median age of patients was 57 years (range 14 to 91 years), with 27.8% of patients aged ≥65 years; 5 patients were pediatric patients 14 to 16 years of age, of whom 3 were treated with posaconazole and 2 with voriconazole. The majority of patients were male (59.8%) and white (67.1%). With regard to risk factors for invasive aspergillosis, approximately two-thirds of the patients in the study had a recent history of neutropenia, while approximately 20% with a history of an allogeneic stem cell transplant. Over 80% of subjects in each treatment group had infection limited to the lower respiratory tract (primarily lung), while approximately 11% to 13% also had infection in another organ. Invasive aspergillosis was proven or probable in 58.1% of patients as classified by independent adjudicators blinded to study treatment assignment. At least one Aspergillus species was identified in 21% of the patients; A. fumigatus and A. flavus were the most common pathogens identified.
Patients randomized to receive posaconazole were given a dose of 300 mg once daily (twice daily on Day 1) IV or tablet. Patients randomized to receive voriconazole were given a dose of 6 mg/kg twice daily Day 1 followed by 4 mg/kg twice daily IV, or oral 300 mg twice daily Day 1 followed by 200 mg twice daily. The recommended initial route of administration was IV; however, patients could begin oral therapy if clinically stable and able to tolerate oral dosing. The transition from IV to oral therapy occurred when the patient was clinically stable. The protocol recommended duration of therapy was 84 days with a maximum allowed duration of 98 days. Median treatment duration was 67 days for posaconazole patients and 64 days for voriconazole patients. Overall, 55% to 60% of patients began treatment with the IV formulation with a median duration of 9 days for the initial IV dosing.
The Intent to Treat (ITT) population included all patients randomized and receiving at least one dose of study treatment. All-cause mortality through Day 42 in the overall population (ITT) was 15.3% for posaconazole patients compared to 20.6% for voriconazole patients for an adjusted treatment difference of -5.3% with a 95% confidence interval of -11.6 to 1.0%. Consistent results were seen in patients with proven or probable invasive aspergillosis per EORTC criteria (see Table 32).
Table 32: Posaconazole Injection and Noxafil® (posaconazole) Delayed-Release Tablets Invasive Aspergillosis Treatment Study: All-Cause Mortality Through Day 42
| Posaconazole Injection and Delayed- Release Tablets | Voriconazole | ||||
| Population | N | n (%) | N | n (%) | Difference* (95% CI) |
| Intent to Treat | 288 | 44 (15.3) | 287 | 59 (20.6) | -5.3 (-11.6, 1.0) |
| Proven/Probable Invasive Aspergillosis | 163 | 31 (19.0) | 171 | 32 (18.7) | 0.3 (-8.2, 8.8) |
| * Adjusted treatment difference based on Miettinen and Nurminen’s method stratified by randomization factor (risk for mortality/poor outcome), using Cochran-Mantel-Haenszel weighting scheme. | |||||
Global clinical response at Week 6 was assessed by a blinded, independent adjudication committee based upon prespecified clinical, radiologic, and mycologic criteria. In the subgroup of patients with proven or probable invasive aspergillosis per EORTC criteria, the global clinical response of success (complete or partial response) at Week 6 was seen in 44.8% for posaconazole-treated patients compared to 45.6% for voriconazole-treated patients (see Table 33).
Table 33: Posaconazole Injection and Noxafil® (posaconazole) Delayed-Release Tablets Invasive Aspergillosis Treatment Study: Successful Global Clinical Response* at Week 6
| Posaconazole | Voriconazole | ||||
| Population | N | Success | N | Success | Difference† (95% CI) |
| Proven/Probable Invasive Aspergillosis | 163 | 73 (44.8) | 171 | 78 (45.6) | -0.6 (-11.2, 10.1) |
| * Successful Global Clinical Response was defined as survival with a partial or complete response. † Adjusted treatment difference based on Miettinen and Nurminen’s method stratified by randomization factor (risk for mortality/poor outcome), using Cochran-Mantel-Haenszel weighting scheme. | |||||
Two randomized, controlled studies were conducted using posaconazole as prophylaxis for the prevention of invasive fungal infections (IFIs) among patients at high risk due to severely compromised immune systems.
The first study (Noxafil® (posaconazole) Oral Suspension Study 1) was a randomized, double-blind trial that compared Noxafil® (posaconazole) Oral Suspension (200 mg three times a day) with fluconazole capsules (400 mg once daily) as prophylaxis against invasive fungal infections in allogeneic hematopoietic stem cell transplant (HSCT) recipients with Graft versus Host Disease (GVHD). Efficacy of prophylaxis was evaluated using a composite endpoint of proven/probable IFIs, death, or treatment with systemic antifungal therapy (patients may have met more than one of these criteria). This assessed all patients while on study therapy plus 7 days and at 16 weeks post-randomization. The mean duration of therapy was comparable between the 2 treatment groups (80 days, Noxafil® (posaconazole) Oral Suspension; 77 days, fluconazole). Table 34 contains the results from Noxafil® (posaconazole) Oral Suspension Study 1.
Table 34: Results from Blinded Clinical Study in Prophylaxis of IFI in All Randomized Patients with Hematopoietic Stem Cell Transplant (HSCT) and Graft-vs.-Host Disease (GVHD): Noxafil® (posaconazole) Oral Suspension Study 1
Posaconazole n=301 | Fluconazole n=299 | |
| On therapy plus 7 days | ||
| Clinical Failure* | 50 (17%) | 55 (18%) |
| Failure due to: | ||
| Proven/Probable IFI | 7 (2%) | 22 (7%) |
| (Aspergillus) | 3 (1%) | 17 (6%) |
| (Candida) | 1 (<1%) | 3 (1%) |
| (Other) | 3 (1%) | 2 (1%) |
| All Deaths Proven/probable fungal infection prior to death | 22 (7%) 2 (<1%) | 24 (8%) 6 (2%) |
| SAF† | 27 (9%) | 25 (8%) |
| Through 16 weeks | ||
| Clinical Failure*, ‡ | 99 (33%) | 110 (37%) |
| Failure due to: | ||
| Proven/Probable IFI | 16 (5%) | 27 (9%) |
| (Aspergillus) | 7 (2%) | 21 (7%) |
| (Candida) | 4 (1%) | 4 (1%) |
| (Other) | 5 (2%) | 2 (1%) |
| All Deaths Proven/probable fungal infection prior to death | 58 (19%) 10 (3%) | 59 (20%) 16 (5%) |
| SAF† | 26 (9%) | 30 (10%) |
| Event free lost to follow-up§ | 24 (8%) | 30 (10%) |
| *Patients may have met more than one criterion defining failure. † Use of systemic antifungal therapy (SAF) criterion is based on protocol definitions (empiric/IFI usage >4 consecutive days). ‡95% confidence interval (posaconazole-fluconazole) = (-11.5%, +3.7%). §Patients who are lost to follow-up (not observed for 112 days), and who did not meet another clinical failure endpoint. These patients were considered failures. | ||
The second study (Noxafil® (posaconazole) Oral Suspension Study 2) was a randomized, open-label study that compared Noxafil® (posaconazole) Oral Suspension (200 mg 3 times a day) with fluconazole suspension (400 mg once daily) or itraconazole oral solution (200 mg twice a day) as prophylaxis against IFIs in neutropenic patients who were receiving cytotoxic chemotherapy for AML or MDS. As in Noxafil® (posaconazole) Oral Suspension Study 1, efficacy of prophylaxis was evaluated using a composite endpoint of proven/probable IFIs, death, or treatment with systemic antifungal therapy (Patients might have met more than one of these criteria). This study assessed patients while on treatment plus 7 days and 100 days post-randomization. The mean duration of therapy was comparable between the 2 treatment groups (29 days, posaconazole; 25 days, fluconazole or itraconazole). Table 35 contains the results from Noxafil® (posaconazole) Oral Suspension Study 2.
Table 35: Results from Open-Label Clinical Study 2 in Prophylaxis of IFI in All Randomized Patients with Hematologic Malignancy and Prolonged Neutropenia: Noxafil® (posaconazole) Oral Suspension Study 2
Posaconazole n=304 | Fluconazole/Itraconazole n=298 | |
| On therapy plus 7 days | ||
| Clinical Failure*, † | 82 (27%) | 126 (42%) |
| Failure due to: | ||
| Proven/Probable IFI | 7 (2%) | 25 (8%) |
| (Aspergillus) | 2 (1%) | 20 (7%) |
| (Candida) | 3 (1%) | 2 (1%) |
| (Other) | 2 (1%) | 3 (1%) |
| All Deaths Proven/probable fungal infection prior to death | 17 (6%) 1 (<1%) | 25 (8%) 2 (1%) |
| SAF‡ | 67 (22%) | 98 (33%) |
| Through 100 days post-randomization | ||
| Clinical Failure† | 158 (52%) | 191 (64%) |
| Failure due to: | ||
| Proven/Probable IFI | 14 (5%) | 33 (11%) |
| (Aspergillus) | 2 (1%) | 26 (9%) |
| (Candida) | 10 (3%) | 4 (1%) |
| (Other) | 2 (1%) | 3 (1%) |
| All Deaths Proven/probable fungal infection prior to death | 44 (14%) 2 (1%) | 64 (21%) 16 (5%) |
| SAF‡ | 98 (32%) | 125 (42%) |
| Event free lost to follow-up§ | 34 (11%) | 24 (8%) |
| *95% confidence interval (posaconazole-fluconazole/itraconazole) = (-22.9%, -7.8%). † Patients may have met more than one criterion defining failure. ‡ Use of systemic antifungal therapy (SAF) criterion is based on protocol definitions (empiric/IFI usage >3 consecutive days). § Patients who are lost to follow-up (not observed for 100 days), and who did not meet another clinical failure endpoint. These patients were considered failures. | ||
In summary, 2 clinical studies of prophylaxis were conducted with the Noxafil® (posaconazole) oral suspension. As seen in the accompanying tables (Table 34 and Table 35), clinical failure represented a composite endpoint of breakthrough IFI, mortality and use of systemic antifungal therapy. In Noxafil® (posaconazole) Oral Suspension Study 1 (Table 34), the clinical failure rate of posaconazole (33%) was similar to fluconazole (37%), (95% CI for the difference posaconazole–comparator -11.5% to 3.7%) while in Noxafil® (posaconazole) Oral Suspension Study 2 (Table 35) clinical failure was lower for patients treated with posaconazole (27%) when compared to patients treated with fluconazole or itraconazole (42%), (95% CI for the difference posaconazole–comparator -22.9% to -7.8%).
All-cause mortality was similar at 16 weeks for both treatment arms in Noxafil® (posaconazole) Oral Suspension Study 1 [POS 58/301 (19%) vs. FLU 59/299 (20%)]; all-cause mortality was lower at 100 days for posaconazole-treated patients in Noxafil® (posaconazole) Oral Suspension Study 2 [POS 44/304 (14%) vs. FLU/ITZ 64/298 (21%)]. Both studies demonstrated fewer breakthrough infections caused by Aspergillus species in patients receiving posaconazole prophylaxis when compared to patients receiving fluconazole or itraconazole.
Posaconazole Injection
Posaconazole injection is a clear, colorless to yellow sterile liquid in single-dose Type I glass vials closed with bromobutyl rubber stopper and aluminum seal containing 300 mg of posaconazole in 16.7 mL of solution (18 mg of posaconazole per mL) (NDC 68083-577-01).
Posaconazole Injection
Store posaconazole injection vial refrigerated at 2°C to 8°C (36°F to 46°F). Storage conditions for the diluted posaconazole infusion solution are presented in another section of the prescribing information [see Dosage and Administration (2.5)].
Advise the patient to read the FDA-approved patient labeling (Patient Information).
Drug Interactions
Advise patients to inform their physician immediately if they:
• develop severe diarrhea or vomiting.
• are currently taking drugs that are known to prolong the QTc interval and are metabolized through CYP3A4.
• are currently taking a cyclosporine or tacrolimus, or they notice swelling in an arm or leg or shortness of breath.
• are taking other drugs or before they begin taking other drugs as certain drugs can decrease or increase the plasma concentrations of posaconazole.
Serious and Potentially Serious Adverse Reactions
Advise patients to inform their physician immediately if they:
• notice a change in heart rate or heart rhythm or have a heart condition or circulatory disease. Posaconazole can be administered with caution to patients with potentially proarrhythmic conditions.
• are pregnant, plan to become pregnant, or are nursing.
• have liver disease or develop itching, nausea or vomiting, their eyes or skin turn yellow, they feel more tired than usual or feel like they have the flu.
• have ever had an allergic reaction to other antifungal medicines such as ketoconazole, fluconazole, itraconazole, or voriconazole.
Brands listed are the trademarks of their respective owners.
Manufactured by:
Gland Pharma Limited
Hyderabad-500043, India
Revised: 05/2026
Posaconazole (poe-sa-KONE-a-zole) injection
What is posaconazole injection?
Posaconazole injection is a prescription medicine used in adults and children to help prevent or treat fungal infections that can spread throughout your body (invasive fungal infections). These infections are caused by fungi called Aspergillus or Candida. Posaconazole injection is used in people who have an increased chance of getting these infections due to a weak immune system. These include people who have had a hematopoietic stem cell transplantation (bone marrow transplant) with graft versus host disease or those with a low white blood cell count due to chemotherapy for blood cancers (hematologic malignancies).
Posaconazole injection is used for:
It is not known if posaconazole injection is safe and effective in children under 2 years of age.
Do not take posaconazole injection if you:
Ask your healthcare provider or pharmacist if you are not sure if you are taking any of these medicines.
Do not start taking a new medicine without talking to your healthcare provider or pharmacist.
Before you take posaconazole, tell your healthcare provider about all of your medical conditions, including if you:
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Posaconazole can affect the way other medicines work, and other medicines can affect the way posaconazole work, and can cause serious side effects.
Ask your healthcare provider or pharmacist for a list of these medicines if you are not sure.
Know the medicines you take. Keep a list of them with you to show your healthcare provider or pharmacist when you get a new medicine.
How should I take posaconazole?
Follow the instructions from your healthcare provider on how much posaconazole injection you should take and when to take it.
What are the possible side effects of posaconazole?
Posaconazole may cause serious side effects, including:
|
|
|
|
| |
The most common side effects of posaconazole in adults include:
|
|
|
|
|
|
| |
The most common side effects of posaconazole injection in children include:
|
|
|
|
|
|
| |
Tell your healthcare provider if you have any side effect that bothers you or that does not go away.
These are not all the possible side effects of posaconazole. For more information, ask your healthcare provider or pharmacist.
Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088.
How should I store posaconazole?
Posaconazole injection
Safely throw away medicine that is out of date or no longer needed.
Keep posaconazole and all medicines out of the reach of children.
General information about the safe and effective use of posaconazole.
Medicines are sometimes prescribed for purposes other than those listed in a Patient Information leaflet. Do not use posaconazole for a condition for which it was not prescribed. Do not give posaconazole to other people, even if they have the same symptoms that you have. It may harm them. You can ask your pharmacist or healthcare provider for information about posaconazole that is written for health professionals.
What are the ingredients in posaconazole injection?
Active ingredient: posaconazole
Inactive ingredients:
Posaconazole injection: Betadex Sulfobutyl Ether Sodium (SBECD), edetate sodium dihydrate, hydrochloric acid, sodium hydroxide, and water for injection.
Brands listed are the trademarks of their respective owners.
Manufactured by:
Gland Pharma Limited
Hyderabad-500043, India
For more information, call 866-770-7144
This Patient Information has been approved by the U.S. Food and Drug Administration.
Revised: 05/2026
Carton Label:
NDC 68083-577-01
Posaconazole
Injection
300 mg/16.7 mL
(18 mg/mL)
For Intravenous Use Only
Requires further dilution prior to infusion.
Rx only Sterile Single-Dose Vial
Discard Unused Portion

Posaconazole-spl-carton-label (Posaconazole Spl Carton Label)
Vial Label:
NDC 68083-577-01
Posaconazole
Injection
300 mg/16.7 mL
(18 mg/mL)
For Intravenous Use Only
Sterile Single-Dose Vial
Discard Unused Portion Rx only

Posaconazole-spl-vial-label (Posaconazole Spl Vial Label)
* Please review the disclaimer below.
