Amantadine Hcl Capsule, Liquid Filled
FDA Label NDC 69452-142

15 label sections · Submitted to the FDA by Bionpharma Inc. · Indications, Dosage, Usage, and Precautions

Structured Product Label

The following Structured Product Label (SPL) was submitted to the FDA by Bionpharma Inc. for the product Amantadine Hcl (NDC 69452-142). This document serves as the official prescribing information, containing essential scientific data and clinical materials required for healthcare providers and patients.

This specific version of the label includes detailed information regarding description, pharmacodynamics, pharmacokinetics, indications and usage, contraindications, warnings, precautions, information for patients:, and other regulatory disclosures. Use the navigation below to review specific sections of the FDA submission.

Description

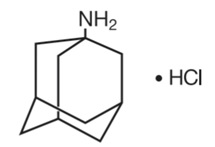
Amantadine hydrochloride, USP is designated chemically as 1-adamantanamine hydrochloride.

Structural Formula (Structure)

Structural Formula (Structure)

Amantadine hydrochloride is a stable white or nearly white crystalline powder, freely soluble in water and soluble in alcohol and in chloroform.

Amantadine hydrochloride has pharmacological actions as both an anti-Parkinson and an antiviral drug.

Each capsule intended for oral administration contains 100 mg amantadine hydrochloride and has the following inactive ingredients: yellow iron oxide, gelatin, glycerin, hydrogenated vegetable oil, lecithin-bleached, soybean oil, sorbitol, sorbitan, mannitol, titanium dioxide, white beeswax, vegetable shortening, simethicone and iron oxide (black imprint ink).

USP Dissolution Test Pending.

Pharmacodynamics

Mechanism of Action:  Antiviral The mechanism by which amantadine exerts its antiviral activity is not clearly understood. It appears to mainly prevent the release of infectious viral nucleic acid into the host cell by interfering with the function of the transmembrane domain of the viral M2 protein. In certain cases, amantadine is also known to prevent virus assembly during virus replication. It does not appear to interfere with the immunogenicity of inactivated influenza A virus vaccine.

Antiviral Activity: Amantadine inhibits the replication of influenza A virus isolates from each of the subtypes, i.e., H1N1, H2N2 and H3N2. It has very little or no activity against influenza B virus isolates. A quantitative relationship between the in vitro susceptibility of influenza A virus to amantadine and the clinical response to therapy has not been established in man. Sensitivity test results, expressed as the concentration of amantadine required to inhibit by 50% the growth of virus (ED 50) in tissue culture vary greatly (from 0.1 mcg/mL to 25.0 mcg/mL) depending upon the assay protocol used, size of virus inoculum, isolates of influenza A virus strains tested, and the cell type used. Host cells in tissue culture readily tolerated amantadine up to a concentration of 100 mcg/mL.

Drug Resistance: Influenza A variants with reduced in vitro sensitivity to amantadine have been isolated from epidemic strains in areas where adamantane derivatives are being used. Influenza viruses with reduced in vitro sensitivity have been shown to be transmissible and to cause typical influenza illness. The quantitative relationship between the in vitro sensitivity of influenza A variants to amantadine and the clinical response to therapy has not been established.

Mechanism of Action:  Parkinson's Disease The mechanism of action of amantadine in the treatment of Parkinson's disease and drug-induced extrapyramidal reactions is not known. Data from earlier animal studies suggest that amantadine hydrochloride may have direct and indirect effects on dopamine neurons. More recent studies have demonstrated that amantadine is a weak, non-competitive NMDA receptor antagonist (K 1= 10µM). Although amantadine has not been shown to possess direct anticholinergic activity in animal studies, clinically, it exhibits anticholinergic-like side effects such as dry mouth, urinary retention, and constipation.

Pharmacokinetics

Amantadine hydrochloride is well absorbed orally. Maximum plasma concentrations are directly related to dose for doses up to 200 mg/day. Doses above 200 mg/day may result in a greater than proportional increase in maximum plasma concentrations. It is primarily excreted unchanged in the urine by glomerular filtration and tubular secretion. Eight metabolites of amantadine have been identified in human urine. One metabolite, an N-acetylated compound, was quantified in human urine and accounted for 5-15% of the administered dose. Plasma acetylamantadine accounted for up to 80% of the concurrent amantadine plasma concentration in 5 of 12 healthy volunteers following the ingestion of a 200 mg dose of amantadine. Acetylamantadine was not detected in the plasma of the remaining seven volunteers. The contribution of this metabolite to efficacy or toxicity is not known.

There appears to be a relationship between plasma amantadine concentrations and toxicity. As concentration increases, toxicity seems to be more prevalent, however, absolute values of amantadine concentrations associated with adverse effects have not been fully defined.

Amantadine pharmacokinetics were determined in 24 normal adult male volunteers after the oral administration of a single amantadine hydrochloride 100 mg soft gel capsule. The mean ± SD maximum plasma concentration was 0.22 ± 0.03 mcg/mL (range: 0.18 to 0.32 mcg/mL). The time to peak concentration was 3.3 ± 1.5 hours (range: 1.5 to 8.0 hours). The apparent oral clearance was 0.28 ± 0.11 L/hr/kg (range: 0.14 to 0.62 L/hr/kg). The half-life was 17 ± 4 hours (range: 10 to 25 hours). Across other studies, amantadine plasma half-life has averaged 16 ± 6 hours (range: 9 to 31 hours) in 19 healthy volunteers.

After oral administration of a single dose of 100 mg amantadine syrup to five healthy volunteers, the mean ± SD maximum plasma concentration C max was 0.24 ± 0.04 mcg/mL and ranged from 0.18 to 0.28 mcg/mL. After 15 days of amantadine 100 mg b.i.d., the C max was 0.47 ± 0.11 mcg/mL in four of the five volunteers. The administration of amantadine tablets as a 200 mg single dose to 6 healthy subjects resulted in a C max of 0.51 ± 0.14 mcg/mL. Across studies, the time to C max (T max) averaged about 2 to 4 hours.

Plasma amantadine clearance ranged from 0.2 to 0.3 L/hr/kg after the administration of 5 mg to 25 mg intravenous doses of amantadine to 15 healthy volunteers.

In six healthy volunteers, the ratio of amantadine renal clearance to apparent oral plasma clearance was 0.79 ± 0.17 (mean ± SD).

The volume of distribution determined after the intravenous administration of amantadine to 15 healthy subjects was 3 to 8 L/kg, suggesting tissue binding. Amantadine, after single oral 200 mg doses to 6 healthy young subjects and to 6 healthy elderly subjects has been found in nasal mucus at mean ± SD concentrations of 0.15 ± 0.16, 0.28 ± 0.26, and 0.39 ± 0.34 mcg/g at 1, 4, and 8 hours after dosing, respectively. These concentrations represented 31 ± 33%, 59 ± 61%, and 95 ± 86% of the corresponding plasma amantadine concentrations. Amantadine is approximately 67% bound to plasma proteins over a concentration range of 0.1 to 2.0 mcg/mL. Following the administration of amantadine 100 mg as a single dose, the mean ± SD red blood cell to plasma ratio ranged from 2.7 ± 0.5 in 6 healthy subjects to 1.4 ± 0.2 in 8 patients with renal insufficiency.

The apparent oral plasma clearance of amantadine is reduced and the plasma half-life and plasma concentrations are increased in healthy elderly individuals age 60 and older. After single dose administration of 25 to 75 mg to 7 healthy, elderly male volunteers, the apparent plasma clearance of amantadine was 0.10 ± 0.04 L/hr/kg (range 0.06 to 0.17 L/hr/kg) and half-life was 29 ± 7 hours (range 20 to 41 hours). Whether these changes are due to decline in renal function or other age related factors is not known.

In a study of young healthy subjects (n = 20), mean renal clearance of amantadine, normalized for body mass index, was 1.5 fold higher in males compared to females (p < 0.032).

Compared with otherwise healthy adult individuals, the clearance of amantadine is significantly reduced in adult patients with renal insufficiency. The elimination half-life increases two to three fold or greater when creatinine clearance is less than 40 mL/min/1.73 m 2 and averages eight days in patients on chronic maintenance hemodialysis. Amanatadine is removed in negligible amounts by hemodialysis.

The pH of the urine has been reported to influence the excretion rate of amantadine hydrochloride. Since the excretion rate of amantadine hydrochloride increases rapidly when the urine is acidic, the administration of urine acidifying drugs may increase the elimination of the drug from the body.

Indications And Usage

Amantadine Hydrochloride Capsules, USP are indicated for the prophylaxis and treatment of signs and symptoms of infection caused by various strains of influenza A virus. Amantadine Hydrochloride Capsules, USP are also indicated in the treatment of parkinsonism and drug-induced extrapyramidal reactions.

Influenza A Prophylaxis: Amantadine Hydrochloride Capsules, USP are indicated for chemoprophylaxis against signs and symptoms of influenza A virus infection. Because Amantadine Hydrochloride does not completely prevent the host immune response to influenza A infection, individuals who take this drug may still develop immune responses to natural disease or vaccination and may be protected when later exposed to antigenically related viruses.

 Following vaccination during an influenza A outbreak, Amantadine Hydrochloride Capsules, USP prophylaxis should be considered for the 2- to 4-week time period required to develop an antibody response.

Influenza A Treatment: Amantadine Hydrochloride Capsules, USP are also indicated in the treatment of uncomplicated respiratory tract illness caused by influenza A virus strains especially when administered early in the course of illness. There are no well-controlled clinical studies demonstrating that treatment with Amantadine Hydrochloride Capsules, USP will avoid the development of influenza A virus pneumonitis or other complications in high risk patients.

There is no clinical evidence indicating that Amantadine Hydrochloride Capsules, USP are effective in the prophylaxis or treatment of viral respiratory tract illnesses other than those caused by influenza A virus strains.

The following points should be considered before initiating treatment or prophylaxis with Amantadine Hydrochloride Capsules, USP:

  • Amantadine Hydrochloride Capsules, USP is not a substitute for early vaccination on an annual basis as recommended by the Centers for Disease Control and Prevention Advisory Committee on Immunization Practices.
  • Influenza viruses change over time. Emergence of resistance mutations could decrease drug effectiveness.  Other factors (for example, changes in viral virulence) might also diminish clinical benefit of antiviral drugs.  Prescribers should consider available information on influenza drug susceptibility patterns and treatment effects when deciding whether to use Amantadine Hydrochloride Capsules, USP.
  • Parkinson's Disease/Syndrome: Amantadine Hydrochloride Capsules, USP are indicated in the treatment of idiopathic Parkinson's disease (Paralysis Agitans), postencephalitic parkinsonism, and symptomatic parkinsonism which may follow injury to the nervous system by carbon monoxide intoxication. It is indicated in those elderly patients believed to develop parkinsonism in association with cerebral arteriosclerosis. In the treatment of Parkinson's disease, Amantadine Hydrochloride Capsules, USP are less effective than levodopa, (-),-3-(3,4-dihydroxyphenyl)-L-alanine, and its efficacy in comparison with the anticholinergic antiparkinson drugs has not yet been established.

    Drug-Induced Extrapyramidal Reactions: Amantadine Hydrochloride Capsules, USP are indicated in the treatment of drug-induced extrapyramidal reactions. Although anticholinergic-type side effects have been noted with Amantadine Hydrochloride Capsules, USP when used in patients with drug-induced extrapyramidal reactions, there is a lower incidence of these side effects than that observed with the anticholinergic antiparkinson drugs.

Contraindications

Amantadine Hydrochloride Capsules are contraindicated in patients with known hypersensitivity to amantadine hydrochloride or to any of the other ingredients in Amantadine Hydrochloride Capsules.

Warnings

Deaths:  Deaths have been reported from overdose with  amantadine hydrochloride. The lowest reported acute lethal dose was 1 gram. Acute toxicity may be attributable to the anticholinergic effects of amantadine. Drug overdose has resulted in cardiac, respiratory, renal or central nervous system toxicity. Cardiac dysfunction includes arrhythmia, tachycardia and hypertension (see  OVERDOSAGE).

Deaths due to drug accumulation (overdose) have been reported in patients with renal impairment, who were prescribed higher than recommended doses of SYMMETREL (amantadine) for their level of renal function (see  DOSAGE AND ADMINISTRATION; Dosage of Impaired Renal Function and  OVERDOSAGE).

Suicide Attempts: Suicide attempts, some of which have been fatal, have been reported in patients treated with amantadine, many of whom received short courses for influenza treatment or prophylaxis. The incidence of suicide attempts is not known and the pathophysiologic mechanism is not understood. Suicide attempts and suicidal ideation have been reported in patients with and without prior history of psychiatric illness. Amantadine can exacerbate mental problems in patients with a history of psychiatric disorders or substance abuse. Patients who attempt suicide may exhibit abnormal mental states which include disorientation, confusion, depression, personality changes, agitation, aggressive behavior, hallucinations, paranoia, other psychotic reactions, and somnolence or insomnia. Because of the possibility of serious adverse effects, caution should be observed when prescribing amantadine hydrochloride capsules to patients being treated with drugs having CNS effects, or for whom the potential risks outweigh the benefit of treatment.

CNS Effects: Patients with a history of epilepsy or other "seizures" should be observed closely for possible increased seizure activity.

Patients receiving amantadine hydrochloride capsules who note central nervous system effects or blurring of vision should be cautioned against driving or working in situations where alertness and adequate motor coordination are important.

Other: Patients with a history of congestive heart failure or peripheral edema should be followed closely as there are patients who developed congestive heart failure while receiving amantadine hydrochloride capsules.

Patients with Parkinson's disease improving on amantadine hydrochloride capsules should resume normal activities gradually and cautiously, consistent with other medical considerations, such as the presence of osteoporosis or phlebothrombosis.

Because Amantadine Hydrochloride Capsules has anticholinergic effects and may cause mydriasis, it should not be given to patients with untreated angle closure glaucoma.

Corneal Edema: Corneal edema has been reported in patients taking amantadine. Symptoms include sudden onset of blurry vision, or progressive vision loss, with or without eye pain. Corneal involvement is usually bilateral. Onset can occur from a few weeks to several years after starting amantadine. Resolution of symptoms typically begins within weeks of amantadine cessation. However, corneal grafts have been required in some patients when the condition is not recognized. Permanent damage can occur if amantadine is continued. Ask patients if their vision has changed and obtain ophthalmologic examinations to rule out corneal edema should vision changes occur after initiation of therapy with amantadine. If corneal edema occurs, taper and discontinue amantadine (see  Dosage and Administration).

Precautions

Amantadine Hydrochloride should not be discontinued abruptly in patients with Parkinson's disease since a few patients have experienced a parkinsonian crisis, i.e., a sudden marked clinical deterioration, when this medication was suddenly stopped. The dose of anticholinergic drugs or of amantadine hydrochloride should be reduced if atropine-like effects appear when these drugs are used concurrently. Abrupt discontinuation may also precipitate delirium, agitation, delusions, hallucinations, paranoid reaction, stupor, anxiety, depression and slurred speech.

Neuroleptic Malignant Syndrome (NMS): Sporadic cases of possible Neuroleptic Malignant Syndrome (NMS) have been reported in association with dose reduction or withdrawal of amantadine hydrochloride therapy. Therefore, patients should be observed carefully when the dosage of amantadine hydrochloride is reduced abruptly or discontinued, especially if the patient is receiving neuroleptics.

NMS is an uncommon but life-threatening syndrome characterized by fever or hyperthermia; neurologic findings including muscle rigidity, involuntary movements, altered consciousness; mental status changes; other disturbances such as autonomic dysfunction, tachycardia, tachypnea, hyper- or hypotension; laboratory findings such as creatine phosphokinase elevation, leukocytosis, myoglobinuria, and increased serum myoglobin.

The early diagnosis of this condition is important for the appropriate management of these patients. Considering NMS as a possible diagnosis and ruling out other acute illnesses (e.g., pneumonia, systemic infection, etc.) is essential. This may be especially complex if the clinical presentation includes both serious medical illness and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever and primary central nervous system (CNS) pathology.

The management of NMS should include: 1) intensive symptomatic treatment and medical monitoring, and 2) treatment of any concomitant serious medical problems for which specific treatments are available. Dopamine agonists, such as bromocriptine, and muscle relaxants, such as dantrolene are often used in the treatment of NMS, however, their effectiveness has not been demonstrated in controlled studies.

Renal disease: Because amantadine hydrochloride is mainly excreted in the urine, it accumulates in the plasma and in the body when renal function declines. Thus, the dose of amantadine hydrochloride should be reduced in patients with renal impairment and in individuals who are 65 years of age or older (see DOSAGE AND ADMINISTRATION; Dosage for Impaired Renal Function).

Liver disease: Care should be exercised when administering amantadine hydrochloride to patients with liver disease. Rare instances of reversible elevation of liver enzymes have been reported in patients receiving amantadine hydrochloride, though a specific relationship between the drug and such changes has not been established.

Information For Patients:

Patients should be advised of the following information:

Blurry vision, eye pain, loss of vision, and/or impaired mental acuity may occur.

Gradually increase physical activity as the symptoms of Parkinson's disease improve.

Avoid excessive alcohol usage, since it may increase the potential for CNS effects such as dizziness, confusion, lightheadedness and orthostatic hypotension.

Avoid getting up suddenly from a sitting or lying position. If dizziness or lightheadedness occurs, notify physician.

Notify physician if mood/mental changes, swelling of extremities, difficulty urinating and/or shortness of breath occur.

Do not take more medication than prescribed because of the risk of overdose. If there is no improvement in a few days, or if medication appears less effective after a few weeks, discuss with a physician.

Consult physician before discontinuing medication.

Seek medical attention immediately if it is suspected that an overdose of medication has been taken.

Adverse Reactions

The adverse reactions reported most frequently at the recommended dose of amantadine hydrochloride (5 to 10%) are: nausea, dizziness (lightheadedness), and insomnia.

Less frequently (1 to 5%) reported adverse reactions are: depression, anxiety and irritability, hallucinations, confusion, anorexia, dry mouth, constipation, ataxia, livedo reticularis, peripheral edema, orthostatic hypotension, headache, somnolence, nervousness, dream abnormality, agitation, dry nose, diarrhea and fatigue.

Infrequently (0.1 to 1%) occurring adverse reactions are: congestive heart failure, psychosis, urinary retention, dyspnea, skin rash, vomiting, weakness, slurred speech, euphoria, thinking abnormality, amnesia, hyperkinesia, hypertension, decreased libido, and visual disturbance, including punctate subepithelial or other corneal opacity, corneal edema, decreased visual acuity, sensitivity to light, and optic nerve palsy.

Rare (less than 0.1%) occurring adverse reactions are: instances of convulsion, leukopenia, neutropenia, eczematoid dermatitis, oculogyric episodes, suicidal attempt, suicide, and suicidal ideation (see WARNINGS).

Other Adverse Reactions Reported During Postmarketing Experience With Amantadine Hydrochloride Usage Include:

Nervous System/Psychiatric-coma, stupor, delirium, hypokinesia, hypertonia, delusions, aggressive behavior, paranoid reaction, manic reaction, involuntary muscle contractions, gait abnormalities, paresthesia, EEG changes, and tremor. Abrupt discontinuation may also precipitate delirium, agitation, delusions, hallucinations, paranoid reaction, stupor, anxiety, depression and slurred speech;

Cardiovascular-cardiac arrest, arrhythmias including malignant arrhythmias, hypotension, and tachycardia;

Respiratory-acute respiratory failure, pulmonary edema, and tachypnea;

Gastrointestinal-dysphagia;

Hematologic-leukocytosis; agranulocytosis;

Special Senses-keratitis, mydriasis, and corneal edema;

Skin and Appendages-pruritus and diaphoresis;

Miscellaneous-neuroleptic malignant syndrome (see WARNINGS), allergic reactions including anaphylactic reactions, edema and fever.

Laboratory Test-elevated: CPK, BUN, serum creatinine, alkaline phosphatase, LDH, bilirubin, GGT, SGOT, and SGPT.

To report SUSPECTED ADVERSE REACTIONS, contact Bionpharma at 1-888-235-2466 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.

Overdosage

Deaths have been reported from overdose with amantadine hydrochloride. The lowest reported acute lethal dose was 1 gram. Because some patients have attempted suicide by overdosing with amantadine, prescriptions should be written for the smallest quantity consistent with good patient management.

Acute toxicity may be attributable to the anticholinergic effects of amantadine. Drug overdose has resulted in cardiac, respiratory, renal or central nervous system toxicity. Cardiac dysfunction includes arrhythmia, tachycardia and hypertension. Pulmonary edema and respiratory distress (including adult respiratory distress syndrome-ARDS) have been reported; renal dysfunction including increased BUN, decreased creatinine clearance and renal insufficiency can occur. Central nervous system effects that have been reported include insomnia, anxiety, agitation, aggressive behavior, hypertonia, hyperkinesia, ataxia, gait abnormality, tremor, confusion, disorientation, depersonalization, fear, delirium, hallucinations, psychotic reactions, lethargy, somnolence and coma. Seizures may be exacerbated in patients with prior history of seizure disorders. Hyperthermia has also been observed in cases where a drug overdose has occurred.

There is no specific antidote for an overdose of amantadine hydrochloride. However, slowly administered intravenous physostigmine in 1 and 2 mg doses in an adult 2 at 1- to 2-hour intervals and 0.5 mg doses in a child 3 at 5- to 10-minute intervals up to a maximum of 2 mg/hour have been reported to be effective in the control of central nervous system toxicity caused by amantadine hydrochloride. For acute overdosing, general supportive measures should be employed along with immediate gastric lavage or induction of emesis. Fluids should be forced, and if necessary, given intravenously. The pH of the urine has been reported to influence the excretion rate of amantadine hydrochloride. Since the excretion rate of amantadine hydrochloride increases rapidly when the urine is acidic, the administration of urine acidifying drugs may increase the elimination of the drug from the body. The blood pressure, pulse, respiration and temperature should be monitored. The patient should be observed for hyperactivity and convulsions; if required, sedation, and anticonvulsant therapy should be administered. The patient should be observed for the possible development of arrhythmias and hypotension; if required, appropriate antiarrhythmic and antihypotensive therapy should be given. Electrocardiographic monitoring may be required after ingestion, since malignant tachyarrhythmias can appear after overdose.

Care should be exercised when administering adrenergic agents, such as isoproterenol, to patients with an amantadine hydrochloride overdose, since the dopaminergic activity of amantadine hydrochloride has been reported to induce malignant arrhythmias.

The blood electrolytes, urine pH and urinary output should be monitored. If there is no record of recent voiding, catheterization should be done.

Dosage And Administration

The dosage of Amantadine Hydrochloride Capsules may need to be reduced in patients with congestive heart failure, peripheral edema, orthostatic hypotension, or impaired renal function (see Dosage for Impaired Renal Function).

How Supplied

Amantadine Hydrochloride Capsules, USP are available as yellow, soft gelatin capsules containing 100 mg of amantadine hydrochloride, in bottles of 100's (NDC 69452-142-20) and 500's (NDC 69452-142-30). Each capsule is imprinted with "A1" in black ink.

Store at 20 to 25°C (68 to 77°F) [See USP Controlled Room Temperature]. Protect from moisture.

Dispense in a tight, light-resistant container, as defined in the USP.

Keep out of reach of children.

References

1W.W. Wilson and A.H. Rajput, Amantadine-Dyazide ® Interaction, Can. Med. Assoc. J.129:974-975, 1983.

2D.F. Casey, N. Engl. J. Med. 298:516, 1978.

3C.D. Berkowitz, J. Pediatr. 95:144, 1979.

Manufactured for:
Bionpharma Inc.
Princeton, NJ 08540, USA

Rev. 06/25

Principal Display Panel - 100 Mg Capsule Bottle Label

BIONPHARMA

NDC 69452-142-20

Amantadine HCl
Capsules, USP

100 mg

Rx only

100 capsules

100 mg Container Label (Image01)

100 mg Container Label (Image01)

* Please review the disclaimer below.