Bexlutry Injection
FDA Label NDC 69945-177

43 label sections · Submitted to the FDA by Curium Us Llc · Indications, Dosage, Usage, and Precautions

Structured Product Label

The following Structured Product Label (SPL) was submitted to the FDA by Curium Us Llc for the product Bexlutry (NDC 69945-177). This document serves as the official prescribing information, containing essential scientific data and clinical materials required for healthcare providers and patients.

This specific version of the label includes detailed information regarding 1 indications and usage, 2.1 important safety instructions, 2.2 recommended dosage, 2.3 premedications and concomitant medications, 2.4 dosage modifications for adverse reactions, 2.5 preparation and administration, 2.6 radiation dosimetry, 3 dosage forms and strengths, and other regulatory disclosures. Use the navigation below to review specific sections of the FDA submission.

Label Section Quick Index

1 Indications And Usage

BEXLUTRY is indicated for the treatment of adults with somatostatin receptor-positive gastroenteropancreatic neuroendocrine tumors (GEP-NETs), including foregut, midgut, and hindgut neuroendocrine tumors.

Pediatric use information is approved for Advanced Accelerator Applications USA INC’s LUTATHERA (lutetium Lu 177 dotatate) injection for intravenous use. However, due to Advanced Accelerator Applications USA Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
2.1 Important Safety Instructions

BEXLUTRY is a radiopharmaceutical; handle with appropriate safety measures to minimize radiation exposure  [see Warnings and Precautions(5.1) ]. Use waterproof gloves and effective radiation shielding when handling BEXLUTRY. Radiopharmaceuticals, including BEXLUTRY, should be used by or under the control of healthcare providers who are qualified by specific training and experience in the safe use and handling of radiopharmaceuticals, and whose experience and training have been approved by the appropriate governmental agency authorized to license the use of radiopharmaceuticals.

Verify pregnancy status of females of reproductive potential prior to initiating BEXLUTRY  [see Use in Specific Populations(8.1), (8.3)].

Monitor patients closely for signs and symptoms of hypersensitivity reactions during and following the BEXLUTRY administration for a minimum of 2 hours in a setting where cardiopulmonary resuscitation medication and equipment are available  [see Warnings and Precautions(5.6)].

2.3 Premedications And Concomitant Medications

Somatostatin Analogs

  • Before initiating BEXLUTRY: Discontinue long-acting somatostatin analogs (e.g., long-acting octreotide) at least 4 weeks prior to initiating BEXLUTRY. Administer short-acting octreotide as needed; discontinue at least 24 hours prior to initiating BEXLUTRY  [see Drug Interactions(7.1)].
  • During BEXLUTRY treatment: Administer long-acting octreotide 30 mg intramuscularly between 4 to 24 hours after each BEXLUTRY dose. Do not administer long-acting octreotide within 4 weeks prior to each subsequent BEXLUTRY dose. Short-acting octreotide may be given for symptomatic management during BEXLUTRY treatment but must be withheld at least 24 hours before each BEXLUTRY dose.
  • Following BEXLUTRY treatment: Continue long-acting octreotide 30 mg intramuscularly every 4 weeks after completing BEXLUTRY until disease progression or for 18 months following treatment initiation at the discretion of the physician.
  • Antiemetics

    Administer antiemetics before the recommended amino acid solution.

    Amino Acid Solution

    Initiate an intravenous infusion of a sterile amino acid solution containing L-lysine and L-arginine (Table 1) 30 minutes before the start of the BEXLUTRY infusion. Use a three-way valve to administer the amino acid solution using the same venous access as BEXLUTRY or administer the amino acid solution through a separate venous access in the patient’s other arm. Continue the amino acid solution infusion during and for at least 3 hours after completion of the BEXLUTRY infusion. Do not decrease the dose of the amino acid solution if a reduced dose of BEXLUTRY is administered  [see Warnings and Precautions(5.4)].

    Table 1. Amino Acid Solution
    ItemSpecification
    L-lysine HClBetween 18 and 25 g a
    L-arginine HClBetween 18 and 25 g b
    Volume1 to 2 L
    Osmolality< 1200 mOsmol/kg

    aequivalent to 14.4 to 20 g L-lysine

    bequivalent to 14.9 to 20.7 g L-arginine

    Hypersensitivity Prophylaxis

    Premedicate patients who have had prior Grade 1 or 2 hypersensitivity reactions to BEXLUTRY. Do not re-challenge patients who experience Grade 3 or 4 hypersensitivity reactions to BEXLUTRY or lutetium Lu 177 dotatate injection  [see Warnings and Precautions(5.6)].

2.4 Dosage Modifications For Adverse Reactions

Recommended dose modifications of BEXLUTRY for adverse reactions are provided in Table 2.

Table 2. Recommended Dosage Modifications of BEXLUTRY for Adverse Reactions
Adverse reactionSeverity of adverse reactionaDose modification

Thrombocytopenia

[see Warnings and Precautions(5.2)]

First occurrence of Grade 2, 3, or 4

Withhold dose until complete or partial resolution (Grade 0 to 1).


Resume BEXLUTRY at 3.7 GBq (100 mCi) in patients with complete or partial resolution. If reduced dose does not result in Grade 2, 3, or 4 thrombocytopenia, administer BEXLUTRY at 7.4 GBq (200 mCi) as next dose.


Permanently discontinue BEXLUTRY for Grade 2 or higher thrombocytopenia requiring a dosing interval beyond 16 weeks.

Recurrent Grade 2, 3, or 4Permanently discontinue BEXLUTRY.
Anemia and Neutropenia
[see Warnings and Precautions(5.2)]
First occurrence of Grade 3 or 4

Withhold dose until complete or partial resolution (Grade 0, 1, or 2).


Resume BEXLUTRY at 3.7 GBq (100 mCi) in patients with complete or partial resolution. If reduced dose does not result in Grade 3 or 4 anemia or neutropenia, administer BEXLUTRY at 7.4 GBq (200 mCi) as next dose.


Permanently discontinue BEXLUTRY for Grade 3 or higher anemia or neutropenia requiring a dosing interval beyond 16 weeks.

Recurrent Grade 3 or 4Permanently discontinue BEXLUTRY.

Renal Toxicity

[see Warnings and Precautions(5.4)].

First occurrence of:
  • Creatinine clearance less than 40 mL/min; calculated using Cockcroft-Gault formula with actual body weight, or
  • 40% increase from baseline serum creatinine, or
  • 40% decrease from baseline creatinine clearance; calculated using Cockcroft-Gault formula with actual body weight.

Withhold dose until resolution or return to baseline.


Resume BEXLUTRY at 3.7 GBq (100 mCi) in patients with resolution or return to baseline. If reduced dose does not result in renal toxicity, administer BEXLUTRY at 7.4 GBq (200 mCi) as next dose.


Permanently discontinue BEXLUTRY for renal toxicity requiring a dosing interval beyond 16 weeks.

Recurrent renal toxicityPermanently discontinue BEXLUTRY.

Hepatotoxicity

[see Warnings and Precautions (5.5)]

First occurrence of:
  • Bilirubinemia greater than 3 times the upper limit of normal (Grade 3 or 4), or
  • Serum albumin less than 30 g/L with international normalized ratio (INR) > 1.5.

Withhold dose until resolution or return to baseline.


Resume BEXLUTRY at 3.7 GBq (100 mCi) in patients with resolution or return to baseline. If the reduced BEXLUTRY dose does not result in hepatotoxicity, administer BEXLUTRY at 7.4 GBq (200 mCi) as next dose.


Permanently discontinue BEXLUTRY for hepatotoxicity requiring a dosing interval beyond 16 weeks.

Recurrent hepatotoxicityPermanently discontinue BEXLUTRY.

Hypersensitivity Reactions b

[see Warnings and Precautions(5.6)]

First occurrence of Grade 3 or 4Permanently discontinue BEXLUTRY.
Any Other Adverse Reactions c
[see Adverse Reactions
(6.1)]
First occurrence of Grade 3 or 4

Withhold dose until complete or partial resolution (Grade 0 to 2).


Resume BEXLUTRY at 3.7 GBq (100 mCi) in patients with complete or partial resolution. If reduced dose does not result in Grade 3 or 4 toxicity, administer BEXLUTRY at 7.4 GBq (200 mCi) as next dose.


Permanently discontinue BEXLUTRY for Grade 3 or higher adverse reactions requiring a dosing interval beyond 16 weeks.

Recurrent Grade 3 or 4Permanently discontinue BEXLUTRY.

aGrading of severity is defined in the most current Common Terminology Criteria for Adverse Events (CTCAE).

bIncluding allergic reaction and anaphylaxis.

cNo dose modification required for hematological toxicities Grade 3 or Grade 4 solely due to lymphopenia.

2.5 Preparation And Administration

Preparation Instructions

  • Use aseptic technique and radiation shielding when handling or administering the BEXLUTRY solution. Use tongs when handling the vial to minimize radiation exposure.
  • Inspect the product visually under a shielded screen for particulate matter and discoloration prior to administration. Discard the vial if particulates and/or discoloration are present.
  • Do not inject the BEXLUTRY solution directly into any other intravenous solution.
  • Confirm the amount of radioactivity of BEXLUTRY delivered to the patient with an appropriate dose calibrator prior to and after each BEXLUTRY administration.
  • Dispose of any unused medicinal product or waste material in accordance with local and federal laws.
  • Administration Instructions

    • Prior to administration, flush the intravenous catheter used for BEXLUTRY administration with ≥ 10 mL of 0.9% Sodium Chloride Injection, USP to ensure patency and to minimize the risk of extravasation. Manage cases of extravasation as per institutional guidelines.
    • The gravity method, peristaltic pump method, or the syringe pump method may be used for the administration of the recommended dosage. Do not administer BEXLUTRY as an intravenous bolus.
    • When using the gravity or peristaltic pump method, infuse BEXLUTRY directly from its original container.
    • Use the peristaltic pump or syringe pump method when administering a reduced dose of BEXLUTRY following a dosage modification for an adverse reaction. When using the gravity method for a reduced dose, adjust the BEXLUTRY dose before the administration to avoid the delivery of an incorrect volume of BEXLUTRY.
    • Intravenous Methods of Administration

      Instructions for the Gravity Method

      • Insert a 2.5 cm, 20-gauge needle (short needle) into the BEXLUTRY vial and connect via a catheter to 500 mL 0.9% Sodium Chloride Injection, USP (used to transport the BEXLUTRY solution during the infusion). Ensure that the short needle does not touch the BEXLUTRY solution in the vial and do not connect this short needle directly to the patient. Do not allow the 0.9% Sodium Chloride Injection, USP to flow into the BEXLUTRY vial prior to the initiation of BEXLUTRY and do not inject the BEXLUTRY solution directly into the 0.9% Sodium Chloride Injection, USP.
      • Insert a second needle that is 9 cm, 18-gauge (long needle) into the BEXLUTRY vial ensuring that this long needle touches and is secured to the bottom of the BEXLUTRY vial during the entire infusion. Connect the long needle to the patient by an intravenous catheter that is pre-filled with 0.9% Sodium Chloride Injection, USP and that is used for the BEXLUTRY infusion into the patient.
      • Use a clamp or an infusion pump to regulate the flow of the 0.9% Sodium Chloride Injection, USP via the short needle into the BEXLUTRY vial at a rate of 50 mL/hour to 100 mL/hour for 5 to 10 minutes and then 200 mL/hour to 300 mL/hour for an additional 25 to 30 minutes (the 0.9% Sodium Chloride Injection, USP entering the vial through the short needle will carry the BEXLUTRY solution from the vial to the patient via the intravenous catheter connected to the long needle over a total duration of 30 to 40 minutes).
      • During the infusion, ensure that the level of solution in the BEXLUTRY vial remains constant.
      • Disconnect the vial from the long needle line and clamp the 0.9% Sodium Chloride Injection, USP line once the level of radioactivity is stable for at least five minutes.
      • Follow the infusion with an intravenous flush of 25 mL of 0.9% Sodium Chloride Injection, USP through the intravenous catheter to the patient.
      • Instructions for the Peristaltic Pump Method

        • Insert a filtered 2.5 cm, 20-gauge needle (short venting needle) into the BEXLUTRY vial. Ensure that the short needle does not touch the BEXLUTRY solution in the vial and do not connect this short needle directly to the patient or to the peristaltic pump.
        • Insert a second needle that is 9 cm, 18 gauge (long needle) into the BEXLUTRY vial ensuring that the long needle touches and is secured to the bottom of the BEXLUTRY vial during the entire infusion. Connect the long needle and a 0.9% Sodium Chloride Injection, USP to a 3-way stopcock valve via appropriate tubing.
        • Connect the output of the 3-way stopcock valve to tubing installed on the input side of the peristaltic pump according to manufacturer’s instructions.
        • Prime the line by opening the 3-way stopcock valve and pumping the BEXLUTRY solution through the tubing until it reaches the exit of the valve.
        • Prime the intravenous catheter that will be connected to the patient by opening the 3-way stopcock valve to the 0.9% Sodium Chloride Injection, USP and pumping the 0.9% Sodium Chloride Injection, USP until it exits the end of the catheter tubing.
        • Connect the primed intravenous catheter to the patient and set the 3-way stopcock valve such that the BEXLUTRY solution is in line with the peristaltic pump.
        • Infuse an appropriate volume of BEXLUTRY solution over a 30-40 min period to deliver the desired radioactivity.
        • When the desired BEXLUTRY radioactivity has been delivered, stop the peristaltic pump and then change the position of the 3-way stopcock valve so that the peristaltic pump is in line with the 0.9% Sodium Chloride Injection, USP. Restart the peristaltic pump and infuse an intravenous flush of 25 mL of 0.9% Sodium Chloride Injection, USP through the intravenous catheter to the patient.
        • Instructions for the Syringe Pump Method

          • Withdraw an appropriate volume of BEXLUTRY solution to deliver the desired radioactivity by using a disposable syringe fitted with a syringe shield and a disposable sterile needle that is 9 cm, 18 gauge (long needle). To aid the withdrawal of the solution, a filtered 2.5 cm, 20-gauge needle (short venting needle) can be used to reduce the resistance from the pressurized vial. Ensure that the short needle does not touch the BEXLUTRY solution in the vial.
          • Fit the syringe into the shielded pump and include a 3-way stopcock valve between the syringe and an intravenous catheter pre-filled with 0.9% Sodium Chloride Injection, USP and used for BEXLUTRY administration to the patient.
          • Infuse an appropriate volume of BEXLUTRY solution over a 30-40 min period to deliver the desired radioactivity.
          • When the desired BEXLUTRY radioactivity has been delivered, stop the syringe pump and then change the position of the 3-way stopcock valve to flush the syringe with 25 mL of 0.9% Sodium Chloride Injection, USP. Restart the syringe pump.
          • After the flush of the syringe has been completed, perform an intravenous flush with 25 mL of 0.9% Sodium Chloride Injection, USP through the intravenous catheter to the patient.

2.6 Radiation Dosimetry

The maximum penetration of lutetium-177 in tissue is 2.2 mm and the mean penetration is 0.67 mm. The mean and standard deviation (SD) of the estimated radiation absorbed doses for adults receiving BEXLUTRY are shown in Table 3. 

Table 3. Estimated Radiation Absorbed Dose for Lutetium Lu 177 Dotatate Injection in Adults in NETTER-1
Absorbed dose per unit activity
(Gy/GBq)
(N=20)
Calculated absorbed dose for 4 x 7.4 GBq
(29.6 GBq cumulative activity)
(Gy)
OrganMeanSDMeanSD
Adrenals0.0370.0161.10.5
Brain0.0270.0160.80.5
Breasts0.0270.0150.80.4
Gallbladder wall0.0420.0191.20.6
Heart wall0.0320.0150.90.4
Kidneys0.6540.29519.48.7
Liver a0.2990.2268.96.7
Lower large intestine wall0.0290.0160.90.5
Lungs0.0310.0150.90.4
Muscle0.0290.0150.80.4
Osteogenic cells0.1510.2684.57.9
Ovaries b0.0310.0130.90.4
Pancreas0.0380.0161.10.5
Red marrow c0.0350.0291.00.8
Skin0.0270.0150.80.4
Small intestine0.0310.0150.90.5
Spleen0.8460.80425.123.8
Stomach wall0.0320.0150.90.5
Testes d0.0260.0180.80.5
Thymus0.0280.0150.80.5
Thyroid0.0270.0160.80.5
Total body0.0520.0271.60.8
Upper large intestine wall0.0320.0150.90.4
Urinary bladder wall0.4370.17612.85.3
Uterus b0.0320.0131.00.4

aN = 18 (two patients excluded because the liver absorbed dose was biased by the uptake of the liver metastases).

bN = 9 (female patients only).

cRed marrow dosimetry estimates were determined using blood radioactivity.

dN = 11 (male patients only).

Pediatric use information is approved for Advanced Accelerator Applications USA INC’s LUTATHERA (lutetium Lu 177 dotatate) injection for intravenous use. However, due to Advanced Accelerator Applications USA Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.

3 Dosage Forms And Strengths

Injection: 370 MBq/mL (10 mCi/mL) of lutetium Lu 177 dotatate, at time of calibration, sufficient for 7.4 GBq (200 mCi) at the time of patient administration, as a clear and colorless to yellow solution in a single-dose vial.

4 Contraindications

None.

5.1 Risk From Radiation Exposure

BEXLUTRY contributes to a patient’s overall long-term cumulative radiation exposure. Long-term cumulative radiation exposure is associated with an increased risk for cancer. These risks of radiation associated with the use of BEXLUTRY are greater in pediatric patients than in adults [ see Use in Specific Populations ( 8.4) ].

Radiation can be detected in the urine for up to 30 days following BEXLUTRY administration. Minimize radiation exposure to patients, medical personnel, and household contacts during and after treatment with BEXLUTRY consistent with institutional good radiation safety practices, patient management procedures, Nuclear Regulatory Commission patient-release guidance, and instructions to the patient for follow-up radiation protection at home  [see Dosage andAdministration(2.1), Clinical Pharmacology(12.3)].

5.2 Myelosuppression

In NETTER-1, myelosuppression occurred more frequently in patients receiving lutetium Lu 177 dotatate injection with long-acting octreotide compared to patients receiving high-dose long-acting octreotide (all Grades/Grade 3 or 4): anemia (81%/0) versus (54%/1%); thrombocytopenia (53%/1%) versus (17%/0); and neutropenia (26%/3%) versus (11%/0). In NETTER-1, platelet nadir occurred at a median of 5.1 months following the first dose. Of the 59 patients who developed thrombocytopenia, 68% had platelet recovery to baseline or normal levels. The median time to platelet recovery was 2 months. Fifteen of the nineteen patients in whom platelet recovery was not documented had post-nadir platelet counts. Among these 15 patients, 5 improved to Grade 1, 9 to Grade 2, and 1 to Grade 3.

Monitor blood cell counts. Withhold dose, reduce dose, or permanently discontinue BEXLUTRY based on the severity of myelosuppression  [see Dosage andAdministration(2.4)].

5.3 Secondarymyelodysplastic Syndrome And Leukemia

In NETTER-1, with a median follow-up time of 76 months in the main study, myelodysplastic syndrome (MDS) was reported in 2.3% of patients receiving lutetium Lu 177 dotatate injection with long-acting octreotide compared to no patients receiving high-dose long-acting octreotide.

In ERASMUS, 16 patients (2.0%) developed MDS and 4 (0.5%) developed acute leukemia. The median time to onset was 29 months (9 to 45 months) for MDS and 55 months (32 to 125 months) for acute leukemia.

5.4 Renal Toxicity

In ERASMUS, 8 patients (< 1%) developed renal failure 3 to 36 months following lutetium Lu 177 dotatate injection. Two of these patients had underlying renal impairment or risk factors for renal failure (e.g., diabetes or hypertension) and required dialysis.

Administer the recommended amino acid solution before, during and after BEXLUTRY  [see Dosage and Administration(2.3)]to decrease the reabsorption of BEXLUTRY through the proximal tubules and decrease the radiation dose to the kidneys. Advise patients to hydrate and to urinate frequently before, on the day of, and the day after administration of BEXLUTRY.

Monitor serum creatinine and calculated creatinine clearance. Withhold dose, reduce dose, or permanently discontinue BEXLUTRY based on the severity of renal toxicity  [see Dosage and Administration(2.4)].

Patients with baseline renal impairment may be at increased risk of toxicity due to increased radiation exposure  [see Use in Specific Populations(8.6)].

5.5 Hepatotoxicity

In ERASMUS, 2 patients (< 1%) were reported to have hepatic tumor hemorrhage, edema, or necrosis, with one patient experiencing intrahepatic congestion and cholestasis. Patients with hepatic metastasis may be at increased risk of hepatotoxicity due to radiation exposure.

Monitor transaminases, bilirubin, serum albumin, and international normalized ratio (INR) during treatment. Withhold dose, reduce dose, or permanently discontinue BEXLUTRY based on the severity of hepatotoxicity  [see Dosage and Administration(2.4)].

5.6 Hypersensitivity Reactions

Hypersensitivity reactions, including angioedema, occurred in patients treated with lutetium Lu 177 dotatate injection  [see Adverse Reactions (6.2)].Monitor patients closely for signs and symptoms of hypersensitivity reactions, including anaphylaxis, during and following BEXLUTRY administration for a minimum of 2 hours in a setting where cardiopulmonary resuscitation medication and equipment are available. Discontinue the infusion upon the first observation of any signs or symptoms consistent with a severe hypersensitivity reaction and initiate appropriate therapy.

Premedicate patients with a history of Grade 1 or 2 hypersensitivity reactions to lutetium Lu 177 dotatate injection before subsequent doses  [see Dosage and Administration(2.3)].Permanently discontinue BEXLUTRY in patients who experience Grade 3 or 4 hypersensitivity reactions  [see Dosage and Administration(2.4)].

5.7 Neuroendocrine Hormonal Crisis

Neuroendocrine hormonal crises, manifesting with flushing, diarrhea, bronchospasm and hypotension, occurred in < 1% of patients in ERASMUS and typically occurred during or within 24 hours following the initial lutetium Lu 177 dotatate injection dose. Two (< 1%) patients were reported to have hypercalcemia.

Monitor patients for flushing, diarrhea, hypotension, bronchoconstriction or other signs and symptoms of tumor-related hormonal release. Administer intravenous somatostatin analogs, fluids, corticosteroids, and electrolytes as indicated.

5.8 Embryo-Fetal Toxicity

Based on its mechanism of action, lutetium Lu 177 dotatate injection can cause fetal harm when administered to a pregnant woman  [see Clinical Pharmacology ( 12.1)] . There are no available data on lutetium Lu 177 dotatate injection use in pregnant women. No animal studies using lutetium Lu 177 dotatate have been conducted to evaluate its effect on female reproduction and embryo-fetal development; however, radioactive emissions, including those from BEXLUTRY can cause fetal harm.

Verify pregnancy status of females of reproductive potential prior to initiating BEXLUTRY  [see Dosage and Administration ( 2.1) ].

Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with BEXLUTRY and for 7 months after the last dose. Advise males with female partners of reproductive potential to use effective contraception during treatment with BEXLUTRY and for 4 months after the last dose  [see Use in Specific Populations ( 8.1, 8.3)] .

5.9 Risk Of Infertility

BEXLUTRY may cause infertility in males and females. The recommended cumulative dose of 29.6 GBq of lutetium Lu 177 dotatate injection results in a radiation absorbed dose to the testes and ovaries within the range where temporary or permanent infertility can be expected following external beam radiotherapy  [see Dosage and Administration(2.6), Use in Specific Populations(8.3)].

6 Adverse Reactions

The following clinically significant adverse reactions are described elsewhere in the labeling:

  • Myelosuppression  [see Warnings and Precautions(5.2)]
  • Secondary Myelodysplastic Syndrome and Leukemia  [see Warnings and Precautions (5.3)]
  • Renal Toxicity  [see Warnings and Precautions(5.4)]
  • Hepatotoxicity  [see Warnings and Precautions(5.5)]
  • Hypersensitivity Reactions  [see Warnings and Precautions(5.6)]
  • Neuroendocrine Hormonal Crisis  [see Warnings and Precautions(5.7)]

6.1 Clinical Trials Experience

Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.

The data in WARNINGS AND PRECAUTIONS reflect exposure to lutetium Lu 177 dotatate injection in 111 patients with advanced, progressive midgut neuroendocrine tumors (NETTER-1). Safety data in WARNINGS AND PRECAUTIONS were also obtained in an additional 22 patients in a non-randomized pharmacokinetic sub-study of NETTER-1 and in a subset of patients (811 of 1214) with advanced somatostatin receptor-positive tumors enrolled in ERASMUS [see Warnings and Precautions(5)].

Adult Population

NETTER-1

The safety data of lutetium Lu 177 dotatate injection with octreotide was evaluated in NETTER-1 [see Clinical Studies(14.1)].Patients with progressive, somatostatin receptor-positive midgut carcinoid tumors received lutetium Lu 177 dotatate injection 7.4 GBq (200 mCi) administered every 8 to 16 weeks concurrently with the recommended amino acid solution and with long-acting octreotide (30 mg administered by intramuscular injection within 24 hours of each lutetium Lu 177 dotatate injection dose) (N = 111), or high-dose octreotide (defined as long-acting octreotide 60 mg by intramuscular injection every 4 weeks) (N = 112) [see Clinical Studies(14.1)].Among patients receiving lutetium Lu 177 dotatate injection with octreotide, 79% received a cumulative dose > 22.2 GBq (> 600 mCi) and 76% of patients received all four planned doses. Six percent (6%) of patients required a dose reduction and 13% of patients discontinued lutetium Lu 177 dotatate injection. Five patients discontinued lutetium Lu 177 dotatate injection for renal-related events and 4 discontinued for hematological toxicities.

Table 4 and Table 5 summarize the incidence of adverse reactions and laboratory abnormalities, respectively. The most common Grade 3-4 adverse reactions occurring with a greater frequency among patients receiving lutetium Lu 177 dotatate injection with octreotide compared to patients receiving high-dose octreotide include: lymphopenia (44%), increased gamma-glutamyltransferase (GGT) (20%), vomiting (7%), nausea and increased aspartate aminotransferase (AST) (5% each), and increased alanine aminotransferase (ALT), hyperglycemia and hypokalemia (4% each).

Table 4. Adverse Reactions Occurring at Higher Incidence in Patients Receiving Lutetium Lu 177 Dotatate Injection with Long-Acting Octreotide Compared to High-Dose Long-Acting Octreotide (Between Arm Difference of ≥ 5% All Grades or ≥ 2% Grades 3-4) a
Adverse reaction aLutetiumLu 177Dotatate Injection with Long-acting Octreotide
(30 mg)

(N = 111)
Long-acting Octreotide
(60 mg)

(N = 112)
All Grades
%
Grades 3-4
%
All Grades
%
Grades 3-4
%
Gastrointestinal disorders
Nausea655122
Vomiting537100
Abdominal pain263193
Diarrhea263181
Constipation10050
General disorders
Fatigue381262
Peripheral edema16091
Pyrexia8030
Metabolism and nutrition disorders
Decreased appetite210113
Nervous system disorders
Headache17050
Dizziness17080
Dysgeusia8020
Vascular disorders
Flushing14190
Hypertension12272
Musculoskeletal and connective tissue disorders
Back pain132100
Pain in extremity11050
Myalgia5000
Neck pain5000
Renal and urinary disorders
Renal failure b13341
Radiation-related urinary tract adverse reactions c8030
Psychiatric disorders
Anxiety12150
Skin and subcutaneous tissue disorders
Alopecia12020
Respiratory, thoracic and mediastinal disorders
Cough11160
Cardiac disorders
Atrial fibrillation5100

aNational Cancer Institute Common Terminology Criteria for Adverse Events (CTCAE) Version 4.03. Only displays adverse reactions occurring at a higher incidence in lutetium Lu 177 dotatate injection-treated patients [between arm difference of ≥ 5% (all Grades) or ≥ 2% (Grades 3-4)].

bIncludes the terms: Glomerular filtration rate decreased, acute kidney injury, acute prerenal failure, azotemia, renal disorder, renal failure, renal impairment.

cIncludes the terms: Dysuria, micturition urgency, nocturia, pollakiuria, renal colic, renal pain, urinary tract pain and urinary incontinence.

Table 5. Laboratory Abnormalities Occurring at Higher Incidence in Patients Receiving Lutetium Lu 177 Dotatate Injection with Long-Acting Octreotide Compared to High-Dose Long-Acting Octreotide (Between Arm Difference of ≥ 5% All Grades or ≥ 2% Grades 3-4) a,b
Laboratory abnormalitybLutetiumLu 177Dotatate Injectionwith Long-acting Octreotide
(30 mg)

(N = 111)
Long-acting Octreotide
(60 mg)

(N = 112)
All Grades
%
Grades 3-4
%
All Grades
%
Grades 3-4
%
Hematology
Lymphopenia9044395
Anemia810551
Leukopenia552200
Thrombocytopenia531170
Neutropenia263110
Renal/Metabolic
Creatinine increased851730
Hyperglycemia824672
Hyperuricemia346306
Hypocalcemia320140
Hypokalemia264212
Hyperkalemia190110
Hypernatremia17070
Hypoglycemia15080
Hepatic
GGT increased66206716
Alkaline phosphatase increased655559
AST increased505350
ALT increased434340
Blood bilirubin increased302280

aValues are worst grade observed after randomization.

bNational Cancer Institute Common Terminology Criteria for Adverse Events (CTCAE) Version 4.03. Only displays laboratory abnormalities occurring at a higher incidence in lutetium Lu 177 dotatate injection-treated patients [between arm difference of ≥ 5% (all Grades) or ≥ 2% (Grades 3-4)].

ERASMUS

Safety data are available from 1214 patients in ERASMUS, an international, single-institution, single-arm, open-label trial of patients with somatostatin receptor-positive tumors (neuroendocrine and other primaries). Patients received lutetium Lu 177 dotatate injection 7.4 GBq (200 mCi) administered every 6 to 13 weeks with or without octreotide. Retrospective medical record review was conducted on a subset of 811 patients to document serious adverse reactions. Eighty-one (81%) percent of patients in the subset received a cumulative dose ≥ 22.2 GBq (≥ 600 mCi). With a median follow-up time of more than 4 years, the following rates of serious adverse reactions were reported: myelodysplastic syndrome (2%), acute leukemia (1%), renal failure (2%), hypotension (1%), cardiac failure (2%), myocardial infarction (1%), and neuroendocrine hormonal crisis (1%).

Pediatric use information is approved for Advanced Accelerator Applications USA INC’s LUTATHERA (lutetium Lu 177 dotatate) injection for intravenous use. However, due to Advanced Accelerator Applications USA Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.

6.2 Postmarketing Experience

The following adverse reactions have been identified during post approval use of lutetium Lu 177 dotatate injection. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.

Immune System Disorders: hypersensitivity reactions, including angioedema

7.1 Somatostatin Analogs

Somatostatin and its analogs competitively bind to somatostatin receptors and may interfere with the efficacy of BEXLUTRY. Discontinue long-acting somatostatin analogs at least 4 weeks and short-acting octreotide at least 24 hours prior to each BEXLUTRY dose. Administer short- and long-acting octreotide during BEXLUTRY treatment as recommended [ see Dosage and Administration(2.3)].

7.2 Glucocorticoids

Glucocorticoids can induce down-regulation of subtype 2 somatostatin receptors (SSTR2). Avoid repeated administration of high doses of glucocorticoids during treatment with BEXLUTRY.

8.1 Pregnancy

Risk Summary

Based on its mechanism of action, lutetium Lu 177 dotatate injection can cause fetal harm when administered to a pregnant woman [ see Clinical Pharmacology(12.1)]. There are no available data on lutetium Lu 177 dotatate injection use in pregnant women. No animal studies using lutetium Lu 177 dotatate have been conducted to evaluate its effect on female reproduction and embryo-fetal development; however, radioactive emissions, including those from BEXLUTRY, can cause fetal harm. Advise pregnant women of the potential risk to a fetus.

In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.

8.2 Lactation

Risk Summary

There are no data on the presence of lutetium Lu 177 dotatate in human milk, or its effects on the breastfed child or milk production. No lactation studies in animals were conducted. Because of the potential risk for serious adverse reactions in breastfed children, advise women not to breastfeed during treatment with BEXLUTRY and for 2.5 months after the last dose.

8.3 Females And Males Of Reproductive Potential

Based on mechanism of action, lutetium Lu 177 dotatate injection can cause fetal harm when administered to a pregnant woman [ see Use in Specific Populations(8.1)].

Pregnancy Testing

Verify pregnancy status of females of reproductive potential prior to initiating BEXLUTRY [ see Use in Specific Populations(8.1)].

Contraception

Females

Advise females of reproductive potential to use effective contraception during treatment with BEXLUTRY and for 7 months after the last dose.

Males

Advise males with female partners of reproductive potential to use effective contraception during treatment with BEXLUTRY and for 4 months after the last dose [ see Clinical Pharmacology(12.1), Nonclinical Toxicology(13.1)].

Infertility

The recommended cumulative dose of 29.6 GBq of BEXLUTRY results in a radiation absorbed dose to the testes and ovaries within the range where temporary or permanent infertility can be expected following external beam radiotherapy [ see Dosage and Administration(2.6)].

8.4 Pediatric Use

Somatostatin Receptor-Positive Gastroenteropancreatic Neuroendocrine Tumors

The risks of radiation exposure associated with BEXLUTRY are greater in pediatric patients than in adult patients due to longer life expectancy.

The safety and effectiveness of BEXLUTRY have not been established in pediatric patients younger than 12 years old with somatostatin receptor-positive GEP-NETs.

Pediatric use information is approved for Advanced Accelerator Applications USA INC’s LUTATHERA (lutetium Lu 177 dotatate) injection for intravenous use. However, due to Advanced Accelerator Applications USA Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.

8.5 Geriatric Use

Of the 1325 patients treated with lutetium Lu 177 dotatate injection in clinical trials, 438 patients (33%) were 65 years and older. No overall differences in safety or effectiveness were observed between older and younger patients.

8.6 Renal Impairment

No dose adjustment is recommended for patients with baseline mild to moderate (creatinine clearance 30 to 89 mL/min by Cockcroft-Gault formula) renal impairment. However, patients with baseline mild or moderate renal impairment may be at greater risk of toxicity, including renal toxicity, due to increased radiation exposure. Perform more frequent assessments of renal function in patients with baseline mild to moderate impairment. The pharmacokinetic profile and safety of lutetium Lu 177 dotatate injection in patients with baseline severe renal impairment (creatinine clearance < 30 mL/min by Cockcroft-Gault formula) or end-stage renal disease have not been studied [ see Warnings and Precautions(5.4)].

8.7 Hepatic Impairment

No dose adjustment is recommended for patients with baseline mild or moderate hepatic impairment. The pharmacokinetic profile and safety of lutetium Lu 177 dotatate injection in patients with baseline severe hepatic impairment (total bilirubin > 3 times upper limit of normal, regardless of AST level) have not been studied.

11 Description

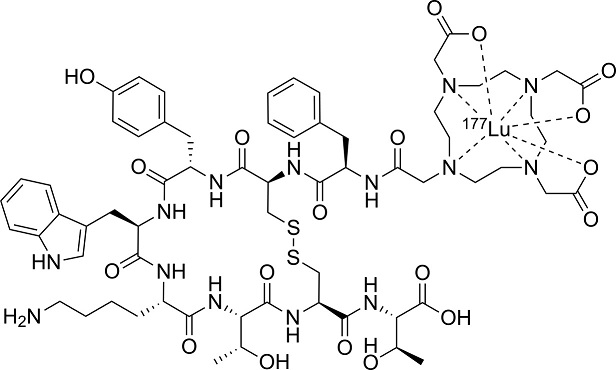
Lutetium Lu 177 dotatate is a radiolabeled somatostatin analog. The drug substance lutetium Lu 177 dotatate is a cyclic peptide linked with the covalently bound chelator 1,4,7,10-tetraazacyclododecane-1,4,7,10-tetraacetic acid to a radionuclide.

Lutetium Lu 177 dotatate is described as lutetium (Lu 177)-N-[(4,7,10-Tricarboxymethyl-1,4,7,10-tetraazacyclododec-1-yl) acetyl]-D-phenylalanyl-L-cysteinyl-L-tyrosyl-D-tryptophanyl-L-lysyl-L-threoninyl-L-cysteinyl-L-threonine-cyclic (2-7) disulfide. The molecular weight is 1609.6 Daltons and the structural formula is as follows:

Image Description (Lutetium Lu 177 Dotatate Injection 01)

Image Description (Lutetium Lu 177 Dotatate Injection 01)

BEXLUTRY, 370 MBq/mL (10 mCi/mL), is a sterile, clear, colorless to yellow solution for intravenous use. Each single-dose vial contains sodium ascorbate (15 mg/mL), dehydrated alcohol (ethanol) (19.72 mg/mL), diethylenetriaminepentaacetic acid (0.05 mg/mL), and water for injection (ad 1 mL). The pH range of the solution is 4.5 to 6.

11.1 Physical Characteristics

Lutetium-177 decays to stable hafnium-177 with a half-life of 6.647 days, by emitting beta-minus radiation with a maximum energy of 0.498 MeV (79%) and photonic radiation (γ) of 0.208 MeV (11%) and 0.113 MeV (6.2%). The main radiations of lutetium-177 are detailed in Table 6.

Table 6. Lutetium-177 Main Radiations
RadiationEnergy (keV)Iβ-%Iγ%
β -176.512.2
β -248.10.05
β -384.99.1
β -497.878.6
γ71.60.15
γ112.96.20
γ136.70.05
γ208.411.0
γ249.70.21
γ321.30.22

11.2 External Radiation

Table 7 summarizes the radioactive decay properties of lutetium-177.

Table 7. Physical Decay Chart: Lutetium-177 Physical Half-Life = 6.647 Days
HoursFraction remainingHoursFraction remaining
01.00048 (2 days)0.812
10.99672 (3 days)0.731
20.991168 (7 days)0.482
50.979336 (14 days)0.232
100.958720 (30 days)0.044
24 (1 day)0.9011080 (45 days)0.009

12.1 Mechanism Of Action

Lutetium Lu 177 dotatate binds to somatostatin receptors with highest affinity for subtype 2 somatostatin receptors (SSTR2). Upon binding to somatostatin receptor expressing cells, including malignant somatostatin receptor-positive tumors, the compound is internalized. The beta-minus emission from lutetium-177 induces cellular damage by formation of free radicals in somatostatin receptor-positive cells and in neighboring cells.

12.2 Pharmacodynamics

Lutetium Lu 177 dotatate exposure-response relationships and the time course of pharmacodynamics response are unknown.

Cardiac Electrophysiology

The ability of lutetium Lu 177 dotatate injection to prolong the QTc interval at the recommended dose was assessed in an open-label study in 20 patients with somatostatin receptor-positive midgut carcinoid tumors. No large changes in the mean QTc interval (i.e., > 20 ms) were detected.

12.3 Pharmacokinetics

The pharmacokinetics (PK) of lutetium Lu 177 dotatate have been characterized in patients with progressive, somatostatin receptor-positive neuroendocrine tumors. The mean blood exposure (area under the curve) of lutetium Lu 177 dotatate at the recommended dose is 41 ng.h/mL [coefficient of variation (CV) 36%]. The mean maximum blood concentration (C max) for lutetium Lu 177 dotatate is 10 ng/mL (CV 50%), which generally occurred at the end of the lutetium Lu 177 dotatate infusion.

Distribution

The mean volume of distribution (V z) for lutetium Lu 177 dotatate is 460 L (CV 54%).

The non-radioactive lutetium Lu 175 dotatate is 43% bound to human plasma proteins.

Within 4 hours after administration, lutetium Lu 177 dotatate distributes in kidneys, tumor lesions, liver, spleen, and, in some patients, pituitary gland and thyroid. The co-administration of amino acids reduced the median radiation dose to the kidneys by 47% (34% to 59%) and increased the mean beta-phase blood clearance of lutetium Lu 177 dotatate by 36%.

Elimination

The mean clearance (CL) is 4.5 L/h (CV 31%) and the mean terminal half-life is 71 (±28) hours for lutetium 177 dotatate.

Metabolism

Lutetium Lu 177 dotatate does not undergo hepatic metabolism.

Excretion

Lutetium Lu 177 dotatate is primarily eliminated renally with cumulative excretion of 44% within 5 hours, 58% within 24 hours, and 65% within 48 hours following lutetium Lu 177 dotatate injection administration. Prolonged elimination of lutetium Lu 177 dotatate in the urine is expected; however, based on the half-life of lutetium-177 and terminal half-life of lutetium Lu 177 dotatate, greater than 99% of the administered radioactivity will be eliminated within 14 days after administration of lutetium Lu 177 dotatate injection [ see Warnings and Precautions (5.1)].

Drug Interaction Studies

In Vitro Studies

CYP450 enzymes: The non-radioactive lutetium Lu 175 dotatate is not an inhibitor or inducer of cytochrome P450 (CYP) 1A2, 2B6, 2C9, 2C19 or 2D6 in vitro.

Transporters:The non-radioactive lutetium Lu 175 dotatate is not an inhibitor of P-glycoprotein, BCRP, OAT1, OAT3, OCT1, OCT2, OATP1B1, or OATP1B3 in vitro.

Pediatric use information is approved for Advanced Accelerator Applications USA INC’s LUTATHERA (lutetium Lu 177 dotatate) injection for intravenous use. However, due to Advanced Accelerator Applications USA Inc.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.

13.1 Carcinogenesis, Mutagenesis, Impairment Of Fertility

Carcinogenicity and mutagenicity studies have not been conducted with lutetium Lu 177 dotatate; however, radiation is a carcinogen and a mutagen.

No animal studies were conducted to determine the effects of lutetium Lu 177 dotatate on fertility.

13.2 Animal Toxicology And/Or Pharmacology

The primary target organ in animal studies using the non-radioactive lutetium Lu 175 dotatate was the pancreas, a high SSTR2 expressing organ. Pancreatic acinar apoptosis occurred at lutetium Lu 175 dotatate doses ≥ 5 mg/kg in repeat dose toxicology studies in rats. Pancreatic acinar cell atrophy also occurred in repeat dose toxicology studies in dogs at doses ≥ 500 mcg/kg. These findings were consistent with high uptake of the radiolabeled peptide in the pancreas in animal biodistribution studies.

14.1 Progressive, Well-Differentiated Advanced Or Metastatic Somatostatin Receptor-Positive Midgut Carcinoid Tumors

The efficacy of lutetium Lu 177 dotatate injection in patients with progressive, well-differentiated, locally advanced/inoperable or metastatic somatostatin receptor-positive midgut carcinoid tumors was established in NETTER-1 ( NCT01578239), a randomized, multicenter, open-label, active-controlled trial. Key eligibility criteria included Ki67 index ≤ 20%, Karnofsky performance status ≥ 60, confirmed presence of somatostatin receptors on all lesions (OctreoScan uptake ≥ normal liver), creatinine clearance ≥ 50 mL/min, no prior treatment with peptide receptor radionuclide therapy (PRRT), and no prior external beam radiation therapy to more than 25% of the bone marrow.

At the time of the primary analysis, 229 patients were randomized (1:1) to receive either lutetium Lu 177 dotatate injection 7.4 GBq (200 mCi) every 8 weeks (±1 week) for up to 4 administrations (maximum cumulative dose of 29.6 GBq) or high-dose long-acting octreotide (defined as 60 mg by intramuscular injection every 4 weeks). Patients in the lutetium Lu 177 dotatate injection arm also received long-acting octreotide 30 mg as an intramuscular injection 4 to 24 hours after each lutetium Lu 177 dotatate injection dose and every 4 weeks after completion of lutetium Lu 177 dotatate injection treatment until disease progression or until week 76 of the study. Patients in both arms could receive short-acting octreotide for symptom management; however, short-acting octreotide was withheld at least 24 hours before each lutetium Lu 177 dotatate injection dose. Randomization was stratified by OctreoScan tumor uptake score (Grade 2, 3, or 4) and the length of time that patients had been on the most recent constant dose of octreotide prior to randomization (≤ 6 or > 6 months). The major efficacy outcome measure was progression-free survival (PFS) as determined by a blinded independent review committee (IRC) per RECIST v1.1. Additional efficacy outcome measures were overall response rate (ORR) by IRC, duration of response (DoR) by IRC, and overall survival (OS).

Demographic and baseline disease characteristics were balanced between the treatment arms. Of the 229 patients, 82% were White, 4% were Black, 3% were Hispanic or Latino, 0.4% were Asian, 0.4% were Other, and 9% were not reported. The median age was 64 years (28 to 87 years); 51% were male, 74% had an ileal primary, and 96% had metastatic disease in the liver. The median Karnofsky performance score was 90 (60 to 100), 74% received a constant dose of octreotide for > 6 months and 12% received prior treatment with everolimus. Sixty-nine percent of patients had Ki67 expression in ≤ 2% of tumor cells, 77% had CgA > 2 times the upper limit of normal (ULN), 65% had 5-HIAA > 2 times ULN, and 65% had alkaline phosphatase ≤ ULN.

At the time of the final OS analysis, which occurred 66 months after the primary PFS analysis, 117 patients were randomized to the lutetium Lu 177 dotatate injection arm and 114 patients were randomized to the octreotide arm. In the final OS analysis, there was no statistically significant difference in OS between the two treatment arms.

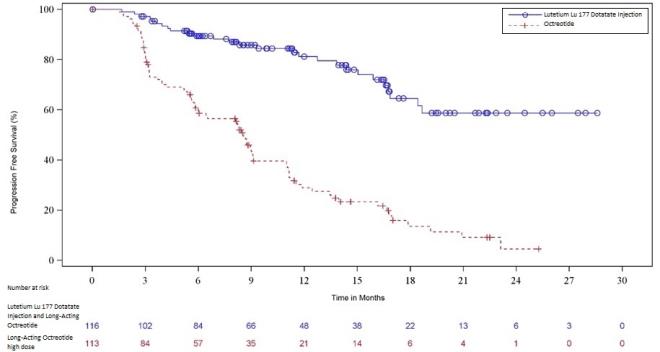
Efficacy results for NETTER-1 are presented in Table 8 and Figure 1.

Table 8. Efficacy Results in NETTER-1
Lutetium Lu 177 Dotatate Injectionwith Long-acting Octreotide
(30 mg)
N = 116
Long-acting Octreotide
(60 mg)
N = 113
PFS by IRC
Events (%)27 (23%)78 (69%)
Progressive disease, n (%)15 (13%)61 (54%)
Death, n (%)12 (10%)17 (15%)
Median in months (95% CI)NR (18.4, NE)8.5 (6.0, 9.1)
Hazard ratio a (95% CI) 0.21 (0.13, 0.32)
p-value b< 0.0001
ORR by IRC
ORR, % (95% CI)13% (7%, 19%)4% (0.1%, 7%)
Complete response rate, n (%)1 (1%)0
Partial response rate, n (%)14 (12%)4 (4%)
p-value c0.0148
Duration of response, median in months (95% CI)NR (2.8, NE)1.9 (1.9, NE)

Abbreviations: CI, confidence interval; IRC, independent radiology committee; NE, not evaluable; NR, not reached; ORR, overall response rate; PFS, progression-free survival.

aHazard ratio based on the unstratified Cox model.

bUnstratified log rank test.

cFisher’s exact test.

Figure 1. Kaplan-Meier Curves for Progression-Free Survival in NETTER-1

Image Description (Lutetium Lu 177 Dotatate Injection 021)

Image Description (Lutetium Lu 177 Dotatate Injection 021)

14.2 Somatostatin Receptor-Positive Gastroenteropancreatic Neuroendocrine Tumors

The efficacy of lutetium Lu 177 dotatate injection in patients with foregut, midgut, and hindgut gastroenteropancreatic neuroendocrine tumors (GEP-NETs) was assessed in 360 patients in the ERASMUS study. In ERASMUS, lutetium Lu 177 dotatate was initially provided as expanded access under a general peptide receptor radionuclide therapy protocol at a single site in the Netherlands. A subsequent lutetium Lu 177 dotatate-specific protocol written eight years after study initiation did not describe a specific sample size or hypothesis testing plan but allowed for retrospective data collection. A total of 1214 patients received lutetium Lu 177 dotatate injection in ERASMUS, of whom 578 patients had baseline tumor assessments. Of the 578 patients, 360 (62%) had GEP-NETs and long-term follow-up. Of these 360 patients, 145 (40%) had their tumors prospectively evaluated according to RECIST criteria. Lutetium Lu 177 dotatate injection 7.4 GBq (200 mCi) was administered every 6 to 13 weeks for up to 4 doses concurrently with the recommended amino acid solution. The major efficacy outcome was investigator-assessed ORR. The median age in the efficacy subset was 60 years (30 to 85 years), 51% were male, 71% had a baseline Karnofsky performance status ≥ 90, 51% had progressed within 12 months of treatment, and 7% had received prior chemotherapy. Fifty-two percent (52%) of patients received a concomitant somatostatin analog. The median dose of lutetium Lu 177 dotatate injection was 29.6 GBq (800 mCi). The investigator-assessed ORR was 17% (95% CI: 13, 21) based on an analysis that required responders to have had prospective response assessments according to RECIST criteria. Three complete responses were observed (< 1%). Median DoR in the 60 responding patients was 35 months (95% CI: 17, 38).

16 How Supplied/Storage And Handling

How Supplied

BEXLUTRY containing 370 MBq/mL (10 mCi/mL) of lutetium Lu-177 dotatate, at time of calibration, is a sterile, preservative-free and clear, colorless to yellow solution for intravenous use supplied in a clear, colorless Type I glass 30 mL single-dose vial containing 7.4 GBq (200 mCi) of lutetium Lu 177 dotatate at the time of patient administration (NDC# 69945-177-01). The solution volume in the vial ranges between 23 to 25 mL to provide a total of 7.4 GBq (200 mCi) of radioactivity.

The product vial is enclosed within a lead shielded container placed in a plastic sealed container. The product is shipped in a Type A package.

Storage and Handling

Store upright at controlled room temperature 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Store in the original package to protect from ionizing radiation (lead shielding).

Calibration is 21 hours from end of product formulation. Reference administration time is 48 hours after calibration. Expiration is 3 hours after reference administration time. Discard appropriately at 72 hours.

17 Patient Counseling Information

Risk From Radiation Exposure

Advise patients and/or caregivers to minimize radiation exposure to household contacts during and after treatment with BEXLUTRY consistent with institutional good radiation safety practices and patient management procedures  [see Dosage and Administration(2.1), Warnings and Precautions(5.1)].

Myelosuppression

Advise patients and/or caregivers to contact their healthcare provider for any signs or symptoms of myelosuppression or infection  [see Warnings and Precautions(5.2)].

Secondary Myelodysplastic Syndrome and Leukemia

Advise patients and/or caregivers of the potential for secondary cancers, including myelodysplastic syndrome and acute leukemia  [see Warnings and Precautions(5.3)].

Renal Toxicity

Advise patients and/or caregivers to hydrate and to urinate frequently before, on the day of, and the day after administration of BEXLUTRY  [see Warnings and Precautions(5.4)]. Advise patients to contact their healthcare provider for any signs or symptoms of renal toxicity  [see Warnings and Precautions(5.4)].

Hepatotoxicity

Advise patients and/or caregivers of the need for periodic laboratory tests to monitor for hepatotoxicity  [see Warnings and Precautions(5.5)]. Advise patients to contact their healthcare provider for any signs or symptoms of hepatotoxicity  [see Warnings and Precautions(5.5)].

Hypersensitivity

Advise patients and/or caregivers that BEXLUTRY may cause hypersensitivity reactions, including angioedema, and to seek immediate medical attention for signs or symptoms of hypersensitivity  [see Warnings and Precautions(5.6)].

Neuroendocrine Hormonal Crises

Advise patients and/or caregivers to contact their healthcare provider for signs or symptoms that may occur following tumor-related hormonal release  [see Warnings and Precautions(5.7)].

Embryo-Fetal Toxicity

Advise pregnant women and males and females of reproductive potential of the potential risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy  [see Warnings and Precautions (5.8), Use in Specific Populations(8.1, 8.3)].

Advise females of reproductive potential to use effective contraception during treatment with BEXLUTRY and for 7 months after the last dose  [see Use in Specific Populations(8.1,8.3)].

Advise male patients with female partners of reproductive potential to use effective contraception during treatment with BEXLUTRY and for 4 months after the last dose  [see Use in Specific Populations(8.1,8.3)].

Lactation

Advise females not to breastfeed during treatment with BEXLUTRY and for 2.5 months after the last dose  [see Use in Specific Populations(8.2)].

Infertility

Advise female and male patients that BEXLUTRY may impair fertility  [see Warnings and Precautions(5.9), Use in Specific Populations(8.3)].

Manufactured by:
Curium US LLC
Noblesville IN 46060

©2026 Curium US LLC
Curium TMand the Curium logo are trademarks of a Curium company.

LUTATHERA ®is a registered trademark of Advanced Accelerator Applications International SA.

A177I6

R09/2026

Principal Display Panel

BEXLUTRY TM

(lutetium Lu 177 dotatate injection),

for intravenous infusion

370 MBq/mL (10 mCi/mL) at calibration time

                             1700 ET

Activity at infusion time:         MBq       (       mCi)

                                     ET

Lot:                              Volume:          mL

EXP:                              ET

A177V0       R08/2026

NDC 69945-177-01

Rx only Single-dose vial.

Discard unused portion.

Recommended Dosage: See prescribing information.

Store at controlled room temperature 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].

CURIUM ™

Manufactured by:

Curium US LLC

Noblesville, IN

46060 USA

CAUTION RADIOACTIVE MATERIAL

* Please review the disclaimer below.