Mometasone Furoate Monohydrate Spray, Metered
FDA Label NDC 70436-154

21 label sections · Submitted to the FDA by Slate Run Pharmaceuticals, Llc. · Indications, Dosage, Usage, and Precautions

Structured Product Label

The following Structured Product Label (SPL) was submitted to the FDA by Slate Run Pharmaceuticals, Llc. for the product Mometasone Furoate Monohydrate (NDC 70436-154). This document serves as the official prescribing information, containing essential scientific data and clinical materials required for healthcare providers and patients.

This specific version of the label includes detailed information regarding 1 indications and usage, 2 dosage and administration, 3 dosage forms and strengths, 4 contraindications, 5 warnings and precautions, 6 adverse reactions, 6.1 clinical trials experience, 6.2 post-marketing experience, and other regulatory disclosures. Use the navigation below to review specific sections of the FDA submission.

1 Indications And Usage

1.1 Prophylaxis of Seasonal Allergic Rhinitis

Mometasone furoate monohydrate nasal spray is indicated for the prophylaxis of the nasal symptoms of seasonal allergic rhinitis in adult and pediatric patients 12 years and older.

1.2 Treatment of Chronic Rhinosinusitis with Nasal Polyps

Mometasone furoate monohydrate nasal spray is indicated for the treatment of chronic rhinosinusitis with nasal polyps in adult patients 18 years of age and older.

2 Dosage And Administration

2.1 Preparation and Administration

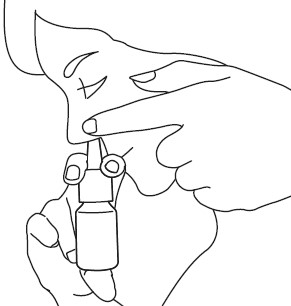
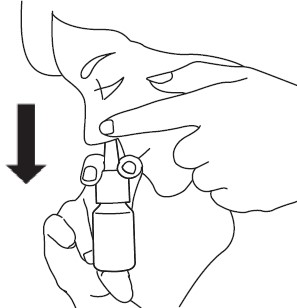
Administer mometasone furoate monohydrate nasal spray by the nasal route only.

Initial Priming

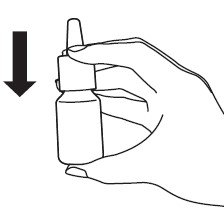
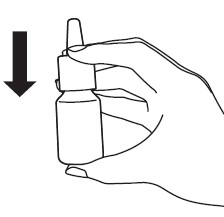
Prior to initial use of mometasone furoate monohydrate nasal spray, the pump must be primed by actuating ten times or until a fine spray appears. The pump may be stored unused for up to 1 week without repriming.

Repriming (as needed)

If unused for more than 1 week, reprime by actuating two times, or until a fine spray appears.

2.2 Recommended Dosage for Prophylaxis of Seasonal Allergic Rhinitis

The recommended dosage for prophylaxis treatment of nasal symptoms of seasonal allergic rhinitis in adult and pediatric patients 12 years and older is mometasone furoate monohydrate nasal spray 2 sprays (2 sprays deliver a total of 100 mcg of mometasone furoate) in each nostril once daily (total daily dose of 200 mcg).

In patients with a known seasonal allergen that precipitates nasal symptoms of seasonal allergic rhinitis, prophylaxis with 2 sprays (2 sprays deliver a total of 100 mcg of mometasone furoate) in each nostril once daily (total daily dose of 200 mcg) is recommended 2 to 4 weeks prior to the anticipated start of the pollen season.

2.3 Recommended Dosage for Treatment of Chronic Rhinosinusitis with Nasal Polyps

The recommended dosage for the treatment of chronic rhinosinusitis with nasal polyps in adults 18 years and older is mometasone furoate monohydrate nasal spray 2 sprays (2 sprays deliver a total of 100 mcg of mometasone furoate) in each nostril twice daily (total daily dose of 400 mcg). A dose of 2 sprays (2 sprays deliver a total of 100 mcg of mometasone furoate) in each nostril once daily (total daily dose of 200 mcg) is also effective in some patients.

3 Dosage Forms And Strengths

Nasal spray: 50 mcg of mometasone furoate in each spray.

4 Contraindications

Mometasone furoate monohydrate nasal spray is contraindicated in patients with known hypersensitivity to mometasone furoate or any of its ingredients [see Warnings and Precautions (5.3), Description (11)].

5 Warnings And Precautions

5.1 Local Nasal Adverse Reactions

Epistaxis

Epistaxis was observed more frequently in patients with allergic rhinitis and patients with chronic rhinosinusitis with nasal polyps who received mometasone furoate monohydrate nasal spray than those who received placebo [see Adverse Reactions (6.1)].

Candida Infection

Localized infections of the nose and pharynx with Candida albicans has occurred from nasal administration of mometasone furoate. When such an infection develops, use of mometasone furoate monohydrate nasal spray should be discontinued and appropriate local or systemic therapy instituted, if needed.

Nasal Septum Perforation

Instances of nasal septum perforation occurred in patients following the nasal application of corticosteroids, including mometasone furoate monohydrate nasal spray. As with any long-term topical treatment of the nasal cavity, patients using mometasone furoate monohydrate nasal spray over several months or longer should be examined periodically for possible changes in the nasal mucosa.

Impaired Wound Healing

Because of the inhibitory effect of corticosteroids on wound healing, patients who have experienced recent nasal septum ulcers, nasal surgery, or nasal trauma should not use a nasal corticosteroid until healing has occurred.

5.2 Glaucoma and Cataracts

Glaucoma and cataracts may be reported with systemic and topical (including nasal, inhaled and ophthalmic) corticosteroid use. Consider referral to an ophthalmologist in patients who develop ocular symptoms or use mometasone furoate monohydrate nasal spray long term [see Adverse Reactions (6) ] .

5.3 Hypersensitivity Reactions

Hypersensitivity reactions including instances of wheezing may occur after the nasal administration of mometasone furoate monohydrate. Discontinue mometasone furoate monohydrate nasal spray if such reactions occur [see Contraindications (4)].

5.4 Immunosuppression and Risk of Infections

Persons who are on drugs which suppress the immune system are more susceptible to infections than healthy individuals. Chickenpox and measles, for example, can have a more serious or even fatal course in nonimmune children or adults on corticosteroids. In such children or adults who have not had these diseases, particular care should be taken to avoid exposure. How the dose, route, and duration of corticosteroid administration affect the risk of developing a disseminated infection is not known. The contribution of the underlying disease and/or prior corticosteroid treatment to the risk is also not known. If exposed to chickenpox, prophylaxis with varicella zoster immune globulin (VZIG) may be indicated. If exposed to measles, prophylaxis with pooled intramuscular immunoglobulin (IG) may be indicated. (See the respective Prescribing Information for VZIG and IG.) If chickenpox develops, treatment with antiviral agents may be considered.

Corticosteroids should be used with caution, if at all, in patients with active or quiescent tuberculous infection of the respiratory tract, or in untreated fungal, bacterial, systemic viral infections, or ocular herpes simplex because of the potential for worsening of these infections.

5.5 Hypercorticism and Adrenal Suppression

Hypercorticism and adrenal suppression may occur when nasal corticosteroids, including mometasone furoate monohydrate nasal spray, are used at higher-than-recommended dosages [see Dosage and Administration (2)] or in patients at risk for such effects. If such changes occur, the dosage of mometasone furoate monohydrate nasal spray should be discontinued slowly, consistent with accepted procedures for discontinuing oral corticosteroid therapy.

5.6 Effect on Growth

Corticosteroids, including mometasone furoate monohydrate nasal spray, may cause a reduction in growth velocity when administered to pediatric patients. Routinely, monitor the growth of pediatric patients receiving mometasone furoate monohydrate nasal spray. To minimize the systemic effects of nasal corticosteroids, including mometasone furoate monohydrate nasal spray, titrate each patient’s dose to the lowest dosage that effectively controls his/her symptoms [see Use in Specific Populations (8.4)] .

6 Adverse Reactions

The following clinically significant adverse reactions are described elsewhere in labeling:

7 Drug Interactions

No formal drug-drug interaction studies have been conducted with mometasone furoate monohydrate nasal spray.

10 Overdosage

There are no data available on the effects of acute or chronic overdosage with mometasone furoate monohydrate nasal spray. Because of low systemic bioavailability, and an absence of acute drug-related systemic findings in clinical studies, overdose is unlikely to require any therapy other than observation. Chronic overdosage with any corticosteroid may result in signs or symptoms of hypercorticism [see Warnings and Precautions (5.5)] .

11 Description

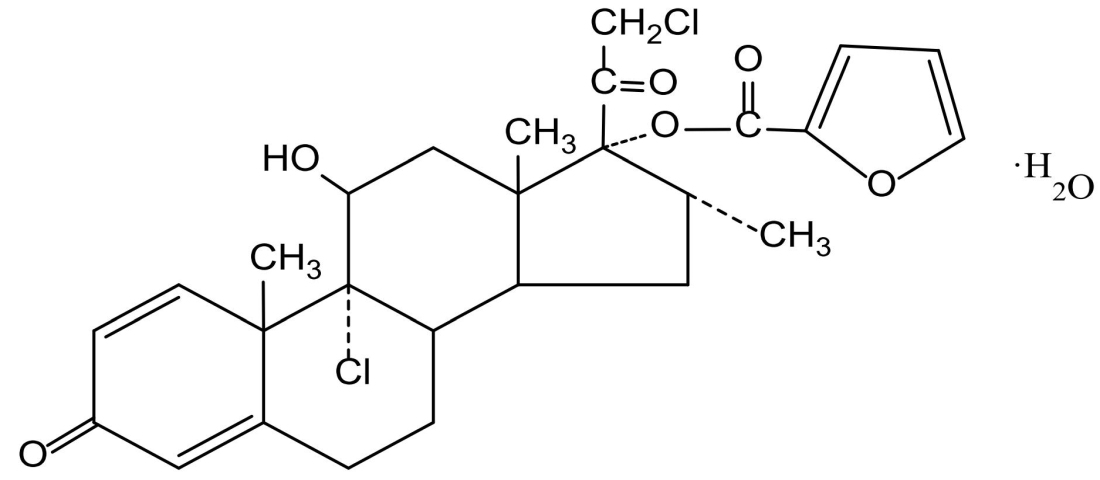
Mometasone furoate monohydrate, the active component of mometasone furoate monohydrate nasal spray, 50 mcg, is an anti-inflammatory corticosteroid having the chemical name, 9,21-Dichloro-11ß,17-dihydroxy-16α-methylpregna-1,4-diene-3,20-dione17-(2 furoate) monohydrate, and the following chemical structure:

Image Of Mometasone Furoate Monohydrate Chemical Structure (Naspress Mometasone Furoate 01)

Image Of Mometasone Furoate Monohydrate Chemical Structure (Naspress Mometasone Furoate 01)

Mometasone furoate monohydrate is a white powder, with an empirical formula of C 27H 30C 12O 6•H 2O, and a molecular weight of 539.45. It is practically insoluble in water; slightly soluble in methanol, ethanol, and isopropanol; soluble in acetone and chloroform; and freely soluble in tetrahydrofuran. Its partition coefficient between octanol and water is greater than 5000.

Mometasone furoate monohydrate nasal spray is a metered-dose, manual pump spray. After initial priming (10 actuations), each actuation of the pump delivers a metered spray containing 100 mg or 100 microliter of aqueous suspension of mometasone furoate monohydrate equivalent to 50 mcg (0.05% w/w) mometasone furoate calculated on the anhydrous basis; in an aqueous medium containing benzalkonium chloride, carboxymethylcellulose sodium, citric acid, glycerin, microcrystalline cellulose, polysorbate 80 and sodium citrate. The pH is between 4.3 and 4.9.

12 Clinical Pharmacology

12.1 Mechanism of Action

Mometasone furoate monohydrate nasal spray is a corticosteroid demonstrating potent anti-inflammatory properties. The precise mechanism of corticosteroid action on allergic rhinitis is not known. Corticosteroids have been shown to have a wide range of effects on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in inflammation.

In two clinical studies utilizing nasal antigen challenge, mometasone furoate monohydrate nasal spray decreased some markers of the early- and late-phase allergic response. These observations included decreases (vs. placebo) in histamine and eosinophil cationic protein levels, and reductions (vs. baseline) in eosinophils, neutrophils, and epithelial cell adhesion proteins. The clinical significance of these findings is not known.

The effect of mometasone furoate monohydrate nasal spray on nasal mucosa following 12 months of treatment was examined in 46 patients with allergic rhinitis. There was no evidence of atrophy and there was a marked reduction in intraepithelial eosinophilia and inflammatory cell infiltration (e.g., eosinophils, lymphocytes, monocytes, neutrophils, and plasma cells).

12.2 Pharmacodynamics

Adrenal Function in Adults: Four clinical pharmacology studies have been conducted in humans to assess the effect of mometasone furoate monohydrate nasal spray at various doses on adrenal function. In one study, daily doses of 200 and 400 mcg of mometasone furoate monohydrate nasal spray and 10 mg of prednisone were compared to placebo in 64 patients (22 to 44 years of age) with allergic rhinitis. Adrenal function before and after 36 consecutive days of treatment was assessed by measuring plasma cortisol levels following a 6-hour Cortrosyn (ACTH) infusion and by measuring 24-hour urinary free cortisol levels. Mometasone furoate monohydrate nasal spray at both the 200- and 400-mcg dose, was not associated with a statistically significant decrease in mean plasma cortisol levels post-Cortrosyn infusion or a statistically significant decrease in the 24-hour urinary free cortisol levels compared to placebo. A statistically significant decrease in the mean plasma cortisol levels post-Cortrosyn infusion and 24-hour urinary free cortisol levels was detected in the prednisone treatment group compared to placebo.

A second study assessed adrenal response to mometasone furoate monohydrate nasal spray (400 and 1600 mcg/day), prednisone (10 mg/day), and placebo, administered for 29 days in 48 male volunteers (21 to 40 years of age). The 24-hour plasma cortisol area under the curve (AUC 0-24), during and after an 8-hour Cortrosyn infusion and 24-hour urinary free cortisol levels were determined at baseline and after 29 days of treatment. No statistically significant differences in adrenal function were observed with mometasone furoate monohydrate nasal spray compared to placebo.

A third study evaluated single, rising doses of mometasone furoate monohydrate nasal spray (1000, 2000, and 4000 mcg/day), orally administered mometasone furoate (2000, 4000, and 8000 mcg/day), orally administered dexamethasone (200, 400, and 800 mcg/day), and placebo (administered at the end of each series of doses) in 24 male volunteers (22 to 39 years of age). Dose administrations were separated by at least 72 hours. Determination of serial plasma cortisol levels at 8 AM and for the 24-hour period following each treatment were used to calculate the plasma cortisol area under the curve (AUC 0-24). In addition, 24-hour urinary free cortisol levels were collected prior to initial treatment administration and during the period immediately following each dose. No statistically significant decreases in the plasma cortisol AUC, 8 AM cortisol levels, or 24-hour urinary free cortisol levels were observed in volunteers treated with either mometasone furoate monohydrate nasal spray or oral mometasone, as compared with placebo treatment. Conversely, nearly all volunteers treated with the three doses of dexamethasone demonstrated abnormal 8 AM cortisol levels (defined as a cortisol level <10 mcg/dL), reduced 24-hour plasma AUC values, and decreased 24-hour urinary free cortisol levels, as compared to placebo treatment.

In a fourth study, adrenal function was assessed in 213 patients (18 to 81 years of age) with chronic rhinosinusitis with nasal polyps before and after 4 months of treatment with either mometasone furoate monohydrate nasal spray (200 mcg once or twice daily) or placebo by measuring 24-hour urinary free cortisol levels. Mometasone furoate monohydrate nasal spray at both doses (200 and 400 mcg/day), was not associated with statistically significant decreases in the 24-hour urinary free cortisol levels compared to placebo.

Three clinical pharmacology studies have been conducted in pediatric patients to assess the effect of mometasone furoate nasal spray on the adrenal function at daily doses of 50, 100, and 200 mcg vs. placebo. In one study, adrenal function before and after 7 consecutive days of treatment was assessed in 48 pediatric patients with allergic rhinitis (ages 6 to 11 years) by measuring morning plasma cortisol and 24-hour urinary free cortisol levels. Mometasone furoate nasal spray, at all three doses, was not associated with a statistically significant decrease in mean plasma cortisol levels or a statistically significant decrease in the 24-hour urinary free cortisol levels compared to placebo. In the second study, adrenal function before and after 14 consecutive days of treatment was assessed in 48 pediatric patients (ages 3 to 5 years) with allergic rhinitis by measuring plasma cortisol levels following a 30-minute Cortrosyn infusion. Mometasone furoate nasal spray, 50 mcg, at all three doses (50, 100, and 200 mcg/day), was not associated with a statistically significant decrease in mean plasma cortisol levels post-Cortrosyn infusion compared to placebo. All patients had a normal response to Cortrosyn. In the third study, adrenal function before and after up to 42 consecutive days of once-daily treatment was assessed in 52 patients with allergic rhinitis (ages 2 to 5 years), 28 of whom received mometasone furoate nasal spray, 50 mcg per nostril (total daily dose 100 mcg), by measuring morning plasma cortisol and 24-hour urinary free cortisol levels. Mometasone furoate nasal spray was not associated with a statistically significant decrease in mean plasma cortisol levels or a statistically significant decrease in the 24-hour urinary free cortisol levels compared to placebo.

12.3 Pharmacokinetics

Absorption:

Mometasone furoate monohydrate administered as a nasal spray suspension has very low bioavailability (<1%) in plasma using a sensitive assay with a lower quantitation limit (LOQ) of 0.25 pcg/mL.

Distribution:

The in vitro protein binding for mometasone furoate was reported to be 98% to 99% in concentration range of 5 to 500 ng/mL.

Elimination:

Following intravenous administration, the effective plasma elimination half-life of mometasone furoate is 5.8 hours. Any absorbed drug is excreted as metabolites mostly via the bile, and to a limited extent, into the urine.

Metabolism:

Studies have shown that any portion of a mometasone furoate dose which is swallowed and absorbed undergoes extensive metabolism to multiple metabolites. There are no major metabolites detectable in plasma. Upon in vitro incubation, one of the minor metabolites formed is 6β-hydroxy-mometasone furoate. In human liver microsomes, the formation of the metabolite is regulated by cytochrome P-450 3A4 (CYP3A4).

Specific Populations:

Patients withHepatic Impairment: Administration of a single inhaled dose of 400 mcg mometasone furoate to subjects with mild (n=4), moderate (n=4), and severe (n=4) hepatic impairment resulted in only 1 or 2 subjects in each group having detectable peak plasma concentrations of mometasone furoate (ranging from 50 to 105 pcg/mL). The observed peak plasma concentrations appear to increase with severity of hepatic impairment, however, the numbers of detectable levels were few.

Patients with Renal Impairment: The effects of renal impairment on mometasone furoate pharmacokinetics have not been adequately investigated.

Pediatric Patients: Mometasone furoate pharmacokinetics have not been investigated in the pediatric population [see Use in Specific Populations (8.4)] .

Male and Female Patients: The effects of gender on mometasone furoate pharmacokinetics have not been adequately investigated.

Racial or Ethnic Groups: The effects of race on mometasone furoate pharmacokinetics have not been adequately investigated.

Drug Interaction Studies:

Inhibitors of Cytochrome P450 3A4: In a drug interaction study, an inhaled dose of mometasone furoate 400 mcg was given to 24 healthy subjects twice daily for 9 days and ketoconazole 200 mg (as well as placebo) were given twice daily concomitantly on Days 4 to 9. Mometasone furoate plasma concentrations were <150 pcg/mL on Day 3 prior to coadministration of ketoconazole or placebo. Following concomitant administration of ketoconazole, 4 out of 12 subjects in the ketoconazole treatment group (n=12) had peak plasma concentrations of mometasone furoate >200 pcg/mL on Day 9 (211-324 pcg/mL).
13 Nonclinical Toxicology

13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility

In a 2-year carcinogenicity study in Sprague Dawley rats, mometasone furoate demonstrated no statistically significant increase in the incidence of tumors at inhalation doses up to 67 mcg/kg (approximately 1 and 2 times the maximum recommended daily nasal dose [MRDID] in adults [400 mcg] and children [100 mcg], respectively, on a mcg/m 2 basis). In a 19-month carcinogenicity study in Swiss CD-1 mice, mometasone furoate demonstrated no statistically significant increase in the incidence of tumors at inhalation doses up to 160 mcg/kg (approximately 2 times the MRDID in adults and children, respectively, on a mcg/m 2 basis).

Mometasone furoate increased chromosomal aberrations in an in vitro Chinese hamster ovary-cell assay, but did not increase chromosomal aberrations in an in vitro Chinese hamster lung cell assay. Mometasone furoate was not mutagenic in the Ames test or mouse-lymphoma assay, and was not clastogenic in an in vivo mouse micronucleus assay and a rat bone marrow chromosomal aberration assay or a mouse male germ-cell chromosomal aberration assay. Mometasone furoate also did not induce unscheduled DNA synthesis in vivo in rat hepatocytes.

In reproductive studies in rats, impairment of fertility was not produced by subcutaneous doses up to 15 mcg/kg (less than the MRDID in adults on a mcg/m 2 basis).

13.2 Animal Toxicology and/or Pharmacology

Reproduction Toxicology Studies

In mice, mometasone furoate caused cleft palate at subcutaneous doses of 60 mcg/kg and above (less than the MRDID in adults on a mcg/m 2 basis). Fetal survival was reduced at 180 mcg/kg (approximately 2 times the MRDID in adults on a mcg/m 2 basis). No toxicity was observed at 20 mcg/kg (less than the MRDID in adults on a mcg/m 2 basis).

In rats, mometasone furoate produced umbilical hernia at topical dermal doses of 600 mcg/kg and above (approximately 10 times the MRDID in adults on a mcg/m 2 basis). A dose of 300 mcg/kg (approximately 6 times the MRDID in adults on a mcg/m 2 basis) produced delays in ossification, but no malformations. In rabbits, mometasone furoate caused multiple malformations (e.g., flexed front paws, gallbladder agenesis, umbilical hernia, hydrocephaly) at topical dermal doses of 150 mcg/kg and above (approximately 6 times the MRDID in adults on a mcg/m 2 basis). In an oral study, mometasone furoate increased resorptions and caused cleft palate and/or head malformations (hydrocephaly or domed head) at 700 mcg/kg (approximately 30 times the MRDID in adults on a mcg/m 2 basis). At 2800 mcg/kg (approximately 110 times the MRDID in adults on a mcg/m 2 basis), most litters were aborted or resorbed. No toxicity was observed at 140 mcg/kg (approximately 6 times the MRDID in adults on a mcg/m 2 basis).

When rats received subcutaneous doses of mometasone furoate throughout pregnancy or during the later stages of pregnancy, 15 mcg/kg (less than the MRDID in adults on a mcg/m 2 basis) caused prolonged and difficult labor and reduced the number of live births, birth weight, and early pup survival. Similar effects were not observed at 7.5 mcg/kg (less than the MRDID in adults on a mcg/m 2 basis).

14 Clinical Studies

14.1 Prophylaxis of Seasonal Allergic Rhinitis in Adult and Pediatric Patients 12 Years of Age and Older

The efficacy and safety of mometasone furoate monohydrate nasal spray in the prophylaxis and treatment of seasonal allergic rhinitis and the treatment of perennial allergic rhinitis have been evaluated in 18 controlled trials, and one uncontrolled clinical trial, in approximately 3000 adults (ages 17 to 85 years) and pediatric patients (ages 12 to 16 years). Of the total number of patients, there were 1757 males and 1453 females, including a total of 283 adolescents (182 boys and 101 girls) with seasonal allergic or perennial allergic rhinitis. Patients were treated with mometasone furoate monohydrate nasal spray at doses ranging from 50 to 800 mcg/day. The majority of patients were treated with 200 mcg/day. The allergic rhinitis trials evaluated the total nasal symptom scores that included stuffiness, rhinorrhea, itching, and sneezing. Patients treated with mometasone furoate monohydrate nasal spray 200 mcg/day had a statistically significant decrease in total nasal symptom scores compared to placebo-treated patients. No additional benefit was observed for mometasone furoate doses greater than 200 mcg/day. A total of 350 patients have been treated with mometasone furoate monohydrate nasal spray for 1 year or longer.

Prophylaxis of seasonal allergic rhinitis for patients 12 years of age and older with mometasone furoate monohydrate nasal spray given at a dose of 200 mcg/day, was evaluated in two clinical studies in 284 patients. These studies were designed such that patients received 4 weeks of prophylaxis with mometasone furoate monohydrate nasal spray prior to the anticipated onset of the pollen season; however, some patients received only 2 to 3 weeks of prophylaxis. Patients receiving 2 to 4 weeks of prophylaxis with mometasone furoate monohydrate nasal spray demonstrated a statistically significantly smaller mean increase in total nasal symptom scores with onset of the pollen season as compared to placebo patients.

14.2 Chronic Rhinosinusitis with Nasal Polyps in Adults 18 Years of Age and Older

Two studies were performed to evaluate the efficacy and safety of mometasone furoate monohydrate nasal spray in the treatment of chronic rhinosinusitis with nasal polyps. These studies involved 664 patients with chronic rhinosinusitis with nasal polyps, 441 of whom received mometasone furoate monohydrate nasal spray. These studies were randomized, double-blind, placebo-controlled, parallel-group, multicenter studies in patients 18 to 86 years of age with bilateral nasal polyps. Patients were randomized to receive mometasone furoate monohydrate nasal spray 200 mcg once daily, 200 mcg twice daily or placebo for a period of 4 months. The co-primary efficacy endpoints were 1) change from baseline in nasal congestion/obstruction averaged over the first month of treatment; and 2) change from baseline to last assessment in bilateral polyp grade during the entire 4 months of treatment as assessed by endoscopy. Efficacy was demonstrated in both studies at a dose of 200 mcg twice daily and in one study at a dose of 200 mcg once a day (see Table 2 below).

Table 2: Effect of Mometasone Furoate Monohydrate Nasal Spray in Two Randomized, Placebo-Controlled Trials in Patients with Chronic Rhinosinusitis with Nasal Polyps
Mometasone furoate monohydrate nasal spray
200 mcg qd
Mometasone furoate monohydrate nasal spray
200 mcg bid
PlaceboP-value for mometasone furoate monohydrate nasal spray
200 mcg qd vs. placebo
P-value for mometasone furoate monohydrate nasal spray
200 mcg bid vs. placebo
Study 1N=115N=122N=117
Baseline bilateral polyp grade *4.214.274.25
Mean change from baseline in bilateral polyps grade-1.15-0.96-0.50<0.0010.01
Baseline nasal congestion †2.292.352.28
Mean change from baseline in nasal congestion-0.47-0.61-0.240.001<0.001
Study 2N=102N=102N=106
Baseline bilateral polyp grade *4.004.104.17
Mean change from baseline in bilateral polyps grade-0.78-0.96-0.620.330.04
Baseline nasal congestion †2.232.202.18
Mean change from baseline in nasal congestion-0.42-0.66-0.230.01<0.001

* polyps in each nasal fossa were graded by the investigator based on endoscopic visualization, using a scale of 0-3 where 0=no polyps; 1=polyps in the middle meatus, not reaching below the inferior border of the middle turbinate; 2=polyps reaching below the inferior border of the middle turbinate but not the inferior border of the inferior turbinate; 3=polyps reaching to or below the border of the inferior turbinate, or polyps medial to the middle turbinate (score reflects sum of left and right nasal fossa grades).

† nasal congestion/obstruction was scored daily by the patient using a 0-3 categorical scale where 0=no symptoms, 1=mild symptoms, 2=moderate symptoms and 3=severe symptoms.

There were no clinically relevant differences in the effectiveness of mometasone furoate monohydrate nasal spray in the studies evaluating treatment of chronic rhinosinusitis with nasal polyps across subgroups of patients defined by gender, age, or race.

16 How Supplied/Storage And Handling

Mometasone Furoate Monohydrate Nasal Spray:

  • 50 mcg mometasone furoate monohydrate per spray
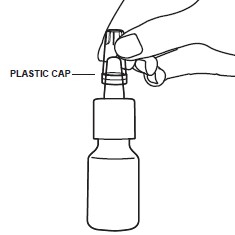
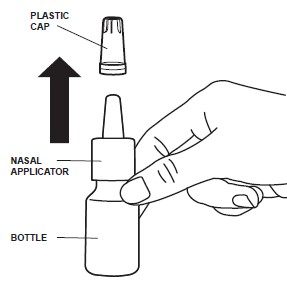
  • is supplied in a white, high-density, polyethylene bottle fitted with a white metered-dose, manual spray pump, and translucent cap
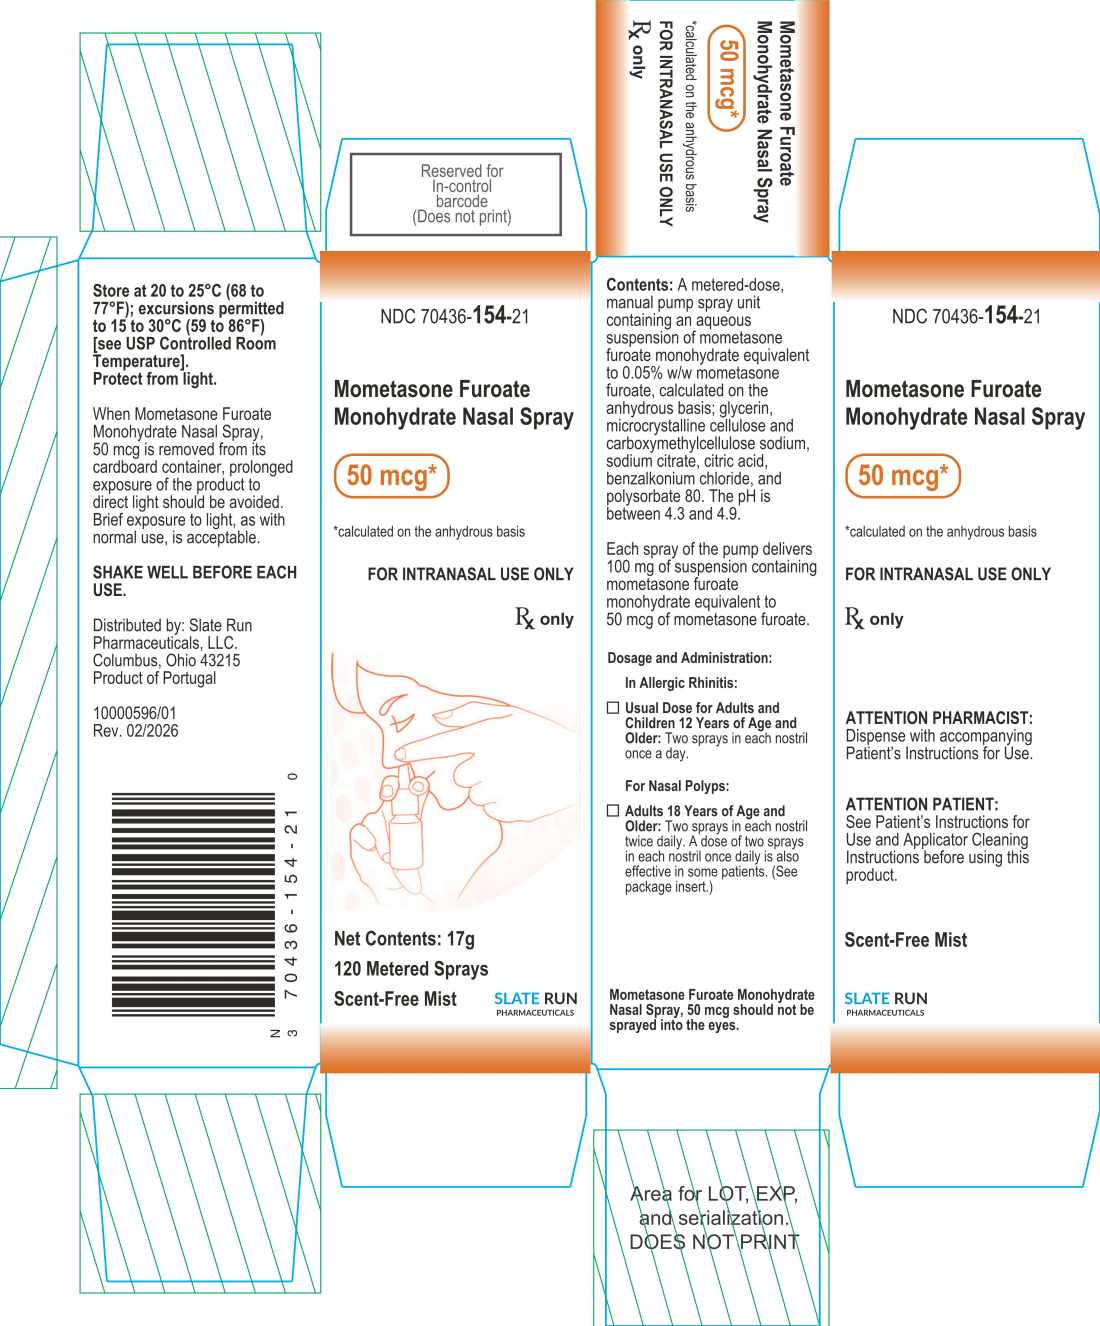
  • contains 17 g of product formulation (NDC 70436-154-21)
  • 120 sprays, each delivering 50 mcg of mometasone furoate per actuation

17 Patient Counseling Information

Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).

Local Nasal Adverse Reactions

Patients should be informed that treatment with mometasone furoate monohydrate nasal spray may be associated with adverse reactions which include epistaxis (nose bleed) and nasal septum perforation. Candida infection may also occur. Because of the inhibitory effect of corticosteroids on wound healing, patients who have experienced recent nasal septum ulcers, nasal surgery, or nasal trauma should not use a nasal corticosteroid until healing has occurred [see Warnings and Precautions (5.1)] . Patients should be cautioned not to spray mometasone furoate monohydrate nasal spray directly onto the nasal septum.

Glaucoma and Cataracts

Advise patients that long-term use of nasal and inhaled corticosteroids may increase the risk of some eye problems (glaucoma or cataracts); regular eye examinations should be considered. Patients should be cautioned not to spray mometasone furoate monohydrate nasal spray into the eyes [see Warnings and Precautions (5.2)] .

Immunosuppression and Risk of Infections

Persons who are on immunosuppressant doses of corticosteroids should be warned to avoid exposure to chickenpox or measles, and patients should also be advised that if they are exposed, medical advice should be sought without delay [see Warnings and Precautions (5.4)] .

Use Regularly for Best Effect

Patients should use mometasone furoate monohydrate nasal spray on a regular basis for optimal effect. Improvement in nasal symptoms of allergic rhinitis has been shown to occur within 1 to 2 days after initiation of dosing. Maximum benefit is usually achieved within 1 to 2 weeks after initiation of dosing. Patients should not increase the prescribed dosage but should contact their physician if symptoms do not improve, or if the condition worsens. Administration to young children should be aided by an adult.

If a patient missed a dose, the patient should be advised to administer the dose as soon as they remember. The patient should not use more than the recommended dose for the day.

* Please review the disclaimer below.