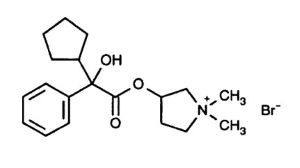
Risk Summary
Limited available data over decades of use with glycopyrrolate in pregnant women have not identified a drug-associated risk of birth defects and miscarriage, however, most of the reported exposures occurred after the first trimester. Most of the available data are based on studies with exposures that occurred at the time of Cesarean section delivery, and these studies have not identified an adverse effect on maternal outcomes or infant Apgar scores (see Data).
In animal reproduction studies in pregnant rats and rabbits administered glycopyrrolate orally (rats) and intramuscularly (rabbits) during the period of organogenesis, no teratogenic effects were seen at 320-times and 5-times the maximum recommended human dose (MRHD) of 2 mg (on a mg/m2 basis), respectively (see Data).
The background risk for major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data
Human Data
Published, randomized, controlled trials over several decades, which compared the use of glycopyrrolate to another antimuscarinic agent in pregnant women during Cesarean section, have not identified adverse maternal or infant outcomes. In normal doses (0.004 mg/kg), glycopyrrolate does not appear to affect fetal heart rate or fetal heart rate variability to a significant degree. Concentrations of glycopyrrolate in umbilical venous and arterial blood and in the amniotic fluid are low after intramuscular administration to parturients. Therefore, glycopyrrolate does not appear to penetrate through the placental barrier in significant amounts.
There are no studies on the safety of glycopyrrolate exposure during the period of organogenesis, and therefore, it is not possible to draw any conclusions on the risk of birth defects following exposure to glycopyrrolate during pregnancy. In addition, there are no data on the risk of miscarriage following fetal exposure to glycopyrrolate.
Animal Data
Reproduction studies with glycopyrrolate were performed in rats at a dietary dose of approximately 65 mg/kg/day (exposure was approximately 320 times the maximum recommended daily human dose of 2 mg on a mg/m2basis) and rabbits at intramuscular doses of up to 0.5 mg/kg/day (exposure was approximately 5 times the maximum recommended daily human dose on a mg/m2 basis). These studies produced no teratogenic effects to the fetus.
A preclinical study on reproductive performance of rats given glycopyrrolate resulted in a decreased rate of conception and survival at weaning.