Absorption
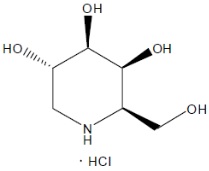
Following a single GALAFOLD oral dose of 123 mg, the absolute bioavailability (AUC) of migalastat was approximately 75% and the time to peak plasma concentration (tmax) was approximately 3 hours. Plasma migalastat exposure (AUC0‑∞ and Cmax) demonstrated dose‑proportional increases at oral doses from 75 mg to 1250 mg (doses from 0.5 to 8.3‑fold of the approved recommended dosage). Migalastat does not accumulate following administration of 123 mg GALAFOLD every other day.
Effect of Food: Administration of GALAFOLD one hour before a high‑fat (850 calories; 56% from fat) or light meal (507 calories; 30% from fat), or one hour after a light meal, reduced the mean migalastat AUC0‑∞ by 37% to 42% and Cmax by 15% to 39% compared to the fasting state [see Dosage and Administration (2.2)].
Distribution
The apparent volume of distribution (Vz/F) of migalastat in Fabry patients was approximately 89 L (range: 77 to 133 L) at steady state. There was no detectable plasma protein binding following administration of [14C]‑migalastat in the concentration range between 1 to 100 microM.
Elimination
Metabolism: Based upon in vivo data, migalastat is a substrate for uridine diphosphate glucuronosyltransferase (UDPGT), a minor elimination pathway.
Excretion: In a mass balance study in healthy male subjects, following oral administration of 123 mg [14C]‑migalastat, approximately 77% of the total radiolabeled dose was recovered in urine and 20% of the total radiolabeled dose was recovered in feces with an overall total recovery of 98% within 96 hours post‑dose. In urine, unchanged migalastat accounted for 80% of the radioactivity, which equates to 62% of the administered dose. In feces, unchanged migalastat was the only drug‑related component. In plasma, unchanged migalastat accounted for approximately 77% of the plasma radioactivity and three dehydrogenated O‑glucuronide conjugated metabolites, M1 to M3, together accounted for approximately 13% of the plasma radioactivity, none of which comprised more than 6% of the radiolabeled dose. Approximately 9% of the total radioactivity in plasma was unassigned.
Following a single oral dose of 123 mg GALAFOLD, migalastat is cleared from plasma with a mean half‑life (t½) of approximately 4 hours and apparent clearance of 12.5 L/hr.
Specific Populations
Male and Female Patients: The pharmacokinetic characteristics of migalastat were not significantly different between healthy male and female subjects or patients with Fabry disease.
Racial or Ethnic Groups: Clinical data indicate no ethnic differences in patient populations studied with migalastat.
Patients with Renal Impairment: In a single‑dose study in subjects with varying degrees of renal impairment, exposure to migalastat (AUC) was increased by 1.2-, 1.8-, and 4.3-fold in subjects with mild (eGFR 60 to 90 mL/min/1.73 m2), moderate (eGFR 30 to 59 mL/min/1.73 m2), and severe renal impairment (eGFR less than 30 mL/min/1.73 m2), respectively, while the Cmax remained unchanged with severity of renal impairment [see Use in Specific Populations (8.6)].
Drug Interaction Studies
In Vitro Studies
Migalastat is not a known inhibitor or inducer of cytochrome P450 (CYP450) enzymes, nor is it an inhibitor of BCRP, MDR1, P‑glycoprotein (P‑gp), or BSEP human efflux transporters, or OATP1B1, OATP1B3, OAT1, OAT3, OCT1, OCT2, MATE1, or MATE2‑K human uptake transporters. Migalastat is not a substrate of P‑gp, BCRP, MDR1 or MATE1, MATE2‑K, OAT1, OAT3, or OCT2. Migalastat showed low affinity for SGLT1, as both a substrate and an inhibitor, and showed no activity for SGLT2.
Clinical Studies: Effects of other Drugs on Migalastat
Co‑administration of 190 mg caffeine reduced the mean migalastat AUC0‑∞ by 55% and Cmax by 60% compared to without caffeine co‑administration. The tmax of migalastat was not affected by co‑administration of caffeine. No clinically significant pharmacokinetic changes were observed for migalastat when co‑administered with sucrose, aspartame or acesulfame potassium [see Dosage and Administration (2.2) and Drug Interactions (7.1)].